
Corporate Update November 12, 2026

2 November 12, 2026 Legal Notices The information in this slide deck is current as of November 12, 2026, unless otherwise noted, and is qualified in its entirety by reference to MacroGenics’ Annual, Quarterly and Current Reports filed with the SEC. MacroGenics undertakes no obligation to update any of the information herein. Cautionary Note on Forward-Looking Statements Any statements in this slide presentation about future expectations, plans and prospects for MacroGenics (“Company”), including statements about the Company’s strategy, future operations, clinical development of and regulatory plans for the Company’s therapeutic candidates, expected timing of the release of clinical updates and safety and efficacy data for the Company’s ongoing clinical trials, anticipated cash runway and other statements containing the words “subject to”, "believe", “anticipate”, “plan”, “expect”, “intend”, “estimate”, “potential”, “project”, “may”, “will”, “should”, “would”, “could”, “can”, the negatives thereof, variations thereon and similar expressions, or by discussions of strategy, including our ability to execute on our key strategic priorities for 2026, constitute forward-looking statements within the meaning of Section 27A of the Securities Act of 1933 and Section 21E of the Securities Exchange Act of 1934. Actual results may differ materially from those indicated by such forward-looking statements as a result of various important factors, including: risks related to the reproducibility of any results initially seen in any product candidate discussed herein; risks that any product candidate’s revenue, expenses and costs may not be as expected; risks relating to any product candidate’s market acceptance, competition, reimbursement and regulatory actions; future data updates for any product candidates, including timing and results of efficacy and safety data with respect to any product candidates in ongoing clinical trials; the uncertainties inherent in the initiation and enrollment of future clinical trials; the availability of financing to fund the internal development of our product candidates; expectations regarding the expansion of ongoing clinical trials; expectations for the timing and steps required in the regulatory review process; expectations for regulatory approvals; expectations of future milestone payments; the impact of competitive products; our ability to enter into agreements with strategic partners and other matters that could affect the availability or commercial potential of the Company's product candidates; business, economic or political disruptions due to catastrophes or other events, including natural disasters, terrorist attacks, civil unrest and actual or threatened armed conflict, or public health crises; costs of litigation and the failure to successfully defend lawsuits and other claims against us; risks related to the transition of the CDMO operations to the purchaser following the sale of our CDMO operations; and other risks described in the Company's filings with the Securities and Exchange Commission. In addition, the forward-looking statements included in this presentation represent the Company's views only as of the date hereof. The Company anticipates that subsequent events and developments will cause the Company's views to change. However, while the Company may elect to update these forward-looking statements at some point in the future, the Company specifically disclaims any obligation to do so, except as may be required by law. These forward-looking statements should not be relied upon as representing the Company's views as of any date subsequent to the date hereof. Trademarks DART, TRIDENT, MacroGenics, and the MacroGenics logo are trademarks or registered trademarks of MacroGenics, Inc. All third-party trademarks used herein are registered trademarks of their respective owners. Investigational Agents The safety and efficacy of investigational agents and/or investigational uses of approved products have not been established.
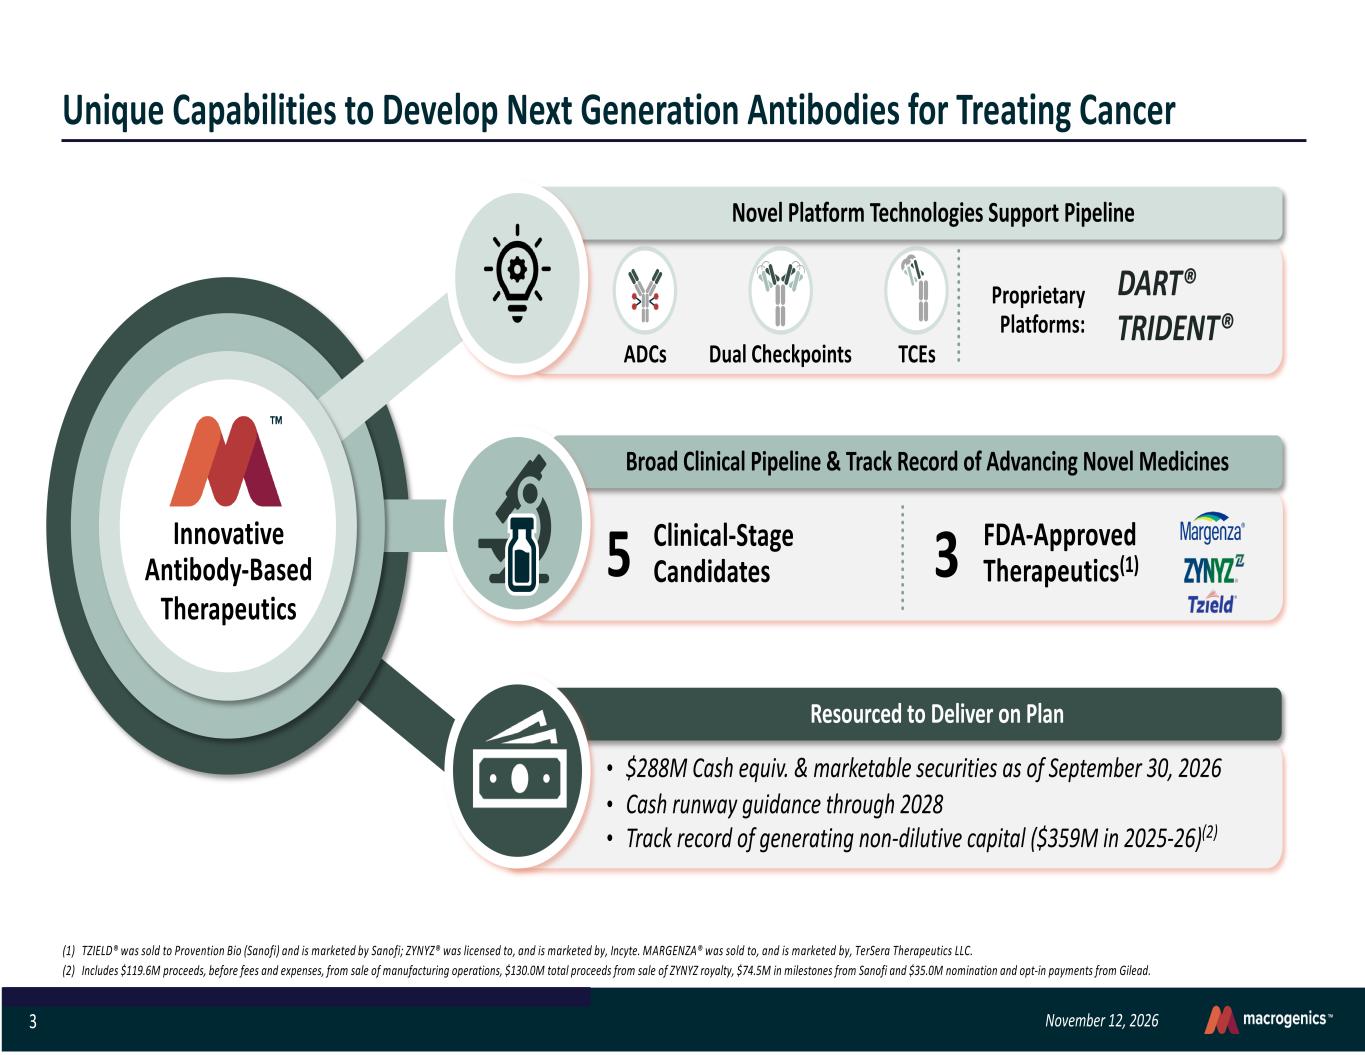
3 November 12, 2026 (1) TZIELD® was sold to Provention Bio (Sanofi) and is marketed by Sanofi; ZYNYZ® was licensed to, and is marketed by, Incyte. MARGENZA® was sold to, and is marketed by, TerSera Therapeutics LLC. (2) Includes $119.6M proceeds, before fees and expenses, from sale of manufacturing operations, $130.0M total proceeds from sale of ZYNYZ royalty, $74.5M in milestones from Sanofi and $35.0M nomination and opt-in payments from Gilead. ` • $288M Cash equiv. & marketable securities as of September 30, 2026 • Cash runway guidance through 2028 • Track record of generating non-dilutive capital ($359M in 2025-26)(2) Resourced to Deliver on Plan ADCs Dual Checkpoints TCEs Broad Clinical Pipeline & Track Record of Advancing Novel Medicines Novel Platform Technologies Support Pipeline Innovative Antibody-Based Therapeutics Proprietary Platforms: DART® TRIDENT® 5 Clinical-Stage Candidates 3 FDA-Approved Therapeutics(1) Unique Capabilities to Develop Next Generation Antibodies for Treating Cancer
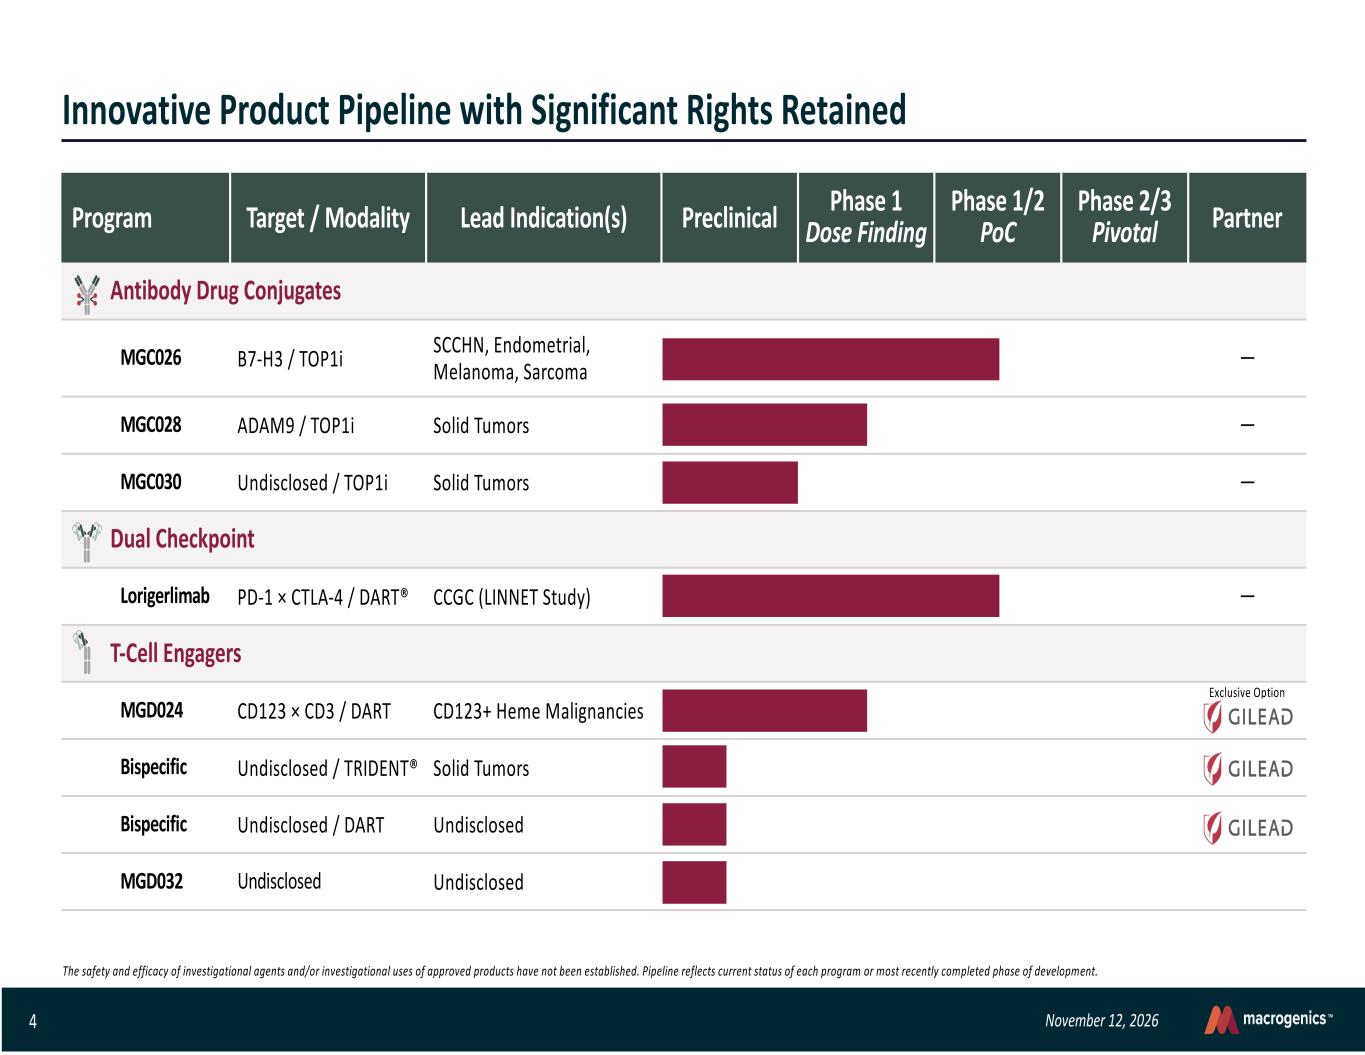
4 November 12, 2026 Program Target / Modality Lead Indication(s) Preclinical Phase 1 Dose Finding Phase 1/2 PoC Phase 2/3 Pivotal Partner Antibody Drug Conjugates MGC026 B7-H3 / TOP1i SCCHN, Endometrial, Melanoma, Sarcoma — MGC028 ADAM9 / TOP1i Solid Tumors — MGC030 Undisclosed / TOP1i Solid Tumors — Dual Checkpoint Lorigerlimab PD-1 × CTLA-4 / DART® CCGC (LINNET Study) — T-Cell Engagers MGD024 CD123 × CD3 / DART CD123+ Heme Malignancies Exclusive Option Bispecific Undisclosed / TRIDENT® Solid Tumors Bispecific Undisclosed / DART Undisclosed MGD032 Undisclosed Undisclosed Innovative Product Pipeline with Significant Rights Retained The safety and efficacy of investigational agents and/or investigational uses of approved products have not been established. Pipeline reflects current status of each program or most recently completed phase of development.
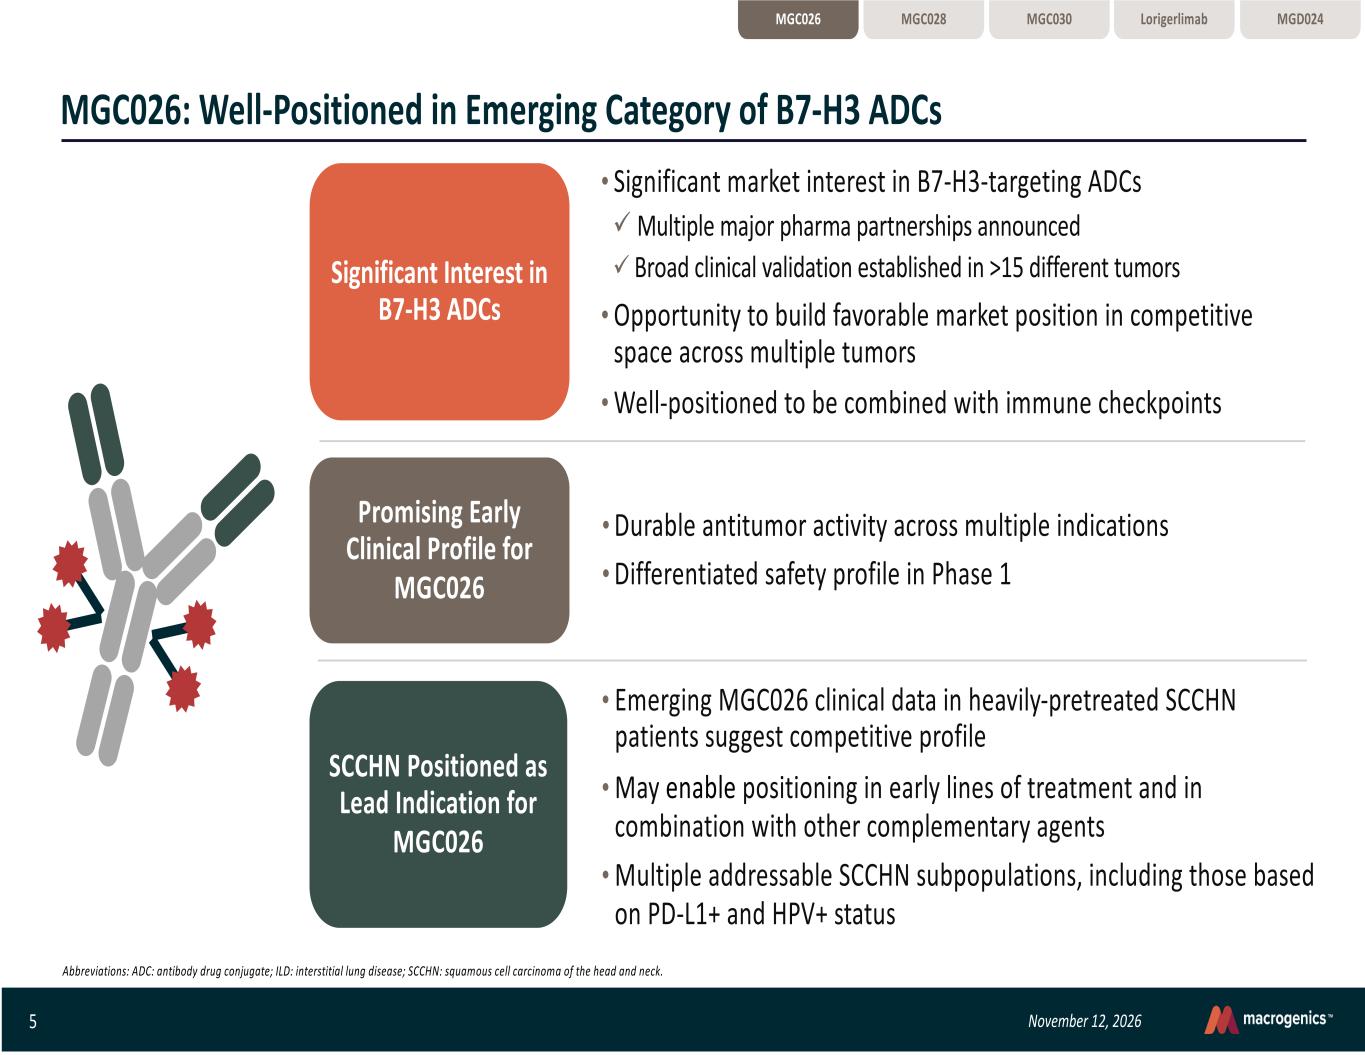
5 November 12, 2026 Significant Interest in B7-H3 ADCs • Significant market interest in B7-H3-targeting ADCs ü Multiple major pharma partnerships announced ü Broad clinical validation established in >15 different tumors •Opportunity to build favorable market position in competitive space across multiple tumors •Well-positioned to be combined with immune checkpoints Promising Early Clinical Profile for MGC026 •Durable antitumor activity across multiple indications •Differentiated safety profile in Phase 1 MGC026: Well-Positioned in Emerging Category of B7-H3 ADCs SCCHN Positioned as Lead Indication for MGC026 • Emerging MGC026 clinical data in heavily-pretreated SCCHN patients suggest competitive profile •May enable positioning in early lines of treatment and in combination with other complementary agents •Multiple addressable SCCHN subpopulations, including those based on PD-L1+ and HPV+ status Abbreviations: ADC: antibody drug conjugate; ILD: interstitial lung disease; SCCHN: squamous cell carcinoma of the head and neck. Lorigerlimab MGD024MGC028 MGC030MGC026
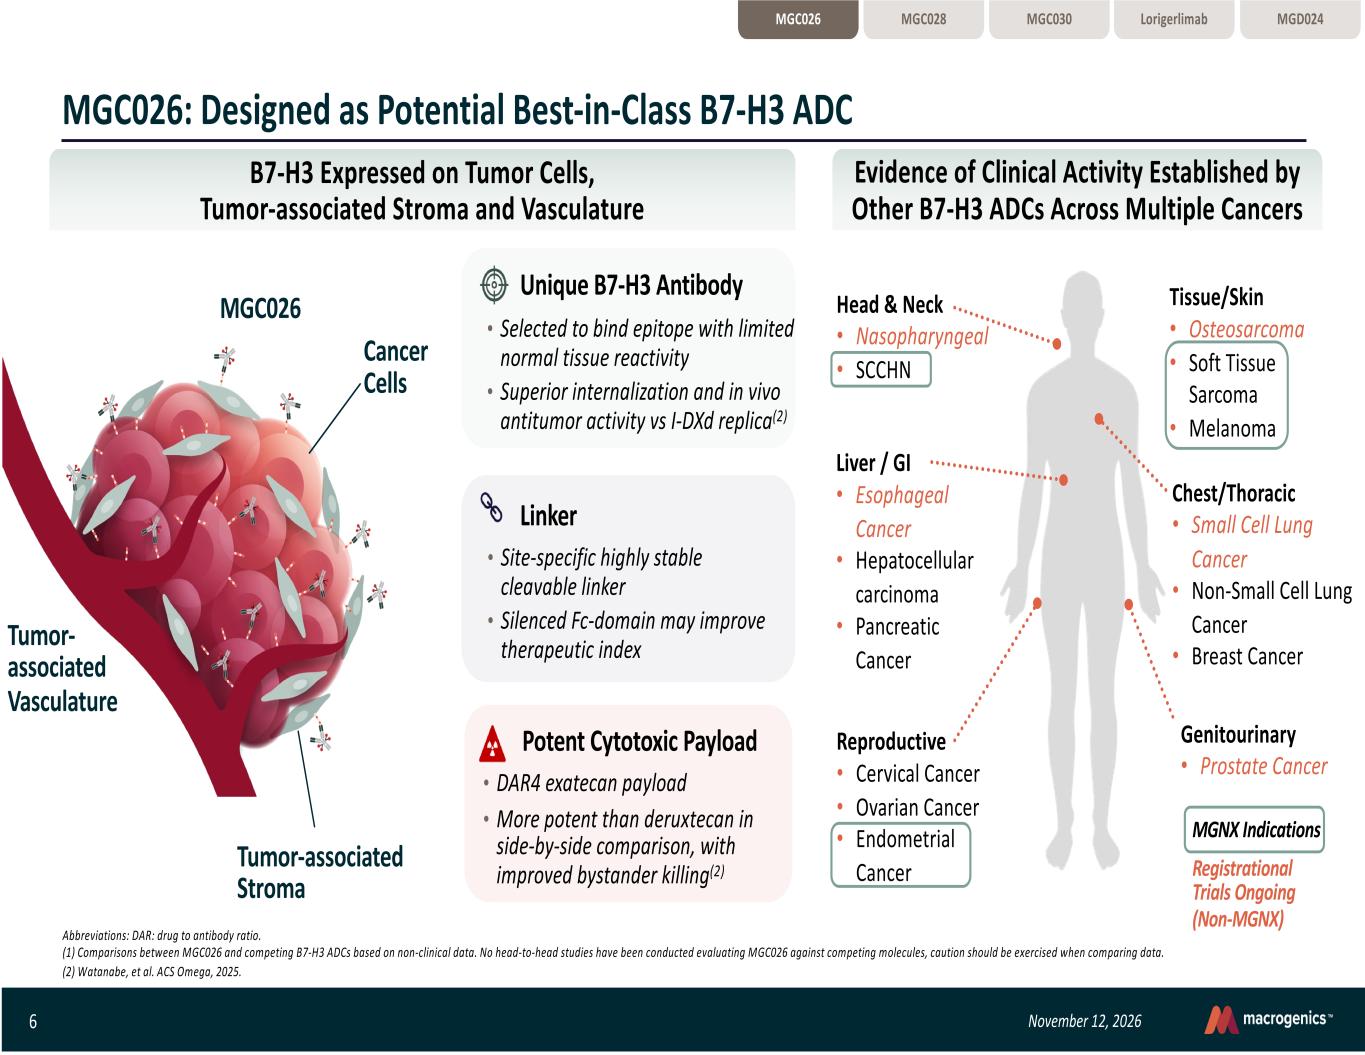
6 November 12, 2026 MGC026: Designed as Potential Best-in-Class B7-H3 ADC Abbreviations: DAR: drug to antibody ratio. (1) Comparisons between MGC026 and competing B7-H3 ADCs based on non-clinical data. No head-to-head studies have been conducted evaluating MGC026 against competing molecules, caution should be exercised when comparing data. (2) Watanabe, et al. ACS Omega, 2025. Unique B7-H3 Antibody • Selected to bind epitope with limited normal tissue reactivity • Superior internalization and in vivo antitumor activity vs I-DXd replica(2) Linker • Site-specific highly stable cleavable linker • Silenced Fc-domain may improve therapeutic index Potent Cytotoxic Payload • DAR4 exatecan payload • More potent than deruxtecan in side-by-side comparison, with improved bystander killing(2) Tumor- associated Vasculature Cancer Cells Tumor-associated Stroma B7-H3 Expressed on Tumor Cells, Tumor-associated Stroma and Vasculature Evidence of Clinical Activity Established by Other B7-H3 ADCs Across Multiple Cancers MGC026 Genitourinary • Prostate Cancer Head & Neck • Nasopharyngeal • SCCHN Tissue/Skin • Osteosarcoma • Soft Tissue Sarcoma • Melanoma Reproductive • Cervical Cancer • Ovarian Cancer • Endometrial Cancer Liver / GI • Esophageal Cancer • Hepatocellular carcinoma • Pancreatic Cancer Registrational Trials Ongoing (Non-MGNX) MGNX Indications Chest/Thoracic • Small Cell Lung Cancer • Non-Small Cell Lung Cancer • Breast Cancer Lorigerlimab MGD024MGC028 MGC030MGC026
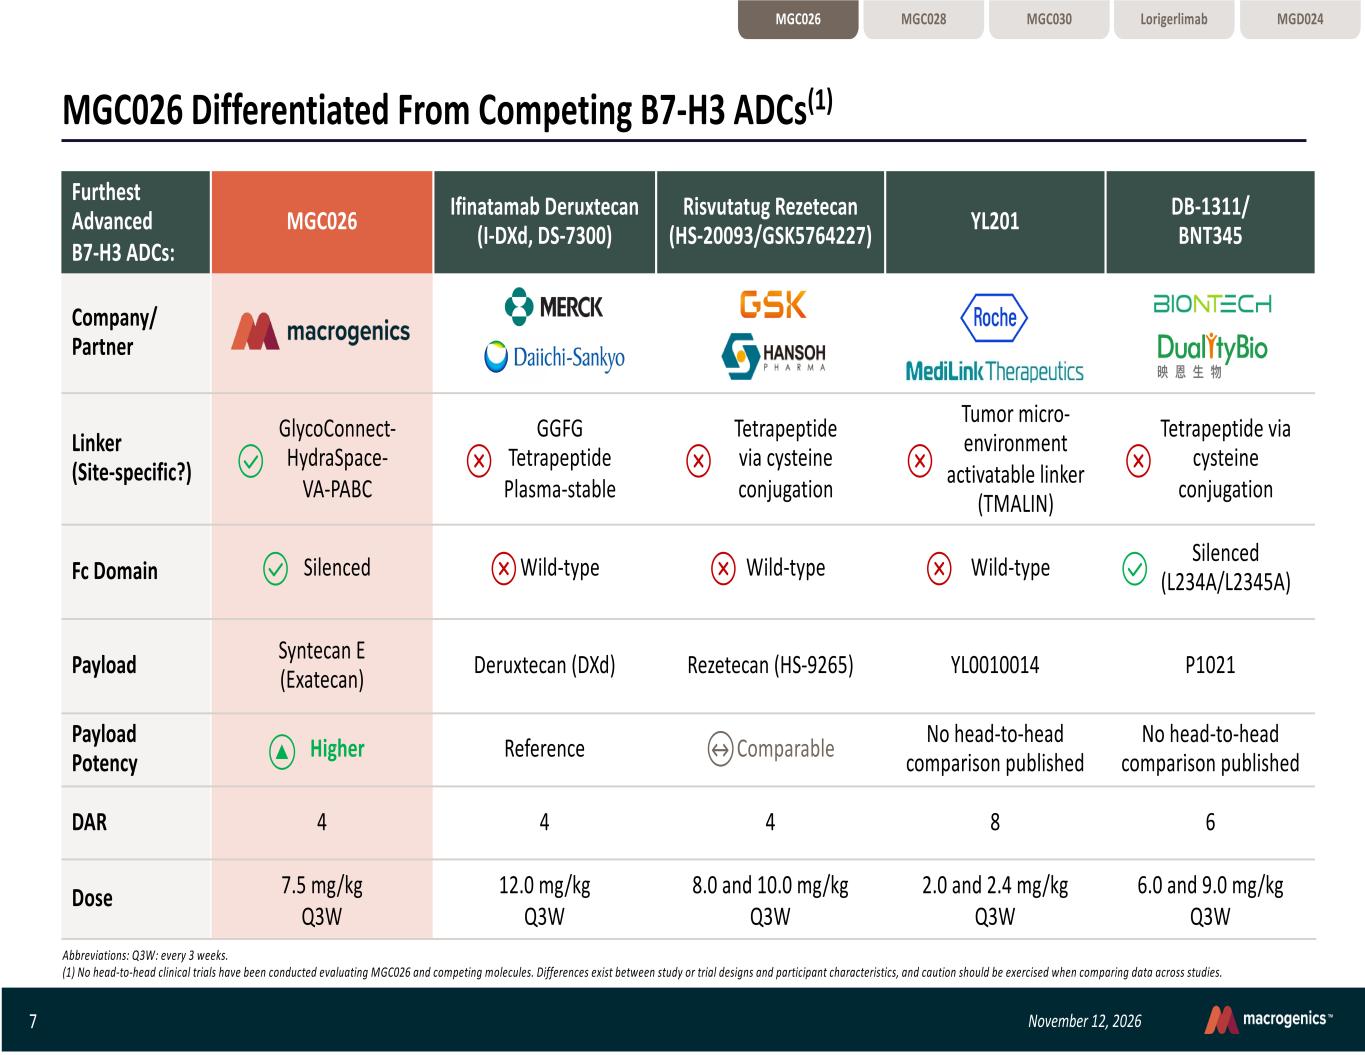
7 November 12, 2026 MGC026 Differentiated From Competing B7-H3 ADCs(1) Furthest Advanced B7-H3 ADCs: MGC026 Ifinatamab Deruxtecan (I-DXd, DS-7300) Risvutatug Rezetecan (HS-20093/GSK5764227) YL201 DB-1311/ BNT345 Company/ Partner Linker (Site-specific?) GlycoConnect- HydraSpace- VA-PABC GGFG Tetrapeptide Plasma-stable Tetrapeptide via cysteine conjugation Tumor micro- environment activatable linker (TMALIN) Tetrapeptide via cysteine conjugation Fc Domain Silenced Wild-type Wild-type Wild-type Silenced (L234A/L2345A) Payload Syntecan E (Exatecan) Deruxtecan (DXd) Rezetecan (HS-9265) YL0010014 P1021 Payload Potency Higher Reference Comparable No head-to-head comparison published No head-to-head comparison published DAR 4 4 4 8 6 Dose 7.5 mg/kg Q3W 12.0 mg/kg Q3W 8.0 and 10.0 mg/kg Q3W 2.0 and 2.4 mg/kg Q3W 6.0 and 9.0 mg/kg Q3W ↔p Abbreviations: Q3W: every 3 weeks. (1) No head-to-head clinical trials have been conducted evaluating MGC026 and competing molecules. Differences exist between study or trial designs and participant characteristics, and caution should be exercised when comparing data across studies. Lorigerlimab MGD024MGC028 MGC030MGC026
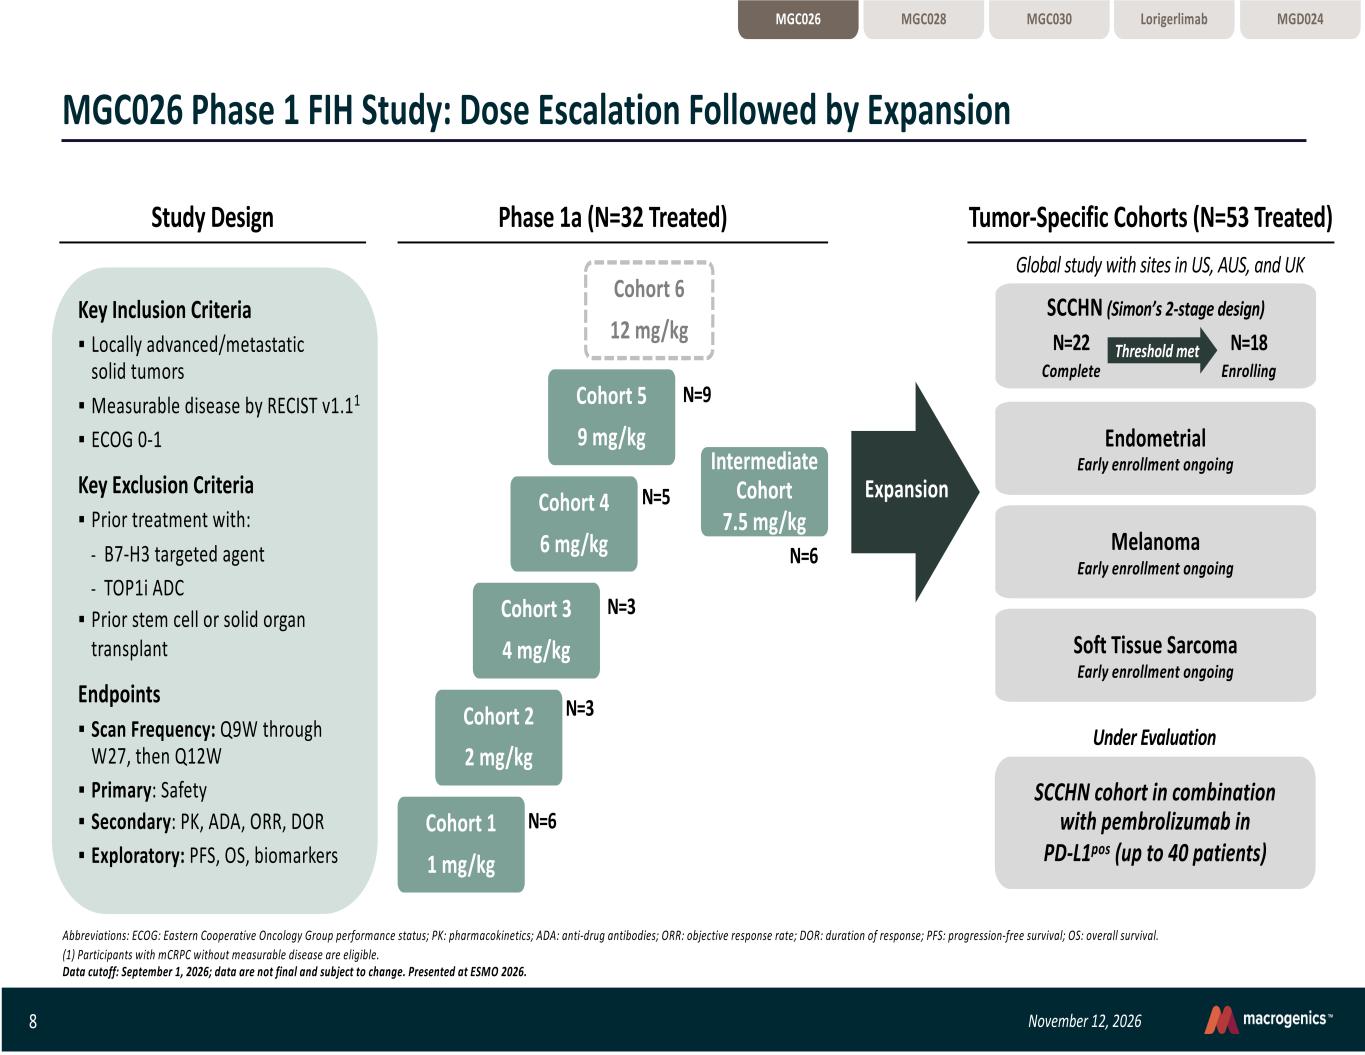
8 November 12, 2026 Key Inclusion Criteria § Locally advanced/metastatic solid tumors § Measurable disease by RECIST v1.11 § ECOG 0-1 Key Exclusion Criteria § Prior treatment with: - B7-H3 targeted agent - TOP1i ADC § Prior stem cell or solid organ transplant Endpoints § Scan Frequency: Q9W through W27, then Q12W § Primary: Safety § Secondary: PK, ADA, ORR, DOR § Exploratory: PFS, OS, biomarkers MGC026 Phase 1 FIH Study: Dose Escalation Followed by Expansion SCCHN (Simon’s 2-stage design) Melanoma Early enrollment ongoing Endometrial Early enrollment ongoing Soft Tissue Sarcoma Early enrollment ongoing Phase 1a (N=32 Treated) Tumor-Specific Cohorts (N=53 Treated) Cohort 1 1 mg/kg Cohort 2 2 mg/kg Cohort 3 4 mg/kg Cohort 4 6 mg/kg Cohort 5 9 mg/kg Cohort 6 12 mg/kg N=6 N=3 N=3 N=5 N=9 Intermediate Cohort 7.5 mg/kg N=6 Abbreviations: ECOG: Eastern Cooperative Oncology Group performance status; PK: pharmacokinetics; ADA: anti-drug antibodies; ORR: objective response rate; DOR: duration of response; PFS: progression-free survival; OS: overall survival. (1) Participants with mCRPC without measurable disease are eligible. Data cutoff: September 1, 2026; data are not final and subject to change. Presented at ESMO 2026. Study Design Expansion N=22 Complete N=18 Enrolling Threshold met Global study with sites in US, AUS, and UK SCCHN cohort in combination with pembrolizumab in PD-L1pos (up to 40 patients) Under Evaluation Lorigerlimab MGD024MGC028 MGC030MGC026
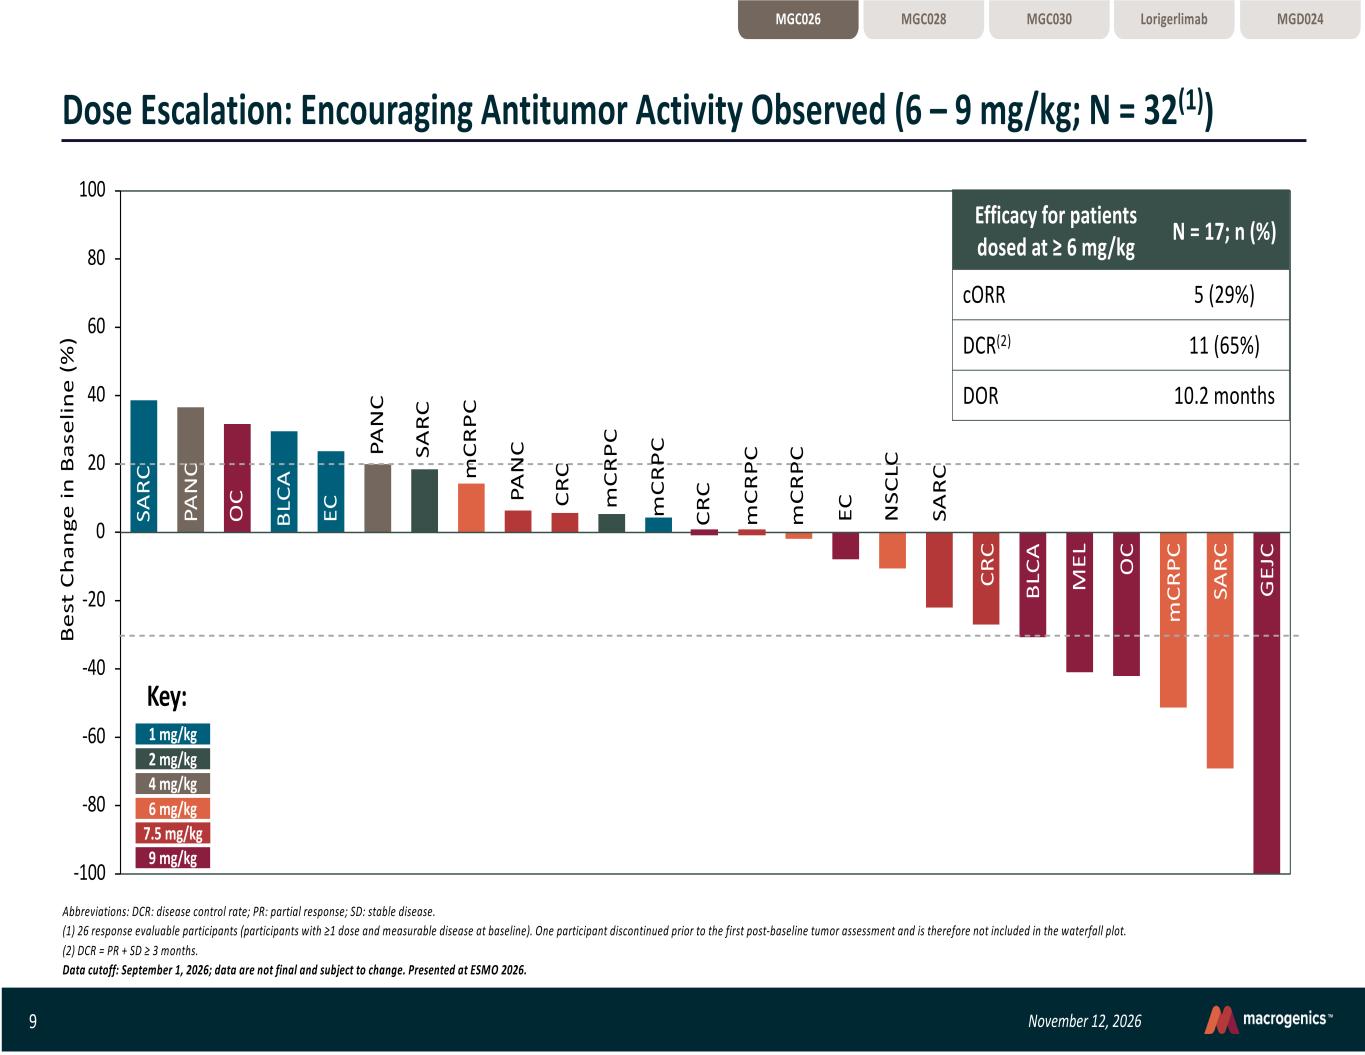
9 November 12, 2026 Lorigerlimab MGD024MGC028 MGC030MGC026 -100 -80 -60 -40 -20 0 20 40 60 80 100 Dose Escalation: Encouraging Antitumor Activity Observed (6 – 9 mg/kg; N = 32(1)) Abbreviations: DCR: disease control rate; PR: partial response; SD: stable disease. (1) 26 response evaluable participants (participants with ≥1 dose and measurable disease at baseline). One participant discontinued prior to the first post-baseline tumor assessment and is therefore not included in the waterfall plot. (2) DCR = PR + SD ≥ 3 months. Data cutoff: September 1, 2026; data are not final and subject to change. Presented at ESMO 2026. Efficacy for patients dosed at ≥ 6 mg/kg N = 17; n (%) cORR 5 (29%) DCR(2) 11 (65%) DOR 10.2 months 1 mg/kg 4 mg/kg 9 mg/kg 2 mg/kg 7.5 mg/kg 6 mg/kg Key: SA RC PA N C O C BL CA EC PA N C SA RC m CR PC PA N C CR C m CR PC m CR PC CR C m CR PC m CR PC EC N SC LC SA RC CR C BL CA M EL O C m CR PC SA RC G EJ C Be st C ha ng e in B as el in e (% )
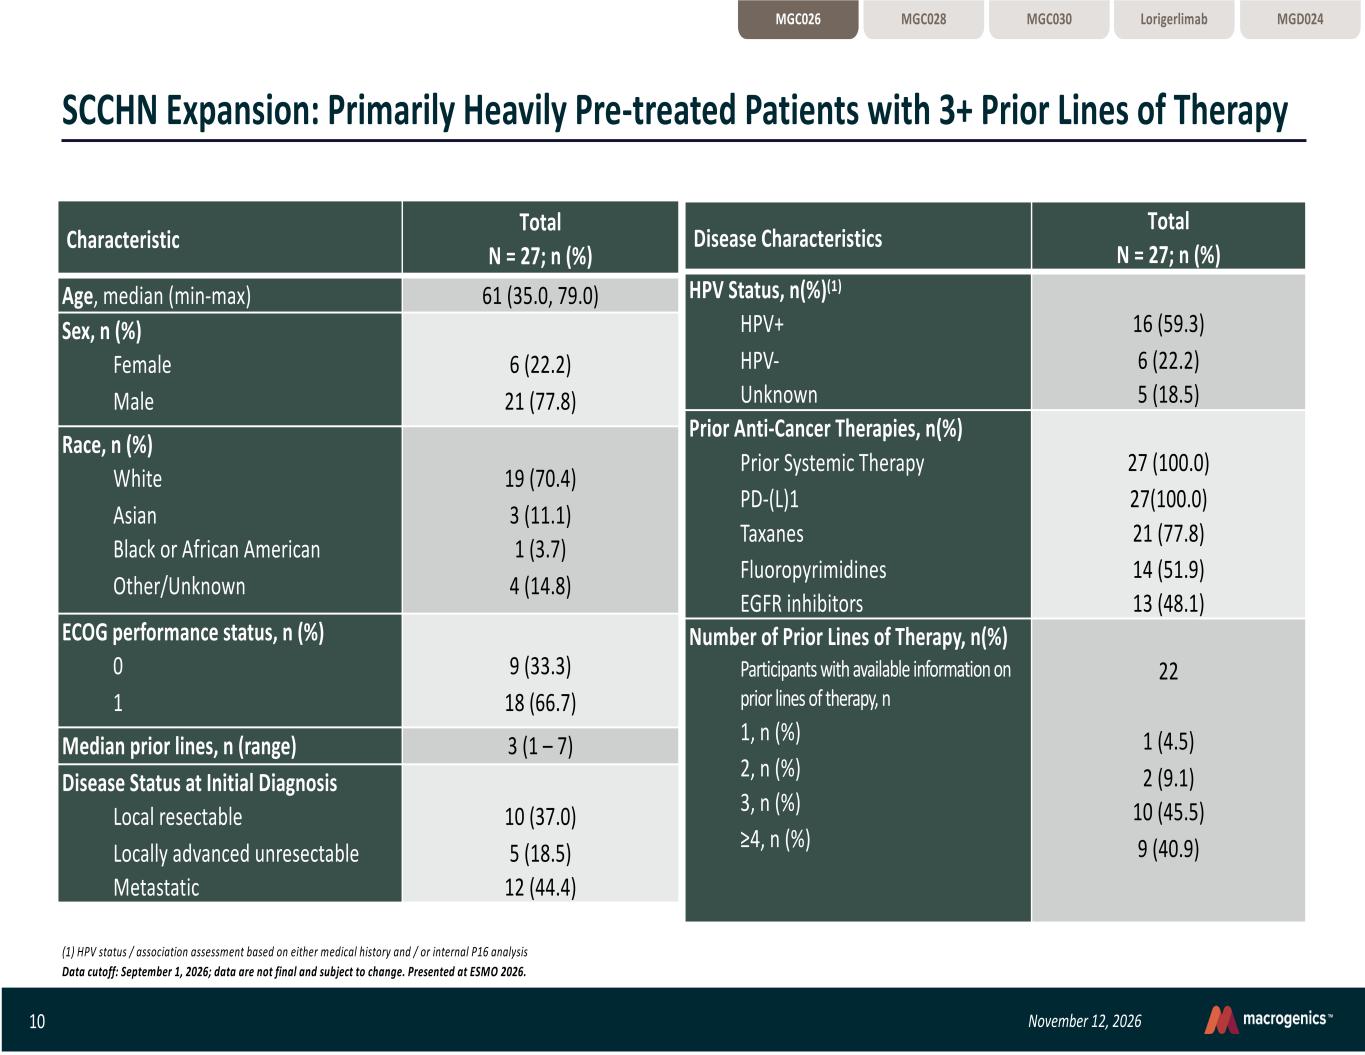
10 November 12, 2026 SCCHN Expansion: Primarily Heavily Pre-treated Patients with 3+ Prior Lines of Therapy Characteristic Total N = 27; n (%) Age, median (min-max) 61 (35.0, 79.0) Sex, n (%) Female Male 6 (22.2) 21 (77.8) Race, n (%) White Asian Black or African American Other/Unknown 19 (70.4) 3 (11.1) 1 (3.7) 4 (14.8) ECOG performance status, n (%) 0 1 9 (33.3) 18 (66.7) Median prior lines, n (range) 3 (1 – 7) Disease Status at Initial Diagnosis Local resectable Locally advanced unresectable Metastatic 10 (37.0) 5 (18.5) 12 (44.4) Disease Characteristics Total N = 27; n (%) HPV Status, n(%)(1) HPV+ HPV- Unknown 16 (59.3) 6 (22.2) 5 (18.5) Prior Anti-Cancer Therapies, n(%) Prior Systemic Therapy PD-(L)1 Taxanes Fluoropyrimidines EGFR inhibitors 27 (100.0) 27(100.0) 21 (77.8) 14 (51.9) 13 (48.1) Number of Prior Lines of Therapy, n(%) Participants with available information on prior lines of therapy, n 1, n (%) 2, n (%) 3, n (%) ≥4, n (%) 22 1 (4.5) 2 (9.1) 10 (45.5) 9 (40.9) (1) HPV status / association assessment based on either medical history and / or internal P16 analysis Data cutoff: September 1, 2026; data are not final and subject to change. Presented at ESMO 2026. Lorigerlimab MGD024MGC028 MGC030MGC026
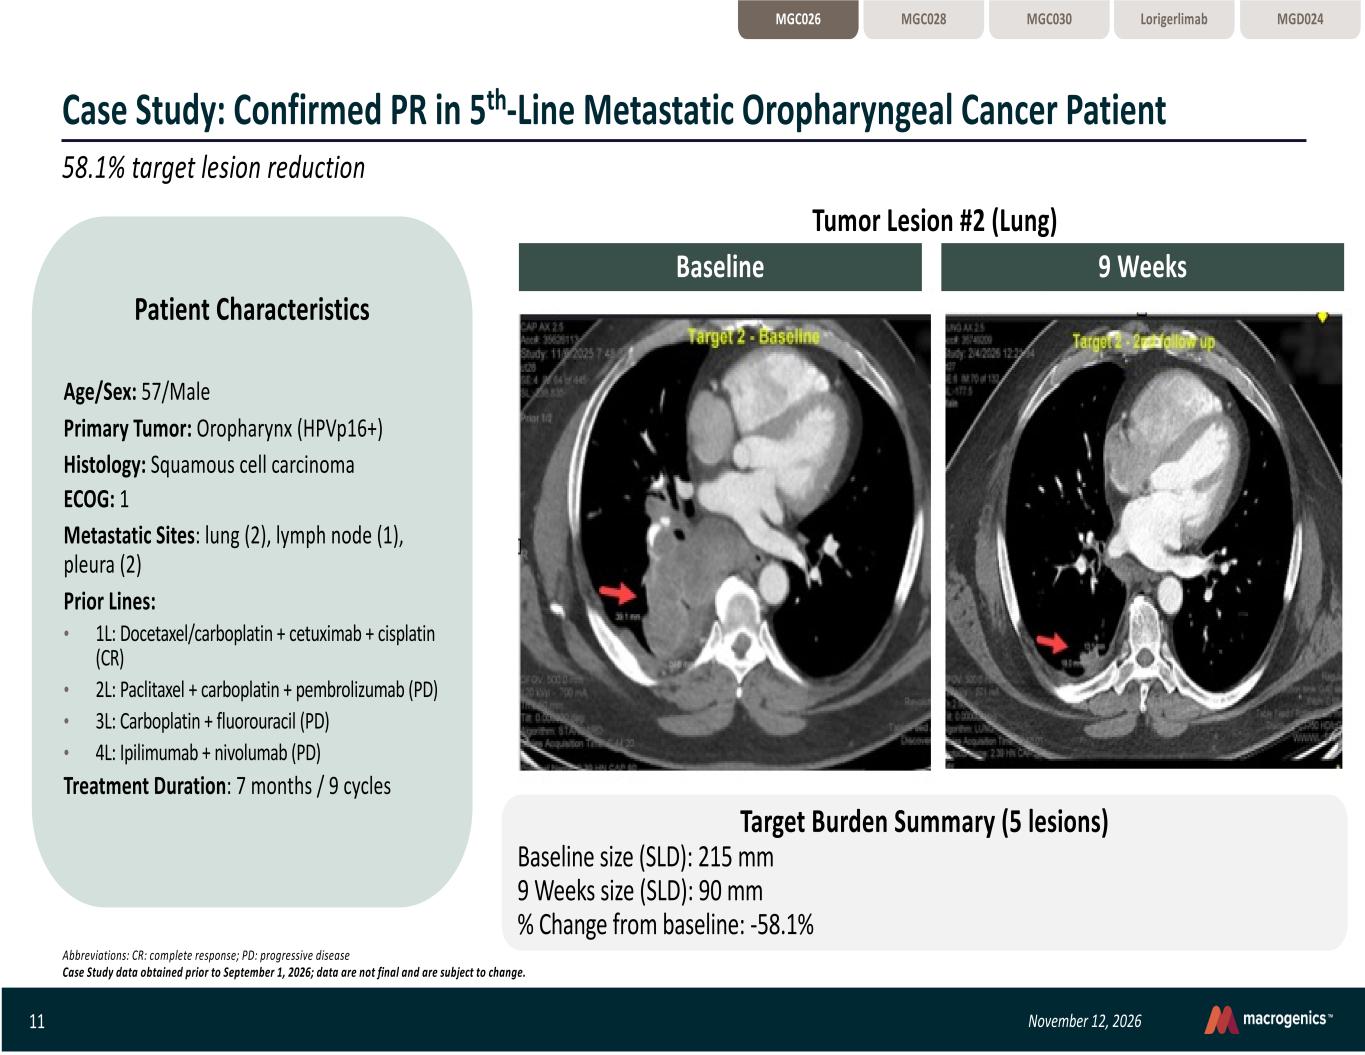
11 November 12, 2026 Case Study: Confirmed PR in 5th-Line Metastatic Oropharyngeal Cancer Patient 58.1% target lesion reduction Target Burden Summary (5 lesions) Baseline size (SLD): 215 mm 9 Weeks size (SLD): 90 mm % Change from baseline: -58.1% Baseline 9 Weeks Abbreviations: CR: complete response; PD: progressive disease Case Study data obtained prior to September 1, 2026; data are not final and are subject to change. Tumor Lesion #2 (Lung) Patient Characteristics Age/Sex: 57/Male Primary Tumor: Oropharynx (HPVp16+) Histology: Squamous cell carcinoma ECOG: 1 Metastatic Sites: lung (2), lymph node (1), pleura (2) Prior Lines: • 1L: Docetaxel/carboplatin + cetuximab + cisplatin (CR) • 2L: Paclitaxel + carboplatin + pembrolizumab (PD) • 3L: Carboplatin + fluorouracil (PD) • 4L: Ipilimumab + nivolumab (PD) Treatment Duration: 7 months / 9 cycles Lorigerlimab MGD024MGC028 MGC030MGC026
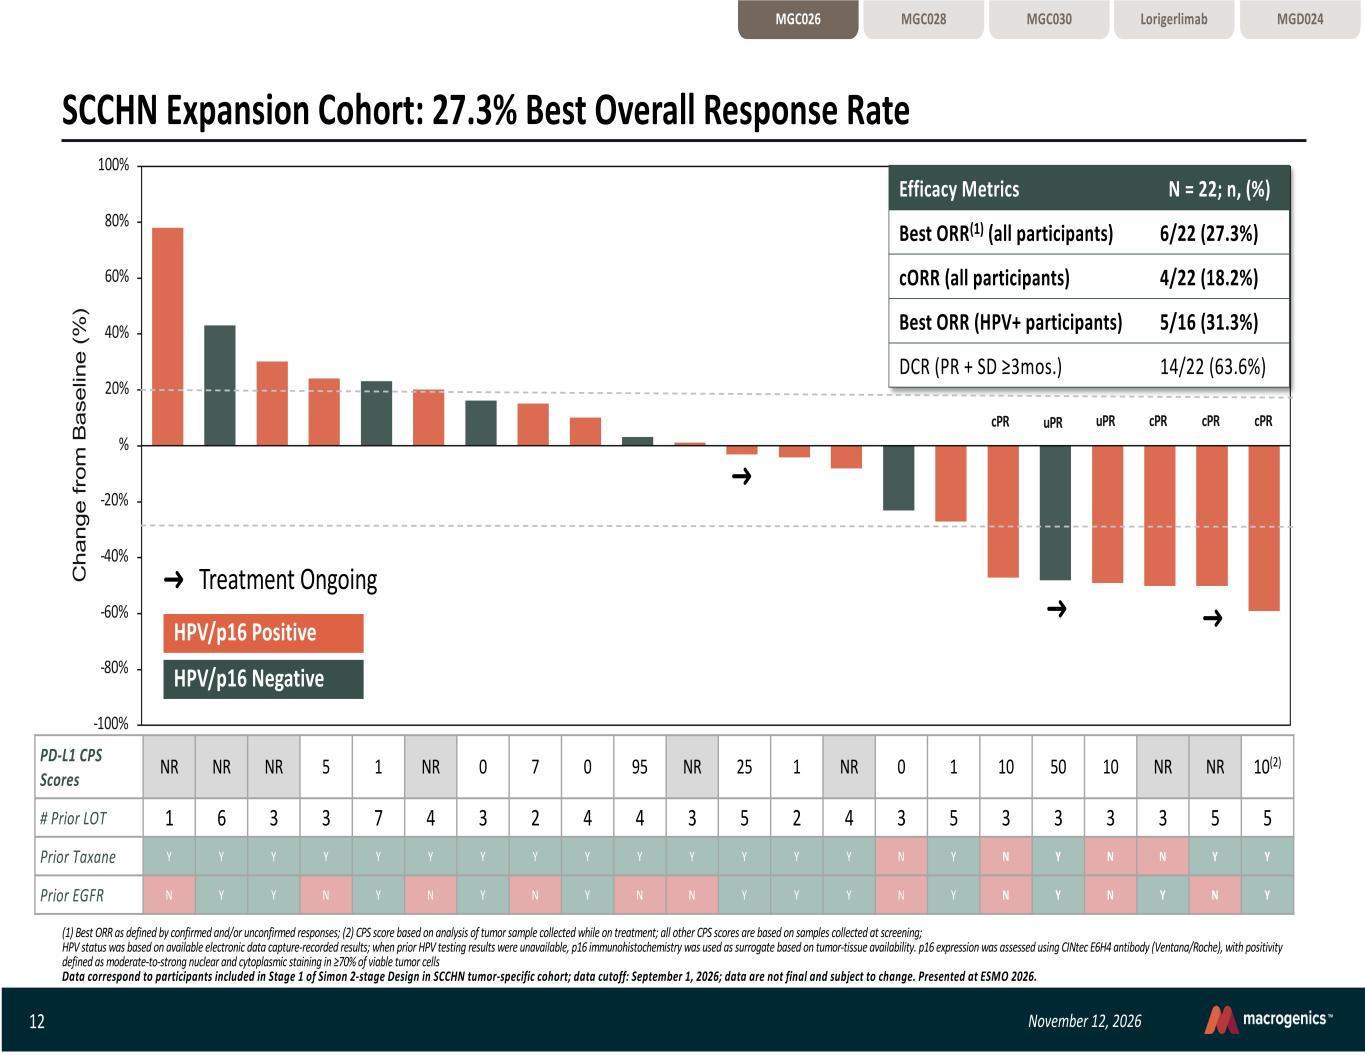
12 November 12, 2026 SCCHN Expansion Cohort: 27.3% Best Overall Response Rate (1) Best ORR as defined by confirmed and/or unconfirmed responses; (2) CPS score based on analysis of tumor sample collected while on treatment; all other CPS scores are based on samples collected at screening; HPV status was based on available electronic data capture-recorded results; when prior HPV testing results were unavailable, p16 immunohistochemistry was used as surrogate based on tumor-tissue availability. p16 expression was assessed using CINtec E6H4 antibody (Ventana/Roche), with positivity defined as moderate-to-strong nuclear and cytoplasmic staining in ≥70% of viable tumor cells Data correspond to participants included in Stage 1 of Simon 2-stage Design in SCCHN tumor-specific cohort; data cutoff: September 1, 2026; data are not final and subject to change. Presented at ESMO 2026. -100% -80% -60% -40% -20% % 20% 40% 60% 80% 100% C ha ng e fro m B as el in e (% ) Efficacy Metrics N = 22; n, (%) Best ORR(1) (all participants) 6/22 (27.3%) cORR (all participants) 4/22 (18.2%) Best ORR (HPV+ participants) 5/16 (31.3%) DCR (PR + SD ≥3mos.) 14/22 (63.6%) HPV/p16 Positive HPV/p16 Negative Treatment Ongoing➜ ➜ ➜ ➜ cPR uPR uPR cPR cPR cPR PD-L1 CPS Scores NR NR NR 5 1 NR 0 7 0 95 NR 25 1 NR 0 1 10 50 10 NR NR 10(2) # Prior LOT 1 6 3 3 7 4 3 2 4 4 3 5 2 4 3 5 3 3 3 3 5 5 Prior Taxane Y Y Y Y Y Y Y Y Y Y Y Y Y Y N Y N Y N N Y Y Prior EGFR N Y Y N Y N Y N Y N N Y Y Y N Y N Y N Y N Y Lorigerlimab MGD024MGC028 MGC030MGC026
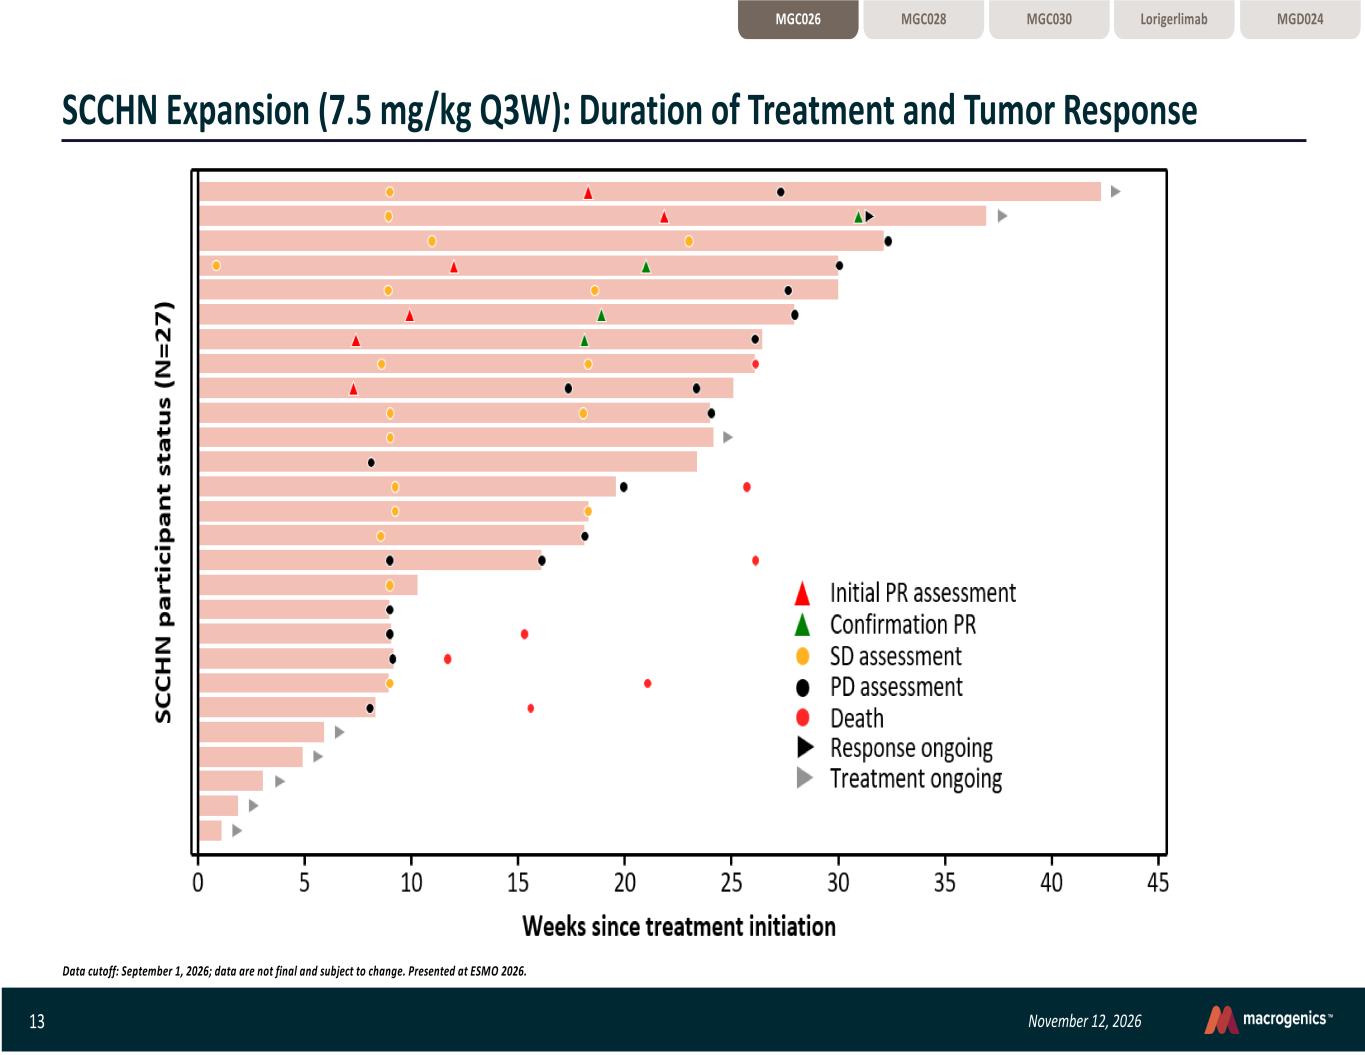
13 November 12, 2026 SCCHN Expansion (7.5 mg/kg Q3W): Duration of Treatment and Tumor Response Data cutoff: September 1, 2026; data are not final and subject to change. Presented at ESMO 2026. Lorigerlimab MGD024MGC028 MGC030MGC026
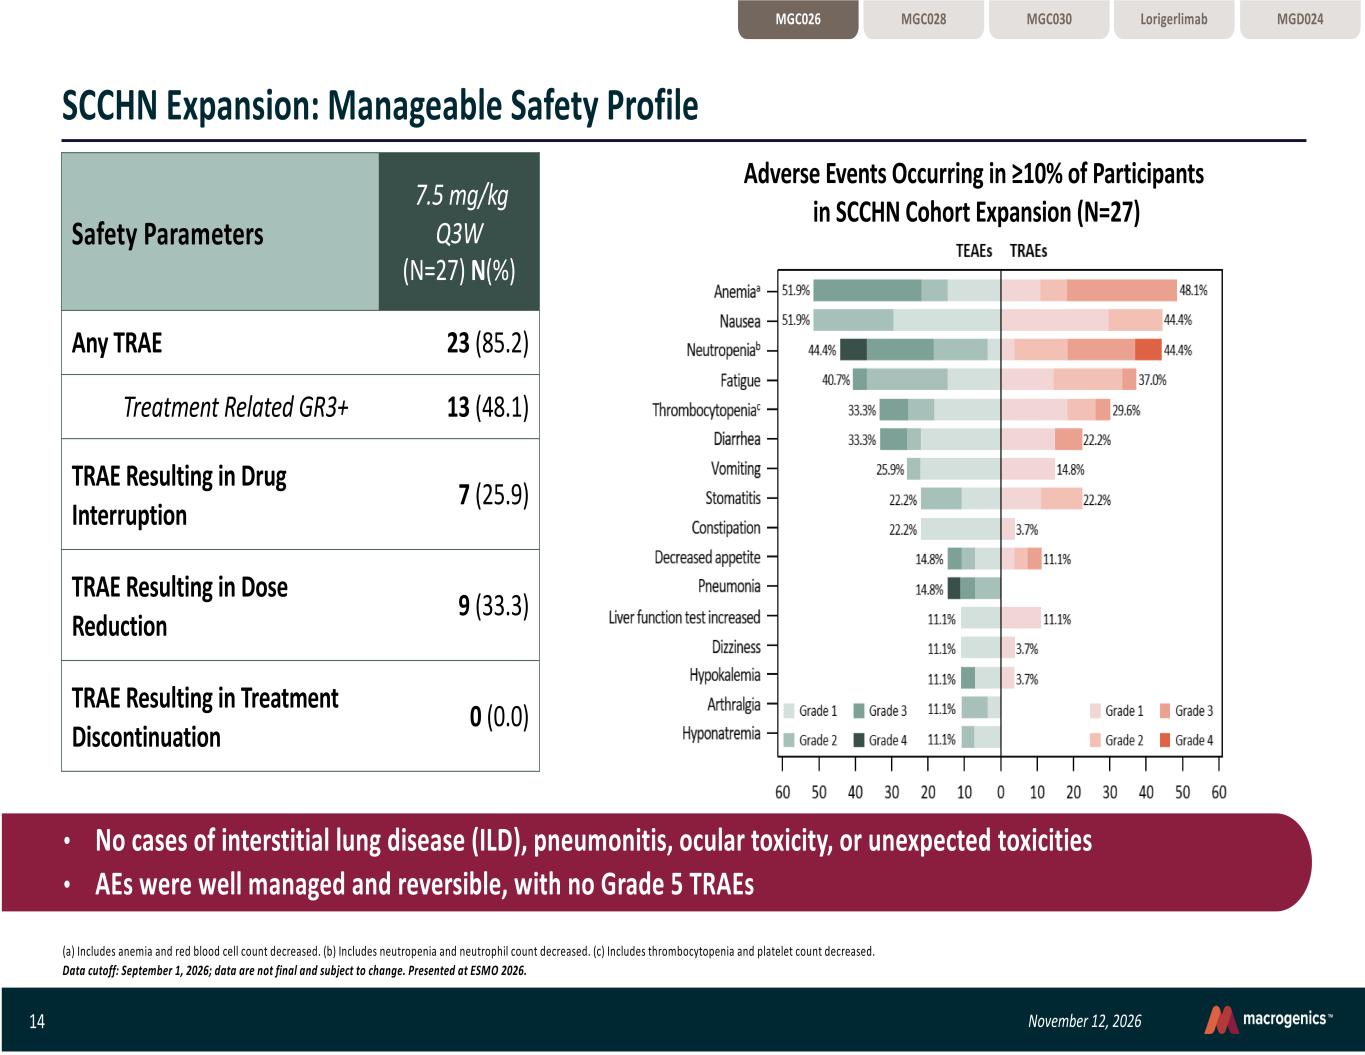
14 November 12, 2026 SCCHN Expansion: Manageable Safety Profile Safety Parameters 7.5 mg/kg Q3W (N=27) N(%) Any TRAE 23 (85.2) Treatment Related GR3+ 13 (48.1) TRAE Resulting in Drug Interruption 7 (25.9) TRAE Resulting in Dose Reduction 9 (33.3) TRAE Resulting in Treatment Discontinuation 0 (0.0) (a) Includes anemia and red blood cell count decreased. (b) Includes neutropenia and neutrophil count decreased. (c) Includes thrombocytopenia and platelet count decreased. Data cutoff: September 1, 2026; data are not final and subject to change. Presented at ESMO 2026. • No cases of interstitial lung disease (ILD), pneumonitis, ocular toxicity, or unexpected toxicities • AEs were well managed and reversible, with no Grade 5 TRAEs Adverse Events Occurring in ≥10% of Participants in SCCHN Cohort Expansion (N=27) Lorigerlimab MGD024MGC028 MGC030MGC026
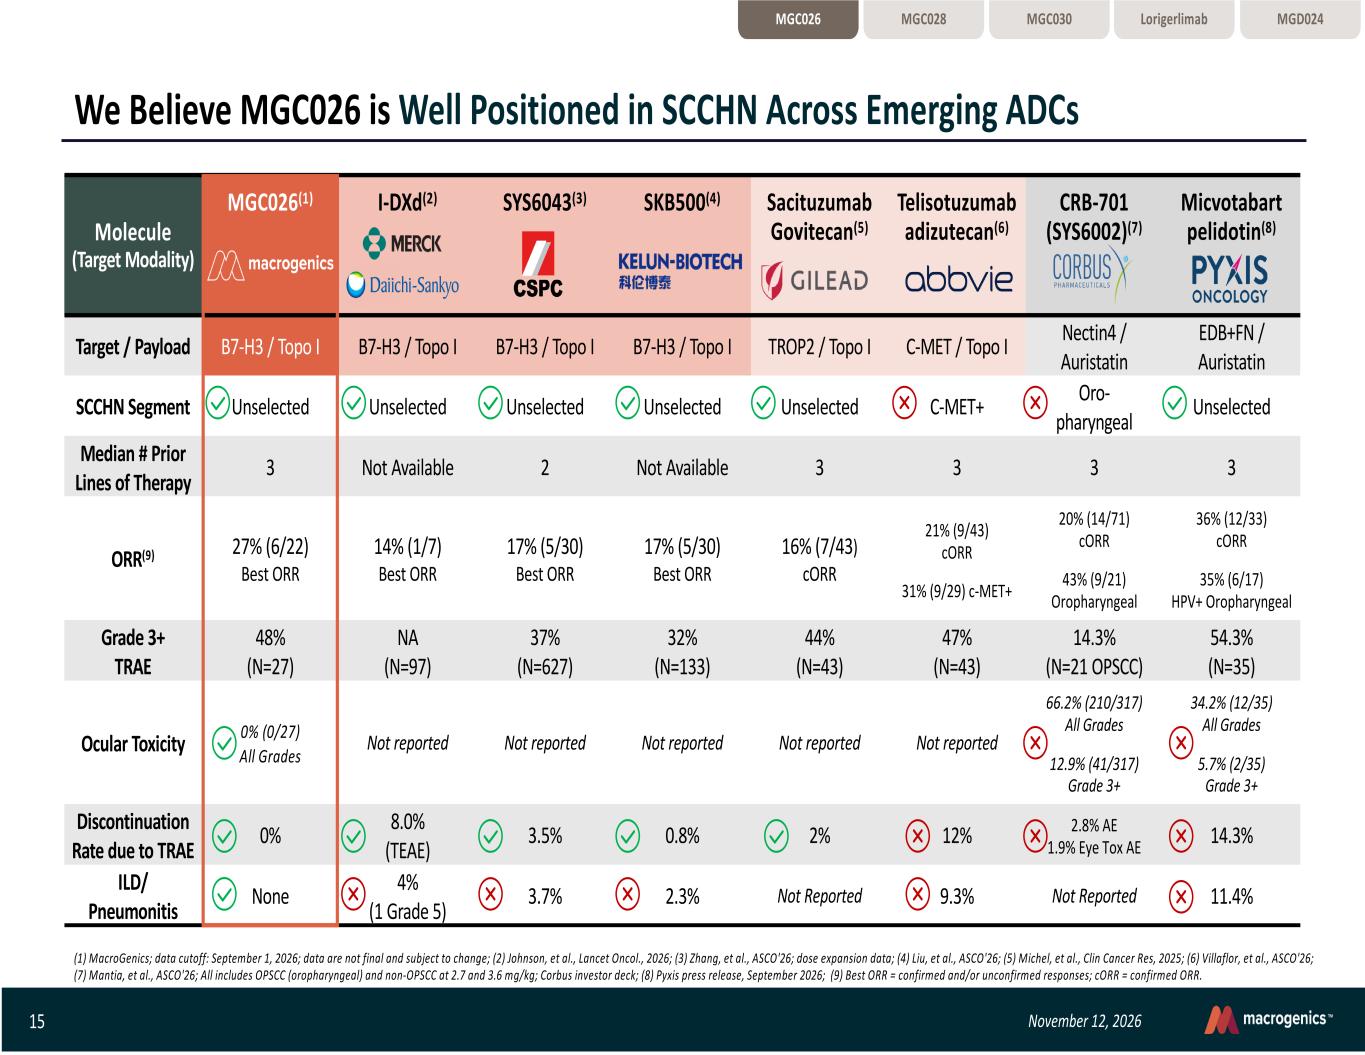
15 November 12, 2026 We Believe MGC026 is Well Positioned in SCCHN Across Emerging ADCs (1) MacroGenics; data cutoff: September 1, 2026; data are not final and subject to change; (2) Johnson, et al., Lancet Oncol., 2026; (3) Zhang, et al., ASCO'26; dose expansion data; (4) Liu, et al., ASCO'26; (5) Michel, et al., Clin Cancer Res, 2025; (6) Villaflor, et al., ASCO'26; (7) Mantia, et al., ASCO'26; All includes OPSCC (oropharyngeal) and non-OPSCC at 2.7 and 3.6 mg/kg; Corbus investor deck; (8) Pyxis press release, September 2026; (9) Best ORR = confirmed and/or unconfirmed responses; cORR = confirmed ORR. Molecule (Target Modality) MGC026(1) I-DXd(2) SYS6043(3) SKB500(4) Sacituzumab Govitecan(5) Telisotuzumab adizutecan(6) CRB-701 (SYS6002)(7) Micvotabart pelidotin(8) Target / Payload B7-H3 / Topo I B7-H3 / Topo I B7-H3 / Topo I B7-H3 / Topo I TROP2 / Topo I C-MET / Topo I Nectin4 / Auristatin EDB+FN / Auristatin SCCHN Segment Unselected Unselected Unselected Unselected Unselected C-MET+ Oro- pharyngeal Unselected Median # Prior Lines of Therapy 3 Not Available 2 Not Available 3 3 3 3 ORR(9) 27% (6/22) Best ORR 14% (1/7) Best ORR 17% (5/30) Best ORR 17% (5/30) Best ORR 16% (7/43) cORR 21% (9/43) cORR 31% (9/29) c-MET+ 20% (14/71) cORR 43% (9/21) Oropharyngeal 36% (12/33) cORR 35% (6/17) HPV+ Oropharyngeal Grade 3+ TRAE 48% (N=27) NA (N=97) 37% (N=627) 32% (N=133) 44% (N=43) 47% (N=43) 14.3% (N=21 OPSCC) 54.3% (N=35) Ocular Toxicity 0% (0/27) All Grades Not reported Not reported Not reported Not reported Not reported 66.2% (210/317) All Grades 12.9% (41/317) Grade 3+ 34.2% (12/35) All Grades 5.7% (2/35) Grade 3+ Discontinuation Rate due to TRAE 0% 8.0% (TEAE) 3.5% 0.8% 2% 12% 2.8% AE 1.9% Eye Tox AE 14.3% ILD/ Pneumonitis None 4% (1 Grade 5) 3.7% 2.3% Not Reported 9.3% Not Reported 11.4% Lorigerlimab MGD024MGC028 MGC030MGC026
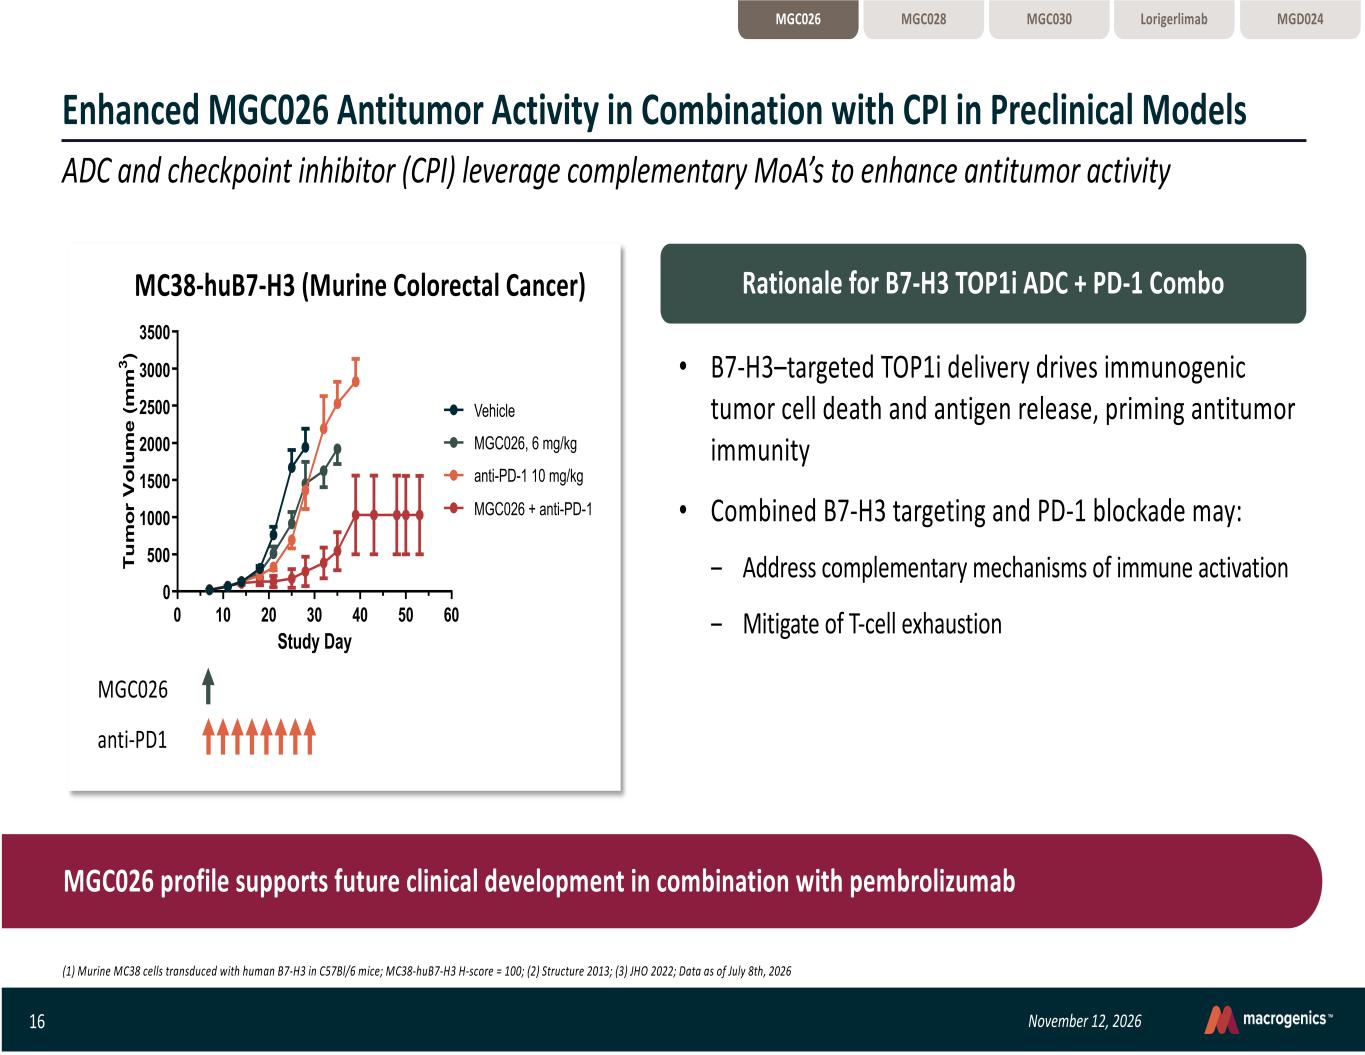
16 November 12, 2026 0 10 20 30 40 50 60 0 500 1000 1500 2000 2500 3000 3500 Vehicle MGC026, 6 mg/kg Study Day Tu m or V ol um e (m m 3 ) anti-PD-1 10 mg/kg MGC026 + anti-PD-1 MGC026 anti-PD1 Enhanced MGC026 Antitumor Activity in Combination with CPI in Preclinical Models MGC026 profile supports future clinical development in combination with pembrolizumab ADC and checkpoint inhibitor (CPI) leverage complementary MoA’s to enhance antitumor activity (1) Murine MC38 cells transduced with human B7-H3 in C57Bl/6 mice; MC38-huB7-H3 H-score = 100; (2) Structure 2013; (3) JHO 2022; Data as of July 8th, 2026 MC38-huB7-H3 (Murine Colorectal Cancer) • B7-H3–targeted TOP1i delivery drives immunogenic tumor cell death and antigen release, priming antitumor immunity • Combined B7-H3 targeting and PD-1 blockade may: ‒ Address complementary mechanisms of immune activation ‒ Mitigate of T-cell exhaustion Rationale for B7-H3 TOP1i ADC + PD-1 Combo Lorigerlimab MGD024MGC028 MGC030MGC026

17 November 12, 2026 MGC026 Summary: Promising Development Path in SCCHN 0% TRAEs leading to discontinuation (SCCHN) 27% Best Overall Response in late line SCCHN 31% Best Overall Response in HPV+ patients 64% Disease control rate 0 Cases ILD/pneumonitis or ocular toxicity to date Differentiated B7-H3 TOP1i ADC with encouraging preliminary activity in heavily pretreated patients • Enroll remaining Simon's 2-stage monotherapy SCCHN cohort (n=40 patients) by YE2026 • Enroll other tumor-specific cohorts (endometrial cancer, melanoma, soft tissue sarcoma) Ongoing Development • Promising profile supports evaluation of MGC026 + CPIs and in early-line setting • Plans to initiate MGC026 + pembrolizumab combo cohort in Phase 1 study under evaluation Future Development Data cutoff: September 1, 2026; data are not final and subject to change. Presented at ESMO 2026. • Next MGC026 update anticipated mid-2027 • Evaluating evolving competitive landscape to inform development and collaboration strategies Lorigerlimab MGD024MGC028 MGC030MGC026
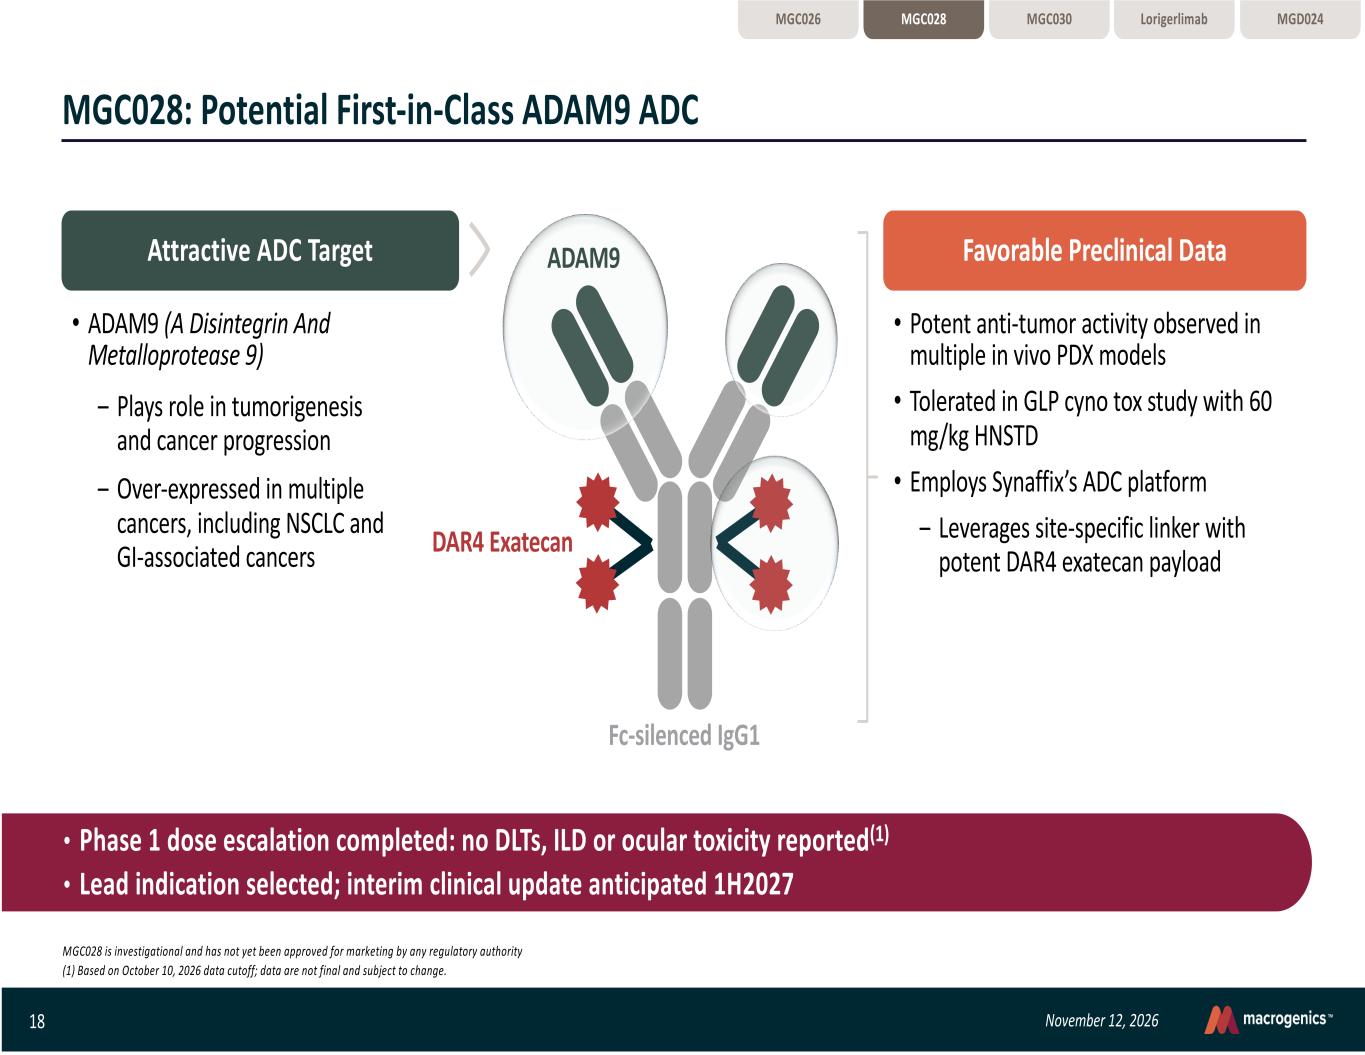
18 November 12, 2026 MGC028: Potential First-in-Class ADAM9 ADC MGC028 is investigational and has not yet been approved for marketing by any regulatory authority (1) Based on October 10, 2026 data cutoff; data are not final and subject to change. • ADAM9 (A Disintegrin And Metalloprotease 9) ‒ Plays role in tumorigenesis and cancer progression ‒ Over-expressed in multiple cancers, including NSCLC and GI-associated cancers • Potent anti-tumor activity observed in multiple in vivo PDX models • Tolerated in GLP cyno tox study with 60 mg/kg HNSTD • Employs Synaffix’s ADC platform ‒ Leverages site-specific linker with potent DAR4 exatecan payload Attractive ADC Target Favorable Preclinical Data • Phase 1 dose escalation completed: no DLTs, ILD or ocular toxicity reported(1) • Lead indication selected; interim clinical update anticipated 1H2027 DAR4 Exatecan ADAM9 Lorigerlimab MGD024MGC028 MGC030MGC026 Fc-silenced IgG1
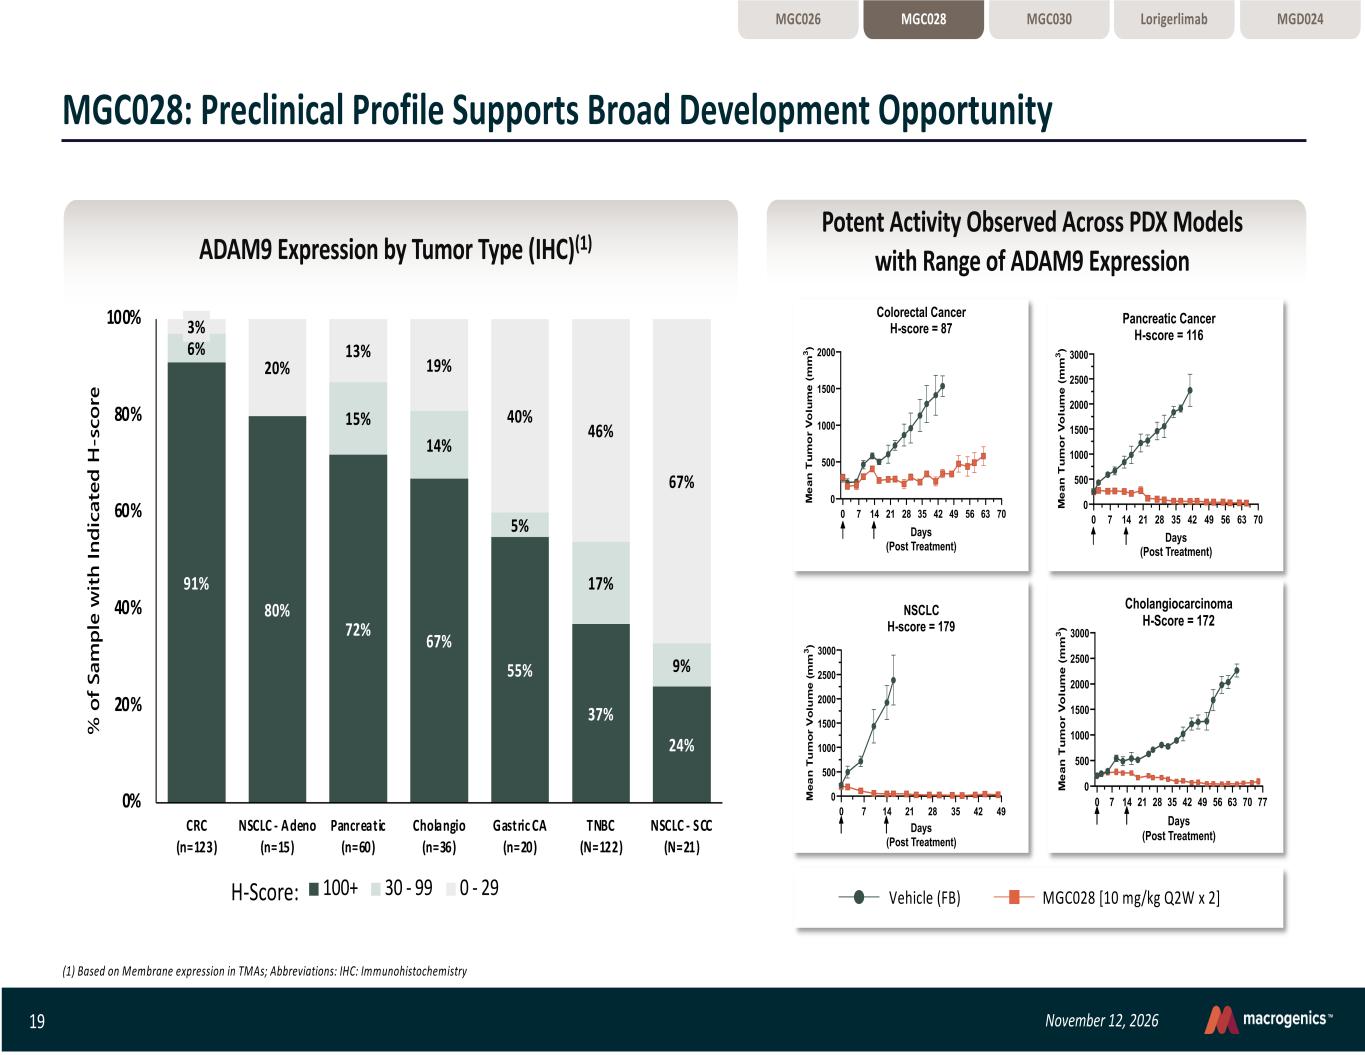
19 November 12, 2026 91% 80% 72% 67% 55% 37% 24% 6% 15% 14% 5% 17% 9% 3% 20% 13% 19% 40% 46% 67% 0% 20% 40% 60% 80% 100% CRC (n=123) NSCLC - Adeno (n=15) Pancreatic (n=60) Cholangio (n=36) Gastric CA (n=20) TNBC (N=122) NSCLC - SCC (N=21) % o f S am pl e w ith In di ca te d H -s co re 100+ 30 - 99 0 - 29 ADAM9 Expression by Tumor Type (IHC)(1) Potent Activity Observed Across PDX Models with Range of ADAM9 Expression MGC028: Preclinical Profile Supports Broad Development Opportunity H-Score: 0 7 14 21 28 35 42 49 56 63 70 0 500 1000 1500 2000 Colorectal Cancer H-score = 87 Days (Post Treatment) M ea n Tu m or V ol um e (m m 3 ) 7 21 28 35 42 49 56 63 70 0 500 1000 1500 2000 2500 3000 Days (Post Treatment) M ea n Tu m or V ol um e (m m 3 ) 0 14 Pancreatic Cancer H-score = 116 7 21 28 35 42 49 0 500 1000 1500 2000 2500 3000 NSCLC H-score = 179 Days (Post Treatment) M ea n Tu m or V ol um e (m m 3 ) 0 14 0 7 14 21 28 35 42 49 56 63 70 77 0 500 1000 1500 2000 2500 3000 Cholangiocarcinoma H-Score = 172 Days (Post Treatment) M ea n Tu m or V ol um e (m m 3 ) Vehicle (FB) MGC028 [10 mg/kg Q2W x 2] (1) Based on Membrane expression in TMAs; Abbreviations: IHC: Immunohistochemistry Lorigerlimab MGD024MGC028 MGC030MGC026
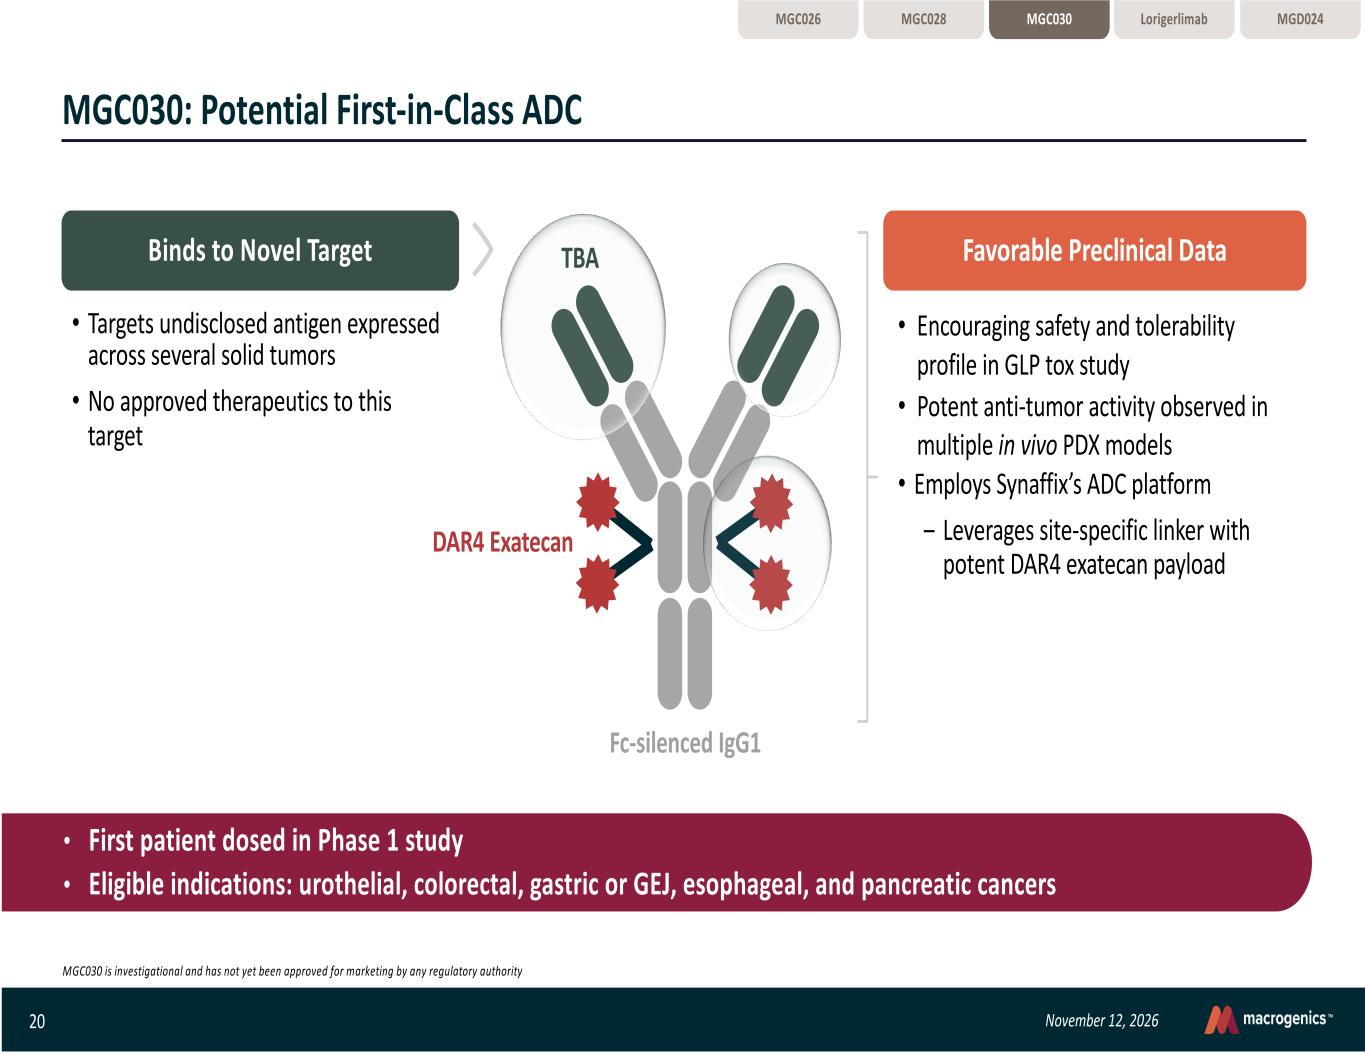
20 November 12, 2026 MGC030: Potential First-in-Class ADC MGC030 is investigational and has not yet been approved for marketing by any regulatory authority • First patient dosed in Phase 1 study • Eligible indications: urothelial, colorectal, gastric or GEJ, esophageal, and pancreatic cancers • Encouraging safety and tolerability profile in GLP tox study • Potent anti-tumor activity observed in multiple in vivo PDX models • Employs Synaffix’s ADC platform ‒ Leverages site-specific linker with potent DAR4 exatecan payload Favorable Preclinical Data • Targets undisclosed antigen expressed across several solid tumors • No approved therapeutics to this target Binds to Novel Target Fc-silenced IgG1 DAR4 Exatecan TBA Lorigerlimab MGD024MGC028 MGC030MGC026
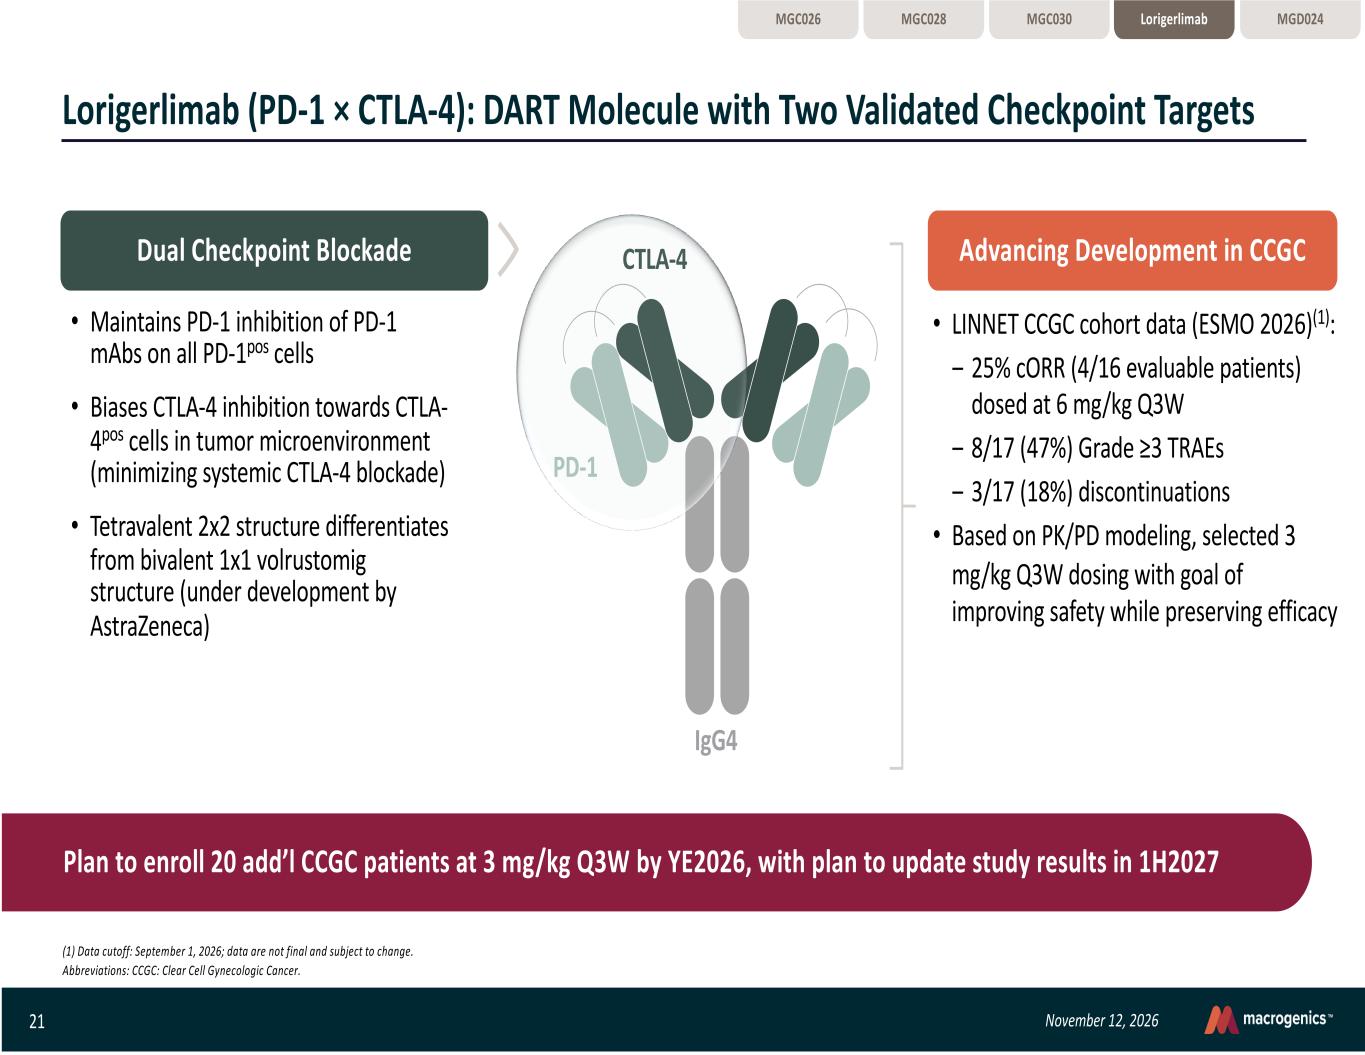
21 November 12, 2026 Lorigerlimab (PD-1 × CTLA-4): DART Molecule with Two Validated Checkpoint Targets (1) Data cutoff: September 1, 2026; data are not final and subject to change. Abbreviations: CCGC: Clear Cell Gynecologic Cancer. Dual Checkpoint Blockade • Maintains PD-1 inhibition of PD-1 mAbs on all PD-1pos cells • Biases CTLA-4 inhibition towards CTLA- 4pos cells in tumor microenvironment (minimizing systemic CTLA-4 blockade) • Tetravalent 2x2 structure differentiates from bivalent 1x1 volrustomig structure (under development by AstraZeneca) Advancing Development in CCGC • LINNET CCGC cohort data (ESMO 2026)(1): ‒ 25% cORR (4/16 evaluable patients) dosed at 6 mg/kg Q3W ‒ 8/17 (47%) Grade ≥3 TRAEs ‒ 3/17 (18%) discontinuations • Based on PK/PD modeling, selected 3 mg/kg Q3W dosing with goal of improving safety while preserving efficacy Plan to enroll 20 add’l CCGC patients at 3 mg/kg Q3W by YE2026, with plan to update study results in 1H2027 PD-1 CTLA-4 Lorigerlimab MGD024MGC028 MGC030MGC026 IgG4
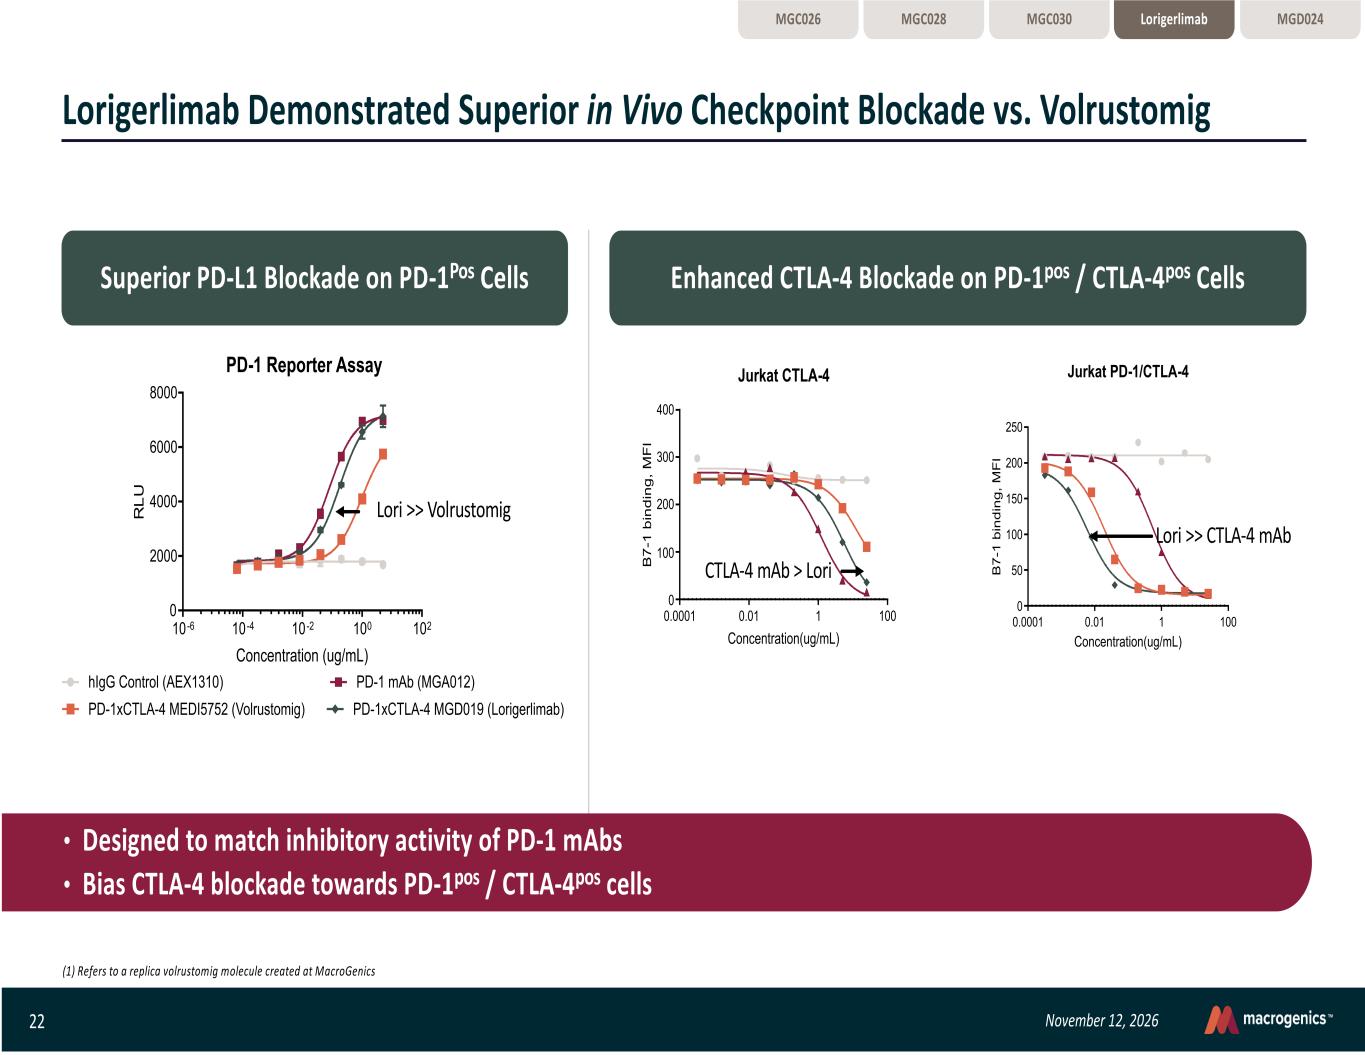
22 November 12, 2026 Lorigerlimab Demonstrated Superior in Vivo Checkpoint Blockade vs. Volrustomig 0.0001 0.01 1 100 0 100 200 300 400 Jurkat CTLA-4 Concentration(ug/mL) B7 -1 b in di ng , M FI 0.0001 0.01 1 100 0 50 100 150 200 250 Jurkat PD-1/CTLA-4 Concentration(ug/mL) B7 -1 b in di ng , M FI 0.0001 0.01 1 100 0 100 200 300 400 Jurkat CTLA-4 20181218 Exp72 PP Concentration(ug/mL) B7 -1 b in di ng , M FI 0.0001 0.01 1 100 0 50 100 150 200 250 Jurkat PD1/CTLA4 20181218 Exp72 PP Concentration(ug/mL) B7 -1 b in di ng , M FI PD-1xCTLA-4 MEDI5752 (Volrustomig) PD-1xCTLA-4 MGD019 (Lorigerlimab) CTLA-4 mAb (parental)hIgG Control (AEX2100) Lori >> CTLA-4 mAb CTLA-4 mAb > Lori Superior PD-L1 Blockade on PD-1Pos Cells 10 -6 10 -4 10 -2 100 102 0 2000 4000 6000 8000 PD-1 Reporter Assay Concentration (ug/mL) R LU PD-1xCTLA-4 MEDI5752 (Volrustomig) PD-1xCTLA-4 MGD019 (Lorigerlimab) PD-1 mAb (MGA012)hIgG Control (AEX1310) Lori >> Volrustomig Enhanced CTLA-4 Blockade on PD-1pos / CTLA-4pos Cells (1) Refers to a replica volrustomig molecule created at MacroGenics Lorigerlimab MGD024MGC028 MGC030MGC026 • Designed to match inhibitory activity of PD-1 mAbs • Bias CTLA-4 blockade towards PD-1pos / CTLA-4pos cells
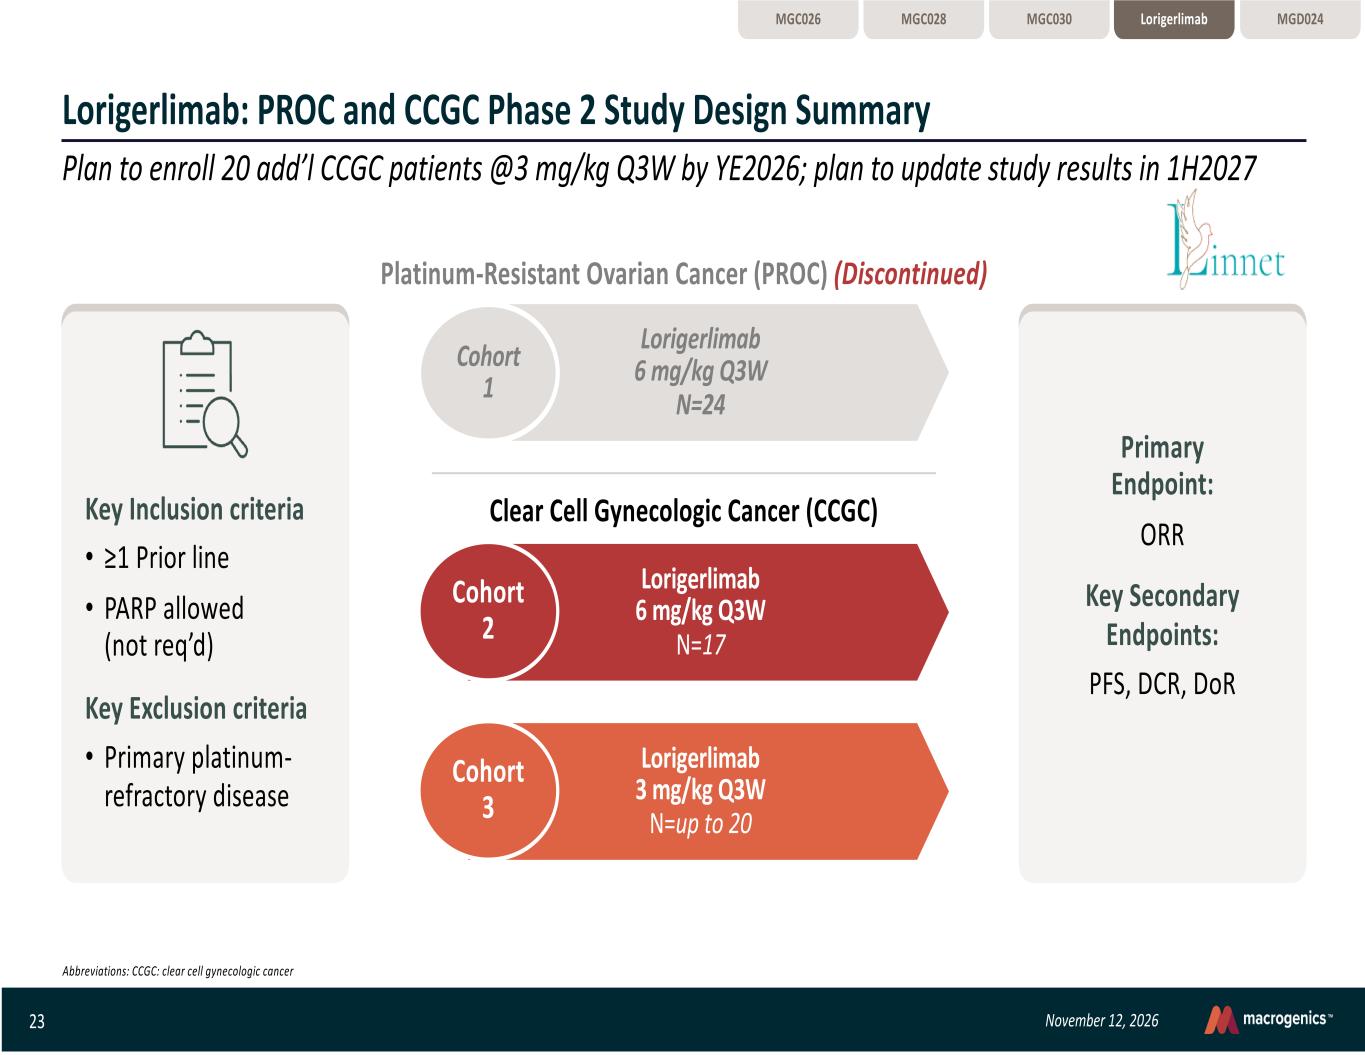
23 November 12, 2026 Key Inclusion criteria • ≥1 Prior line • PARP allowed (not req’d) Key Exclusion criteria • Primary platinum- refractory disease Lorigerlimab: PROC and CCGC Phase 2 Study Design Summary Abbreviations: CCGC: clear cell gynecologic cancer Plan to enroll 20 add’l CCGC patients @3 mg/kg Q3W by YE2026; plan to update study results in 1H2027 Primary Endpoint: ORR Key Secondary Endpoints: PFS, DCR, DoR Lorigerlimab 6 mg/kg Q3W N=24 Platinum-Resistant Ovarian Cancer (PROC) (Discontinued) Cohort 1 Lorigerlimab 3 mg/kg Q3W N=up to 20 Cohort 3 Lorigerlimab 6 mg/kg Q3W N=17 Cohort 2 Clear Cell Gynecologic Cancer (CCGC) Lorigerlimab MGD024MGC028 MGC030MGC026
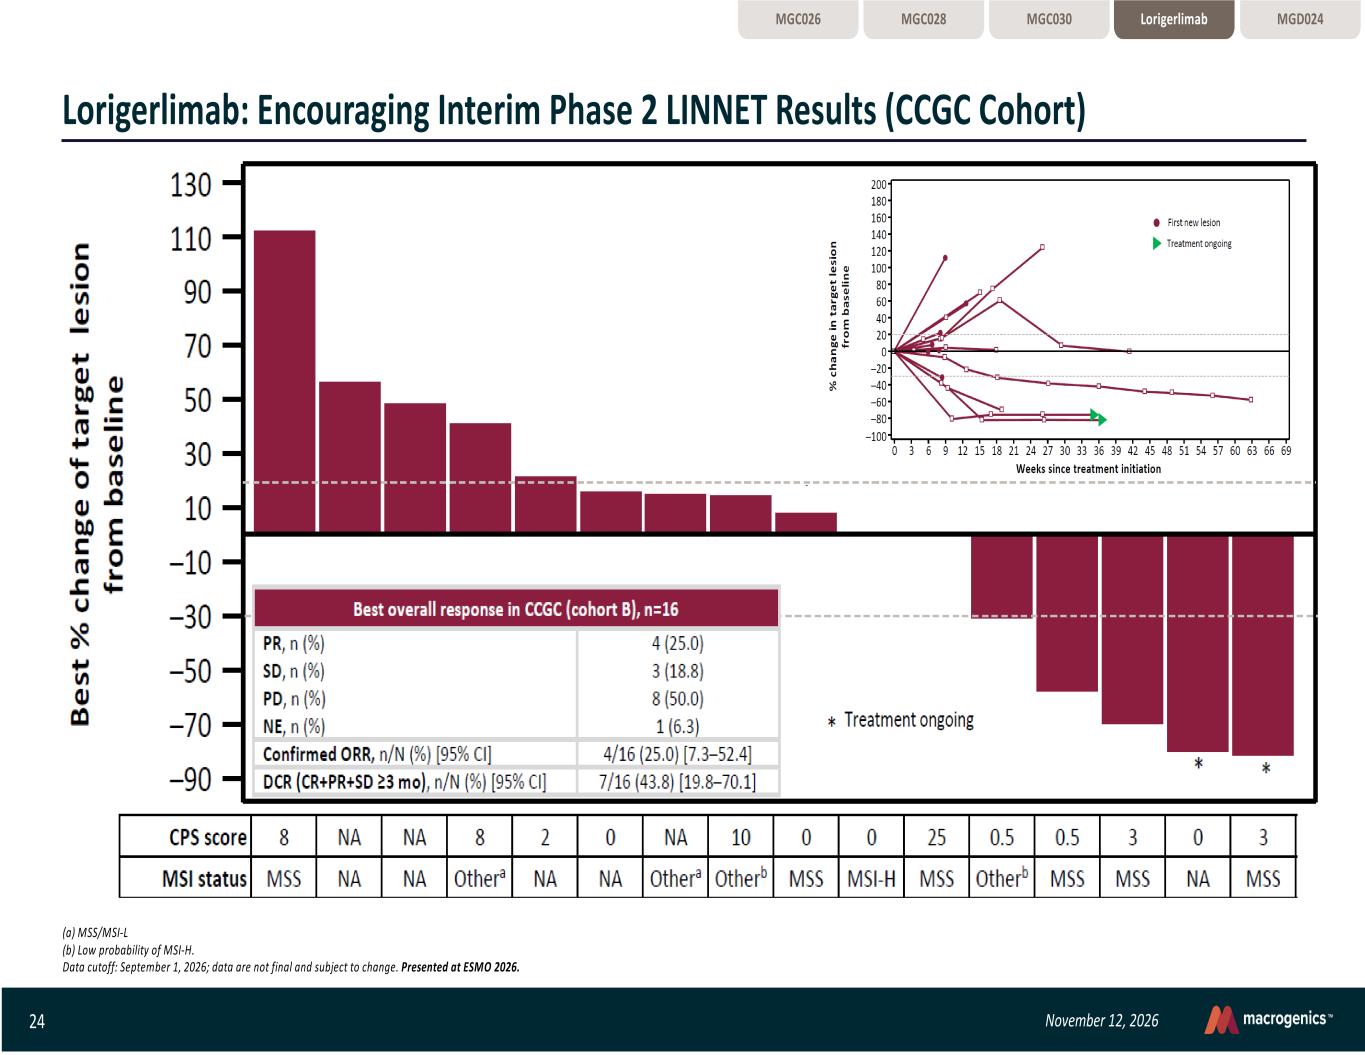
24 November 12, 2026 Lorigerlimab: Encouraging Interim Phase 2 LINNET Results (CCGC Cohort) Lorigerlimab MGD024MGC028 MGC030MGC026 (a) MSS/MSI-L (b) Low probability of MSI-H. Data cutoff: September 1, 2026; data are not final and subject to change. Presented at ESMO 2026.
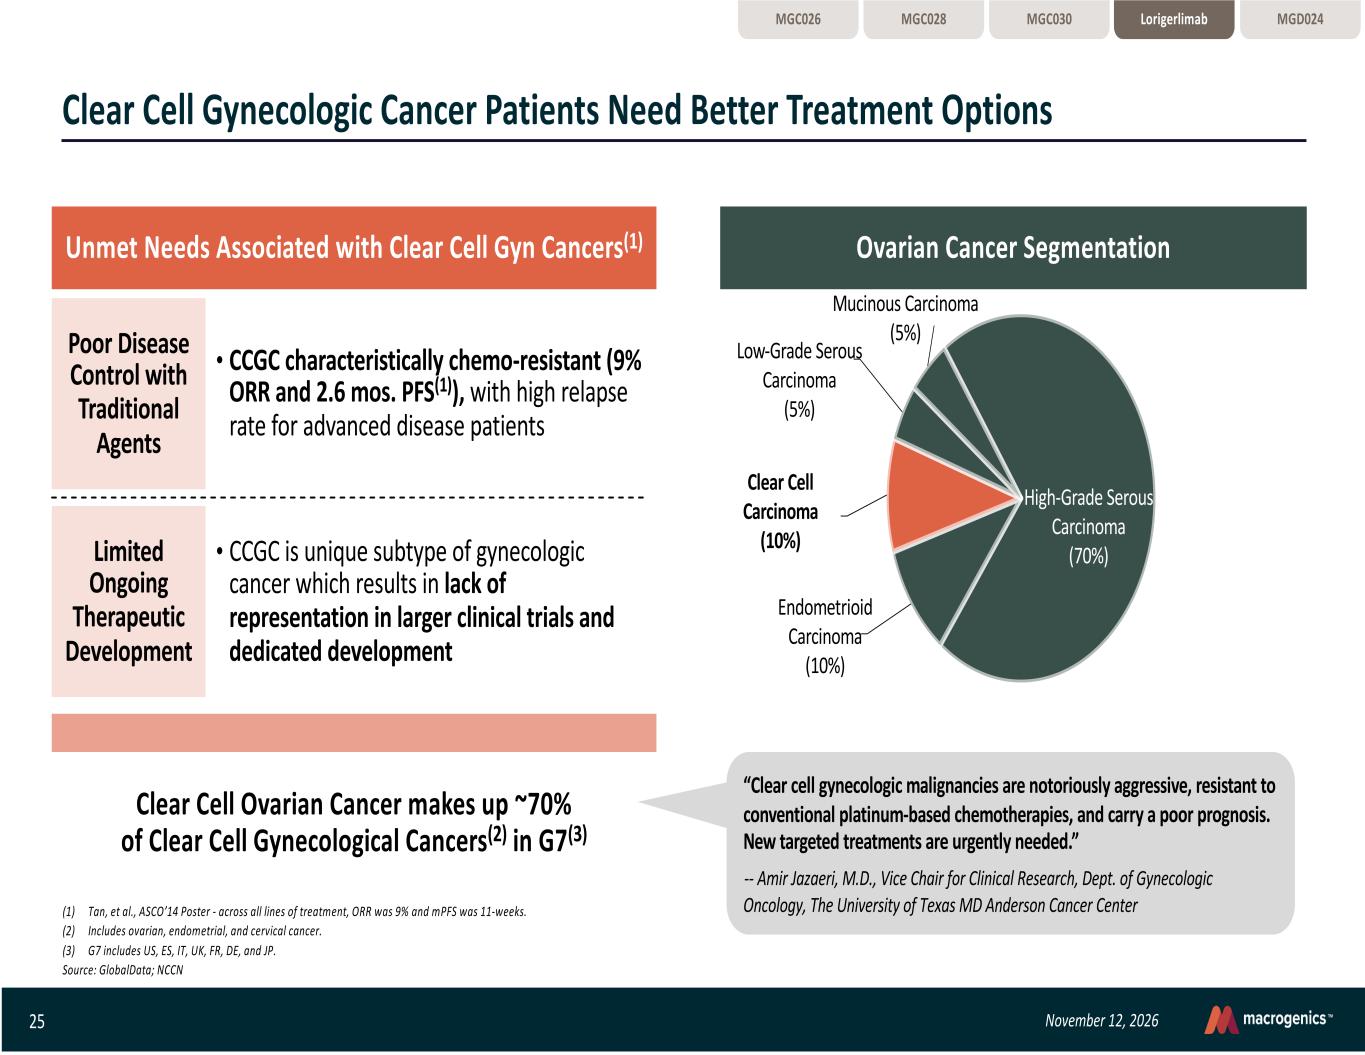
25 November 12, 2026 (1) Tan, et al., ASCO’14 Poster - across all lines of treatment, ORR was 9% and mPFS was 11-weeks. (2) Includes ovarian, endometrial, and cervical cancer. (3) G7 includes US, ES, IT, UK, FR, DE, and JP. Source: GlobalData; NCCN Clear Cell Gynecologic Cancer Patients Need Better Treatment Options Unmet Needs Associated with Clear Cell Gyn Cancers(1) Poor Disease Control with Traditional Agents Limited Ongoing Therapeutic Development • CCGC characteristically chemo-resistant (9% ORR and 2.6 mos. PFS(1)), with high relapse rate for advanced disease patients • CCGC is unique subtype of gynecologic cancer which results in lack of representation in larger clinical trials and dedicated development Lorigerlimab MGD024MGC028 MGC030MGC026 Clear Cell Ovarian Cancer makes up ~70% of Clear Cell Gynecological Cancers(2) in G7(3) Ovarian Cancer Segmentation High-Grade Serous Carcinoma (70%) Endometrioid Carcinoma (10%) Clear Cell Carcinoma (10%) Low-Grade Serous Carcinoma (5%) Mucinous Carcinoma (5%) “Clear cell gynecologic malignancies are notoriously aggressive, resistant to conventional platinum-based chemotherapies, and carry a poor prognosis. New targeted treatments are urgently needed.” -- Amir Jazaeri, M.D., Vice Chair for Clinical Research, Dept. of Gynecologic Oncology, The University of Texas MD Anderson Cancer Center
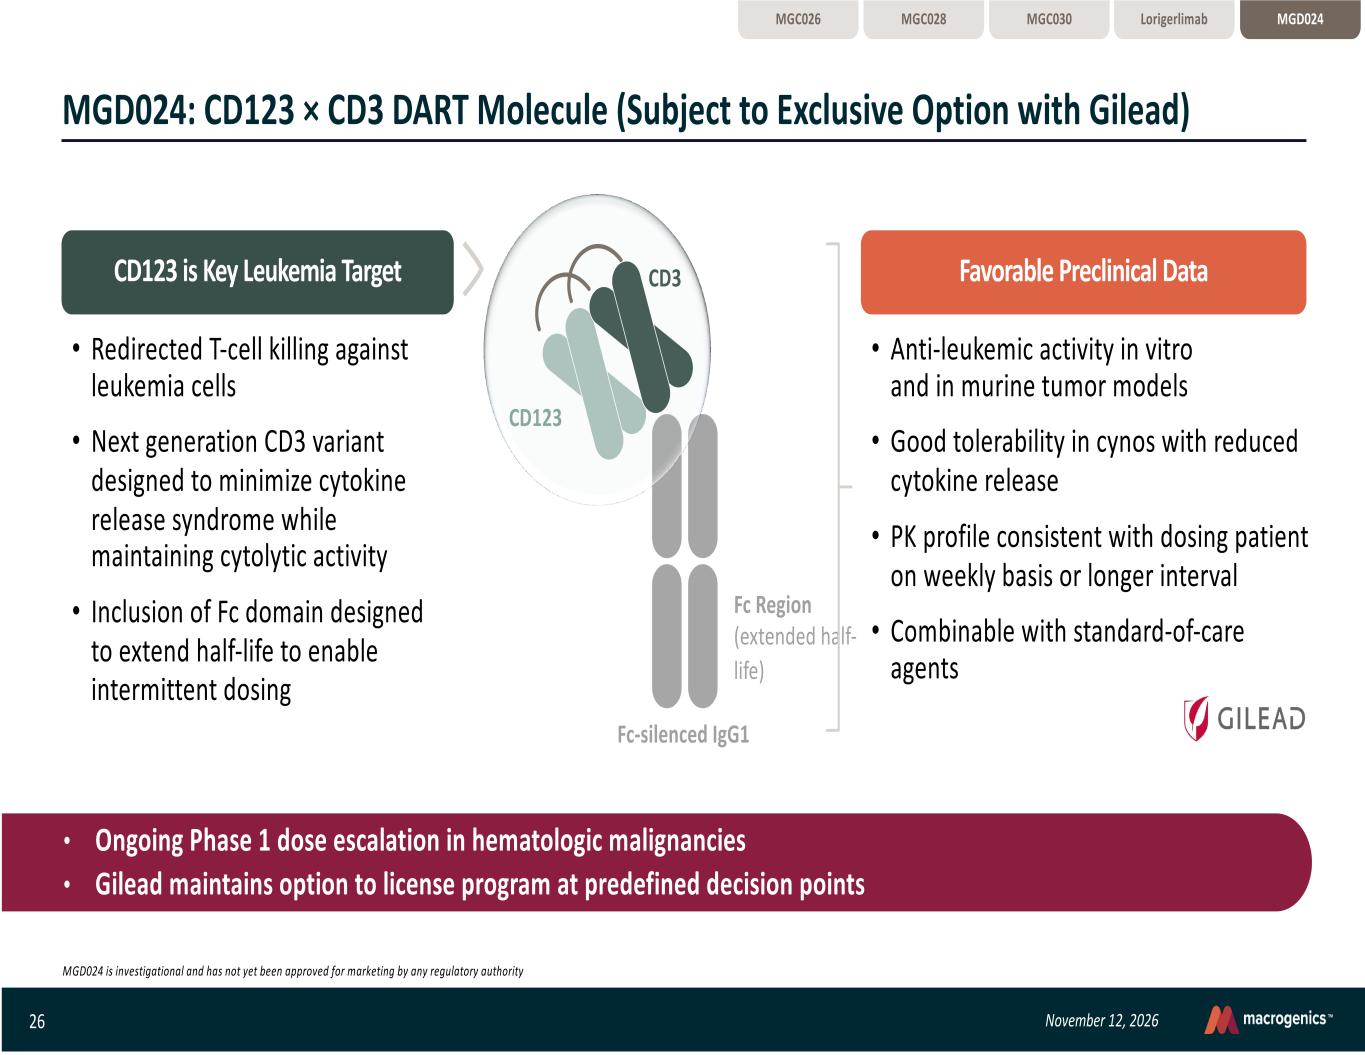
26 November 12, 2026 • Anti-leukemic activity in vitro and in murine tumor models • Good tolerability in cynos with reduced cytokine release • PK profile consistent with dosing patient on weekly basis or longer interval • Combinable with standard-of-care agents CD3 CD123 Fc-silenced IgG1 MGD024: CD123 × CD3 DART Molecule (Subject to Exclusive Option with Gilead) MGD024 is investigational and has not yet been approved for marketing by any regulatory authority Fc Region (extended half- life) CD123 is Key Leukemia Target Favorable Preclinical Data • Redirected T-cell killing against leukemia cells • Next generation CD3 variant designed to minimize cytokine release syndrome while maintaining cytolytic activity • Inclusion of Fc domain designed to extend half-life to enable intermittent dosing Lorigerlimab MGD024MGC028 MGC030MGC026 • Ongoing Phase 1 dose escalation in hematologic malignancies • Gilead maintains option to license program at predefined decision points
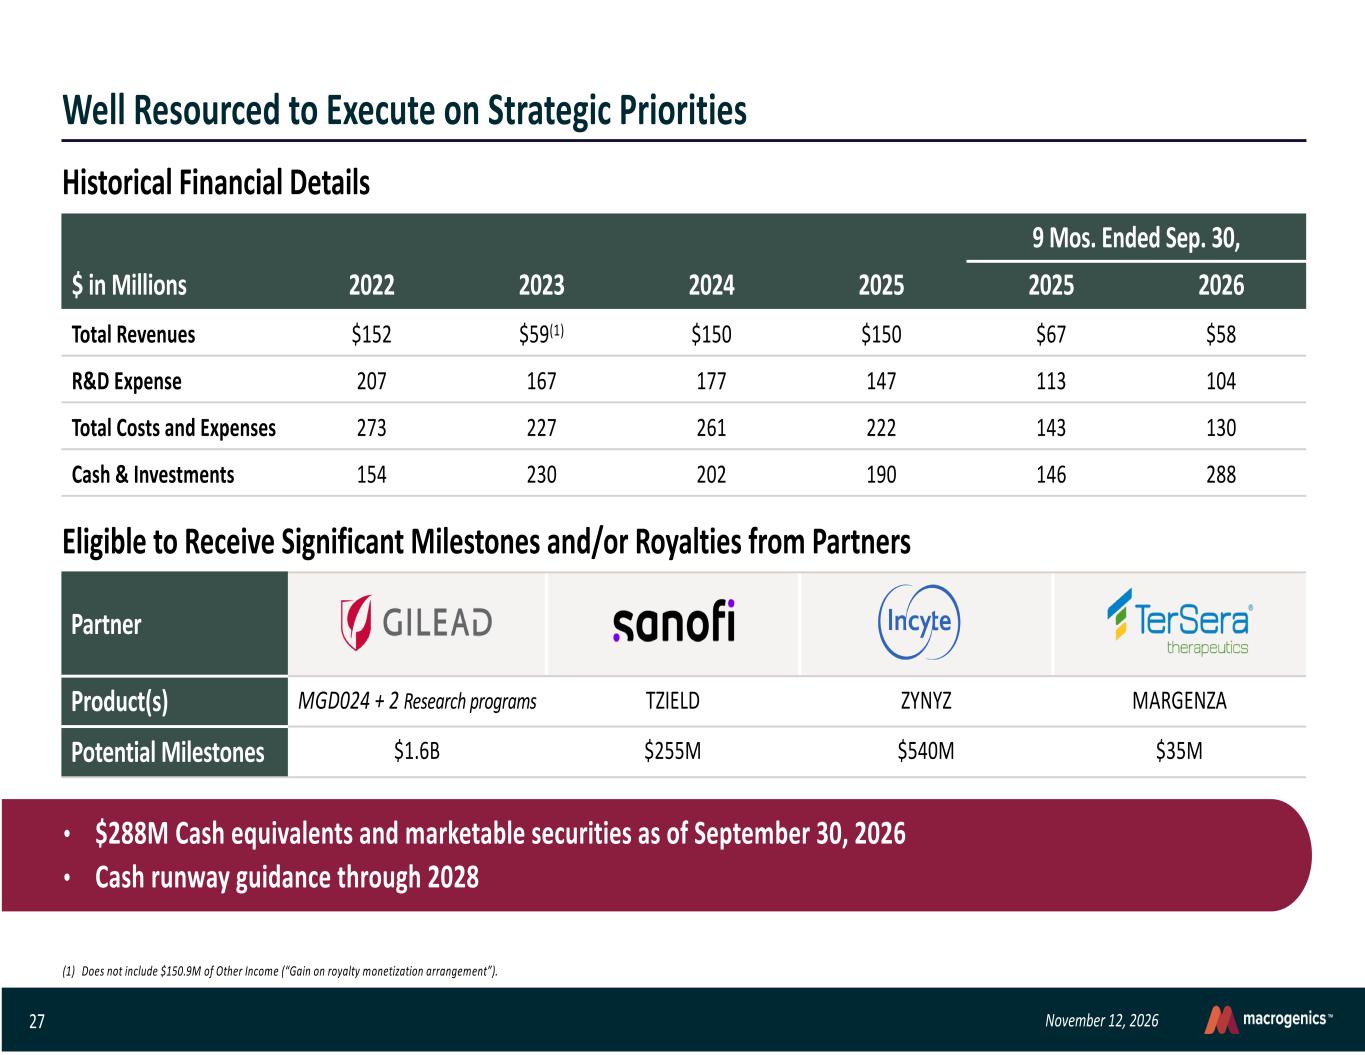
27 November 12, 2026 Well Resourced to Execute on Strategic Priorities (1) Does not include $150.9M of Other Income (“Gain on royalty monetization arrangement”). 9 Mos. Ended Sep. 30, $ in Millions 2022 2023 2024 2025 2025 2026 Total Revenues $152 $59(1) $150 $150 $67 $58 R&D Expense 207 167 177 147 113 104 Total Costs and Expenses 273 227 261 222 143 130 Cash & Investments 154 230 202 190 146 288 Partner Product(s) MGD024 + 2 Research programs TZIELD ZYNYZ MARGENZA Potential Milestones $1.6B $255M $540M $35M Eligible to Receive Significant Milestones and/or Royalties from Partners Historical Financial Details • $288M Cash equivalents and marketable securities as of September 30, 2026 • Cash runway guidance through 2028
28 November 12, 2026 Thank You! Investor Relations Inquiries Jim Karrels – SVP, Chief Financial Officer karrelsj@macrogenics.com Argot Partners macrogenics@argotpartners.com www.macrogenics.com Link to our latest presentations: http://ir.macrogenics.com/events.cfm Business Development Inquiries Harish Krishnaswamy – SVP, Business Development & Portfolio Planning krishnaswamyh@macrogenics.com