
Corporate Presentation November 2026

Disclaimer This presentation and the accompanying oral commentary have been prepared by Aquestive Therapeutics, Inc. (“Aquestive,” the “Company,” “we,” “our” or “us”) and contain “forward-looking statements” within the meaning of the Private Securities Litigation Reform Act of 1995, including statements made by management during the presentation and any question-and-answer session. Words such as “believe,” “anticipate,” “plan,” “expect,” “estimate,” “intend,” “may,” “will,” or the negative of those terms, and similar expressions, are intended to identify forward-looking statements. These forward-looking statements include, but are not limited to, statements regarding the advancement and related timing of our product candidate Anaphylm (dibutepinephrine) sublingual film through the regulatory review and approval process by the U.S. Food and Drug Administration (“FDA”); our belief that the New Drug Application (“NDA”) resubmission addresses the matters identified by the FDA in the Complete Response Letter (“CRL”) dated January 30, 2026; the FDA’s review of the accepted Class 2 resubmission of the NDA and the Prescription Drug User Fee Act (“PDUFA”) goal date of March 16, 2027; whether the FDA will determine that the resubmission adequately addresses the deficiencies identified in the CRL; the significance, interpretation and sufficiency of the human factors and pharmacokinetic study results and the pharmacokinetic and pharmacodynamic data supporting the NDA resubmission; and the potential approval of Anaphylm by the FDA, including by the PDUFA goal date, and the timing thereof. Forward-looking statements also include statements regarding the advancement and related timing of potential international regulatory filings and marketing authorizations for Anaphylm outside the United States, including the anticipated timing of submissions in Canada and the European Union; that Anaphylm will be the first and only non-invasive, orally delivered epinephrine product and may be accepted by patients, prescribers and payors as an alternative to existing standards of care, if approved by the FDA; our commercial launch strategy and launch readiness for Anaphylm, if approved by the FDA; the anticipated size and deployment of our sales force; the number and types of prescribers we intend to target; anticipated prescriber and market coverage; our patient support, affordability and product-fulfillment programs; our payer engagement and market-access strategy; and our ability to compete effectively in the market. These forward-looking statements further include statements regarding the advancement, growth and related timing of our AdrenaVerse pipeline, including AQST-108 (epinephrine) topical gel, through clinical development and the FDA regulatory approval process; the design, timing, conduct and data of clinical studies for AQST-108, including studies relating to atopic dermatitis and other potential dermatologic or immunologic indications; the mechanism of action and potential benefits of AQST-108, including its potential to reduce inflammation and itch; the ability of our PharmFilm® and AdrenaVerse technology platforms to support the development of additional product candidates and treatment indications; the timing and outcome of FDA review of Libervant® (diazepam) buccal film, including potential final approval, label expansion and commercial availability for epilepsy patients experiencing acute repetitive seizures, and the effect of the expiration of the orphan drug market exclusivity of an approved FDA product of another company; Eton Pharmaceuticals, Inc.’s (“Eton”) U.S. commercialization of Libervant; our potential receipt of contingent regulatory and sales-based milestone payments and royalties from Eton; our manufacture and supply of Libervant to Eton; the future commercial opportunities for Anaphylm, Libervant and AQST-108; potential market growth, revenues and projected peak annual sales; the size, growth and projected value of the epinephrine and atopic dermatitis markets; the potential benefits our products and product candidates may provide to patients; and business strategies, market opportunities and other statements that are not historical facts. Such forward-looking statements also include statements regarding anticipated timelines, milestones and guidance relating to regulatory submissions, clinical studies, regulatory interactions and potential approvals, all of which are inherently uncertain and subject to change based on regulatory feedback, data sufficiency and other factors outside the Company’s control. Forward-looking statements also include statements regarding our cash position, liquidity and capital resources; the availability, timing, amount and conditions of funding under our strategic funding agreement and debt facility, including funding contingent upon FDA approval of Anaphylm; our ability to satisfy applicable funding conditions and access such capital when needed; the sufficiency of available cash and financing to support planned operations, development programs and commercialization activities; the prevalence, severity, diagnosed population, actively managed population and unmet need associated with atopic dermatitis; the competitive profile, target product profile attributes, market receptivity and potential commercial positioning of AQST-108; potential expansion into additional indications; and projected market or portfolio revenues. These forward-looking statements are based on our current expectations and beliefs and are subject to risks and uncertainties that could cause actual results to differ materially from those described in the forward-looking statements. Such risks and uncertainties include, but are not limited to, the risk that the FDA may determine that the Anaphylm NDA resubmission does not adequately address the deficiencies identified in the CRL, or may otherwise delay or decline approval; the risk that the FDA may not complete its review or take action by the March 16, 2027 PDUFA goal date, including if the FDA extends the goal date or requests additional information; risks that preliminary, topline, interim or summary human factors, pharmacokinetic or pharmacodynamic results may differ from final analyses or may be interpreted differently by regulatory authorities; the possibility that the FDA may disagree with the Company’s interpretation of study results, findings or conclusions, or may request additional information, analyses, human factors studies or clinical studies; risks associated with our ability to address the FDA’s comments on and identified deficiencies in the Anaphylm NDA, including the concerns raised by the FDA in the CRL, and whether the FDA may request further information from us, including additional studies, disagree with our protocols, study designs or findings, or otherwise undertake a lengthy review of the resubmitted NDA; the risk that the FDA may consider issues raised in one or more citizen petitions or similar submissions relating to Anaphylm; risks relating to FDA inspections of manufacturing and clinical-study sites; risks associated with our development activities, including delays or changes to the timing, design, cost, conduct, data or success of our product-development programs and clinical studies for Anaphylm and AQST-108; Additional risks include the possibility that financing expected to become available upon FDA approval or other milestones may not become available when anticipated or at all; that estimates of atopic dermatitis prevalence and active management may be materially inaccurate; that claims analyses may not reflect current treatment patterns; that AQST-108 may not demonstrate the proposed mechanism, localized activity, efficacy, safety, durability or commercial differentiation suggested by early-stage observations; and that development in atopic dermatitis or any additional indication may require additional studies and may not result in regulatory approval or a commercially viable product; risks of delays in, or failure to obtain, regulatory approval of Anaphylm, Libervant or AQST-108, including final approval and label expansion for Libervant and the effect of changes in regulatory requirements or competing products’ exclusivity; risks relating to our license of Libervant to Eton, including Eton’s commercialization costs and execution, whether and when contingent milestone events are achieved (which depend on FDA actions and Eton’s commercialization efforts), the amount of any royalties (which depends on net sales), and Eton’s right to terminate the license agreement; risks related to government shutdowns, reductions in government workforce or other governmental resource constraints that may adversely affect the FDA’s ability to review or act upon regulatory submissions in a timely manner or at all; and the risk of delays in the regulatory approval process outside the United States, including the risk that foreign regulatory authorities may require different, additional or more extensive clinical, nonclinical, human factors, pharmacokinetic, manufacturing or other data than anticipated or may not accept data generated for U.S. regulatory purposes. Further risks and uncertainties include challenges associated with the potential commercial launch of Anaphylm, if approved by the FDA, including with respect to reimbursement and the manufacturing and supply of Anaphylm; risks inherent in commercializing a new product, including technology, financial, market, implementation and regulatory risks; risks associated with developing and maintaining the sales, marketing, patient-support, distribution and other capabilities necessary to commercialize our products and product candidates; the risk that our planned sales-force size and deployment, prescriber targeting, patient-support and affordability programs, payer engagement, market-access strategy and product-fulfillment arrangements may not achieve the coverage, access, adoption or financial returns we anticipate; risks relating to competition and the success of competing products, including generics; and the rate and degree of market acceptance of our products and product candidates by patients, prescribers and payors. Projected peak annual sales, market size, market growth, potential revenues, prescriber coverage and other commercial estimates may prove materially inaccurate because they are based on assumptions regarding regulatory approval, product labeling, pricing, reimbursement, competition, prescribing behavior, patient preference, market adoption and other factors, as well as internal estimates and third-party data that we have not independently verified. Survey results, market research findings and stated preferences may not predict actual prescribing, utilization, adherence, clinical outcomes or market adoption. Target product profile attributes for AQST-108 reflect our current expectations and may not be achieved in clinical development or be reflected in any approved labeling. Other risks and uncertainties include risks concerning our ability to maintain sufficient capital and cash resources, and access available debt and equity financing to satisfy our short-term and longer-term liquidity requirements and fund our business operations, key initiatives, clinical-development activities and potential commercialization activities; the possibility that assumptions underlying projected liquidity or capital sufficiency may prove incorrect; risks relating to our manufacturing capacity and supply chain; risks associated with intellectual-property rights and infringement claims; risks relating to legislation, regulatory actions and changes in laws or regulations affecting our business, including product pricing, reimbursement and market access; risks relating to claims, citizen petitions, investigations and legal proceedings; risks associated with information-technology and cybersecurity disruptions; risks relating to general economic, political, business, industry, regulatory, financial and market conditions; uncertainty regarding presidential-administration initiatives, including tariffs and trade restrictions; and the other uncertainties described in the “Risk Factors” section and other sections of the Company’s Annual Report on Form 10-K, Quarterly Reports on Form 10-Q and Current Reports on Form 8-K filed with the U.S. Securities and Exchange Commission. Given these uncertainties, you should not place undue reliance on these forward-looking statements, which speak only as of the date made. All subsequent forward-looking statements attributable to the Company or any person acting on its behalf are expressly qualified in their entirety by this cautionary statement. The Company assumes no obligation to update any forward-looking statement, outlook or guidance after the date of this presentation, whether as a result of new information, future events or otherwise, except as required by applicable law. The industry, market and competitive-position data used in this presentation are derived from the Company’s internal estimates, research and industry experience and from third-party industry publications, surveys and studies, none of which the Company has independently verified. Such data reflect assumptions and limitations, involve risks and uncertainties, are subject to change and should not be given undue weight. Libervant®, PharmFilm®, Sympazan® and the Aquestive logo are registered trademarks of Aquestive Therapeutics, Inc. All other trademarks referenced herein are the property of their respective owners. 2© 2026 Aquestive Therapeutics, Inc.

3 Who we are A publicly traded biopharmaceutical company (NASDAQ: AQST) focused on advancing medicines to bring meaningful improvement to patients' lives through innovative science.
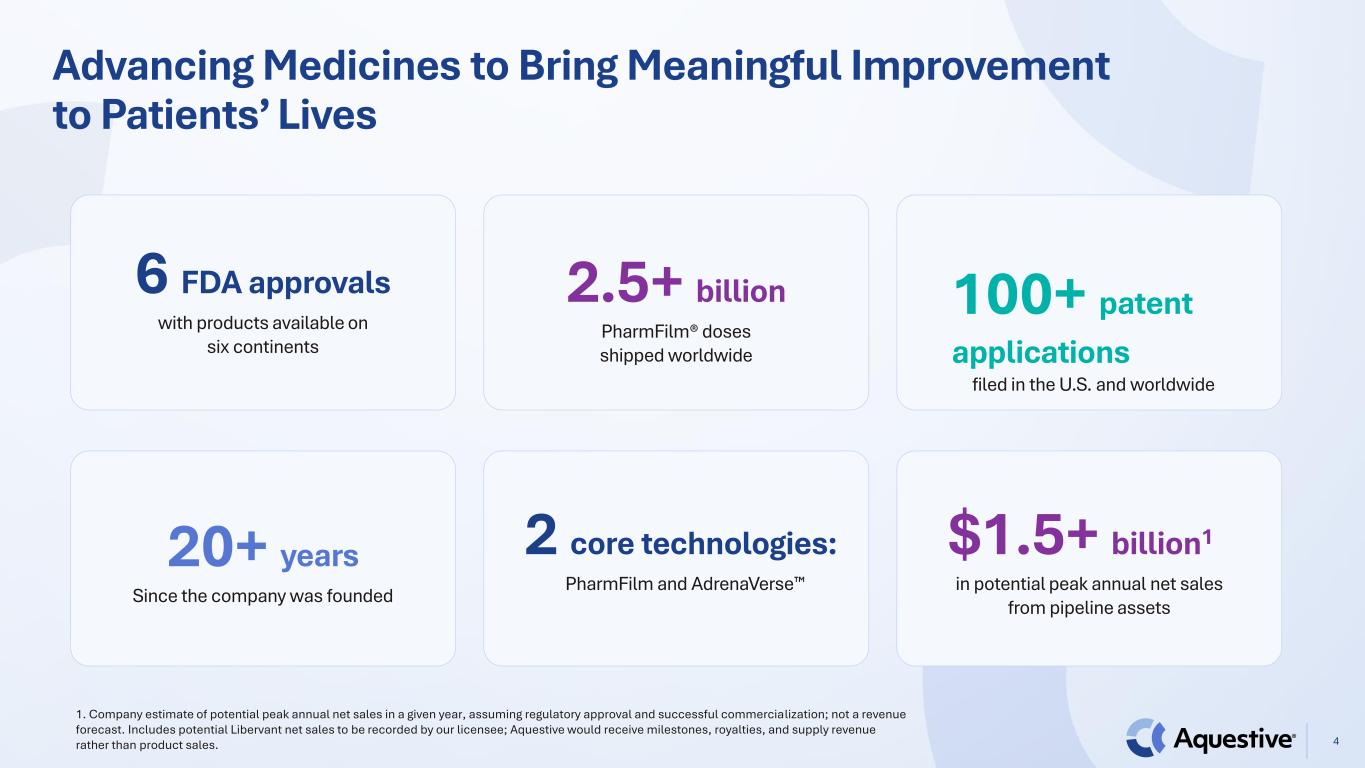
Advancing Medicines to Bring Meaningful Improvement to Patients’ Lives 4 1. Company estimate of potential peak annual net sales in a given year, assuming regulatory approval and successful commercialization; not a revenue forecast. Includes potential Libervant net sales to be recorded by our licensee; Aquestive would receive milestones, royalties, and supply revenue rather than product sales. 6 FDA approvals with products available on six continents 2.5+ billion PharmFilm® doses shipped worldwide 100+ patent applications filed in the U.S. and worldwide 20+ years Since the company was founded 2 core technologies: PharmFilm and AdrenaVerse $1.5+ billion1 in potential peak annual net sales from pipeline assets

Our Technologies PharmFilm® 5 PharmFilm® is a unique and versatile technology for high-performance drug delivery. Aquestive scientists combine the customizable features of PharmFilm® with patented formulation and engineering processes to optimize the delivery of active pharmaceutical ingredients (APIs). The AdrenaVerse platform contains a library of over 20 epinephrine prodrugs that demonstrate control of absorption and conversion rates across a variety of dosage forms including lotions, creams, and ointments (LCOs) and delivery sites. The AdrenaVerse platform enables us to pursue a variety of allergy and dermatology indications. TM

Our Products 1. Ondif collaboration with Hypera-Pharma (Brazil). 2. Sympazan collaboration with Cosette Pharmaceuticals, Inc. (worldwide). 3. Emylif collaboration with Zambon (EU). 4. Suboxone collaboration with Indivior (worldwide). 6 Aquestive is the go-to formulation development and commercial manufacturing partner for oral thin film products worldwide 4 licensed commercial products 1-4 Validation from

Diversified Pipeline Fuels Our Growth Plan 7 1. Company estimates of potential peak annual net sales and annual U.S. product sales, as applicable, in a given year, assuming regulatory approval and successful commercialization; not forecasts of revenue for any period. Actual results may differ materially. 2. Libervant is licensed to Eton Pharmaceuticals, Inc., which is responsible for U.S. commercialization. Aquestive’s economics consist of contingent milestone payments, royalties on Eton’s net sales, and supply revenue from manufacturing Libervant for Eton. Anaphylm (dibutepinephrine) sublingual film (SEVERE ALLERGIES, ANAPHYLAXIS) PDUFA goal date of March 16, 2027 >$1B1 Annual U.S. Revenue Libervant® (diazepam) buccal film (ACUTE REPETITIVE SEIZURES) >$100M2 Potential Annual U.S. Product Sales AQST-108 (epinephrine) topical gel >$500M1 Annual Revenue Proprietary Growth Drivers Preclinical Clinical Filed Marketed Illustrative Opportunity (ATOPIC DERMATITIS & other dermatology indications)

Dedicated and Experienced Leadership Team 8 Daniel Barber President, CEO & Director Matthew Greenhawt Chief Medical Officer Peter Boyd Chief People Officer Melina Cioffi SVP, Regulatory Affairs Sherry Korczynski Chief Commercial Officer Matthew Davis Chief Development Officer Ernie Toth Chief Financial Officer Thomas A. Zalewski Chief Legal Officer, Chief Compliance Officer Cassie Jung Chief Operating Officer

Cash Position Supports Anaphylm Review and Launch Preparation 9 $90.3 million in cash and cash equivalents as of September 30, 2026 Potential access to $75 million under a strategic funding agreement with RTW Investments, subject to applicable conditions including FDA approval of Anaphylm An additional $20 million potentially available under the Oaktree Capital Management debt facility, subject to applicable conditions including FDA approval of Anaphylm; no assurance either facility will become available

Lead Asset Anaphylm (dibutepinephrine) sublingual film 10 ANAPHYLM (dibutepinephrine) sublingual film is an investigational product candidate that has not been approved by the U.S. Food and Drug Administration. Safety and efficacy have not been established. Statements regarding potential benefits, clinical performance, market opportunity, commercialization plans and regulatory timing are subject to FDA review and approval.

A Novel Approach to Epinephrine Delivery Anaphylm (dibutepinephrine) sublingual film Needle-Free Easy to Use Designed to Work Quickly1 Device-Free Easy to Carry 1. Aquestive Therapeutics data on file. First and only non-device, orally delivered epinephrine product candidate 11 ANAPHYLM (dibutepinephrine) sublingual film is an investigational product candidate that has not been approved by the U.S. Food and Drug Administration. Safety and efficacy have not been established. Statements regarding potential benefits, clinical performance, market opportunity, commercialization plans and regulatory timing are subject to FDA review and approval.
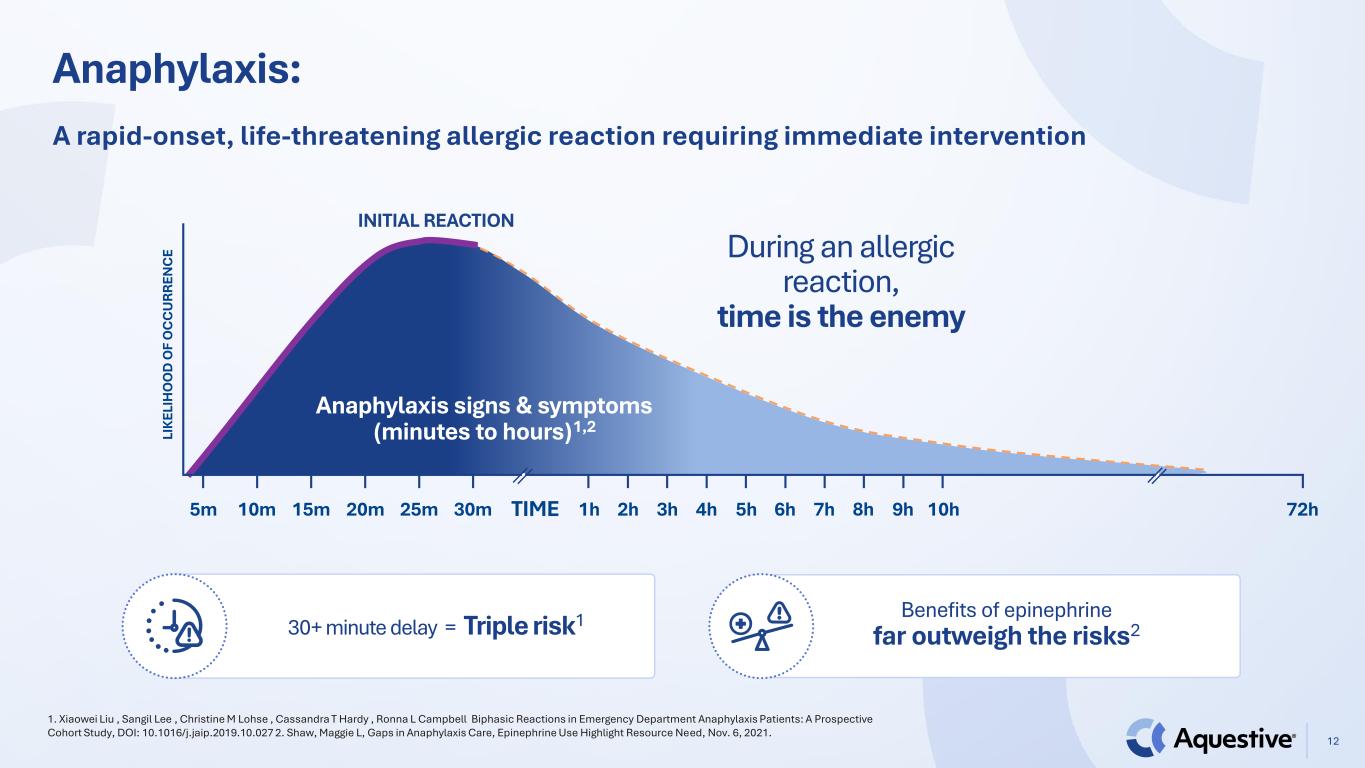
Anaphylaxis: 12 1. Xiaowei Liu , Sangil Lee , Christine M Lohse , Cassandra T Hardy , Ronna L Campbell Biphasic Reactions in Emergency Department Anaphylaxis Patients: A Prospective Cohort Study, DOI: 10.1016/j.jaip.2019.10.027 2. Shaw, Maggie L, Gaps in Anaphylaxis Care, Epinephrine Use Highlight Resource Need, Nov. 6, 2021. A rapid-onset, life-threatening allergic reaction requiring immediate intervention Anaphylaxis signs & symptoms (minutes to hours)1,2LI KE LI H O O D O F O C C U R R EN C E INITIAL REACTION 5m 10m 15m 20m 25m 30m 1h 8h 72h2h 3h 4h 5h 6h 7h 9h 10hTIME During an allergic reaction, time is the enemy 30+ minute delay = Triple risk1 Benefits of epinephrine far outweigh the risks2
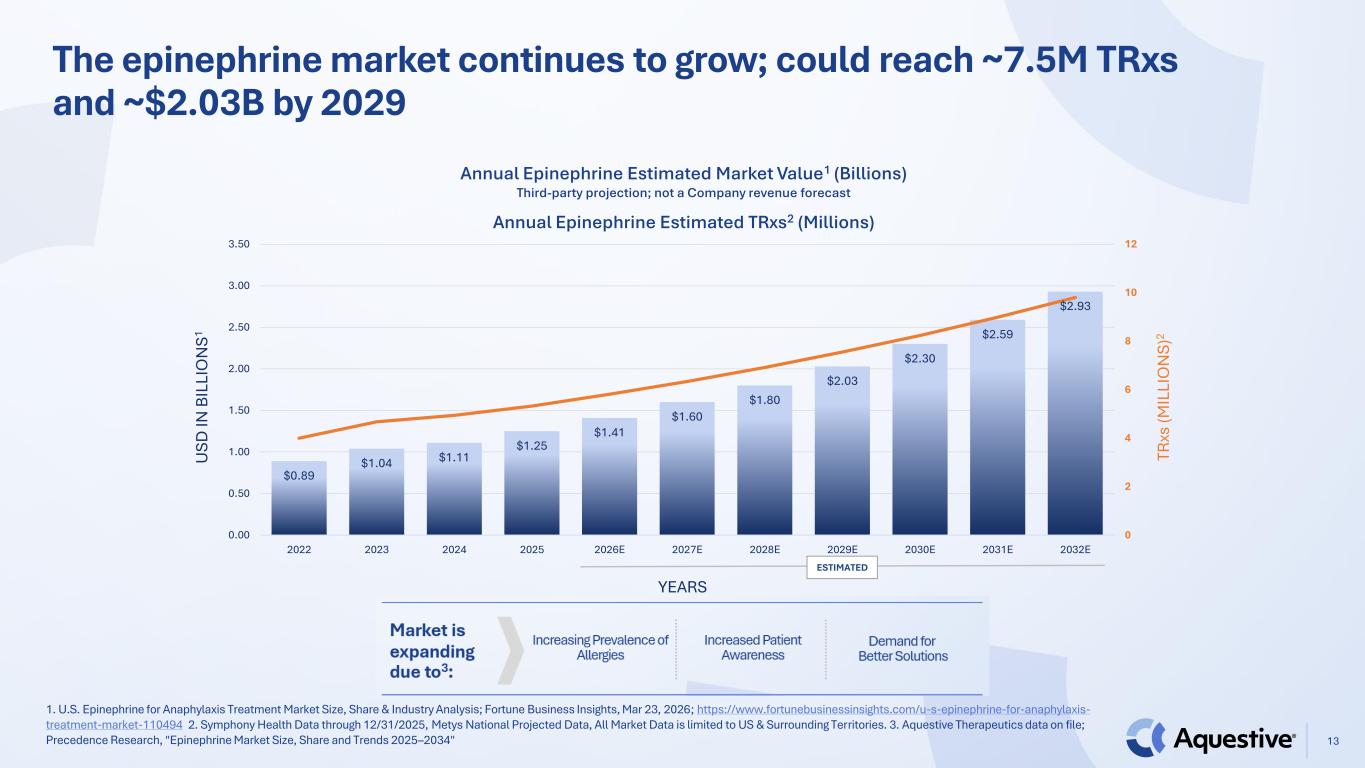
1. U.S. Epinephrine for Anaphylaxis Treatment Market Size, Share & Industry Analysis; Fortune Business Insights, Mar 23, 2026; https://www.fortunebusinessinsights.com/u-s-epinephrine-for-anaphylaxis- treatment-market-110494 2. Symphony Health Data through 12/31/2025, Metys National Projected Data, All Market Data is limited to US & Surrounding Territories. 3. Aquestive Therapeutics data on file; Precedence Research, "Epinephrine Market Size, Share and Trends 2025–2034" The epinephrine market continues to grow; could reach ~7.5M TRxs and ~$2.03B by 2029 13 $0.89 $1.04 $1.11 $1.25 $1.41 $1.60 $1.80 $2.03 $2.30 $2.59 $2.93 0 2 4 6 8 10 12 0.00 0.50 1.00 1.50 2.00 2.50 3.00 3.50 2022 2023 2024 2025 2026E 2027E 2028E 2029E 2030E 2031E 2032E Annual Epinephrine Estimated Market Value1 (Billions) Third-party projection; not a Company revenue forecast Annual Epinephrine Estimated TRxs2 (Millions) U SD IN B IL LI O N S1 YEARS TR xs (M IL LI O N S) 2 ESTIMATED
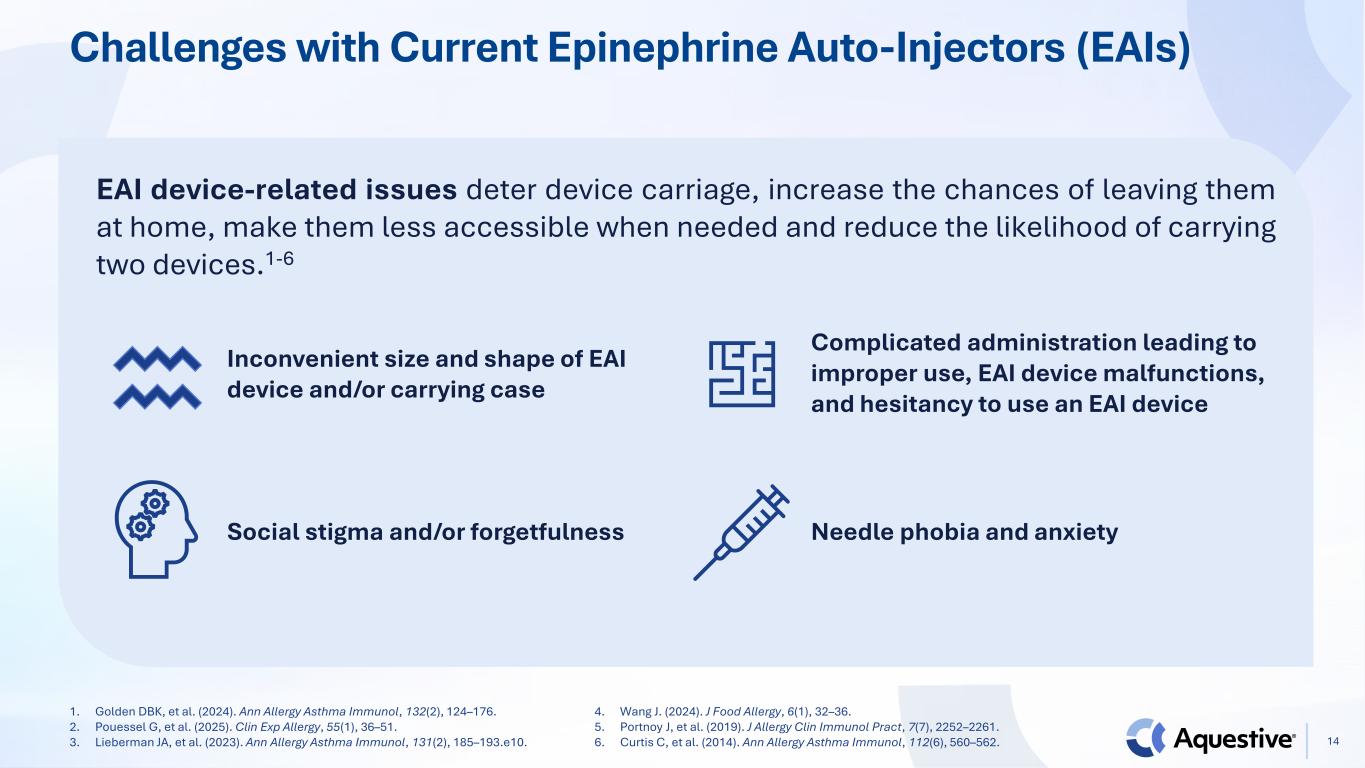
Challenges with Current Epinephrine Auto-Injectors (EAIs) 1. Golden DBK, et al. (2024). Ann Allergy Asthma Immunol, 132(2), 124–176. 2. Pouessel G, et al. (2025). Clin Exp Allergy, 55(1), 36–51. 3. Lieberman JA, et al. (2023). Ann Allergy Asthma Immunol, 131(2), 185–193.e10. 4. Wang J. (2024). J Food Allergy, 6(1), 32–36. 5. Portnoy J, et al. (2019). J Allergy Clin Immunol Pract, 7(7), 2252–2261. 6. Curtis C, et al. (2014). Ann Allergy Asthma Immunol, 112(6), 560–562. EAI device-related issues deter device carriage, increase the chances of leaving them at home, make them less accessible when needed and reduce the likelihood of carrying two devices.1-6 Inconvenient size and shape of EAI device and/or carrying case Social stigma and/or forgetfulness Complicated administration leading to improper use, EAI device malfunctions, and hesitancy to use an EAI device Needle phobia and anxiety 14
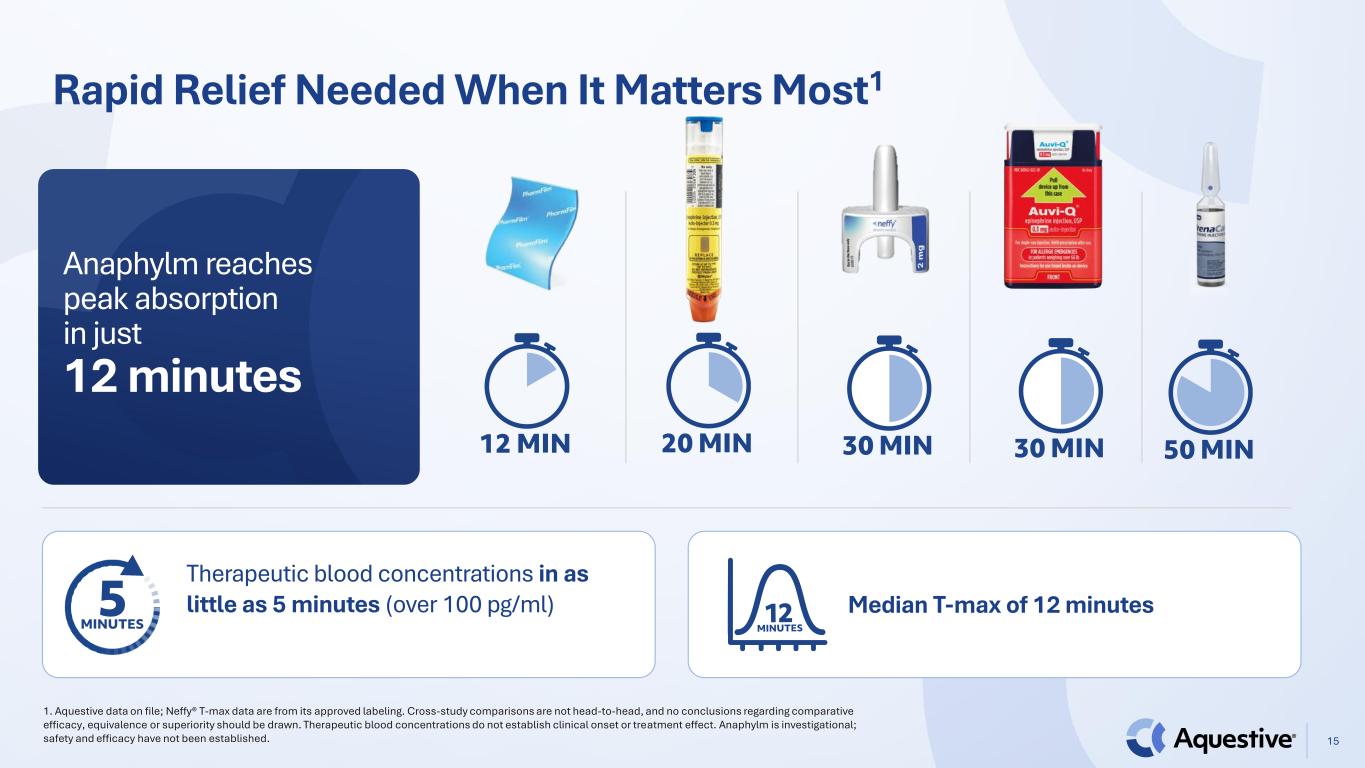
Rapid Relief Needed When It Matters Most1 1. Aquestive data on file; Neffy® T-max data are from its approved labeling. Cross-study comparisons are not head-to-head, and no conclusions regarding comparative efficacy, equivalence or superiority should be drawn. Therapeutic blood concentrations do not establish clinical onset or treatment effect. Anaphylm is investigational; safety and efficacy have not been established. 15 Therapeutic blood concentrations in as little as 5 minutes (over 100 pg/ml) Median T-max of 12 minutes Anaphylm reaches peak absorption in just 12 minutes
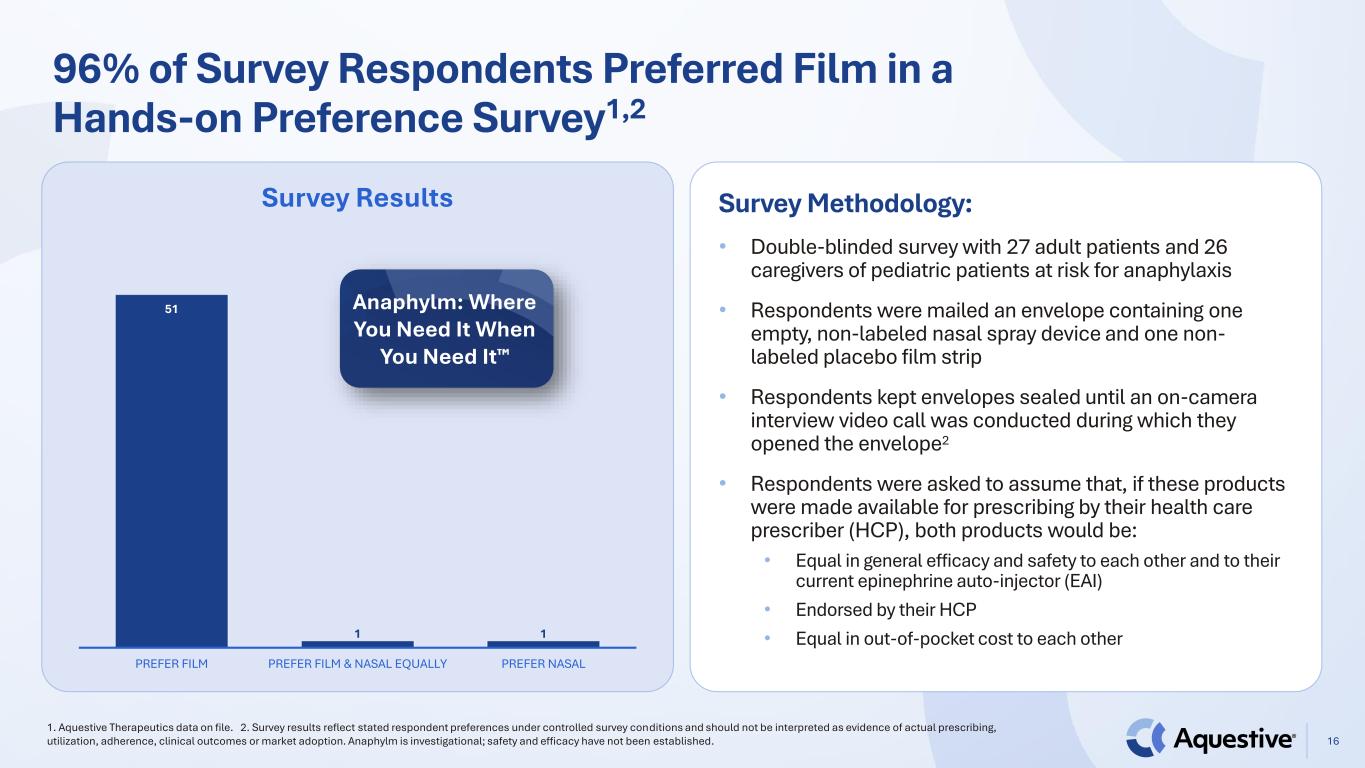
96% of Survey Respondents Preferred Film in a Hands-on Preference Survey1,2 51 1 1 PREFER FILM PREFER FILM & NASAL EQUALLY PREFER NASAL Survey Results 1. Aquestive Therapeutics data on file. 2. Survey results reflect stated respondent preferences under controlled survey conditions and should not be interpreted as evidence of actual prescribing, utilization, adherence, clinical outcomes or market adoption. Anaphylm is investigational; safety and efficacy have not been established. 16 Survey Methodology: • Double-blinded survey with 27 adult patients and 26 caregivers of pediatric patients at risk for anaphylaxis • Respondents were mailed an envelope containing one empty, non-labeled nasal spray device and one non- labeled placebo film strip • Respondents kept envelopes sealed until an on-camera interview video call was conducted during which they opened the envelope2 • Respondents were asked to assume that, if these products were made available for prescribing by their health care prescriber (HCP), both products would be: • Equal in general efficacy and safety to each other and to their current epinephrine auto-injector (EAI) • Endorsed by their HCP • Equal in out-of-pocket cost to each other Anaphylm: Where You Need It When You Need It
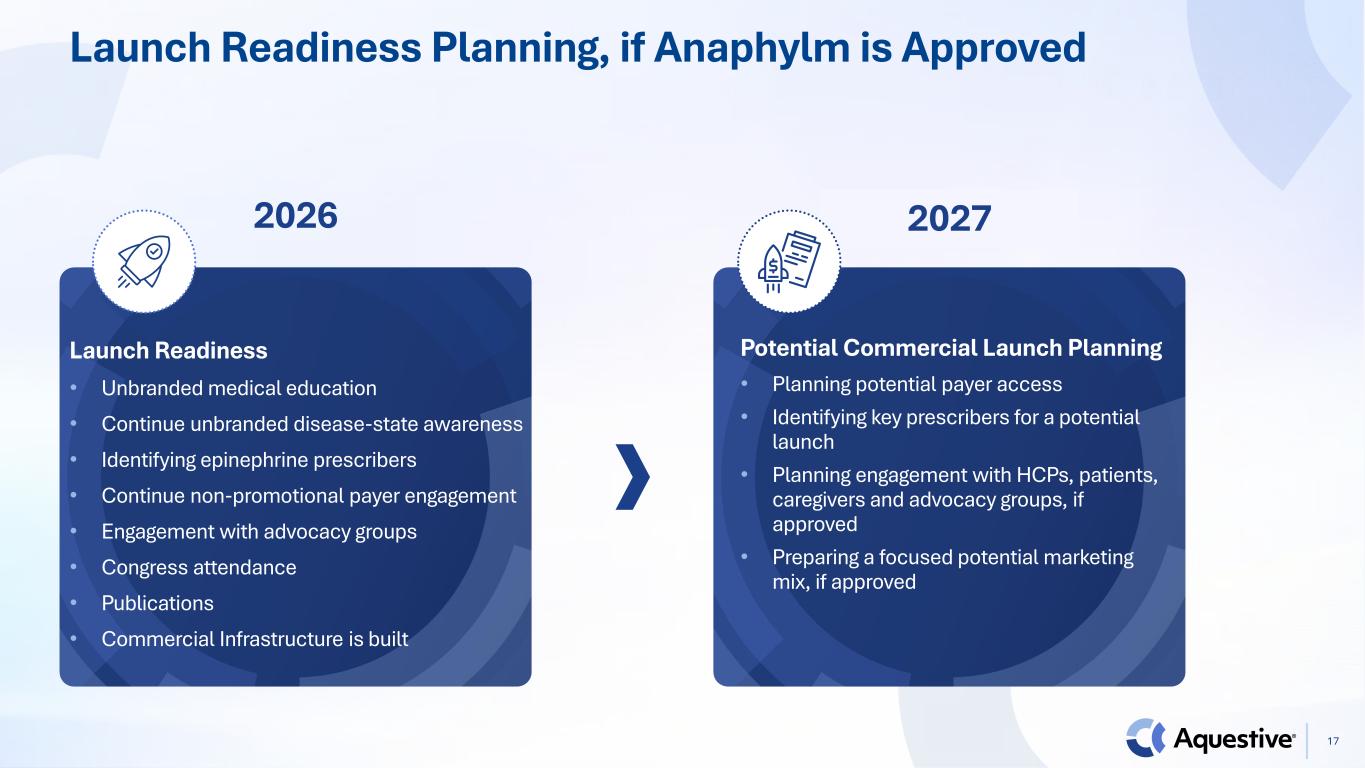
Launch Readiness Planning, if Anaphylm is Approved 2026 2027 Potential Commercial Launch Planning • Planning potential payer access • Identifying key prescribers for a potential launch • Planning engagement with HCPs, patients, caregivers and advocacy groups, if approved • Preparing a focused potential marketing mix, if approved Launch Readiness • Unbranded medical education • Continue unbranded disease-state awareness • Identifying epinephrine prescribers • Continue non-promotional payer engagement • Engagement with advocacy groups • Congress attendance • Publications • Commercial Infrastructure is built 17

Anaphylm Regulatory Milestones 18 Q1 2027Q4 2026Q3 2026Q2 2026Q1 2026 NDA Resubmitted Targeted Ex-U.S. filing in Canada PDUFA Goal Date March 16, 2027 • Anaphylm advances toward a March 16, 2027, PDUFA goal date following FDA acceptance of the NDA resubmission. • Ex-U.S. filings are targeted for Canada by year-end 2026 and the E.U. in Q1 2027; timing remains subject to regulatory requirements and change FDA Complete Response Letter Targeted Ex-U.S. filing in European Union

AQST-108 (epinephrine) Topical Gel 19
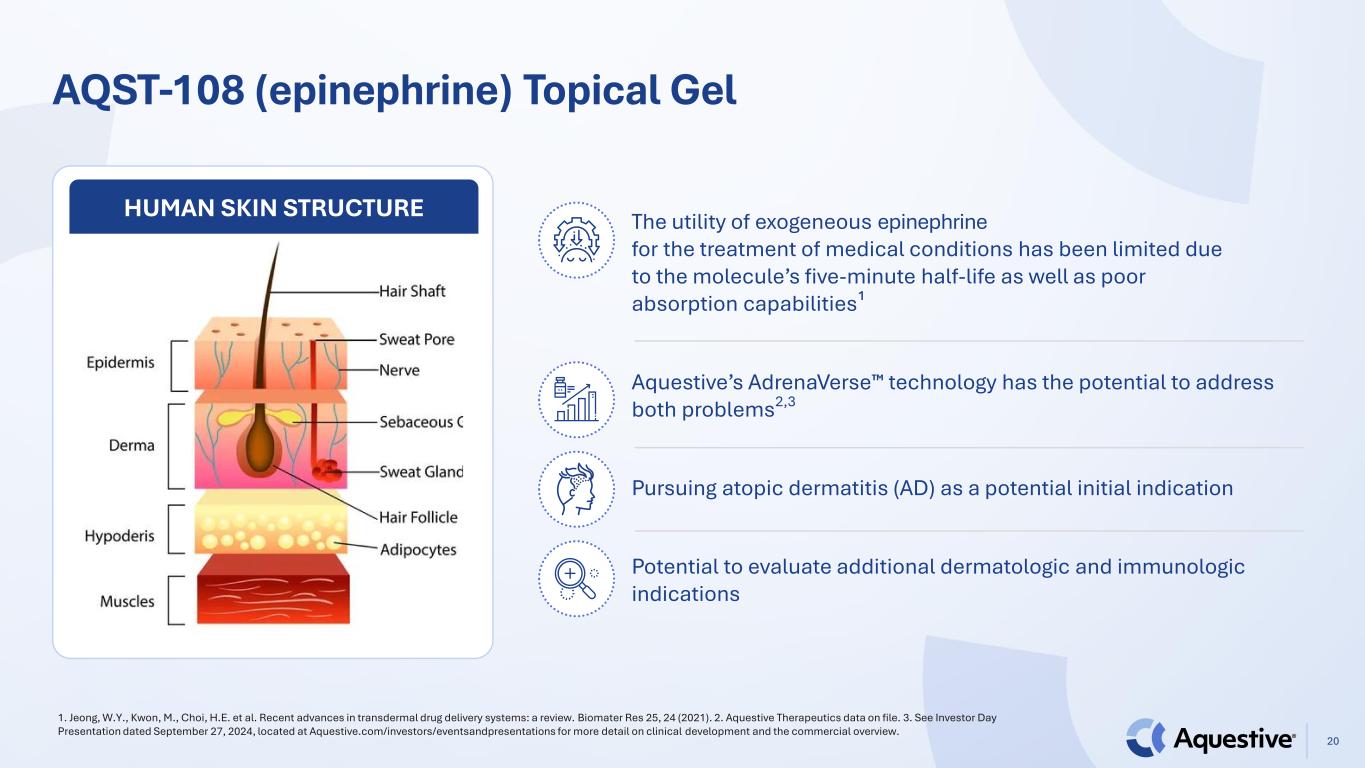
AQST-108 (epinephrine) Topical Gel 1. Jeong, W.Y., Kwon, M., Choi, H.E. et al. Recent advances in transdermal drug delivery systems: a review. Biomater Res 25, 24 (2021). 2. Aquestive Therapeutics data on file. 3. See Investor Day Presentation dated September 27, 2024, located at Aquestive.com/investors/eventsandpresentations for more detail on clinical development and the commercial overview. 20 The utility of exogeneous epinephrine for the treatment of medical conditions has been limited due to the molecule’s five-minute half-life as well as poor absorption capabilities¹ Aquestive’s AdrenaVerse technology has the potential to address both problems2,3 Pursuing atopic dermatitis (AD) as a potential initial indication Potential to evaluate additional dermatologic and immunologic indications HUMAN SKIN STRUCTURE
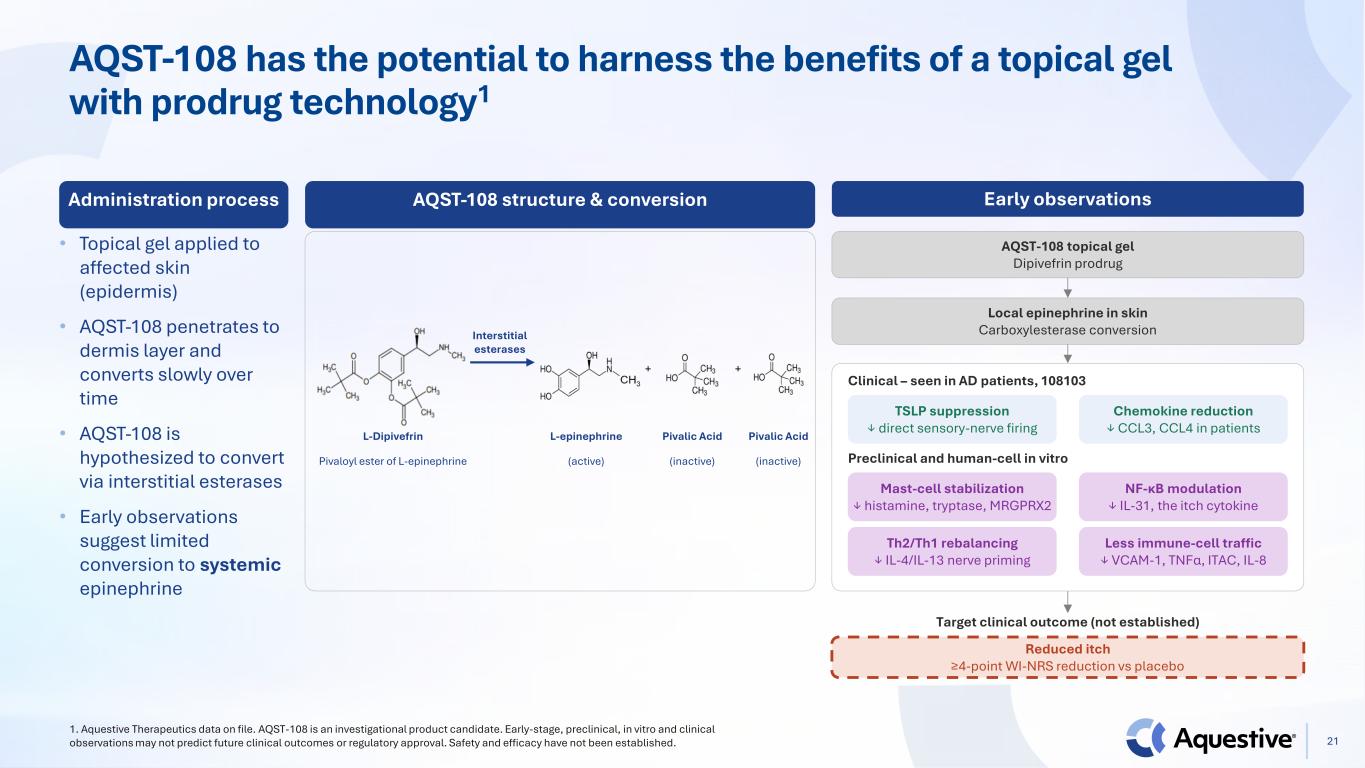
AQST-108 has the potential to harness the benefits of a topical gel with prodrug technology1 Administration process • Topical gel applied to affected skin (epidermis) • AQST-108 penetrates to dermis layer and converts slowly over time • AQST-108 is hypothesized to convert via interstitial esterases • Early observations suggest limited conversion to systemic epinephrine Early observations AQST-108 topical gel Dipivefrin prodrug Local epinephrine in skin Carboxylesterase conversion Clinical – seen in AD patients, 108103 TSLP suppression ↓ direct sensory-nerve firing Chemokine reduction ↓ CCL3, CCL4 in patients Preclinical and human-cell in vitro Mast-cell stabilization ↓ histamine, tryptase, MRGPRX2 NF-κB modulation ↓ IL-31, the itch cytokine Th2/Th1 rebalancing ↓ IL-4/IL-13 nerve priming Less immune-cell traffic ↓ VCAM-1, TNFα, ITAC, IL-8 Target clinical outcome (not established) Reduced itch ≥4-point WI-NRS reduction vs placebo AQST-108 structure & conversion L-Dipivefrin Pivaloyl ester of L-epinephrine L-epinephrine (active) Pivalic Acid (inactive) Pivalic Acid (inactive) Interstitial esterases 1. Aquestive Therapeutics data on file. AQST-108 is an investigational product candidate. Early-stage, preclinical, in vitro and clinical observations may not predict future clinical outcomes or regulatory approval. Safety and efficacy have not been established. 21
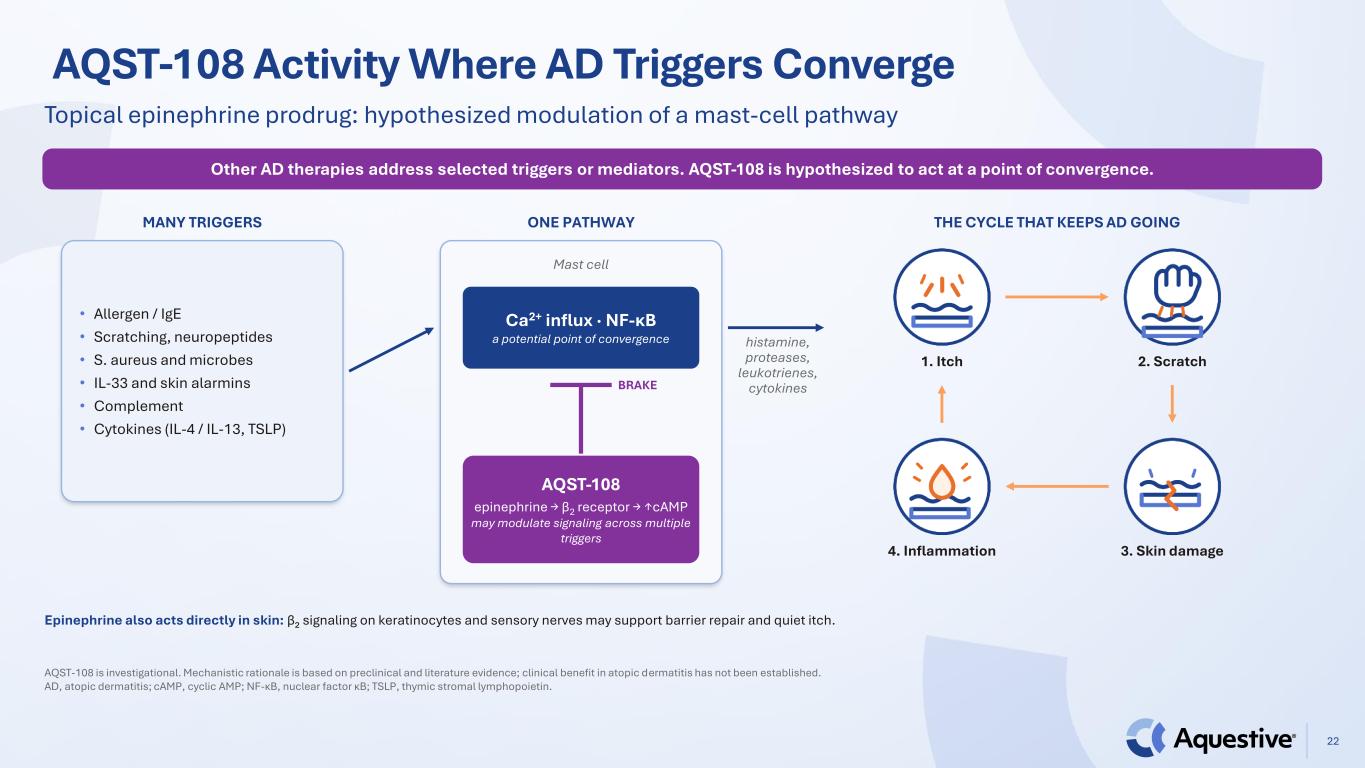
AQST-108 Activity Where AD Triggers Converge Topical epinephrine prodrug: hypothesized modulation of a mast-cell pathway Other AD therapies address selected triggers or mediators. AQST-108 is hypothesized to act at a point of convergence. MANY TRIGGERS • Allergen / IgE • Scratching, neuropeptides • S. aureus and microbes • IL-33 and skin alarmins • Complement • Cytokines (IL-4 / IL-13, TSLP) ONE PATHWAY Mast cell Ca2+ influx · NF-κB a potential point of convergence AQST-108 epinephrine → β2 receptor → ↑cAMP may modulate signaling across multiple triggers BRAKE THE CYCLE THAT KEEPS AD GOING histamine, proteases, leukotrienes, cytokines 1. Itch 2. Scratch 3. Skin damage4. Inflammation Epinephrine also acts directly in skin: β₂ signaling on keratinocytes and sensory nerves may support barrier repair and quiet itch. AQST-108 is investigational. Mechanistic rationale is based on preclinical and literature evidence; clinical benefit in atopic dermatitis has not been established. AD, atopic dermatitis; cAMP, cyclic AMP; NF-κB, nuclear factor κB; TSLP, thymic stromal lymphopoietin. 22

Atopic Dermatitis (AD) Treatment Landscape 23
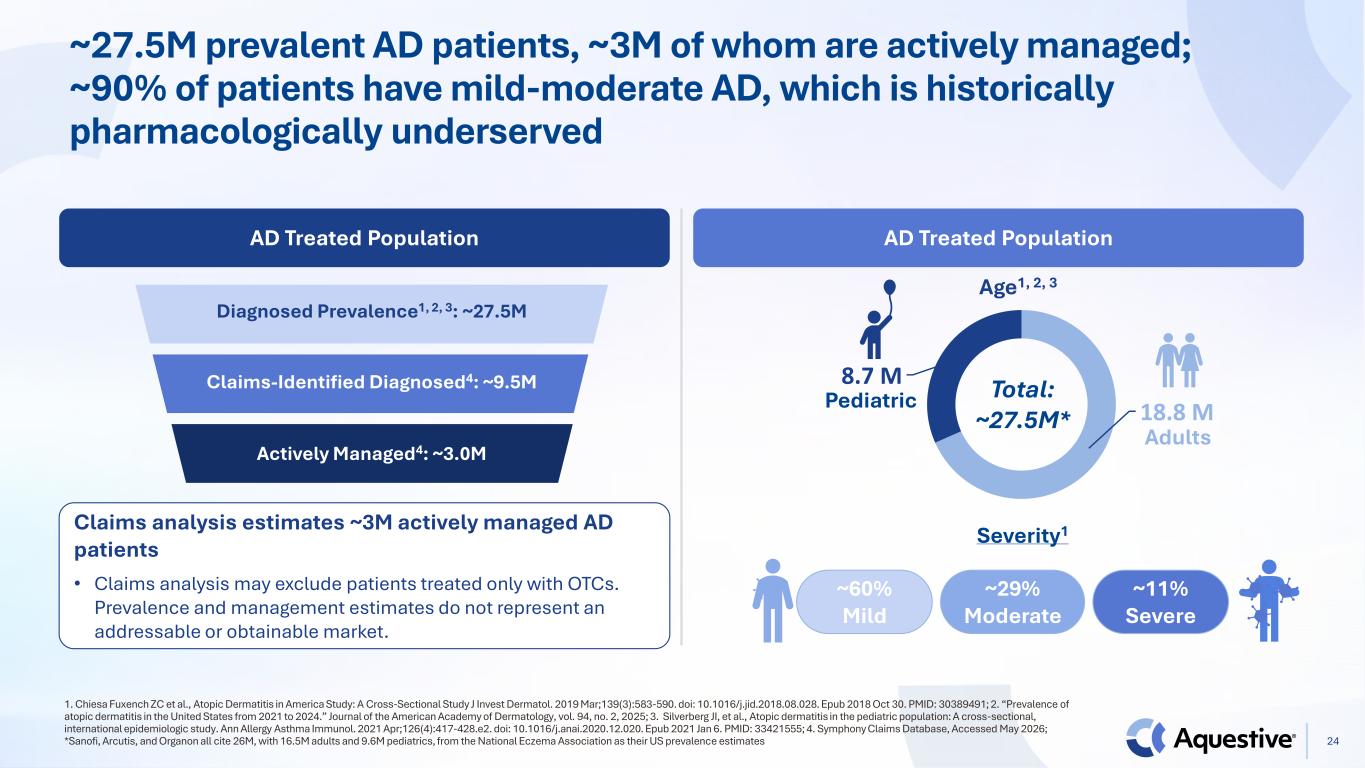
~27.5M prevalent AD patients, ~3M of whom are actively managed; ~90% of patients have mild-moderate AD, which is historically pharmacologically underserved 1. Chiesa Fuxench ZC et al., Atopic Dermatitis in America Study: A Cross-Sectional Study J Invest Dermatol. 2019 Mar;139(3):583-590. doi: 10.1016/j.jid.2018.08.028. Epub 2018 Oct 30. PMID: 30389491; 2. “Prevalence of atopic dermatitis in the United States from 2021 to 2024.” Journal of the American Academy of Dermatology, vol. 94, no. 2, 2025; 3. Silverberg JI, et al., Atopic dermatitis in the pediatric population: A cross-sectional, international epidemiologic study. Ann Allergy Asthma Immunol. 2021 Apr;126(4):417-428.e2. doi: 10.1016/j.anai.2020.12.020. Epub 2021 Jan 6. PMID: 33421555; 4. Symphony Claims Database, Accessed May 2026; *Sanofi, Arcutis, and Organon all cite 26M, with 16.5M adults and 9.6M pediatrics, from the National Eczema Association as their US prevalence estimates AD Treated Population AD Treated Population Claims analysis estimates ~3M actively managed AD patients • Claims analysis may exclude patients treated only with OTCs. Prevalence and management estimates do not represent an addressable or obtainable market. 18.8 M 8.7 M Pediatric Adults Total: ~27.5M* Age1, 2, 3 Severity1 Diagnosed Prevalence1, 2, 3: ~27.5M Claims-Identified Diagnosed4: ~9.5M Actively Managed4: ~3.0M ~60% Mild ~29% Moderate ~11% Severe 24
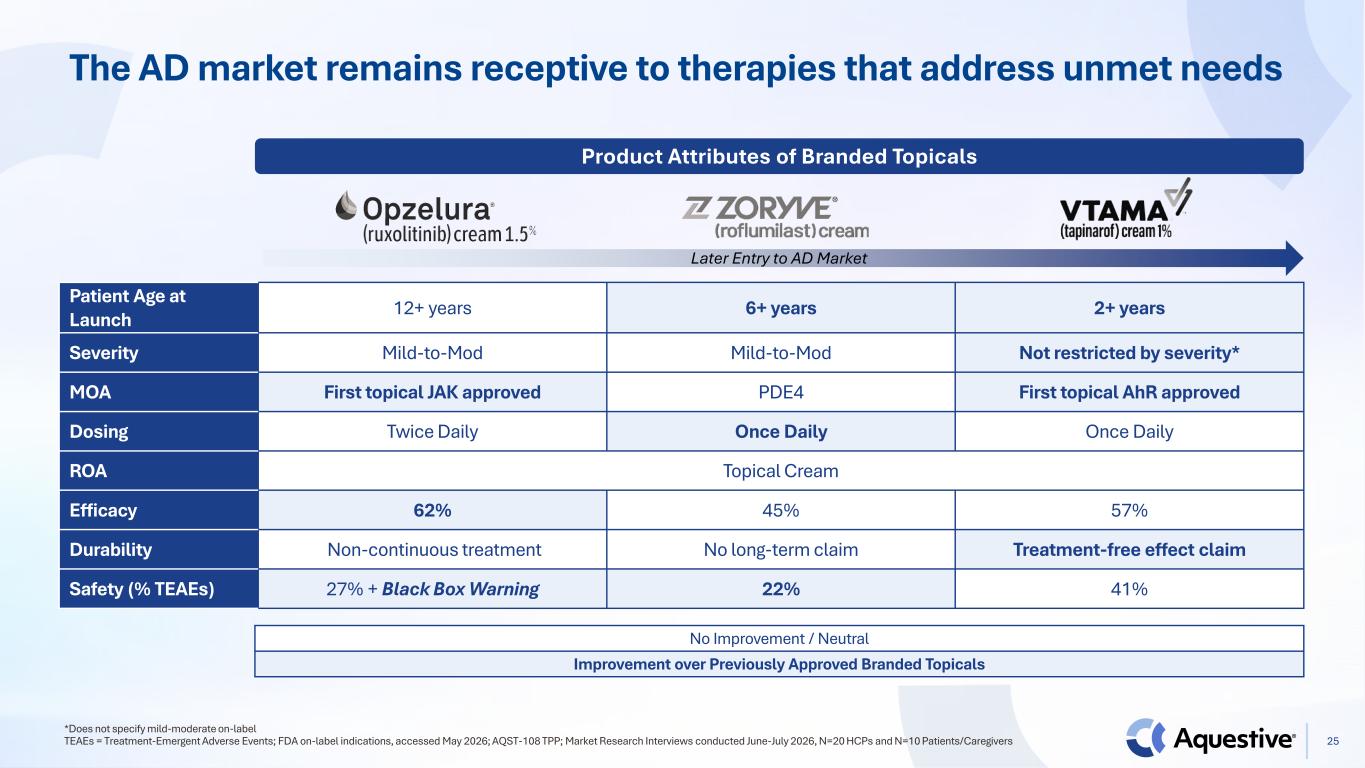
The AD market remains receptive to therapies that address unmet needs *Does not specify mild-moderate on-label TEAEs = Treatment-Emergent Adverse Events; FDA on-label indications, accessed May 2026; AQST-108 TPP; Market Research Interviews conducted June-July 2026, N=20 HCPs and N=10 Patients/Caregivers Patient Age at Launch 12+ years 6+ years 2+ years Severity Mild-to-Mod Mild-to-Mod Not restricted by severity* MOA First topical JAK approved PDE4 First topical AhR approved Dosing Twice Daily Once Daily Once Daily ROA Topical Cream Efficacy 62% 45% 57% Durability Non-continuous treatment No long-term claim Treatment-free effect claim Safety (% TEAEs) 27% + Black Box Warning 22% 41% Later Entry to AD Market Product Attributes of Branded Topicals No Improvement / Neutral Improvement over Previously Approved Branded Topicals 25
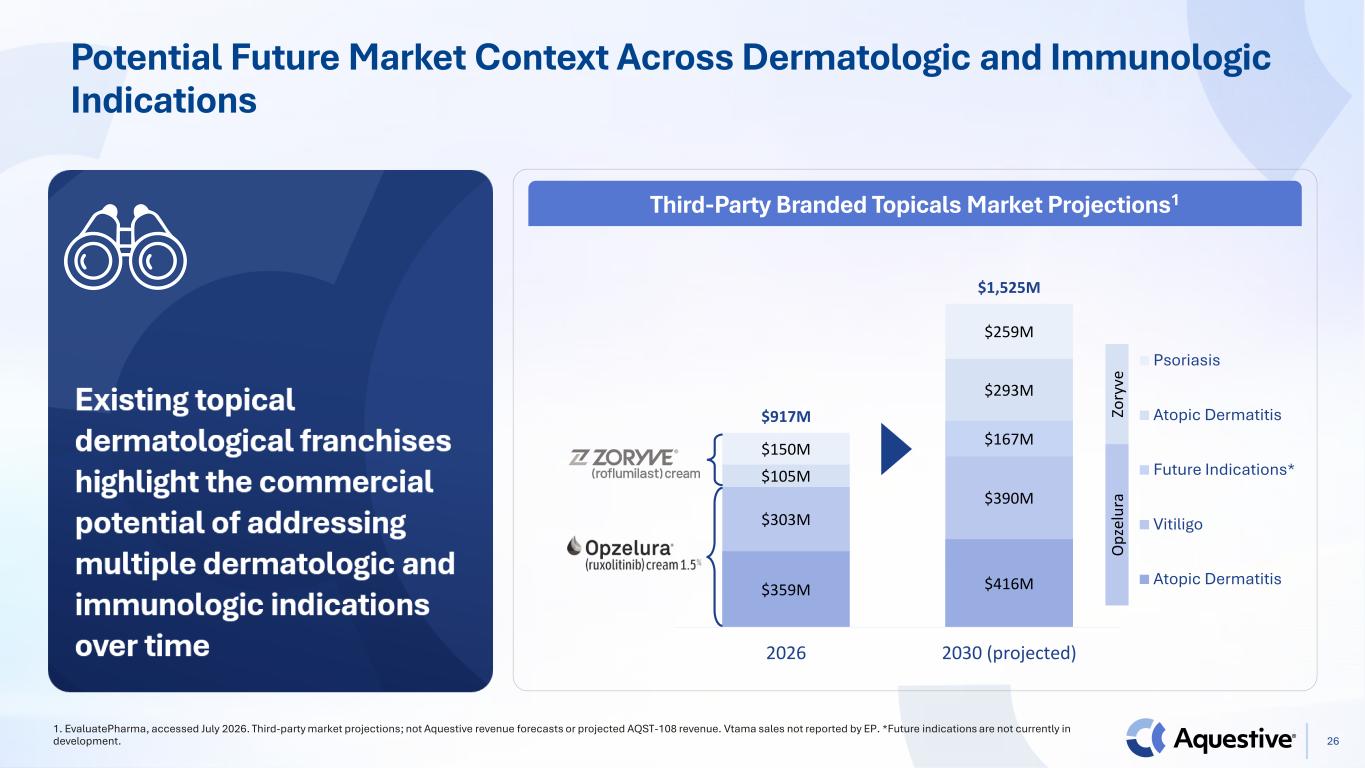
Potential Future Market Context Across Dermatologic and Immunologic Indications 1. EvaluatePharma, accessed July 2026. Third-party market projections; not Aquestive revenue forecasts or projected AQST-108 revenue. Vtama sales not reported by EP. *Future indications are not currently in development. $359M $416M $303M $390M $167M $105M $293M $150M $259M $917M $1,525M 2026 2030 (projected) Psoriasis Atopic Dermatitis Future Indications* Vitiligo Atopic Dermatitis O p ze lu ra Zo ry ve Third-Party Branded Topicals Market Projections1 26

27 Thank You