
Exhibit 99.1
Delivering Novel Therapies for RAS/MAPK Pathway - Driven Cancers CORPORATE PRESENTATION NOVEMBER 2026

2 FORWARD - LOOKING STATEMENTS This presentation includes forward - looking statements about, among other things, Verastem Oncology’s (the “Company”) programs an d product candidates, strategy, future plans and prospects, including statements related to the approval and commercialization of AVMAPKI® FAKZYNJA® CO - PACK ( avutometinib capsules; defactinib tablets) as a treatment for adult patients with Kirsten rat sarcoma viral oncogene homolog (KRAS) mutant - type (mt) recurrent Lo w - Grade Serous Ovarian Cancer (LGSOC), the expected outcome and benefits of collaborations, including with GenFleet Therapeutics (Shanghai), Inc. ( GenFleet ), including the conduct of a Phase 1/2a study and subsequent studies with respect to VS - 7375, the potential of the results of the RAMP 301 Phase 3 trial to confirm the results of the RAMP 201 study specific to KRAS mutant recurrent LGSOC patients and to expand the indication for AVMAPKI FAKZYNJA CO - PACK as a treatment for LGSOC regardless of KRAS mutation status, the structure and potential clinical value of our completed, planned and pending clinical trials, including the RAMP 201, RAM P 2 01J, RAMP 205, RAMP 301, TARGET - D 101, TARGET - D 201, TARGET - D 202, TARGET – D 203, and TARGET - D 301 trials, the timing of commencing and completing trials, including topline data reports, the Company’s proforma cash position, our interactio ns with regulators, the timeline and indications for clinical development, regulatory submissions and the potential for and timing of commercialization of our product candidates and potential for additional development programs involving the Company ’s lead compound and the potential market opportunities thereof; and the estimated addressable markets for, and anticipated market opportunities of our drug candidates. The words "anticipate," "believe," "estimate," "expect," "may," "pla n," "target," "potential," "would," "could," "should," "continue," “can” and similar expressions are intended to identify forward - looking statements, although not all forward - looking statements contain these identifying words. Each forward - looking statement is subject to risks and uncertainties that could cause actual results to differ materially from those expressed or implied in such statement. Each forward - looking statements is subject to a number of risks and uncertainties that could cause actual results to differ mate rially from those expressed or implied in such statement. These include, but are not limited to: the assumptions underlying the forward - looking statements; risks related to the development and successful commercialization of our product candidates; obtaini ng and maintaining regulatory approvals, including, but not limited to, potential regulatory delays or rejections; the challenges with the commercialization of a new product; our history of operating losses and the possibility that we may never ac hieve or maintain profitability; risks associated with meeting the objectives of the Company's clinical trials, including, bu t n ot limited to Verastem's ability to achieve enrollment objectives concerning patient numbers (including an adequate safety datab ase ), outcomes objectives and/or timing objectives for Company's trials; any delays or failures in enrollment and the occurrence of adverse safety events; our ability to successfully commercialize AVMAPKI FAKZYNJA CO - PACK in the U.S. including ou r ability to generate market demand for and acceptance of AVMAPKI FAKZYNJA CO - PACK; the potential inability to raise sufficient capital to fund ongoing operations as currently planned or to obtain financing on acceptable terms or to fun d o perations from revenues generated by the sales of AVMAPKI FAKZYNJA CO - PACK; actions or advice of regulatory agencies to maintain regulatory approval of AVMAPKI FAKZYNJA CO - PACK; the impact of current and future healthcare reforms, including those a ffecting the delivery of or payment for healthcare products and services; uncertainties related to the activities and initiatives of the current U.S. presidential administration, including regulatory and policy changes that may adversely affec t o ur business; risks related to our ability to obtain, maintain and enforce patent and other intellectual property protection for our product candidates; decisions by regulatory authorities regarding trial design, labeling and other matters that could affect the timing, availability or commercial potential of our product candidates; whether preclinical testing of our product candidates and preliminary or interim data from clinical trials will be predictive of the results or success of ongoing or later clinica l t rials; that the timing, scope and rate of reimbursement for our product candidates is uncertain; that the market opportunitie s o f our drug candidates are based on internal and third - party estimates which may prove to be incorrect; that third - party payors (includ ing government agencies) may not reimburse; that there may be competitive developments affecting our product candidates; that data may not be available when expected; that enrollment of clinical trials may take longer than expected; the risks tha t w e will not satisfy our post - marketing requirements and commitments established and agreed to as part of the FDA's approval of AVMAPKI FAKZYNJA CO - PACK; that our marketed product candidates may cause adverse safety events and/or unexpected concerns may ar ise from additional data or analysis, or result in unmanageable safety profiles as compared to their levels of efficacy; that we may not be able to confirm the results from the RAMP 201 study or expand the approved indication for AVMAPK I F AKZYNJA CO - PACK; that our product candidates may experience manufacturing or supply interruptions or failures; that any of our third - party contract research organizations, contract manufacturing organizations, clinical sites, or contractors, am ong others, who we rely on may fail to fully perform; that we face substantial competition, which may result in others develo pin g or commercializing products before or more successfully than we do which could result in reduced market share or market poten tia l for our product candidates; that we may be unable to successfully initiate or complete the clinical development and eventual commercialization of our product candidates; that the development and commercialization of our product candidates ma y t ake longer or cost more than planned, including as a result of conducting additional studies or our decisions regarding execution of such commercialization; that we may not attract and retain high quality personnel; that we or Pfizer, Inc. may f ail to fully perform under the license agreement covering certain Pfizer FAK inhibitors, including defactinib ; that we or Chu gai Pharma ceutical Co., Ltd. may fail to fully perform under the avutometinib license agree ment; that w e or GenFleet may fail to fully perform under the collaboration and option agreement covering VS - 7375 and other assets we may decide to option in; that our total addressable and target markets for our product candidates might be smaller than we are presently estimating; that w e o r Secura Bio, Inc. may fail to fully perform under the asset purchase agreement with Secura Bio, Inc., including in relation to milestone payments; that we may not be able to establish new or expand on existing collaborations or partnerships, including wit h respect to in - licensing of our product candidates, on favorable terms, or at all; that we may be unable to obtain adequate financing in the future through product licensing, co - promotional arrangements, public or private equity, debt financing or othe rwise; that we may not pursue or submit regulatory filings for our product candidates; that, due to the current presidential administration's significant reduction in the FDA's workforce and potential reductions to the FDA's budget, we may experience a material impact to the FDA's ability to engage in a variety of activities that may affect our business, including routine regulatory and oversight activities; and that our product candidates may not receive regulatory approval, become commercially su ccessful products, or result in new treatment options being offered to patients. Other risks and uncertainties include those identified under the heading “Risk Factors” in the Company’s Annual Report on For m 1 0 - K for the year ended December 31, 2025, as filed with the Securities and Exchange Commission (SEC) on March 04, 2026, and in any subsequent filings with the SEC, which are available at www.sec.gov and www.verastem.com . The forward - looking statements in this presentation speak only as of the original date of this presentation, and we undertake no obligation to update or revise any of these statements whether as a result of new information, future events or otherwise, except as requir ed by law. Our business is subject to substantial risks and uncertainties, including those referenced above. Investors, potentia l investors, and others should give careful consideration to these risks and uncertainties. USE OF NON - GAAP FINANCIAL MEASURES This presentation contains references to our non - GAAP operating expense, a financial measure that is not calculated in accordanc e with generally accepted accounting principles in the US (GAAP). This non - GAAP financial measure excludes certain amounts or expenses from the corresponding financial measures determined in accordance with GAAP. Management believes this non - GAAP information is useful for investors, taken in conjunction with the Company’s GAAP financial statements, because it provides greater transparency and period - over - period comparability with respect to the Company’s operating performanc e and can enhance investors’ ability to identify operating trends in the Company’s business. Management uses this measure, among other factors, to assess and analyze operational results and trends and to make financial and operational deci sio ns. Non - GAAP information is not prepared under a comprehensive set of accounting rules and should only be used to supplement an understanding of the Company’s operating results as reported under GAAP, not in isolation or as a substitute fo r, or superior to, financial information prepared and presented in accordance with GAAP. In addition, this non - GAAP financial measure is unlikely to be comparable with non - GAAP information provided by other companies. The determination of the amounts tha t are excluded from non - GAAP financial measures is a matter of management judgment and depends upon, among other factors, the nature of the underlying expense or income amounts. Reconciliations between this non - GAAP financial measure a nd the most comparable GAAP financial measure are included in the footnotes to the slides in this presentation on which such non - GAAP number appears. THIRD - PARTY SOURCES Certain information contained in this presentation, including industry and market data and other statistical information, rel ate s to or is based on studies, publications, surveys and other data obtained from third - party sources and the Company’s own internal estimates and research. While the Company believes these third - party sources to be reliable as of the date of this pres entation, it has not independently verified, and makes no representation as to the adequacy, fairness, accuracy or completeness of, any information obtained from third - party sources. In addition, all of the market data included in this present ation involves a number of assumptions and limitations, and there can be no guarantee as to the accuracy or reliability of such assumptions. Disclaimers
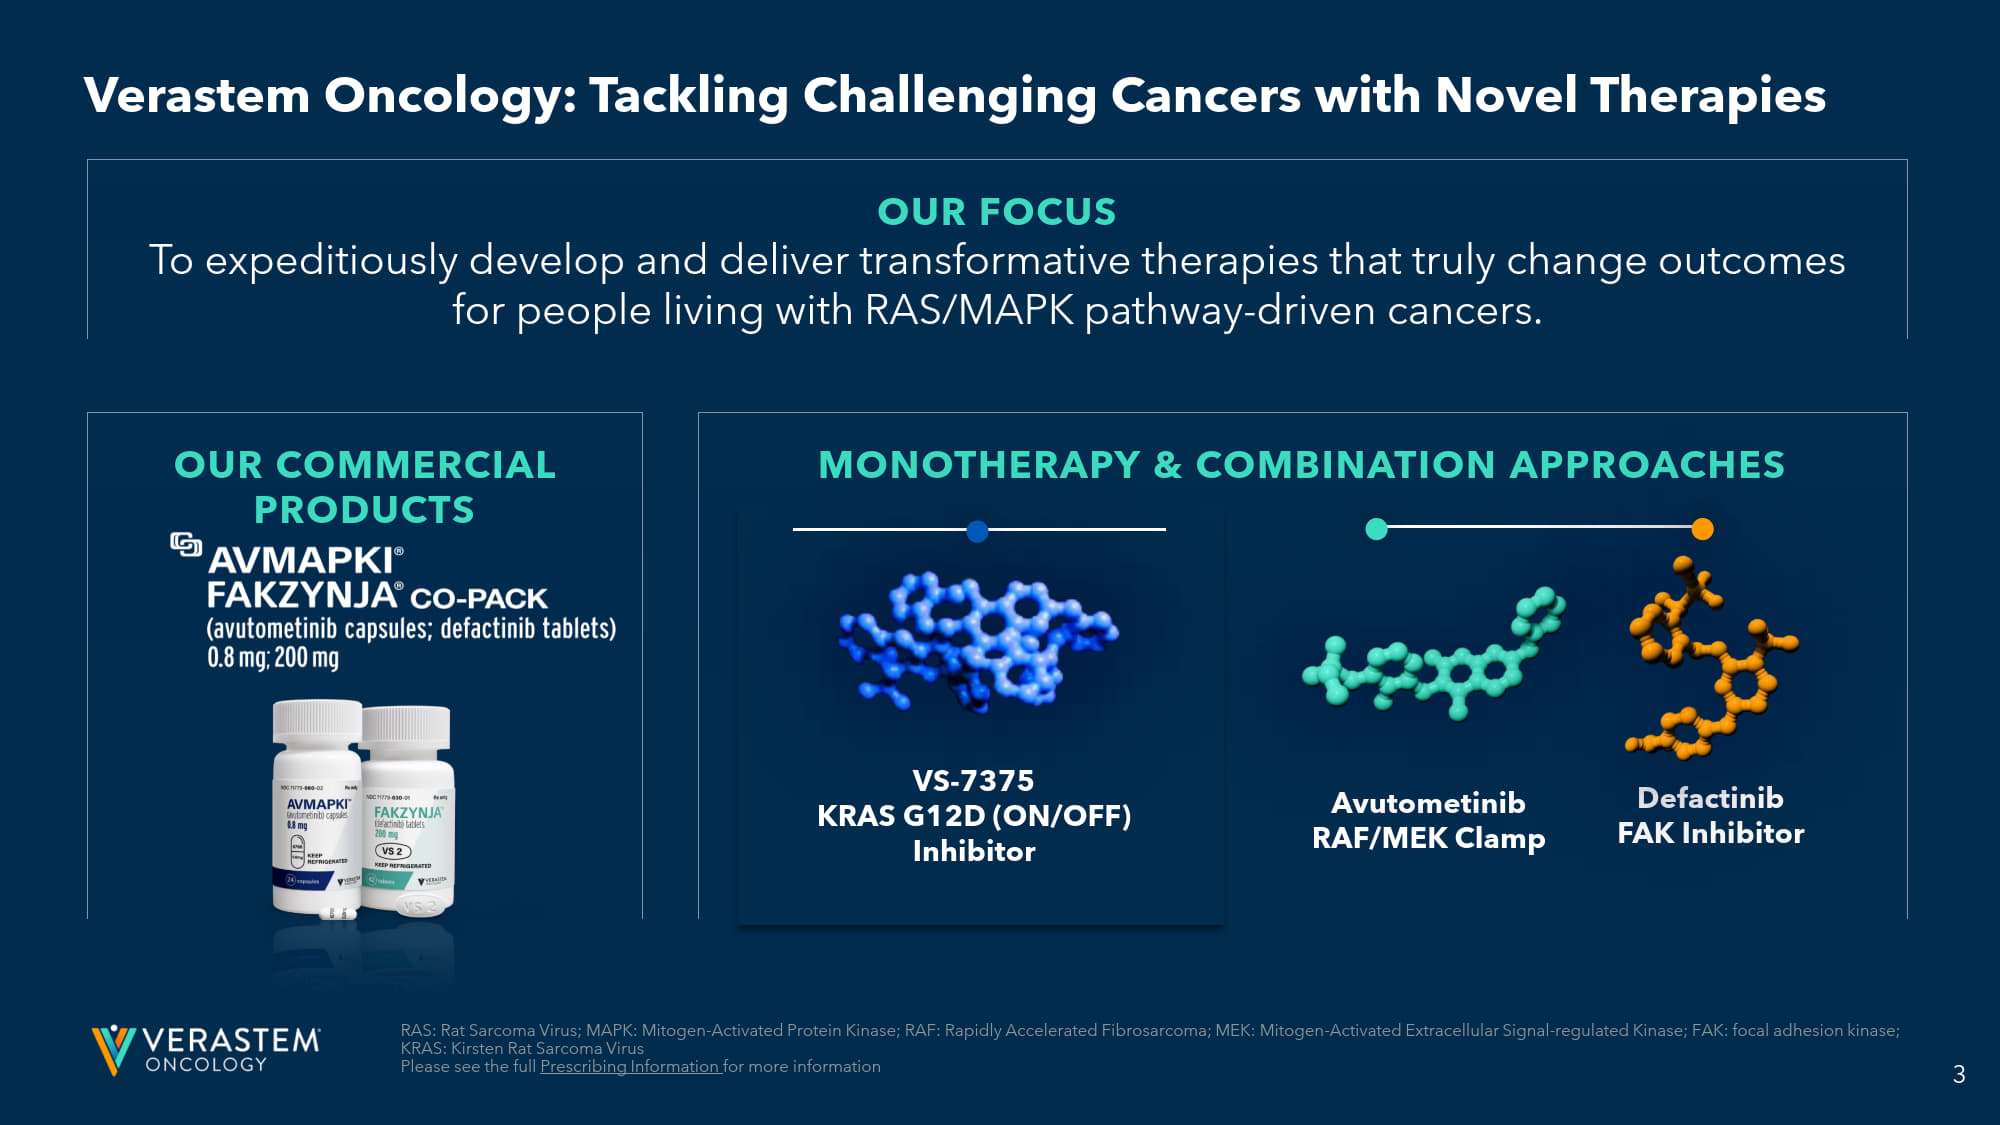
3 OUR COMMERCIAL PRODUCTS MONOTHERAPY & COMBINATION APPROACHES RAS: Rat Sarcoma Virus; MAPK: Mitogen - Activated Protein Kinase; RAF: Rapidly Accelerated Fibrosarcoma; MEK: Mitogen - Activated Ex tracellular Signal - regulated Kinase; FAK: focal adhesion kinase; KRAS: Kirsten Rat Sarcoma Virus Please see the full Prescribing Information for more information OUR FOCUS To expeditiously develop and deliver transformative therapies that truly change outcomes for people living with RAS/MAPK pathway - driven cancers. Avutometinib RAF/MEK Clamp Defactinib FAK Inhibitor VS - 7375 KRAS G12D (ON/OFF) Inhibitor Verastem Oncology: Tackling Challenging Cancers with Novel Therapies
4 FDA: Food and Drug Administration CLINICAL - TO - COMMERCIAL SUCCESS in bringing novel RAS/MAPK pathway - targeted therapies from development to FDA approval to commercialization INNOVATIVE PIPELINE with a potential best - in - class KRAS G12D asset targeting the most prevalent KRAS mutation in human cancers SCALABLE ORGANIZATION to maximize future oncology development programs and launches Well Positioned to Deliver Continued Commercial Success and a Potential Best - in - Class Treatment for Long - term Growth OUR ADVANTAGE: 4
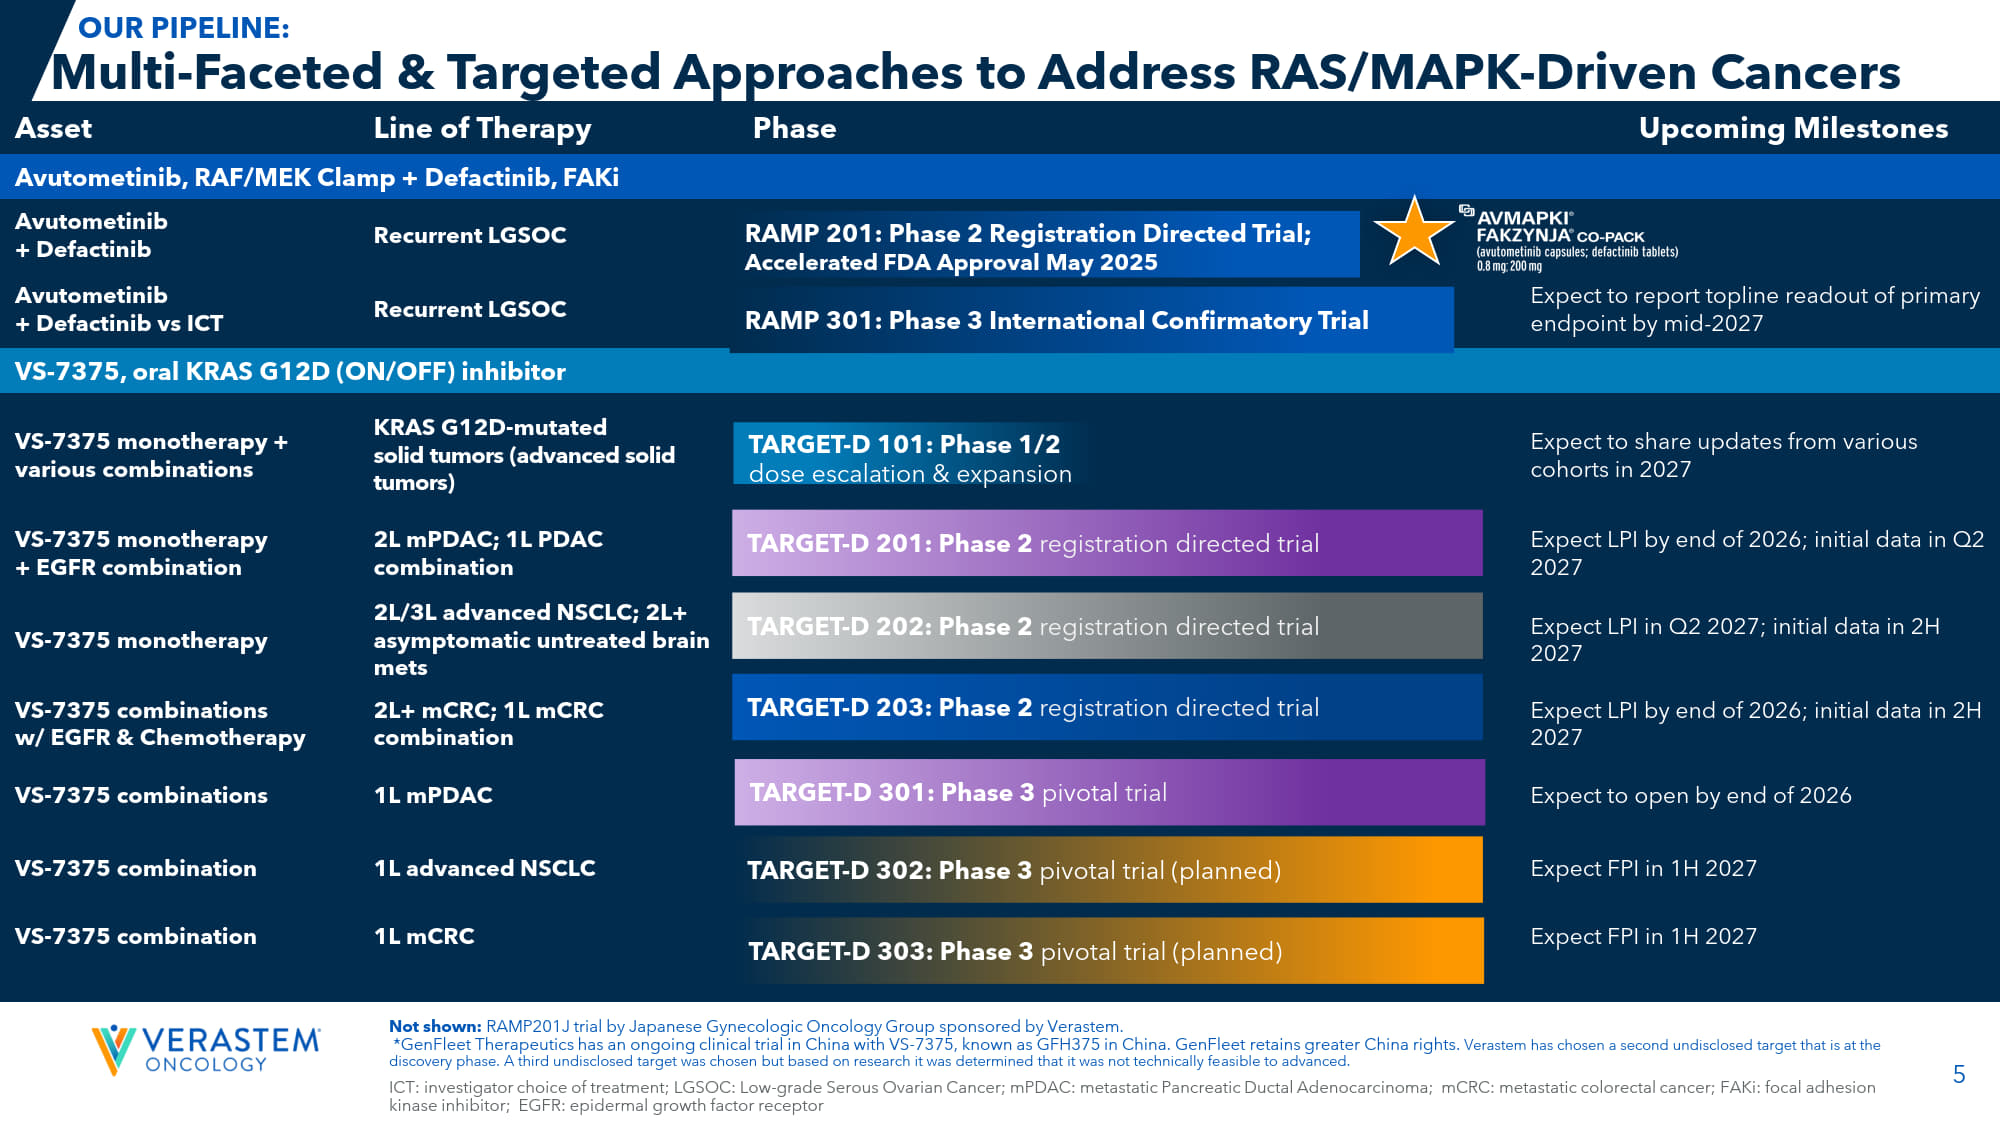
5 ICT: investigator choice of treatment; LGSOC: Low - grade Serous Ovarian Cancer; mPDAC : metastatic Pancreatic Ductal Adenocarcinoma; mCRC: metastatic colorectal cancer; FAKi : focal adhesion kinase inhibitor; EGFR: epidermal growth factor receptor Not shown: RAMP201J trial by Japanese Gynecologic Oncology Group sponsored by Verastem. * GenFleet Therapeutics has an ongoing clinical trial in China with VS - 7375, known as GFH375 in China. GenFleet retains greater China rights. Verastem has chosen a second undisclosed target that is at the discovery phase. A third undisclosed target was chosen but based on research it was determined that it was not technically fe asi ble to advanced. Upcoming Milestones Phase Line of Therapy Asset Avutometinib , RAF/MEK Clamp + Defactinib , FAKi Recurrent LGSOC Avutometinib + Defactinib Expect to report topline readout of primary endpoint by mid - 2027 Recurrent LGSOC Avutometinib + Defactinib vs ICT VS - 7375, oral KRAS G12D (ON/OFF) inhibitor Expect to share updates from various cohorts in 2027 KRAS G12D - mutated solid tumors (advanced solid tumors) VS - 7375 monotherapy + various combinations Expect LPI by end of 2026; initial data in Q2 2027 2L mPDAC ; 1L PDAC combination VS - 7375 monotherapy + EGFR combination Expect LPI in Q2 2027; initial data in 2H 2027 2L/3L advanced NSCLC; 2L+ asymptomatic untreated brain mets VS - 7375 monotherapy Expect LPI by end of 2026; initial data in 2H 2027 2L+ mCRC; 1L mCRC combination VS - 7375 combinations w/ EGFR & Chemotherapy Expect to open by end of 2026 1L mPDAC VS - 7375 combinations Expect FPI in 1H 2027 1L advanced NSCLC VS - 7375 combination Expect FPI in 1H 2027 1L mCRC VS - 7375 combination Multi - Faceted & Targeted Approaches to Address RAS/MAPK - Driven Cancers OUR PIPELINE: RAMP 201: Phase 2 Registration Directed Trial; Accelerated FDA Approval May 2025 RAMP 301: Phase 3 International Confirmatory Trial TARGET - D 101: Phase 1/2 dose escalation & expansion TARGET - D 201: Phase 2 registration directed trial TARGET - D 202: Phase 2 registration directed trial TARGET - D 203: Phase 2 registration directed trial TARGET - D 302: Phase 3 pivotal trial (planned) TARGET - D 303: Phase 3 pivotal trial (planned) TARGET - D 301: Phase 3 pivotal trial
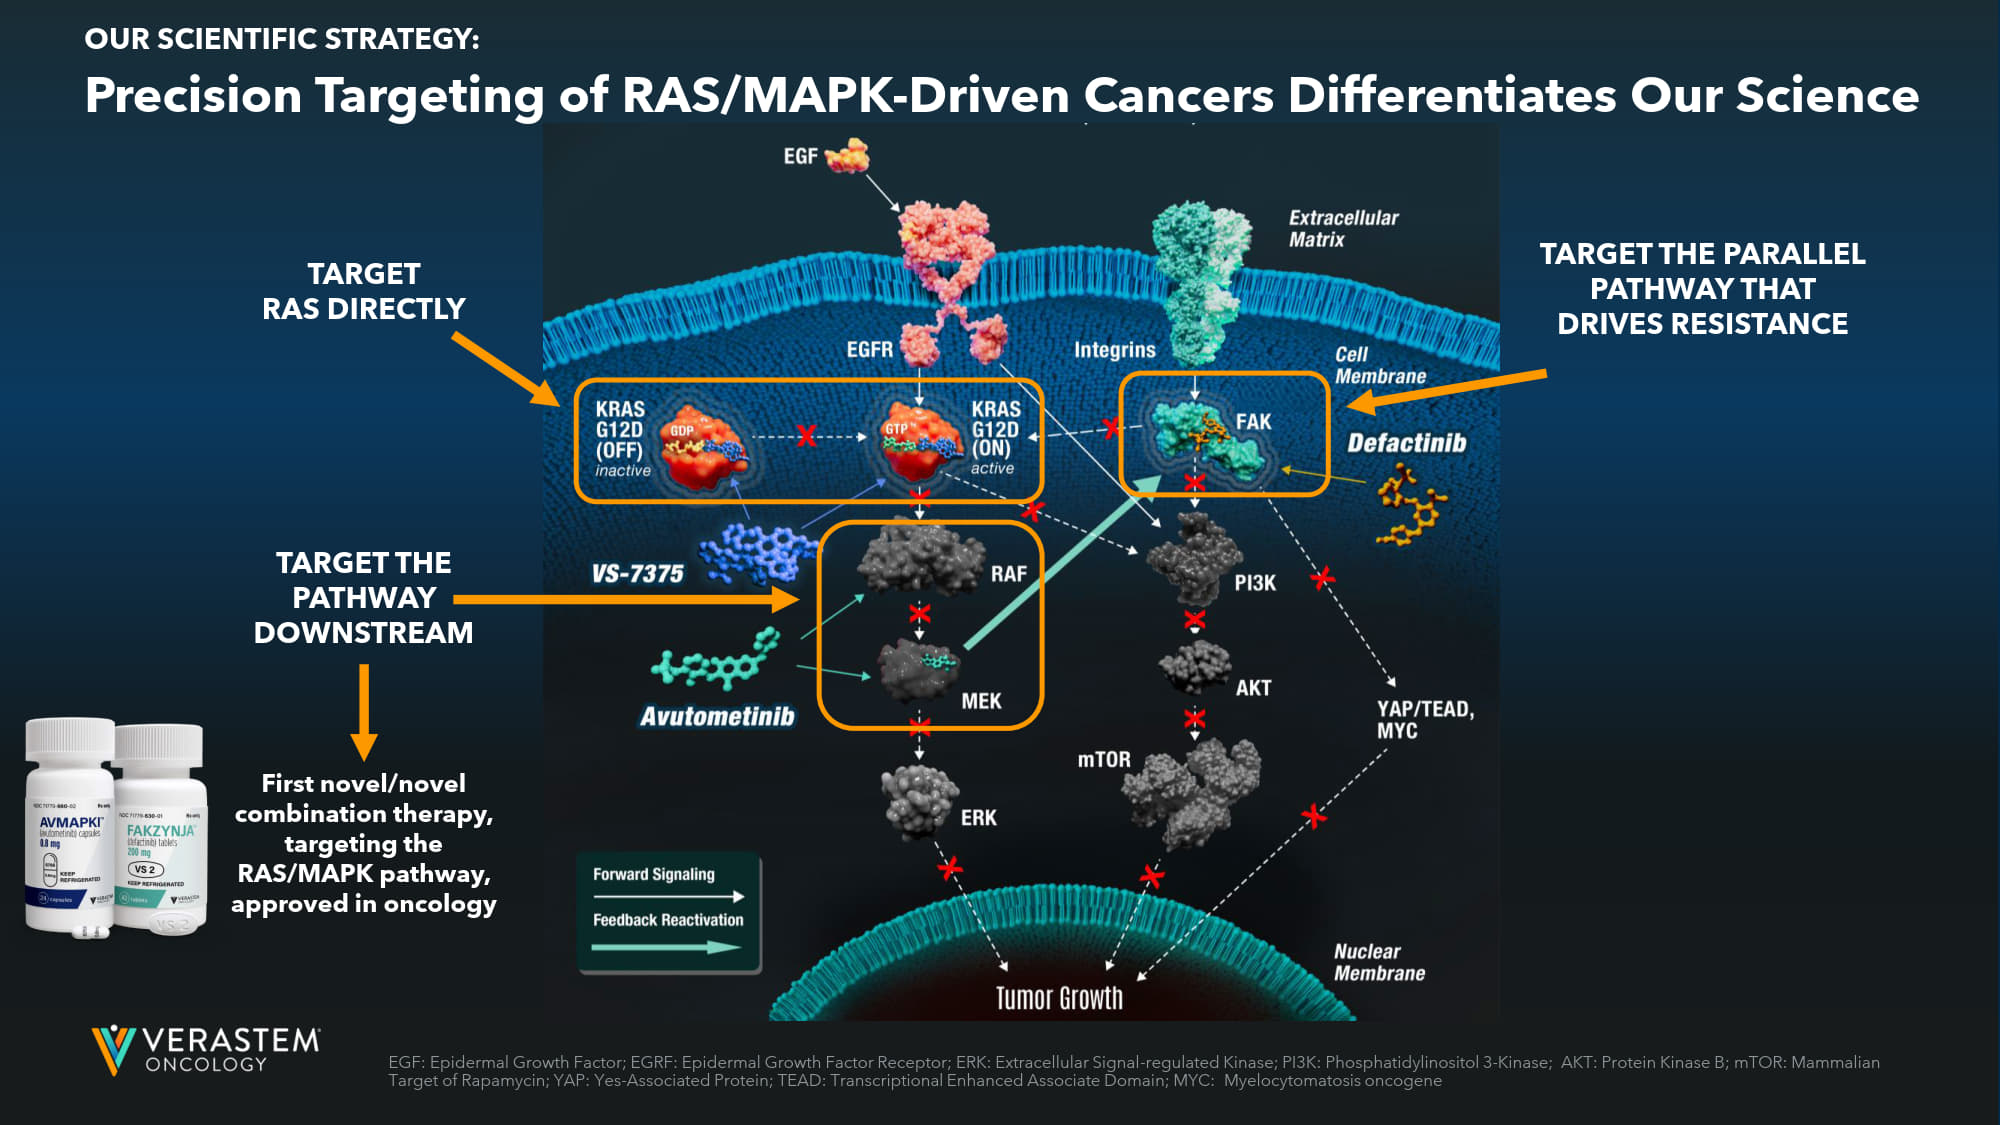
6 TARGET RAS DIRECTLY TARGET THE PATHWAY DOWNSTREAM TARGET THE PARALLEL PATHWAY THAT DRIVES RESISTANCE First novel/novel combination therapy, targeting the RAS/MAPK pathway, approved in oncology Precision Targeting of RAS/MAPK - Driven Cancers Differentiates Our Science OUR SCIENTIFIC STRATEGY: EGF: Epidermal Growth Factor; EGRF: Epidermal Growth Factor Receptor; ERK: Extracellular Signal - regulated Kinase; PI3K: Phosphat idylinositol 3 - Kinase; AKT: Protein Kinase B; mTOR: Mammalian Target of Rapamycin; YAP: Yes - Associated Protein; TEAD: Transcriptional Enhanced Associate Domain; MYC: Myelocytomatosis oncogene
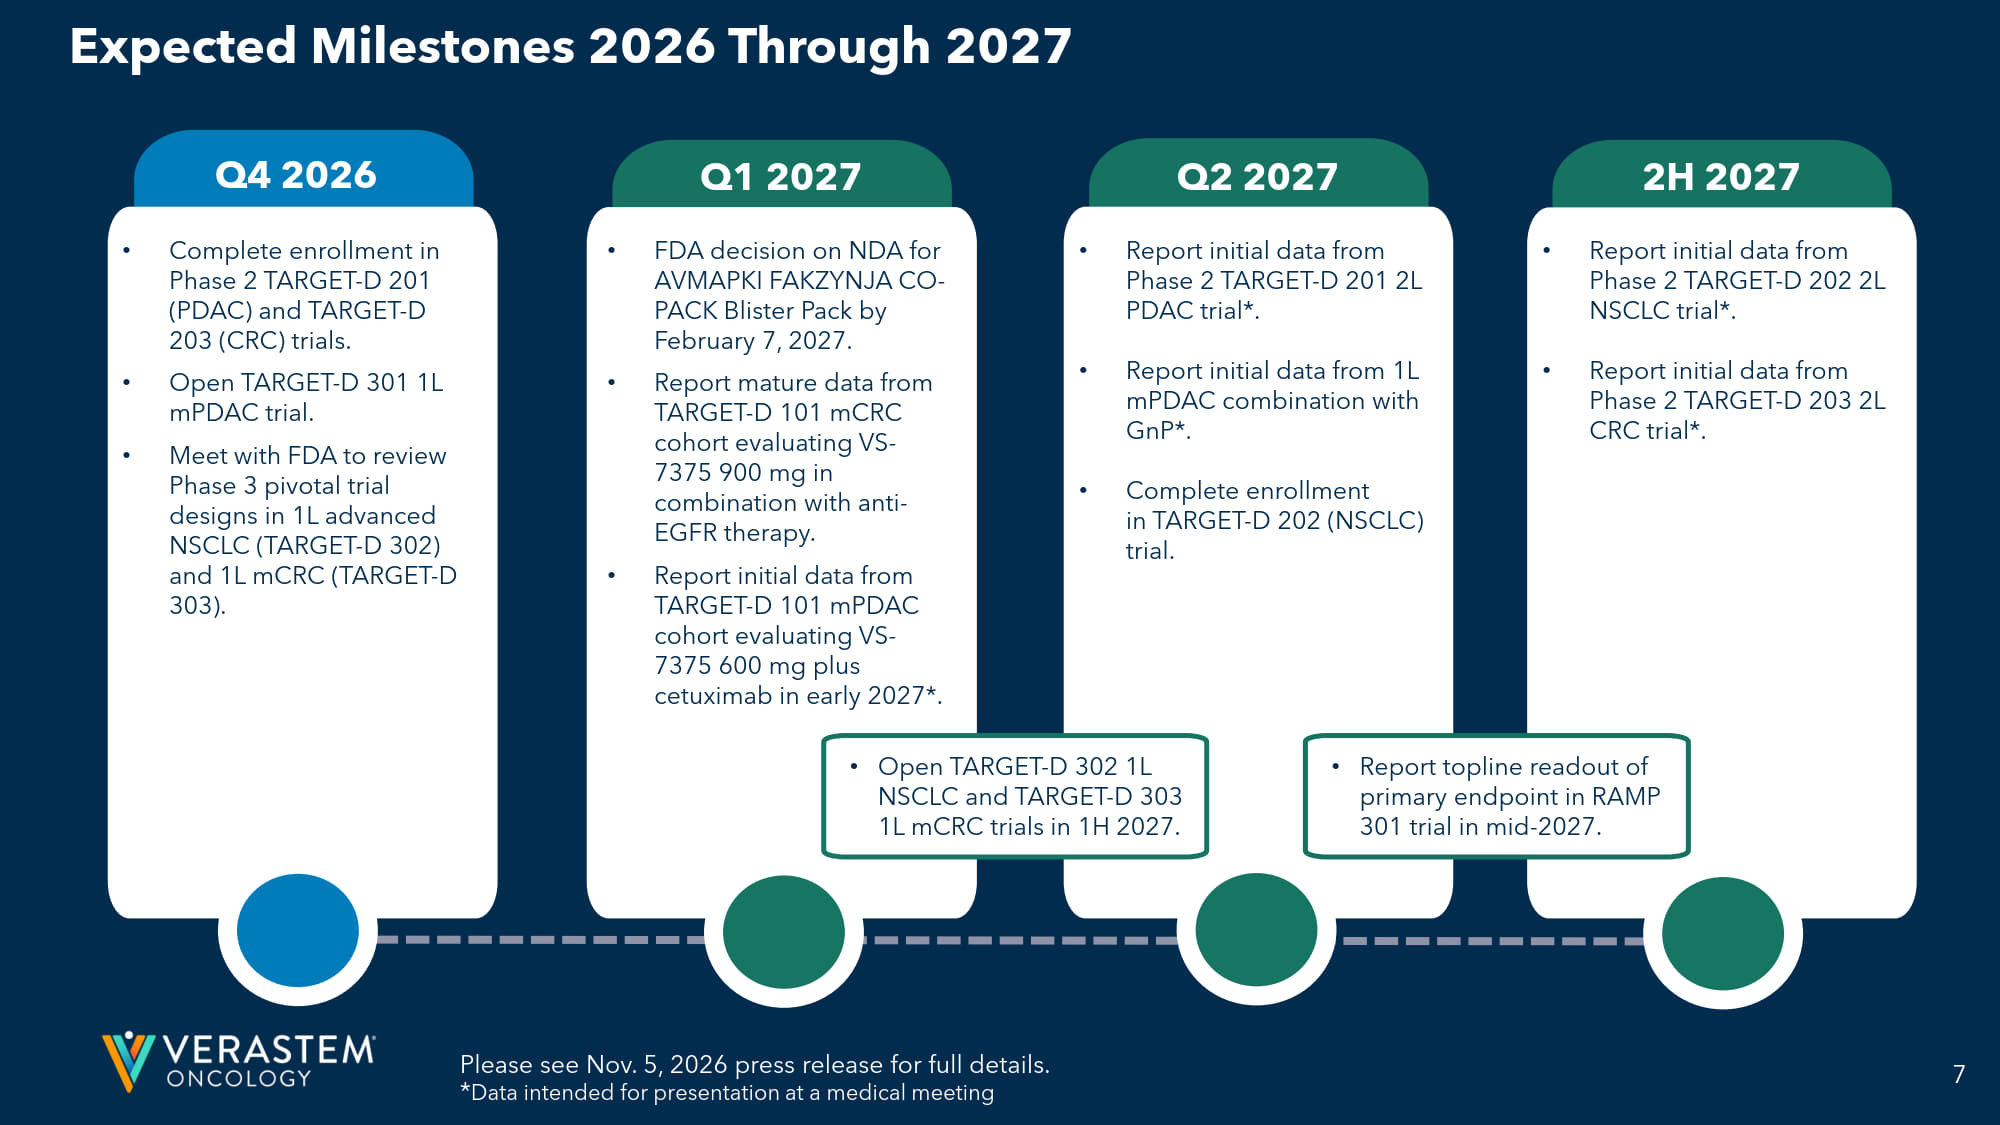
7 2H 2027 Q2 2027 • Complete enrollment in Phase 2 TARGET - D 201 (PDAC) and TARGET - D 203 (CRC) trials. • Open TARGET - D 301 1L mPDAC trial. • Meet with FDA to review Phase 3 pivotal trial designs in 1L advanced NSCLC (TARGET - D 302) and 1L mCRC (TARGET - D 303). Q4 2026 Expected Milestones 2026 Through 2027 • Open TARGET - D 302 1L NSCLC and TARGET - D 303 1L mCRC trials in 1H 2027. • FDA decision on NDA for AVMAPKI FAKZYNJA CO - PACK Blister Pack by February 7, 2027. • Report mature data from TARGET - D 101 mCRC cohort evaluating VS - 7375 900 mg in combination with anti - EGFR therapy. • Report initial data from TARGET - D 101 mPDAC cohort evaluating VS - 7375 600 mg plus cetuximab in early 2027*. • Report initial data from Phase 2 TARGET - D 201 2L PDAC trial*. • Report initial data from 1L mPDAC combination with GnP *. • Complete enrollment in TARGET - D 202 (NSCLC) trial. • Report initial data from Phase 2 TARGET - D 202 2L NSCLC trial*. • Report initial data from Phase 2 TARGET - D 203 2L CRC trial*. Please see Nov. 5, 2026 press release for full details. * Data intended for presentation at a medical meeting Q1 2027 • Report topline readout of primary endpoint in RAMP 301 trial in mid - 2027.

8 Commercially Launched in the U.S. for KRAS - mutated Recurrent LGSOC FDA APPROVAL DATE: MAY 8, 2025
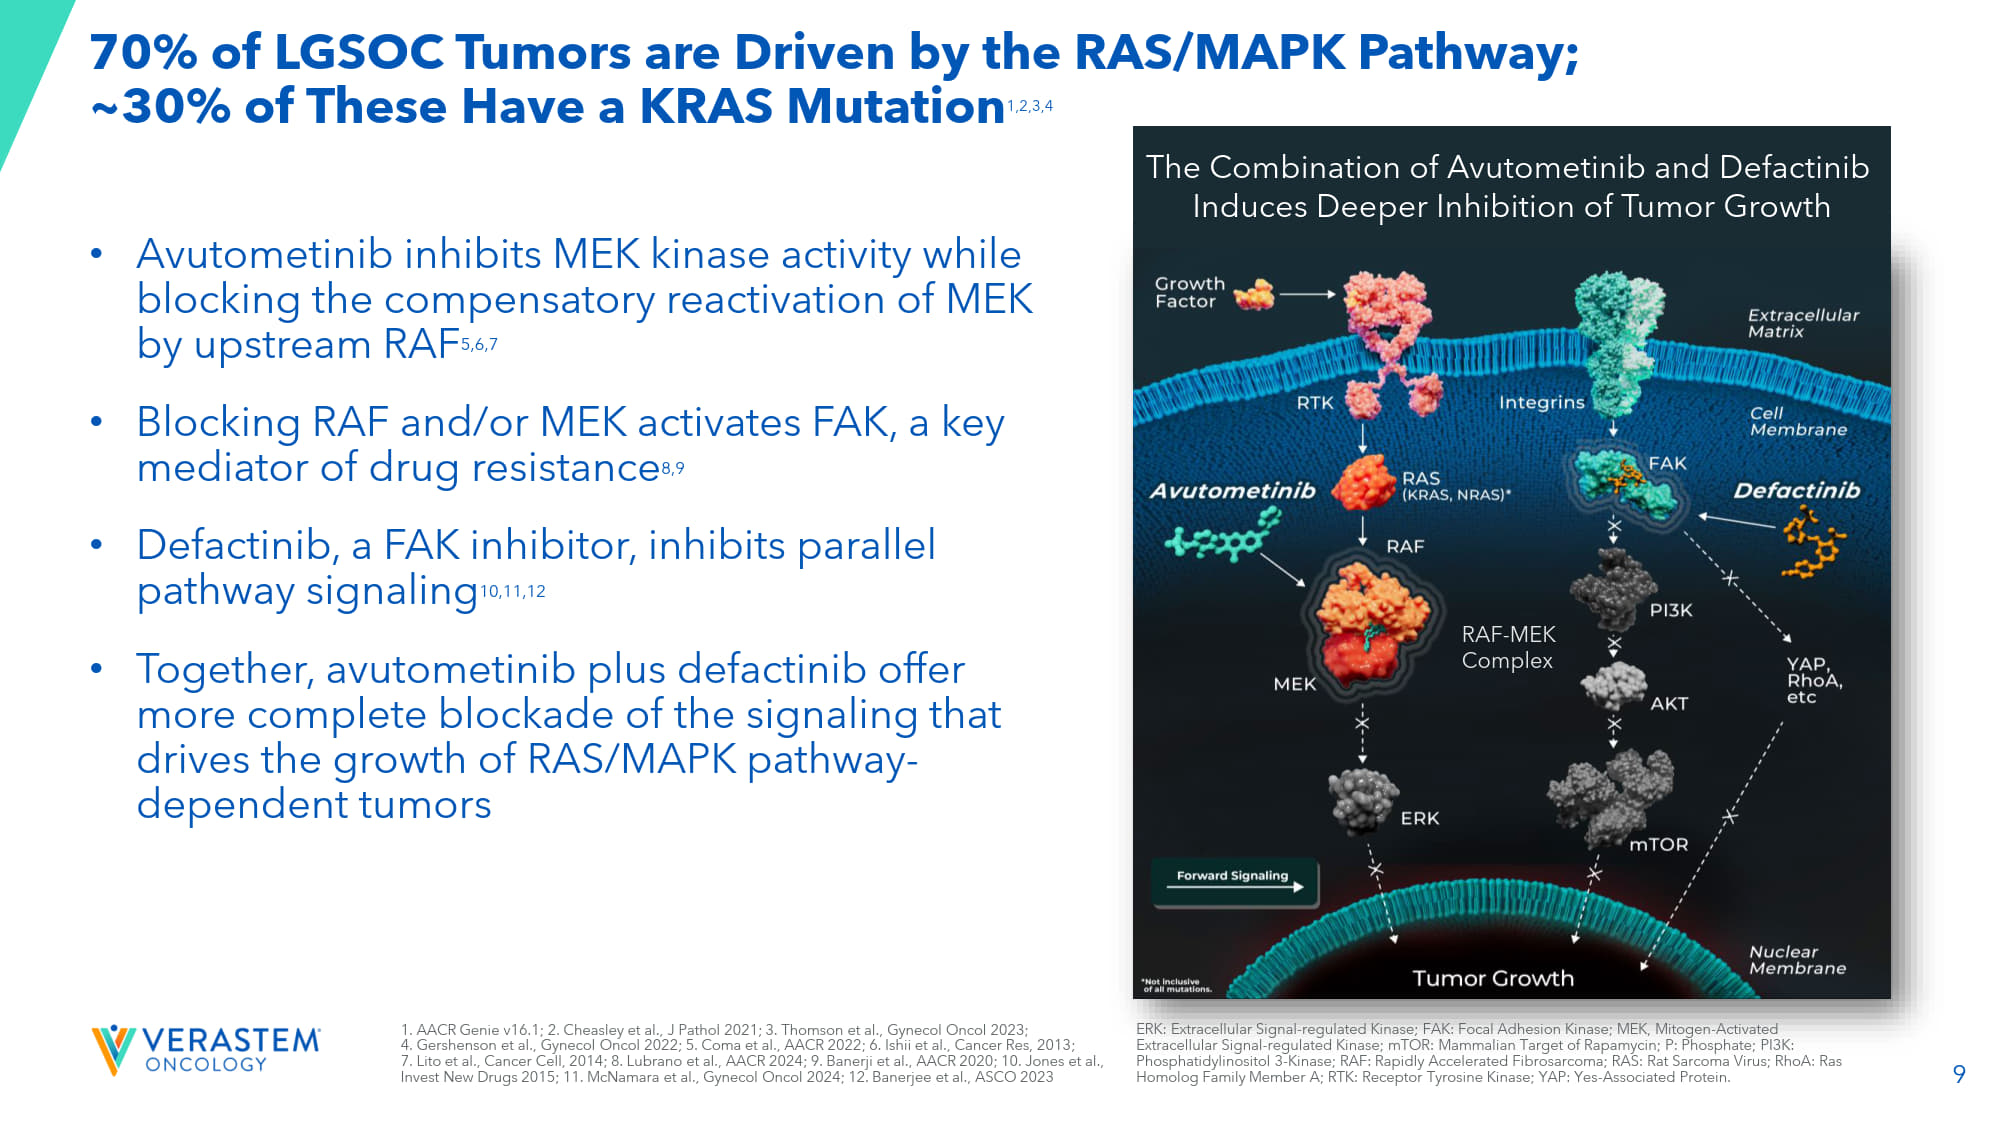
9 70% of LGSOC Tumors are Driven by the RAS/MAPK Pathway; ~30% of These Have a KRAS Mutation 1,2,3,4 • Avutometinib inhibits MEK kinase activity while blocking the compensatory reactivation of MEK by upstream RAF 5,6,7 • Blocking RAF and/or MEK activates FAK, a key mediator of drug resistance 8,9 • Defactinib, a FAK inhibitor, inhibits parallel pathway signaling 10,11,12 • Together, avutometinib plus defactinib offer more complete blockade of the signaling that drives the growth of RAS/MAPK pathway - dependent tumors RAF - MEK Complex The Combination of Avutometinib and Defactinib Induces Deeper Inhibition of Tumor Growth 1. AACR Genie v16.1; 2. Cheasley et al., J Pathol 2021; 3. Thomson et al., Gynecol Oncol 2023; 4. Gershenson et al., Gynecol Oncol 2022; 5. Coma et al., AACR 2022 ; 6. Ishii et al., Cancer Res, 2013 ; 7. Lito et al., Cancer Cell, 2014 ; 8. Lubrano et al., AACR 2024 ; 9. Banerji et al., AACR 2020 ; 10. Jones et al., Invest New Drugs 2015; 11. McNamara et al., Gynecol Oncol 2024 ; 12. Banerjee et al., ASCO 2023 ERK: Extracellular Signal - regulated Kinase; FAK: Focal Adhesion Kinase; MEK, Mitogen - Activated Extracellular Signal - regulated Kinase; mTOR: Mammalian Target of Rapamycin; P: Phosphate; PI3K: Phosphatidylinositol 3 - Kinase; RAF: Rapidly Accelerated Fibrosarcoma; RAS: Rat Sarcoma Virus; RhoA: Ras Homolog Family Member A; RTK: Receptor Tyrosine Kinase; YAP: Yes - Associated Protein.

10 High Unmet Need for an Effective and Tolerable Therapy in Recurrent LGSOC • U.S. annual incidence: ~1,000 - 2,000 1 and prevalence: 6,000 - 8,000 2 • A ffects younger women with bimodal peaks of diagnosis between the ages of 20 - 30 and 50 - 60 – Disproportionately impacts health, fertility and long - term quality of life 3,4 • 80 - 90% of patients will experience a recurrence 5 • Standard of care offers low to moderate response rates (6 - 13%) 6,7,8 When you get told that you have a recurrence, the mental load is a lot. You’re thinking, okay, what did I have to do for treatment the first time? Now I have to repeat that. And will there even be something available for me to take for a second, or a third recurrence? - Amanda, real patient living with recurrent LGSOC; diagnosed at 26 with LGSOC 1. Verastem DOF; 2. US Cancer Statistics. Accessed 2024; 3. Slomovitz Gynecol Oncol 2020; 4. Manning - Geist B et al. Clin Cancer Res 2022;28(20):4456 - 4465; 5. Babaier 2022/p1/para1/ln6,7; 6. Gershenson Gynecol Oncol 2022; 7. Slomovitz Gynecol Oncol 2020; 8. Monk 2020/p3758/table2/footnote - b; 10

11 AVMAPKI FAKZYNJA CO - PACK Q3 Update Please see the full Prescribing Information for more information x Q3 net product revenue: $24M 1 x Demand held steady after significant Q2 growth x Strong refill reinforce a clear priority: helping appropriate patients stay on therapy x Focused execution has the potential to drive sustained growth x New Blister Pack NDA acceptance w/ Priority Review for Q1 27 supports patient convenience and adherence 1.Please see Nov. 5, 2026 press release Drive use in the right patients at the first or next recurrence PRIORITIES Helping patients stay on AVMAPKI FAKZYNJA CO - PACK Growth in new patient starts
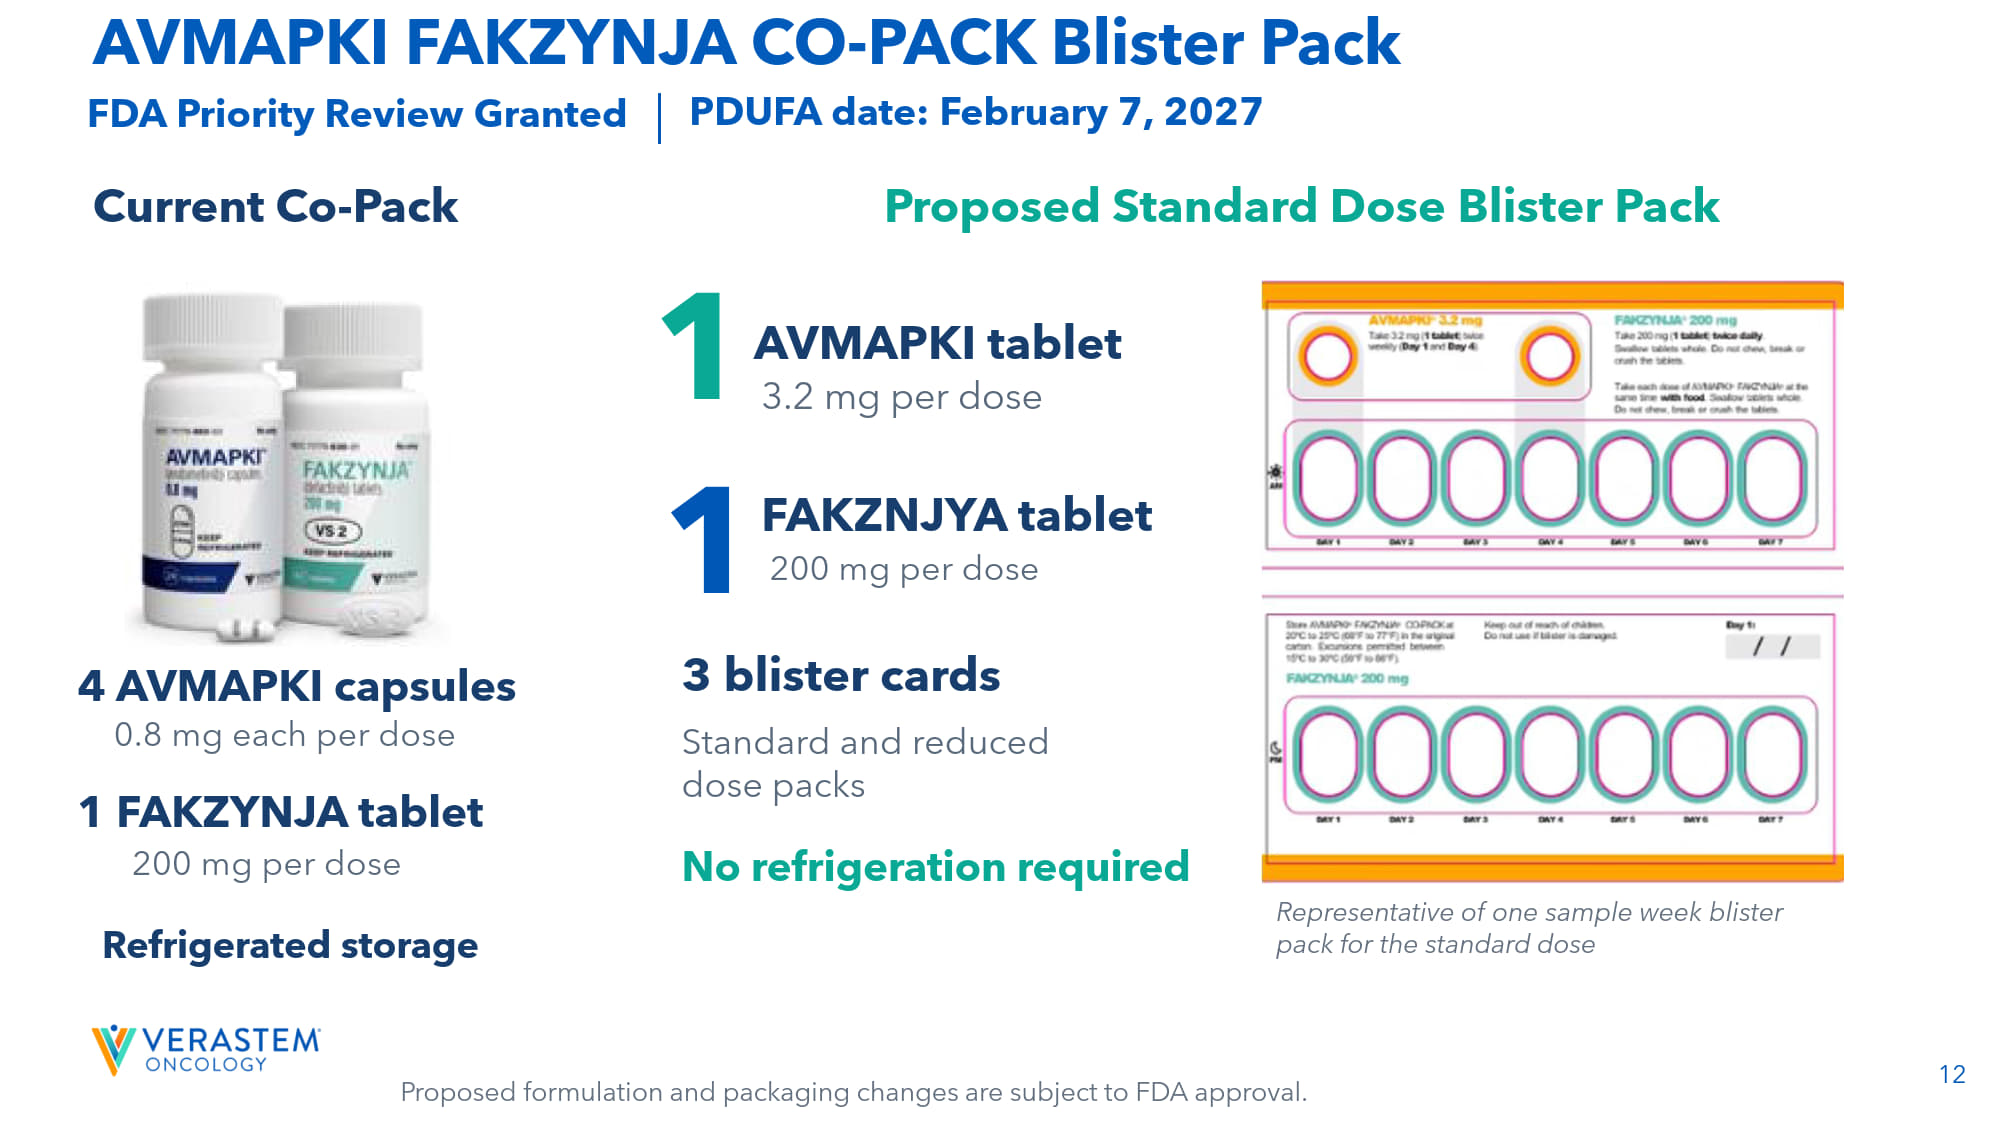
12 AVMAPKI FAKZYNJA CO - PACK Blister Pack FDA Priority Review G ranted PDUFA date: February 7, 2027 Current Co - Pack Proposed Standard Dose B lister P ack 4 AVMAPKI capsules 0.8 mg each per dose Refrigerated storage 1 AVMAPKI tablet 3.2 mg per dose 3 blister cards Standard and reduced dose packs No refrigeration required Representative of one sample week blister pack for the standard dose 1 FAKZYNJA tablet FAKZNJYA tablet 1 200 mg per dose 200 mg per dose Proposed formulation and packaging changes are subject to FDA approval.
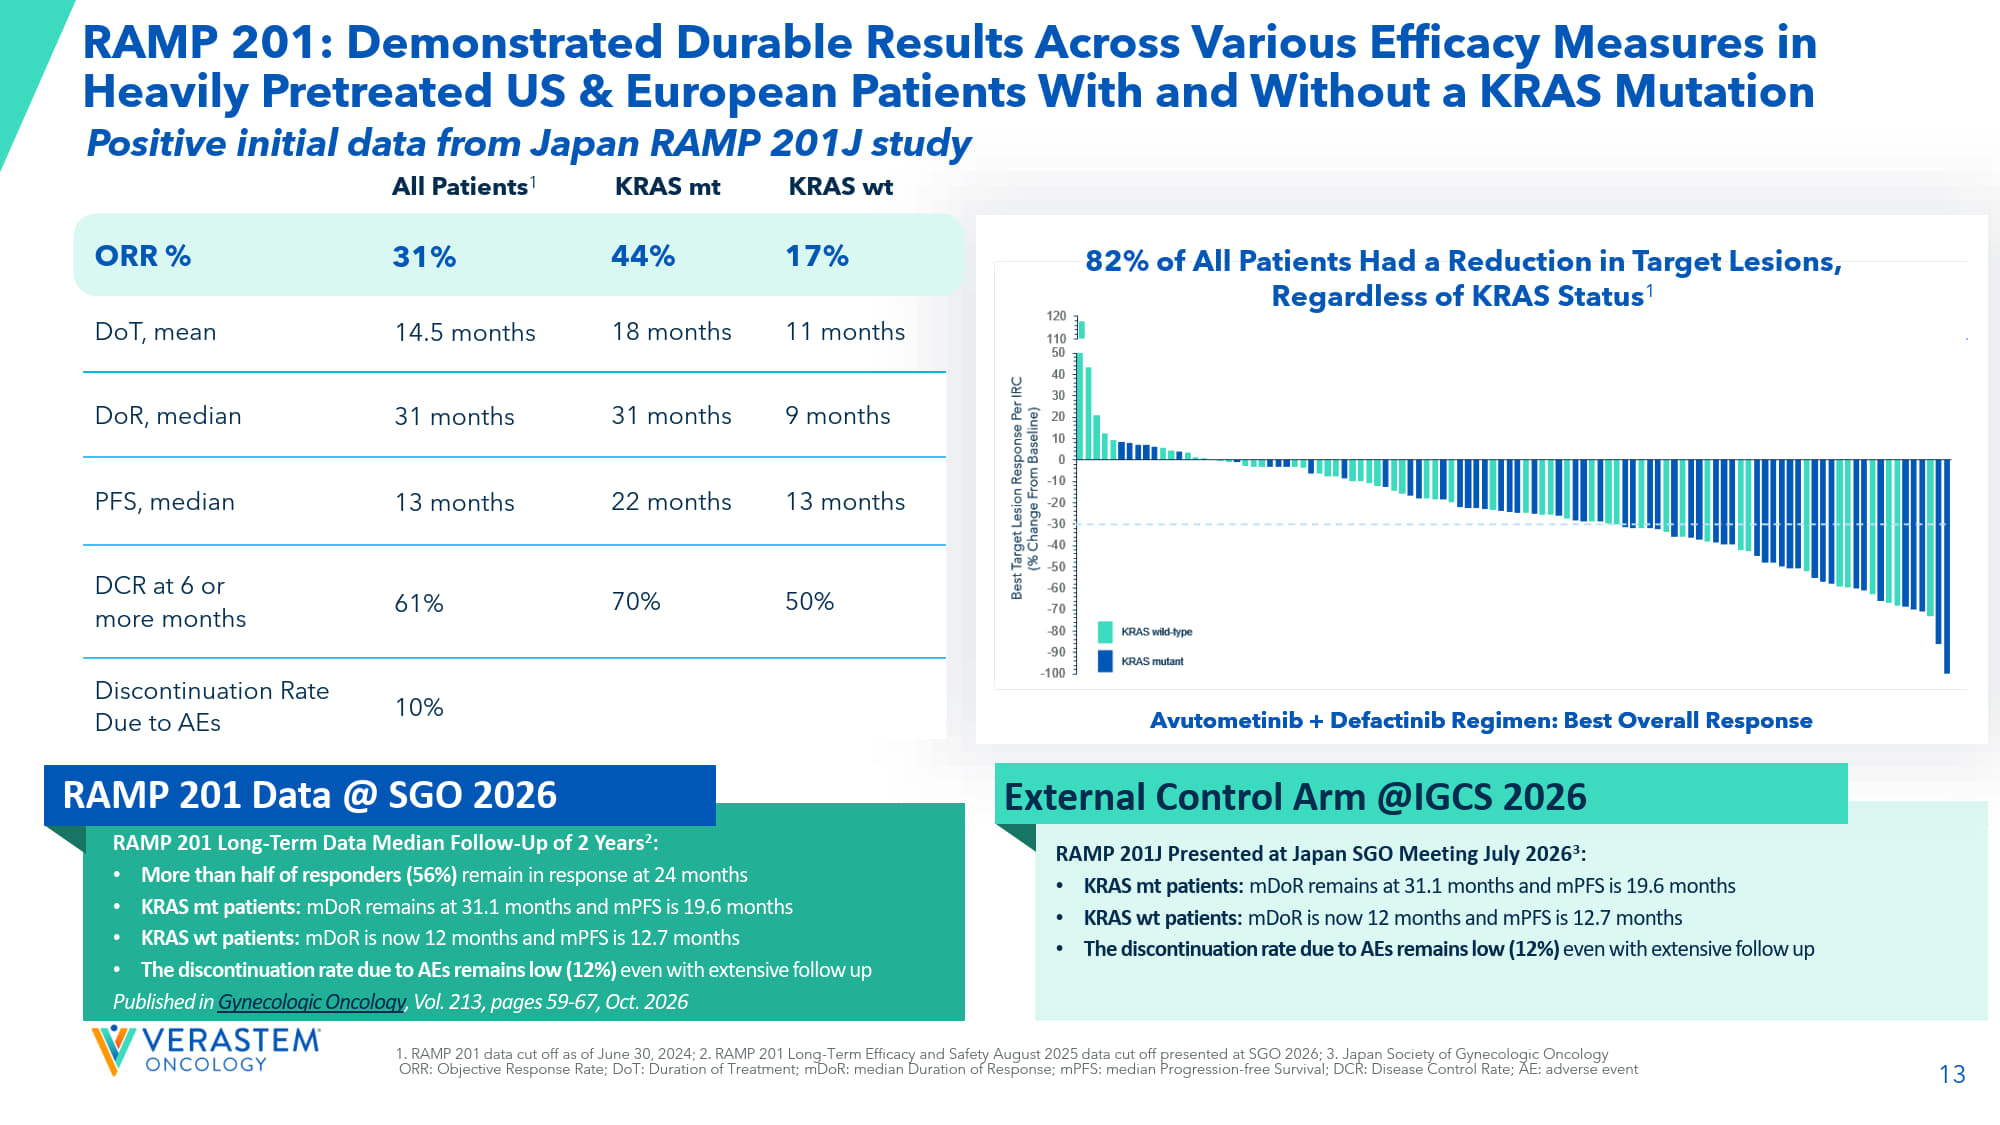
13 RAMP 201: Demonstrated Durable Results Across Various Efficacy Measures in Heavily Pretreated US & European Patients With and Without a KRAS Mutation Avutometinib + Defactinib Regimen: Best Overall Response 82% of All Patients Had a Reduction in Target Lesions, Regardless of KRAS Status 1 KRAS wt KRAS mt All Patients 1 17% 44% 31% ORR % 11 months 18 months 14.5 months DoT, mean 9 months 31 months 31 months DoR , median 13 months 22 months 13 months PFS, median 50% 70% 61% DCR at 6 or more months 10% Discontinuation Rate Due to AEs 1. RAMP 201 data cut off as of June 30, 2024; 2. RAMP 201 Long - Term Efficacy and Safety August 2025 data cut off presented at SG O 2026; 3. Japan Society of Gynecologic Oncology ORR: Objective Response Rate; DoT: Duration of Treatment; mDoR : median Duration of Response; m PFS: median Progression - free Survival; DCR: Disease Control Rate; AE: adverse event Avutometinib + Defactinib Regimen: Best Overall Response RAMP 201 Long - Term Data Median Follow - Up of 2 Years 2 : • More than half of responders (56%) remain in response at 24 months • KRAS mt patients: mDoR remains at 31.1 months and mPFS is 19.6 months • KRAS wt patients: mDoR is now 12 months and mPFS is 12.7 months • The discontinuation rate due to AEs remains low (12%) even with extensive follow up Published in Gynecologic Oncology , Vol. 213, pages 59 - 67, Oct. 2026 RAMP 201 Data @ SGO 2026 External Control Arm @IGCS 2026 RAMP 201J Presented at Japan SGO Meeting July 2026 3 : • KRAS mt patients: mDoR remains at 31.1 months and mPFS is 19.6 months • KRAS wt patients: mDoR is now 12 months and mPFS is 12.7 months • The discontinuation rate due to AEs remains low (12%) even with extensive follow up Positive initial data from Japan RAMP 201J study
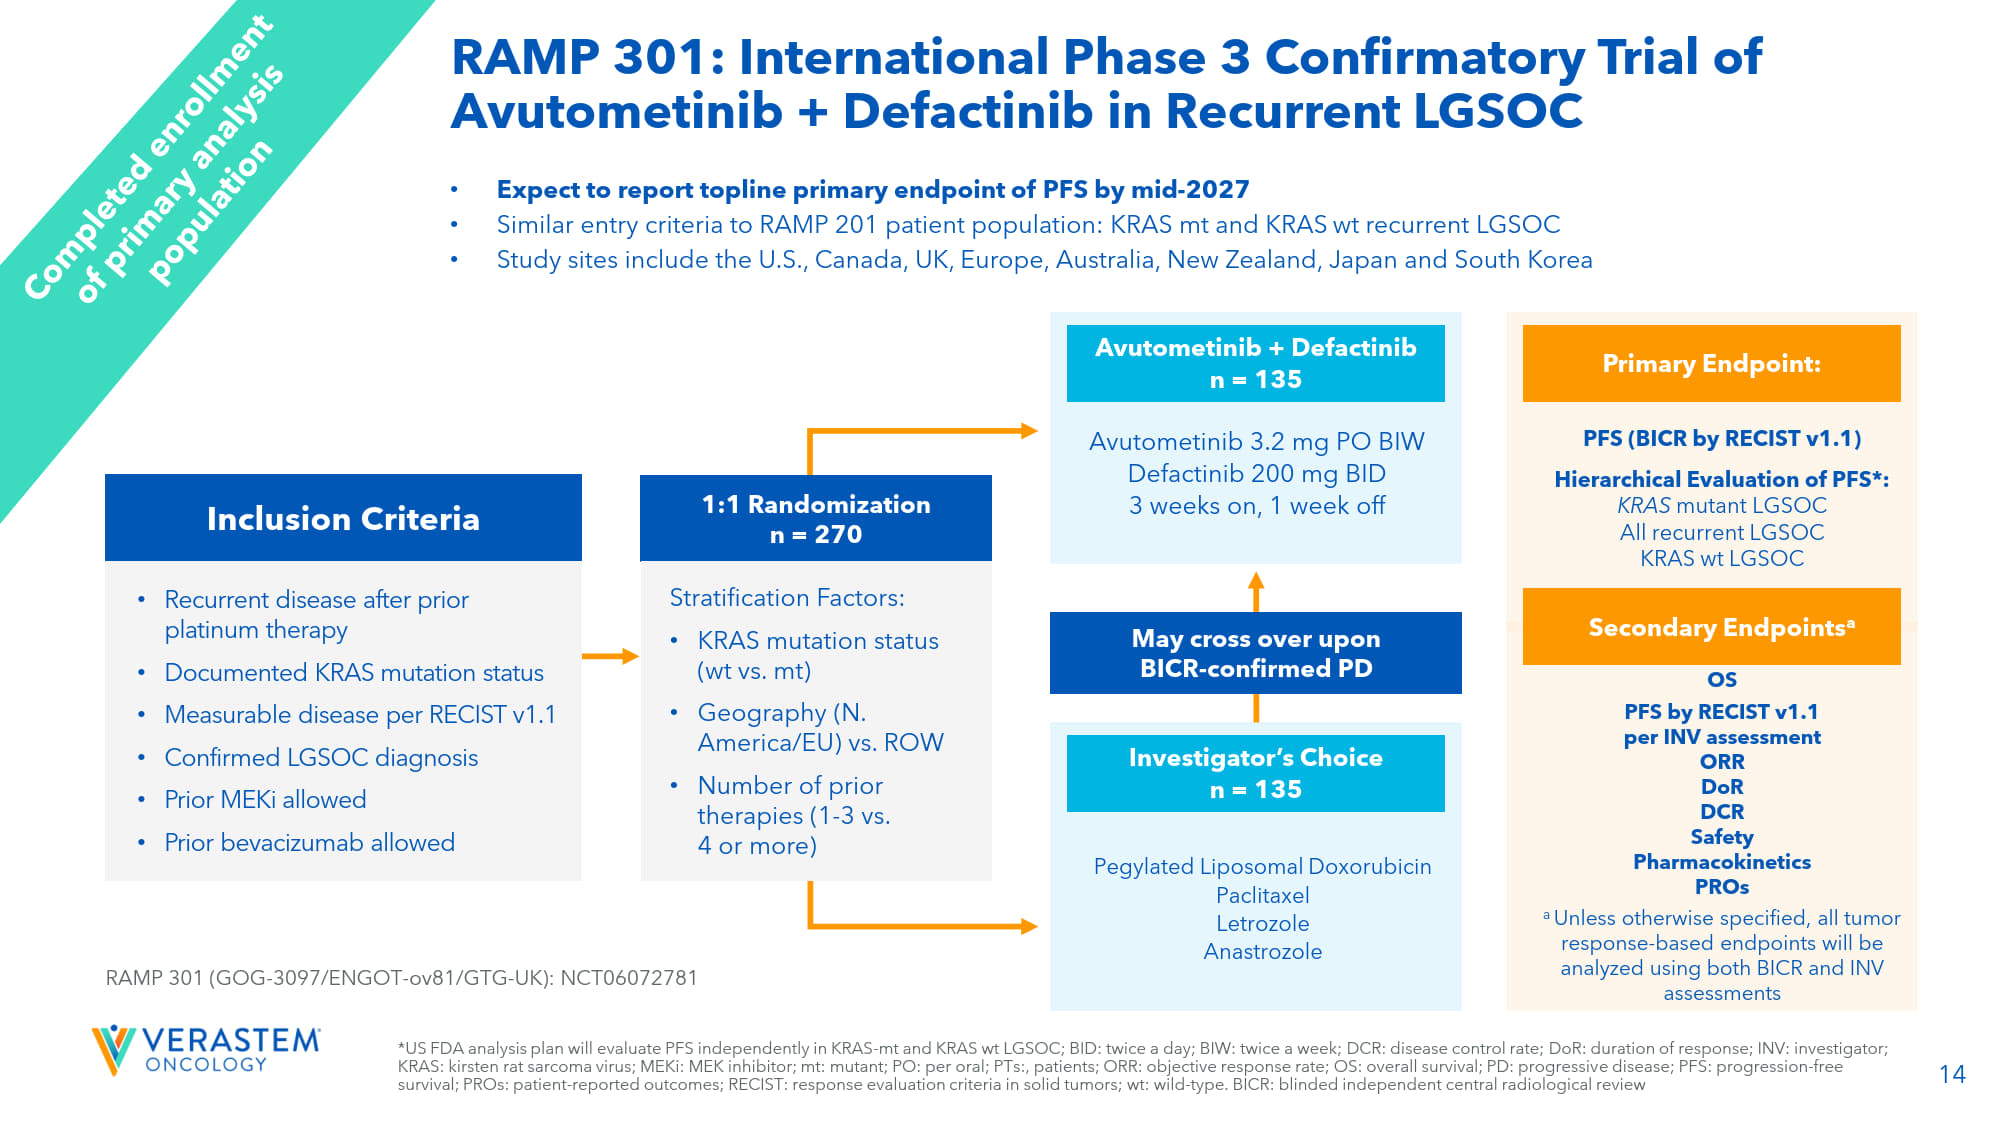
14 OS PFS by RECIST v1.1 per INV assessment ORR DoR DCR Safety Pharmacokinetics PROs a Unless otherwise specified, all tumor response - based endpoints will be analyzed using both BICR and INV assessments *US FDA analysis plan will evaluate PFS independently in KRAS - mt and KRAS wt LGSOC; BID: twice a day; BIW: twice a week; DCR: disease control rate; DoR : duration of response; INV: investigator; KRAS: kirsten rat sarcoma virus; MEKi : MEK inhibitor; mt: mutant; PO: per oral; PTs:, patients; ORR: objective response rate; OS: overall survival; PD: progressiv e d isease; PFS: progression - free survival; PROs: patient - reported outcomes; RECIST: response evaluation criteria in solid tumors; wt : wild - type. BICR: blinded independent central radiological review • Expect to report topline primary endpoint of PFS by mid - 2027 • Similar entry criteria to RAMP 201 patient population: KRAS mt and KRAS wt recurrent LGSOC • Study sites include the U.S., Canada, UK, Europe, Australia, New Zealand, Japan and South Korea • Recurrent disease after prior platinum therapy • Documented KRAS mutation status • Measurable disease per RECIST v1.1 • Confirmed LGSOC diagnosis • Prior MEKi allowed • Prior bevacizumab allowed RAMP 301 (GOG - 3097/ENGOT - ov81/GTG - UK): NCT06072781 Pegylated Liposomal Doxorubicin Paclitaxel Letrozole Anastrozole Investigator’s Choice n = 135 Avutometinib 3.2 mg PO BIW Defactinib 200 mg BID 3 weeks on, 1 week off Avutometinib + Defactinib n = 135 May cross over upon BICR - confirmed PD PFS (BICR by RECIST v1.1) Hierarchical Evaluation of PFS*: KRAS mutant LGSOC All recurrent LGSOC KRAS wt LGSOC Primary Endpoint: Secondary Endpoints a 1:1 Randomization n = 270 Stratification Factors: • KRAS mutation status ( wt vs. mt) • Geography (N. America/EU) vs. ROW • Number of prior therapies (1 - 3 vs. 4 or more) Inclusion Criteria RAMP 301: International Phase 3 Confirmatory Trial of Avutometinib + Defactinib in Recurrent LGSOC
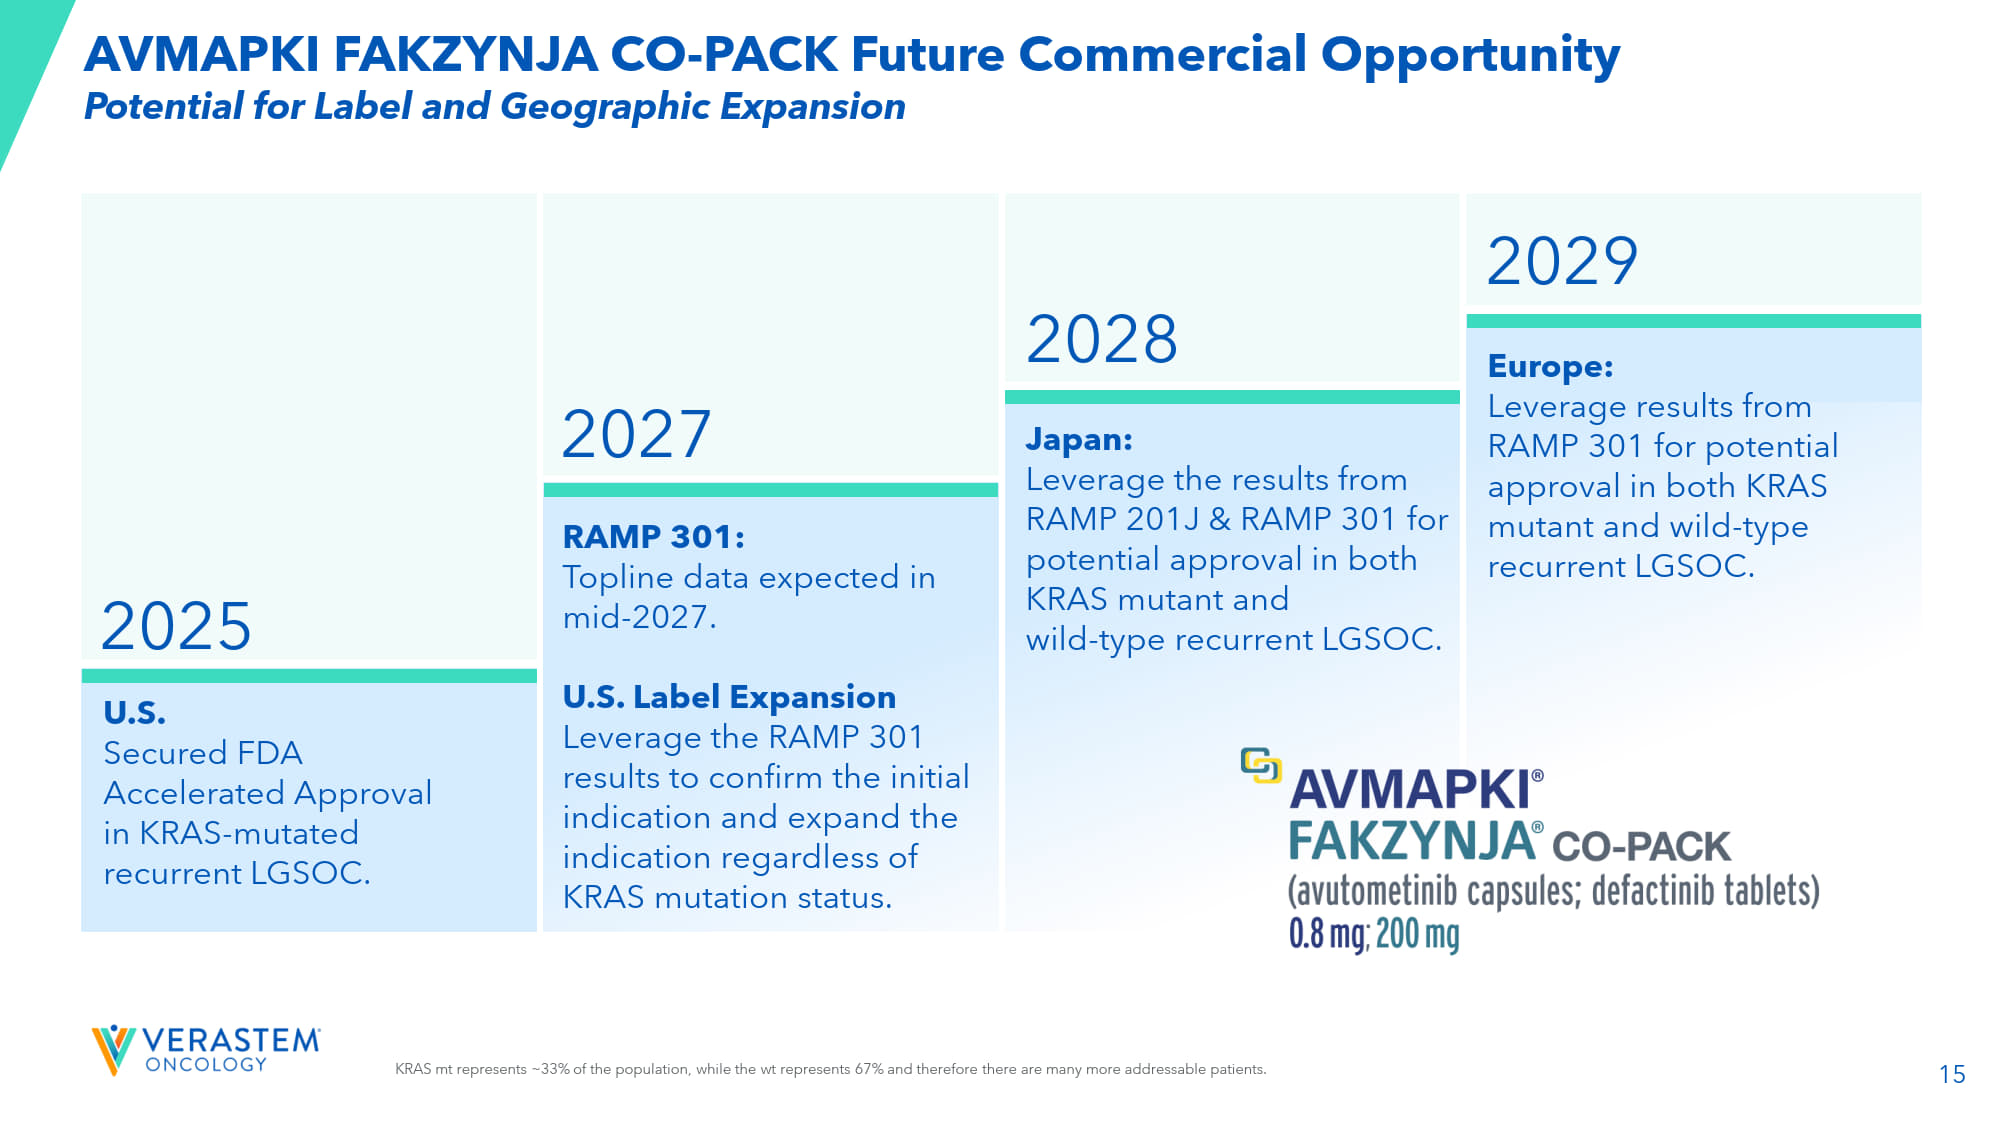
15 U.S. Secured FDA Accelerated Approval in KRAS - mutated recurrent LGSOC. 2029 2025 RAMP 301: Topline data expected in mid - 2027. U.S. Label Expansion Leverage the RAMP 301 results to confirm the initial indication and expand the indication regardless of KRAS mutation status. Japan: Leverage the results from RAMP 201J & RAMP 301 for potential approval in both KRAS mutant and wild - type recurrent LGSOC. Europe: Leverage results from RAMP 301 for potential approval in both KRAS mutant and wild - type recurrent LGSOC. 2028 2027 KRAS mt represents ~33% of the population, while the wt represents 67% and therefore there are many more addressable patients. Potential for Label and Geographic Expansion AVMAPKI FAKZYNJA CO - PACK Future Commercial Opportunity

16 AVMAPKI FAKZYNJA CO - PACK Finalist in the Best Product for Rare/Orphan Diseases category Breakthrough Honoree NORD Industry Innovation Award AVMAPKI FAKZYNJA CO - PACK Product Innovation Awards

17 VS - 7375, Oral KRAS G12D (ON/OFF) Inhibitor
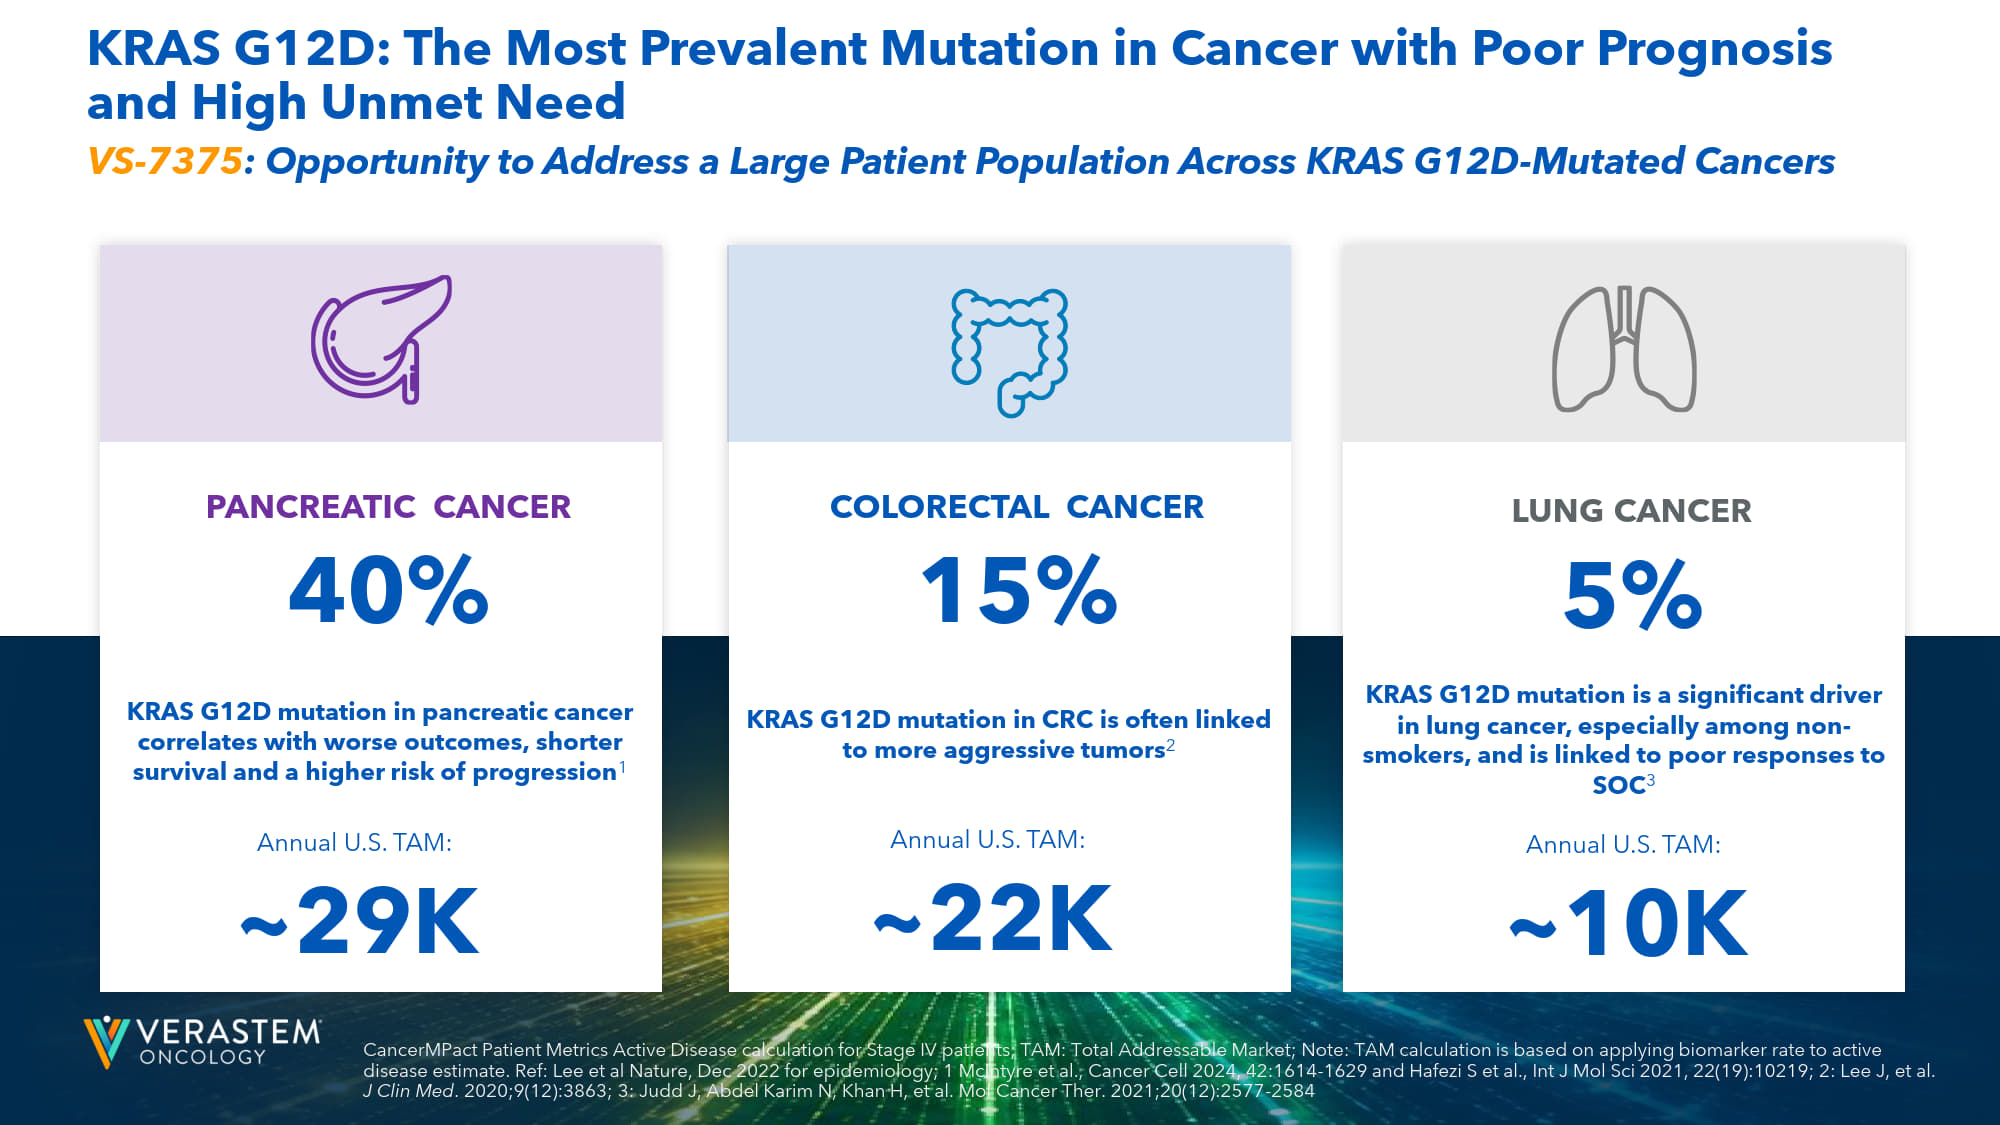
18 PANCREATIC CANCER 40% COLORECTAL CANCER 15% LUNG CANCER 5% KRAS G12D: The Most Prevalent Mutation in Cancer with Poor Prognosis and High Unmet Need Annual U.S. TAM: ~29K Annual U.S. TAM: ~22K Annual U.S. TAM: ~10K CancerMPact Patient Metrics Active Disease calculation for Stage IV patients; TAM: Total Addressable Market; Note: TAM calculation is bas ed on applying biomarker rate to active disease estimate. Ref: Lee et al Nature, Dec 2022 for epidemiology; 1 McIntyre et al., Cancer Cell 2024, 42:1614 - 1629 and Hafezi S et al., Int J M ol Sci 2021, 22(19):10219; 2: Lee J, et al. J Clin Med . 2020;9(12):3863; 3: Judd J, Abdel Karim N, Khan H, et al. Mol Cancer Ther. 2021;20(12):2577 - 2584 KRAS G12D mutation in pancreatic cancer correlates with worse outcomes, shorter survival and a higher risk of progression 1 KRAS G12D mutation is a significant driver in lung cancer, especially among non - smokers, and is linked to poor responses to SOC 3 KRAS G12D mutation in CRC is often linked to more aggressive tumors 2 VS - 7375 : Opportunity to Address a Large Patient Population Across KRAS G12D - Mutated Cancers
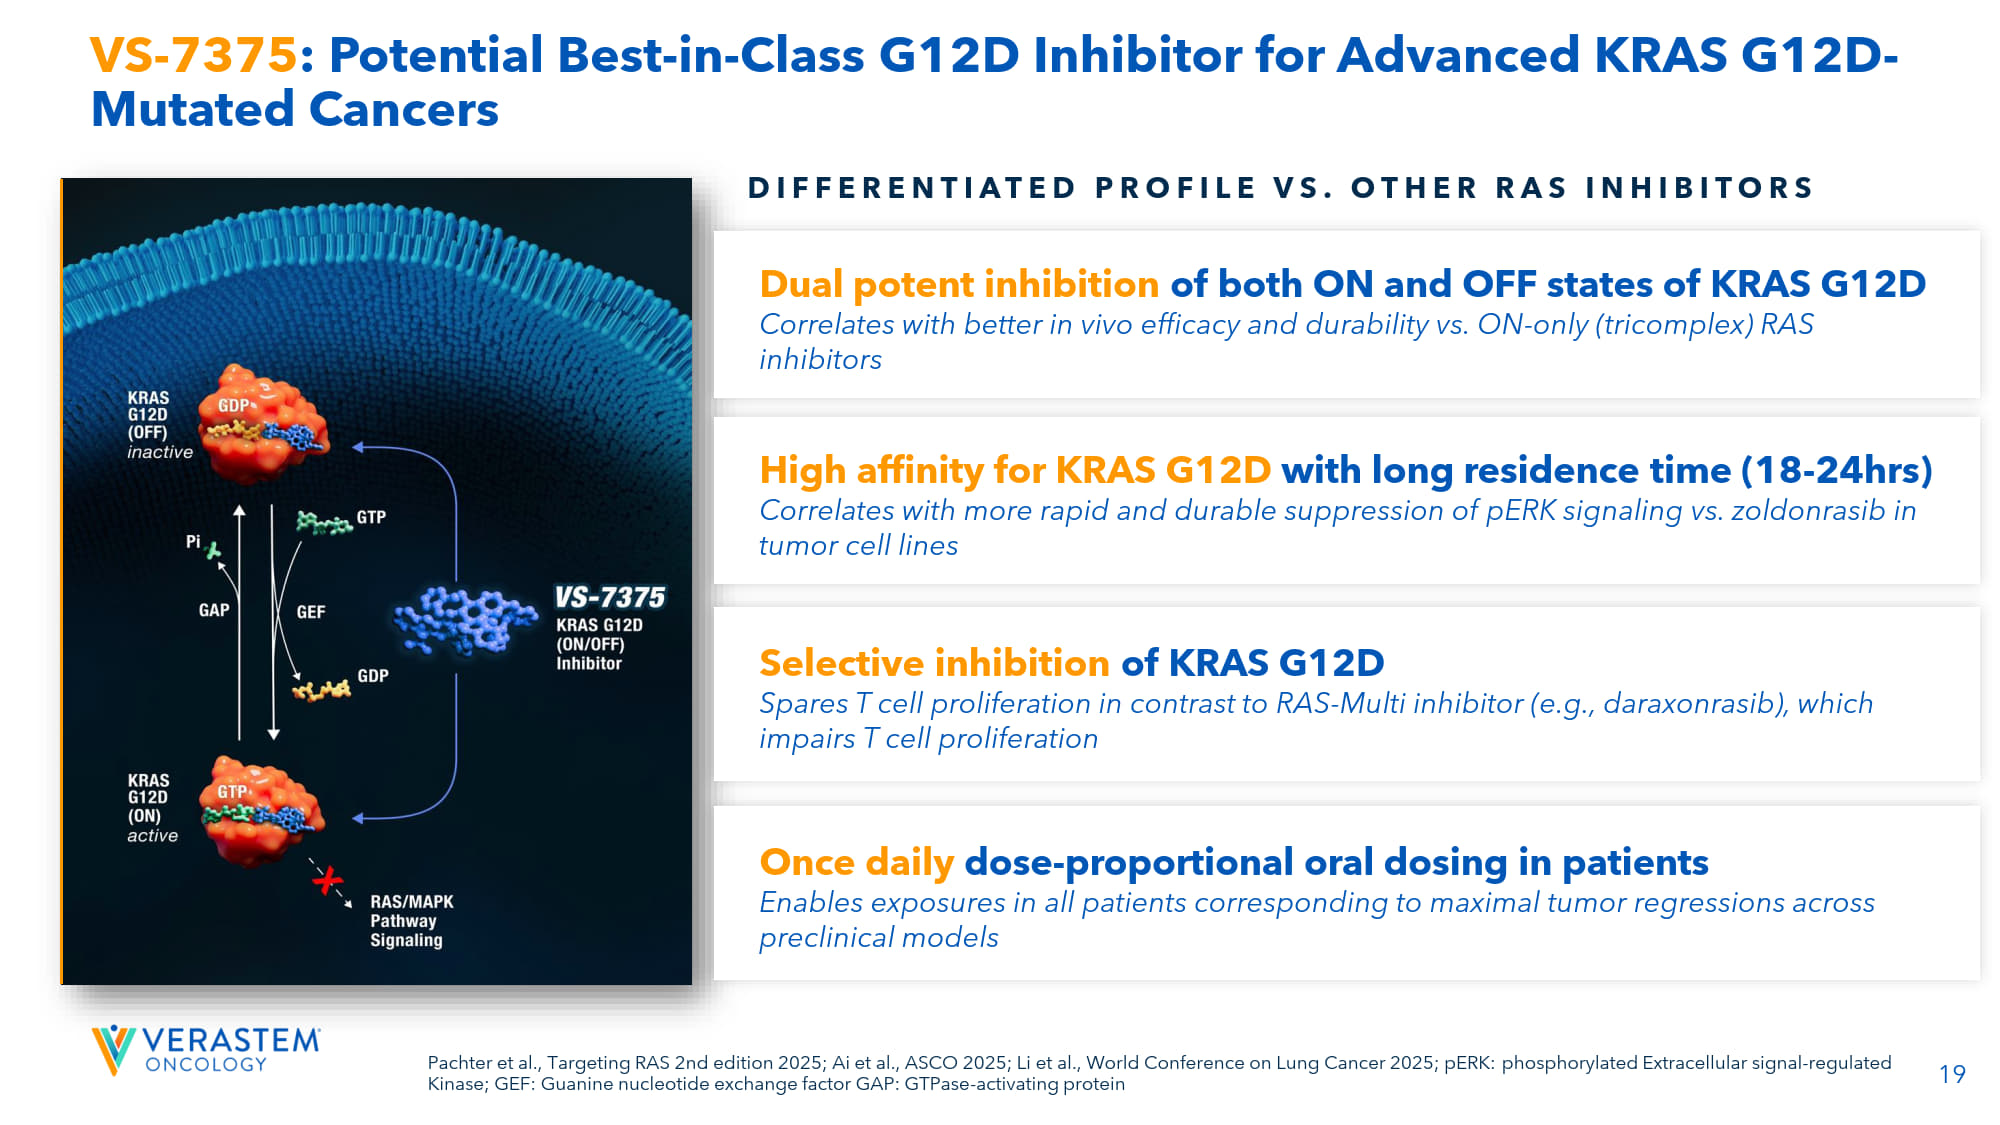
19 Pachter et al., Targeting RAS 2nd edition 2025; Ai et al., ASCO 2025; Li et al., World Conference on Lung Cancer 2025; pERK: pho sphorylated Extracellular signal - regulated Kinase; GEF: Guanine nucleotide exchange factor GAP: GTPase - activating protein VS - 7375 : Potential Best - in - Class G12D Inhibitor for Advanced KRAS G12D - Mutated Cancers DIFFERENTIATED PROFILE VS. OTHER RAS INHIBITORS Dual potent inhibition of both ON and OFF states of KRAS G12D Correlates with better in vivo efficacy and durability vs. ON - only (tricomplex) RAS inhibitors High affinity for KRAS G12D with long residence time (18 - 24hrs) Correlates with more rapid and durable suppression of pERK signaling vs. zoldonrasib in tumor cell lines Selective inhibition of KRAS G12D Spares T cell proliferation in contrast to RAS - Multi inhibitor (e.g., daraxonrasib), which impairs T cell proliferation Once daily dose - proportional oral dosing in patients Enables exposures in all patients corresponding to maximal tumor regressions across preclinical models
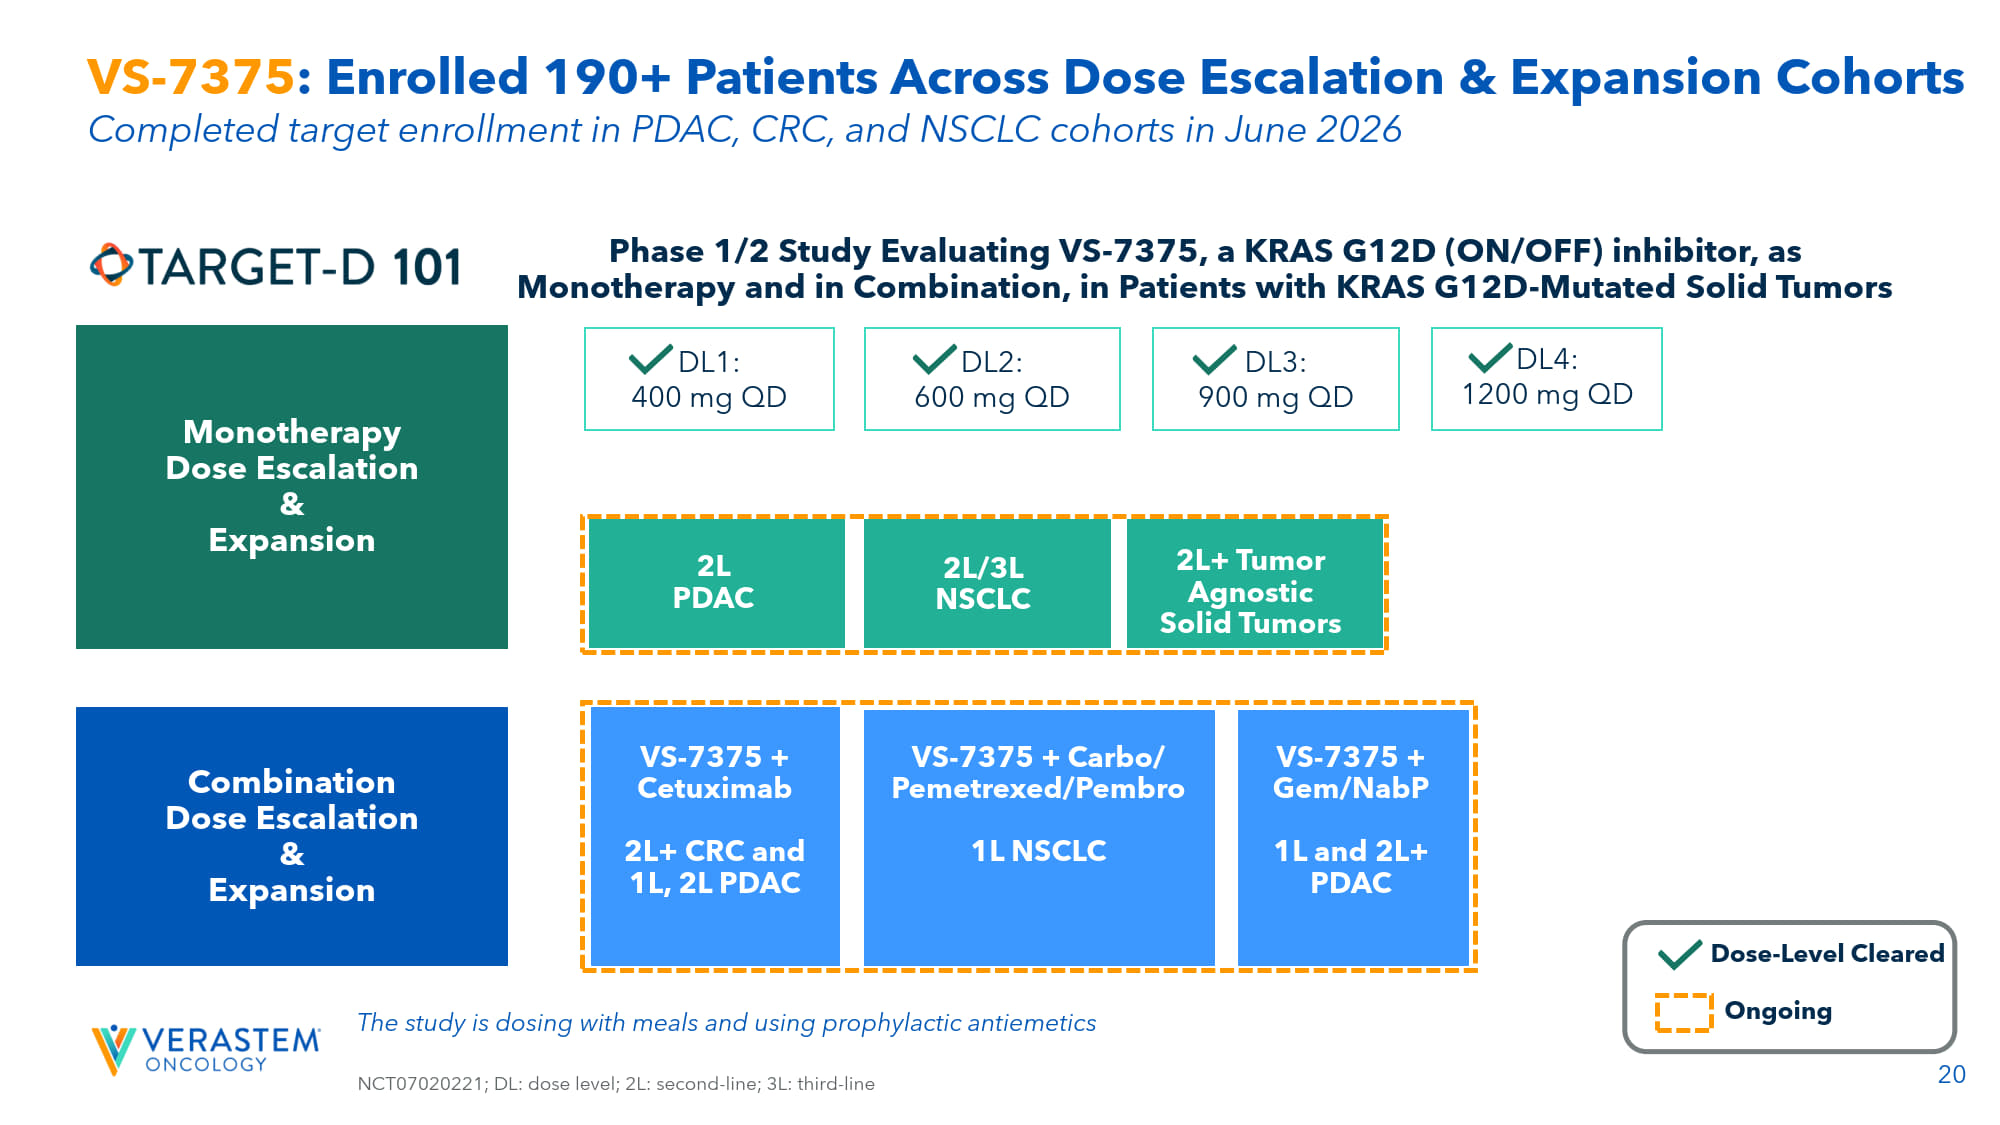
20 VS - 7375 : Enrolled 190+ Patients Across Dose Escalation & Expansion Cohorts Phase 1/2 Study Evaluating VS - 7375, a KRAS G12D (ON/OFF) inhibitor, as Monotherapy and in Combination, in Patients with KRAS G12D - Mutated Solid Tumors The study is dosing with meals and using prophylactic antiemetics NCT07020221; DL: dose level; 2L: second - line; 3L: third - line Monotherapy Dose Escalation & Expansion DL2: 600 mg QD DL3: 900 mg QD DL1: 400 mg QD 2L+ Tumor Agnostic Solid Tumors 2L/3L NSCLC 2L PDAC DL4: 1200 mg QD Combination Dose Escalation & Expansion VS - 7375 + Cetuximab 2L+ CRC and 1L, 2L PDAC VS - 7375 + Carbo/ Pemetrexed/ Pembro 1L NSCLC VS - 7375 + Gem/ NabP 1L and 2L+ PDAC Dose - Level Cleared Ongoing Completed target enrollment in PDAC, CRC, and NSCLC cohorts in June 2026
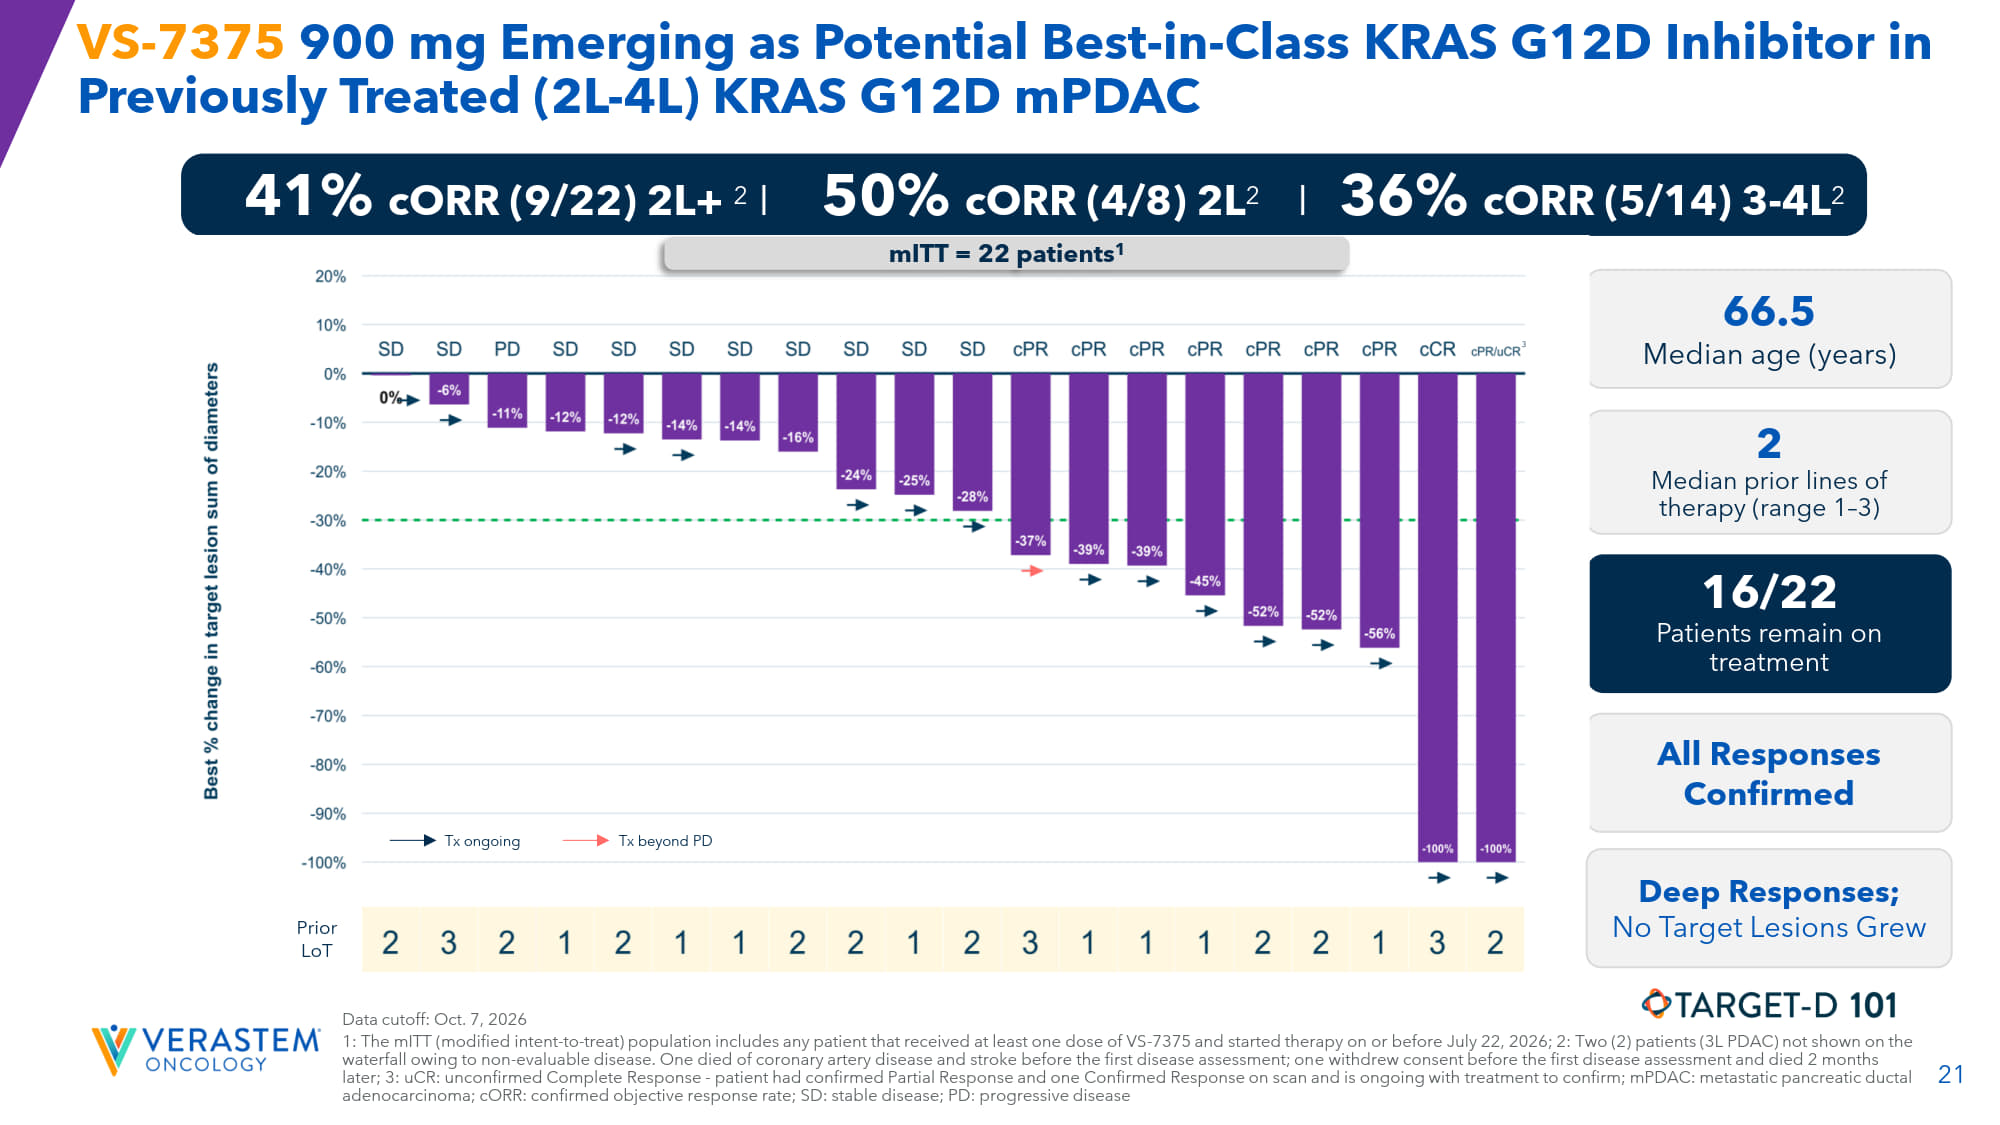
21 VS - 7375 900 mg Emerging as Potential Best - in - Class KRAS G12D Inhibitor in Previously Treated (2L - 4L) KRAS G12D mPDAC Data cutoff: Oct. 7, 2026 1: The mITT (modified intent - to - treat) population includes any patient that received at least one dose of VS - 7375 and started therapy on or before July 22, 2026; 2: Two (2) patients (3L PDAC) not shown on the waterfall owing to non - evaluable disease. One died of coronary artery disease and stroke before the first disease assessment; on e withdrew consent before the first disease assessment and died 2 months later; 3: uCR : unconfirmed Complete Response - patient had confirmed Partial Response and one Confirmed Response on scan and is ongoing with treatment to confirm; mPDAC: metastatic pancreatic ductal adenocarcinoma; cORR : confirmed objective response rate; SD: stable disease; PD: progressive disease 66.5 Median age (years) 2 Median prior lines of therapy (range 1 – 3) 16/22 Patients remain on treatment All Responses Confirmed 41% cORR (9/22) 2L+ 2 I 50% cORR (4/8) 2L 2 I 36% cORR (5/14) 3 - 4L 2 Prior LoT mITT = 22 patients 1 Deep Responses; No Target Lesions Grew Tx ongoing Tx beyond PD 3
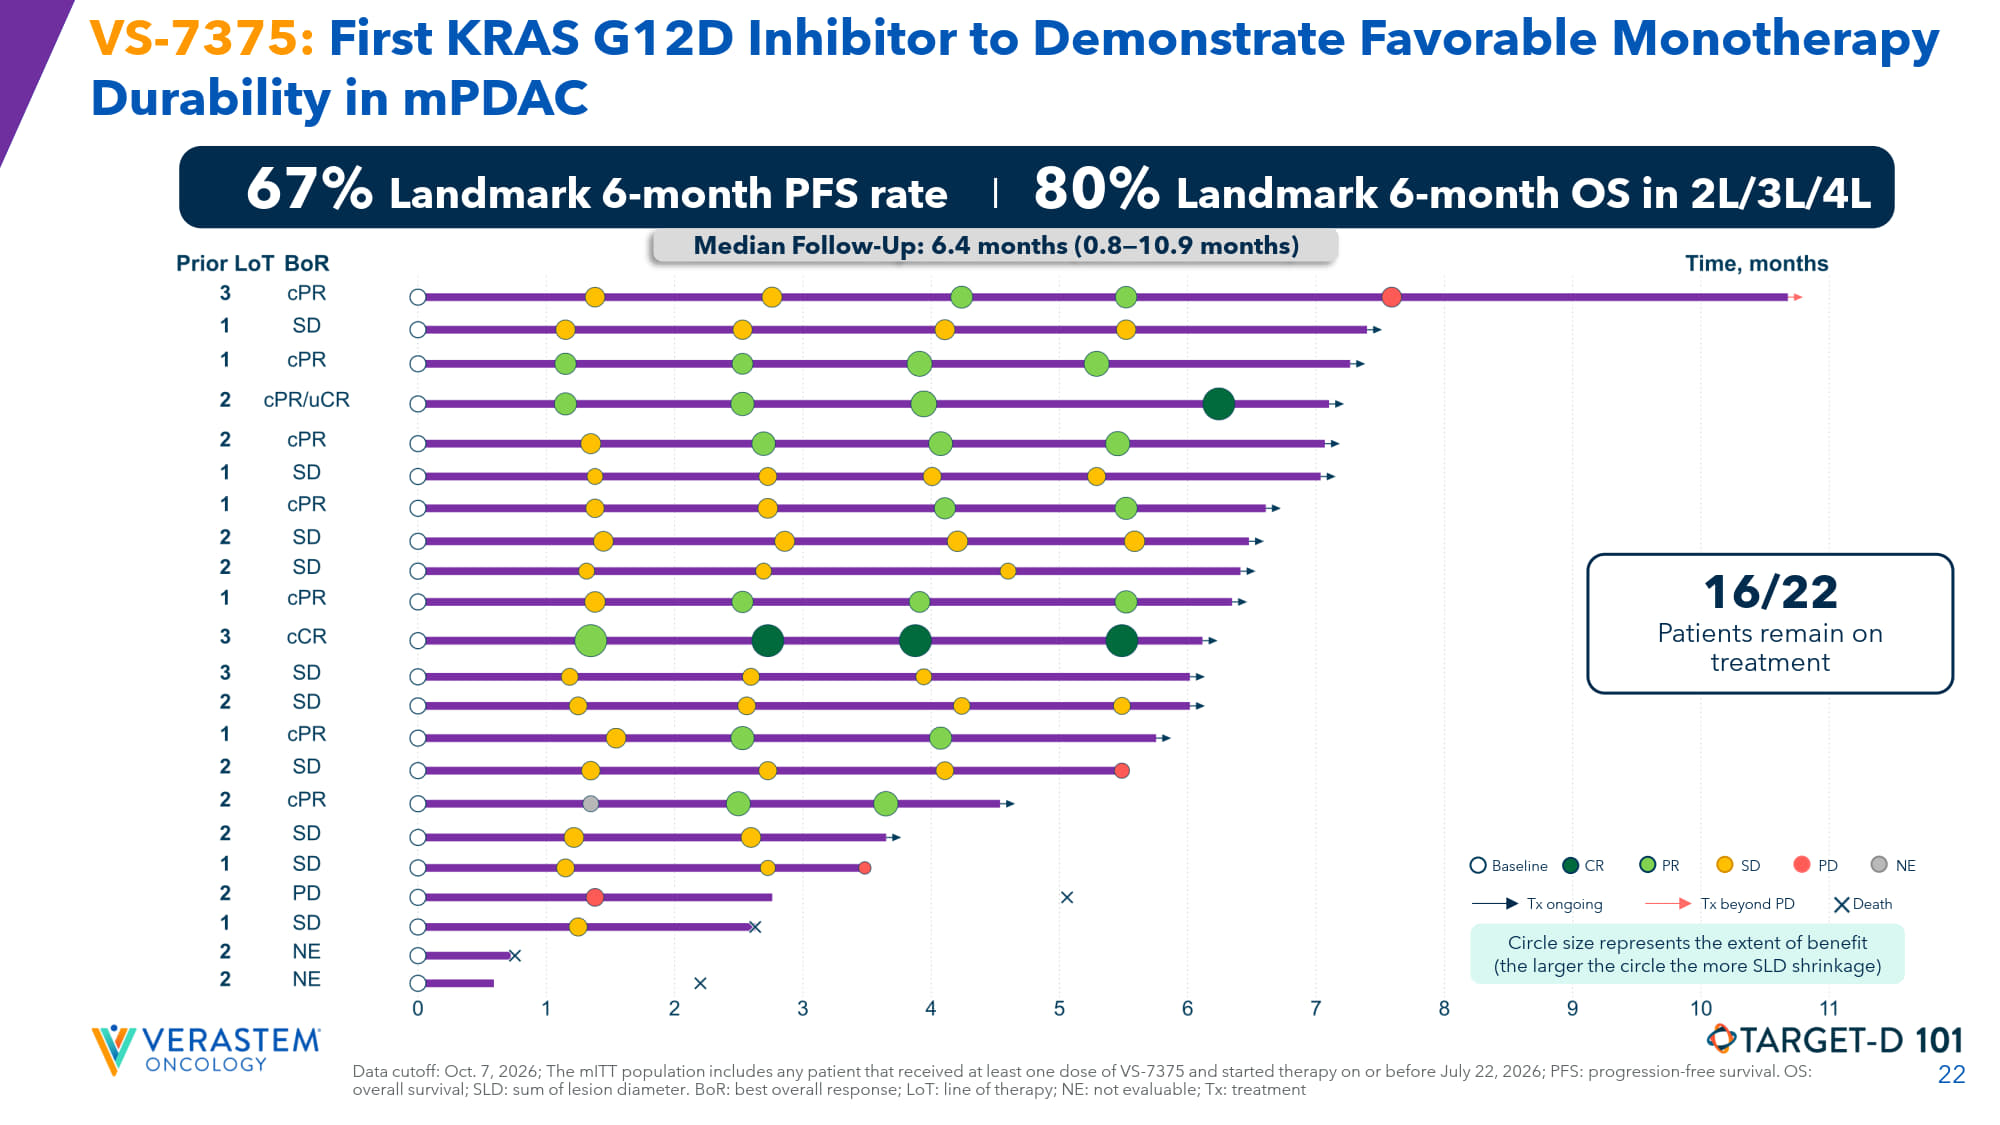
22 VS - 7375: First KRAS G12D Inhibitor to Demonstrate Favorable Monotherapy Durability in mPDAC 67% Landmark 6 - month PFS rate I 80% Landmark 6 - month OS in 2L/3L/4L Data cutoff: Oct. 7, 2026; The mITT population includes any patient that received at least one dose of VS - 7375 and started therapy on or before July 22, 2026; PFS: progression - free survival. OS: overall survival; SLD: sum of lesion diameter. BoR : best overall response; LoT : line of therapy; NE: not evaluable; Tx: treatment Median Follow - Up: 6.4 months (0.8 — 10.9 months) 16/22 Patients remain on treatment Baseline CR PR SD PD NE Tx ongoing Tx beyond PD Death Circle size represents the extent of benefit (the larger the circle the more SLD shrinkage)
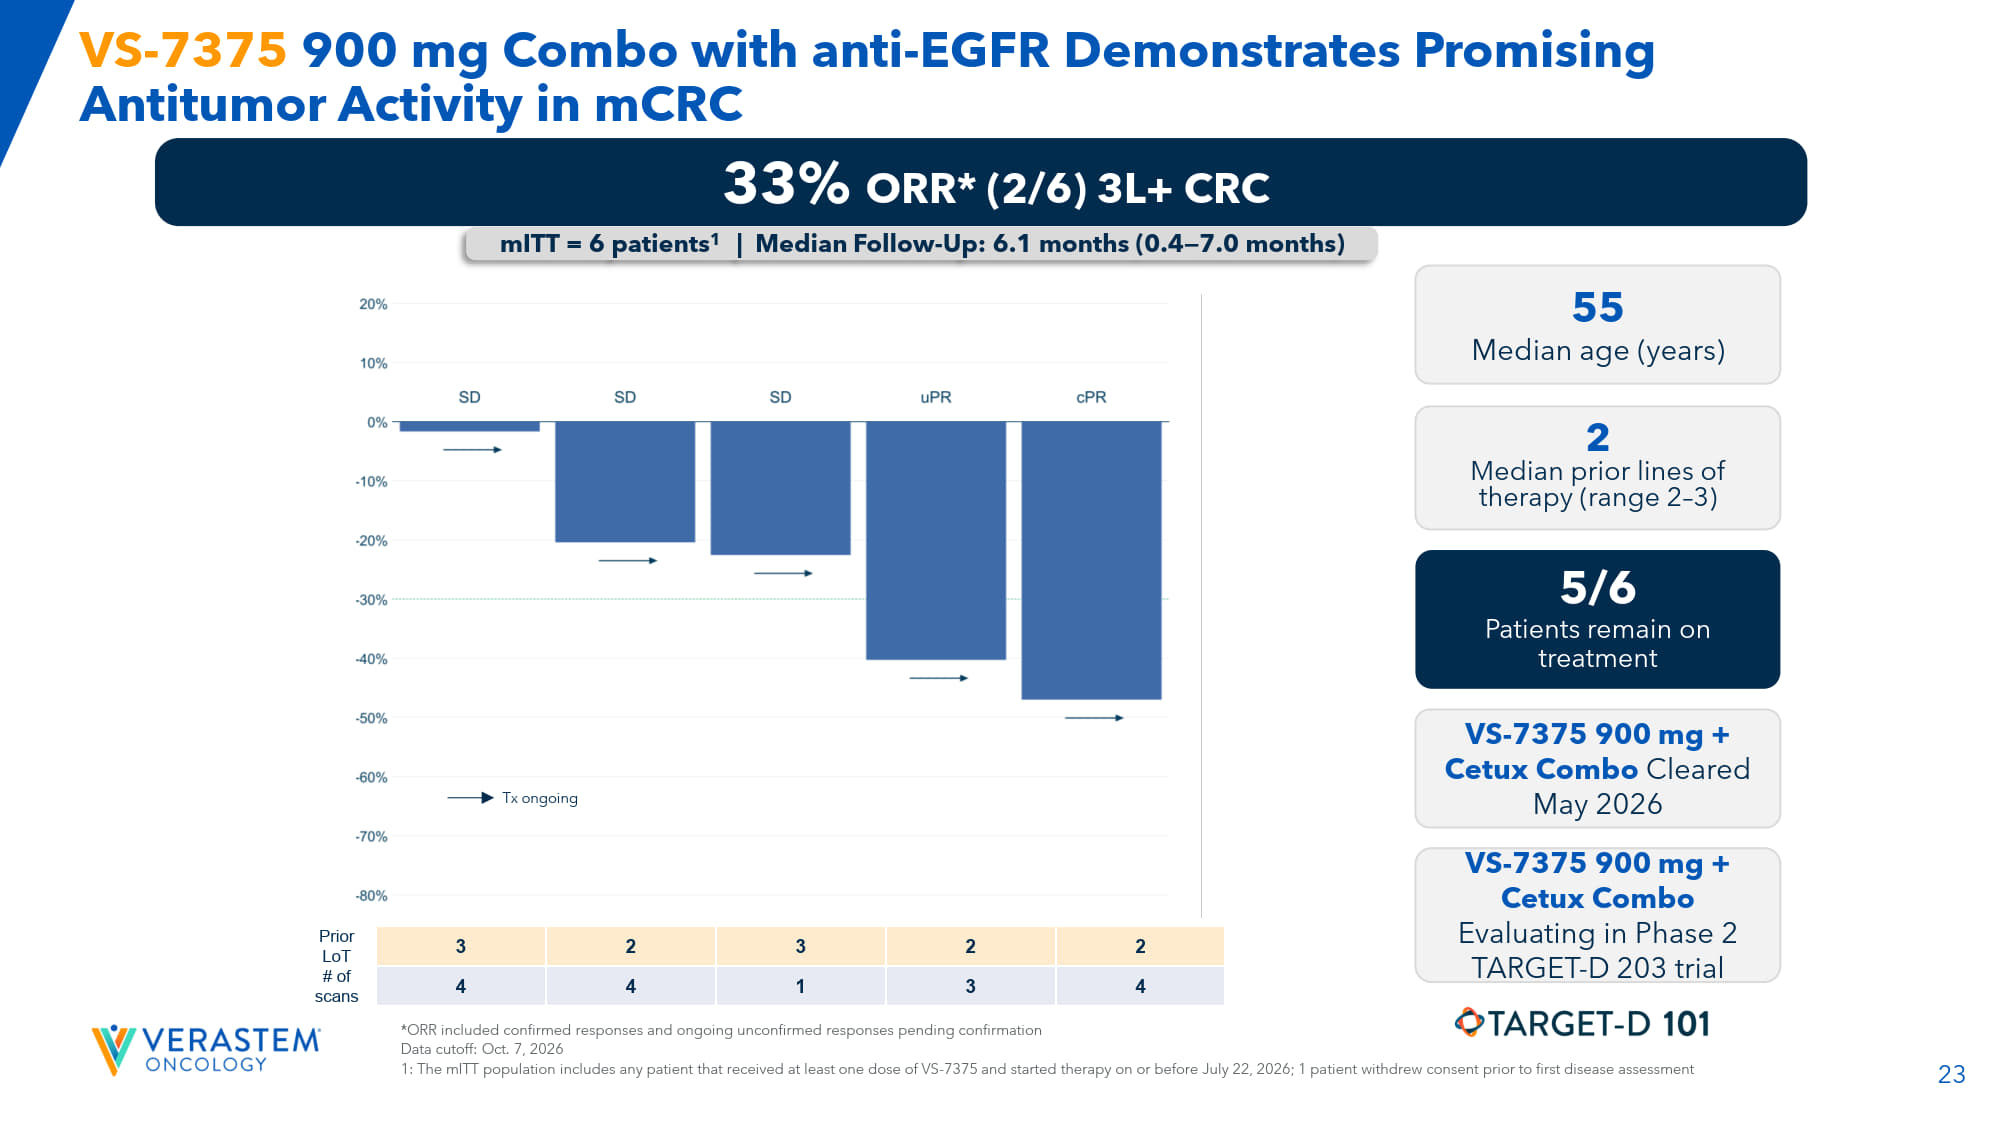
23 *ORR included confirmed responses and ongoing unconfirmed responses pending confirmation Data cutoff: Oct. 7, 2026 1: The mITT population includes any patient that received at least one dose of VS - 7375 and started therapy on or before July 22, 2026; 1 pa tient withdrew consent prior to first disease assessment VS - 7375 900 mg Combo with anti - EGFR Demonstrates Promising Antitumor Activity in mCRC 2 2 3 2 3 Prior LoT 4 3 1 4 4 # of scans 33% ORR* (2/6) 3L+ CRC 55 Median age (years) 2 Median prior lines of therapy (range 2 – 3) 5/6 Patients remain on treatment VS - 7375 900 mg + Cetux Combo Cleared May 2026 VS - 7375 900 mg + Cetux Combo Evaluating in Phase 2 TARGET - D 203 trial mITT = 6 patients 1 | Median Follow - Up: 6.1 months (0.4 — 7.0 months) Tx ongoing
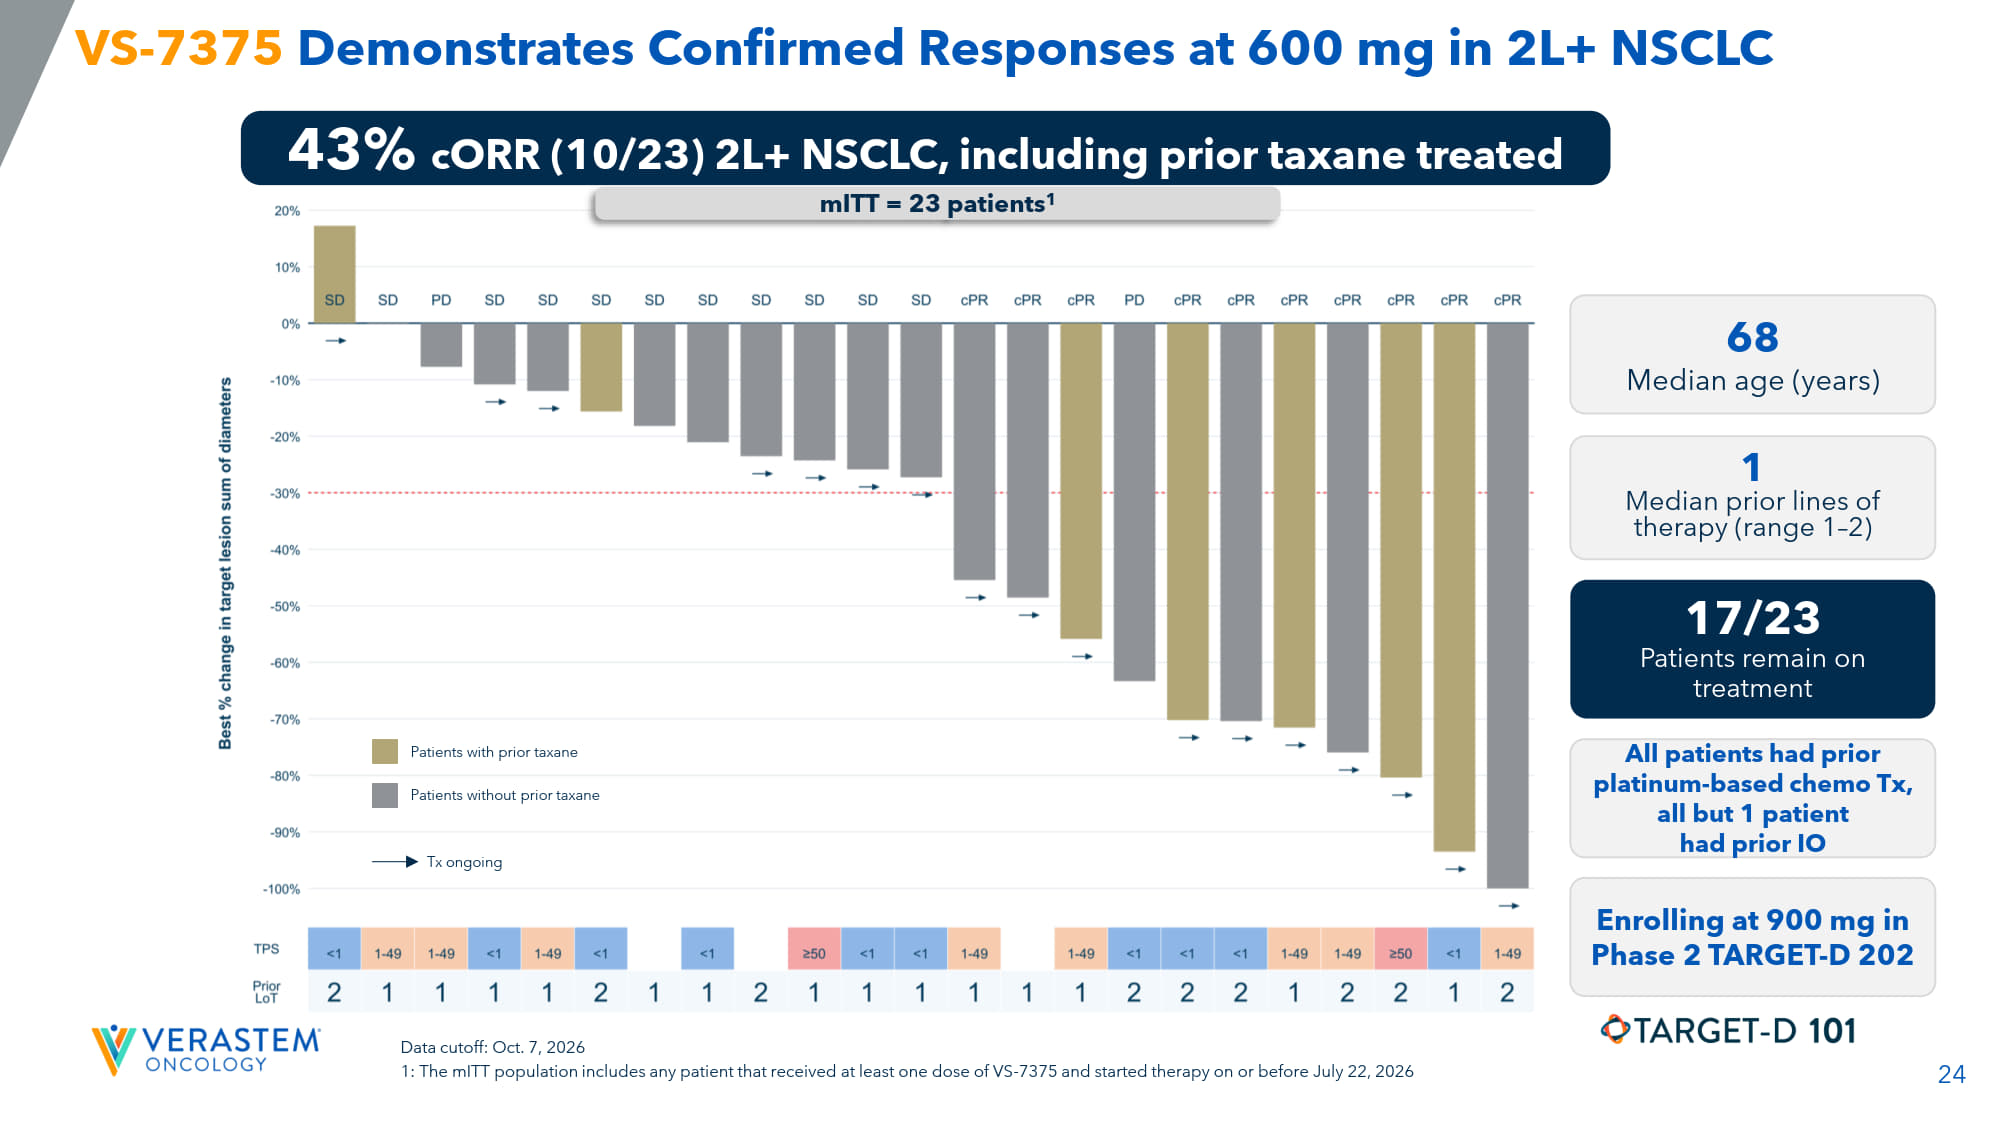
24 VS - 7375 Demonstrates Confirmed Responses at 600 mg in 2L+ NSCLC 43% c ORR (10/23) 2L+ NSCLC, including prior taxane treated 68 Median age (years) 1 Median prior lines of therapy (range 1 – 2) 17/23 Patients remain on treatment All patients had prior platinum - based chemo Tx, all but 1 patient had prior IO Enrolling at 900 mg in Phase 2 TARGET - D 202 mITT = 23 patients 1 Data cutoff: Oct. 7, 2026 1: The mITT population includes any patient that received at least one dose of VS - 7375 and started therapy on or before July 22, 2026 Tx ongoing Patients with prior taxane Patients without prior taxane
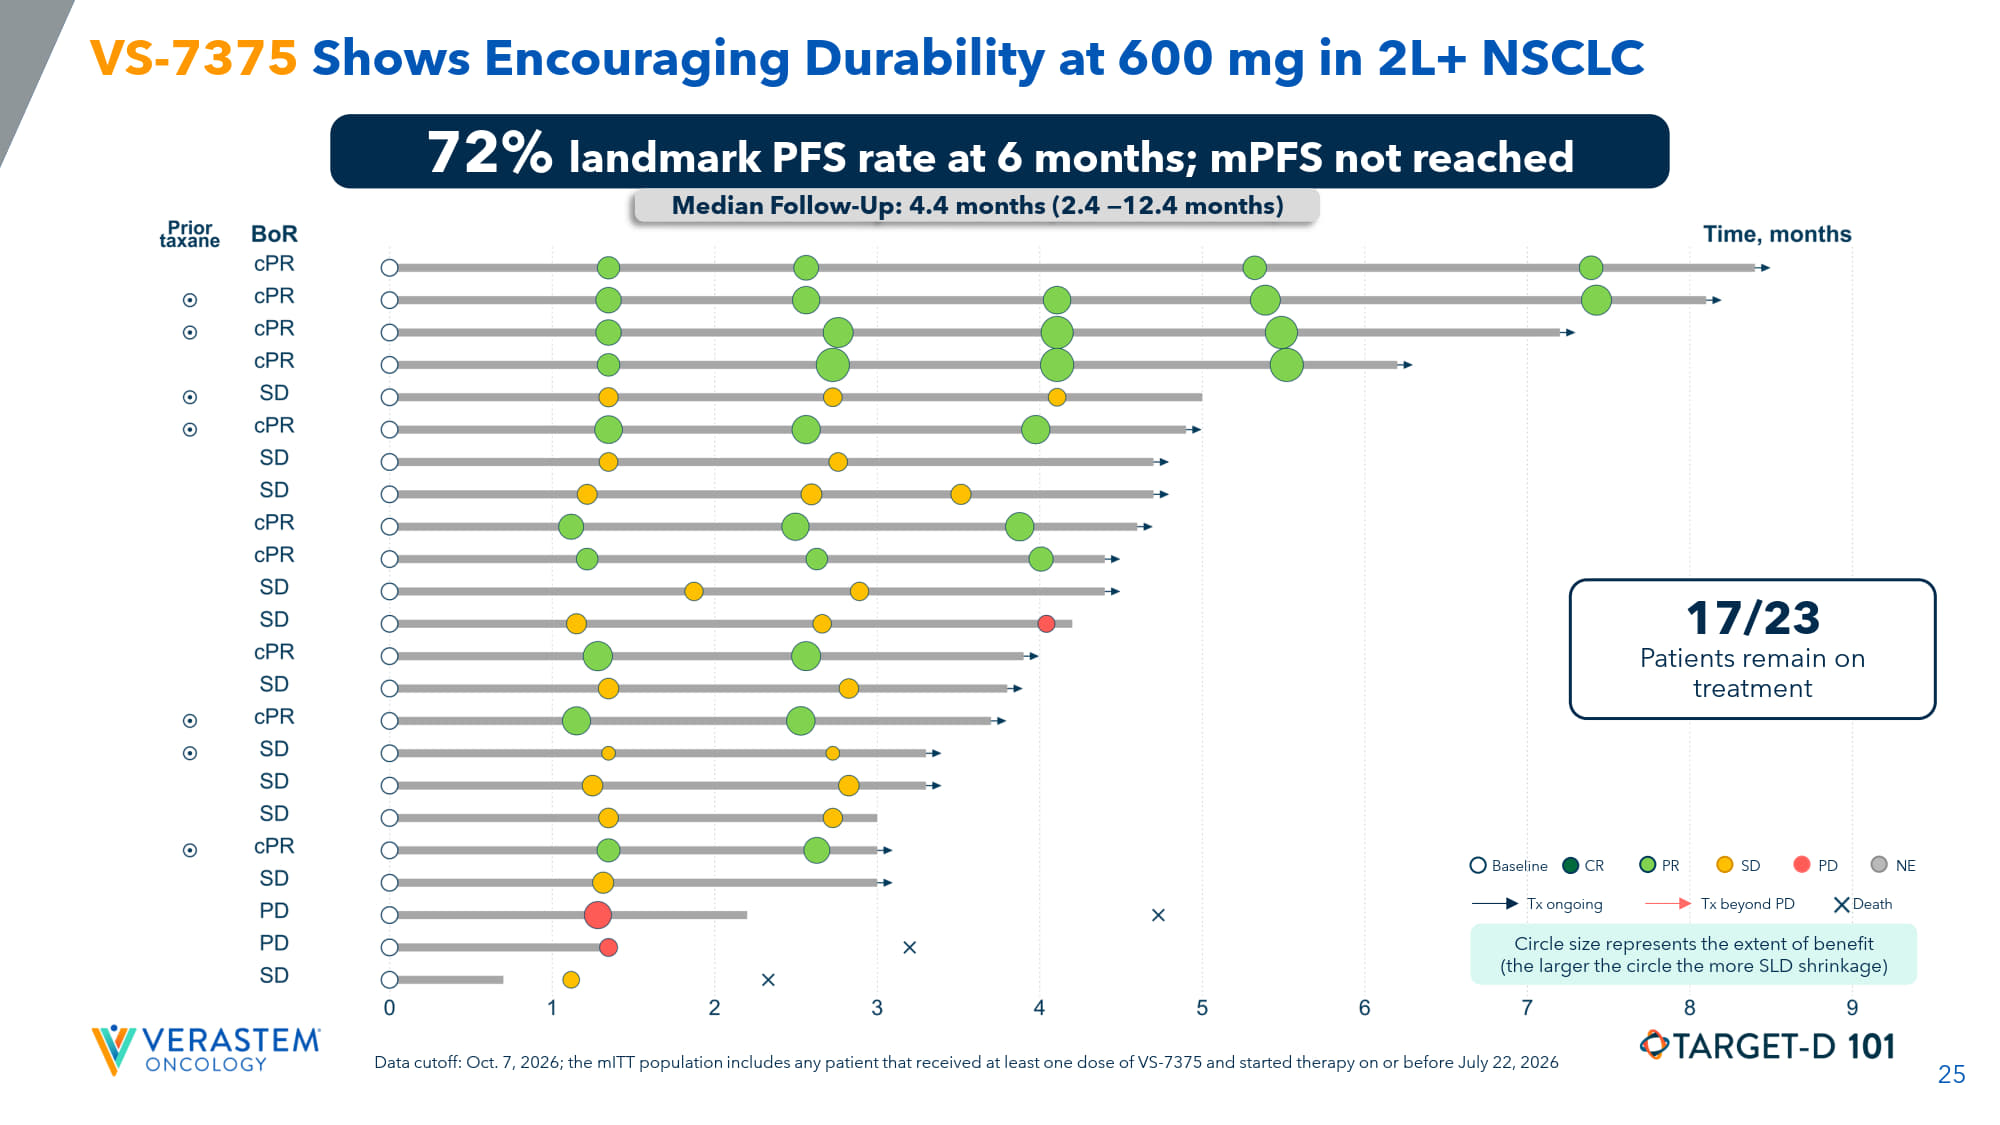
25 VS - 7375 Shows Encouraging Durability at 600 mg in 2L+ NSCLC 72% landmark PFS rate at 6 months; mPFS not reached Median Follow - Up: 4.4 months (2.4 — 12.4 months) 17/23 Patients remain on treatment Baseline CR PR SD PD NE Tx ongoing Tx beyond PD Death Circle size represents the extent of benefit (the larger the circle the more SLD shrinkage) Data cutoff: Oct. 7, 2026; the mITT population includes any patient that received at least one dose of VS - 7375 and started therapy on or before July 22, 2026
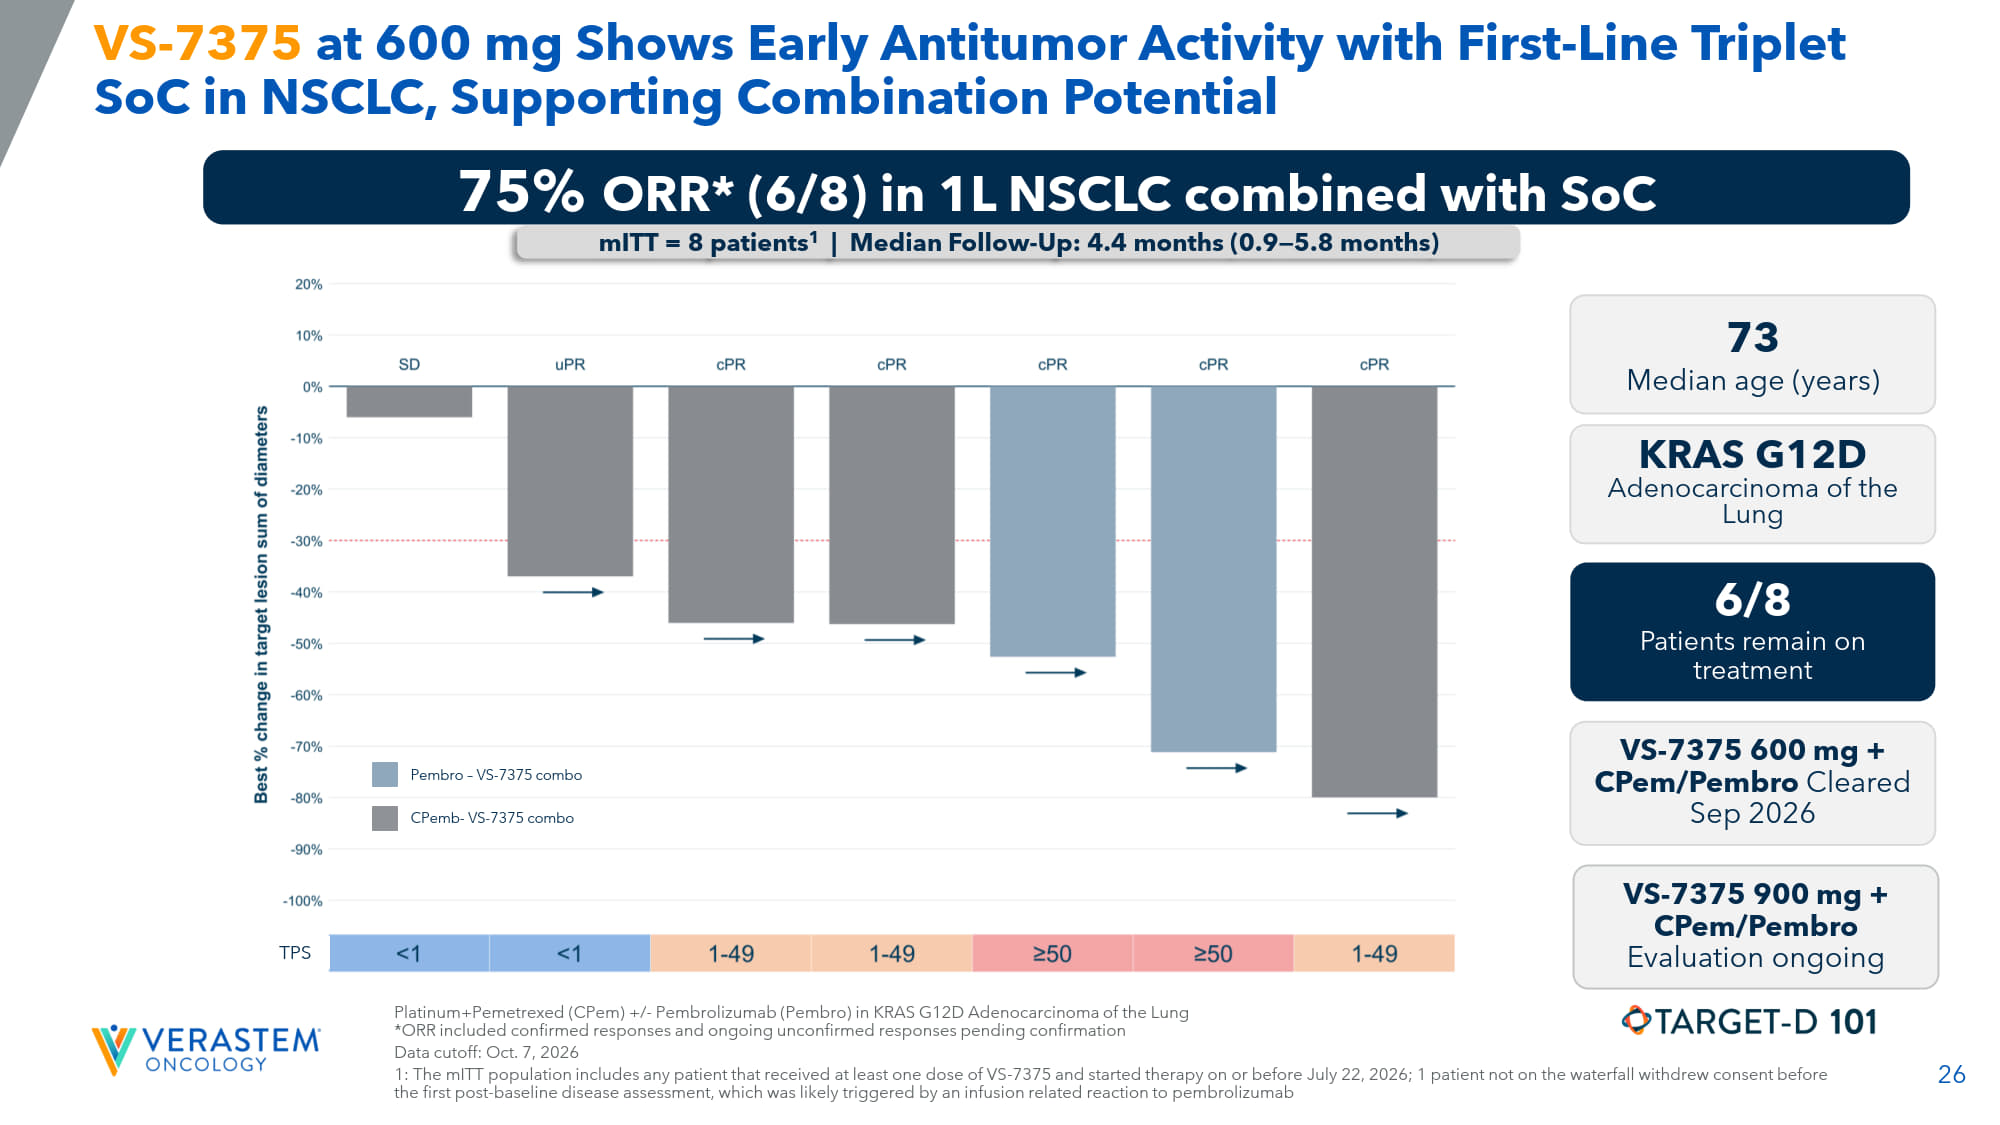
26 TPS VS - 7375 at 600 mg Shows Early Antitumor Activity with First - Line Triplet SoC in NSCLC, Supporting Combination Potential Platinum+Pemetrexed ( CPem ) +/ - Pembrolizumab ( Pembro ) in KRAS G12D Adenocarcinoma of the Lung *ORR included confirmed responses and ongoing unconfirmed responses pending confirmation Data cutoff: Oct. 7, 2026 1: The mITT population includes any patient that received at least one dose of VS - 7375 and started therapy on or before July 22, 2026; 1 pa tient not on the waterfall withdrew consent before the first post - baseline disease assessment, which was likely triggered by an infusion related reaction to pembrolizumab 75% ORR* (6/8) in 1L NSCLC combined with SoC mITT = 8 patients 1 | Median Follow - Up: 4.4 months (0.9 — 5.8 months) 73 Median age (years) 6/8 Patients remain on treatment VS - 7375 600 mg + CPem / Pembro Cleared Sep 2026 VS - 7375 900 mg + CPem/ Pembro Evaluation ongoing KRAS G12D Adenocarcinoma of the Lung Pembro – VS - 7375 combo CPemb - VS - 7375 combo
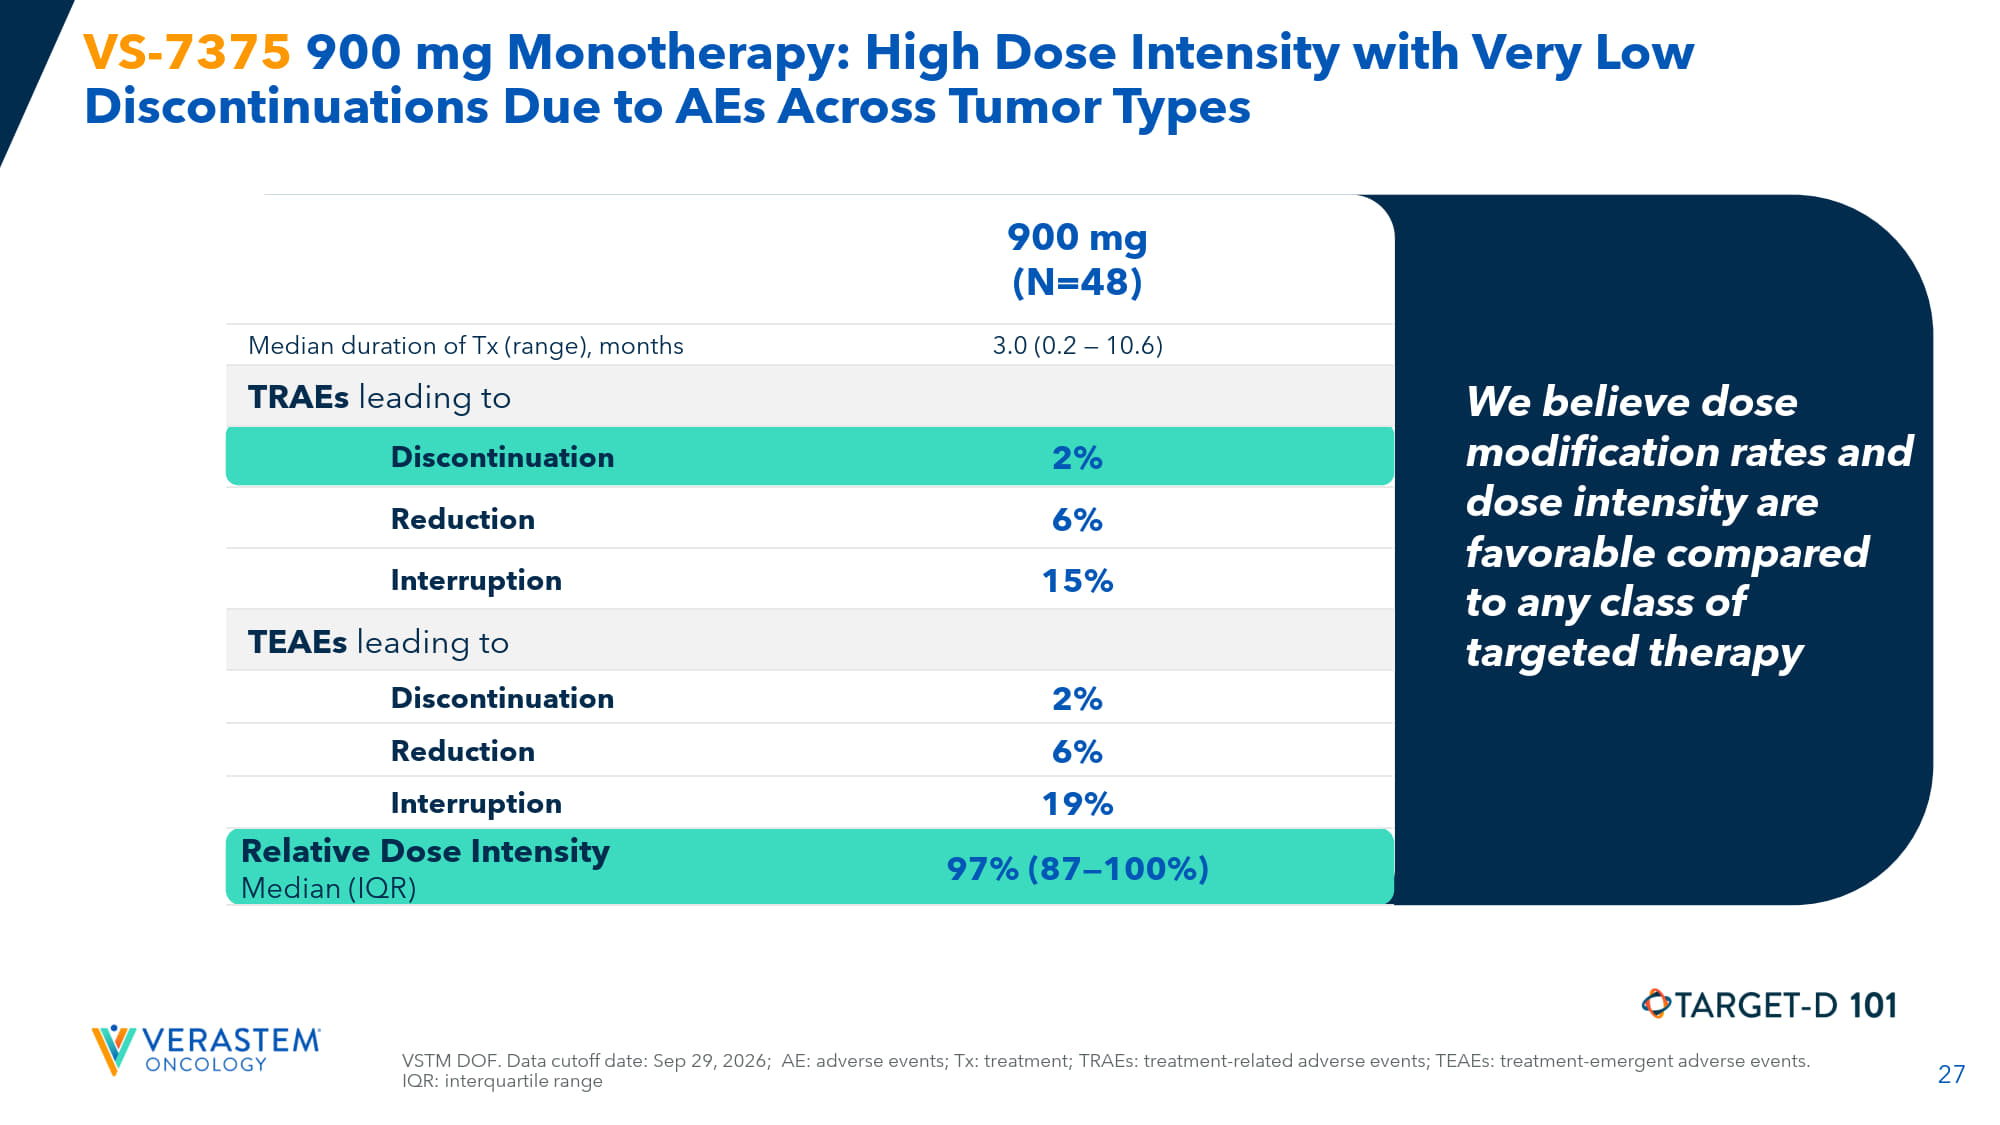
27 VSTM DOF. Data cutoff date: Sep 29, 2026; AE: adverse events; Tx: treatment; TRAEs: treatment - related adverse events; TEAEs: treatment - emergent adverse events. IQR: interquartile range VS - 7375 900 mg Monotherapy: High Dose Intensity with Very Low Discontinuations Due to AEs Across Tumor Types 900 mg (N=48) 3.0 (0.2 — 10.6) Median duration of Tx (range), months TRAEs leading to 2% Discontinuation 6% Reduction 15% Interruption TEAEs leading to 2% Discontinuation 6% Reduction 19% Interruption 97% (87 — 100%) Relative Dose Intensity Median (IQR) We believe dose modification rates and dose intensity are favorable compared to any class of targeted therapy
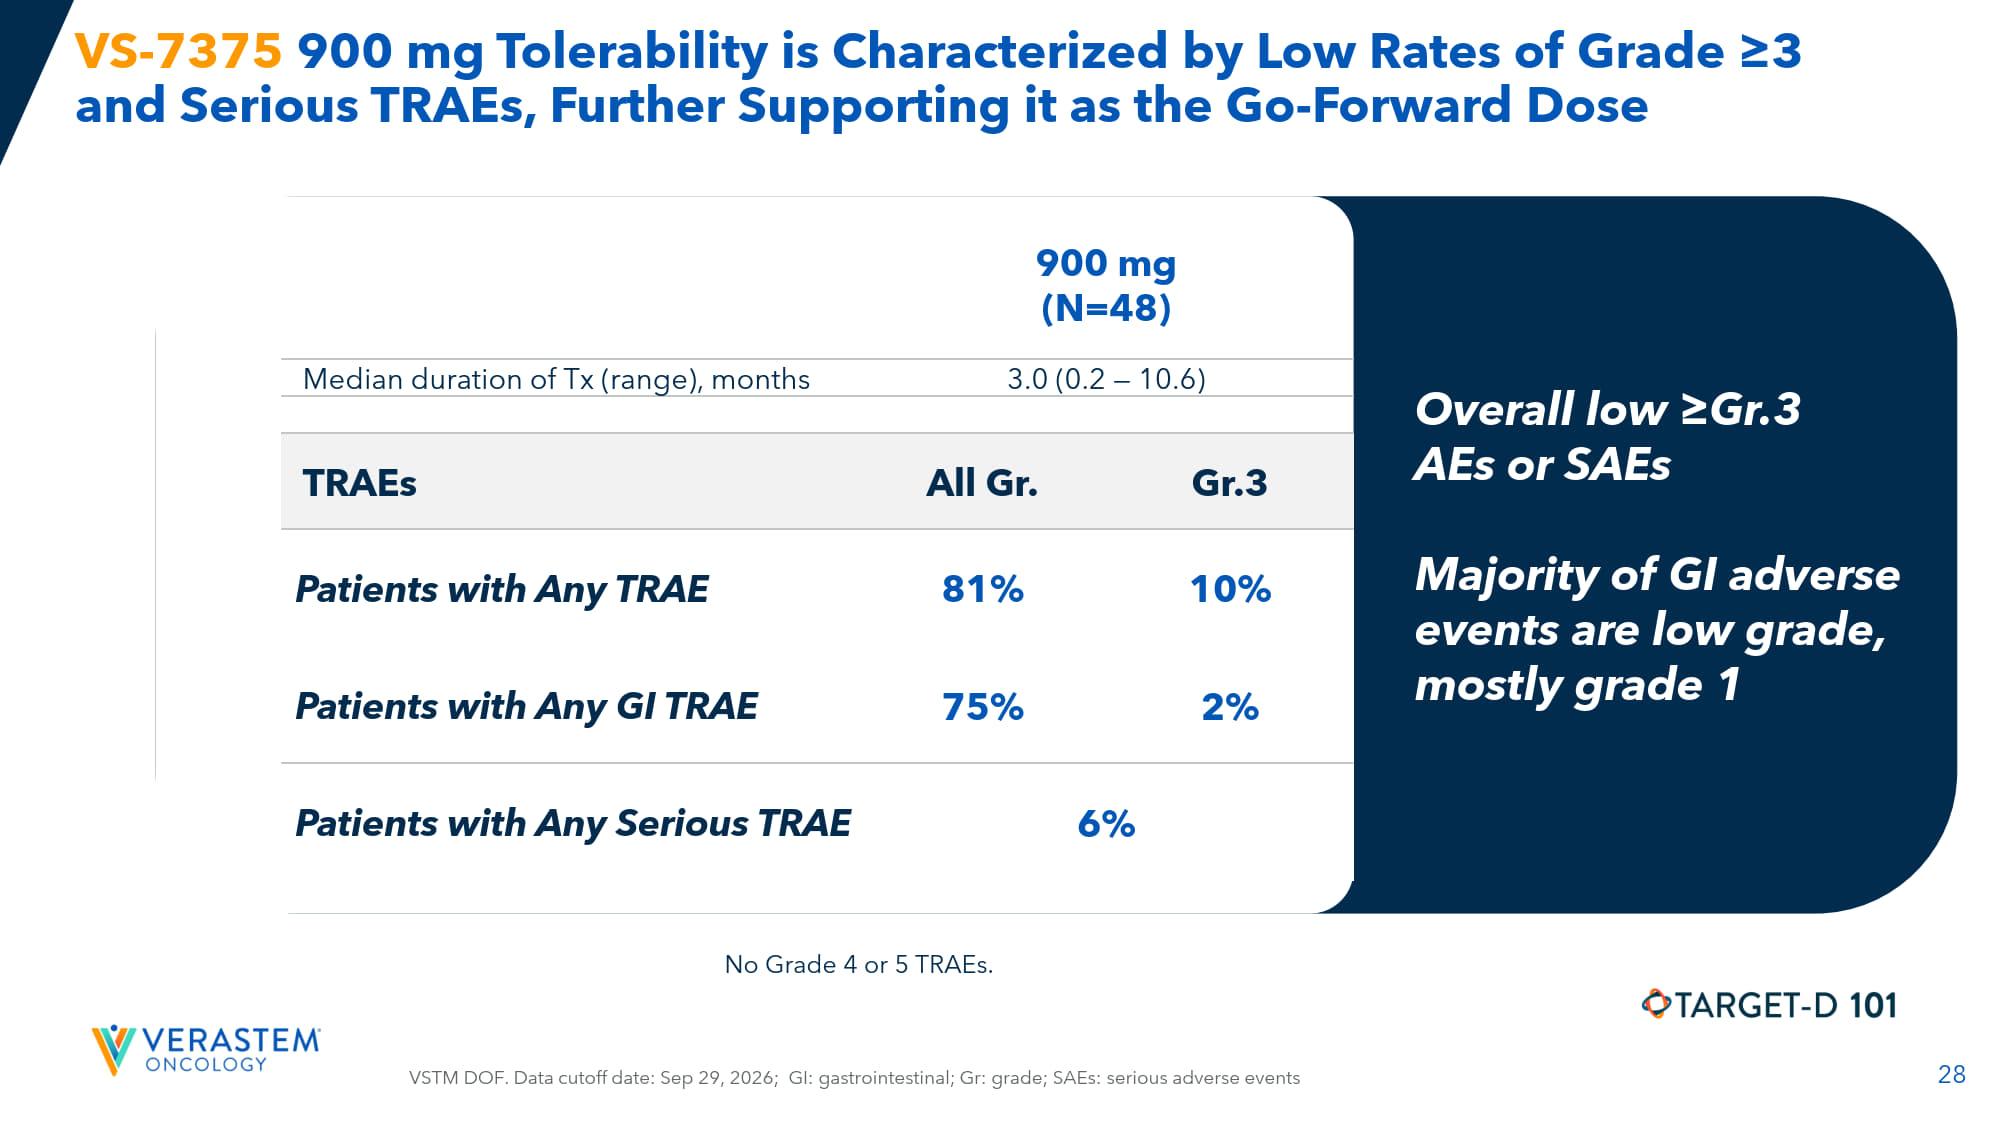
28 VS - 7375 900 mg Tolerability is Characterized by Low Rates of Grade ≥3 and Serious TRAEs, Further Supporting it as the Go - Forward Dose 900 mg (N=48) 3.0 (0.2 — 10.6) Median duration of Tx (range), months Gr.3 All Gr. TRAEs 10% 81% Patients with Any TRAE 2% 75% Patients with Any GI TRAE 6% Patients with Any Serious TRAE Overall low ≥Gr.3 AEs or SAEs Majority of GI adverse events are low grade, mostly grade 1 VSTM DOF. Data cutoff date: Sep 29, 2026; GI: gastrointestinal; Gr: grade; SAEs: serious adverse events No Grade 4 or 5 TRAEs.
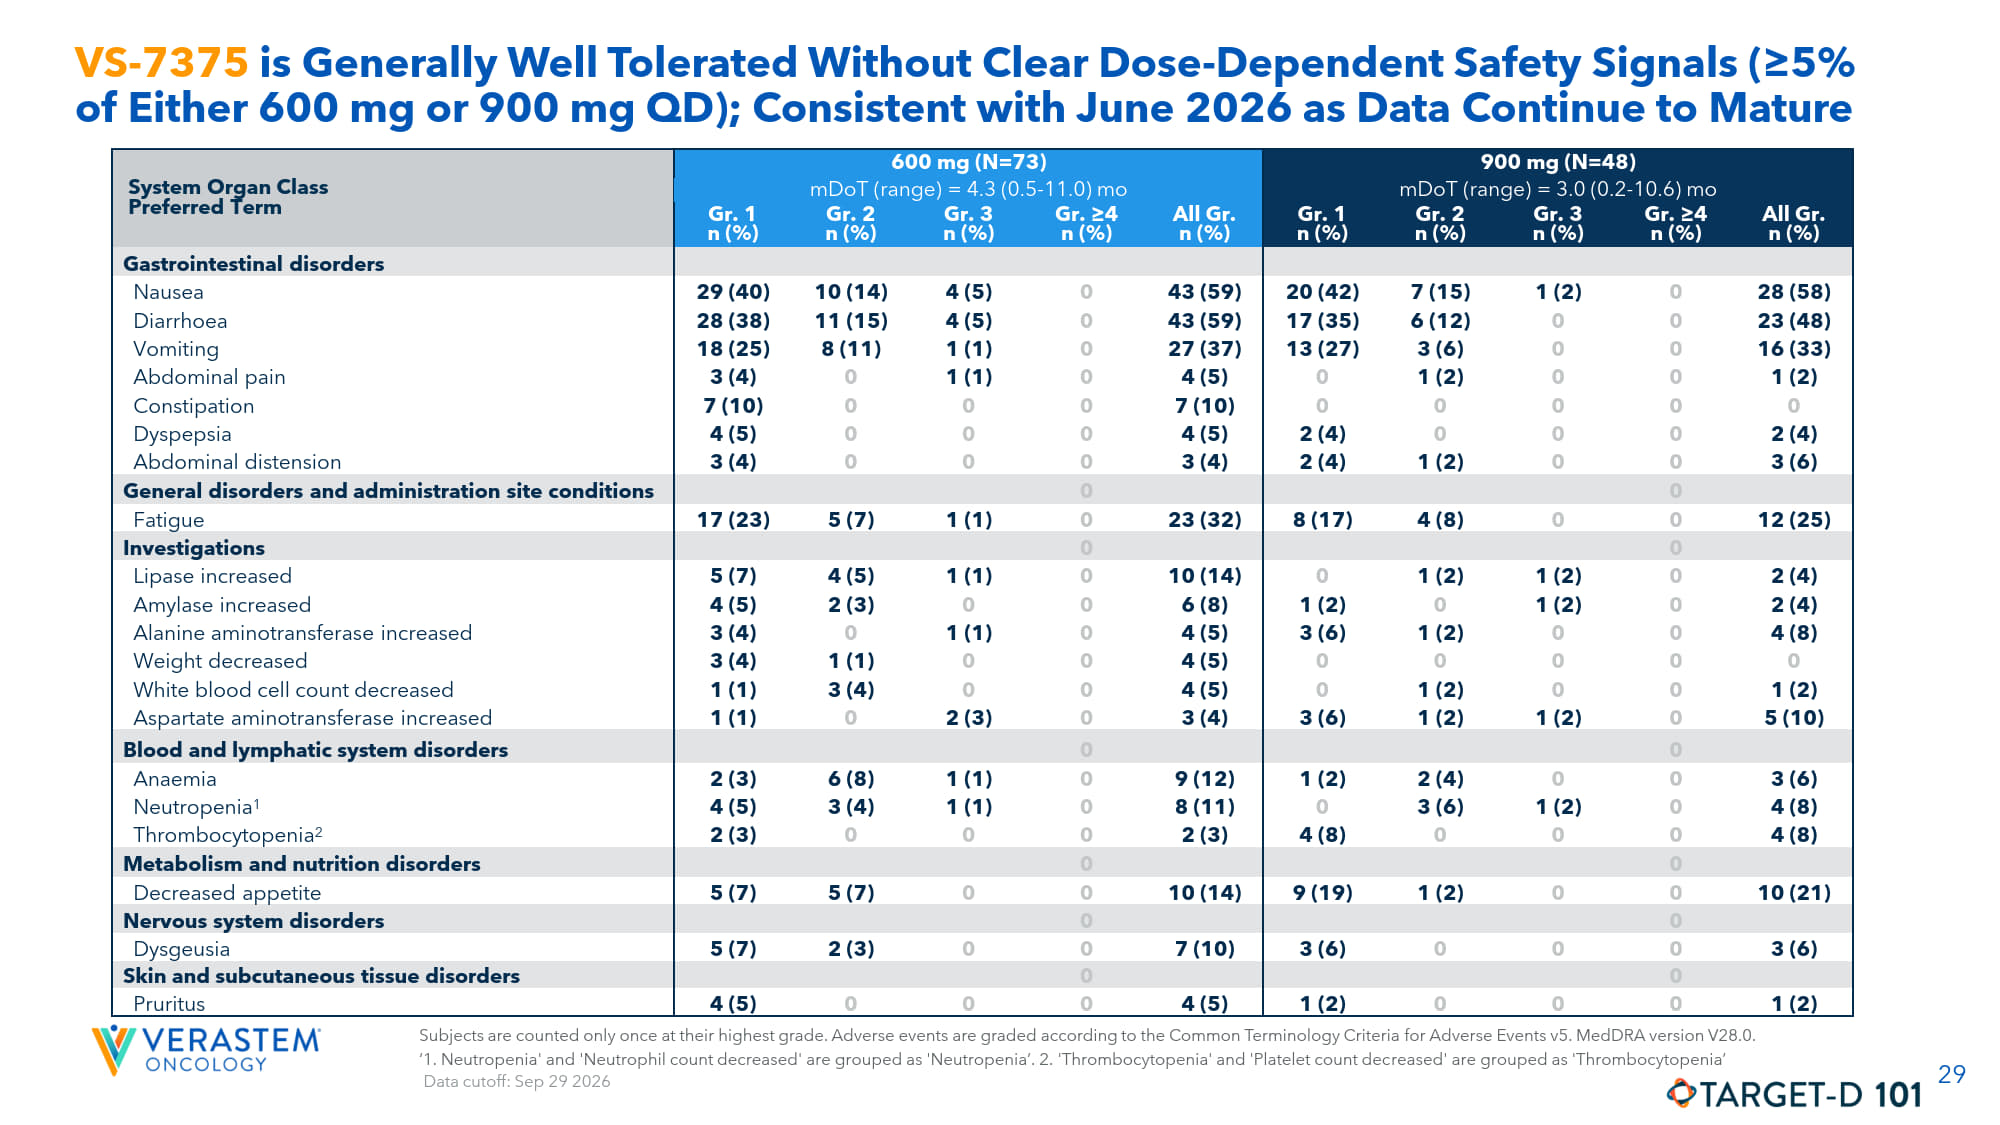
29 VS - 7375 is Generally Well Tolerated Without Clear Dose - Dependent Safety Signals (≥5% of Either 600 mg or 900 mg QD); Consistent with June 2026 as Data Continue to Mature 900 mg (N=48) 600 mg (N=73) System Organ Class Preferred Term mDoT (range) = 3.0 (0.2 - 10.6) mo mDoT (range) = 4.3 (0.5 - 11.0) mo All Gr. n (%) Gr. ≥4 n (%) Gr. 3 n (%) Gr. 2 n (%) Gr. 1 n (%) All Gr. n (%) Gr. ≥4 n (%) Gr. 3 n (%) Gr. 2 n (%) Gr. 1 n (%) Gastrointestinal disorders 28 (58) 0 1 (2) 7 (15) 20 (42) 43 (59) 0 4 (5) 10 (14) 29 (40) Nausea 23 (48) 0 0 6 (12) 17 (35) 43 (59) 0 4 (5) 11 (15) 28 (38) Diarrhoea 16 (33) 0 0 3 (6) 13 (27) 27 (37) 0 1 (1) 8 (11) 18 (25) Vomiting 1 (2) 0 0 1 (2) 0 4 (5) 0 1 (1) 0 3 (4) Abdominal pain 0 0 0 0 0 7 (10) 0 0 0 7 (10) Constipation 2 (4) 0 0 0 2 (4) 4 (5) 0 0 0 4 (5) Dyspepsia 3 (6) 0 0 1 (2) 2 (4) 3 (4) 0 0 0 3 (4) Abdominal distension 0 0 General disorders and administration site conditions 12 (25) 0 0 4 (8) 8 (17) 23 (32) 0 1 (1) 5 (7) 17 (23) Fatigue 0 0 Investigations 2 (4) 0 1 (2) 1 (2) 0 10 (14) 0 1 (1) 4 (5) 5 (7) Lipase increased 2 (4) 0 1 (2) 0 1 (2) 6 (8) 0 0 2 (3) 4 (5) Amylase increased 4 (8) 0 0 1 (2) 3 (6) 4 (5) 0 1 (1) 0 3 (4) Alanine aminotransferase increased 0 0 0 0 0 4 (5) 0 0 1 (1) 3 (4) Weight decreased 1 (2) 0 0 1 (2) 0 4 (5) 0 0 3 (4) 1 (1) White blood cell count decreased 5 (10) 0 1 (2) 1 (2) 3 (6) 3 (4) 0 2 (3) 0 1 (1) Aspartate aminotransferase increased 0 0 Blood and lymphatic system disorders 3 (6) 0 0 2 (4) 1 (2) 9 (12) 0 1 (1) 6 (8) 2 (3) Anaemia 4 (8) 0 1 (2) 3 (6) 0 8 (11) 0 1 (1) 3 (4) 4 (5) Neutropenia 1 4 (8) 0 0 0 4 (8) 2 (3) 0 0 0 2 (3) Thrombocytopenia 2 0 0 Metabolism and nutrition disorders 10 (21) 0 0 1 (2) 9 (19) 10 (14) 0 0 5 (7) 5 (7) Decreased appetite 0 0 Nervous system disorders 3 (6) 0 0 0 3 (6) 7 (10) 0 0 2 (3) 5 (7) Dysgeusia 0 0 Skin and subcutaneous tissue disorders 1 (2) 0 0 0 1 (2) 4 (5) 0 0 0 4 (5) Pruritus Subjects are counted only once at their highest grade. Adverse events are graded according to the Common Terminology Criteria fo r Adverse Events v5. MedDRA version V28.0. ‘1. Neutropenia' and 'Neutrophil count decreased' are grouped as 'Neutropenia’. 2. 'Thrombocytopenia' and 'Platelet count dec rea sed' are grouped as 'Thrombocytopenia’ Data cutoff: Sep 29 2026
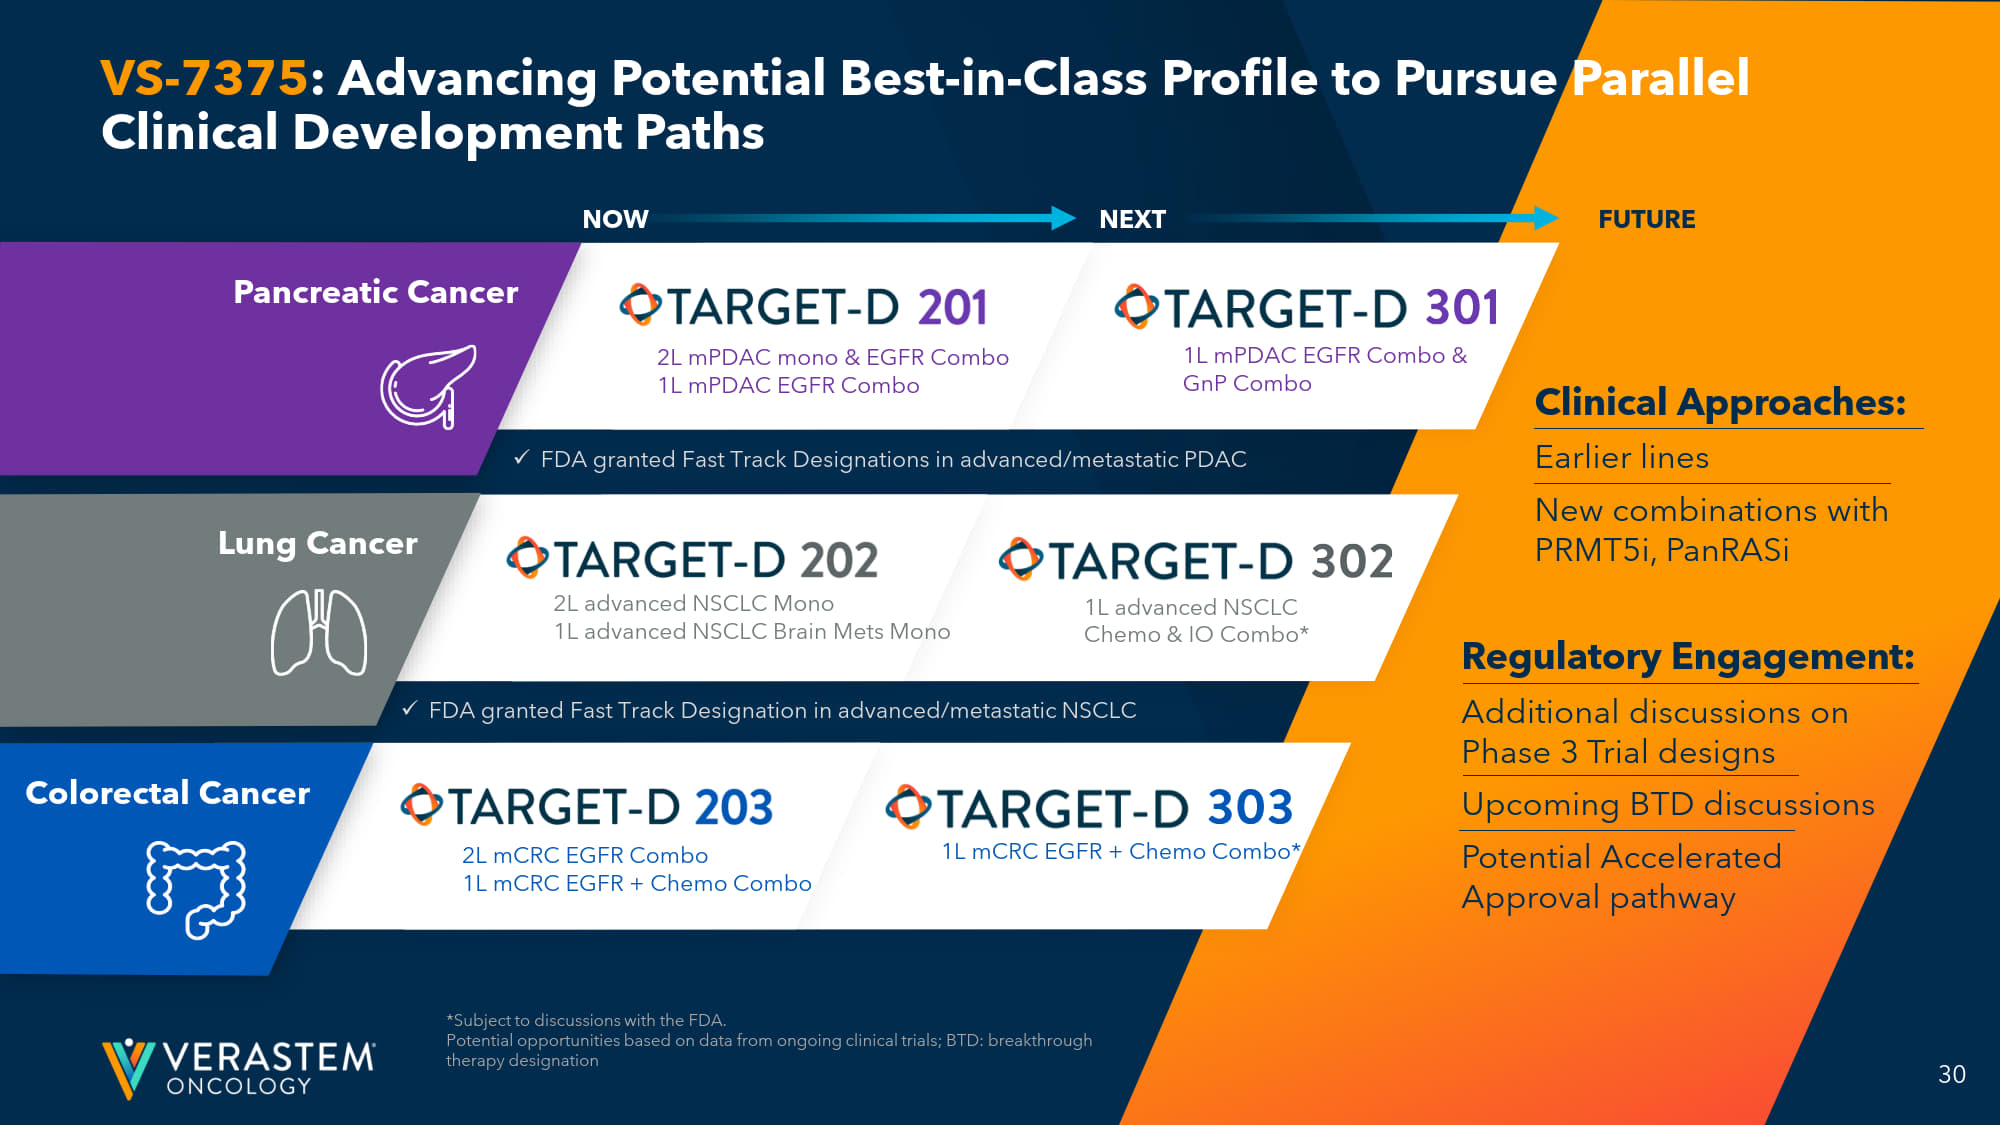
30 VS - 7375 : Advancing Potential Best - in - Class Profile to Pursue Parallel Clinical Development Paths *Subject to discussions with the FDA. Potential opportunities based on data from ongoing clinical trials; BTD: breakthrough therapy designation Clinical Approaches: Earlier lines New combinations with PRMT5i, PanRASi Regulatory Engagement: Additional d iscussions on Phase 3 Trial d esigns Upcoming BTD discussions Potential Accelerated Approval pathway FUTURE 1L advanced NSCLC Chemo & IO Combo* 1L mCRC EGFR + Chemo Combo* 1L mPDAC EGFR Combo & GnP Combo NEXT x FDA granted Fast Track Designations in advanced/metastatic PDAC 2L advanced NSCLC Mono 1L advanced NSCLC Brain Mets Mono 2L mCRC EGFR Combo 1L mCRC EGFR + Chemo Combo 2L mPDAC mono & EGFR Combo 1L mPDAC EGFR Combo Pancreatic Cancer Lung Cancer Colorectal Cancer x FDA granted Fast Track Designation in advanced/metastatic NSCLC NOW
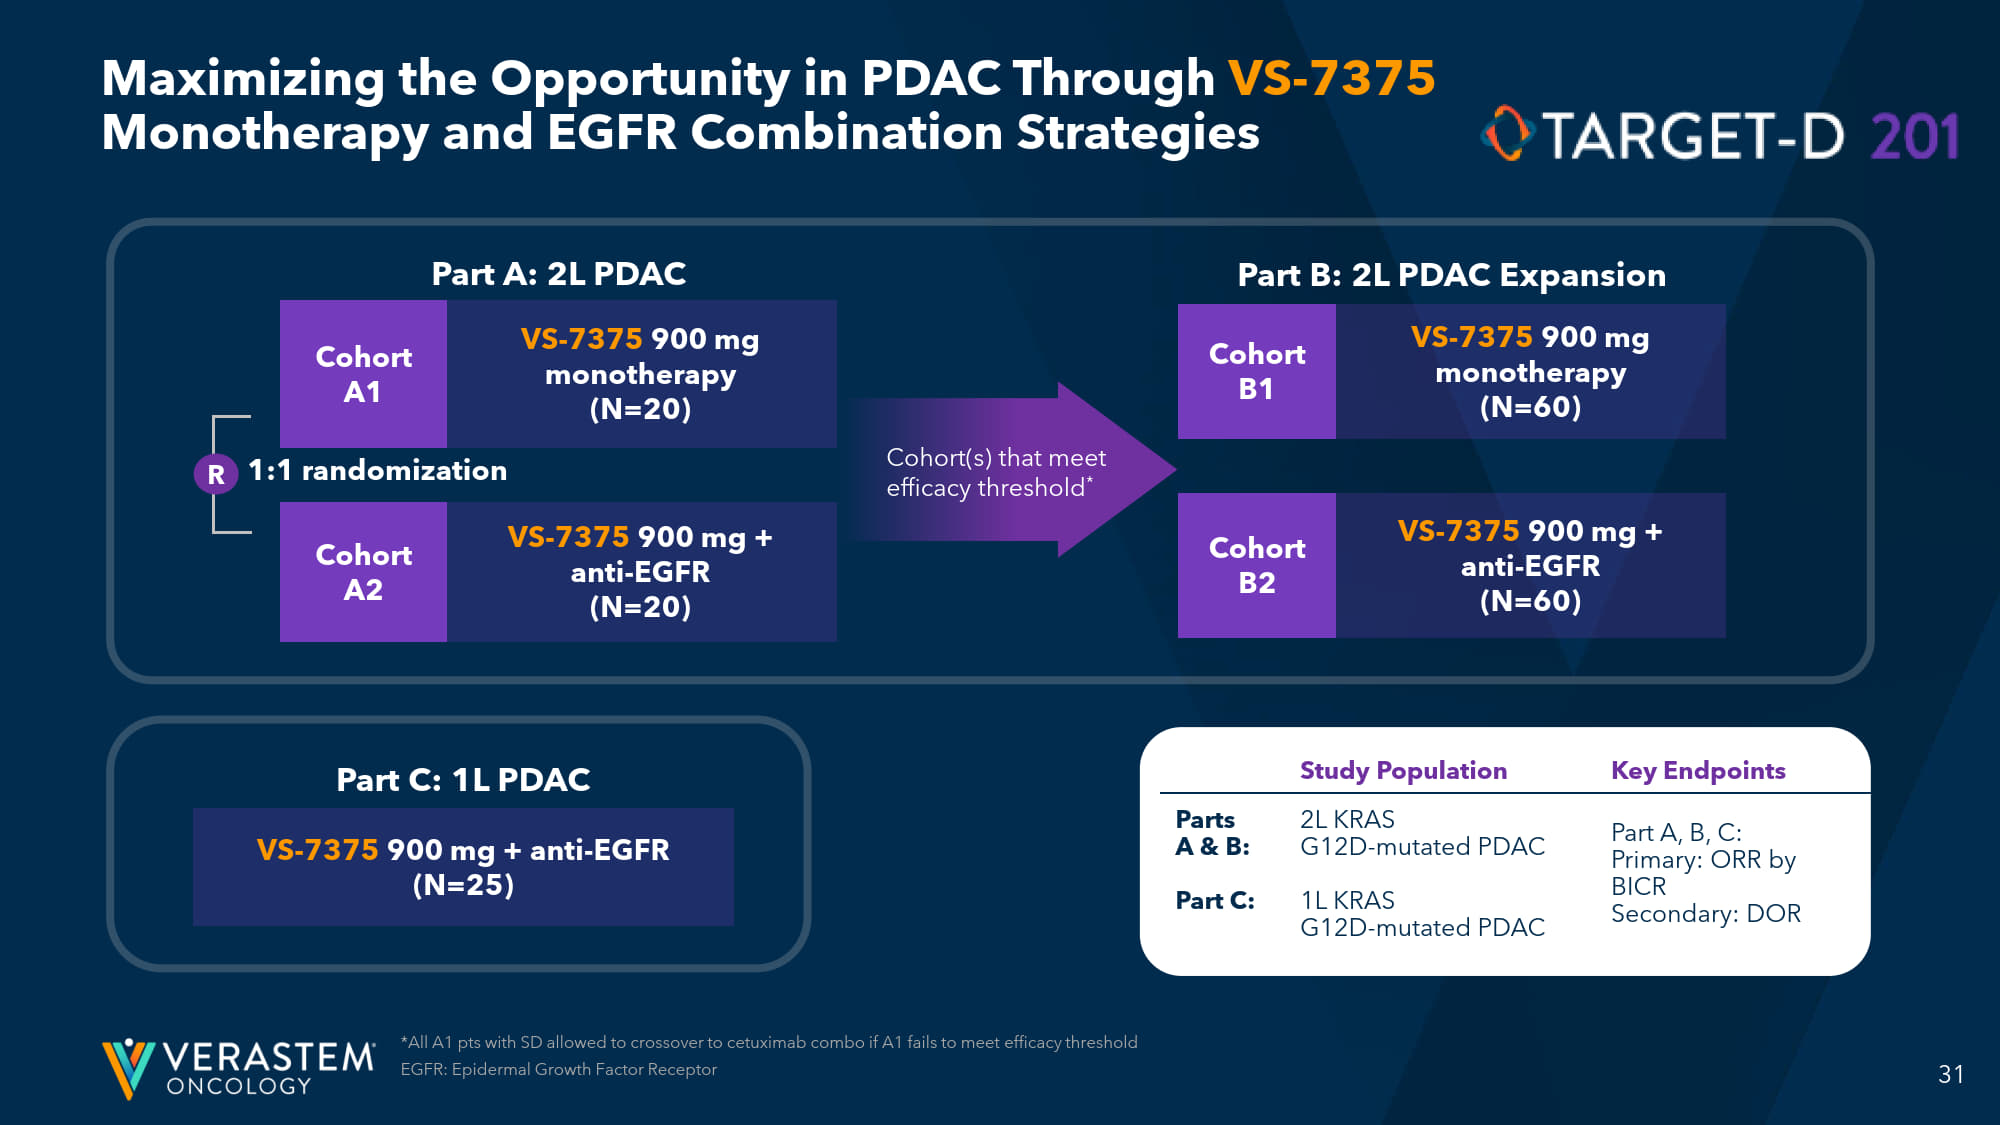
31 Maximizing the Opportunity in PDAC Through VS - 7375 Monotherapy and EGFR Combination Strategies *All A1 pts with SD allowed to crossover to cetuximab combo if A1 fails to meet efficacy threshold EGFR: Epidermal Growth Factor Receptor R 1:1 randomization Part A: 2L PDAC Cohort A 1 Cohort A2 VS - 7375 900 mg monotherapy (N=20) VS - 7375 900 mg + anti - EGFR (N=20) Cohort B1 Cohort B2 VS - 7375 900 mg monotherapy (N=60) VS - 7375 900 mg + anti - EGFR (N=60) Part B: 2L PDAC Expansion Cohort(s) that meet efficacy threshold * Part C: 1L PDAC VS - 7375 900 mg + anti - EGFR (N=25) Key Endpoints Study Population Part A, B, C: Primary: ORR by BICR Secondary: DOR 2L KRAS G12D - mutated PDAC 1L KRAS G12D - mutated PDAC Parts A & B: Part C:
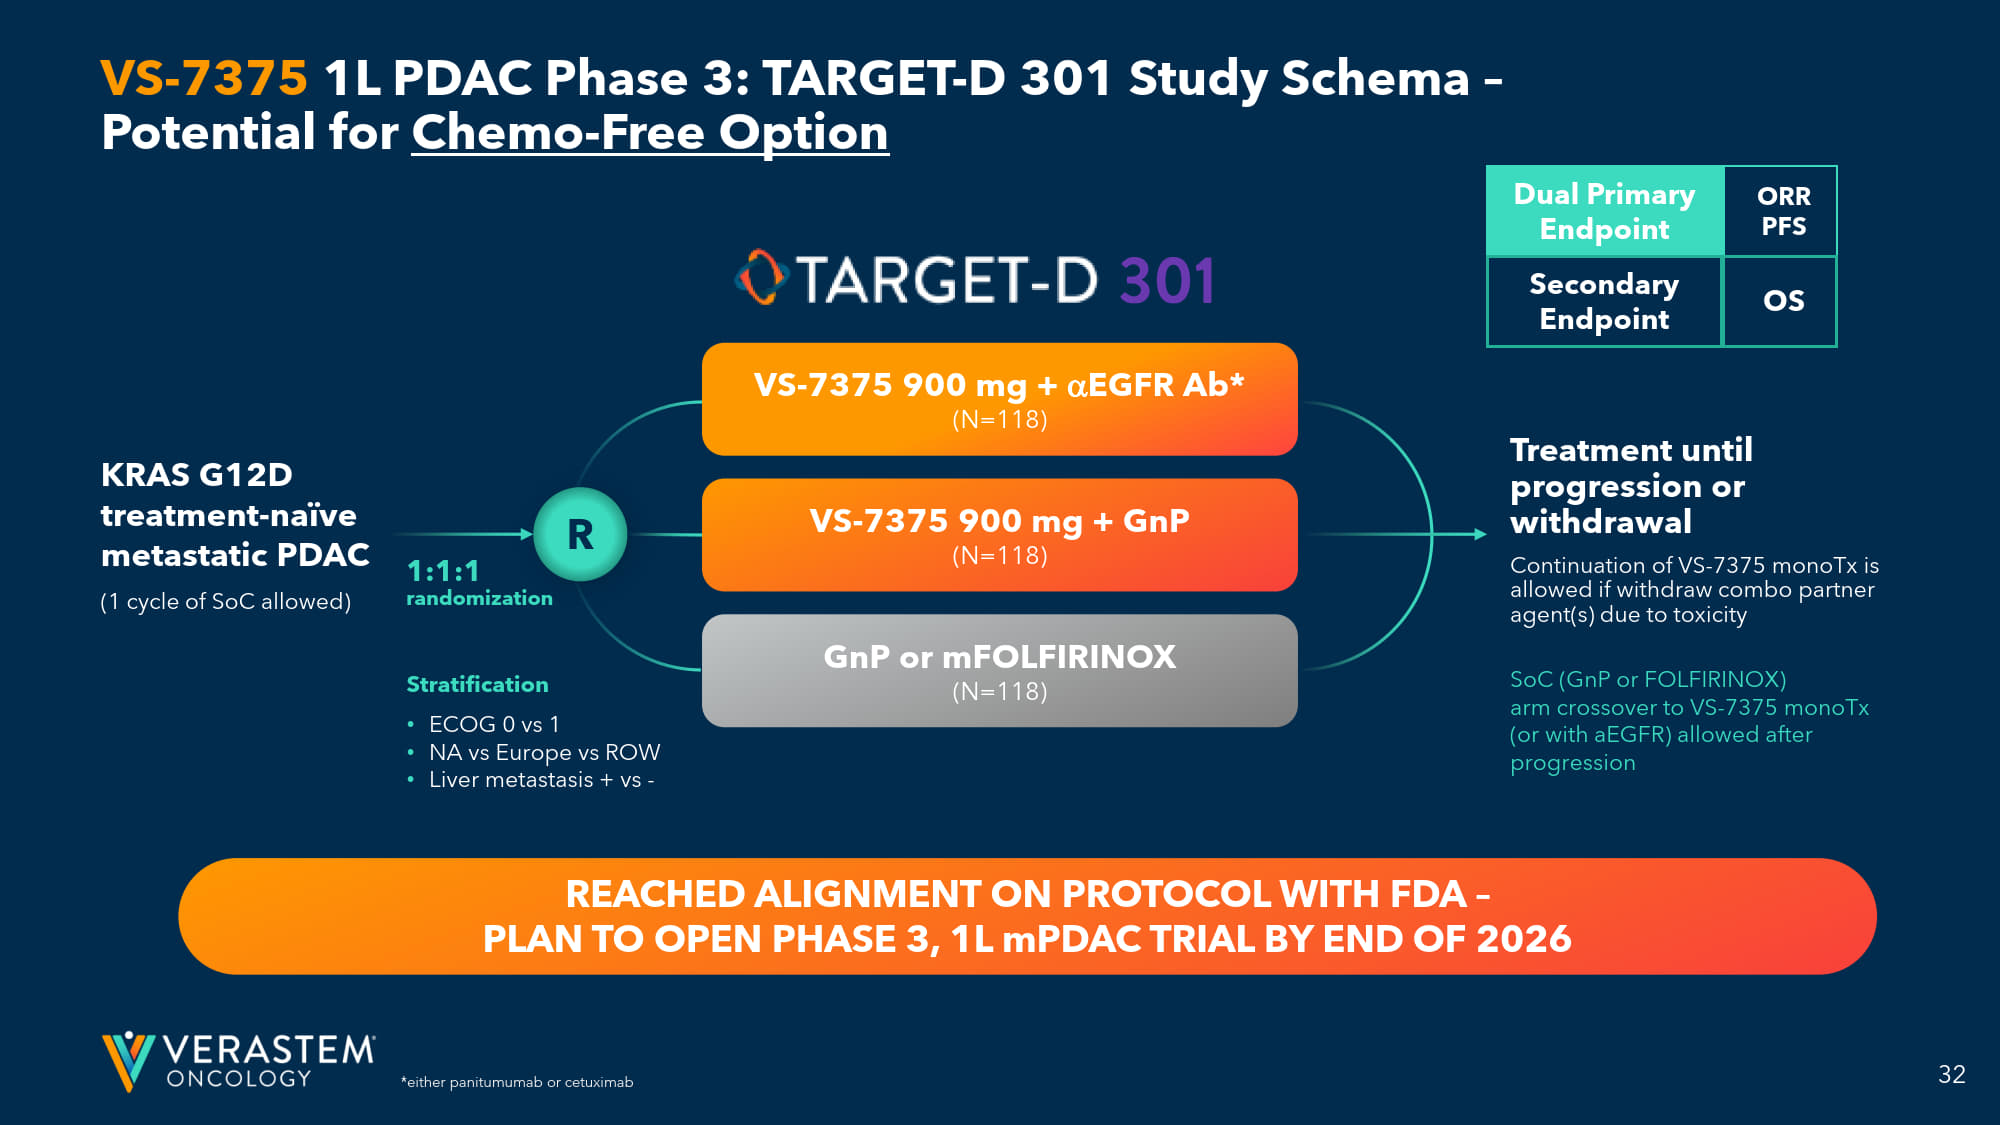
32 ORR PFS *either panitumumab or cetuximab VS - 7375 1L PDAC Phase 3: TARGET - D 301 Study Schema – Potential for Chemo - Free Option 1:1:1 randomization Stratification • ECOG 0 vs 1 • NA vs Europe vs ROW • Liver metastasis + vs - SoC (GnP or FOLFIRINOX) arm crossover to VS - 7375 monoTx (or with a EGFR) allowed after progression Dual Primary Endpoint Secondary Endpoint OS VS - 7375 900 mg + EGFR Ab* (N=118) VS - 7375 900 mg + GnP (N=118) GnP or mFOLFIRINOX (N=118) R Treatment until progression or withdrawal Continuation of VS - 7375 monoTx is allowed if withdraw combo partner agent(s) due to toxicity KRAS G12D treatment - naïve metastatic PDAC (1 cycle of SoC allowed) REACHED ALIGNMENT ON PROTOCOL WITH FDA – PLAN TO OPEN PHASE 3, 1L mPDAC TRIAL BY END OF 2026
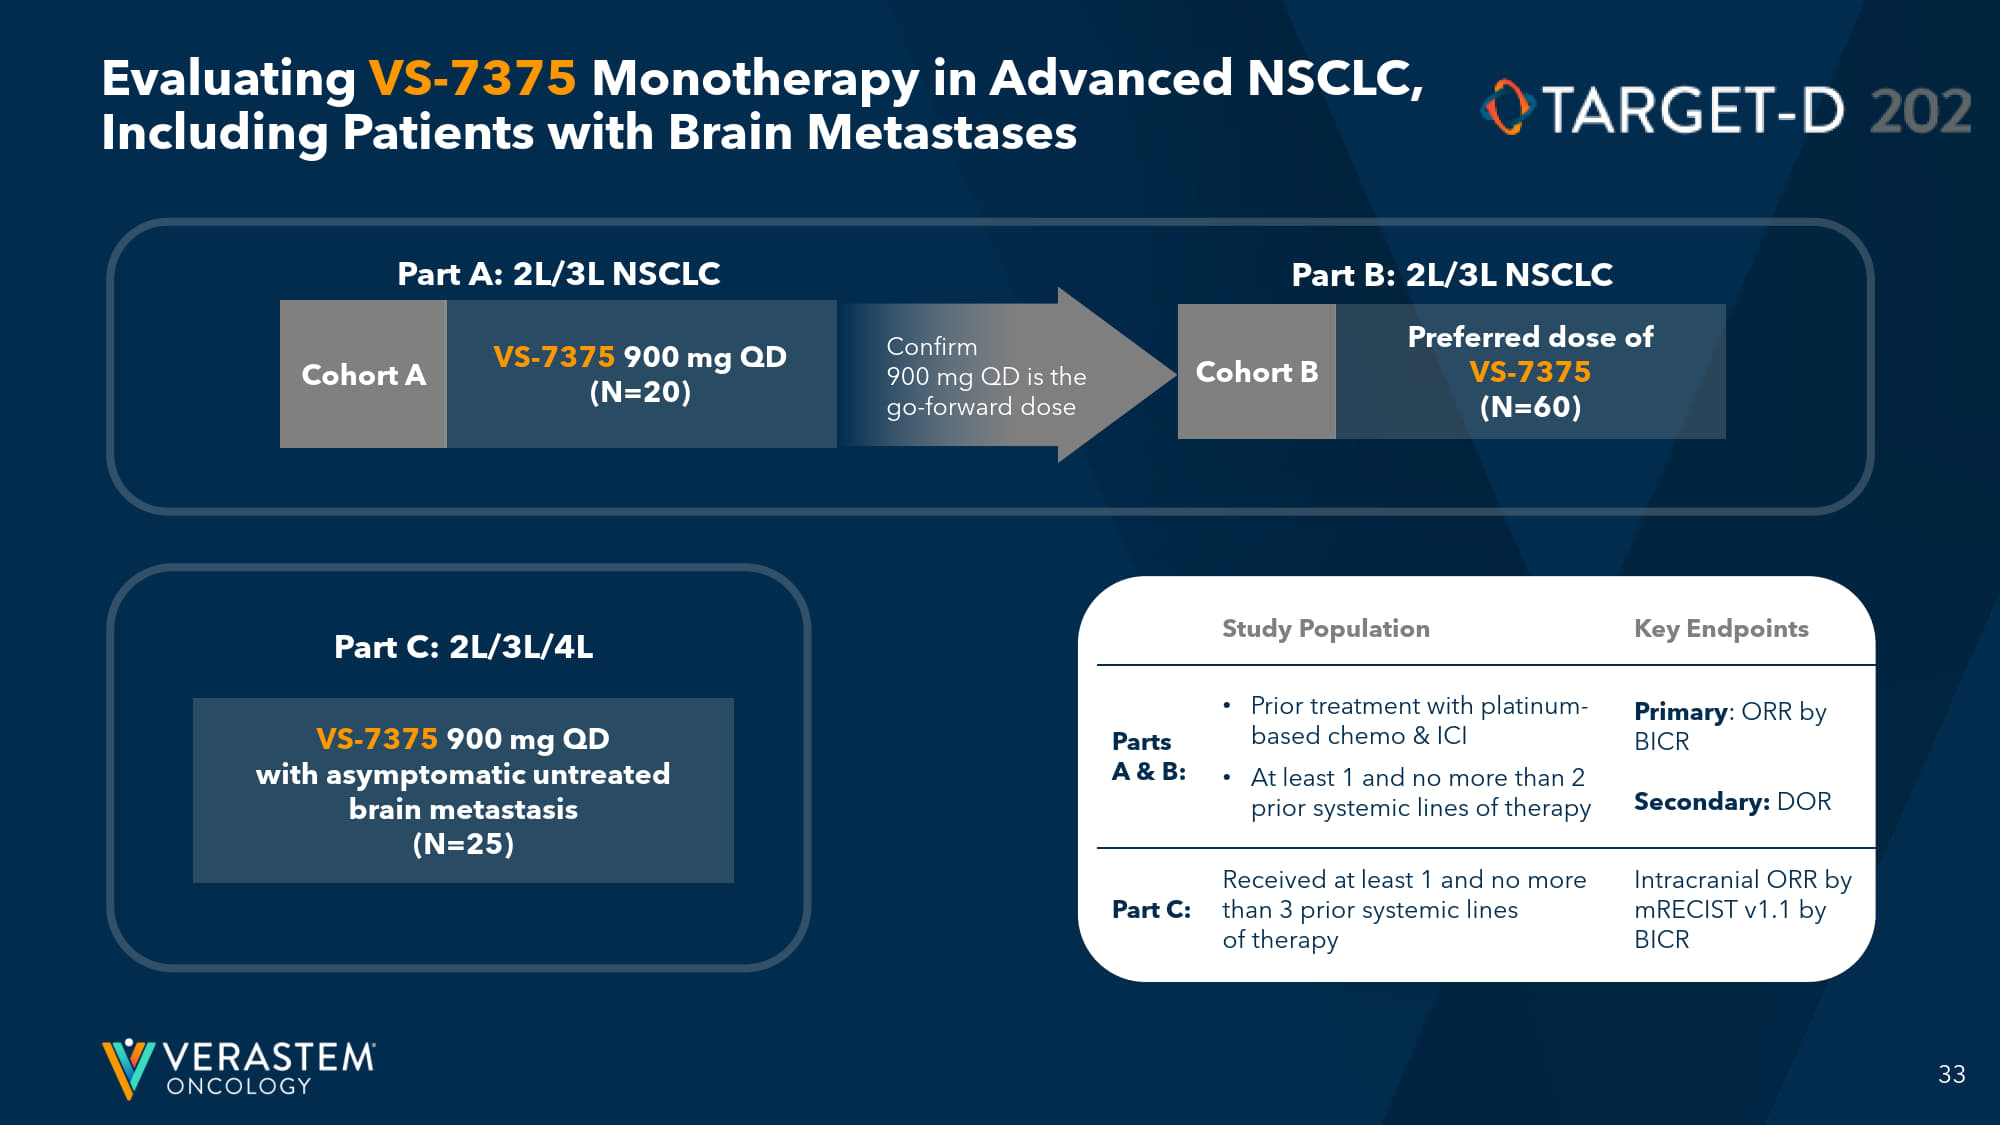
33 Evaluating VS - 7375 Monotherapy in Advanced NSCLC, Including Patients with Brain Metastases Part A: 2L/3L NSCLC Cohort A VS - 7375 900 mg QD (N=20) Cohort B Preferred dose of VS - 7375 (N=60) Part B: 2L/3L NSCLC Confirm 900 mg QD is the go - forward dose Part C: 2L/3L/4L VS - 7375 900 mg QD with asymptomatic untreated brain metastasis (N=25) Key Endpoints Study Population Primary : ORR by BICR Secondary: DOR • Prior treatment with platinum - based chemo & ICI • At least 1 and no more than 2 prior systemic lines of therapy Parts A & B: Intracranial ORR by mRECIST v1.1 by BICR Received at least 1 and no more than 3 prior systemic lines of therapy Part C:
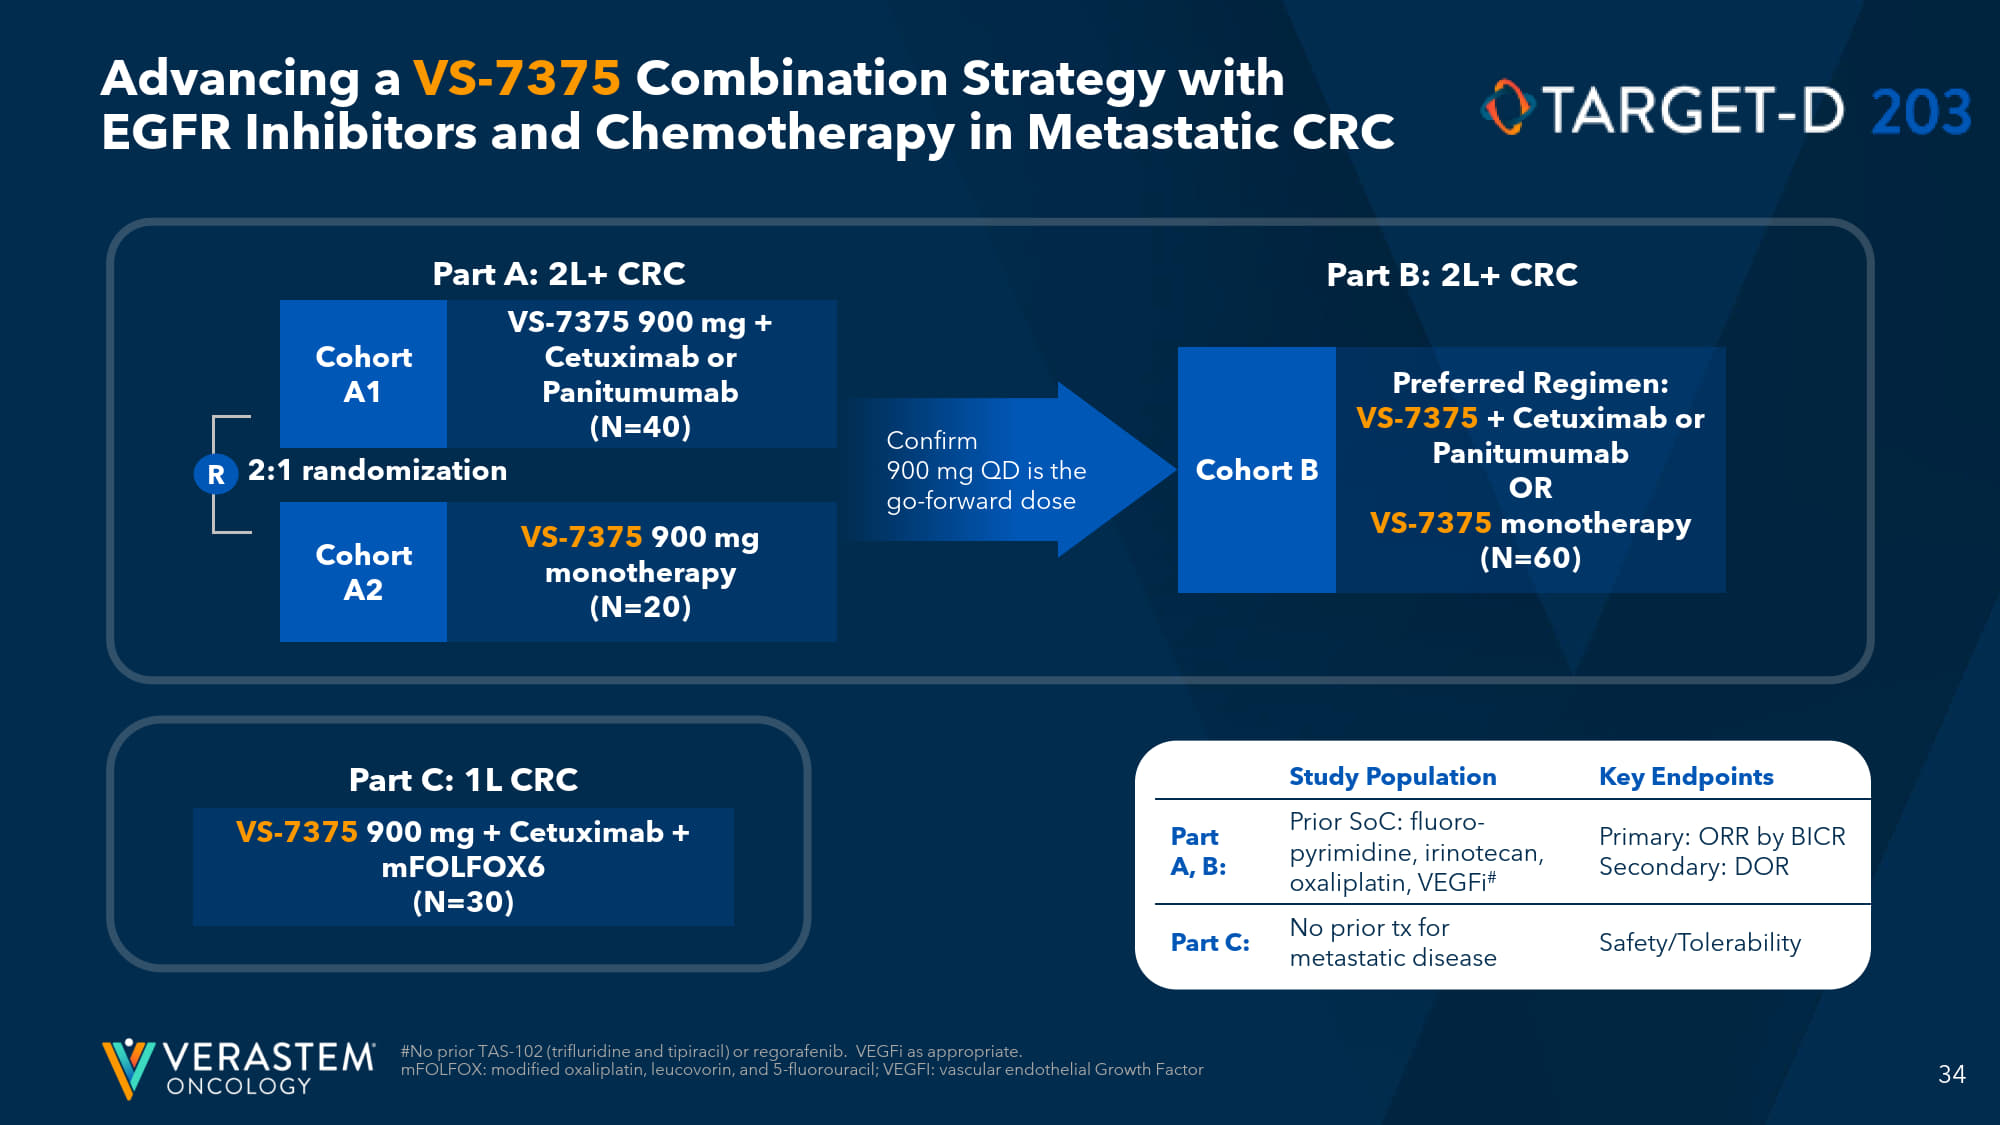
34 Advancing a VS - 7375 Combination Strategy with EGFR Inhibitors and Chemotherapy in Metastatic CRC #No prior TAS - 102 ( trifluridine and tipiracil ) or regorafenib. VEGFi as appropriate. mFOLFOX : modified oxaliplatin, leucovorin, and 5 - fluorouracil; VEGFI: vascular endothelial Growth Factor R 2:1 randomization Part A: 2L+ CRC Cohort A 1 Cohort A2 VS - 7375 900 mg + Cetuximab or Panitumumab (N=40) VS - 7375 900 mg monotherapy (N=20) Cohort B Preferred Regimen: VS - 7375 + Cetuximab or Panitumumab OR VS - 7375 monotherapy (N=60) Part B: 2L+ CRC Confirm 900 mg QD is the go - forward dose Part C: 1L CRC VS - 7375 900 mg + Cetuximab + mFOLFOX6 (N=30) Key Endpoints Study Population Primary: ORR by BICR Secondary: DOR Prior SoC: fluoro - pyrimidine, irinotecan, oxaliplatin, VEGFi # Part A, B: Safety/Tolerability No prior tx for metastatic disease Part C:
RAMP 205: Avutometinib + Defactinib + Standard - of - Care in First - Line Metastatic Pancreatic Cancer
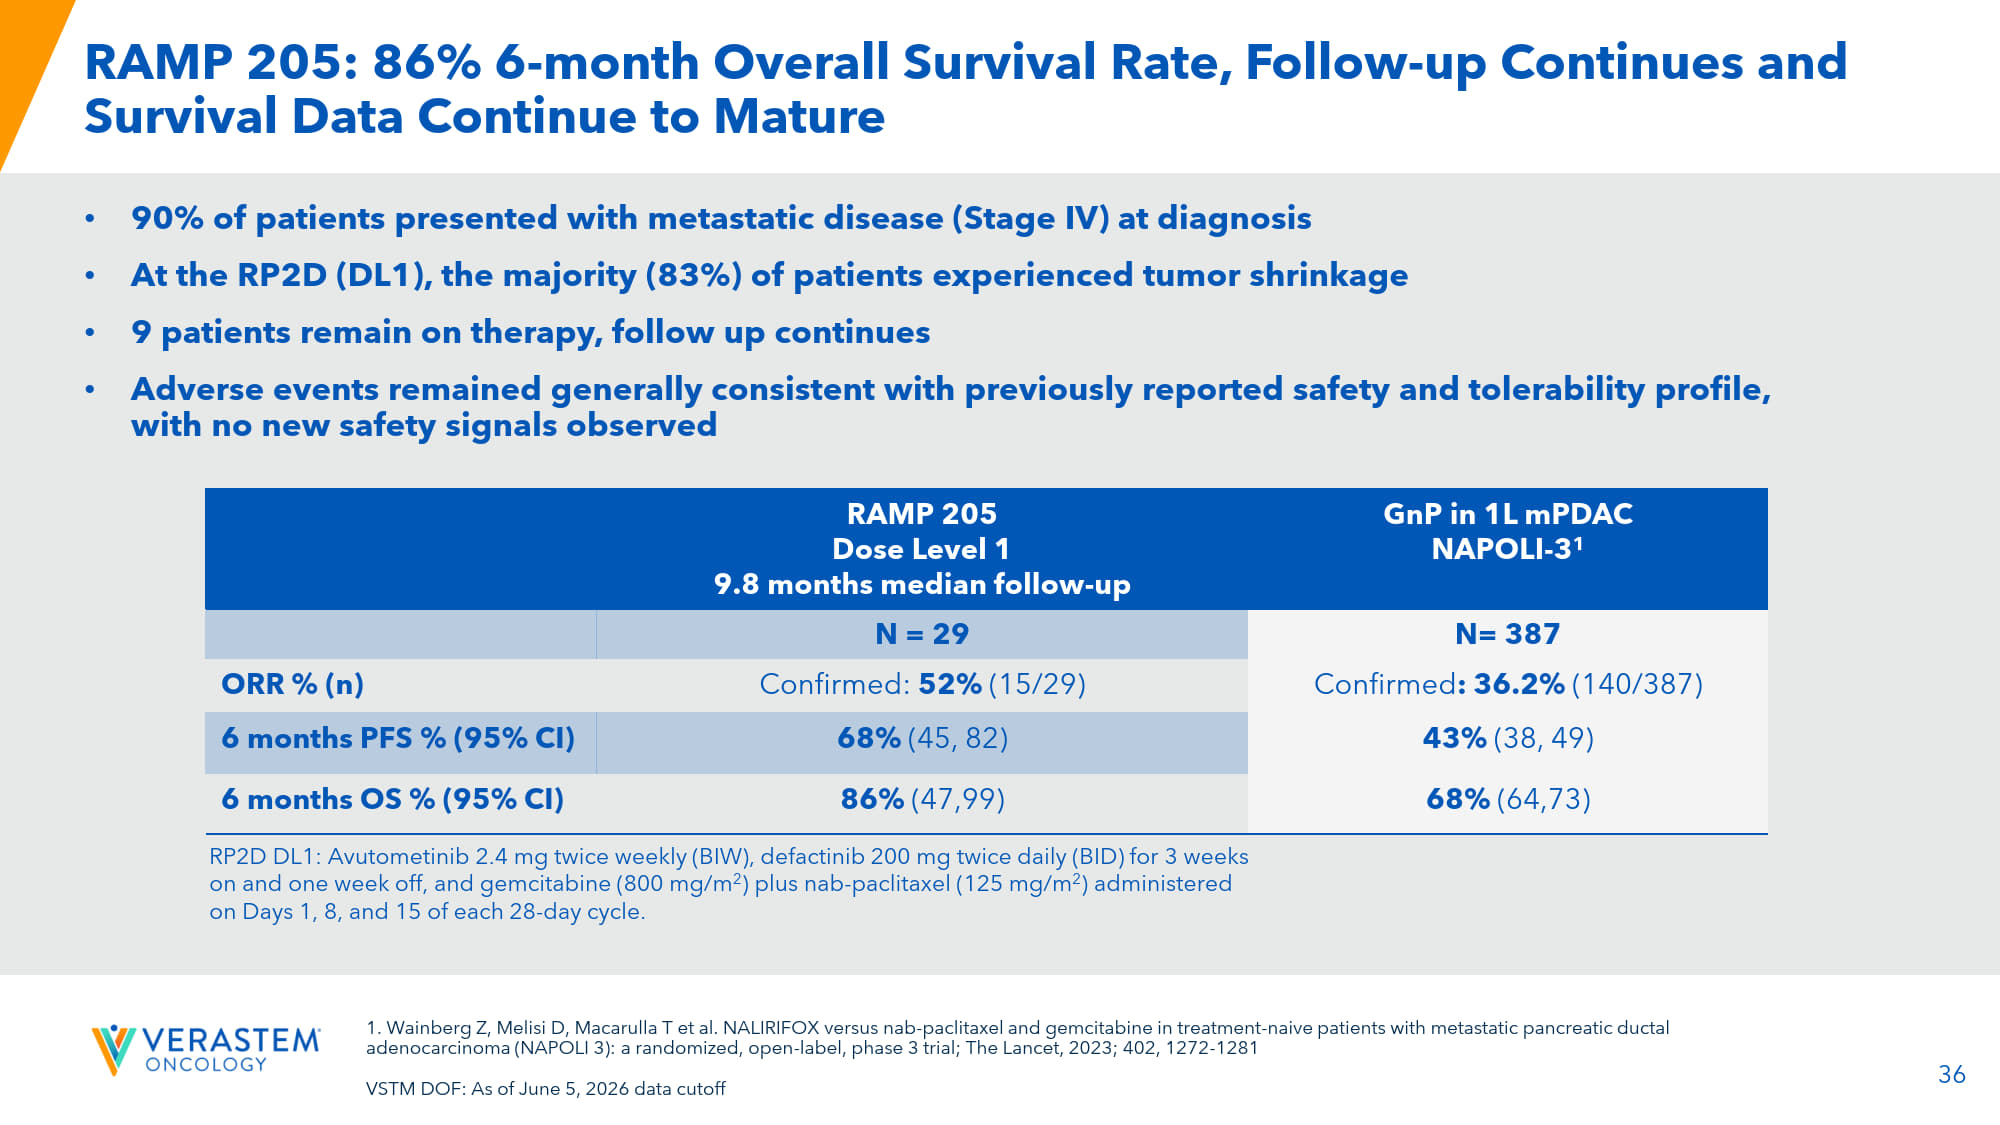
36 RAMP 205: 86% 6 - month Overall Survival Rate, Follow - up Continues and Survival Data Continue to Mature • 90% of patients presented with metastatic disease (Stage IV) at diagnosis • At the RP2D (DL1), the majority (83%) of patients experienced tumor shrinkage • 9 patients remain on therapy, follow up continues • Adverse events remained generally consistent with previously reported safety and tolerability profile, with no new safety signals observed GnP in 1L mPDAC NAPOLI - 3 1 RAMP 205 Dose Level 1 9.8 months median follow - up N= 387 N = 29 Confirmed : 36.2% (140/387) Confirmed: 52% (15/29) ORR % (n) 43% (38, 49) 68% (45, 82) 6 months PFS % (95% CI) 68% (64,73) 86% (47,99) 6 months OS % (95% CI) RP2D DL1: A vutometinib 2.4 mg twice weekly (BIW), defactinib 200 mg twice daily (BID) for 3 weeks on and one week off, and gemcitabine (800 mg/m 2 ) plus nab - paclitaxel (125 mg/m 2 ) administered on Days 1, 8, and 15 of each 28 - day cycle. 1. Wainberg Z, Melisi D, Macarulla T et al. NALIRIFOX versus nab - paclitaxel and gemcitabine in treatment - naive patients with metastatic pancreatic ductal adenocarcinoma (NAPOLI 3): a randomized, open - label, phase 3 trial; The Lancet, 2023; 402, 1272 - 1281 VSTM DOF: As of June 5, 2026 data cutoff

Financials 37
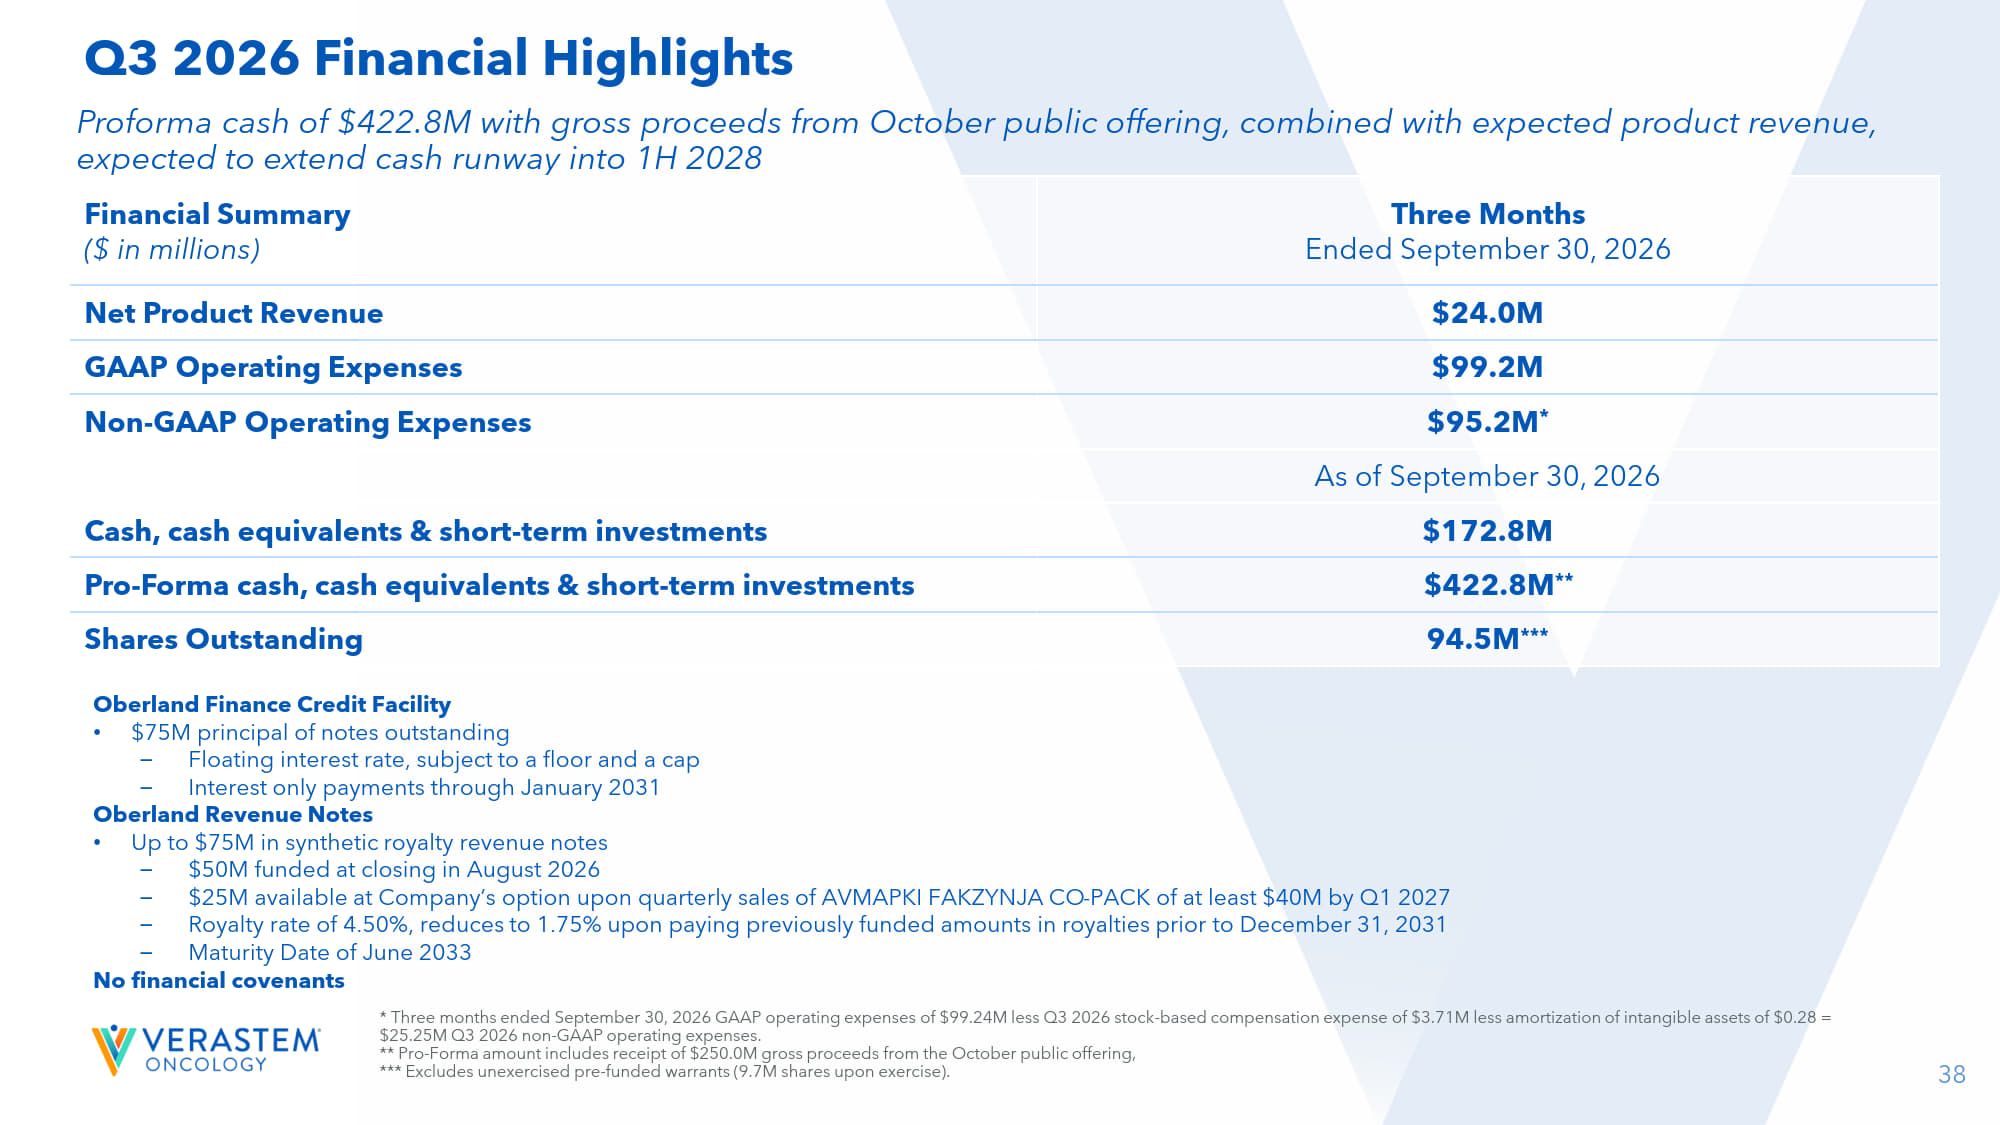
38 Oberland Finance Credit Facility • $75M principal of notes outstanding – Floating interest rate, subject to a floor and a cap – Interest only payments through January 2031 Oberland Revenue Notes • Up to $75M in synthetic royalty revenue notes – $50M funded at closing in August 2026 – $25M available at Company’s option upon quarterly sales of AVMAPKI FAKZYNJA CO - PACK of at least $40M by Q1 2027 – Royalty rate of 4.50%, reduces to 1.75% upon paying previously funded amounts in royalties prior to December 31, 2031 – Maturity Date of June 2033 No financial covenants Proforma cash of $422.8M with gross proceeds from October public offering, combined with expected product revenue, expected to extend cash runway into 1H 2028 Three Months Ended September 30, 2026 Financial Summary ($ in millions) $24.0M Net Product Revenue $99.2M GAAP Operating Expenses $95.2M * Non - GAAP Operating Expenses As of September 30, 2026 $172.8M Cash, cash equivalents & short - term investments $422.8M ** Pro - Forma cash, cash equivalents & short - term investments 94.5M *** Shares Outstanding Q3 2026 Financial Highlights * Three months ended September 30, 2026 GAAP operating expenses of $99.24M less Q3 2026 stock - based compensation expense of $3.7 1M less amortization of intangible assets of $0.28 = $25.25M Q3 2026 non - GAAP operating expenses. ** Pro - Forma amount includes receipt of $250.0M gross proceeds from the October public offering, *** Excludes unexercised pre - funded warrants (9.7M shares upon exercise).

39 39 EU: European Union ; *Please see November 5, 2026 press release. Delivering for Long - term Growth • AVMAPKI FAKZYNJA CO - PACK has potential to be standard - of - care in KRAS - mutated recurrent LGSOC – RAMP 301: Fully - enrolled Phase 3 confirmatory trial has the potential to expand U.S. label and can be leveraged for EU/Japan approvals in recurrent LGSOC regardless of KRAS mutation – Meaningful growth driven by new patient starts, increased refills and expanding physician adoption • VS - 7375 addresses significant opportunity in multiple KRAS G12D solid tumors with a differentiated profile and compelling antitumor activity – Broad clinical development program advancing VS - 7375 across multiple tumor types with multiple registration pathways – Three registration - directed Phase 2 trials underway in pancreatic, lung and colorectal cancers, with three Phase 3 trials planned to initiate in late Q4 2026/1H 2027 • Cash runway into 1H of 2028* to see key data inflection points

THANK YOU!

Appendix
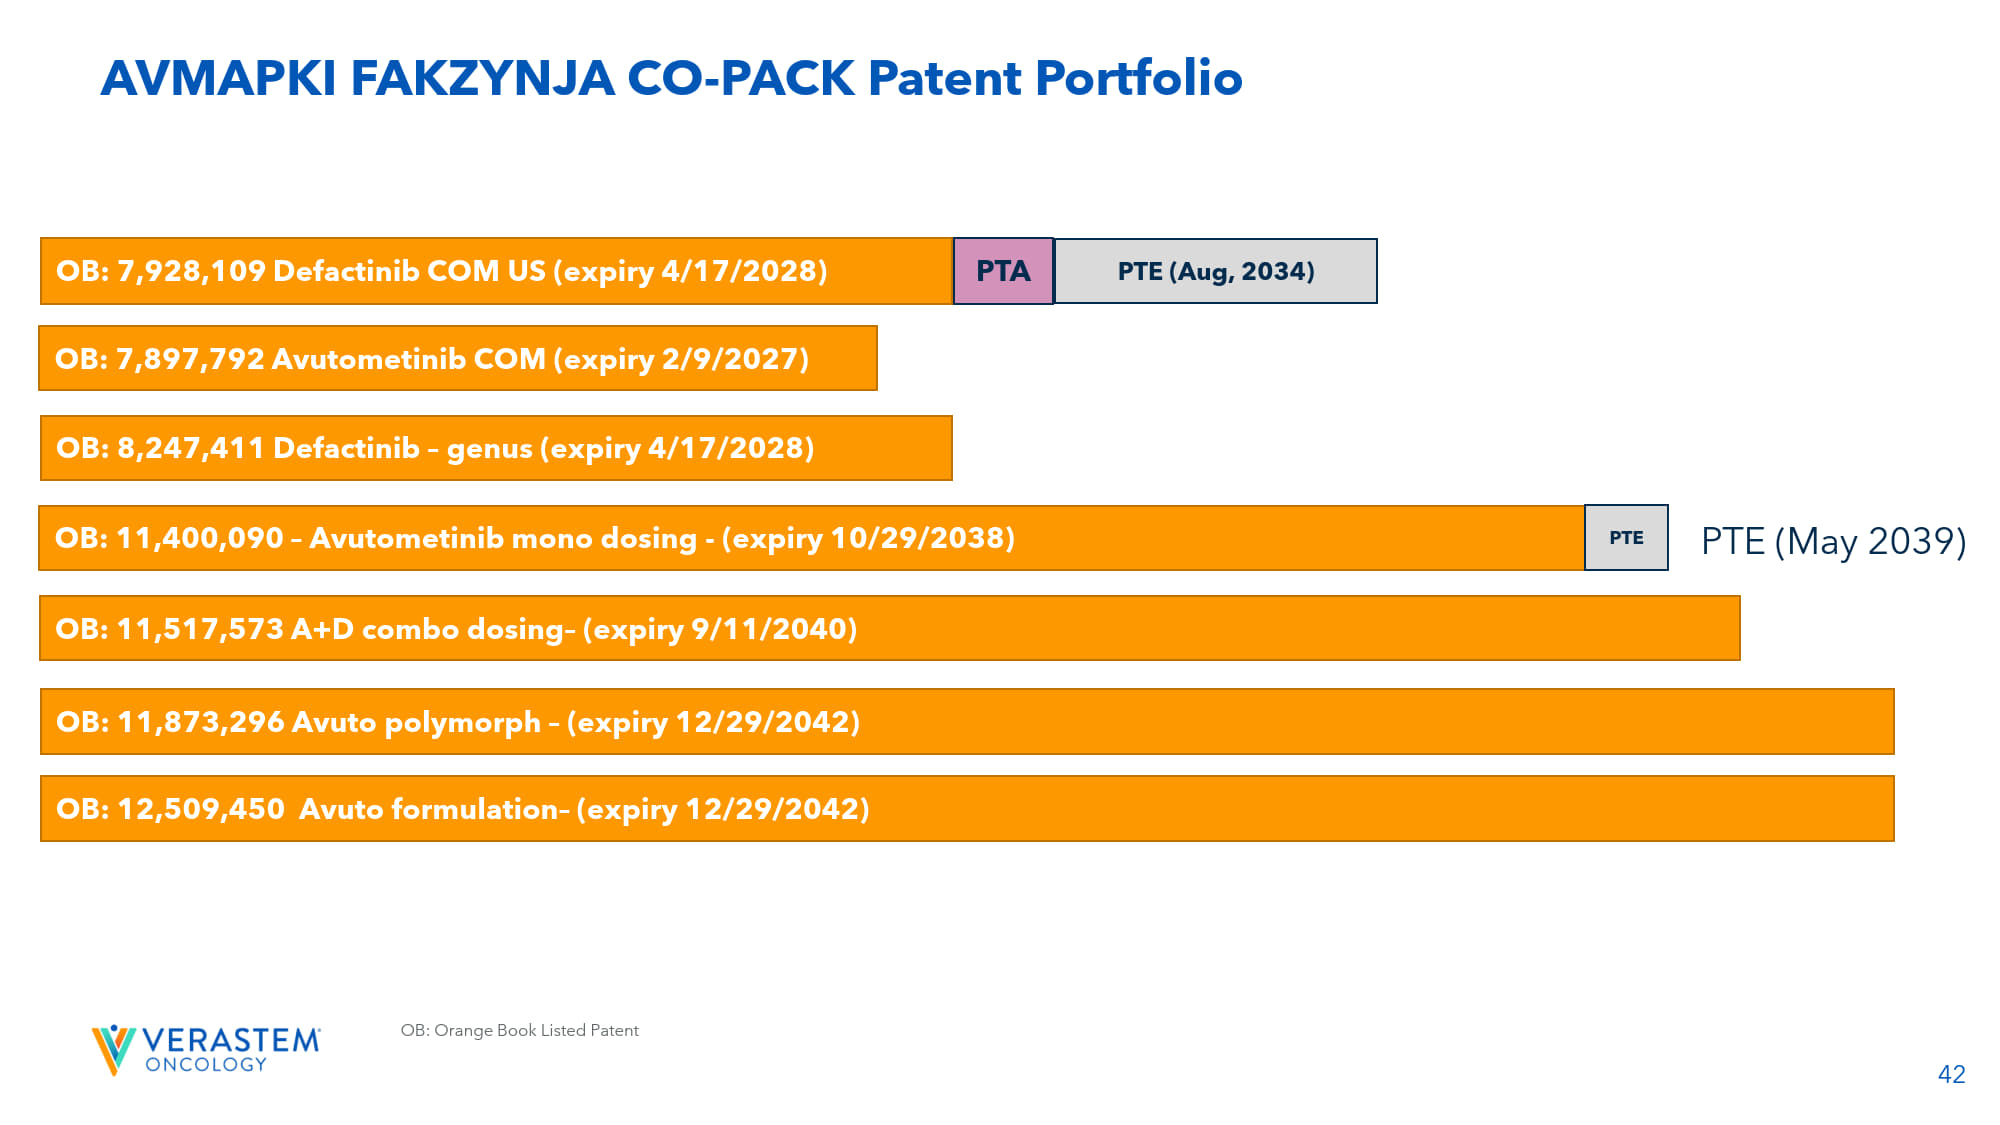
42 OB: Orange Book Listed Patent AVMAPKI FAKZYNJA CO - PACK Patent Portfolio OB: 7,897,792 Avutometinib COM (expiry 2/9/2027) OB: 11,400,090 – Avutometinib mono dosing - (expiry 10/29/2038) PTE OB: 7,928,109 Defactinib COM US (expiry 4/17/2028) PTA PTE (Aug, 2034) OB: 8,247,411 Defactinib – genus (expiry 4/17/2028) OB: 11,517,573 A+D combo dosing – (expiry 9/11/2040) OB: 11,873,296 Avuto polymorph – (expiry 12/29/2042) PTE (May 2039) OB: 12,509,450 Avuto formulation – (expiry 12/29/2042)