
Investor Presentation November 2026

Forward-Looking Statements This presentation, together with other statements and information publicly disseminated by the Company, contains certain forward-looking statements within the meaning of Section 27A of the Securities Act of 1933, as amended, and Section 21E of the Securities Exchange Act of 1934, as amended, which statements are subject to considerable risks and uncertainties. The Company intends such forward-looking statements to be covered by the safe harbor provisions for forward-looking statements contained in the Private Securities Litigation Reform Act of 1995. Forward-looking statements include all statements other than statements of historical fact, including statements regarding our future results of operations, product development, market opportunity, clinical trial results and timeline, and business strategy and plans. The forward-looking statements in this presentation include, but are not limited to, statements concerning the following: the Company's projected financial results, including revenue guidance, adjusted operating expense guidance, and expectations for gross margins; estimates of the Company's addressable markets for its products, including market size, patient population estimates, and market opportunity for standalone and combination minimally invasive glaucoma surgery (MIGS) procedures; the Company's ability to successfully develop and commercialize its product pipeline, including the anticipated timing and commercial impact of the launch of the OMNI® Ultra Surgical System; the expected scope and impact of third-party payer coverage decisions, including Aetna's coverage of the Company's interventional glaucoma technologies, and estimated patient access and reimbursement trends; the Company's ability to obtain and maintain sufficient reimbursement for its products; the Company's plans to scale its commercial resources and pursue expanded market access for its interventional dry eye and interventional glaucoma technologies, including physician targeting and cross-activation of its installed customer base; the Company's strategic initiatives and objectives, including its mission to advance interventional approaches in eye care; the Company's plans to invest in commercial infrastructure; the Company's expectations with respect to tariffs and other economic matters; and regulatory requirements applicable to the Company and its products. These statements often include words such as “anticipate,” “expect,” “suggests,” “plan,” “believe,” “intend,” “estimates,” “targets,” “projects,” “should,” “could,” “would,” “may,” “will,” “forecast” and other similar expressions. Management bases these forward-looking statements on its current expectations, plans and assumptions affecting the Company’s business and industry, and such statements are based on information available to it as of the time such statements are made. Although management believes these forward-looking statements are based upon reasonable assumptions, it cannot guarantee their accuracy or completeness. Forward-looking statements are subject to and involve risks, uncertainties and assumptions that may cause the Company’s actual results, performance or achievements to be materially different from any future results, performance, or achievements predicted, assumed or implied by such forward-looking statements. Some of the risks and uncertainties that may cause actual results to materially differ from those expressed or implied by these forward-looking statements are discussed under the caption “Risk Factors” in the Company’s annual and quarterly reports with the U.S. Securities and Exchange Commission, as such may be updated from time to time in subsequent filings. These cautionary statements should not be construed by you to be exhaustive and are made only as of the date of this presentation. The Company undertakes no obligation to update or revise any forward-looking statements, whether as a result of new information, future events or otherwise, except as required by applicable law. Certain information contained in this presentation relates to, or is based on, studies, publications, surveys and other data obtained from third-party sources and the Company’s own internal estimates and research. While the Company believes these third-party sources to be reliable, it has not independently verified, and makes no representation as to the adequacy, fairness, accuracy or completeness of, any information obtained from third-party sources. In addition, all of the market data included in this presentation involves a number of assumptions and limitations, and there can be no guarantee as to the accuracy or reliability of such assumptions. Finally, while the Company believes its own estimates and research are reliable, such estimates and research have not been verified by any independent source. The Company has proprietary rights to trademarks, trade names and service marks appearing in this presentation that are important to its business. Solely for convenience, the trademarks, trade names and service marks may appear in this presentation without the ® and ™ symbols, but any such references are not intended to indicate that the Company forgoes or will not assert, to the fullest extent under applicable law, its rights or the rights of the applicable licensors to these trademarks, trade names and service marks. All trademarks, trade names and service marks appearing in this presentation are the property of their respective owners. The Company does not intend its use or display of other parties’ trademarks, trade names or service marks to imply, and such use or display should not be construed to imply, a relationship with, or endorsement or sponsorship of the Company by, these other parties. Without limitation, SIGHT SCIENCES™, SIGHT SCIENCES (with design)®, OMNI®, SION®, TEARCARE®, SMARTLIDS® and TruSync™ are trademarks of Sight Sciences, Inc. in the United States and other countries. RESTASIS® is a registered trademark of Allergan, Inc., and IRIS® is a registered trademark of the American Academy of Ophthalmology. Certain financial measures, including adjusted operating expenses (“non-GAAP financial measures”), were not prepared in accordance with generally accepted accounting principles in the United States (“GAAP") and are presented in this presentation to provide information that may assist investors in understanding the Company's financial and operating results. The Company believes these non-GAAP financial measures are important performance indicators because they exclude items that are unrelated to, and may not be indicative of, the Company's core financial and operating results. These non-GAAP financial measures, as calculated, may not necessarily be comparable to similarly titled measures of other companies and may not be appropriate measures for comparing the performance of other companies relative to the Company. These non-GAAP financial measures are not intended to represent, and should not be considered more meaningful measures than, or alternatives to, measures of operating performance as determined in accordance with GAAP. To the extent the Company utilizes such non-GAAP financial measures in the future, it expects to calculate them using a consistent method from period to period. Consistent with Securities and Exchange Commission regulations, the Company has not provided a reconciliation of forward-looking non-GAAP financial measures to the most directly comparable GAAP financial measures in reliance on the “unreasonable efforts” exception set forth in the applicable regulations, because there is substantial uncertainty associated with predicting any future adjustments that may be made to the Company’s GAAP financial measures in calculating the non-GAAP financial measures. For a reconciliation of non-GAAP financial measures referenced in this presentation to the most directly comparable GAAP measures, please refer to the Company's earnings release issued on November 4, 2026.

| 3 We aim to make early intervention the new standard of care in eye care

Two growing franchises, one mission: early intervention | 4 01 Interventional Glaucoma 4M+ Diagnosed glaucoma patients (IG)37 OMNI comprehensively treats the conventional outflow pathway Market leader in implant free MIGS YTD revenue of $60.1M, up 7% Y/Y 02 Interventional Dry Eye 7M+ Diagnosed moderate-to-severe MGD patients (IDE)37 Market leader and pioneer of the procedural reimbursed MGD category SAHARA: All mean signs and symptoms remained statistically significantly better than study baseline at all time points measured through 24 months YTD revenue of $7.9M vs. $0.9M PY 03 Proven technologies >500K IG & IDE procedures performed38 TearCare: the first and only MGD treatment indicated to improve meibomian gland function OMNI: the market leading implant-free microinvasive glaucoma surgery IDE procedure growth following Oct '25 MAC fee schedules
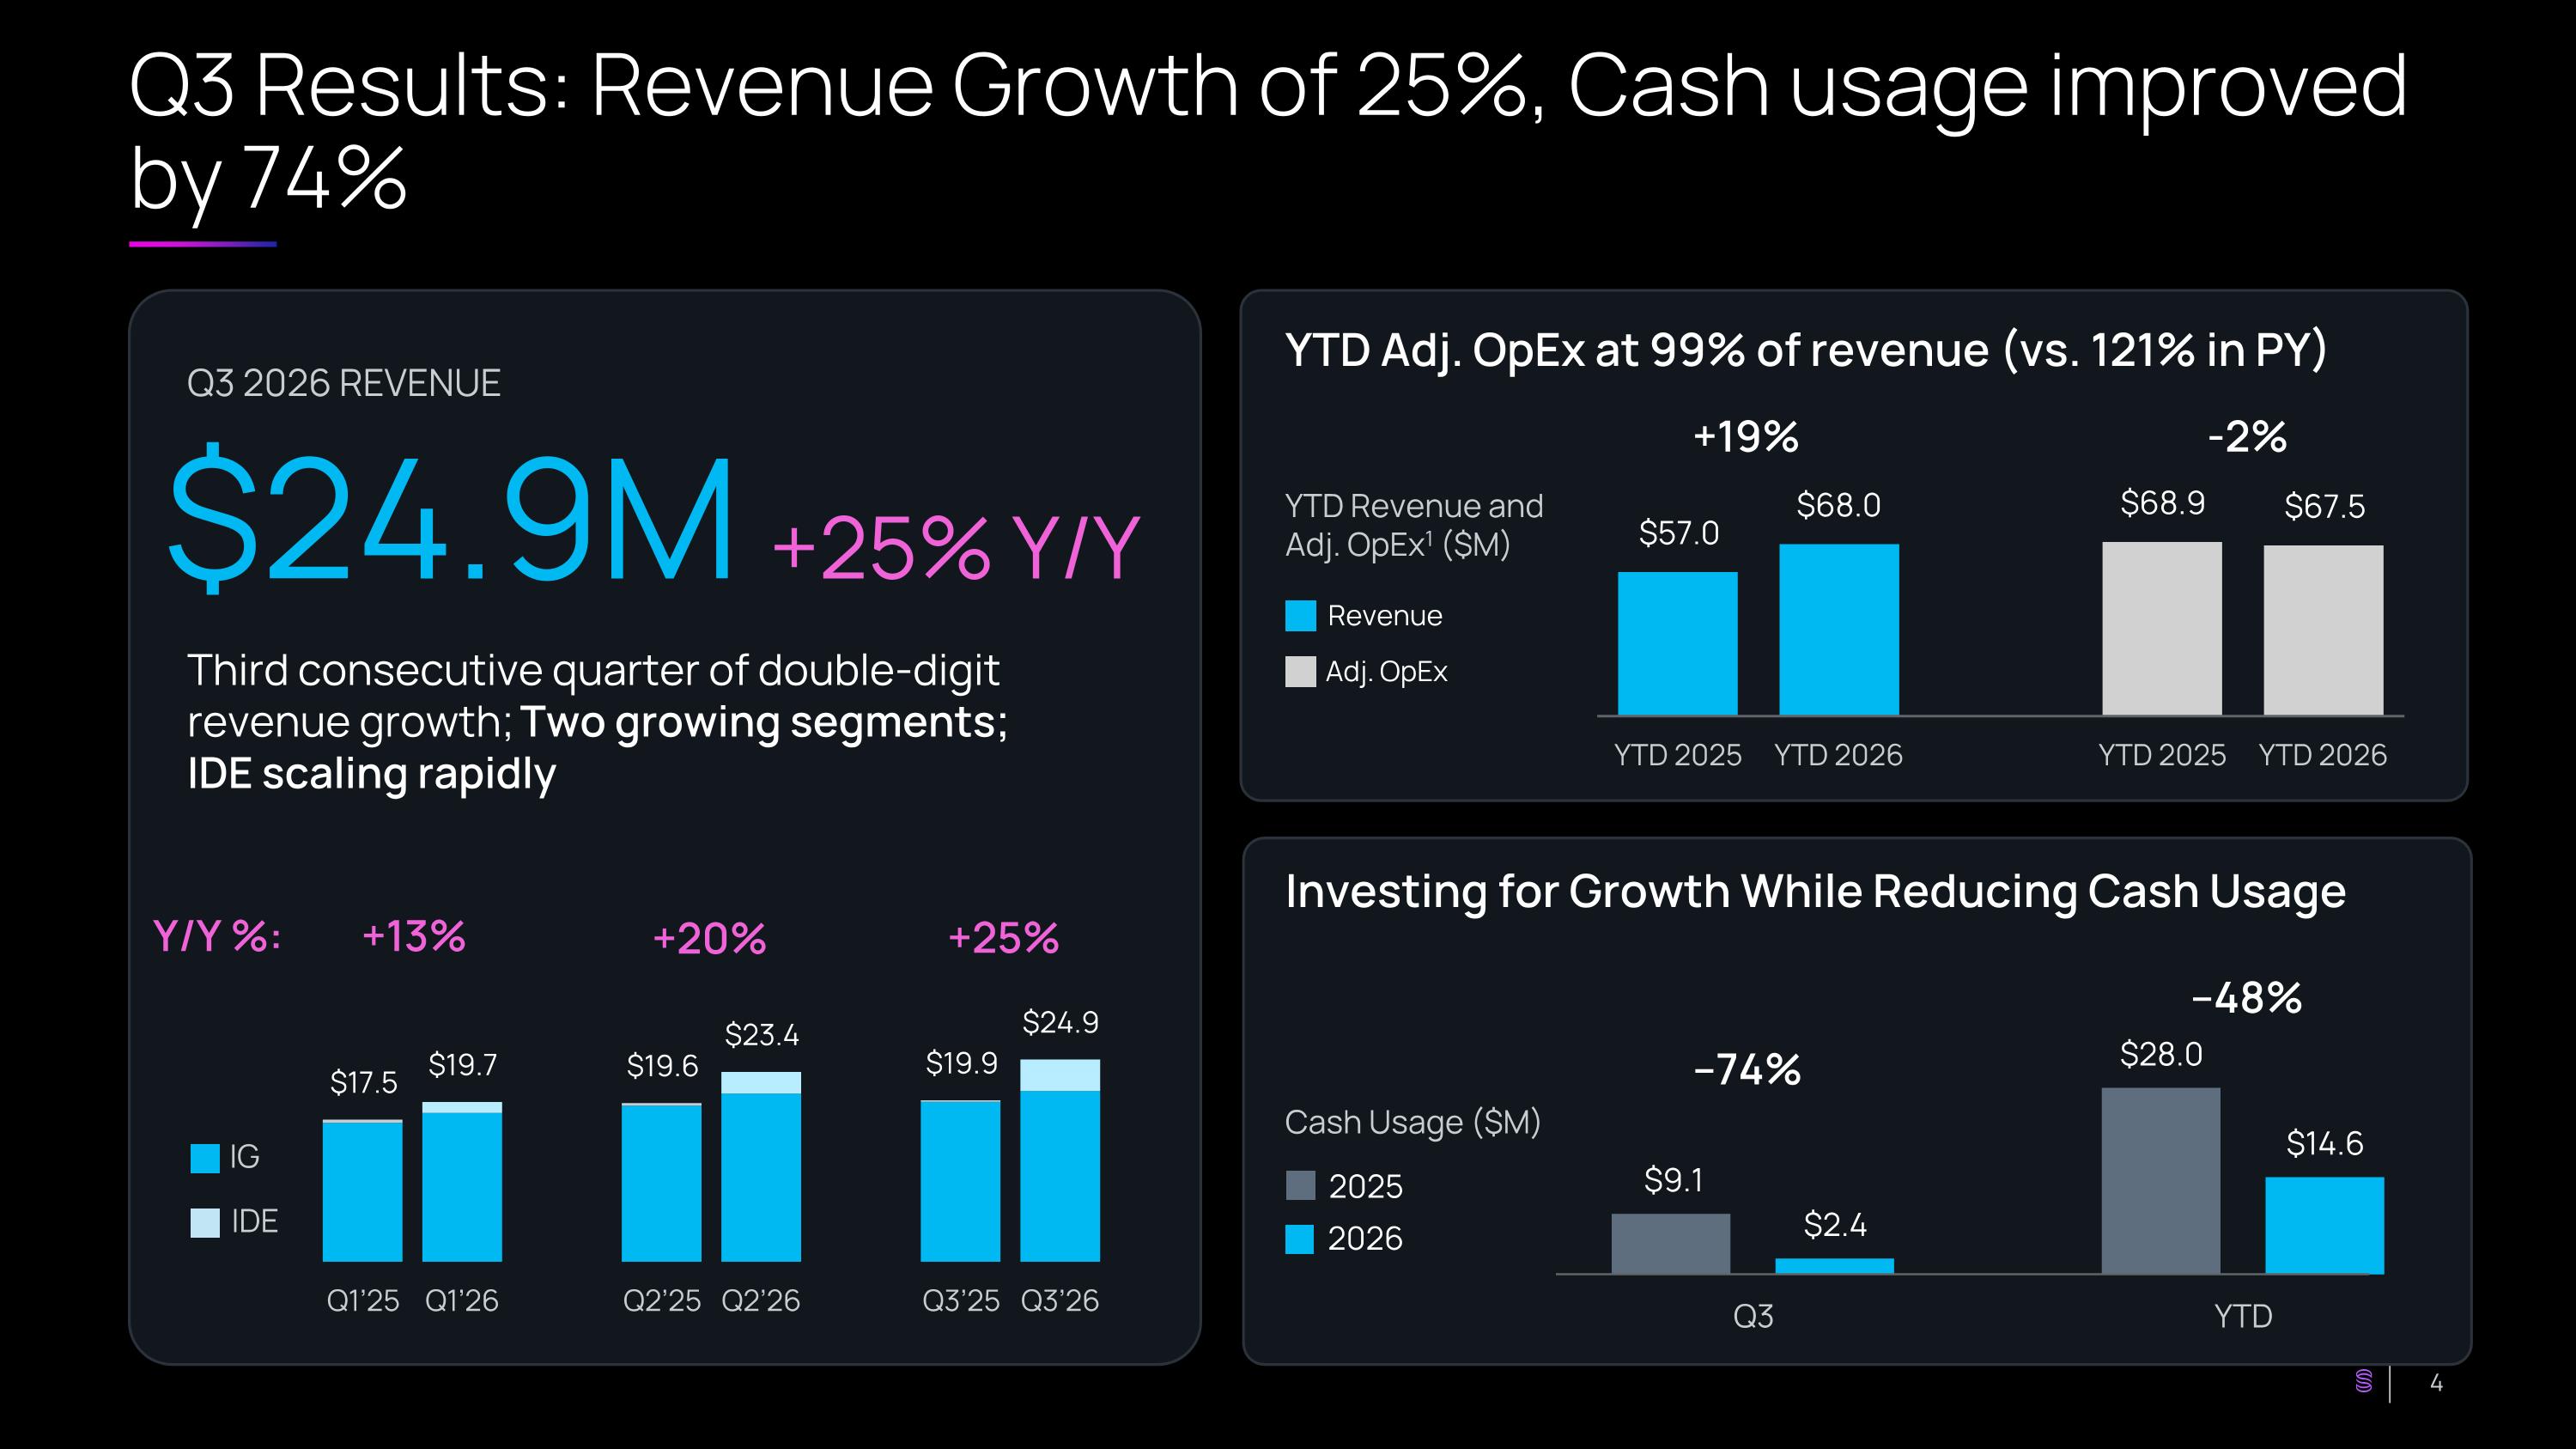
4 Q3 Results: Revenue Growth of 25%, Cash usage improved by 74% Q3 2026 REVENUE $24.9M +25% Y/Y Third consecutive quarter of double-digit revenue growth; Two growing segments; IDE scaling rapidly Investing for Growth While Reducing Cash Usage YTD Adj. OpEx at 99% of revenue (vs. 121% in PY) IG IDE +13% +20% +25% YTD Revenue and Adj. OpEx1 ($M) Revenue Adj. OpEx +19% -2% Cash Usage ($M) –74% –48% 2025 2026 Y/Y %:
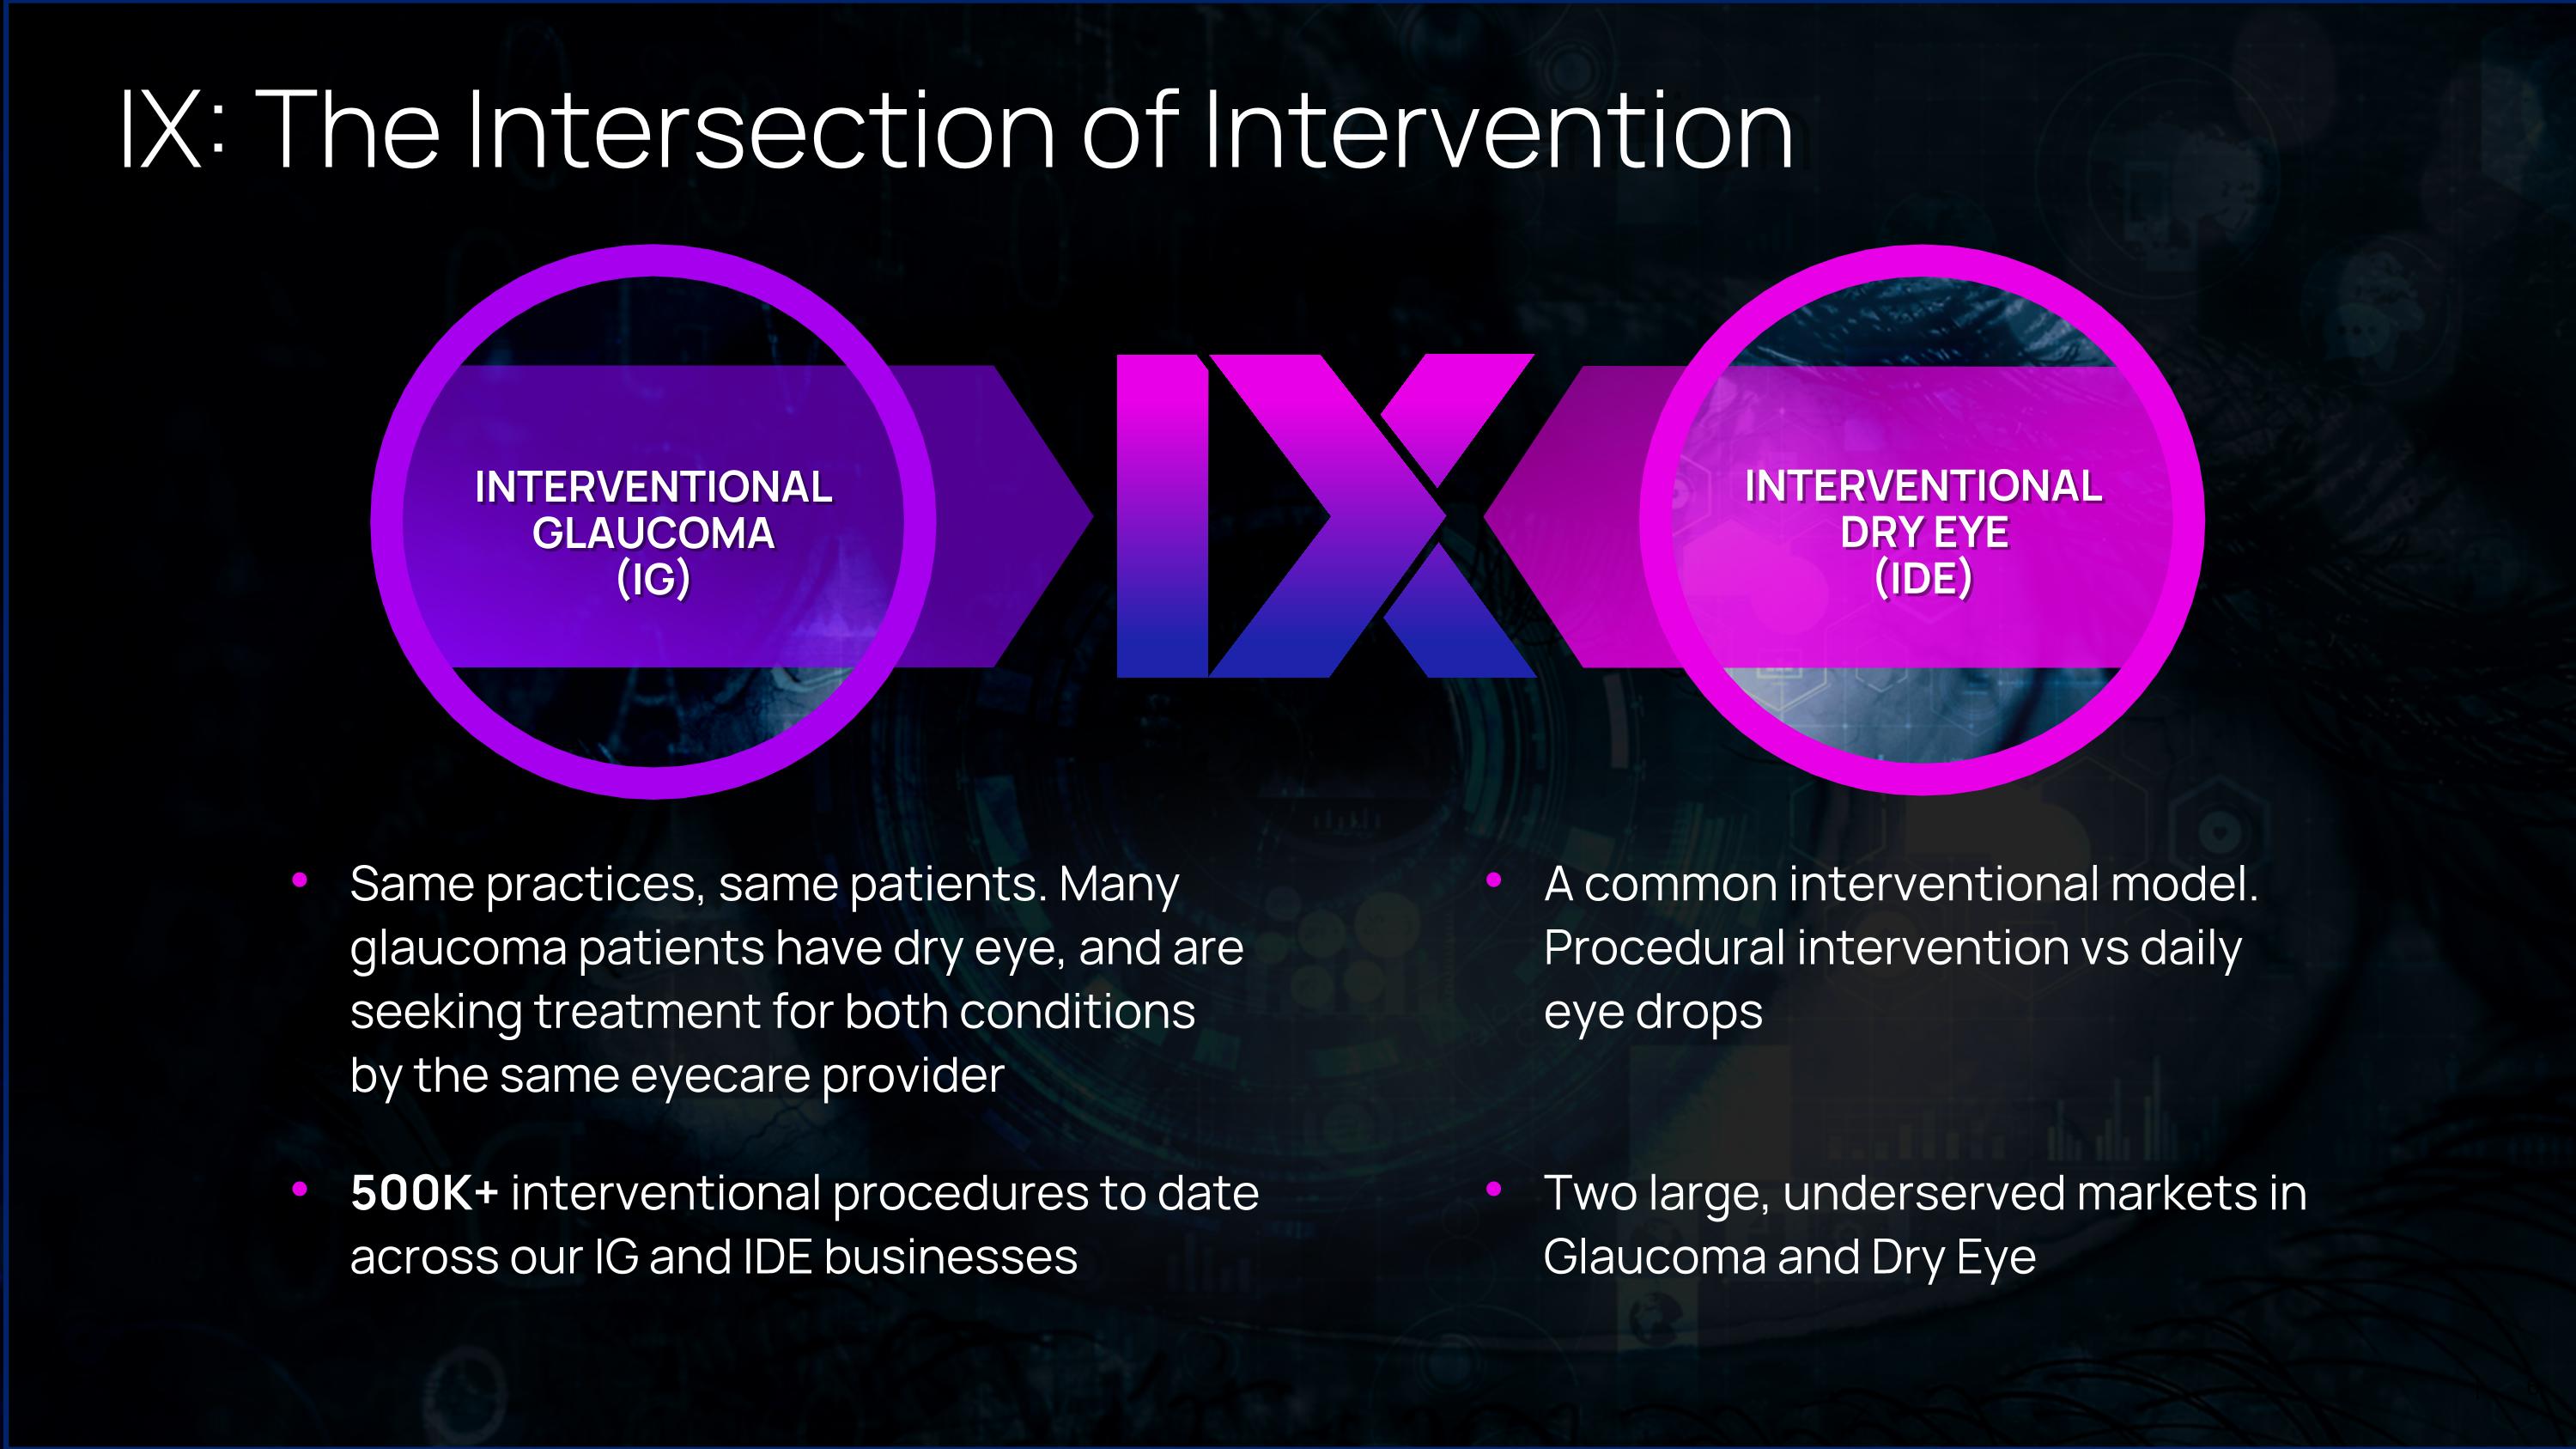
INTERVENTIONAL GLAUCOMA (IG) INTERVENTIONAL DRY EYE (IDE) IX: The Intersection of Intervention Same practices, same patients. Many glaucoma patients have dry eye, and are seeking treatment for both conditions by the same eyecare provider A common interventional model. Procedural intervention vs daily eye drops 500K+ interventional procedures to date across our IG and IDE businesses Two large, underserved markets in Glaucoma and Dry Eye
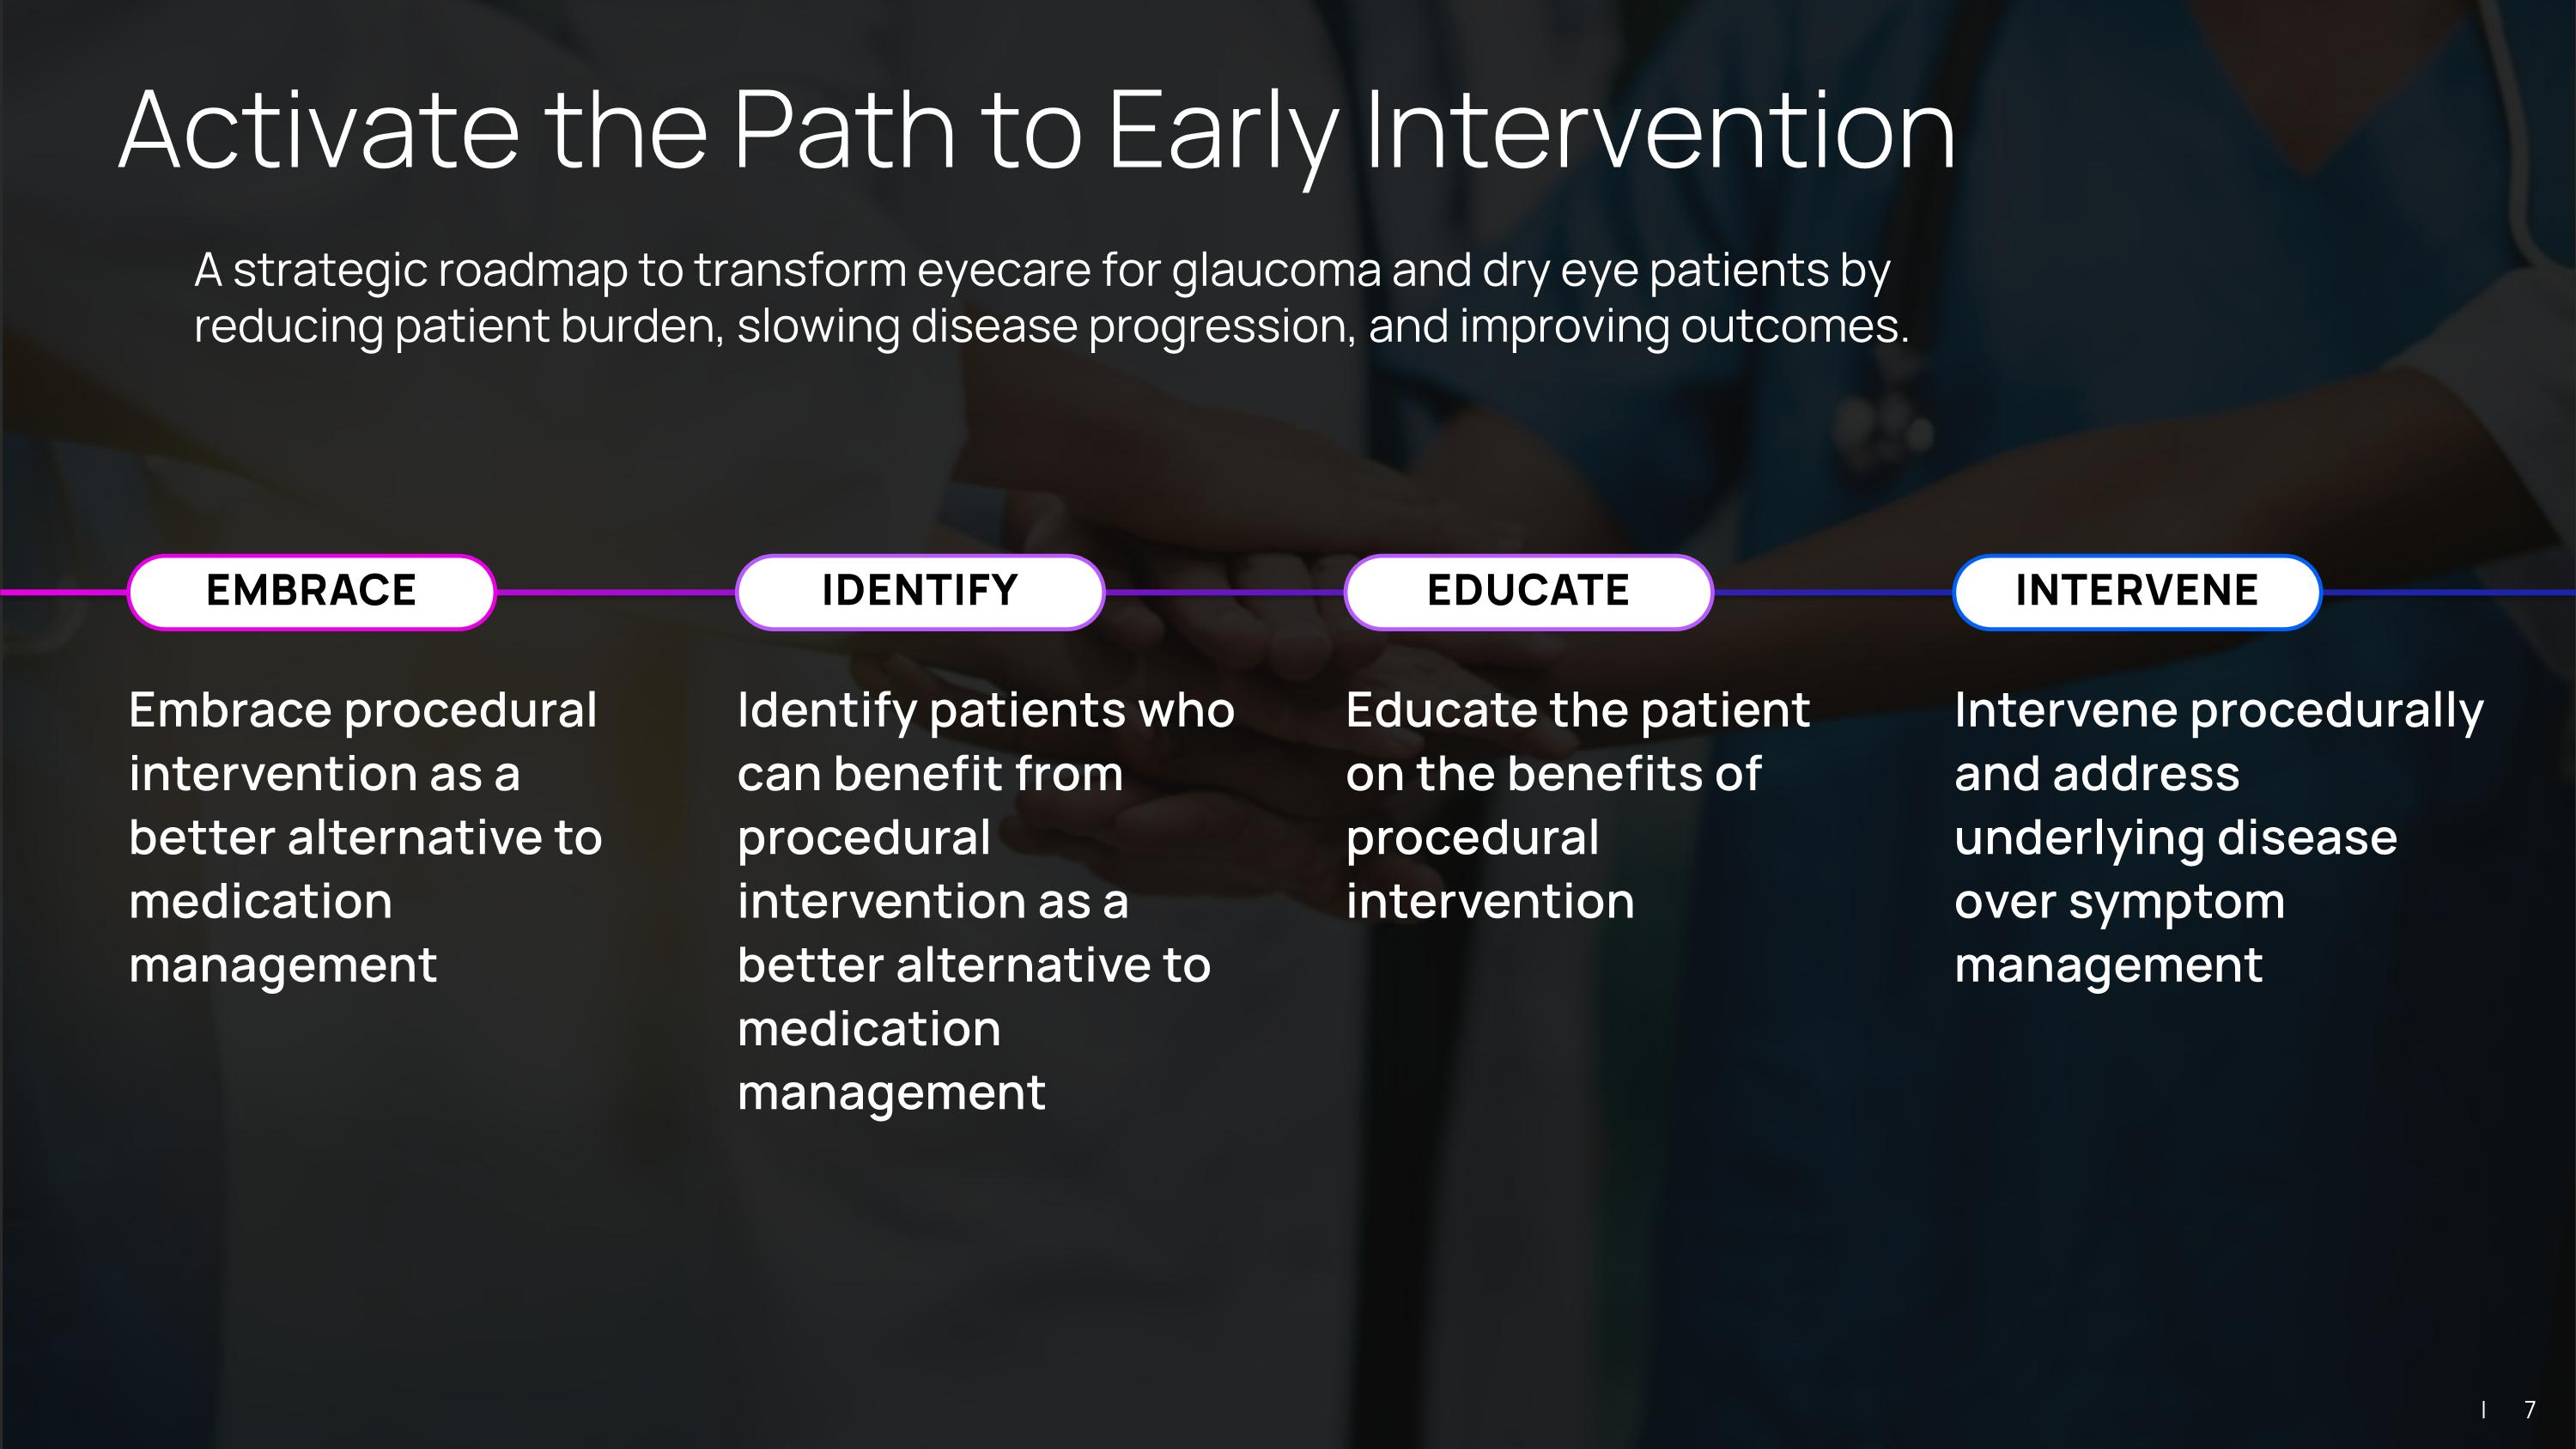
A strategic roadmap to transform eyecare for glaucoma and dry eye patients by reducing patient burden, slowing disease progression, and improving outcomes. Embrace procedural intervention as a better alternative to medication management Intervene procedurally and address underlying disease over symptom management EMBRACE INTERVENE Identify patients who can benefit from procedural intervention as a better alternative to medication management IDENTIFY Activate the Path to Early Intervention EDUCATE Educate the patient on the benefits of procedural intervention | 7
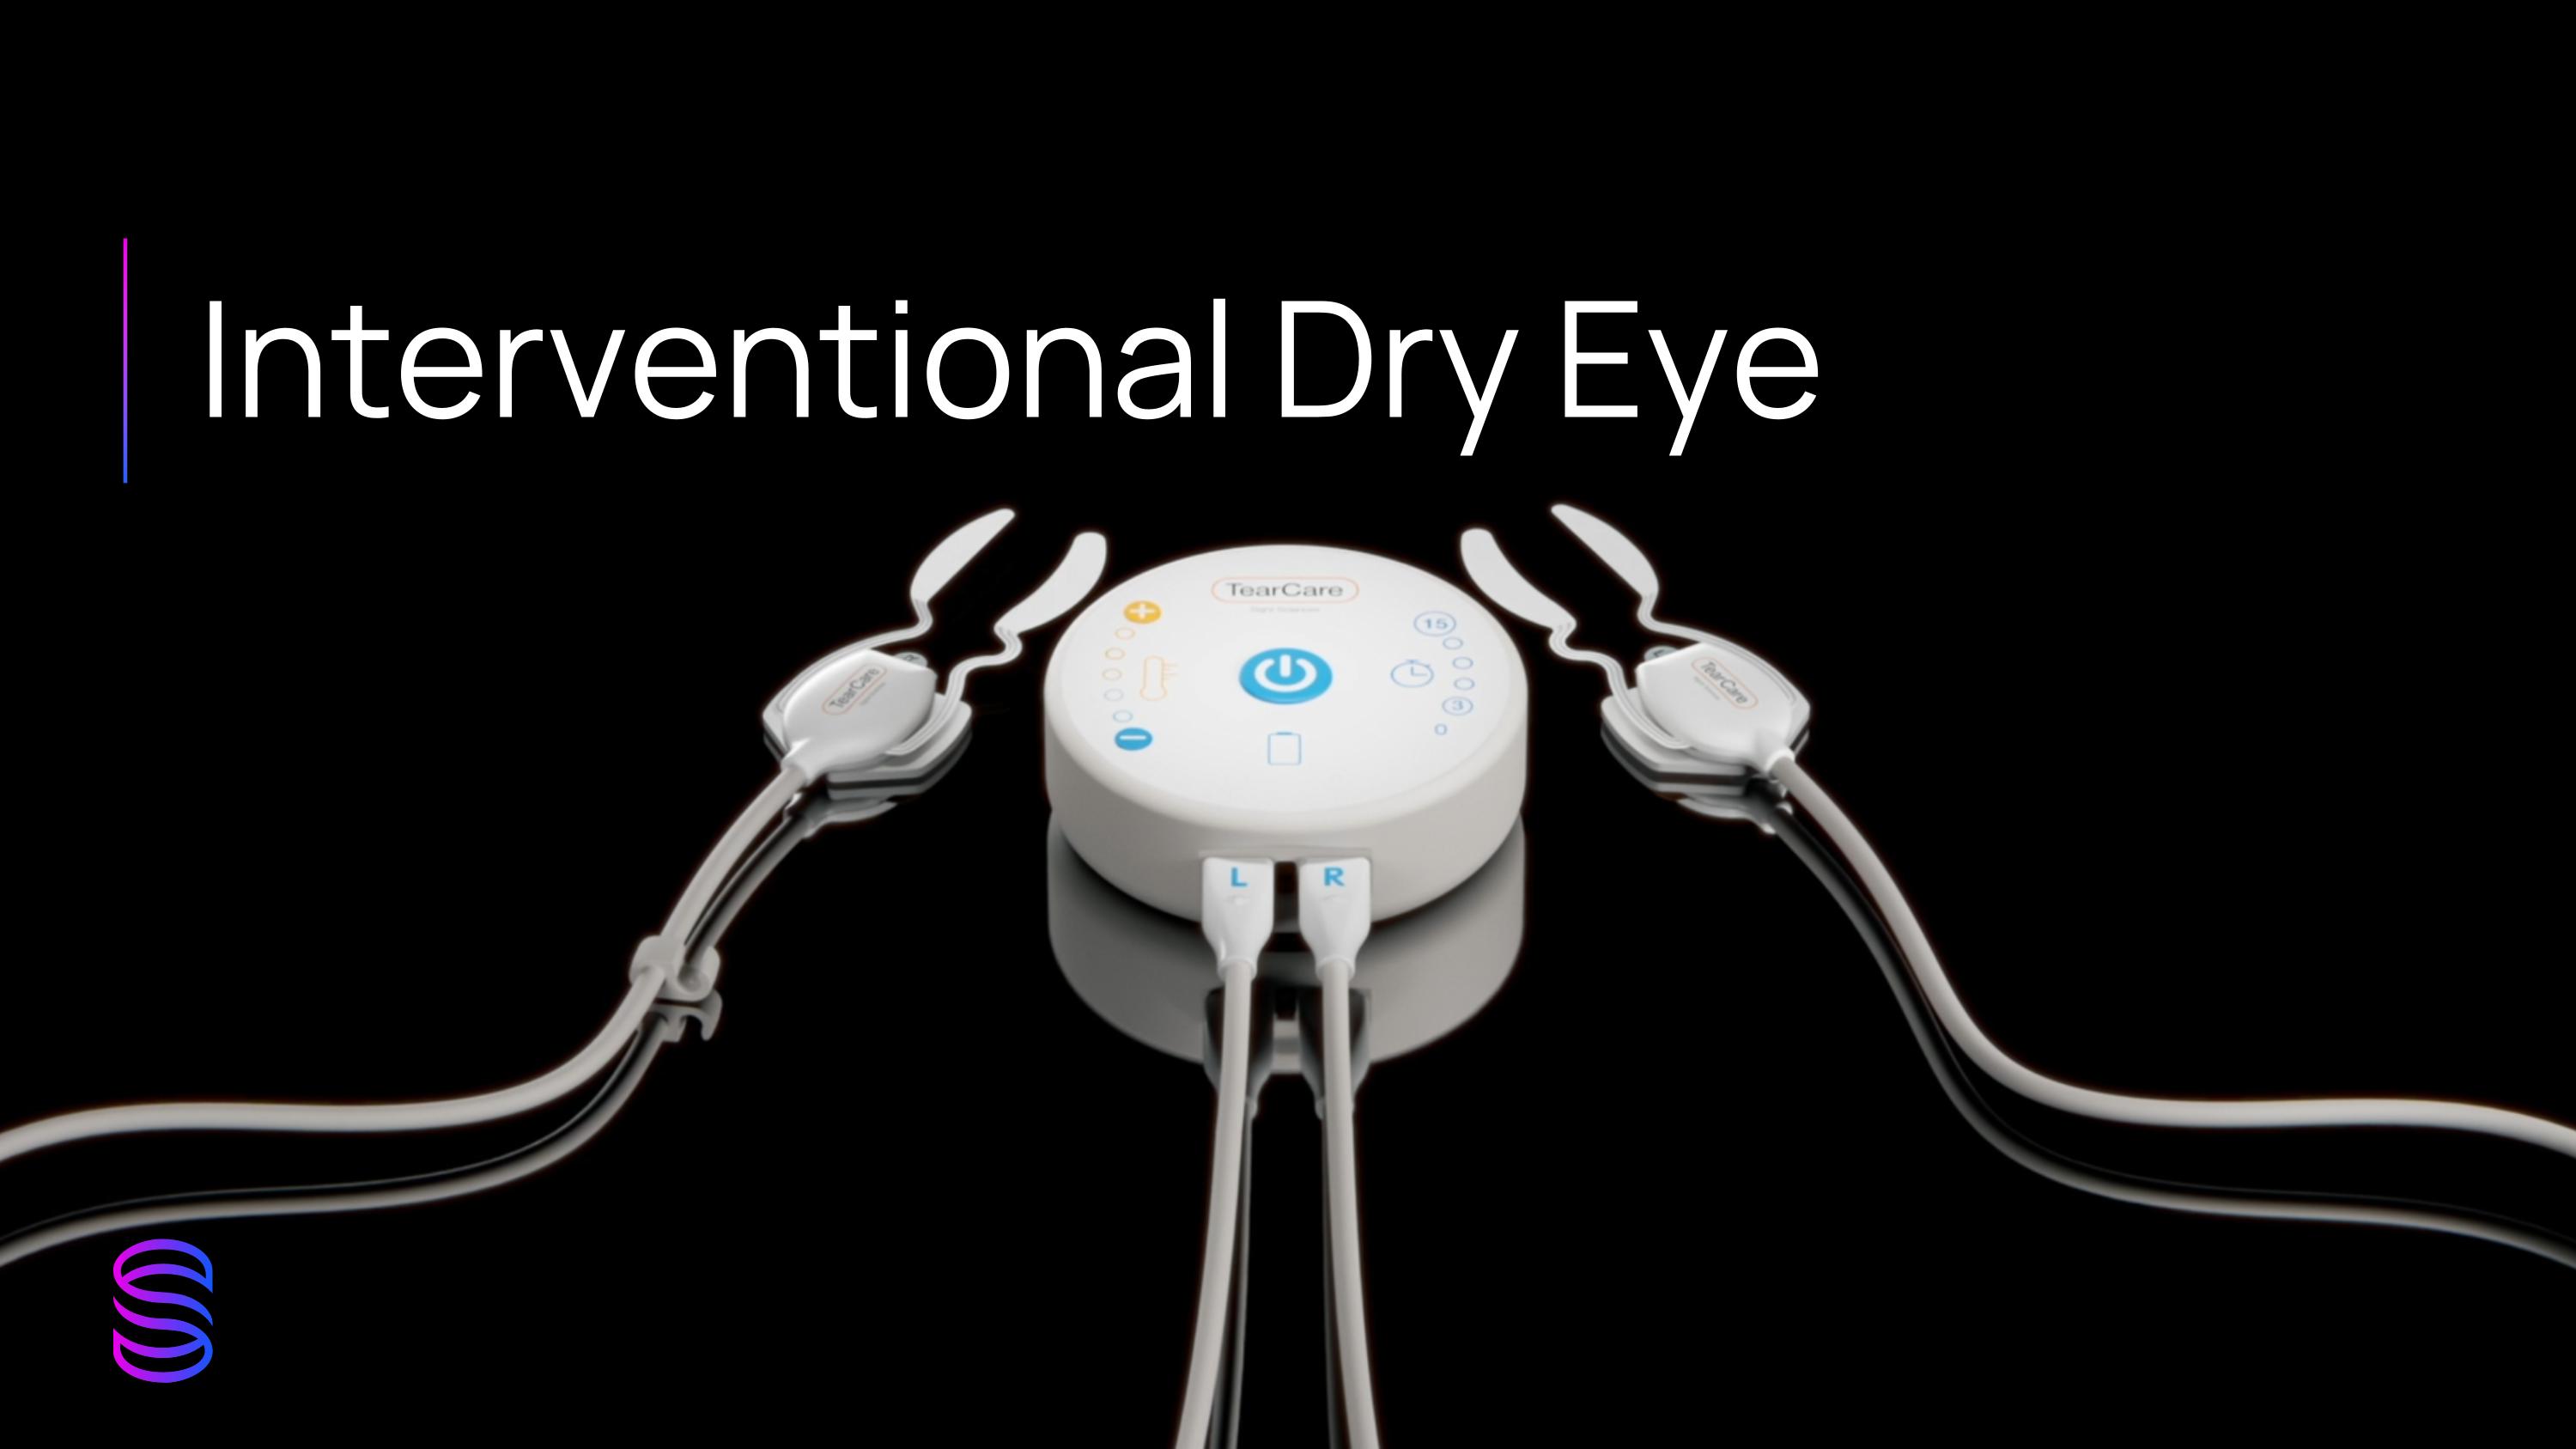
Interventional Dry Eye
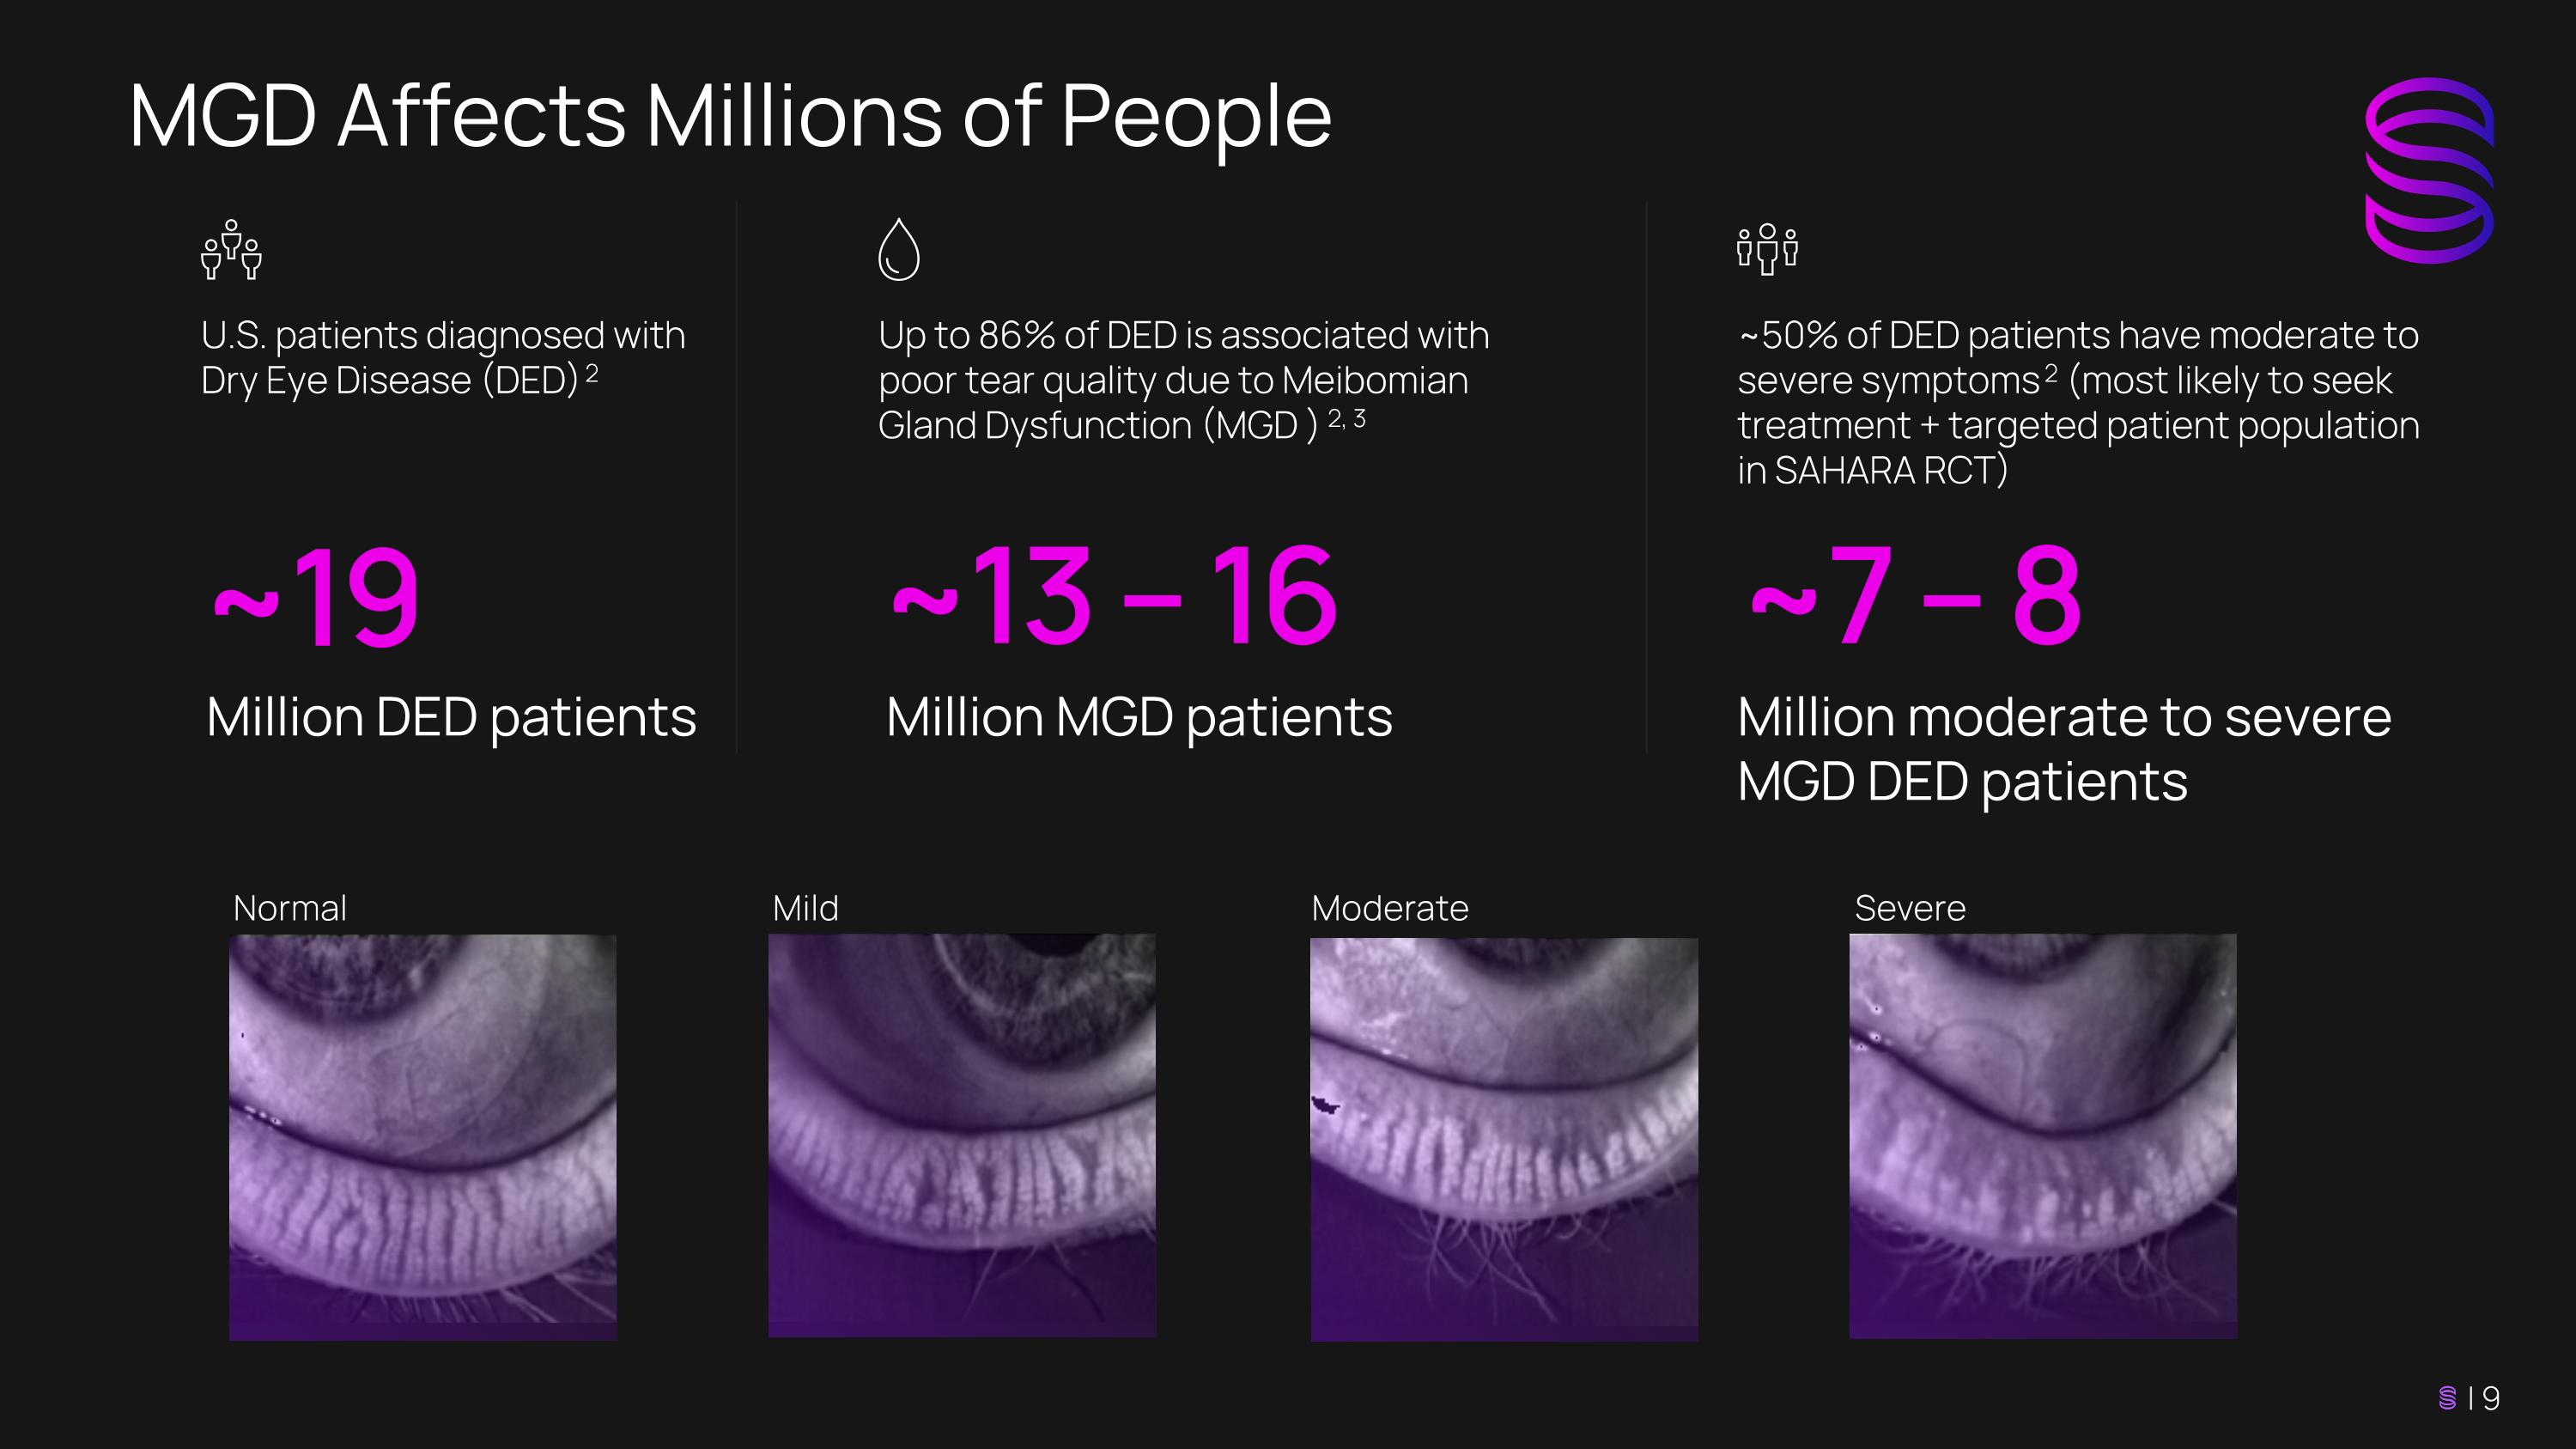
MGD Affects Millions of People U.S. patients diagnosed with Dry Eye Disease (DED) 2 Million DED patients ~19 Up to 86% of DED is associated with poor tear quality due to Meibomian Gland Dysfunction (MGD ) 2, 3 Million MGD patients ~13 – 16 ~50% of DED patients have moderate to severe symptoms 2 (most likely to seek treatment + targeted patient population in SAHARA RCT) Million moderate to severe MGD DED patients ~7 – 8 Normal Mild Moderate Severe
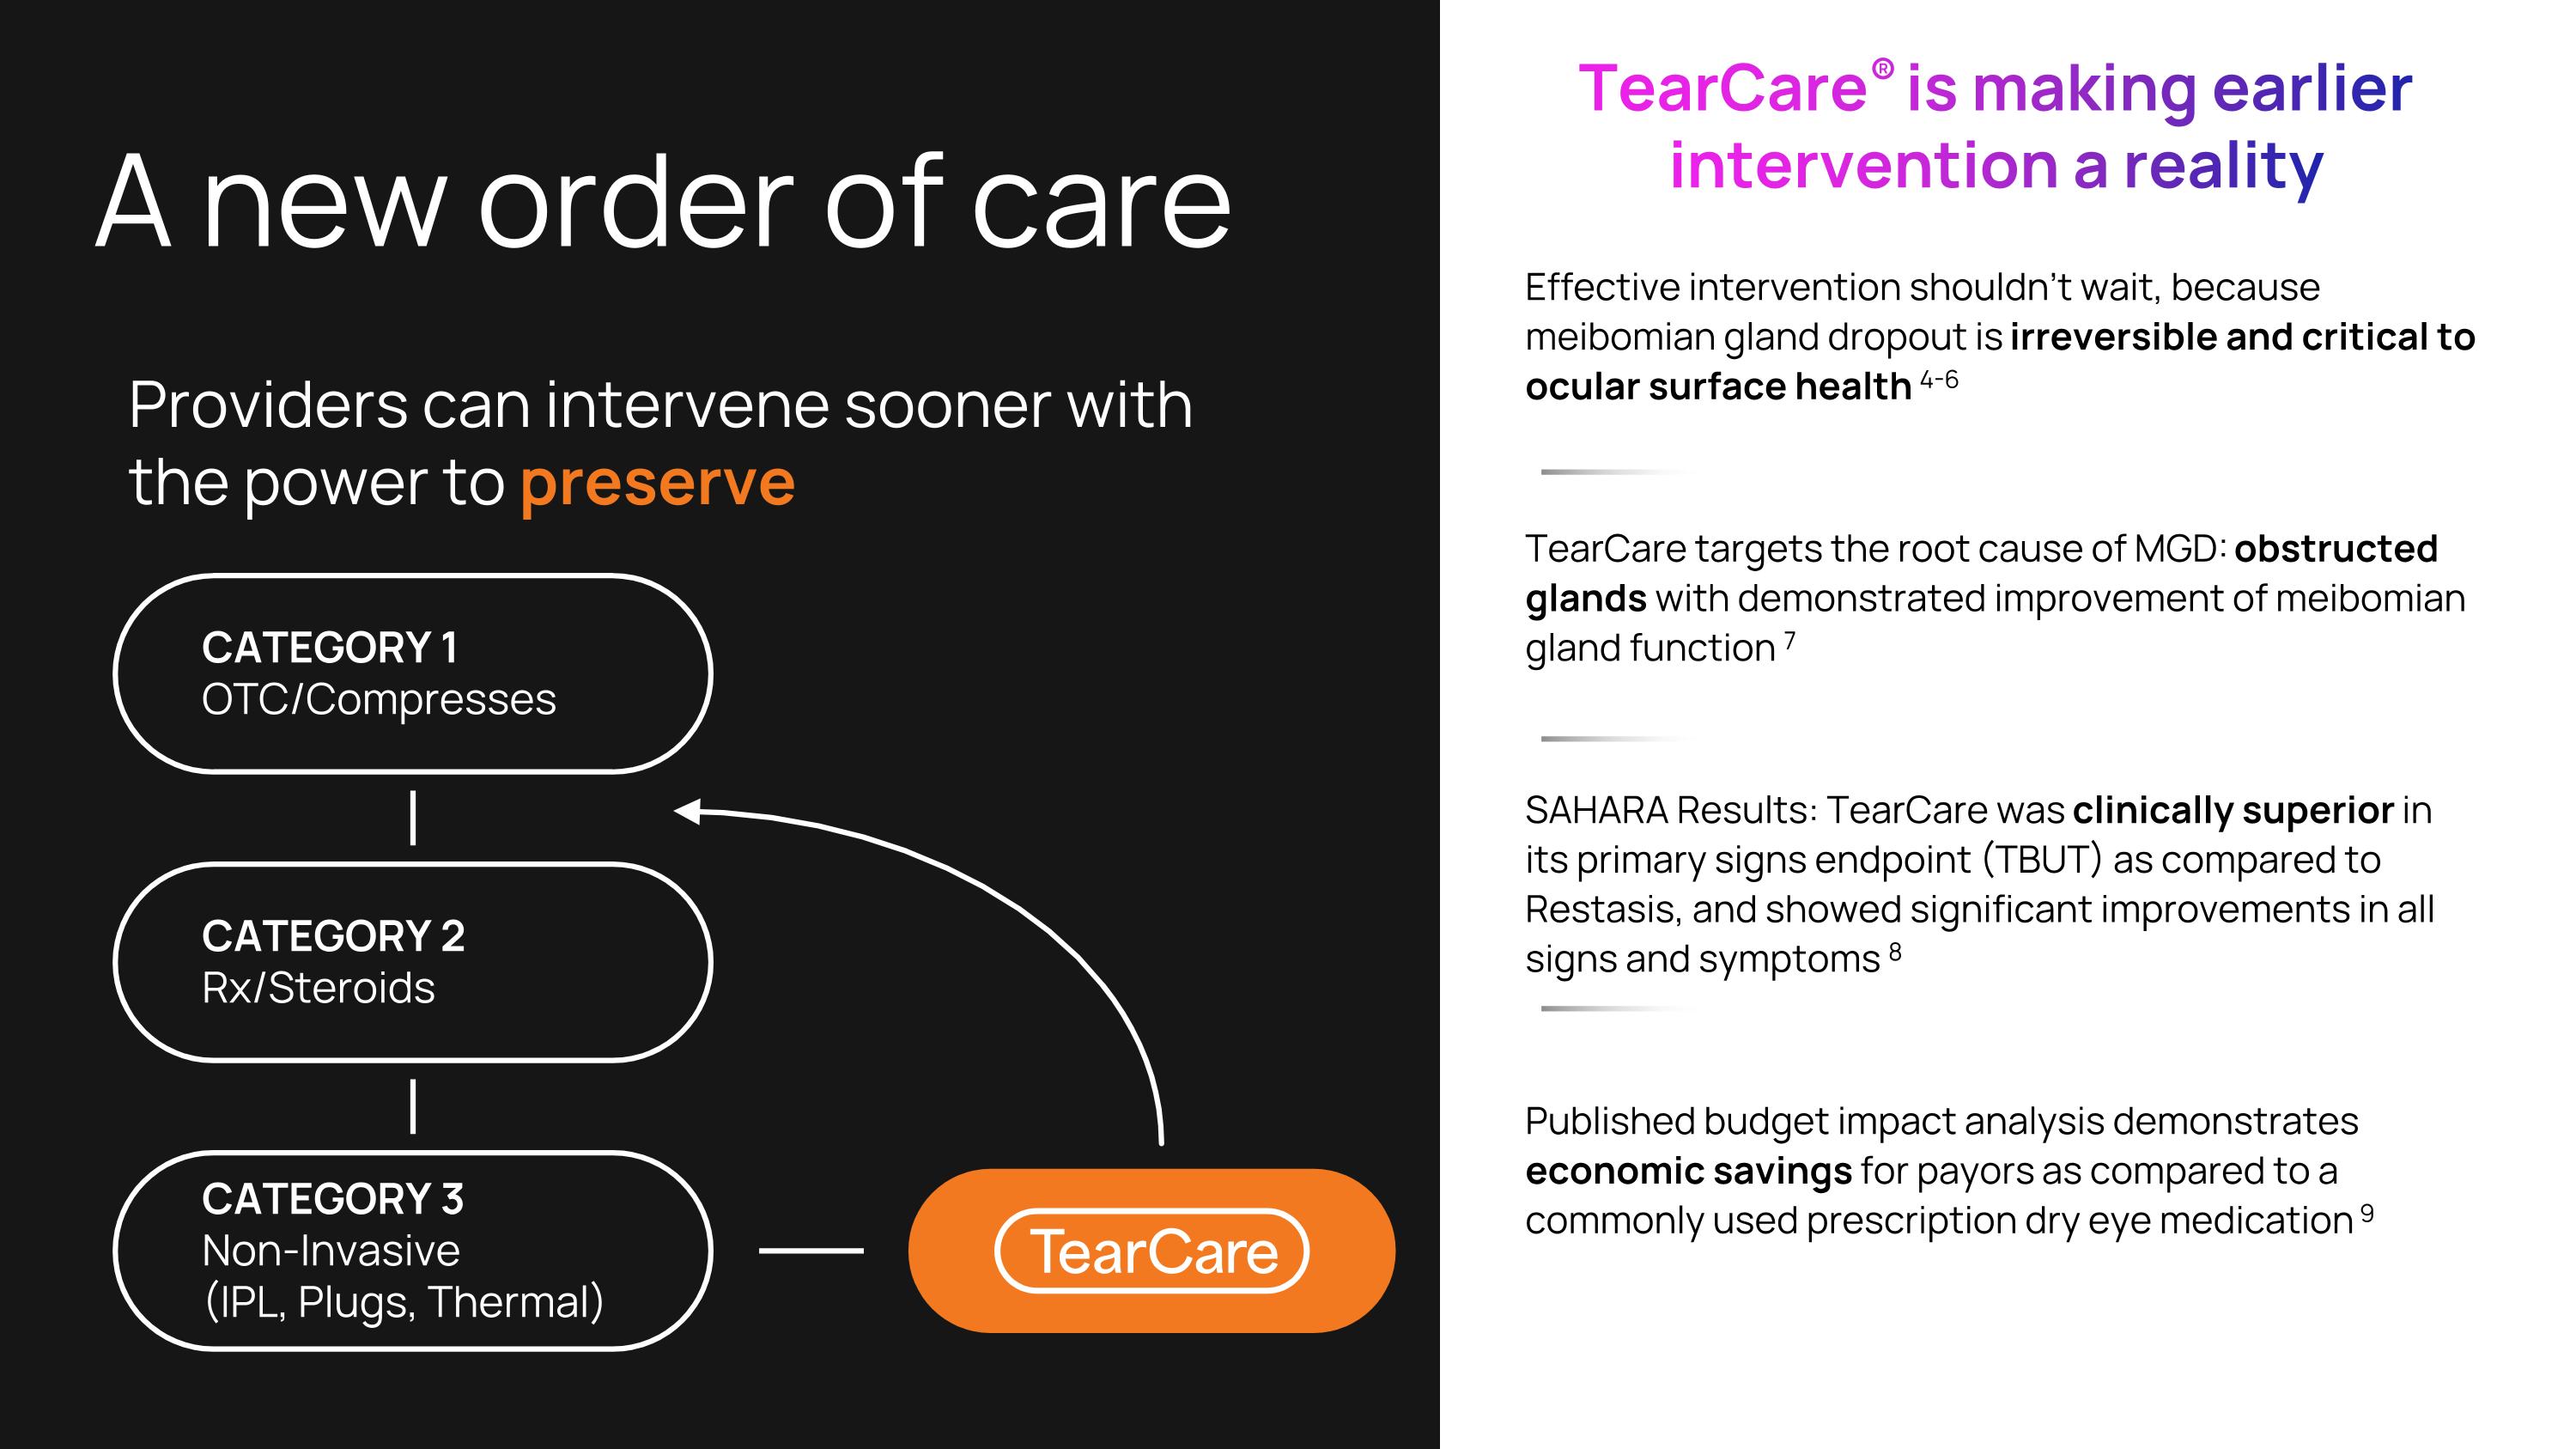
A new order of care Effective intervention shouldn’t wait, because meibomian gland dropout is irreversible and critical to ocular surface health 4-6 TearCare targets the root cause of MGD: obstructed glands with demonstrated improvement of meibomian gland function 7 SAHARA Results: TearCare was clinically superior in its primary signs endpoint (TBUT) as compared to Restasis, and showed significant improvements in all signs and symptoms 8 Published budget impact analysis demonstrates economic savings for payors as compared to a commonly used prescription dry eye medication 9 Providers can intervene sooner with the power to preserve TearCare® is making earlier intervention a reality CATEGORY 1 OTC/Compresses CATEGORY 2 Rx/Steroids CATEGORY 3 Non-Invasive (IPL, Plugs, Thermal)

MGD is an Underserved Disease State The current market is dominated by eyedrops that do not address the underlying causes of MGD 10 Many dry eye treatments focus on increasing tear volume in aqueous deficient patients No interventional standard of care for treatment of MGD There is poor patient compliance with the use of Rx and OTC eyedrops for treatment 11
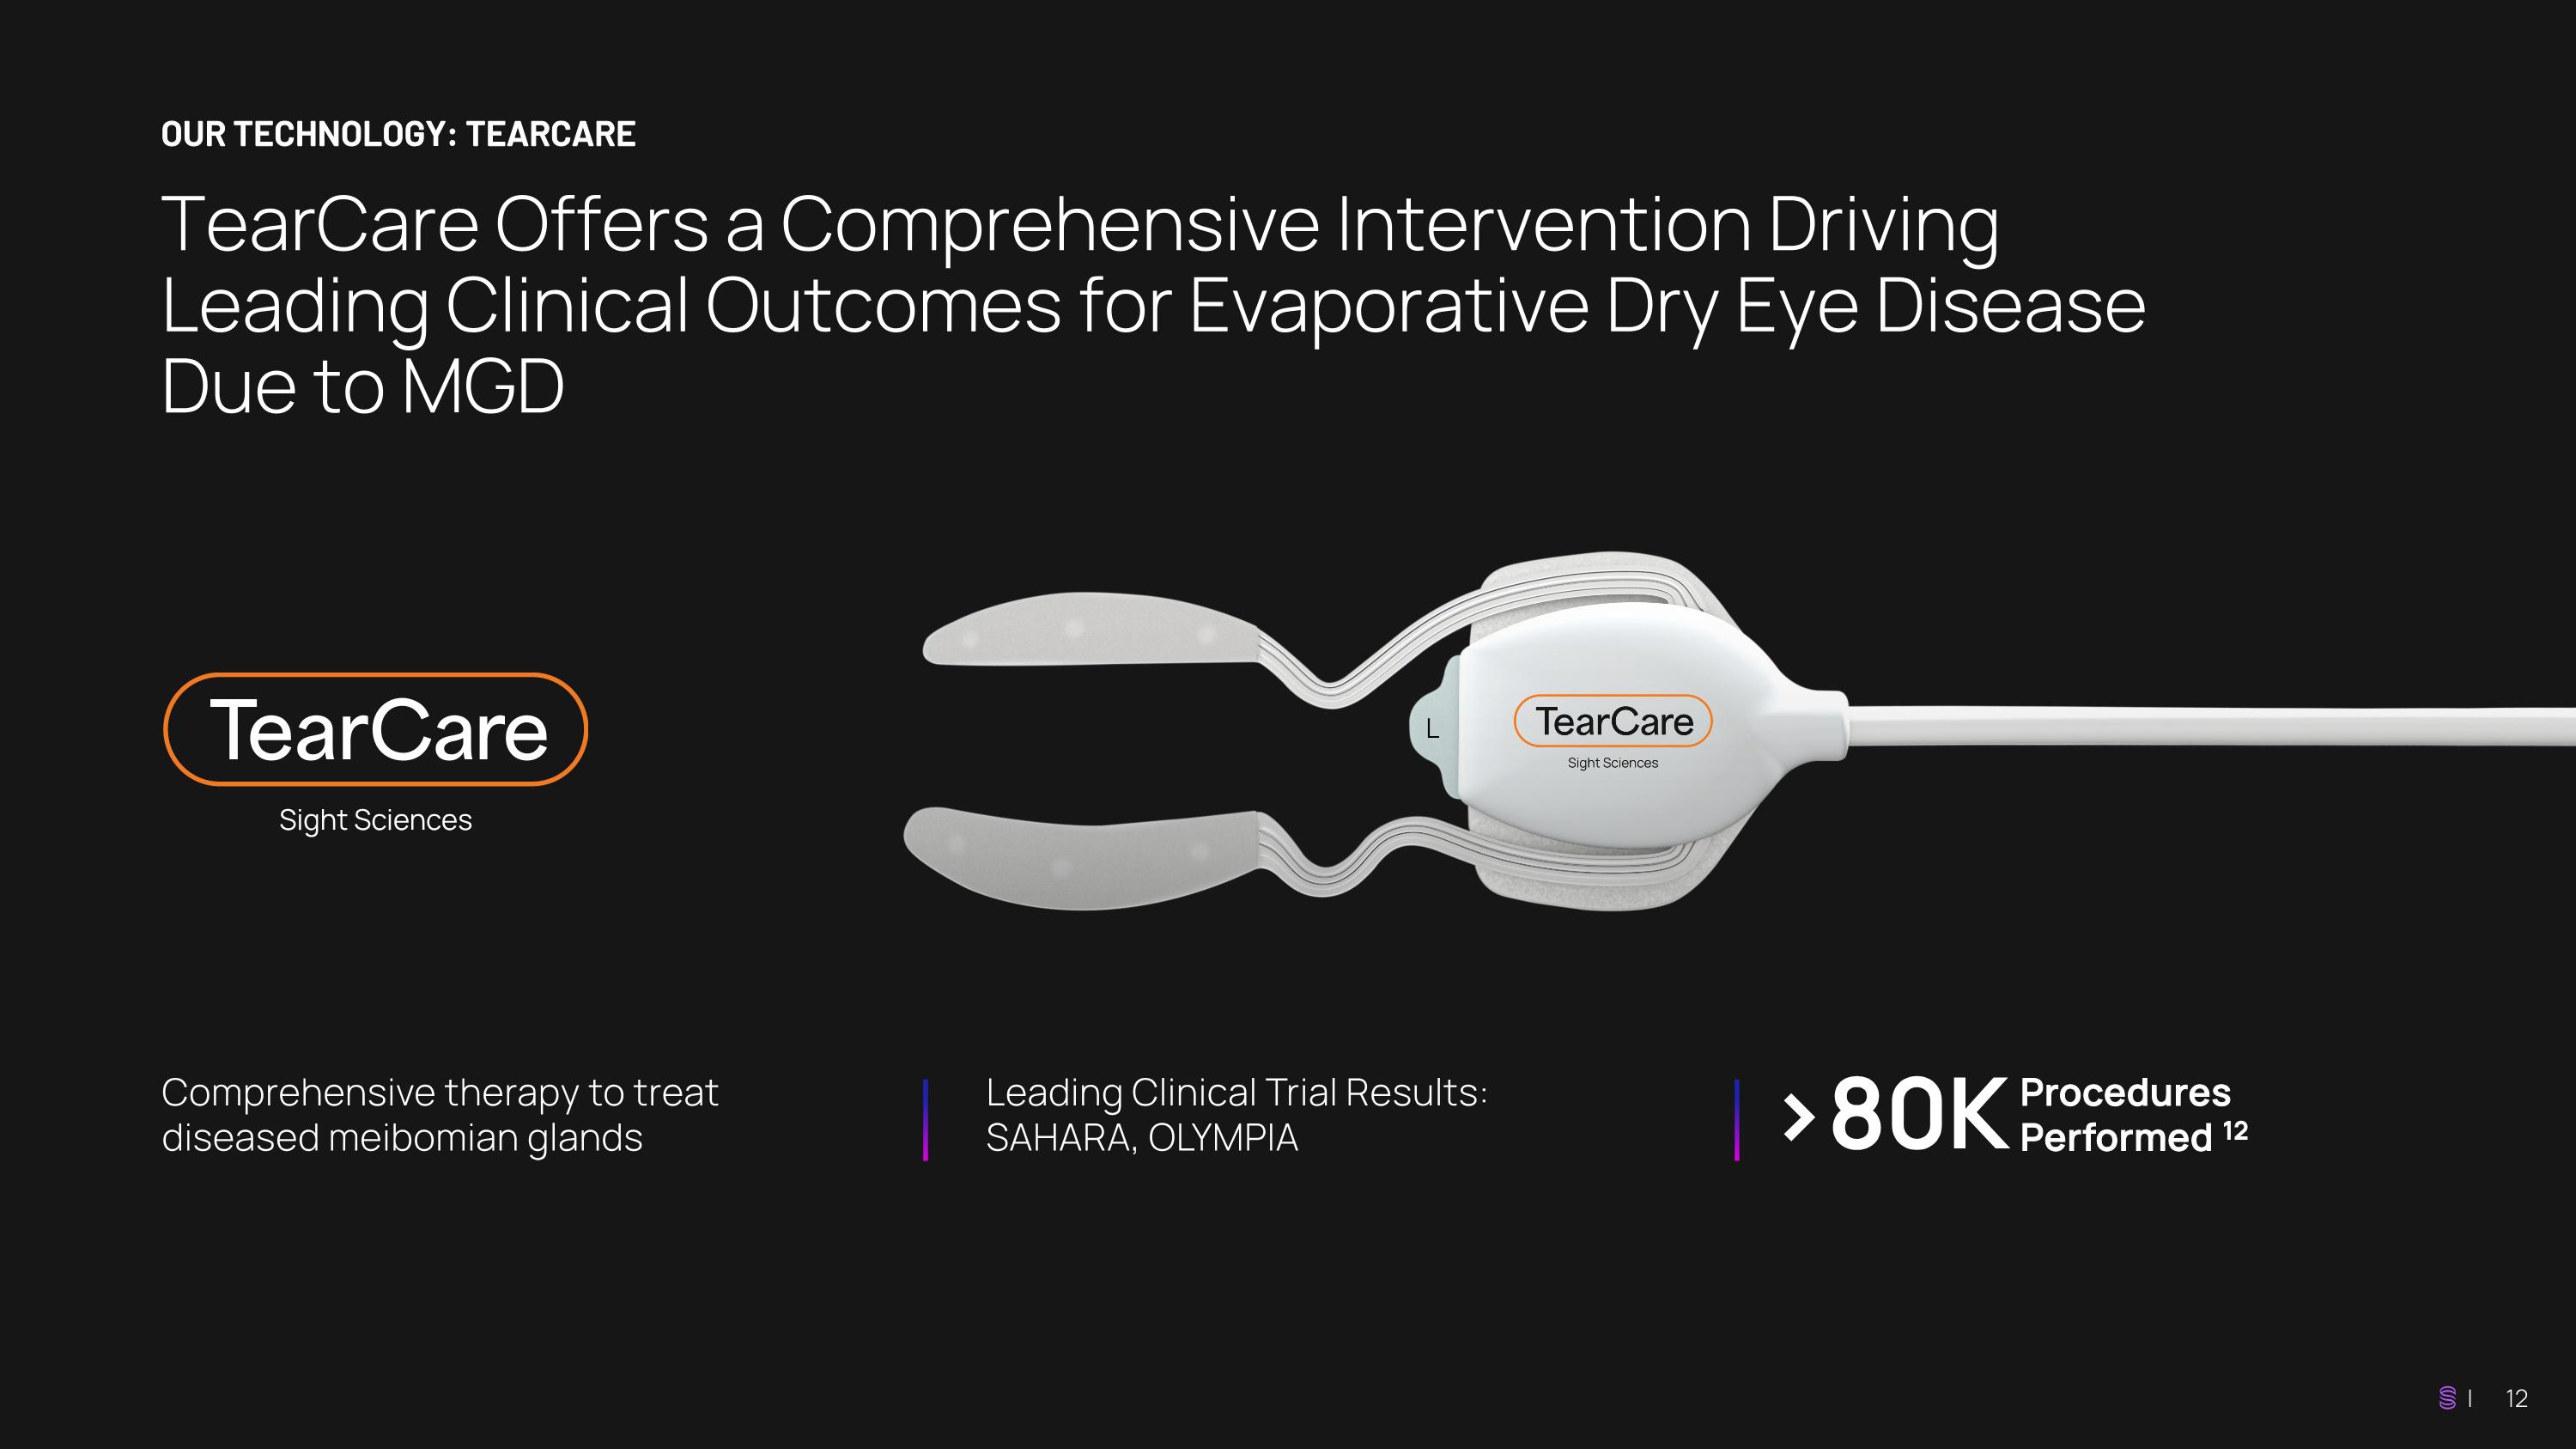
TearCare Offers a Comprehensive Intervention Driving Leading Clinical Outcomes for Evaporative Dry Eye Disease Due to MGD OUR TECHNOLOGY: TEARCARE Comprehensive therapy to treat diseased meibomian glands Leading Clinical Trial Results: SAHARA, OLYMPIA >80K Procedures Performed 12

TearCare: The first and only MGD Treatment Indicated to Improve Meibomian Gland Function Thin, wearable SmartLids® conform to the eyelid and allow natural blinking Precise, consistent, software- controlled thermal therapeutic melting cycle (at 45°C +/- 0.7°C for 15 minutes)13 Comprehensive gland clearing protocol allows providers to manually evacuate the melted meibum comfortably 01 Application 02 Therapy 03 Expression

SAHARA: Randomized Controlled Trial comparing TearCare and Restasis®14 - Signs Superiority + Durability 15 - Head-to-Head Study TearCare vs Restasis 14 - Large Trial (N=345) - Randomized - Assessor Masked - 3 Stages - Long-term (2-year trial)
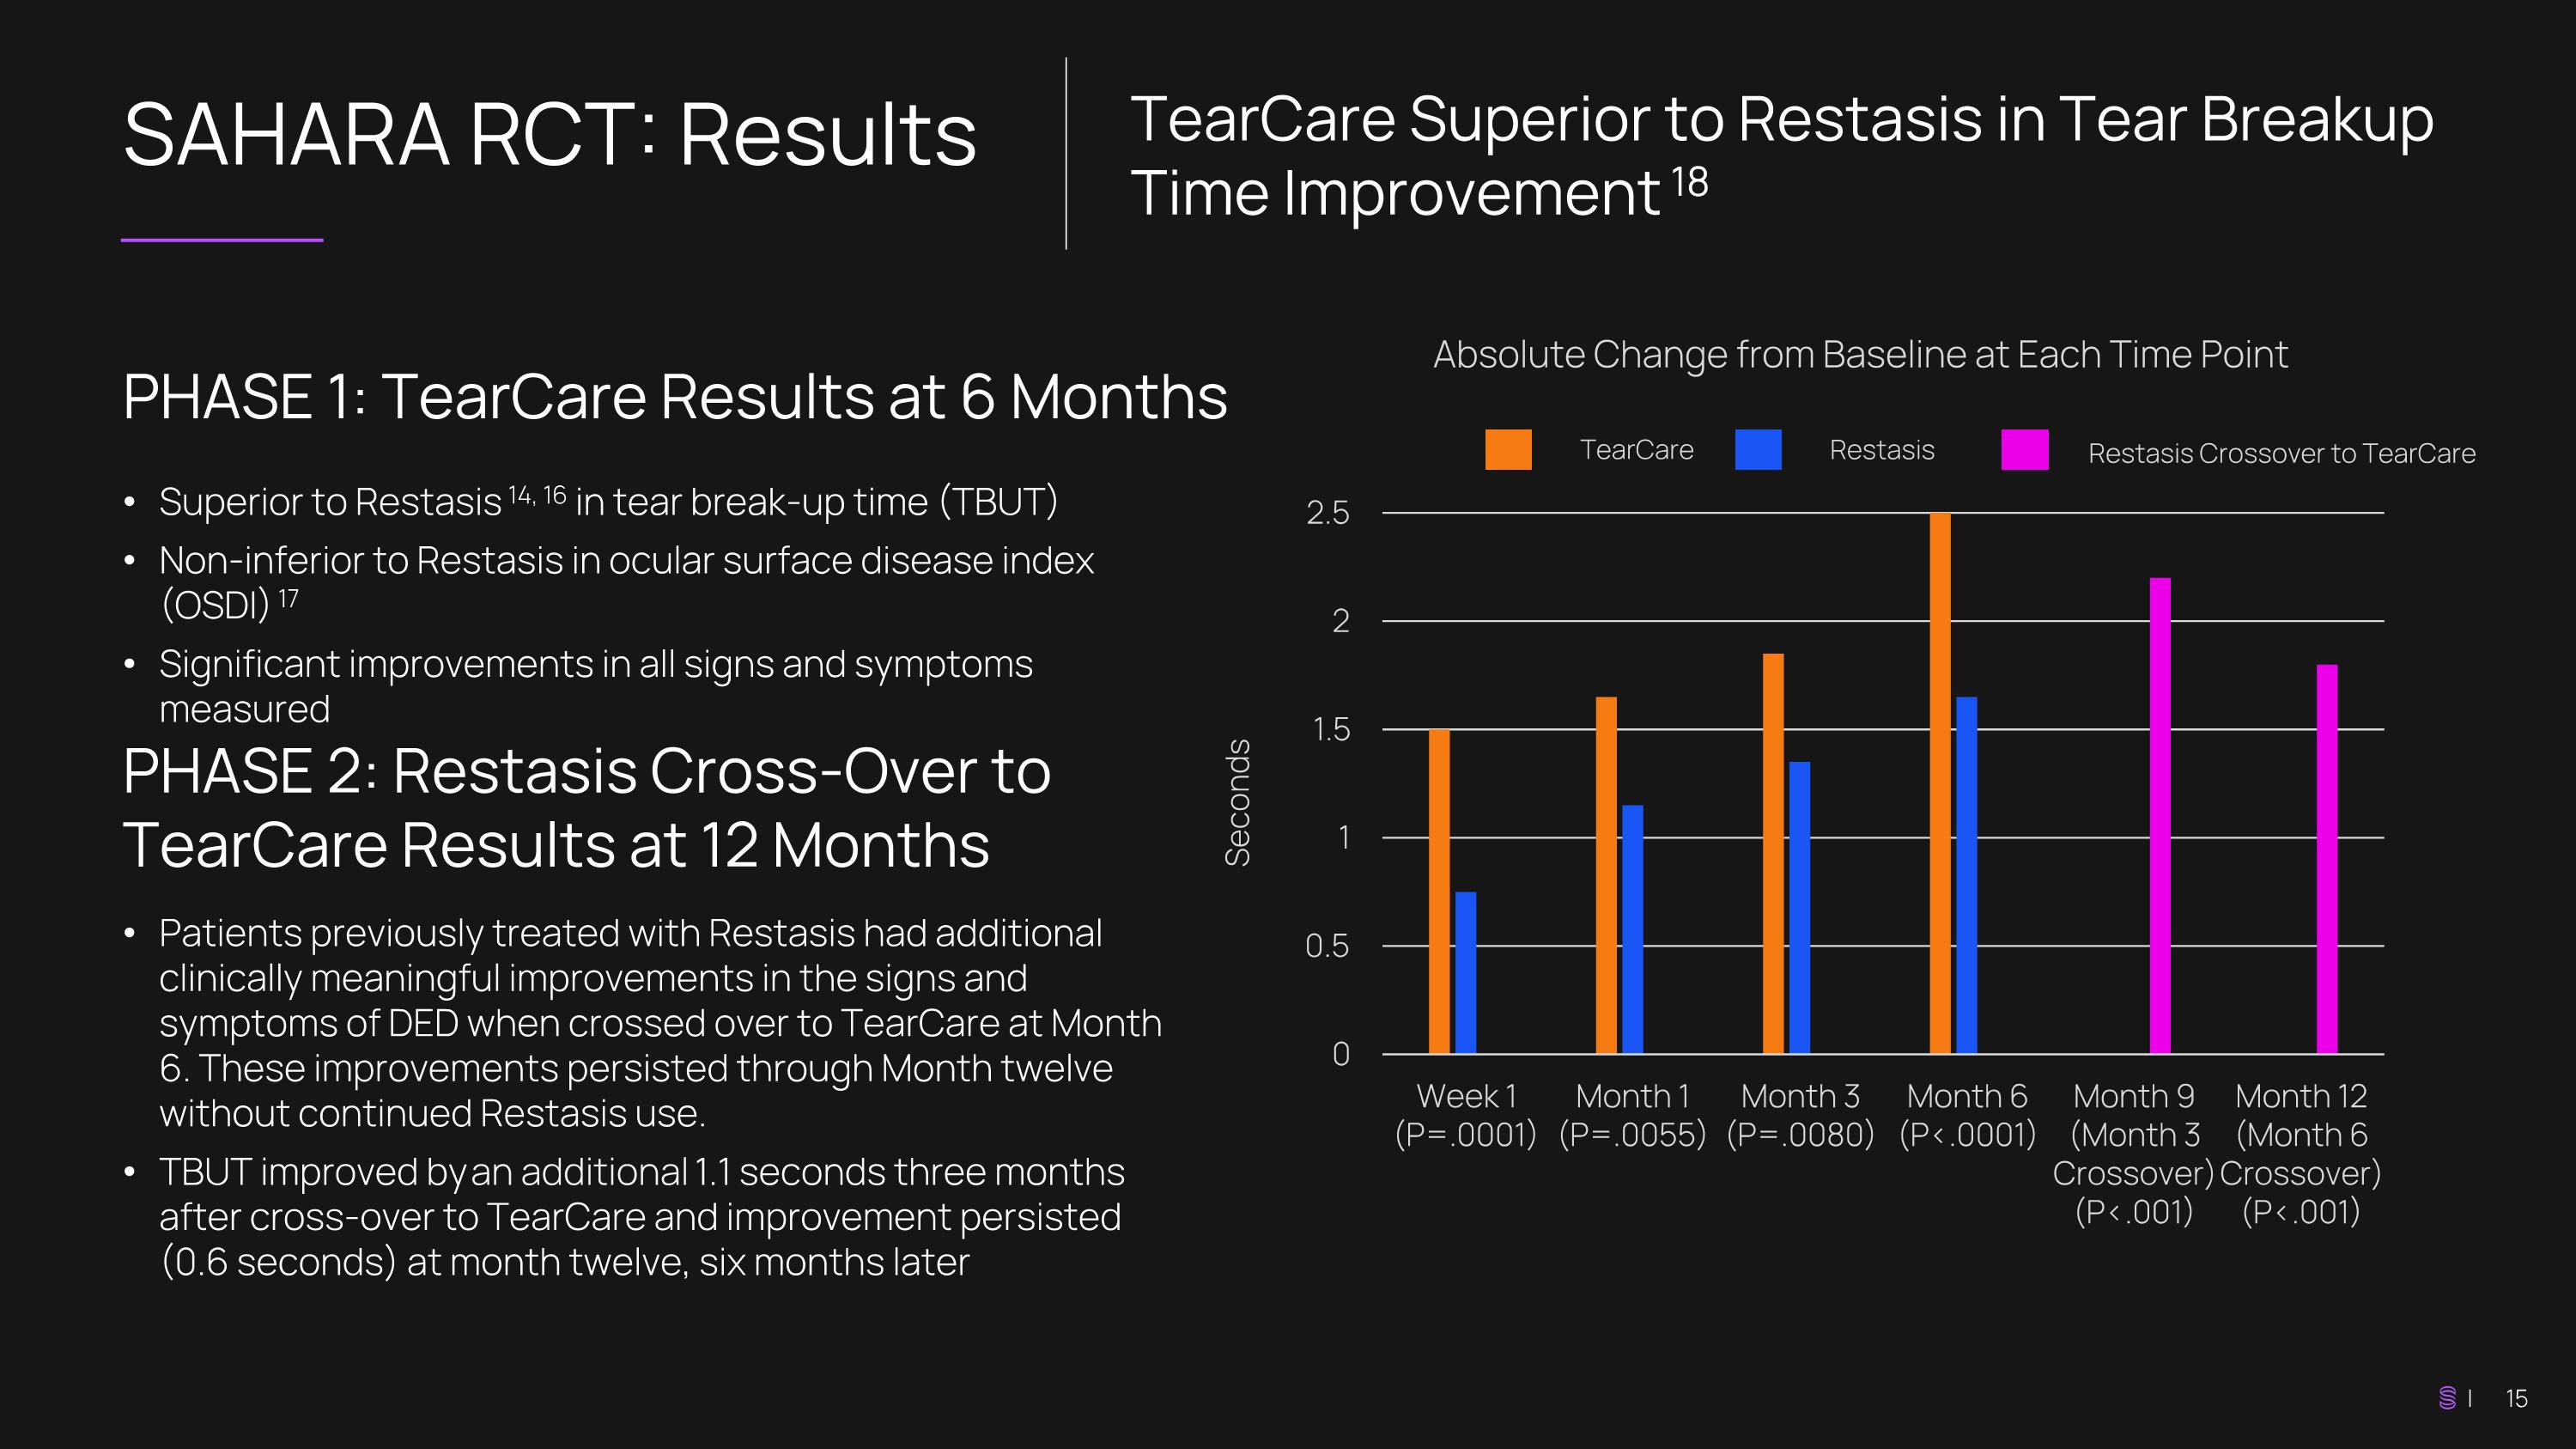
SAHARA RCT: Results TearCare Superior to Restasis in Tear Breakup Time Improvement 18 PHASE 1: TearCare Results at 6 Months Superior to Restasis 14, 16 in tear break-up time (TBUT) Non-inferior to Restasis in ocular surface disease index (OSDI) 17 Significant improvements in all signs and symptoms measured Seconds Absolute Change from Baseline at Each Time Point TearCare Restasis Patients previously treated with Restasis had additional clinically meaningful improvements in the signs and symptoms of DED when crossed over to TearCare at Month 6. These improvements persisted through Month twelve without continued Restasis use. TBUT improved by an additional 1.1 seconds three months after cross-over to TearCare and improvement persisted (0.6 seconds) at month twelve, six months later PHASE 2: Restasis Cross-Over to TearCare Results at 12 Months Restasis Crossover to TearCare
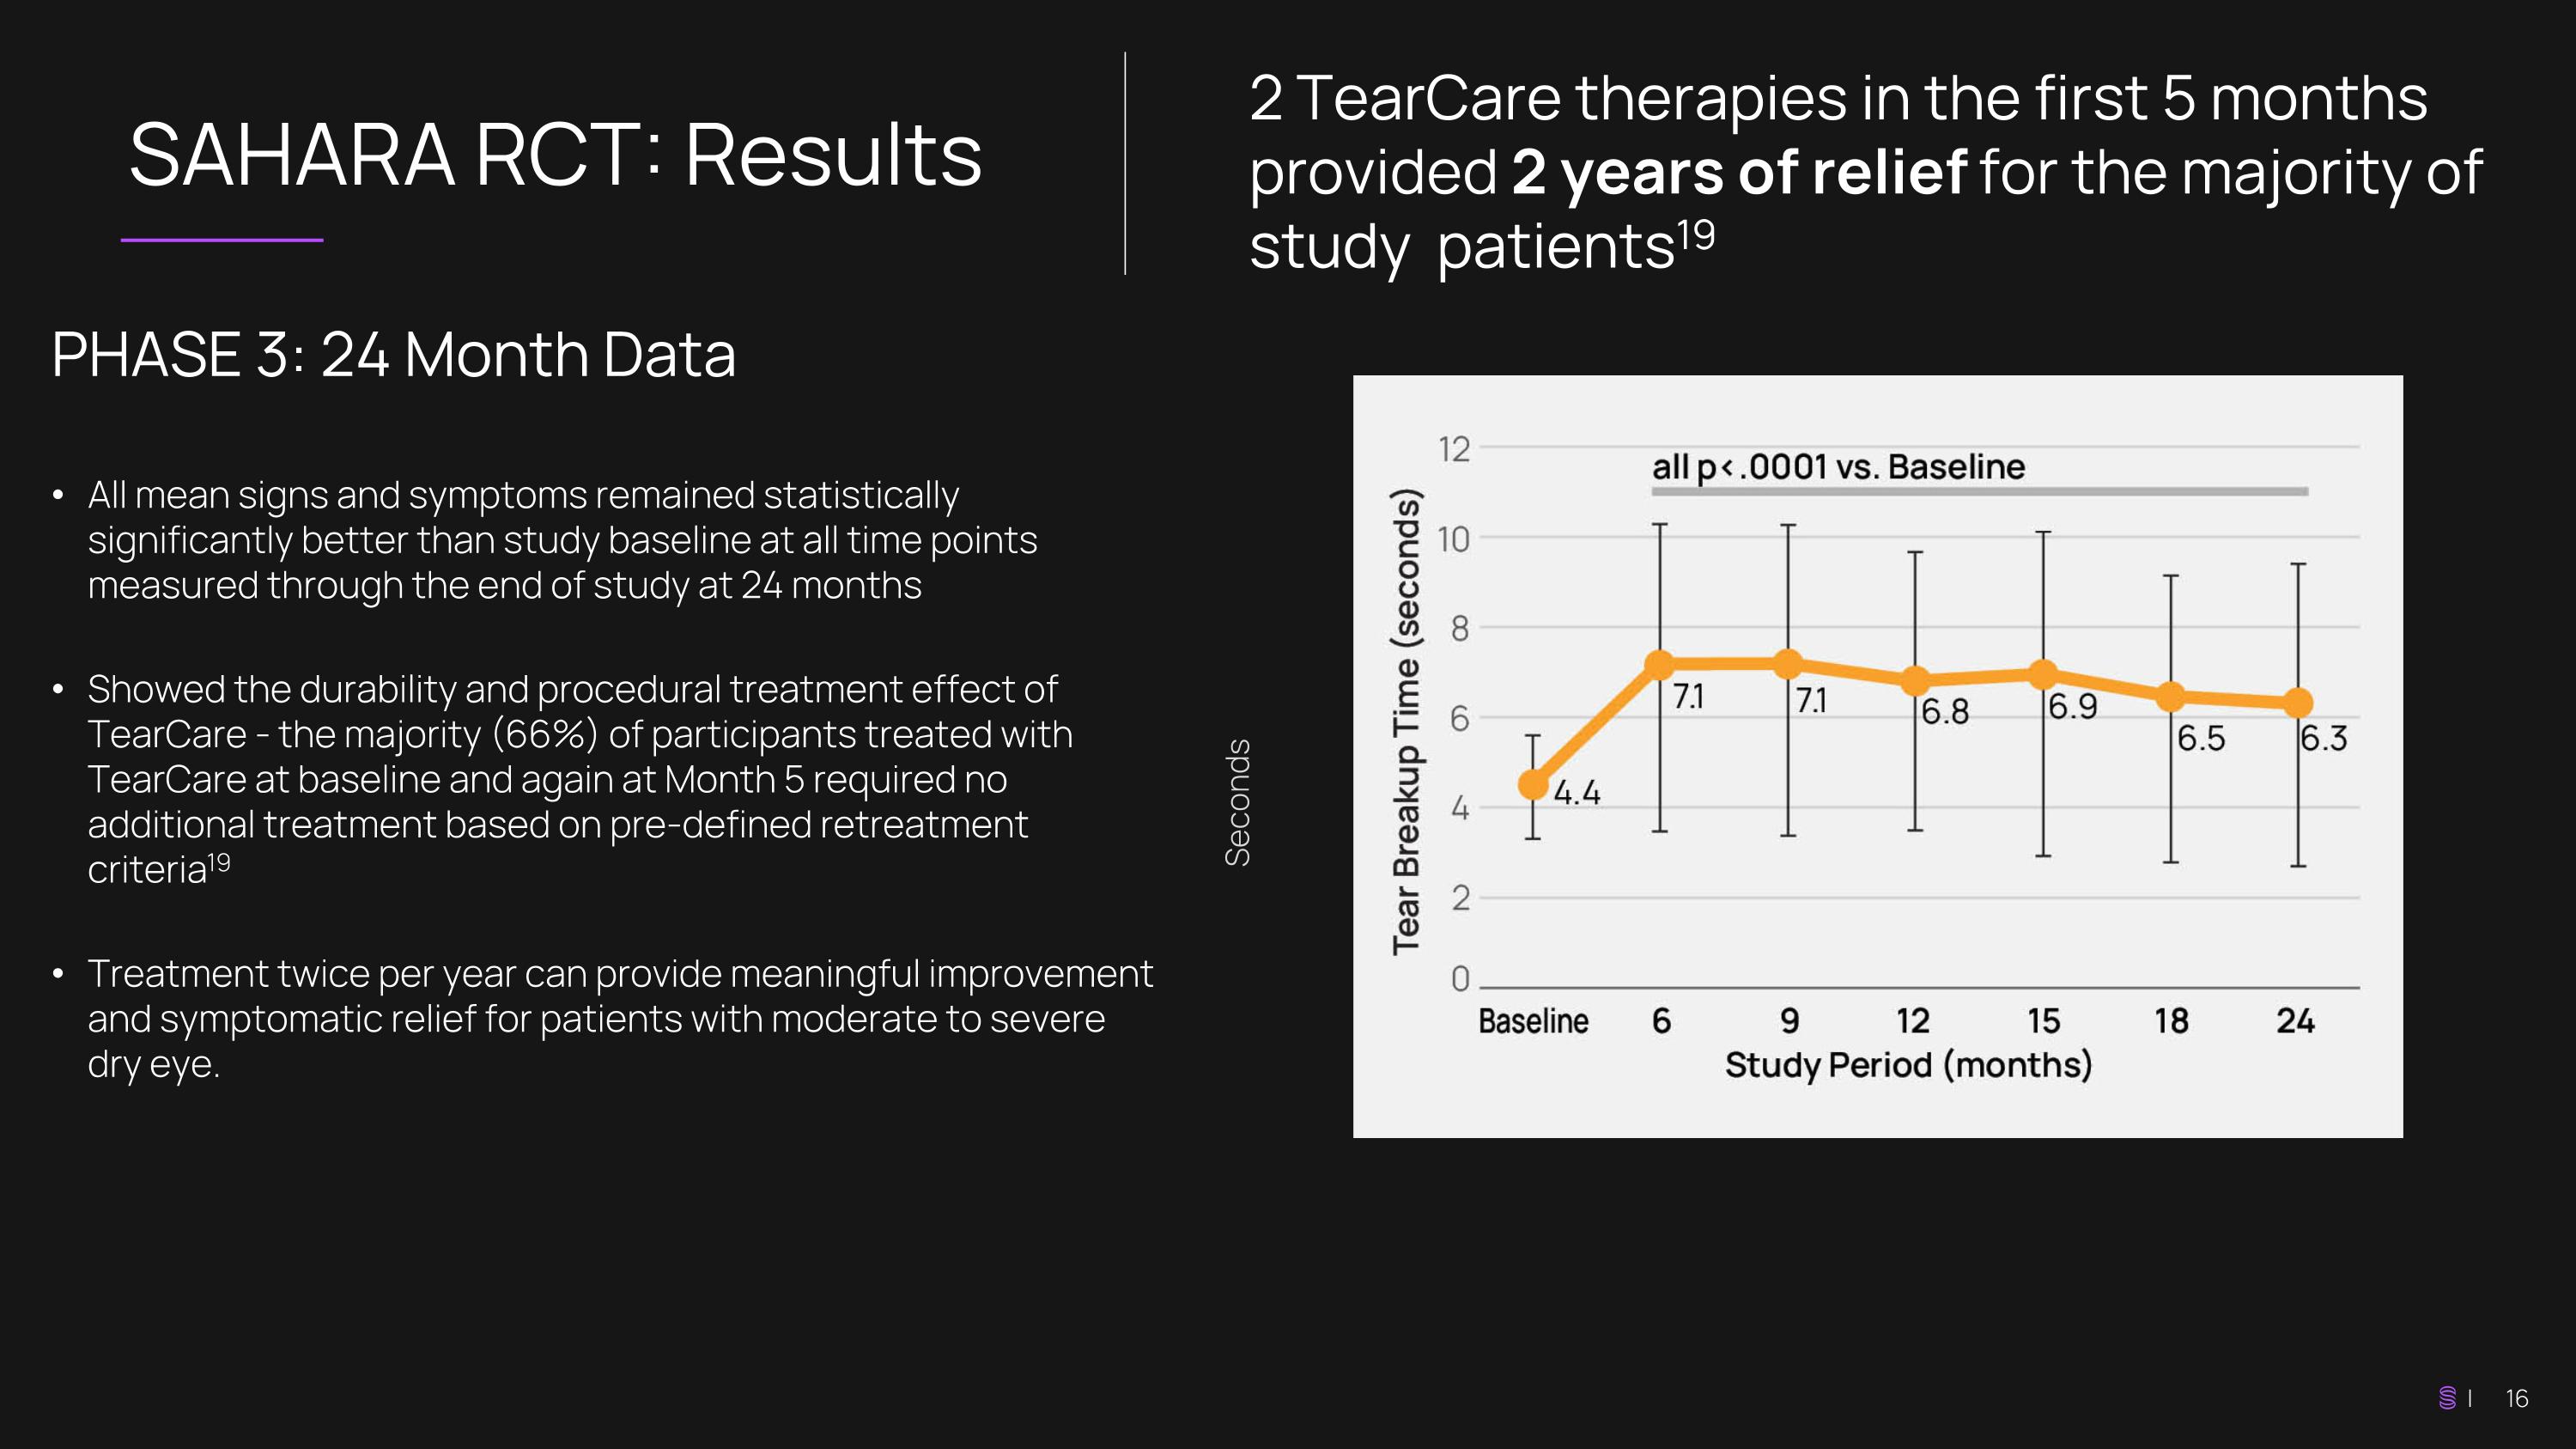
SAHARA RCT: Results 2 TearCare therapies in the first 5 months provided 2 years of relief for the majority of study patients19 PHASE 3: 24 Month Data All mean signs and symptoms remained statistically significantly better than study baseline at all time points measured through the end of study at 24 months Showed the durability and procedural treatment effect of TearCare - the majority (66%) of participants treated with TearCare at baseline and again at Month 5 required no additional treatment based on pre-defined retreatment criteria19 Treatment twice per year can provide meaningful improvement and symptomatic relief for patients with moderate to severe dry eye. Seconds

Interventional Dry Eye Scaling Commercially And Pursuing Expanded Market Access With the power of TearCare, we can: Improve the lives of U.S. MGD patients Scale commercial resources with market access wins Target ~6,500 physicians identified as most likely to adopt MGD treatment procedures20 Activate a large installed customer base, over 80,000 SmartLids sold21, built across real-world testing and data collection since 2019 Leverage synergies with our Interventional Glaucoma customer base and commercial infrastructure

Interventional Glaucoma

Glaucoma - Leading cause of irreversible blindness22 - Predominantly managed with daily eye drops (compliance often poor)23 Normal Mild Moderate Severe Large + Underserved Market U.S. patients diagnosed with Glaucoma22 >4 MILLION
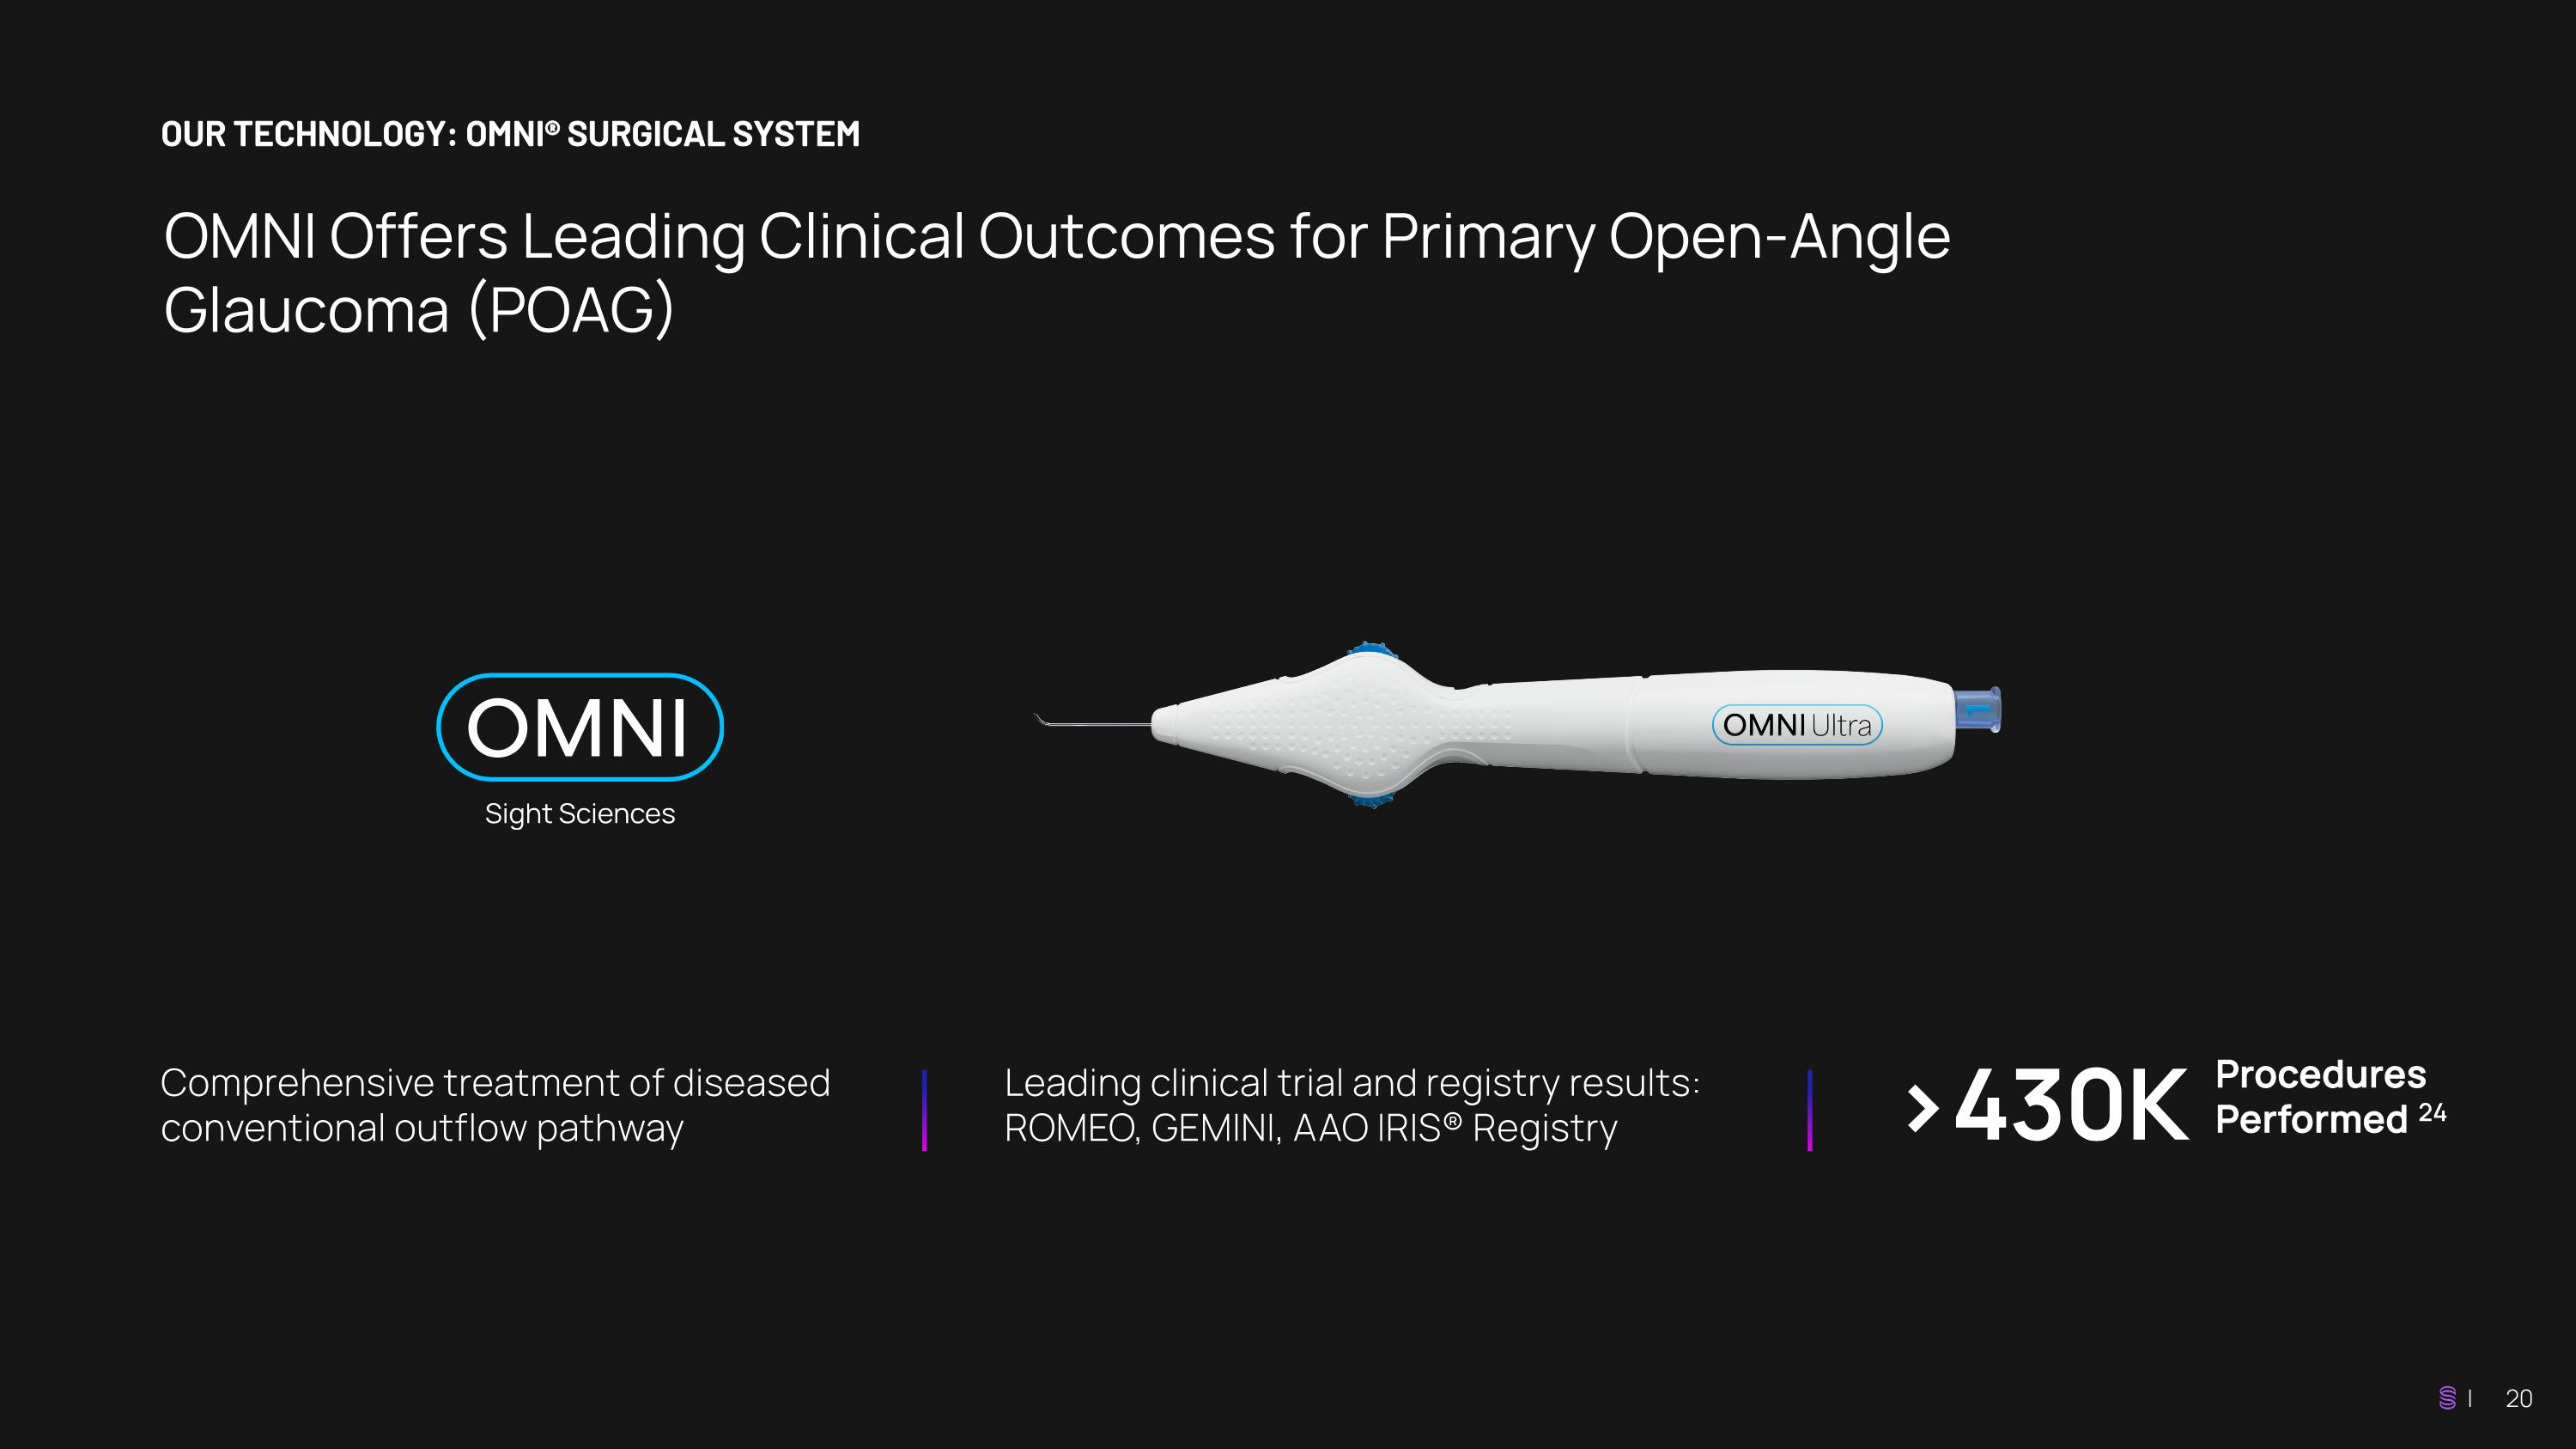
OUR TECHNOLOGY: OMNI® SURGICAL SYSTEM OMNI Offers Leading Clinical Outcomes for Primary Open-Angle Glaucoma (POAG) Comprehensive treatment of diseased conventional outflow pathway Leading clinical trial and registry results: ROMEO, GEMINI, AAO IRIS® Registry >430K Procedures Performed 24
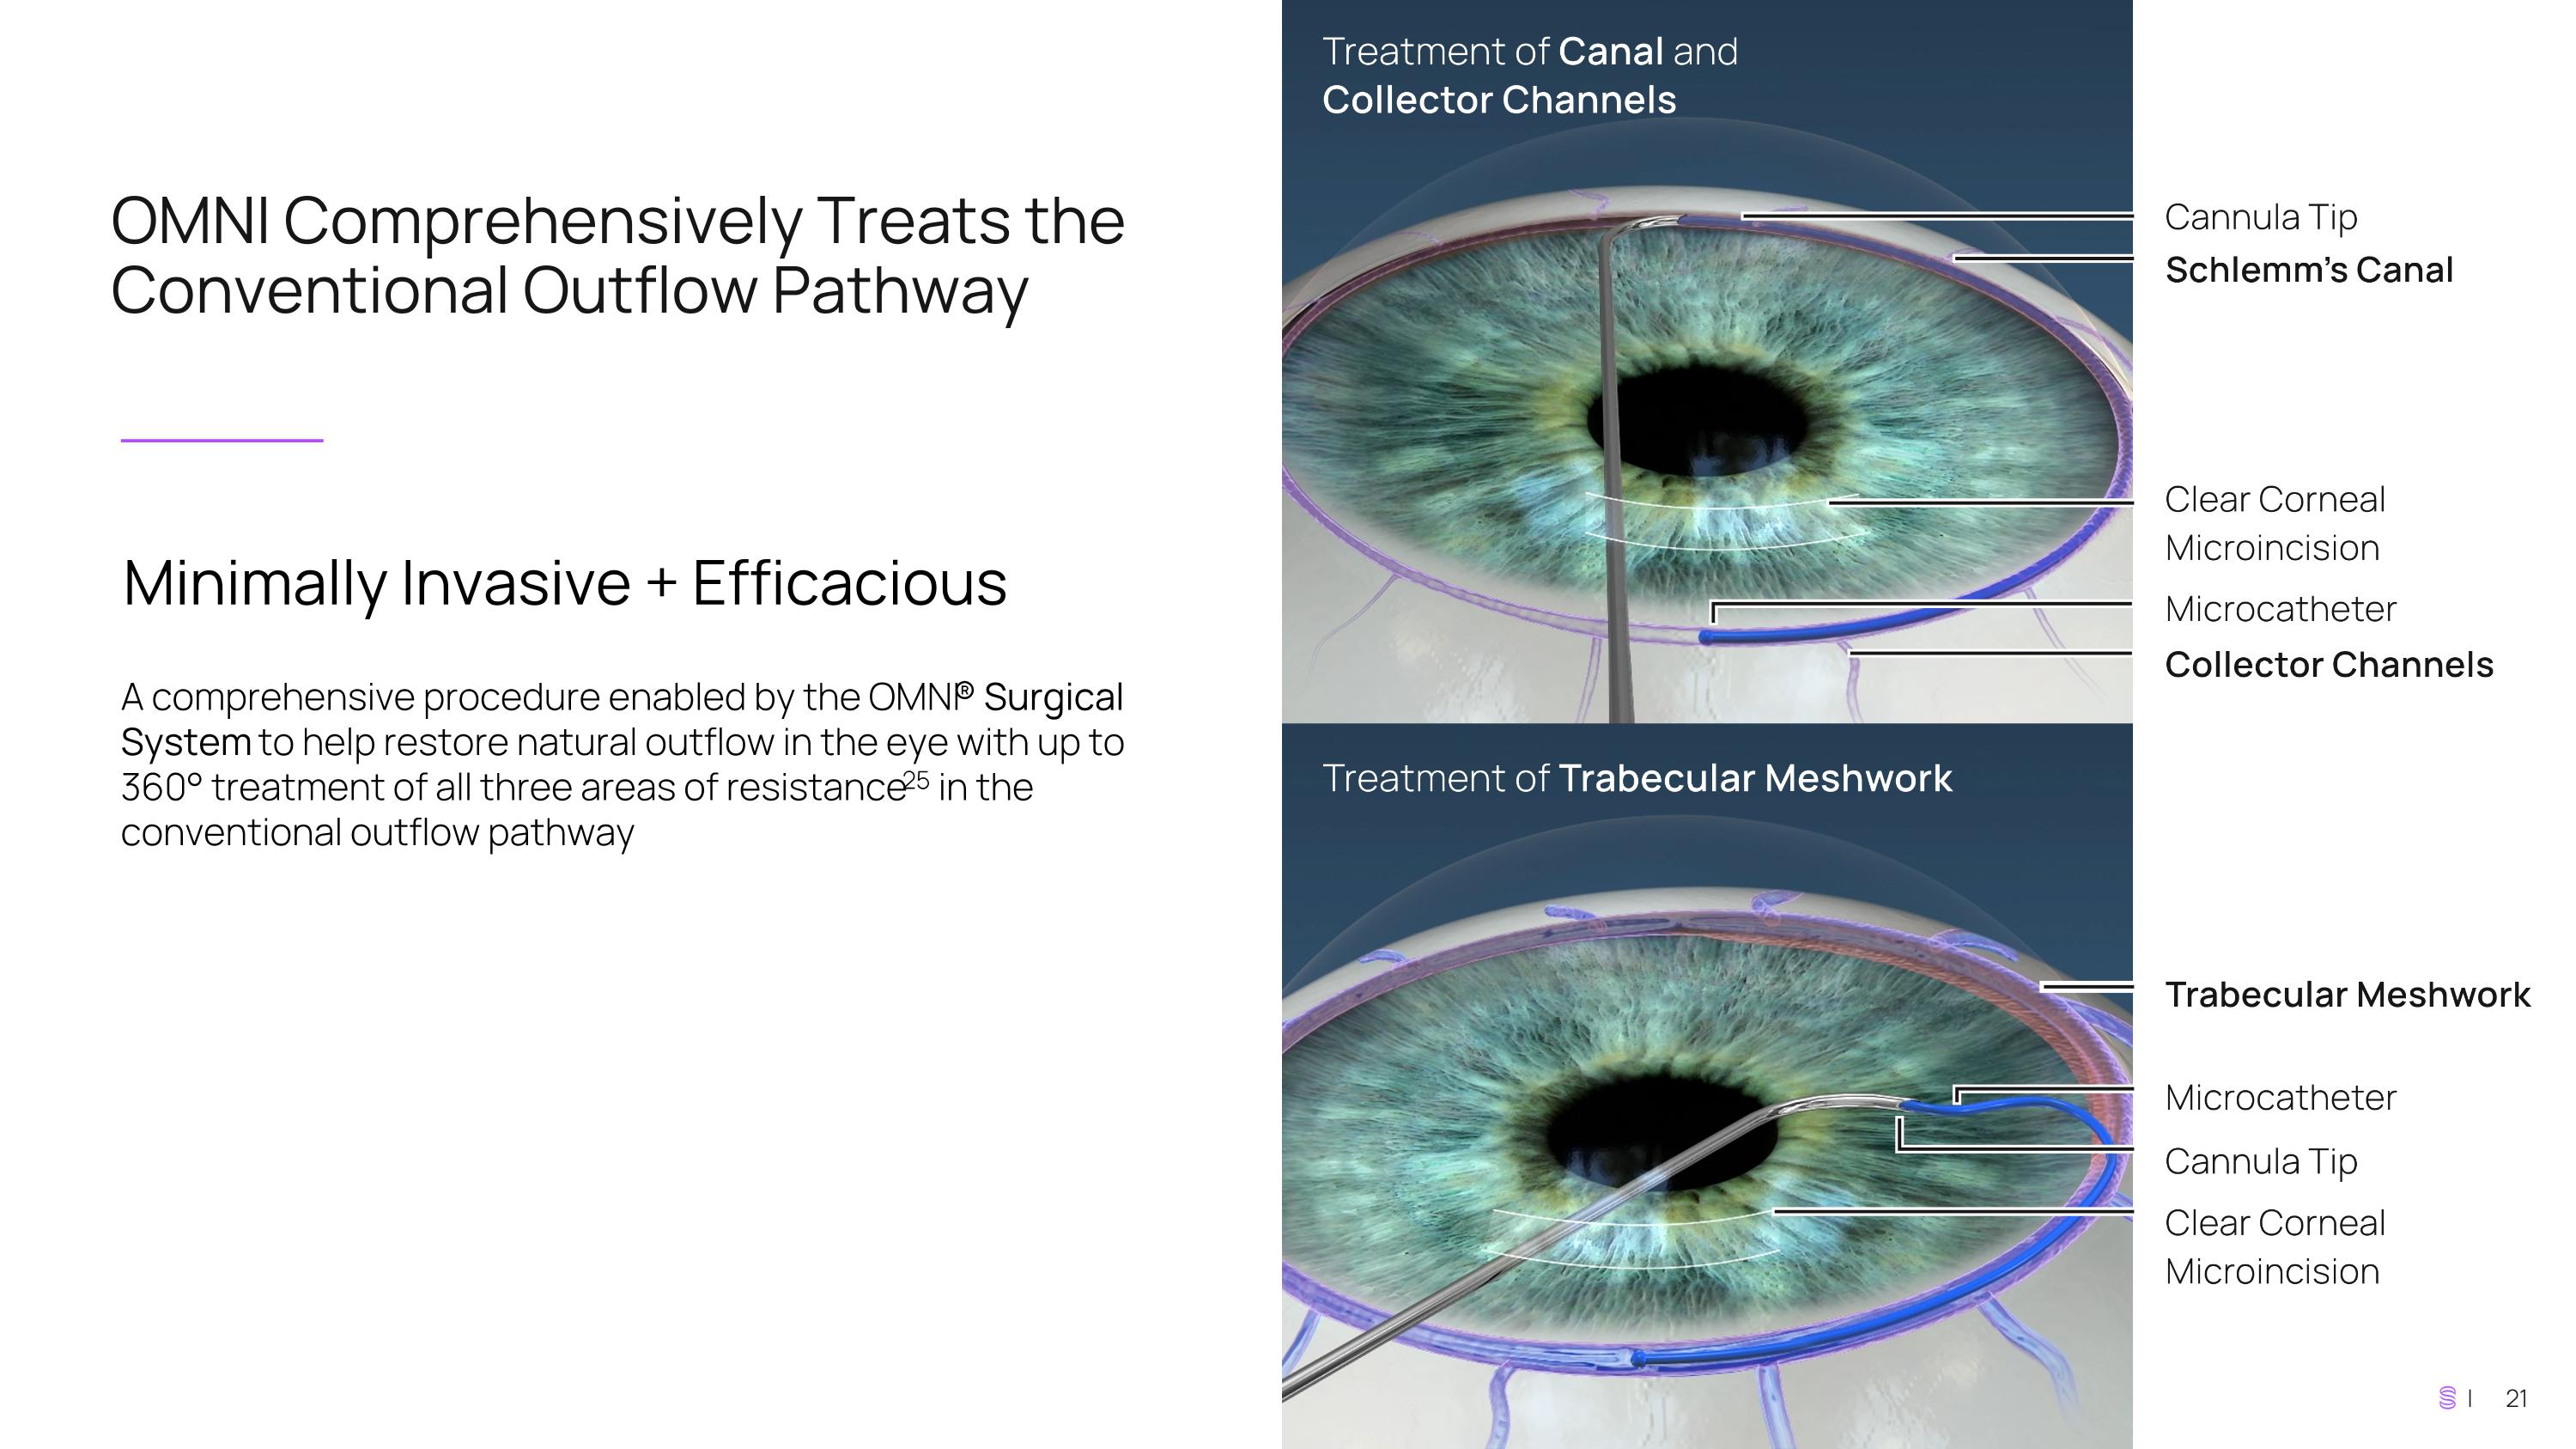
OMNI Comprehensively Treats the Conventional Outflow Pathway Minimally Invasive + Efficacious A comprehensive procedure enabled by the OMNI® Surgical System to help restore natural outflow in the eye with up to 360° treatment of all three areas of resistance25 in the conventional outflow pathway
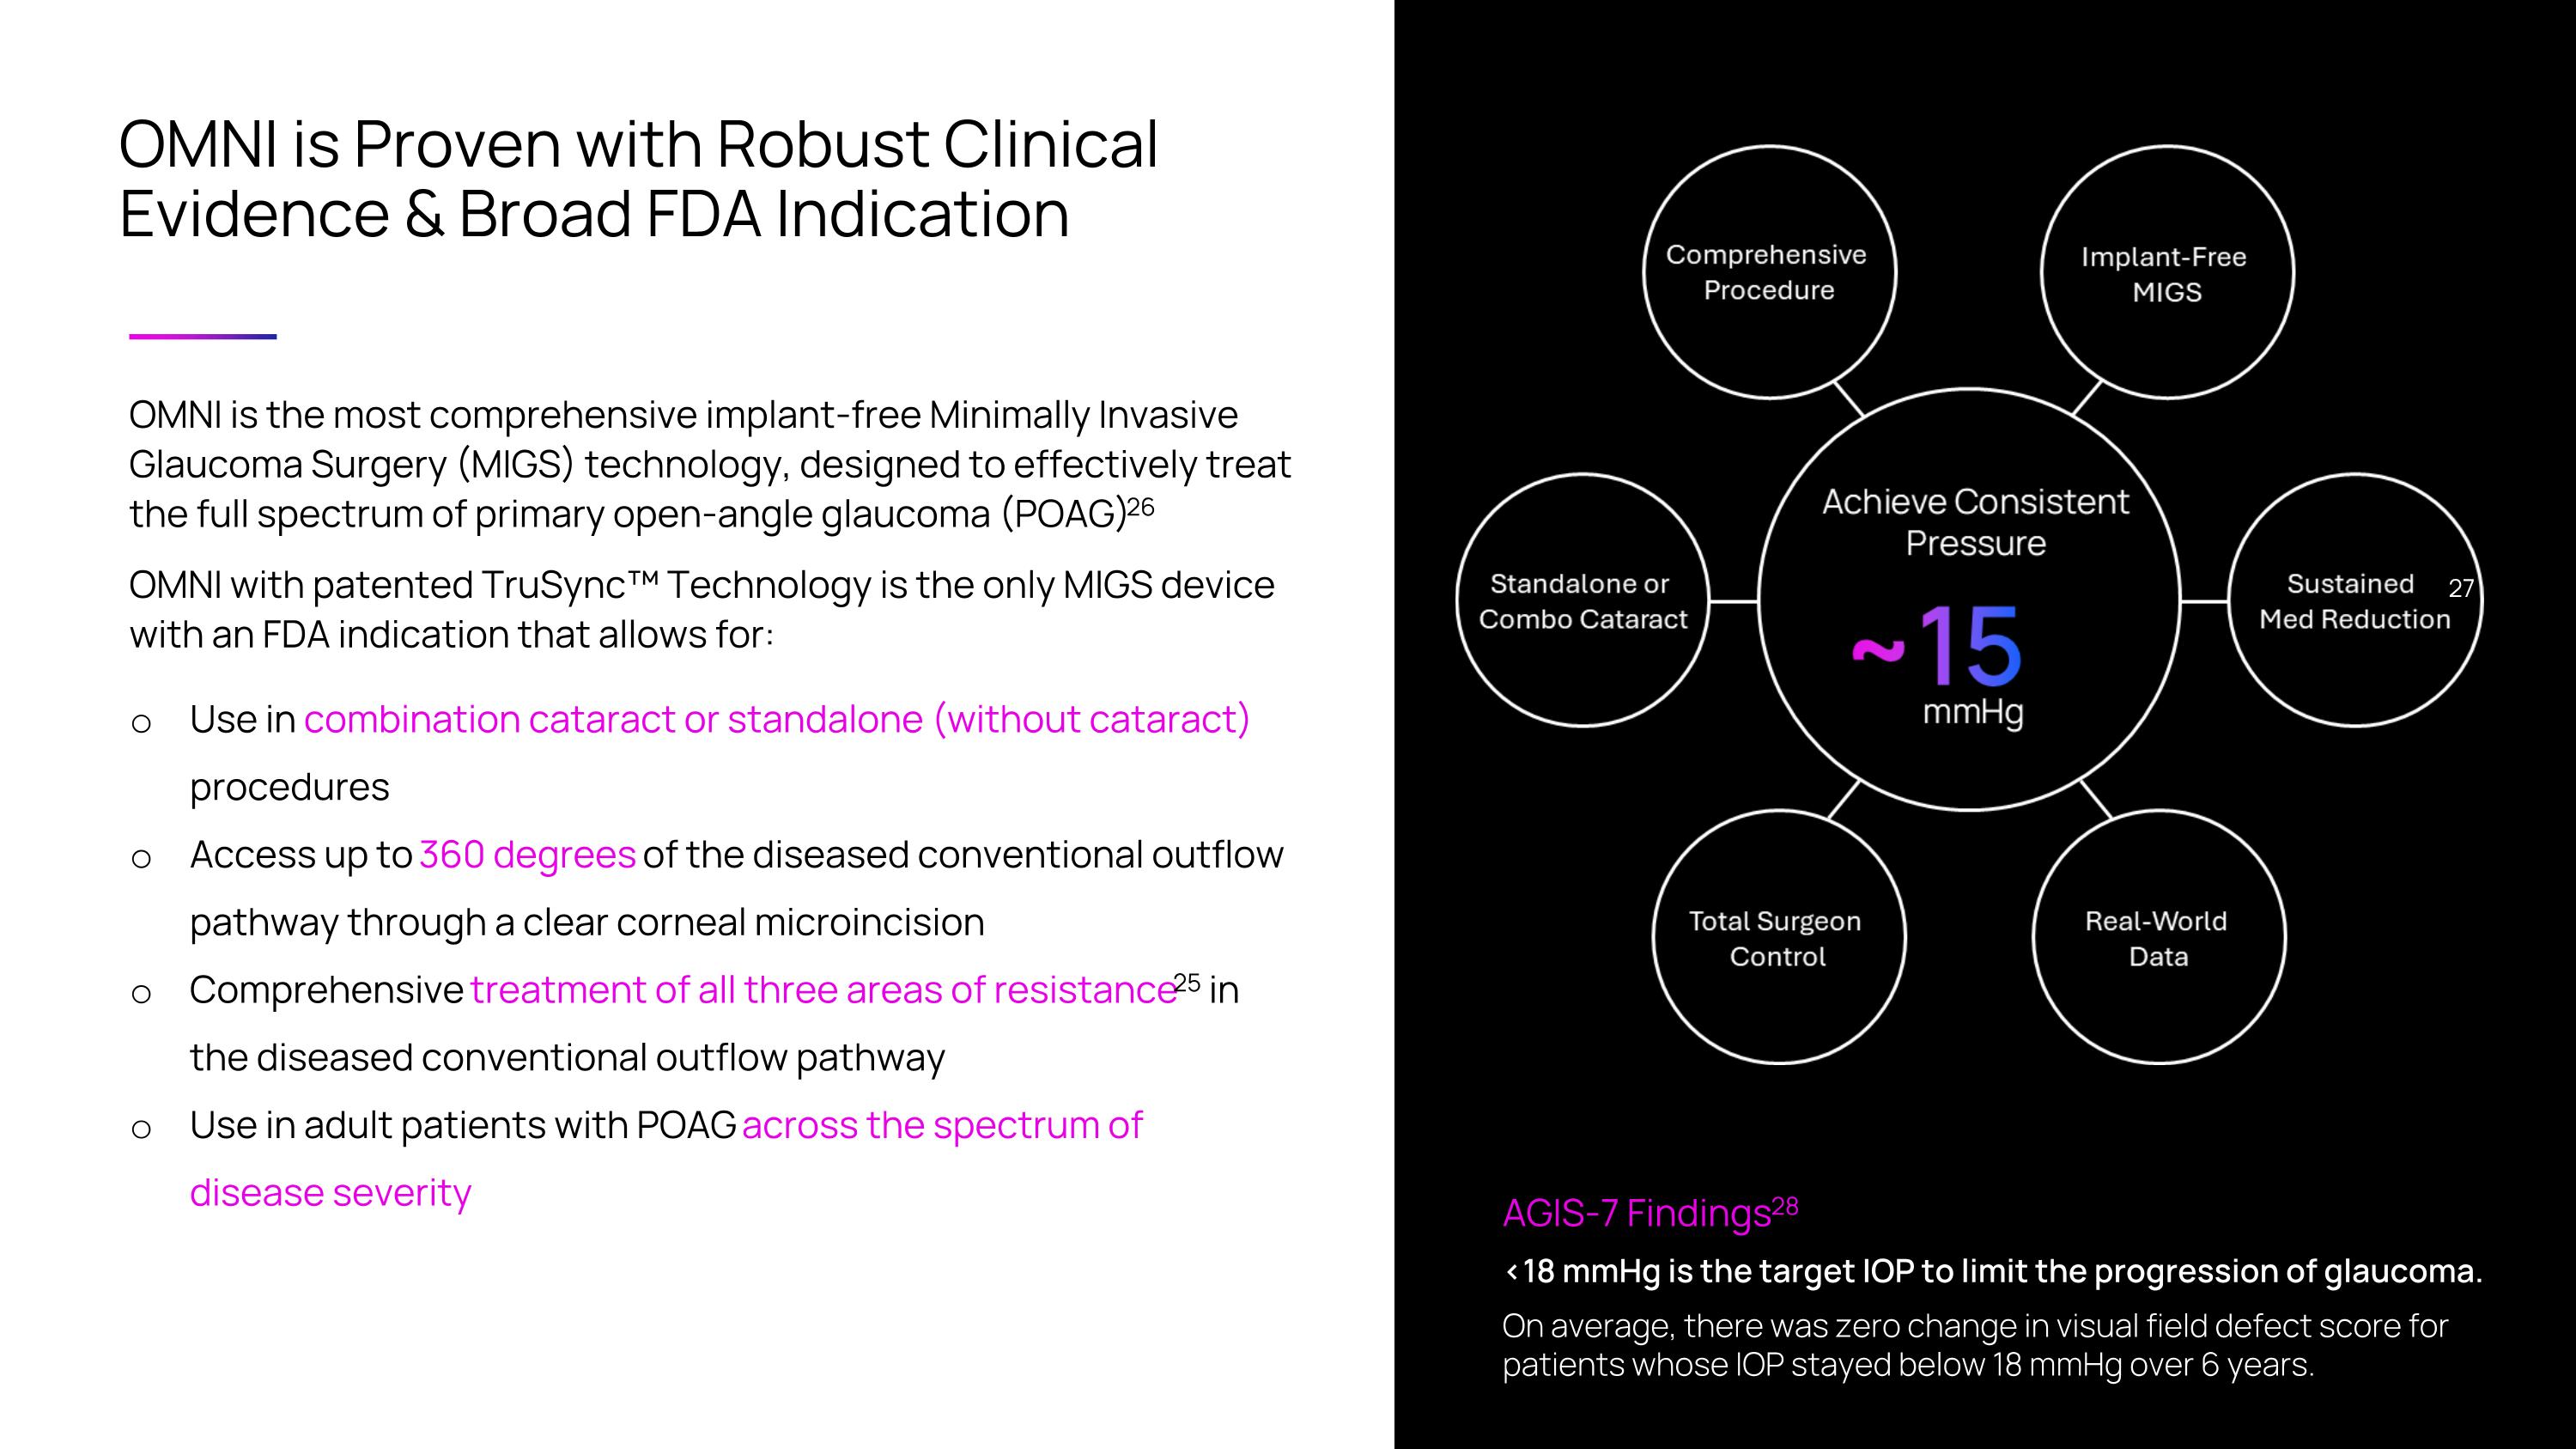
OMNI is Proven with Robust Clinical Evidence & Broad FDA Indication AGIS-7 Findings28 <18 mmHg is the target IOP to limit the progression of glaucoma. On average, there was zero change in visual field defect score for patients whose IOP stayed below 18 mmHg over 6 years. OMNI is the most comprehensive implant-free Minimally Invasive Glaucoma Surgery (MIGS) technology, designed to effectively treat the full spectrum of primary open-angle glaucoma (POAG)26 OMNI with patented TruSync™ Technology is the only MIGS device with an FDA indication that allows for: Use in combination cataract or standalone (without cataract) procedures Access up to 360 degrees of the diseased conventional outflow pathway through a clear corneal microincision Comprehensive treatment of all three areas of resistance25 in the diseased conventional outflow pathway Use in adult patients with POAG across the spectrum of disease severity 27
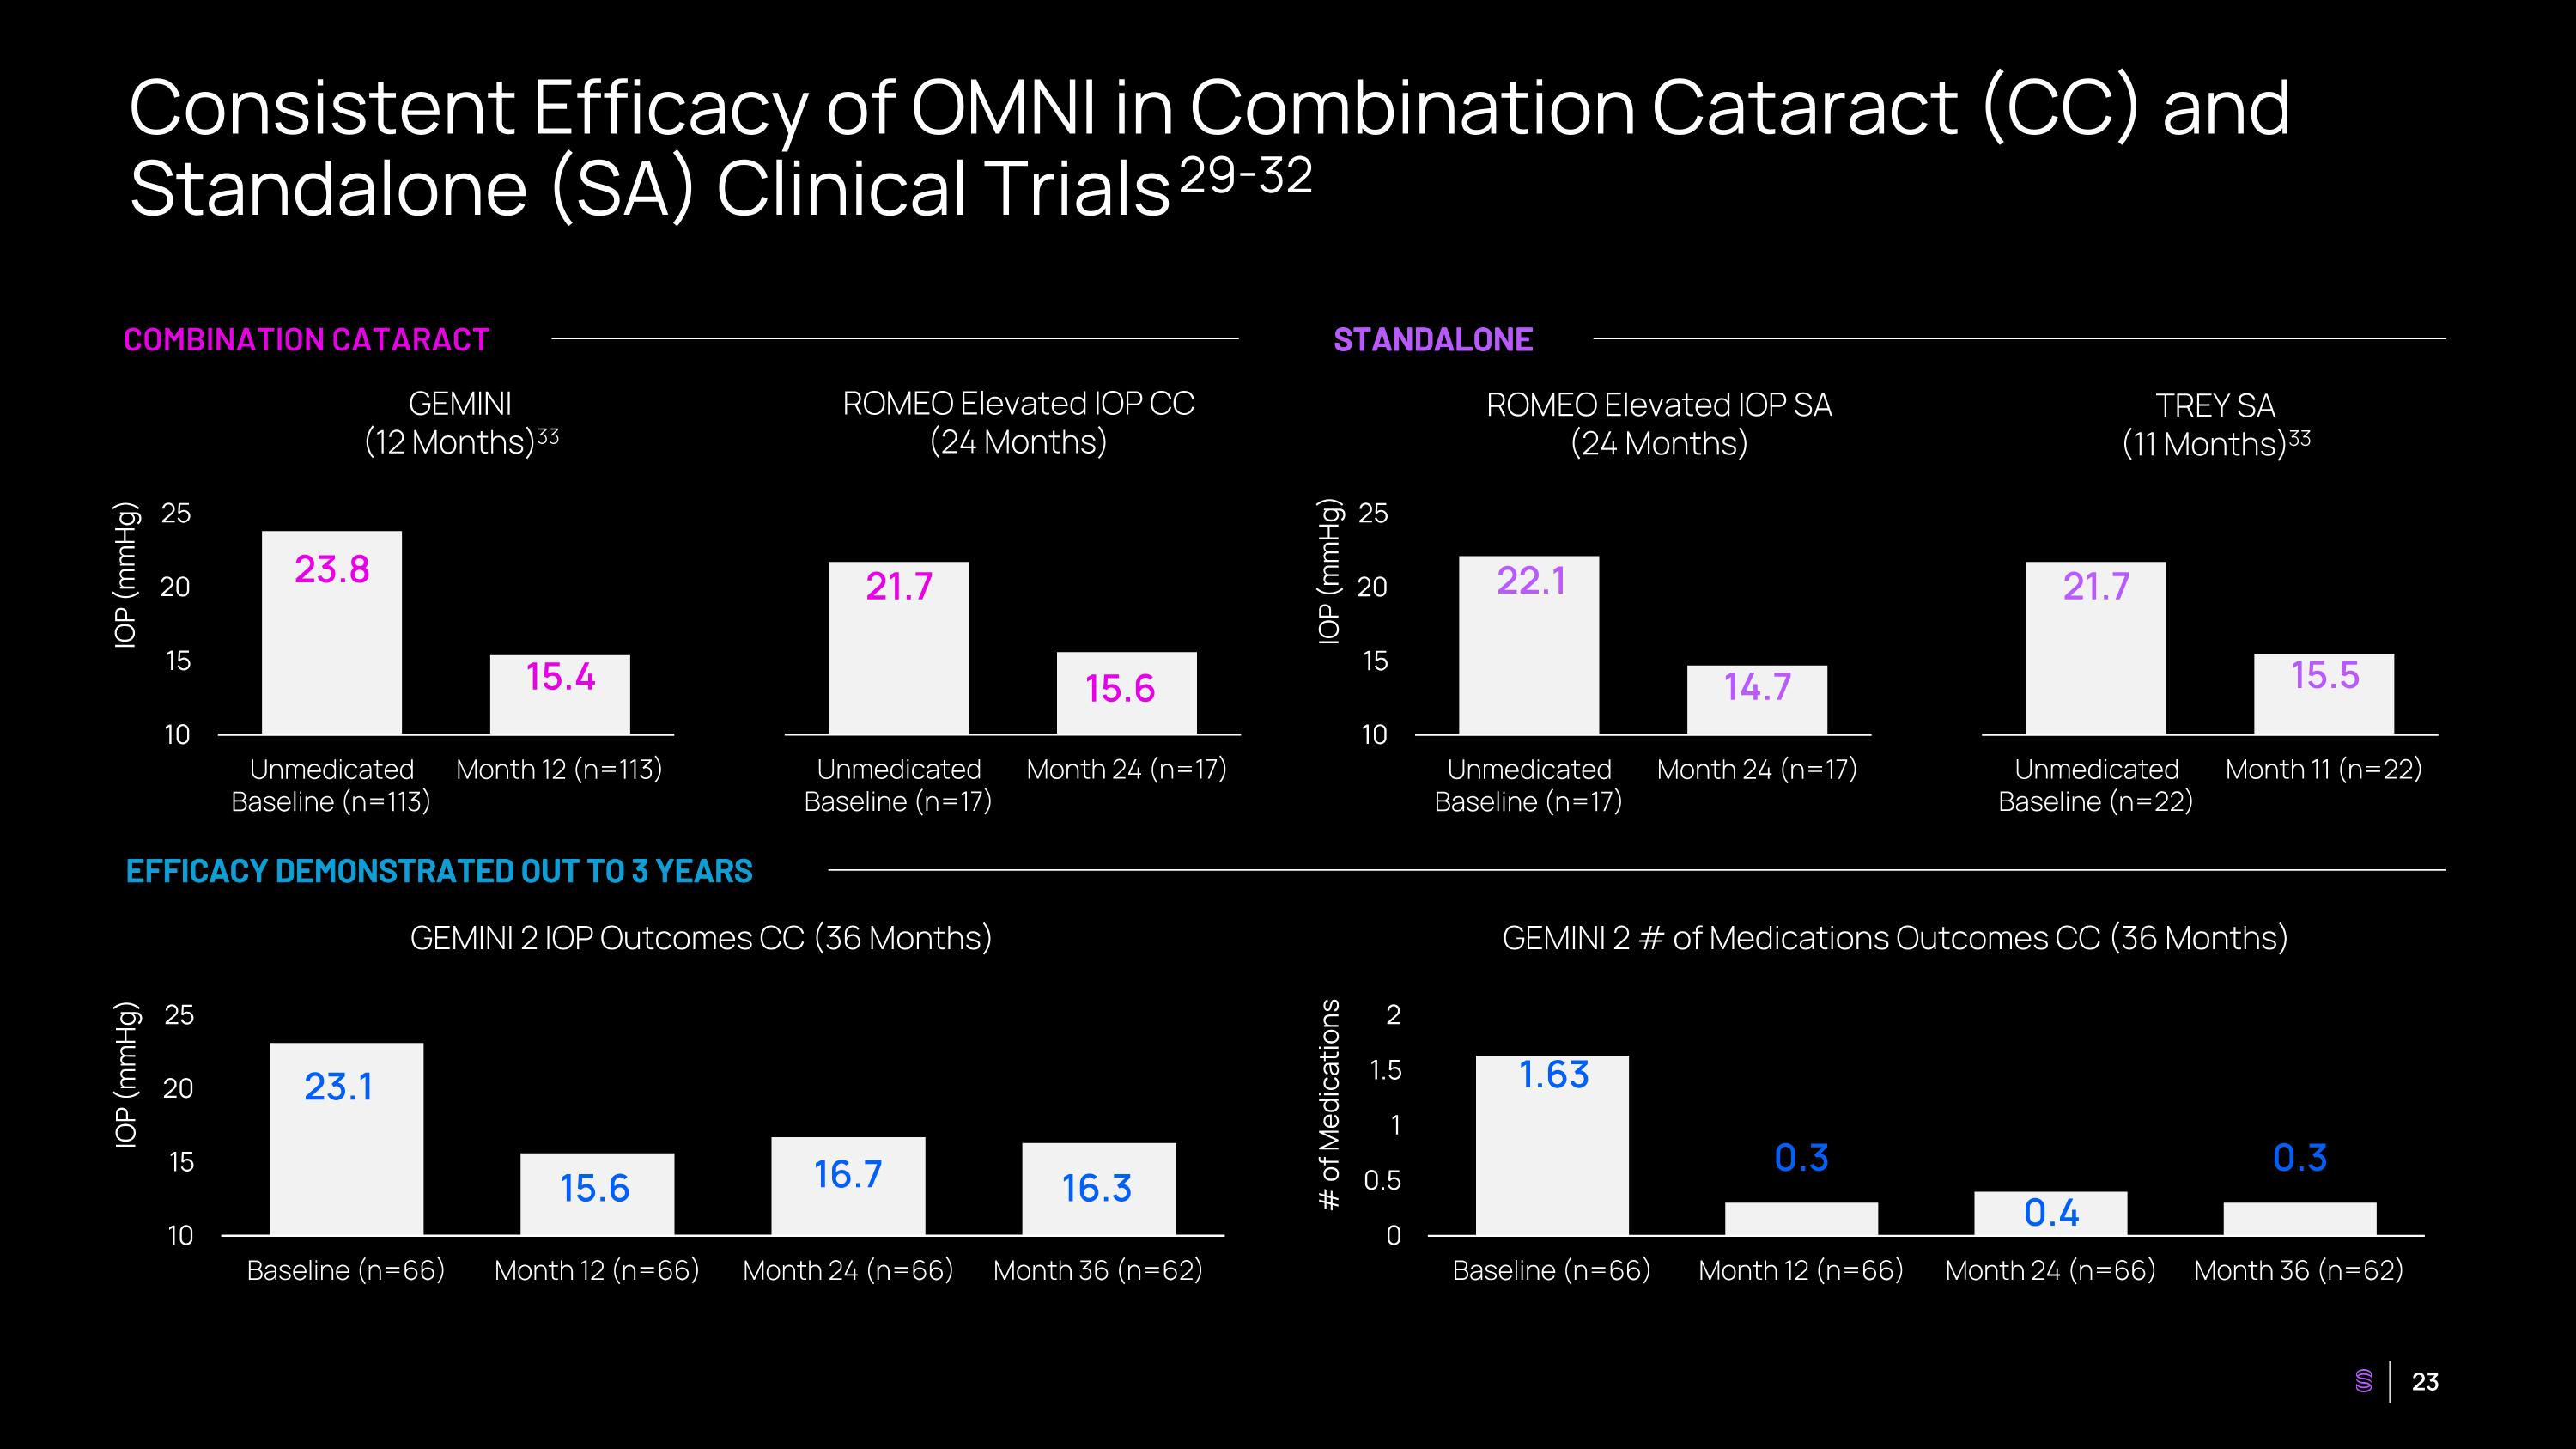
Consistent Efficacy of OMNI in Combination Cataract (CC) and Standalone (SA) Clinical Trials 29-32 COMBINATION CATARACT STANDALONE EFFICACY DEMONSTRATED OUT TO 3 YEARS GEMINI (12 Months)33 ROMEO Elevated IOP CC (24 Months) ROMEO Elevated IOP SA (24 Months) TREY SA (11 Months)33 GEMINI 2 IOP Outcomes CC (36 Months) GEMINI 2 # of Medications Outcomes CC (36 Months) IOP (mmHg) IOP (mmHg) IOP (mmHg) # of Medications
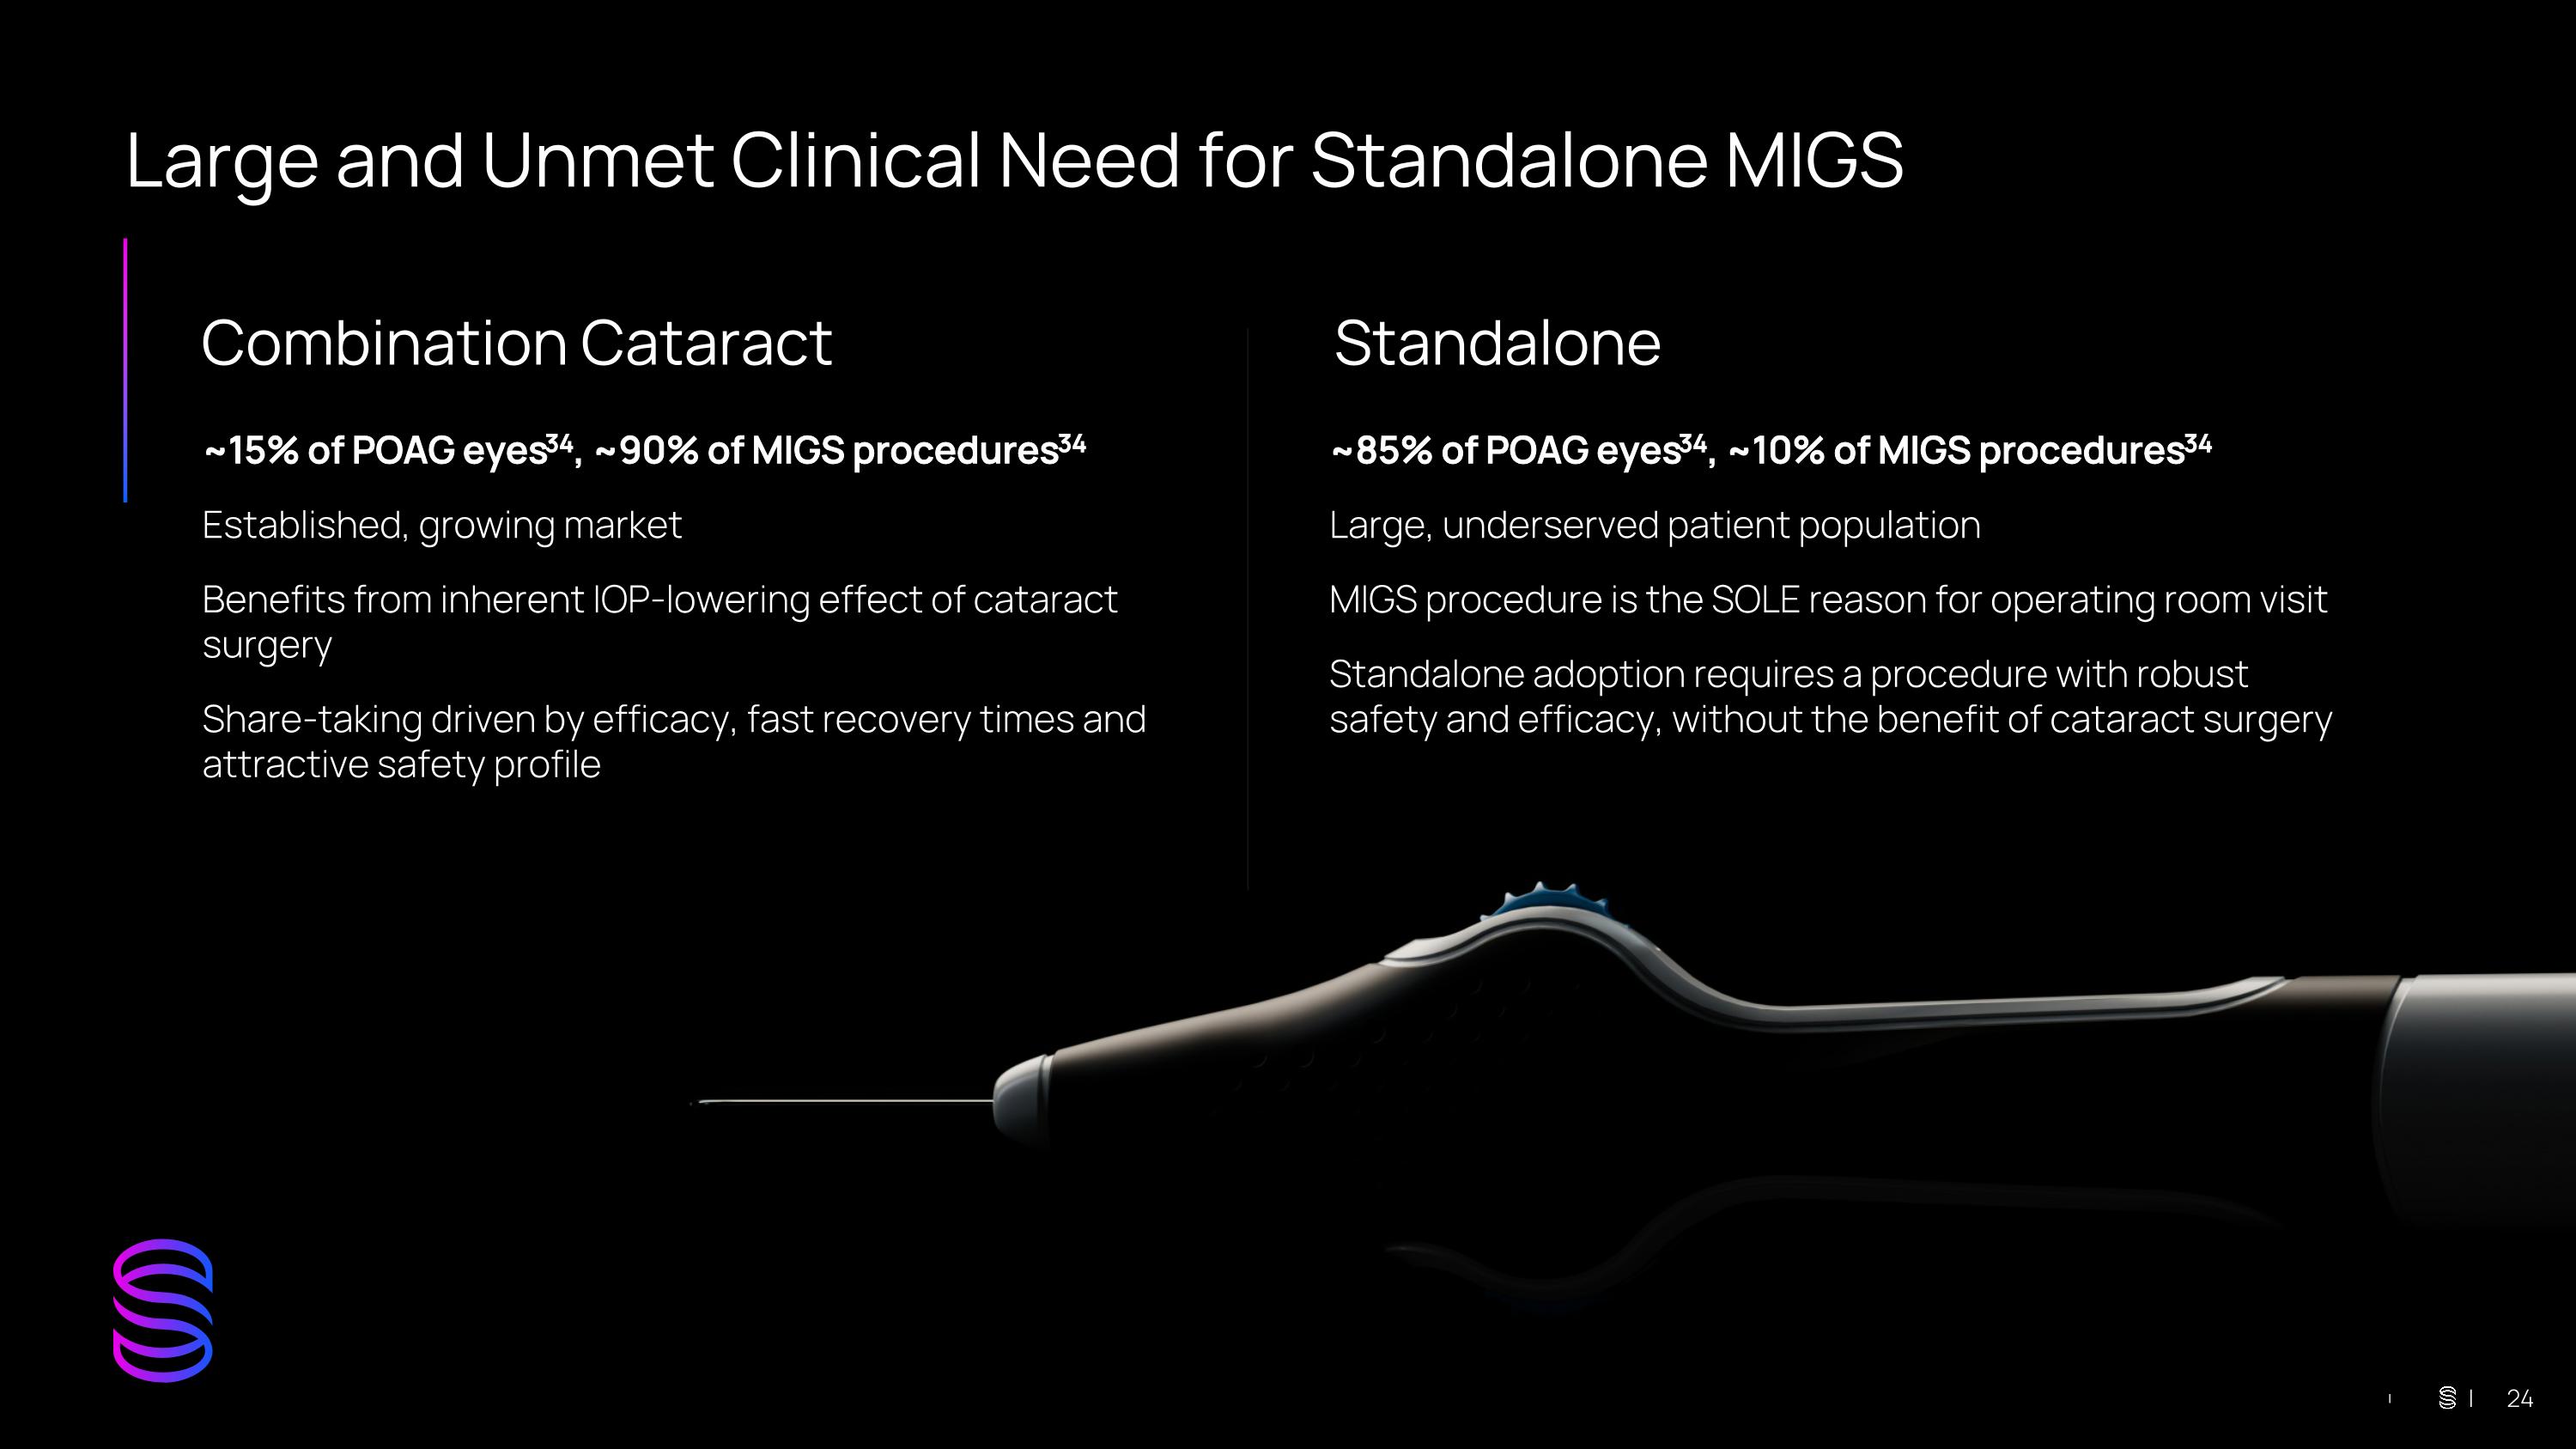
Large and Unmet Clinical Need for Standalone MIGS Combination Cataract Standalone | 24 ~15% of POAG eyes34, ~90% of MIGS procedures34 Established, growing market Benefits from inherent IOP-lowering effect of cataract surgery Share-taking driven by efficacy, fast recovery times and attractive safety profile ~85% of POAG eyes34, ~10% of MIGS procedures34 Large, underserved patient population MIGS procedure is the SOLE reason for operating room visit Standalone adoption requires a procedure with robust safety and efficacy, without the benefit of cataract surgery 34 Represents Company analysis of third-party estimates based on 2025 data.
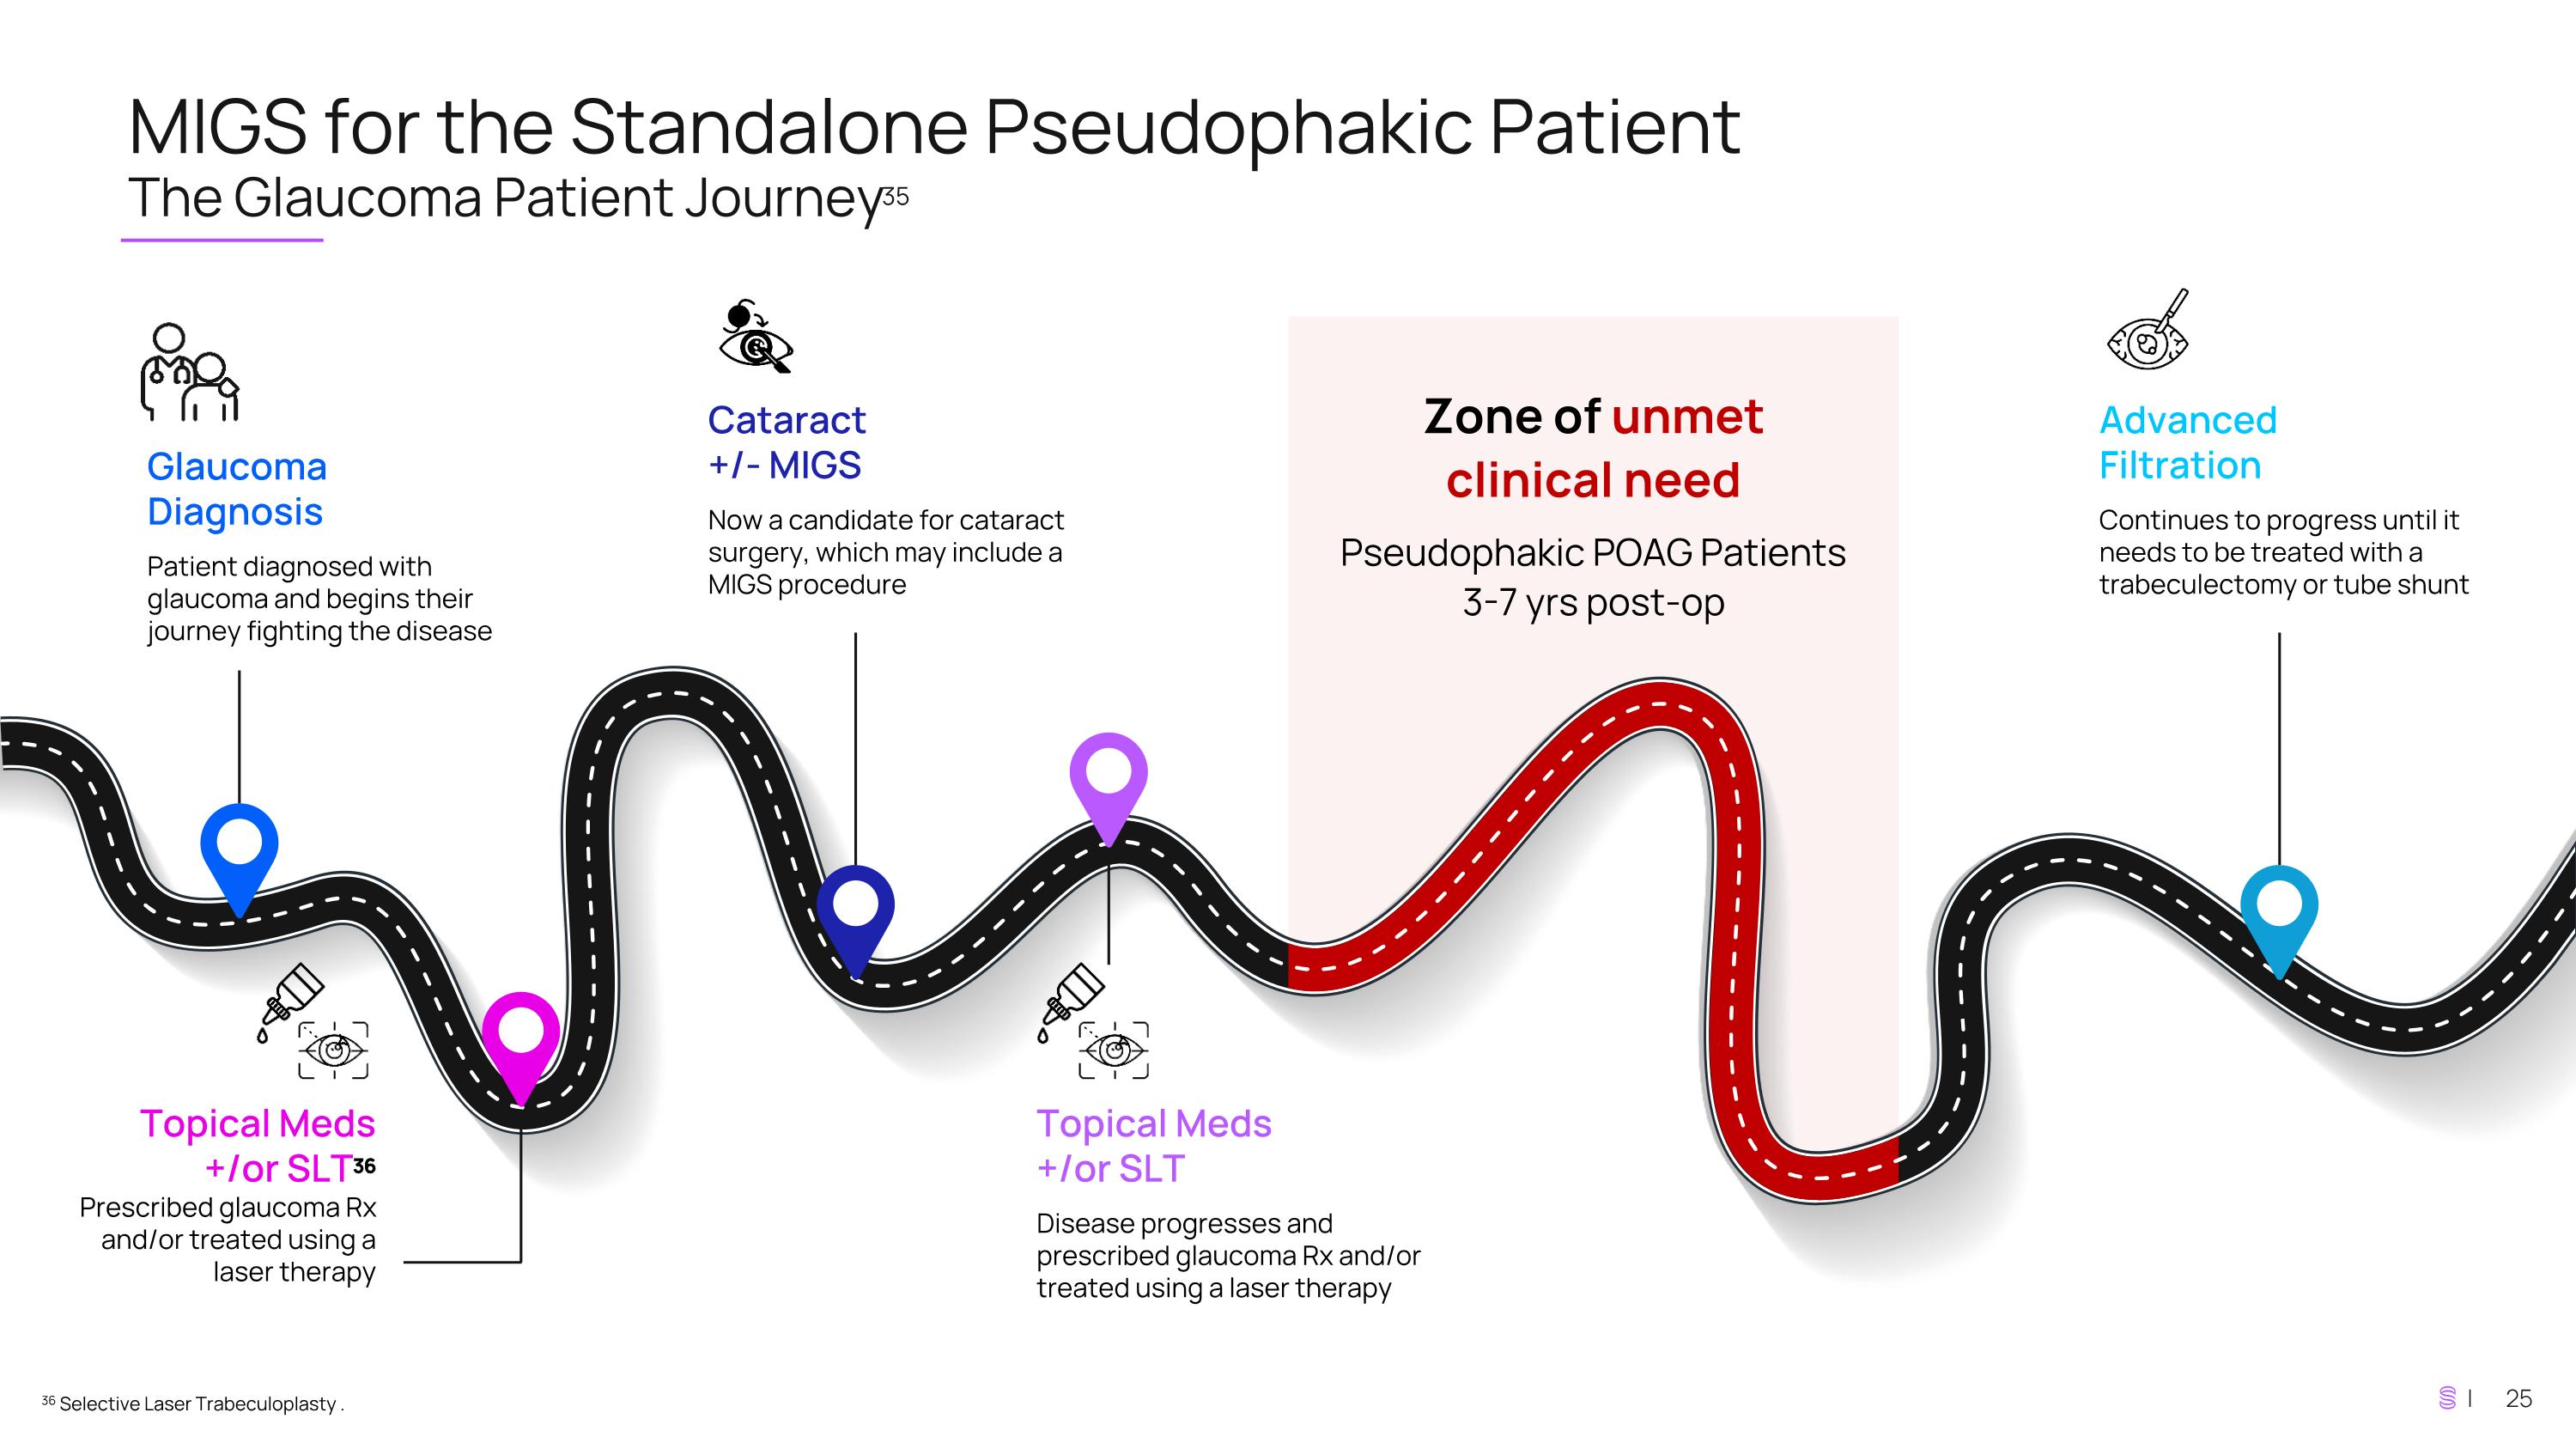
MIGS for the Standalone Pseudophakic Patient The Glaucoma Patient Journey35 36 Selective Laser Trabeculoplasty . Zone of unmet clinical need Pseudophakic POAG Patients 3-7 yrs post-op Glaucoma Diagnosis Patient diagnosed with glaucoma and begins their journey fighting the disease Topical Meds +/or SLT36 Prescribed glaucoma Rx and/or treated using a laser therapy Cataract +/- MIGS Now a candidate for cataract surgery, which may include a MIGS procedure Topical Meds +/or SLT Disease progresses and prescribed glaucoma Rx and/or treated using a laser therapy Advanced Filtration Continues to progress until it needs to be treated with a trabeculectomy or tube shunt
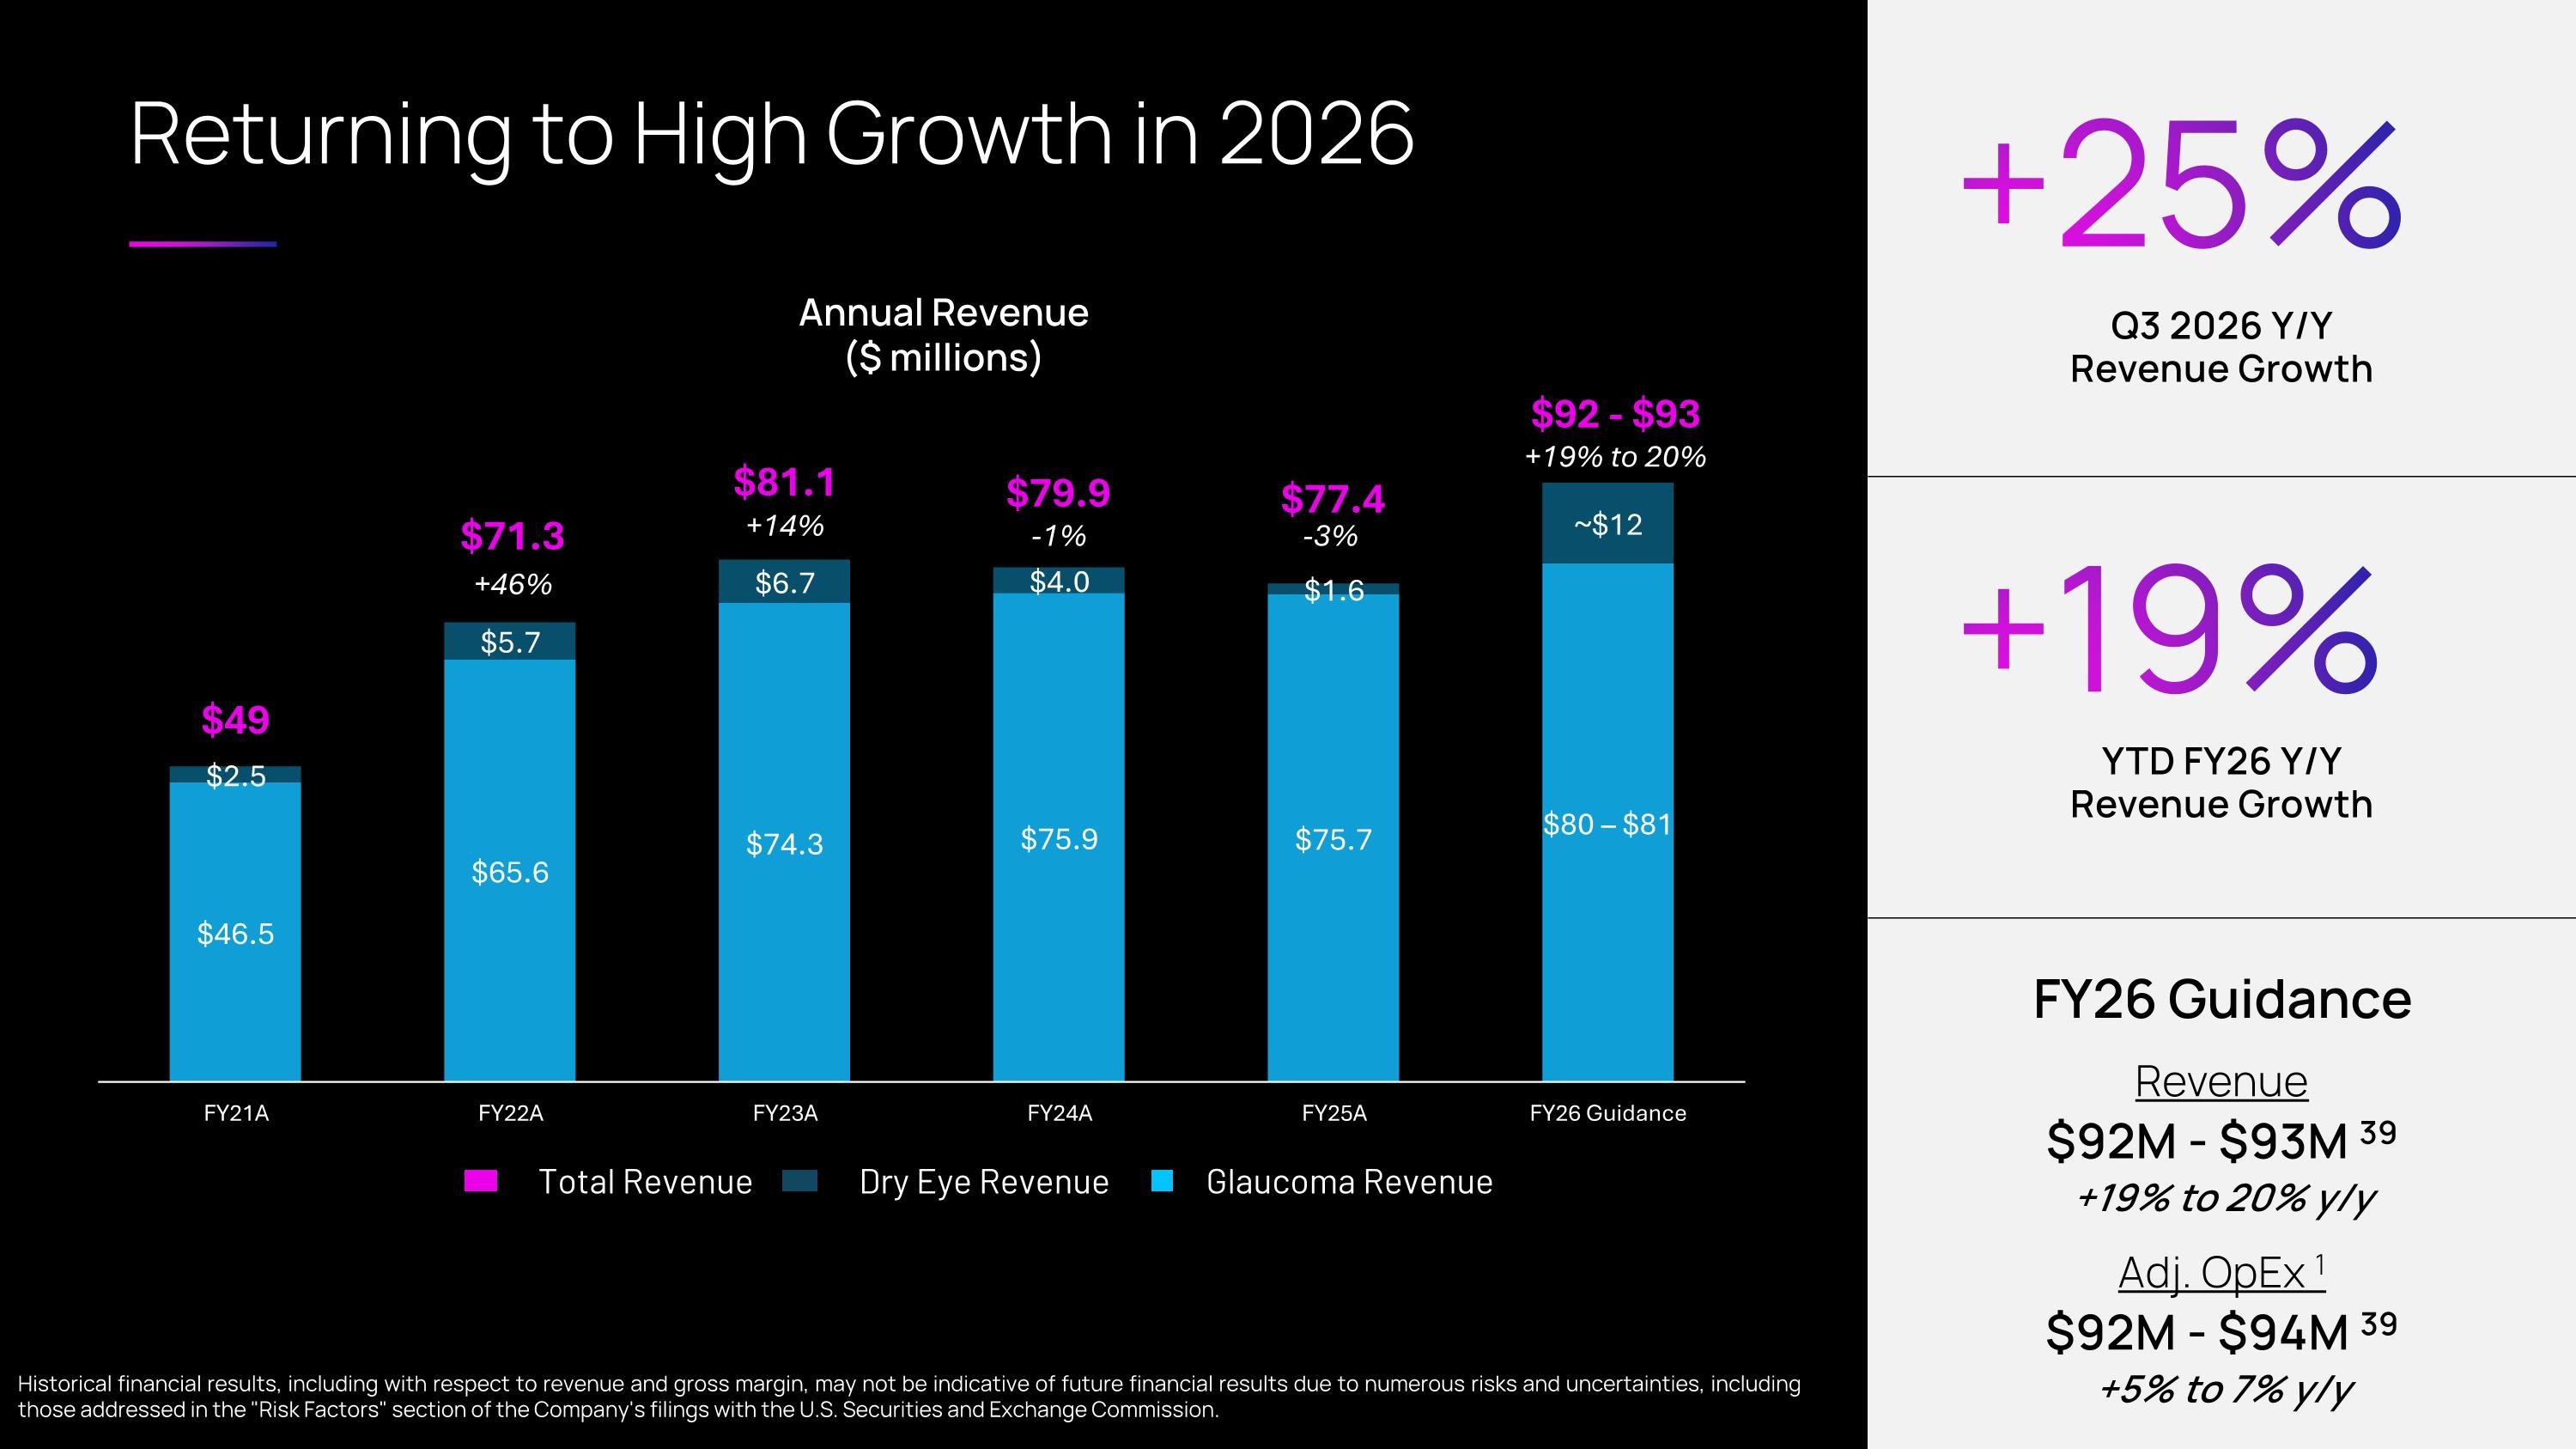
Returning to High Growth in 2026 Total Revenue Dry Eye Revenue Glaucoma Revenue +25% Q3 2026 Y/Y Revenue Growth FY26 Guidance Revenue $92M - $93M 39 +19% to 20% y/y Adj. OpEx 1 $92M - $94M 39 +5% to 7% y/y Historical financial results, including with respect to revenue and gross margin, may not be indicative of future financial results due to numerous risks and uncertainties, including those addressed in the "Risk Factors" section of the Company's filings with the U.S. Securities and Exchange Commission. $49 $71.3 $81.1 $79.9 $77.4 $92 - $93 +19% YTD FY26 Y/Y Revenue Growth +46% +14% -1% -3% +19% to 20% Annual Revenue ($ millions)


References Adjusted operating expenses is a non-GAAP financial measure, which is calculated as operating expenses less stock-based compensation expense, depreciation and amortization, restructuring costs, and other one-time costs. For a reconciliation of adjusted operating expenses to operating expenses, please refer to our earnings release issued on November 4, 2026. Market Scope 2025 Dry Eye Device Report. Lemp MA, Crews LA, Bron AJ, Foulks GN, Sullivan BD. Distribution of aqueous-deficient and evaporative dry eye in a clinic-based patient cohort: a retrospective study. Cornea. 2012;31(5):472-478. Gutgesell VJ et al. Am J Ophthalmol. 1982;94(3):383-387. Liu S, et al. Invest Ophthalmol Vis Sci. 2011;52(5):2727-2740. doi: 10.1167/iovs.10-6482. Finis D, et al Curr Eye Res. 2015;40(10):982-989. doi:10.3109/02713683.2014.971929. Gupta PK, et al. Cornea. 2022;41(4):417-426. doi:10.1097/ICO.0000000000002837. Ayres BD, Bloomenstein M, Loh J, Chester T, Saenz B, Echegoyen J, Kannarr SR, Perez V, Rodriguez T, Dickerson JE Jr. A randomized, controlled trial comparing TearCare and cyclosporine ophthalmic emulsion for the treatment of dry eye disease (SAHARA). Clin Ophthalmol 2023;17:3925-3940. Chester T, Longo R, Masseria C, Riley P, Patel C, Mody L. Budget impact analysis (BIA) of the TearCare System for the treatment of meibomian gland dysfunction (MGD)-associated dry eye disease (DED) in the United States (US). Exp Rev Ophthalmol 2025;20: 55-61, DOI: 10.1080/17469899.2024.2444930 Market Scope 2025 Dry Eye Device Report and Dry Eye Pharmaceuticals Report and internal estimates. Uchino M. Adherence to Eye Drops Usage in Dry Eye Patients and Reasons for Non-Compliance: A Web-Based Survey. J Clin Med. 2022 Jan; 11(2): 367.1. Estimate based on Dry Eye Treatment Lids shipped as of September 30, 2026. Gupta et al. Cornea 2022;41:417–426 Restasis is a trademark of Allergan™ an AbbVie company Endpoints for SAHARA include superiority over Restasis at six months in our primary objective endpoint, tear break-up time. Study through 24 months to show duration of effectiveness. Ayres BD, Bloomenstein MR, Loh J, et al. A Randomized, Controlled Trial Comparing TearCare® and Cyclosporine Ophthalmic Emulsion for the Treatment of Dry Eye Disease (SAHARA). Clin Ophthalmol. 2023;17:3925-3940. Hovanesian J, Ayres BD, Bloomenstein MR, Loh J, Chester T, Saenz B, Echegoyen J, Kannarr SR, Rodriguez TC, Dickerson JE Jr. Durability of the TearCare treatment effect in subjects with dry eye disease: Stage 3 of the Sahara randomized controlled trial. Optom Vision Sci 2025;102:495-504 doi:10.1097/OPX.0000000000002278. Endpoints for SAHARA include superiority over Restasis at six months in our primary objective endpoint, tear break-up time. TearCare treatment at Baseline and Month 5, Restasis twice a day for six months. Study through 24 months to show duration of effectiveness. Ocular Surface Disease Index is a commonly used patient-reported survey to assess dry eye severity. Ayres BD, Bloomenstein M, Loh J, Chester T, Saenz B, Echegoyen J, Kannarr SR, Rodriguez T, Dickerson JE Jr. Improved Signs and Symptoms of Dry Eye Disease for Restasis® Patients Following a Single Tearcare® Treatment: Phase 2 of the SAHARA Study. Clin Ophthalmol 2024;18:1525-1534

References 66% of TearCare® patients experienced dry eye relief for 2 years from study baseline. Study baseline refers to assessment at the start of SAHARA prior to any treatment and 5 months prior to the start of the Stage 3 durability stage. Months are measured from Study Baseline. Error bars are ± 1 standard deviation. Hovanesian J, Ayres BD, Bloomenstein MR, Loh J, Chester T, Saenz B, Echegoyen J, Kannarr SR, Rodriguez TC, Dickerson JE Jr. Durability of the TearCare treatment effect in subjects with dry eye disease: Stage 3 of the Sahara randomized controlled trial. Optom Vision Sci 2025;102:495-504 doi:10.1097/OPX.0000000000002278. Estimated as of September 30, 2025 based on review of claims data and Company analytics As of September 30, 2026 Market Scope 2025 report and JAMA Ophthalmology Prevalence of Glaucoma Among US Adults in 2022 Oct 17, 2024 . Newman-Casey PA, Robin AL, Blachley T, Farris KB, Heisler M, Resnicow K, Lee PP. The most common barriers to glaucoma medication adherence: A cross-sectional survey. Ophthalmology. 2015 Jul;122(7):1308-16. doi: 10.1016/j.ophtha.2015.03.026. Estimate based on units of OMNI (and predicates) and SION products shipped as of September 30, 2026 Trabecular meshwork, Schlemm’s Canal, and collector channels Dickerson J, et al. Ab Interno Canaloplasty and Trabeculotomy Outcomes for Mild, Moderate, and Advanced Open-Angle Glaucoma: A ROMEO Analysis. Clin Ophthalmol. 2024: 18 1433-1440. GEMINI 36-month paper (Greenwood MR, Yadgarov A, Flowers BE, Sarkisian SR, Ohene-Nyako A, Dickerson JE Jr. 36-month outcomes from the prospective GEMINI study: canaloplasty and trabeculotomy combined with cataract surgery for patients with primary open-angle glaucoma. Clin Ophthalmol 2023;17:3817-3824.) The Advanced Glaucoma Intervention Study (AGIS): 7. The relationship between control of intraocular pressure and visual field deterioration. The AGIS Investigators GEMINI (Clin Ophthalmol. 2022;16:1225–1234) TREY (Int Ophthalmol (2022)) ROMEO 2 Year (Clin Ophthalmol. 2023:17 1057–1066) GEMINI 2: Greenwood MD et al. 36-Month Outcomes from the Prospective GEMINI Study: Canaloplasty and Trabeculotomy Combined with Cataract Surgery for Patients with Primary Open-Angle Glaucoma. Clinical Ophthalmology (December 2023). Data refers to sub-populations of POAG patients. Represents Company analysis of third-party estimates based on 2025 data. ESCRS. “Glaucoma Treatment Paradigm Shift.” By Dr. Karl Mercieca. EuroTimes. Selective Laser Trabeculoplasty . Market Scope 2025 Dry Eye Device Report; Market Scope 2025 report and JAMA Ophthalmology, Prevalence of Glaucoma Among US Adults. >500K estimate based on units of OMNI (and predicates), SION and TearCare products shipped as of September 30, 2026. The Company expects full year 2026 revenue of approximately $92.0 to $93.0 million and adjusted operating expenses of $92.0 to $94.0 million, as of the Company's earnings release dated November 4, 2026