
Earnings 3Q26 November 3, 2026 1

This presentation of Recursion Pharmaceuticals, Inc. (“Recursion,” “we,” “us,” or “our”) and any accompanying discussion contain statements that are not historical facts may be considered forward-looking statements under federal securities laws and may be identified by words such as “anticipates,” “believes,” “estimates,” “expects,” “intends,” “plans,” “potential,” “predicts,” “projects,” “seeks,” “should,” “will,” or words of similar meaning and include, but are not limited to, statements regarding our collaborations with Sanofi, Roche and Genentech, including the timing of Phase 1 initiation, the advancement of targets and programs, and potential milestone payments, royalties and option exercises; the therapeutic potential, safety, and potential first-in-class status of REC-4881, REC-1245, REC-4539 and our other product candidates; the timing and outcome of FDA discussions, the initiation of a registrational study of REC-4881, and the timing of data readouts and expansion cohorts; our financial position, cash runway, cash operating expense guidance, use of proceeds from our October 2026 financing, and capital allocation priorities; our ability to use AI and the Recursion OS to accelerate and improve drug discovery and clinical development; the potential size of the market opportunity for our product candidates, including in FAP and endometrial cancer; the expected impact of changes to our Board leadership; the initiation, timing, progress, results, and cost of our research and development programs; and many others. Other important factors and information are contained in Recursion’s most recent Quarterly Report on Form 10-Q, Annual Report on Form 10-K, and the Company’s other filings with the U.S. Securities and Exchange Commission (the “SEC”), which can be accessed at https://ir.recursion.com, or www.sec.gov. All forward-looking statements are qualified by these cautionary statements and apply only as of the date they are made. Recursion does not undertake any obligation to update any forward-looking statement, whether as a result of new information, future events or otherwise. Certain information contained in this presentation relates to or is based on studies, publications, surveys and other data obtained from third-party sources and the company’s own internal estimates and research. While the company believes these third-party sources to be reliable as of the date of this presentation, it has not independently verified, and makes no representation as to the adequacy, fairness, accuracy or completeness of, any information obtained from third- party sources. In addition, all of the market data included in this presentation involves a number of assumptions and limitations, and there can be no guarantee as to the accuracy or reliability of such assumptions. Finally, while the company believes its own internal research is reliable, such research has not been verified by any independent source. Information contained in, or that can be accessed through our website is not a part of and is not incorporated into this presentation. Cross-trial or cross-candidate information about other investigational assets and drug candidates are not based on head-to-head studies and are presented for informational purposes; data presented are based on publicly available information for other clinical trials and other drug candidates. ® 2026 Recursion Pharmaceuticals, Inc. Recursion and its related logo are registered trademarks of Recursion Pharmaceuticals, Inc. All other trademarks are property of their respective owners. Important Information 2
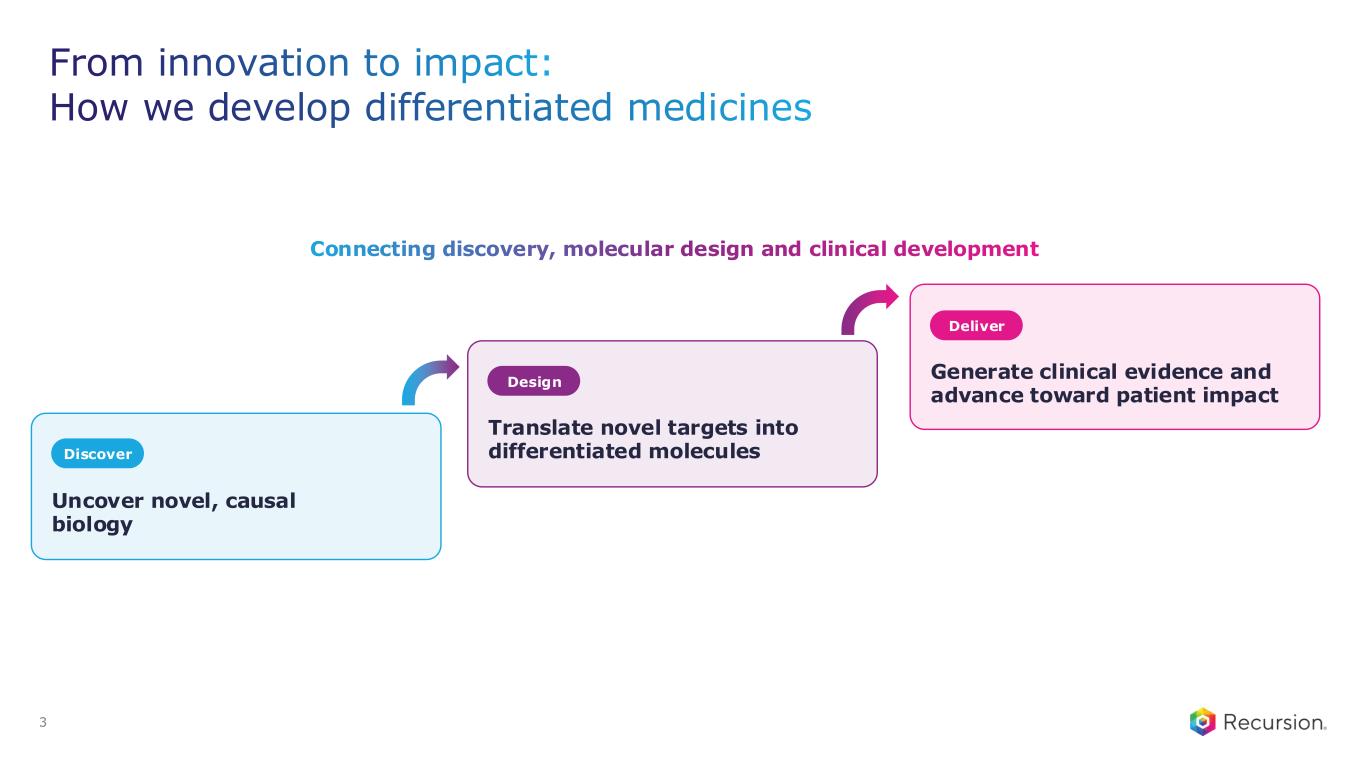
3 Uncover novel, causal biology Discover Design Deliver Translate novel targets into differentiated molecules Generate clinical evidence and advance toward patient impact Connecting discovery, molecular design and clinical development From innovation to impact: How we develop differentiated medicines
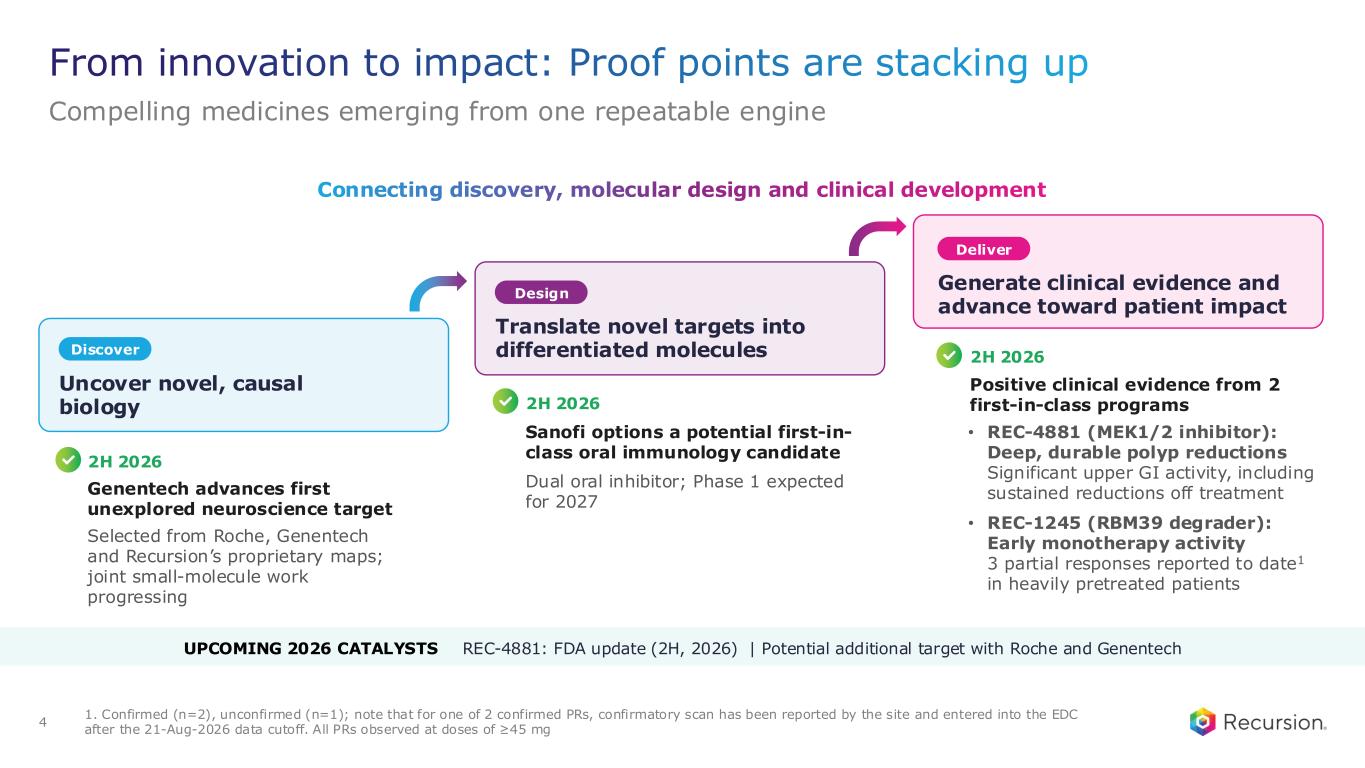
From innovation to impact: Proof points are stacking up Compelling medicines emerging from one repeatable engine 4 1. Confirmed (n=2), unconfirmed (n=1); note that for one of 2 confirmed PRs, confirmatory scan has been reported by the site and entered into the EDC after the 21-Aug-2026 data cutoff. All PRs observed at doses of ≥45 mg UPCOMING 2026 CATALYSTS REC-4881: FDA update (2H, 2026) | Potential additional target with Roche and Genentech Uncover novel, causal biology Discover Design Deliver Translate novel targets into differentiated molecules Generate clinical evidence and advance toward patient impact Selected from Roche, Genentech and Recursion’s proprietary maps; joint small-molecule work progressing Dual oral inhibitor; Phase 1 expected for 2027 2H 2026 Genentech advances first unexplored neuroscience target 2H 2026 Sanofi options a potential first-in- class oral immunology candidate Positive clinical evidence from 2 first-in-class programs • REC-4881 (MEK1/2 inhibitor): Deep, durable polyp reductions Significant upper GI activity, including sustained reductions off treatment • REC-1245 (RBM39 degrader): Early monotherapy activity 3 partial responses reported to date1 in heavily pretreated patients 2H 2026 Connecting discovery, molecular design and clinical development
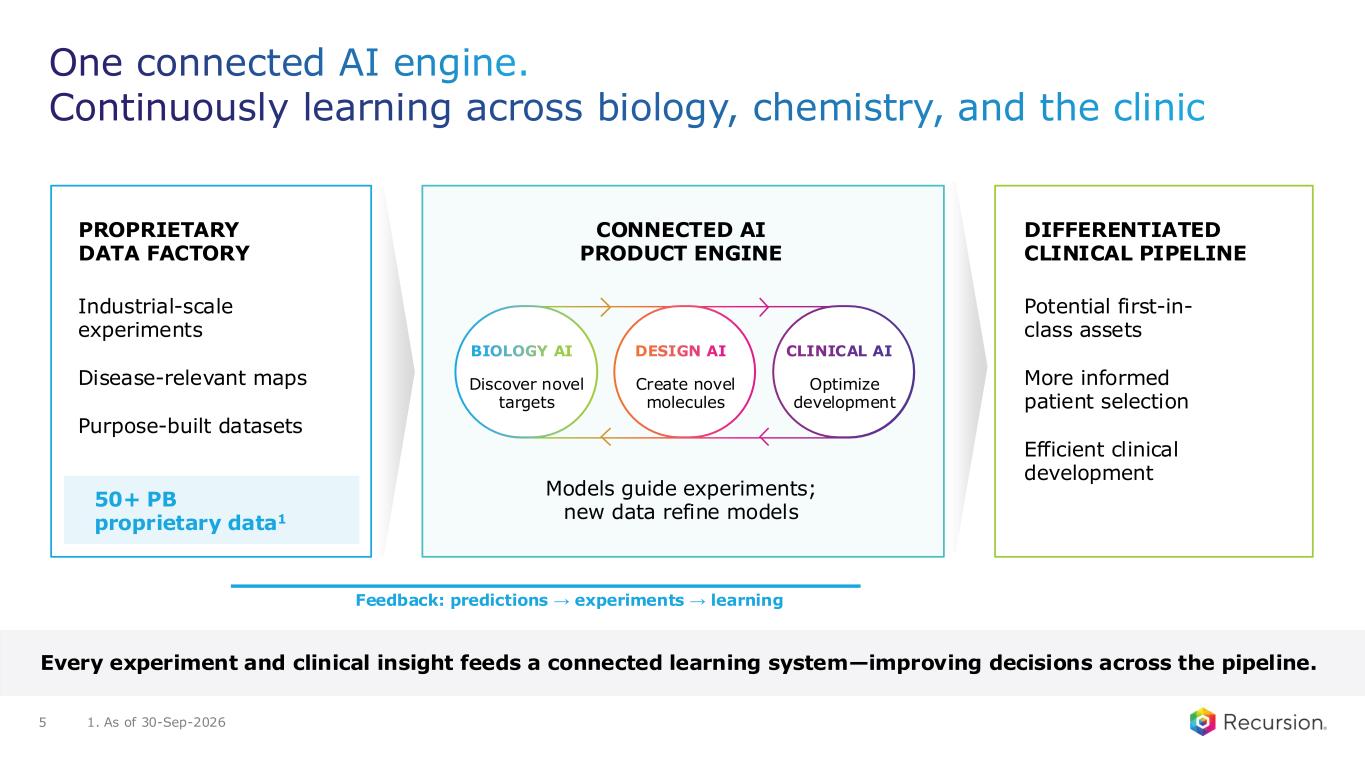
One connected AI engine. Continuously learning across biology, chemistry, and the clinic 5 PROPRIETARY DATA FACTORY Industrial-scale experiments Disease-relevant maps Purpose-built datasets 50+ PB proprietary data1 CONNECTED AI PRODUCT ENGINE Models guide experiments; new data refine models DIFFERENTIATED CLINICAL PIPELINE Potential first-in- class assets More informed patient selection Efficient clinical development Feedback: predictions → experiments → learning Every experiment and clinical insight feeds a connected learning system—improving decisions across the pipeline. BIOLOGY AI Discover novel targets DESIGN AI Create novel molecules CLINICAL AI Optimize development 1. As of 30-Sep-2026
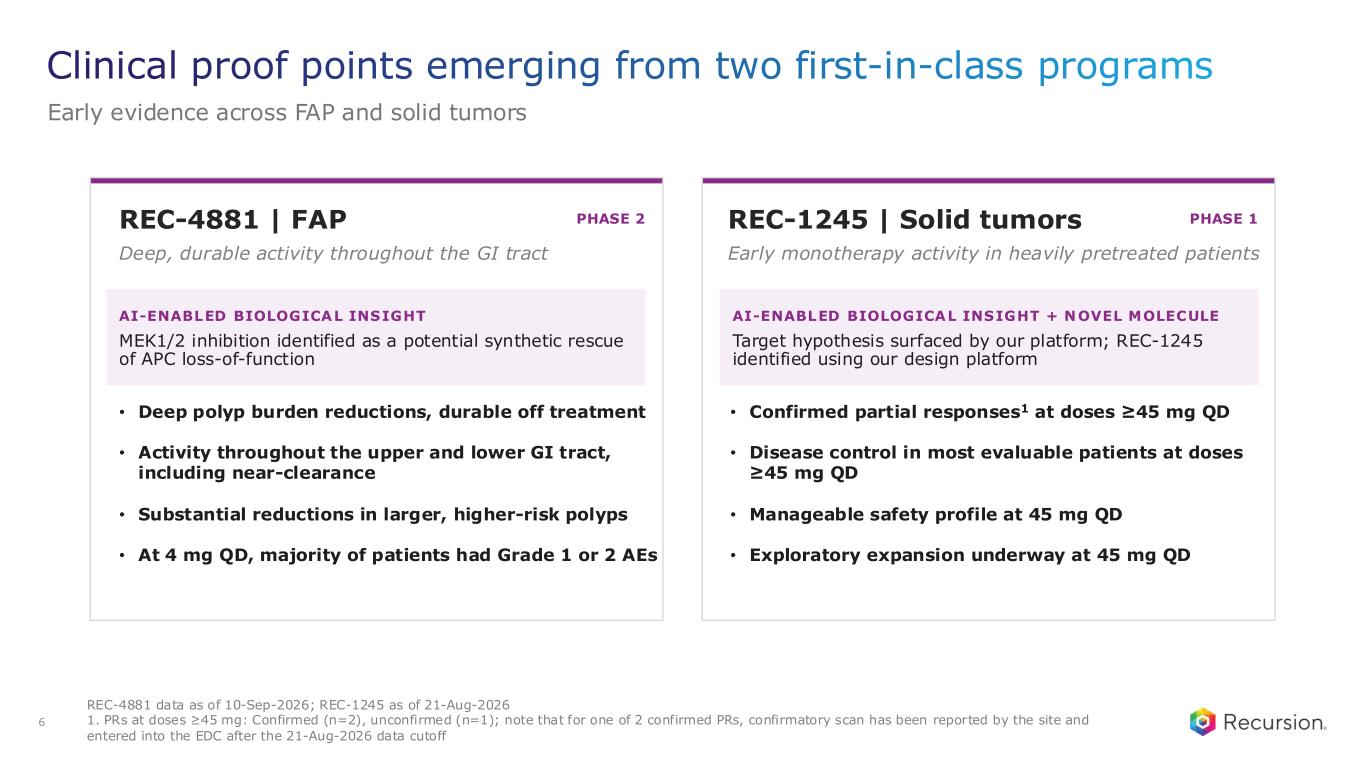
Clinical proof points emerging from two first-in-class programs Early evidence across FAP and solid tumors 6 REC-4881 data as of 10-Sep-2026; REC-1245 as of 21-Aug-2026 1. PRs at doses ≥45 mg: Confirmed (n=2), unconfirmed (n=1); note that for one of 2 confirmed PRs, confirmatory scan has been reported by the site and entered into the EDC after the 21-Aug-2026 data cutoff REC-4881 | FAP PHASE 2 Deep, durable activity throughout the GI tract AI-ENABLED BIOLOGICAL INSIGHT MEK1/2 inhibition identified as a potential synthetic rescue of APC loss-of-function • Deep polyp burden reductions, durable off treatment • Activity throughout the upper and lower GI tract, including near-clearance • Substantial reductions in larger, higher-risk polyps • At 4 mg QD, majority of patients had Grade 1 or 2 AEs REC-1245 | Solid tumors PHASE 1 Early monotherapy activity in heavily pretreated patients AI-ENABLED BIOLOGICAL INSIGHT + NOVEL MOLECULE Target hypothesis surfaced by our platform; REC-1245 identified using our design platform • Confirmed partial responses1 at doses ≥45 mg QD • Disease control in most evaluable patients at doses ≥45 mg QD • Manageable safety profile at 45 mg QD • Exploratory expansion underway at 45 mg QD
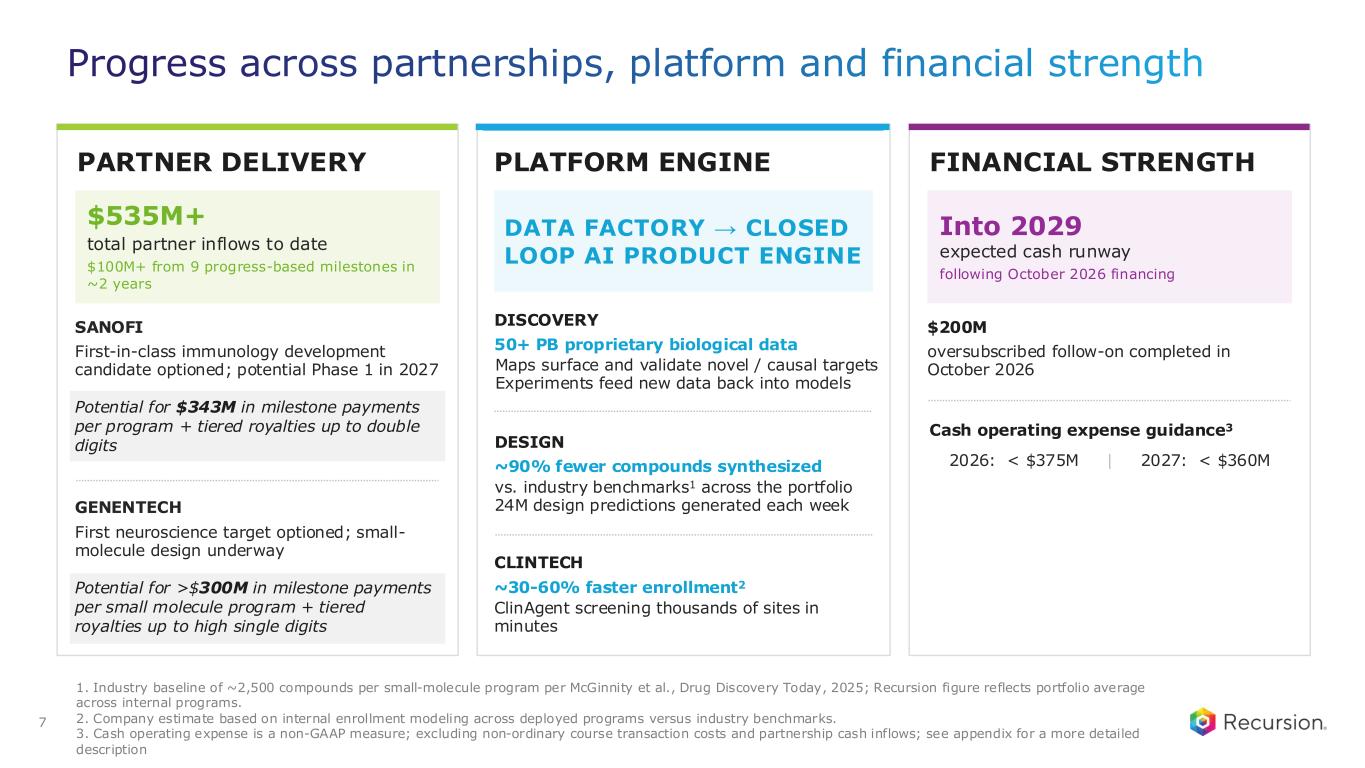
Progress across partnerships, platform and financial strength PARTNER DELIVERY $535M+ total partner inflows to date $100M+ from 9 progress-based milestones in ~2 years SANOFI First-in-class immunology development candidate optioned; potential Phase 1 in 2027 Potential for $343M in milestone payments per program + tiered royalties up to double digits GENENTECH First neuroscience target optioned; small- molecule design underway Potential for >$300M in milestone payments per small molecule program + tiered royalties up to high single digits PLATFORM ENGINE FINANCIAL STRENGTH Into 2029 expected cash runway following October 2026 financing $200M oversubscribed follow-on completed in October 2026 Cash operating expense guidance3 2026: < $375M | 2027: < $360M DATA FACTORY → CLOSED LOOP AI PRODUCT ENGINE DISCOVERY 50+ PB proprietary biological data Maps surface and validate novel / causal targets Experiments feed new data back into models DESIGN ~90% fewer compounds synthesized vs. industry benchmarks1 across the portfolio 24M design predictions generated each week CLINTECH ~30-60% faster enrollment2 ClinAgent screening thousands of sites in minutes 7 1. Industry baseline of ~2,500 compounds per small-molecule program per McGinnity et al., Drug Discovery Today, 2025; Recursion figure reflects portfolio average across internal programs. 2. Company estimate based on internal enrollment modeling across deployed programs versus industry benchmarks. 3. Cash operating expense is a non-GAAP measure; excluding non-ordinary course transaction costs and partnership cash inflows; see appendix for a more detailed description

Recursion announces Sanofi options potential first-in-class immunology development candidate from our collaboration 1. The $10 million milestone payment will be recognized as revenue in the third quarter of 2026, and ends Recursion’s operational requirements related to this candidate, with all future payments resulting in profit to Recursion 2. Inclusive of latest achieved $10 million milestone payment 8 6th milestone | $144M upfront & milestone inflows2 | $343M potential milestones per program Potential first-in-class, oral, dual-targeting inhibitor $10M1 Milestone payment achieved Double-digit royalties if approved Expected Phase 1 entry in 2027 Differentiated profile against a challenging dual target implicated in inflammatory disease Optimizing for this target pair required navigating complex and competing chemistry constraints to achieve the desired balance of drug-like properties. Recursion Announces Sanofi Options Potential First-in-Class Immunology Development Candidate from Their Collaboration October 15, 2026 at 8:45 AM EDT Potential first-in-class dual targeting inhibitor oral small molecule to enter Sanofi’s development pipeline, with phase 1 clinical study currently planned to begin in 2027 Salt Lake City, UT, Oct. 15, 2026 (GLOBE NEWSWIRE) -- Recursion Pharmaceuticals, Inc. (“Recursion”) (NASDAQ: RXRX), a leading clinical-stage company pioneering AI-enabled drug discovery and development decoding biology to radically improve lives, today announced that Sanofi has optioned the first development candidate from the two companies’ multi-program research collaboration. The option triggered a $10 million milestone payment to Recursion, bringing total upfront and milestone payments received from Sanofi under the collaboration to $144 million; Recursion is eligible for more than $300 million in additional milestones under the program, with double digit royalties on net product sales, if approved. “The most important test of any technology platform in drug discovery is whether it can translate into differentiated medicines,” said Najat Khan, Ph.D., President and Chief Executive Officer of Recursion. “Together with Sanofi, we tackled a difficult design problem against a dual target product profile with high potential and delivered a molecule that Sanofi has now selected for its development pipeline. With additional programs advancing across our collaboration, this milestone is another important demonstration of how our platform can translate computational capabilities into differentiated medicines — and do so repeatedly.” The potential first-in-class oral small molecule was designed to achieve a differentiated profile against a challenging dual target implicated in inflammatory disease. Optimizing for this target pair required navigating complex and competing chemistry constraints to achieve the desired balance of drug-like properties. The candidate was delivered by the combination of Recursion’s integrated AI-enabled drug design platform and small-molecule chemistry capabilities with Sanofi’s deep expertise in drug discovery and immunology. Recursion applied multiple computational design approaches across iterative cycles of prediction, chemical design, synthesis, and experimental validation to rapidly explore and optimize a complex chemical space. "By combining Sanofi's drug discovery and clinical and translational knowledge in immunology with Recursion's AI- driven platform, we were able to move with speed and precision in a space where that balance is notoriously hard to achieve,” said Alyssa Johnsen, Therapeutic Area Head, Development, Immunology & Inflammation, Sanofi. “This new development candidate has potential to deliver a differentiated oral medicine with highly selective dual targeting that could be a meaningful advance for people living with inflammatory diseases who still lack adequate treatment options.” The candidate has now been added to Sanofi’s development pipeline and is expected to enter phase 1 clinical trials in 2027, with Sanofi funding and leading further development and commercialization to advance the program toward patients.
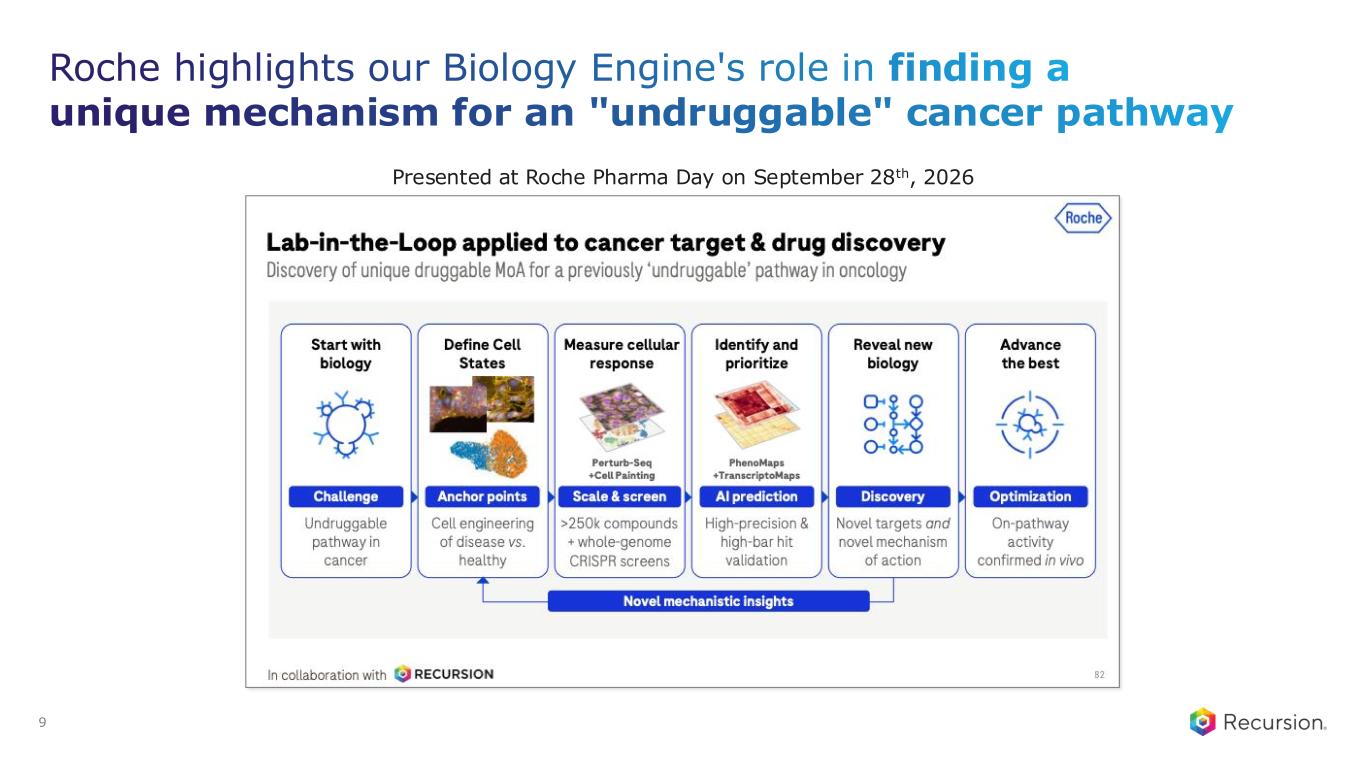
Roche highlights our Biology Engine's role in finding a unique mechanism for an "undruggable" cancer pathway Presented at Roche Pharma Day on September 28th, 2026 9
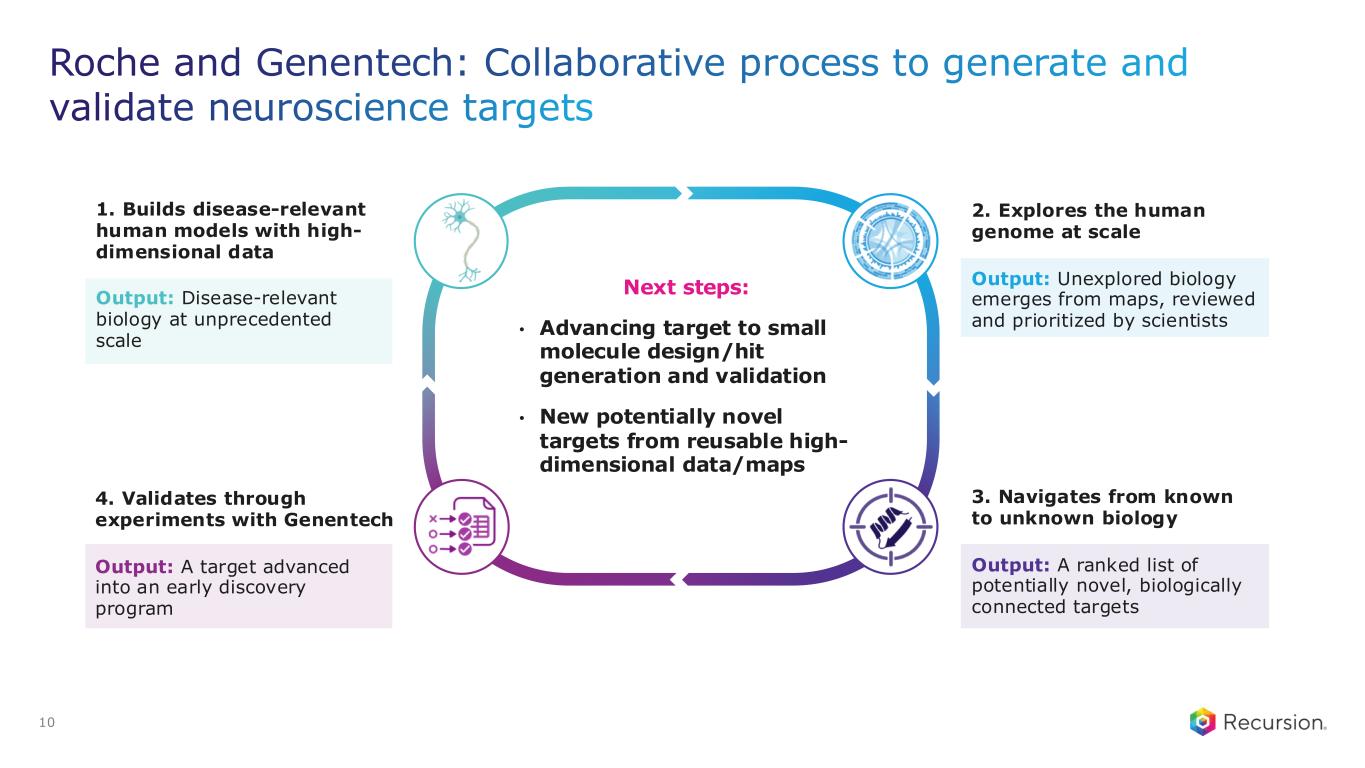
Roche and Genentech: Collaborative process to generate and validate neuroscience targets 10 1. Builds disease-relevant human models with high- dimensional data Output: Disease-relevant biology at unprecedented scale 4. Validates through experiments with Genentech Output: A target advanced into an early discovery program 2. Explores the human genome at scale Output: Unexplored biology emerges from maps, reviewed and prioritized by scientists 3. Navigates from known to unknown biology Output: A ranked list of potentially novel, biologically connected targets Next steps: • Advancing target to small molecule design/hit generation and validation • New potentially novel targets from reusable high- dimensional data/maps

Recursion appoints Fred Hassan as Chair of the Board Fred Hassan Chair of the Board effective October 31, 2026 Four decades in pharma leadership Proven track record of company transformations Experience with innovative business models Board, data and investing insights 11

Internal Pipeline Today’s news
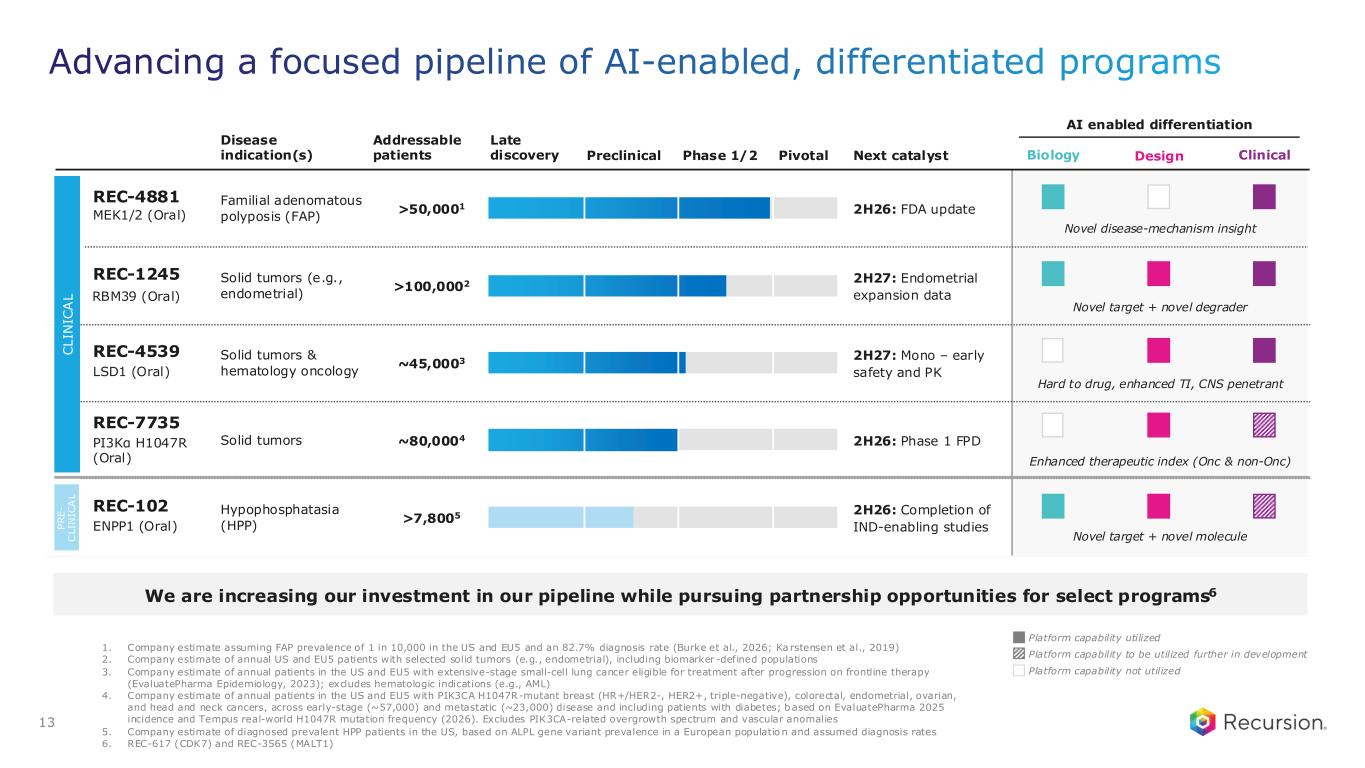
Advancing a focused pipeline of AI-enabled, differentiated programs 13 Platform capability utilized Platform capability not utilized Platform capability to be utilized further in development Disease indication(s) Addressable patients Next catalyst AI enabled differentiation Late discovery Preclinical Phase 1/2 Pivotal Familial adenomatous polyposis (FAP) >50,0001 2H26: FDA update Solid tumors (e.g., endometrial) >100,0002 2H27: Endometrial expansion data Solid tumors & hematology oncology ~45,0003 2H27: Mono – early safety and PK Solid tumors ~80,0004 2H26: Phase 1 FPD Hypophosphatasia (HPP) >7,8005 2H26: Completion of IND-enabling studies C L IN IC A L P R E - C L IN IC A L Design Clinical REC-4881 MEK1/2 (Oral) REC-1245 RBM39 (Oral) REC-4539 LSD1 (Oral) REC-7735 PI3Kα H1047R (Oral) REC-102 ENPP1 (Oral) Biology Novel disease-mechanism insight Novel target + novel degrader Hard to drug, enhanced TI, CNS penetrant Enhanced therapeutic index (Onc & non-Onc) Novel target + novel molecule We are increasing our investment in our pipeline while pursuing partnership opportunities for select programs6 1. Company estimate assuming FAP prevalence of 1 in 10,000 in the US and EU5 and an 82.7% diagnosis rate (Burke et al., 2026; Ka rstensen et al., 2019) 2. Company estimate of annual US and EU5 patients with selected solid tumors (e.g., endometrial), including biomarker -defined populations 3. Company estimate of annual patients in the US and EU5 with extensive-stage small-cell lung cancer eligible for treatment after progression on frontline therapy (EvaluatePharma Epidemiology, 2023); excludes hematologic indications (e.g., AML) 4. Company estimate of annual patients in the US and EU5 with PIK3CA H1047R-mutant breast (HR+/HER2-, HER2+, triple-negative), colorectal, endometrial, ovarian, and head and neck cancers, across early-stage (~57,000) and metastatic (~23,000) disease and including patients with diabetes; based on EvaluatePharma 2025 incidence and Tempus real-world H1047R mutation frequency (2026). Excludes PIK3CA-related overgrowth spectrum and vascular anomalies 5. Company estimate of diagnosed prevalent HPP patients in the US, based on ALPL gene variant prevalence in a European populatio n and assumed diagnosis rates 6. REC-617 (CDK7) and REC-3565 (MALT1)

REC-4881 MEK1/2 Translating proof to products

15 A registrational study of REC-4881 in FAP is expected to begin in 2H 2027 Note: Registrational study initiation pending outcome of ongoing FDA discussions 30th CGA-IGC Annual Meeting, Denver • Leading annual meeting dedicated specifically to hereditary GI cancer syndromes including FAP • Highly targeted audience: Connects the entire care ecosystem including gastroenterologists, surgeons, genetic counselors, and researchers REC-4881 Data Summary • Reductions in larger, higher-risk polyps observed • Combined findings support activity across the upper and lower GI tract • No new safety signals observed in the updated data
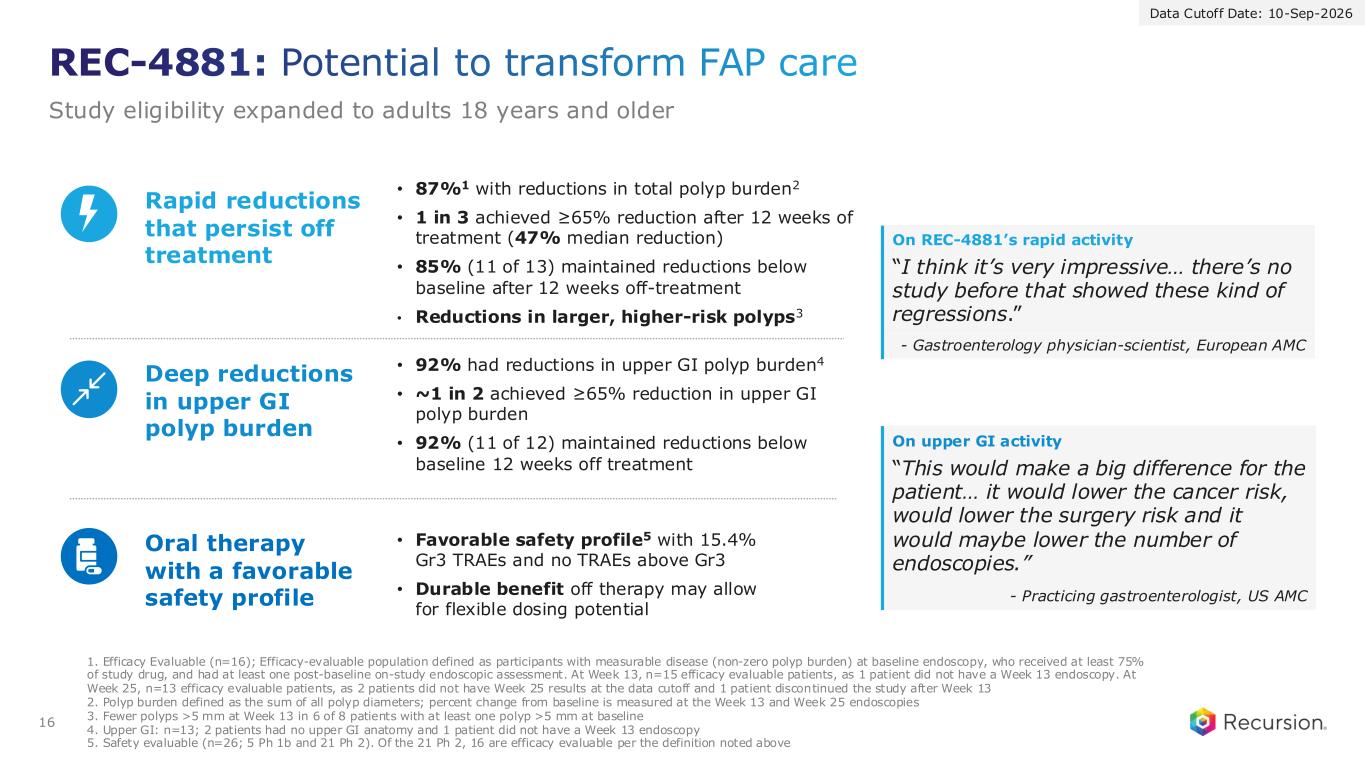
REC-4881: Potential to transform FAP care Study eligibility expanded to adults 18 years and older 16 • Favorable safety profile5 with 15.4% Gr3 TRAEs and no TRAEs above Gr3 • Durable benefit off therapy may allow for flexible dosing potential Oral therapy with a favorable safety profile • 87%1 with reductions in total polyp burden2 • 1 in 3 achieved ≥65% reduction after 12 weeks of treatment (47% median reduction) • 85% (11 of 13) maintained reductions below baseline after 12 weeks off-treatment • Reductions in larger, higher-risk polyps3 Rapid reductions that persist off treatment On REC-4881’s rapid activity “I think it’s very impressive… there’s no study before that showed these kind of regressions.” - Gastroenterology physician-scientist, European AMC • 92% had reductions in upper GI polyp burden4 • ~1 in 2 achieved ≥65% reduction in upper GI polyp burden • 92% (11 of 12) maintained reductions below baseline 12 weeks off treatment Deep reductions in upper GI polyp burden On upper GI activity “This would make a big difference for the patient… it would lower the cancer risk, would lower the surgery risk and it would maybe lower the number of endoscopies.” - Practicing gastroenterologist, US AMC 1. Efficacy Evaluable (n=16); Efficacy-evaluable population defined as participants with measurable disease (non-zero polyp burden) at baseline endoscopy, who received at least 75% of study drug, and had at least one post-baseline on-study endoscopic assessment. At Week 13, n=15 efficacy evaluable patients, as 1 patient did not have a Week 13 endoscopy. At Week 25, n=13 efficacy evaluable patients, as 2 patients did not have Week 25 results at the data cutoff and 1 patient discontinued the study after Week 13 2. Polyp burden defined as the sum of all polyp diameters; percent change from baseline is measured at the Week 13 and Week 25 endoscopies 3. Fewer polyps >5 mm at Week 13 in 6 of 8 patients with at least one polyp >5 mm at baseline 4. Upper GI: n=13; 2 patients had no upper GI anatomy and 1 patient did not have a Week 13 endoscopy 5. Safety evaluable (n=26; 5 Ph 1b and 21 Ph 2). Of the 21 Ph 2, 16 are efficacy evaluable per the definition noted above Data Cutoff Date: 10-Sep-2026
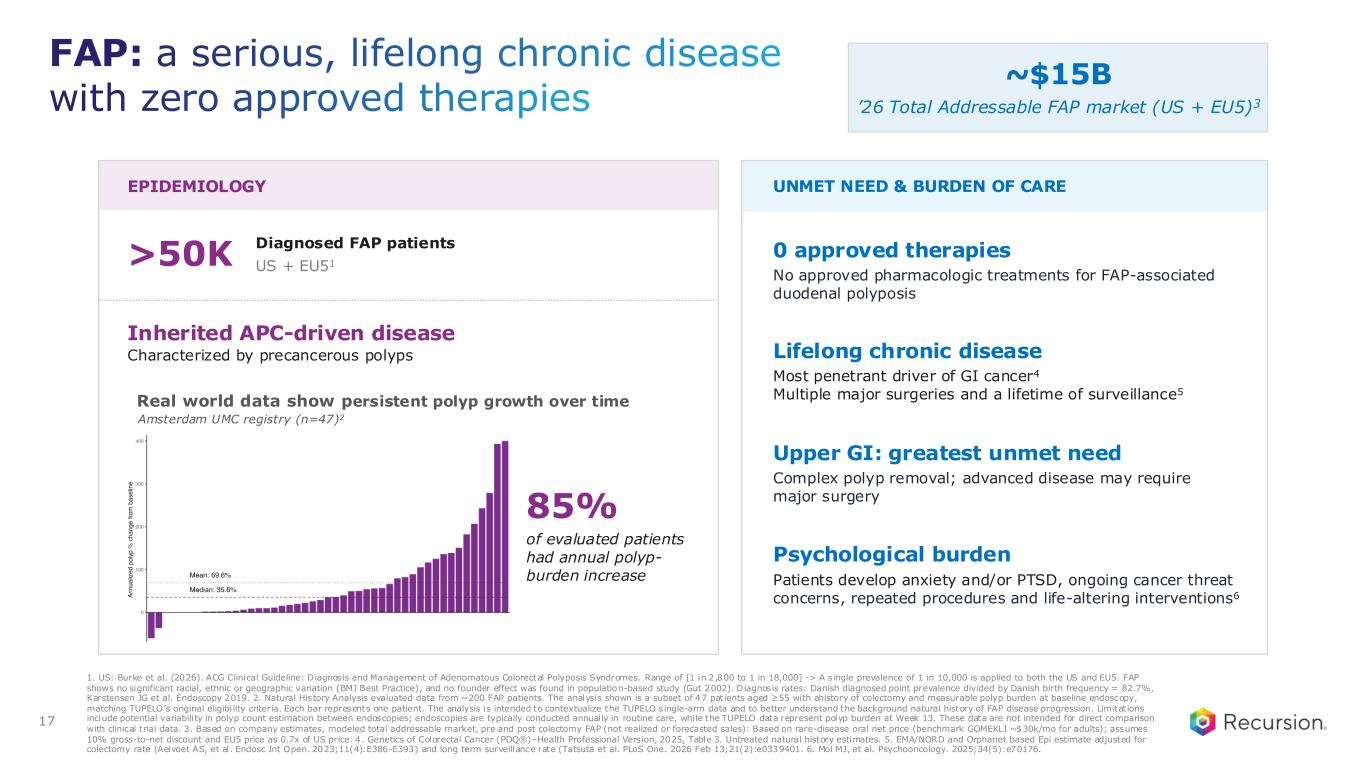
EPIDEMIOLOGY UNMET NEED & BURDEN OF CARE >50K Diagnosed FAP patients US + EU51 Inherited APC-driven disease Characterized by precancerous polyps Real world data show persistent polyp growth over time 0 approved therapies No approved pharmacologic treatments for FAP-associated duodenal polyposis Lifelong chronic disease Most penetrant driver of GI cancer4 Multiple major surgeries and a lifetime of surveillance5 Upper GI: greatest unmet need Complex polyp removal; advanced disease may require major surgery Psychological burden Patients develop anxiety and/or PTSD, ongoing cancer threat concerns, repeated procedures and life-altering interventions6 Amsterdam UMC registry (n=47)2 85% of evaluated patients had annual polyp- burden increase 1. US: Burke et al. (2026). ACG Clinical Guideline: Diagnosis and Management of Adenomatous Colorectal Polyposis Syndromes. Range of [1 in 2,800 to 1 in 18,000] -> A single prevalence of 1 in 10,000 is applied to both the US and EU5. FAP shows no significant racial, ethnic or geographic variation (BMJ Best Practice), and no founder effect was found in population-based study (Gut 2002). Diagnosis rates: Danish diagnosed point prevalence divided by Danish birth frequency = 82.7%, Karstensen JG et al. Endoscopy 2019. 2. Natural History Analysis evaluated data from ~200 FAP patients. The analysis shown is a subset of 47 patients aged ≥55 with a history of colectomy and measurable polyp burden at baseline endoscopy, matching TUPELO’s original eligibi lity criteria. Each bar represents one patient. The analysis is intended to contextualize the TUPELO single-arm data and to better understand the background natural history of FAP disease progression. Limitations include potential variability in polyp count estimation between endoscopies; endoscopies are typically conducted annually in routine care, while the TUPELO data represent polyp burden at Week 13. These data are not intended for direct comparison with clinical trial data. 3. Based on company estimates, modeled total addressable market, pre and post colectomy FAP (not realized or forecasted sales): Based on rare-disease oral net price (benchmark GOMEKLI ~$30k/mo for adults); assumes 10% gross-to-net discount and EU5 price as 0.7x of US price. 4. Genetics of Colorectal Cancer (PDQ®)–Health Professional Version, 2025, Table 3. Untreated natural history estimates. 5. EMA/NORD and Orphanet based Epi estimate adjusted for colectomy rate (Aelvoet AS, et al. Endosc Int Open. 2023;11(4):E386-E393) and long term surveillance rate (Tatsuta et al. PLoS One. 2026 Feb 13;21(2):e0339401. 6. Mol MJ, et al. Psychooncology. 2025;34(5):e70176. ~$15B ’26 Total Addressable FAP market (US + EU5)3 FAP: a serious, lifelong chronic disease with zero approved therapies 17
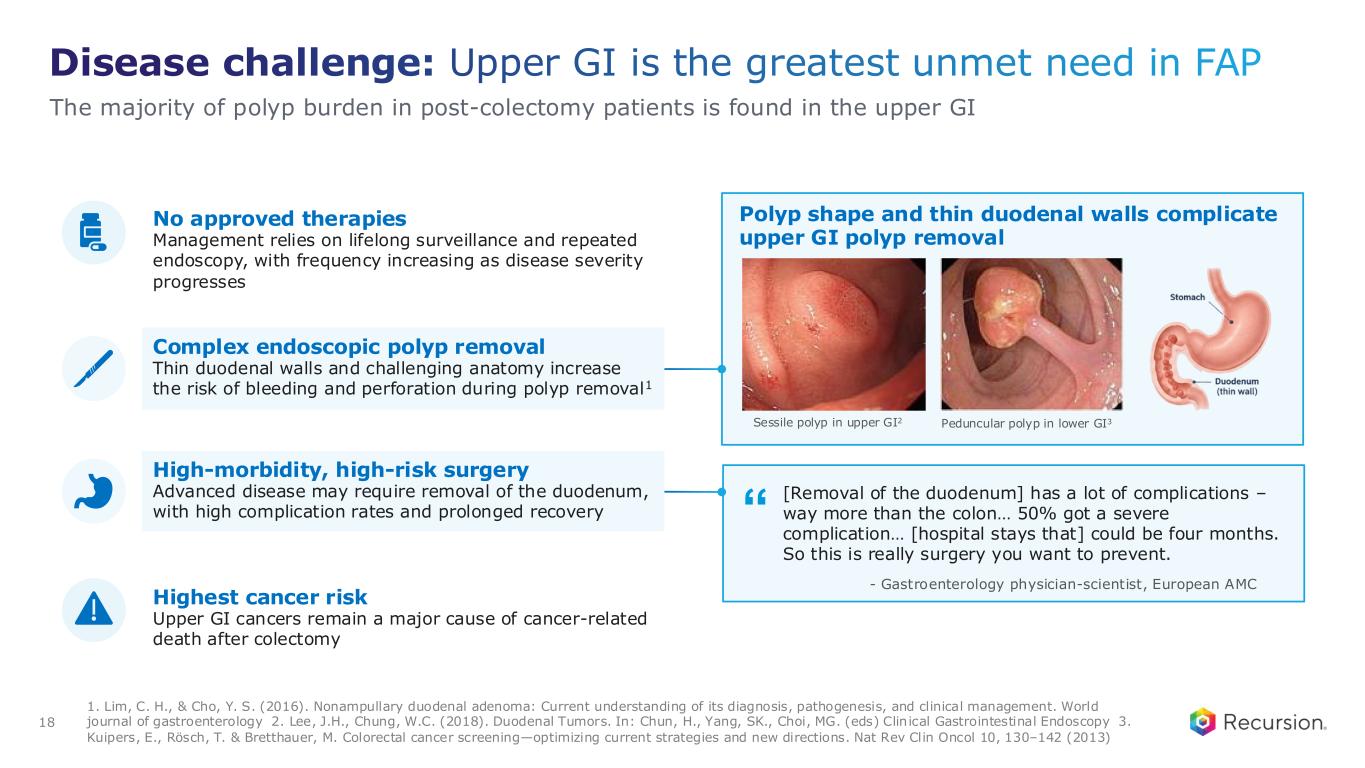
“ Disease challenge: Upper GI is the greatest unmet need in FAP 1. Lim, C. H., & Cho, Y. S. (2016). Nonampullary duodenal adenoma: Current understanding of its diagnosis, pathogenesis, and clinical management. World journal of gastroenterology 2. Lee, J.H., Chung, W.C. (2018). Duodenal Tumors. In: Chun, H., Yang, SK., Choi, MG. (eds) Clinical Gastrointestinal Endoscopy 3. Kuipers, E., Rösch, T. & Bretthauer, M. Colorectal cancer screening—optimizing current strategies and new directions. Nat Rev Clin Oncol 10, 130–142 (2013) No approved therapies Management relies on lifelong surveillance and repeated endoscopy, with frequency increasing as disease severity progresses Complex endoscopic polyp removal Thin duodenal walls and challenging anatomy increase the risk of bleeding and perforation during polyp removal1 High-morbidity, high-risk surgery Advanced disease may require removal of the duodenum, with high complication rates and prolonged recovery Highest cancer risk Upper GI cancers remain a major cause of cancer-related death after colectomy Polyp shape and thin duodenal walls complicate upper GI polyp removal Sessile polyp in upper GI2 Peduncular polyp in lower GI3 [Removal of the duodenum] has a lot of complications – way more than the colon… 50% got a severe complication… [hospital stays that] could be four months. So this is really surgery you want to prevent. - Gastroenterology physician-scientist, European AMC The majority of polyp burden in post-colectomy patients is found in the upper GI 18
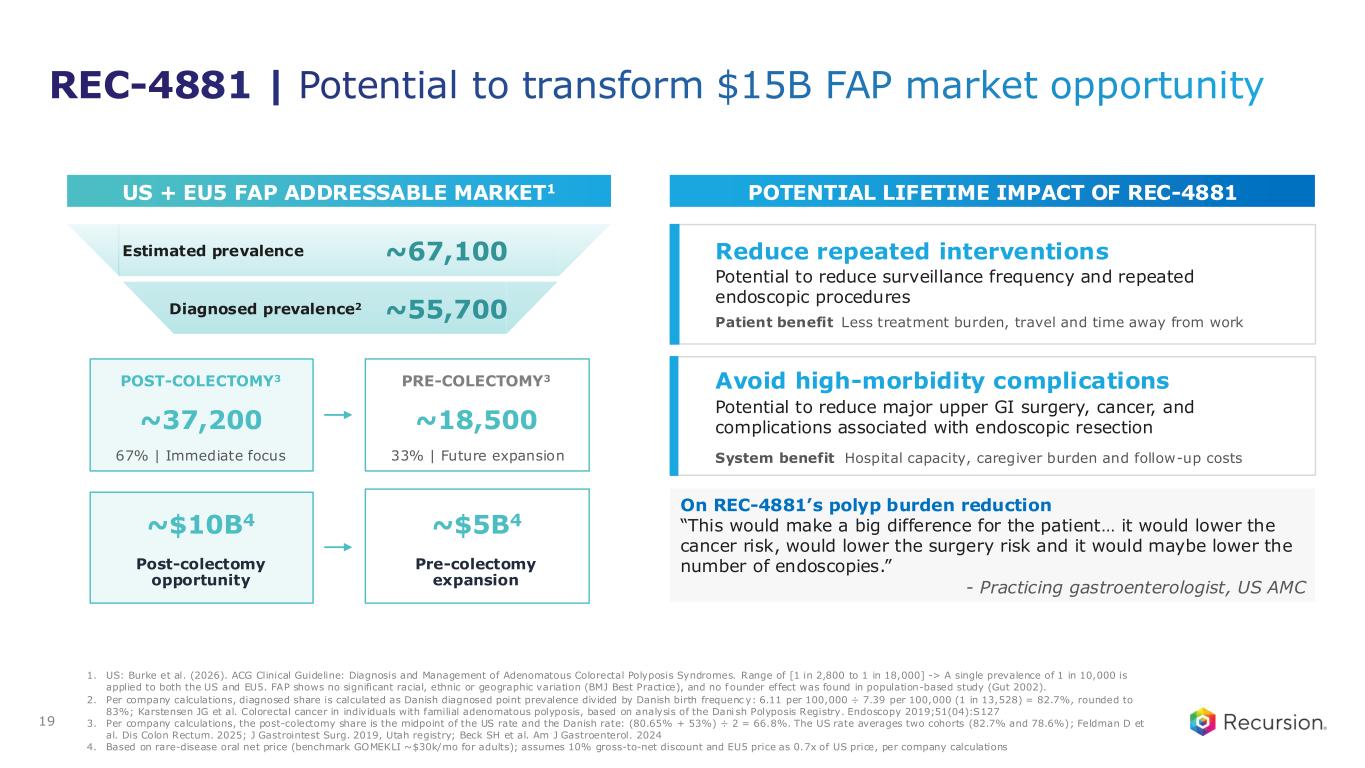
US + EU5 FAP ADDRESSABLE MARKET1 POTENTIAL LIFETIME IMPACT OF REC-4881 Reduce repeated interventions Potential to reduce surveillance frequency and repeated endoscopic procedures Patient benefit Less treatment burden, travel and time away from work Avoid high-morbidity complications Potential to reduce major upper GI surgery, cancer, and complications associated with endoscopic resection System benefit Hospital capacity, caregiver burden and follow-up costs 1. US: Burke et al. (2026). ACG Clinical Guideline: Diagnosis and Management of Adenomatous Colorectal Polyposis Syndromes. Range of [1 in 2,800 to 1 in 18,000] -> A single prevalence of 1 in 10,000 is applied to both the US and EU5. FAP shows no significant racial, ethnic or geographic variation (BMJ Best Practice), and no f ounder effect was found in population-based study (Gut 2002). 2. Per company calculations, diagnosed share is calculated as Danish diagnosed point prevalence divided by Danish birth frequenc y: 6.11 per 100,000 ÷ 7.39 per 100,000 (1 in 13,528) = 82.7%, rounded to 83%; Karstensen JG et al. Colorectal cancer in individuals with familial adenomatous polyposis, based on analysis of the Dani sh Polyposis Registry. Endoscopy 2019;51(04):S127 3. Per company calculations, the post-colectomy share is the midpoint of the US rate and the Danish rate: (80.65% + 53%) ÷ 2 = 66.8%. The US rate averages two cohorts (82.7% and 78.6%); Feldman D et al. Dis Colon Rectum. 2025; J Gastrointest Surg. 2019, Utah registry; Beck SH et al. Am J Gastroenterol. 2024 4. Based on rare-disease oral net price (benchmark GOMEKLI ~$30k/mo for adults); assumes 10% gross-to-net discount and EU5 price as 0.7x of US price, per company calculations Estimated prevalence ~67,100 Diagnosed prevalence2 ~55,700 POST-COLECTOMY3 ~37,200 67% | Immediate focus PRE-COLECTOMY3 ~18,500 33% | Future expansion ~$10B4 Post-colectomy opportunity ~$5B4 Pre-colectomy expansion On REC-4881’s polyp burden reduction “This would make a big difference for the patient… it would lower the cancer risk, would lower the surgery risk and it would maybe lower the number of endoscopies.” - Practicing gastroenterologist, US AMC REC-4881 | Potential to transform $15B FAP market opportunity 19
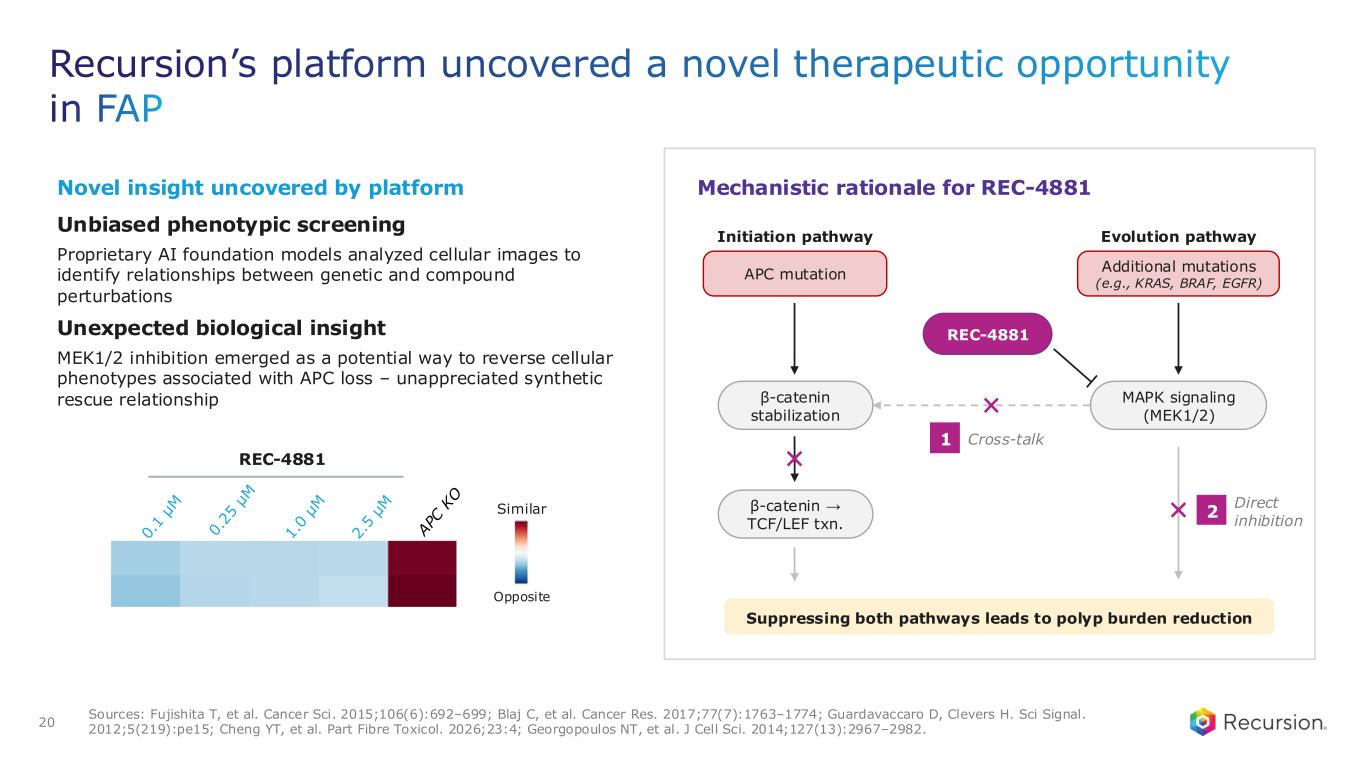
Recursion’s platform uncovered a novel therapeutic opportunity in FAP 20 Sources: Fujishita T, et al. Cancer Sci. 2015;106(6):692–699; Blaj C, et al. Cancer Res. 2017;77(7):1763–1774; Guardavaccaro D, Clevers H. Sci Signal. 2012;5(219):pe15; Cheng YT, et al. Part Fibre Toxicol. 2026;23:4; Georgopoulos NT, et al. J Cell Sci. 2014;127(13):2967–2982. REC-4881 Similar Opposite Unbiased phenotypic screening Proprietary AI foundation models analyzed cellular images to identify relationships between genetic and compound perturbations Novel insight uncovered by platform Suppressing both pathways leads to polyp burden reduction Initiation pathway APC mutation β-catenin stabilization β-catenin → TCF/LEF txn. Evolution pathway Additional mutations (e.g., KRAS, BRAF, EGFR) MAPK signaling (MEK1/2) REC-4881 Cross-talk1 Direct inhibition 2 Mechanistic rationale for REC-4881 Unexpected biological insight MEK1/2 inhibition emerged as a potential way to reverse cellular phenotypes associated with APC loss – unappreciated synthetic rescue relationship
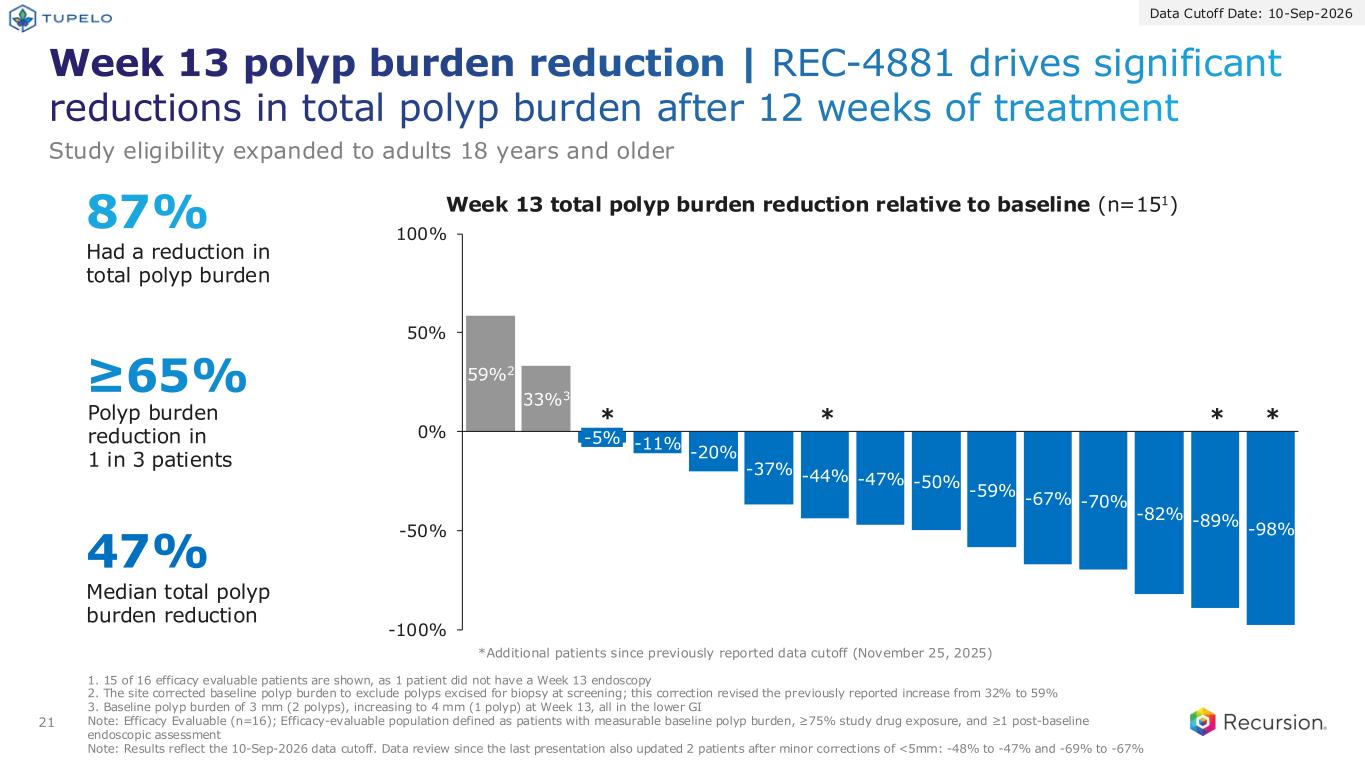
Week 13 polyp burden reduction | REC-4881 drives significant reductions in total polyp burden after 12 weeks of treatment 21 -11% -20% -37% -44% -47% -50% -59% -67% -70% -82% -89% -98% -100% -50% 0% 50% 100% -5% 59%2 33%3 87% Had a reduction in total polyp burden ≥65% Polyp burden reduction in 1 in 3 patients 47% Median total polyp burden reduction Week 13 total polyp burden reduction relative to baseline (n=151) 1. 15 of 16 efficacy evaluable patients are shown, as 1 patient did not have a Week 13 endoscopy 2. The site corrected baseline polyp burden to exclude polyps excised for biopsy at screening; this correction revised the previously reported increase from 32% to 59% 3. Baseline polyp burden of 3 mm (2 polyps), increasing to 4 mm (1 polyp) at Week 13, all in the lower GI Note: Efficacy Evaluable (n=16); Efficacy-evaluable population defined as patients with measurable baseline polyp burden, ≥75% study drug exposure, and ≥1 post-baseline endoscopic assessment Note: Results reflect the 10-Sep-2026 data cutoff. Data review since the last presentation also updated 2 patients after minor corrections of <5mm: -48% to -47% and -69% to -67% *** * *Additional patients since previously reported data cutoff (November 25, 2025) Study eligibility expanded to adults 18 years and older Data Cutoff Date: 10-Sep-2026
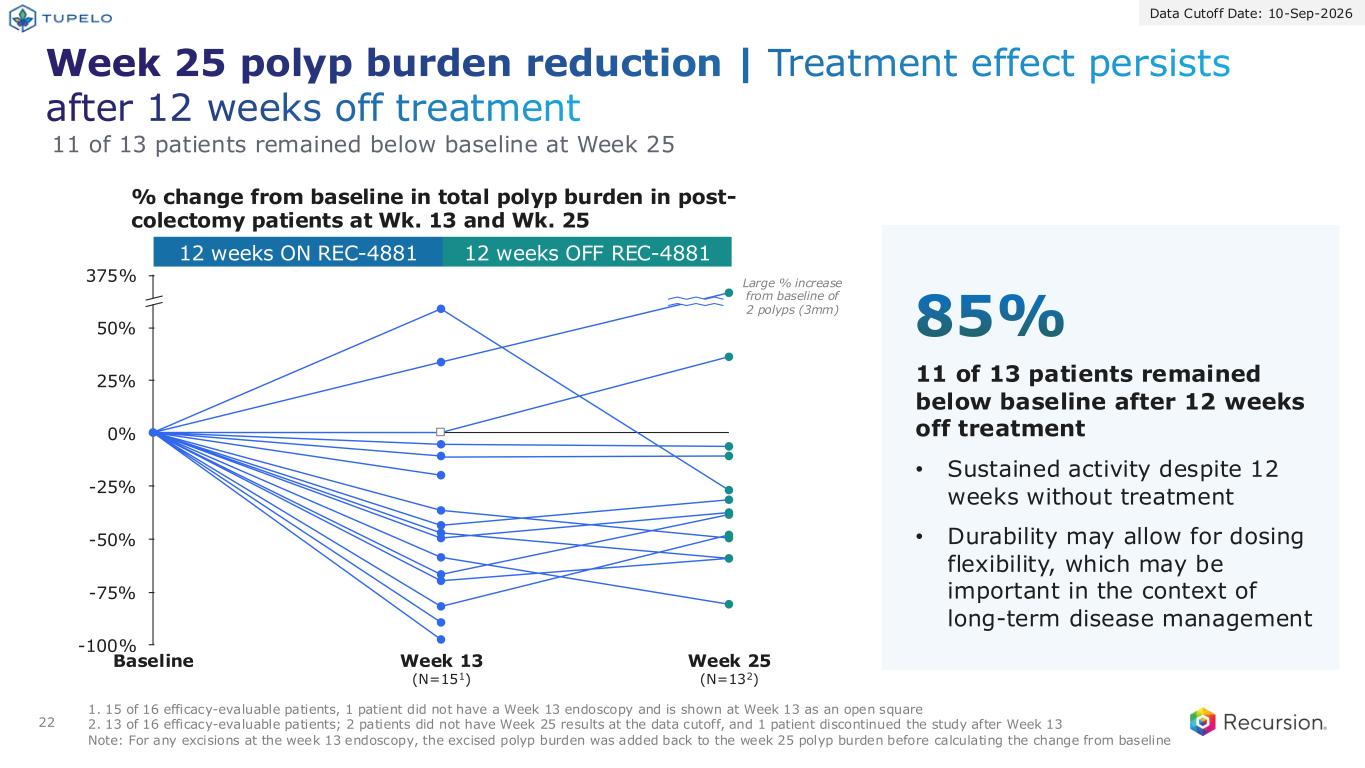
Week 25 polyp burden reduction | Treatment effect persists after 12 weeks off treatment 22 12 weeks ON REC-4881 12 weeks OFF REC-4881 % change from baseline in total polyp burden in post- colectomy patients at Wk. 13 and Wk. 25 1. 15 of 16 efficacy-evaluable patients, 1 patient did not have a Week 13 endoscopy and is shown at Week 13 as an open square 2. 13 of 16 efficacy-evaluable patients; 2 patients did not have Week 25 results at the data cutoff, and 1 patient discontinued the study after Week 13 Note: For any excisions at the week 13 endoscopy, the excised polyp burden was added back to the week 25 polyp burden before calculating the change from baseline -100% 0% -75% -50% -25% 25% 50% 375% Baseline Week 13 (N=151) Week 25 (N=132) 11 of 13 patients remained below baseline at Week 25 Large % increase from baseline of 2 polyps (3mm) 11 of 13 patients remained below baseline after 12 weeks off treatment • Sustained activity despite 12 weeks without treatment • Durability may allow for dosing flexibility, which may be important in the context of long-term disease management 85% Data Cutoff Date: 10-Sep-2026
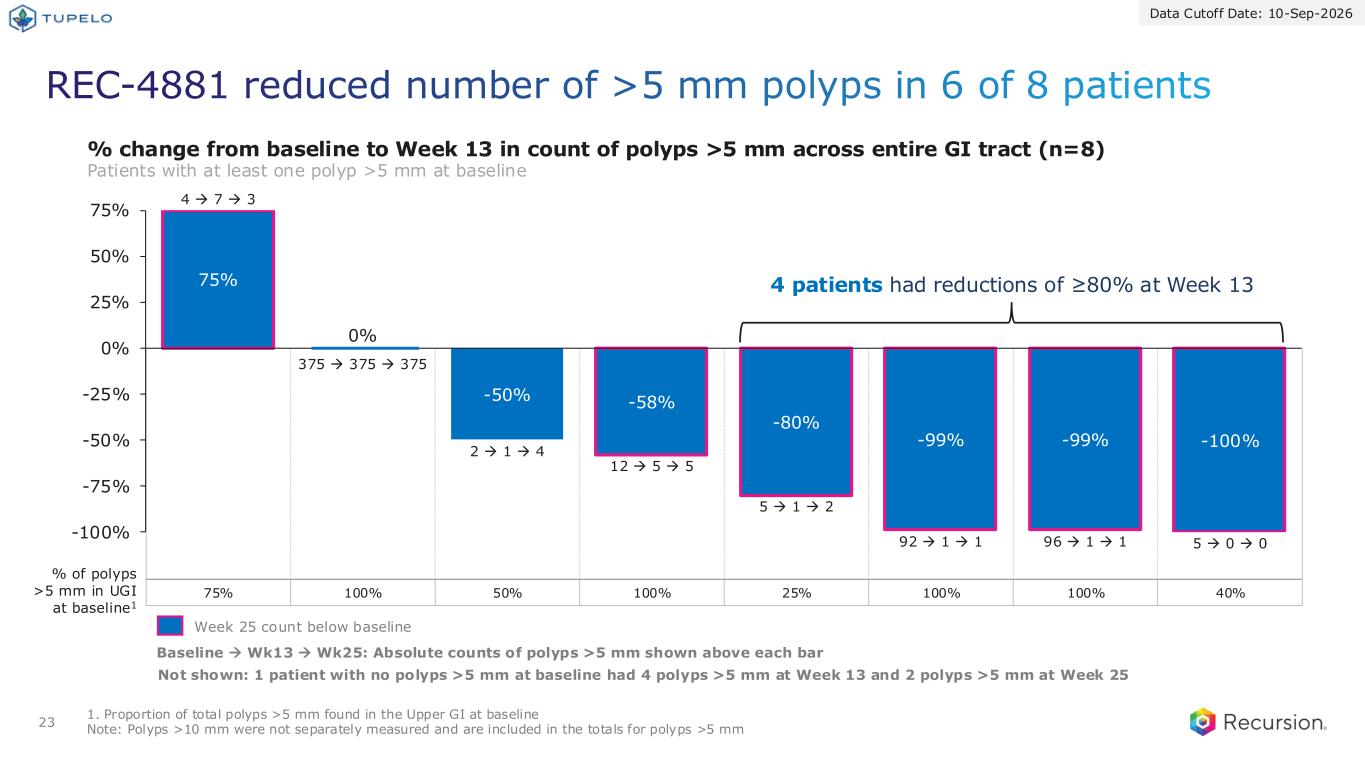
75% 100% 50% 100% 25% 100% 100% 40% REC-4881 reduced number of >5 mm polyps in 6 of 8 patients 23 Data Cutoff Date: 10-Sep-2026 75% -50% -58% -80% -99% -99% -100% -100% -75% -50% -25% 0% 25% 50% 75% 4 → 7 → 3 2 → 1 → 4 12 → 5 → 5 5 → 1 → 2 92 → 1 → 1 96 → 1 → 1 5 → 0 → 0 % change from baseline to Week 13 in count of polyps >5 mm across entire GI tract (n=8) Patients with at least one polyp >5 mm at baseline 1. Proportion of total polyps >5 mm found in the Upper GI at baseline Note: Polyps >10 mm were not separately measured and are included in the totals for polyps >5 mm Baseline → Wk13 → Wk25: Absolute counts of polyps >5 mm shown above each bar % of polyps >5 mm in UGI at baseline1 Week 25 count below baseline 4 patients had reductions of ≥80% at Week 13 375 → 375 → 375 0% Not shown: 1 patient with no polyps >5 mm at baseline had 4 polyps >5 mm at Week 13 and 2 polyps >5 mm at Week 25
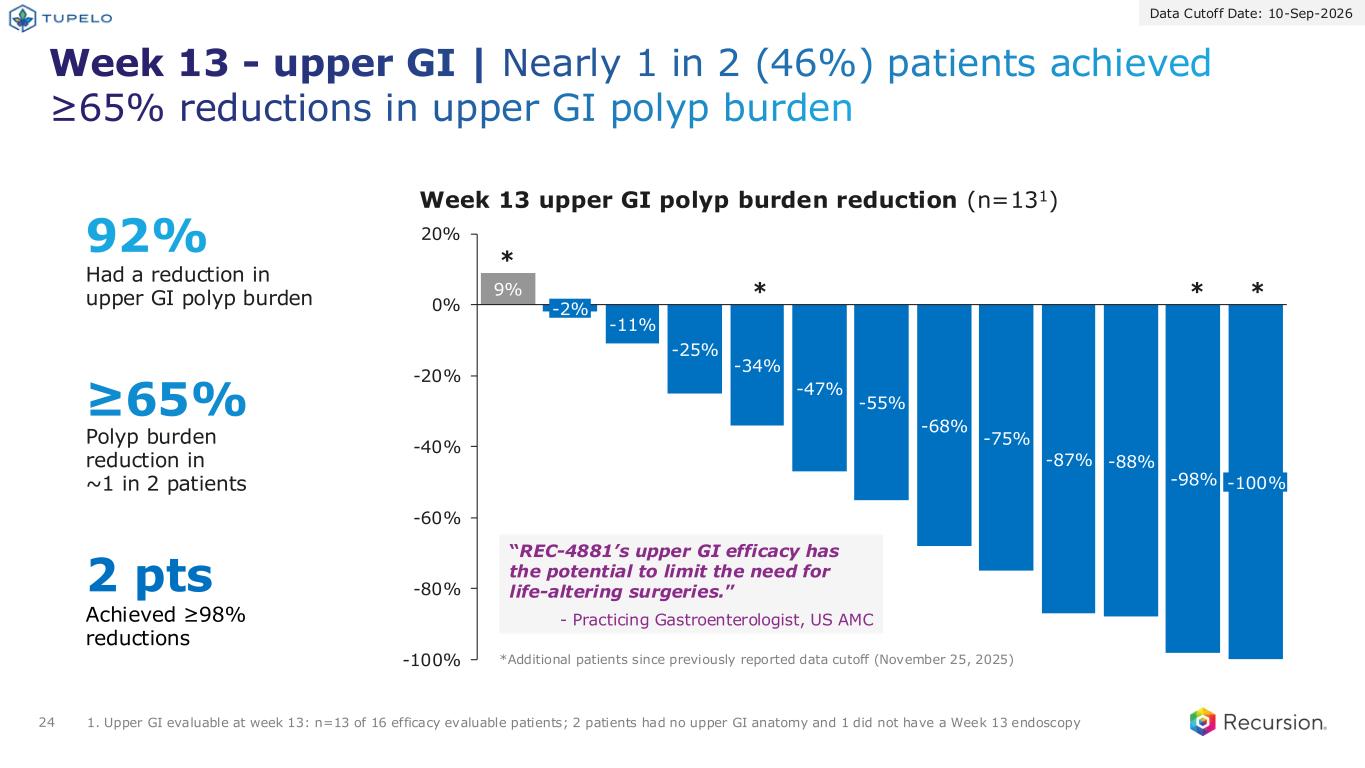
Week 13 - upper GI | Nearly 1 in 2 (46%) patients achieved ≥65% reductions in upper GI polyp burden 24 9% -11% -25% -34% -47% -55% -68% -75% -87% -88% -98% -100% -80% -60% -40% -20% 0% 20% -2% -100% Week 13 upper GI polyp burden reduction (n=131) “REC-4881’s upper GI efficacy has the potential to limit the need for life-altering surgeries.” - Practicing Gastroenterologist, US AMC *** * 92% Had a reduction in upper GI polyp burden ≥65% Polyp burden reduction in ~1 in 2 patients 2 pts Achieved ≥98% reductions 1. Upper GI evaluable at week 13: n=13 of 16 efficacy evaluable patients; 2 patients had no upper GI anatomy and 1 did not have a Week 13 endoscopy *Additional patients since previously reported data cutoff (November 25, 2025) Data Cutoff Date: 10-Sep-2026
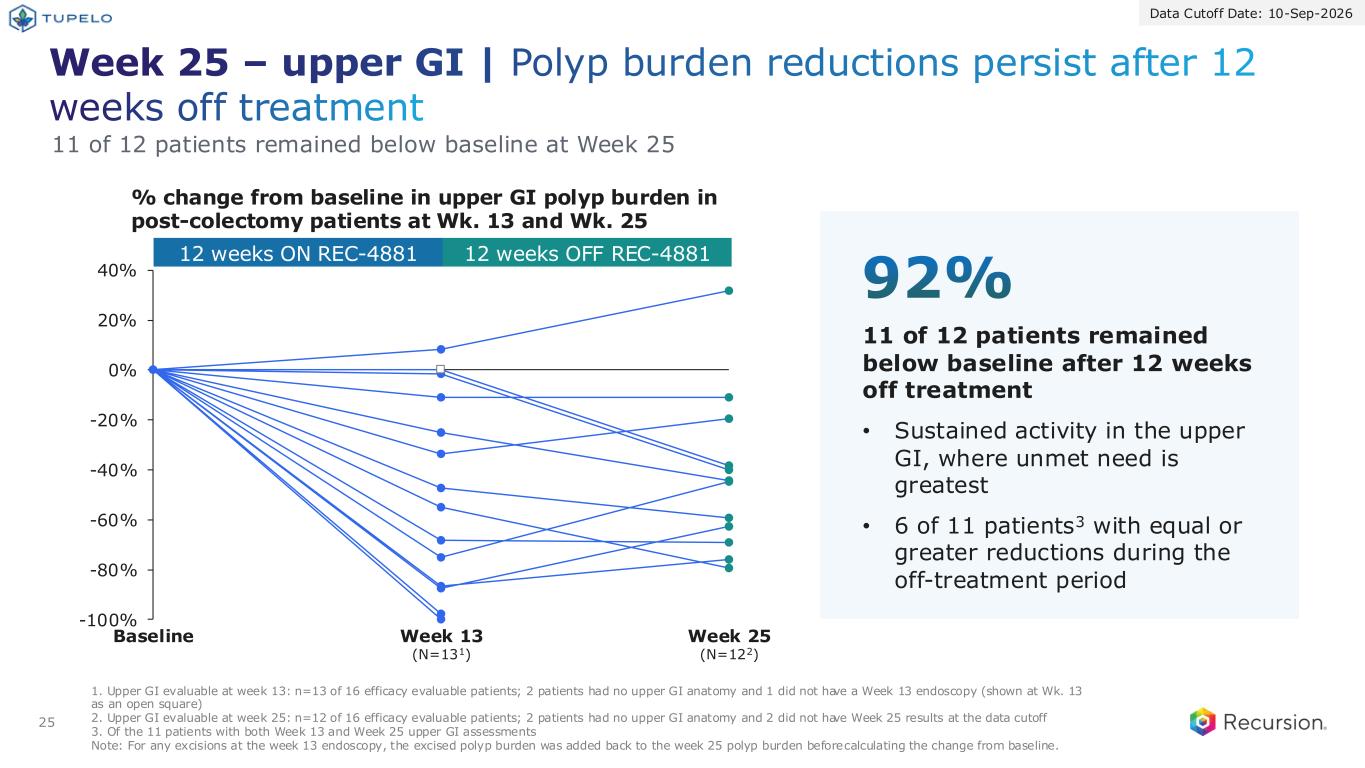
25 Week 25 – upper GI | Polyp burden reductions persist after 12 weeks off treatment -100% -80% -60% -40% -20% 0% 20% 40% Baseline Week 13 (N=131) Week 25 (N=122) 11 of 12 patients remained below baseline at Week 25 11 of 12 patients remained below baseline after 12 weeks off treatment • Sustained activity in the upper GI, where unmet need is greatest • 6 of 11 patients3 with equal or greater reductions during the off-treatment period 92% 12 weeks ON REC-4881 12 weeks OFF REC-4881 % change from baseline in upper GI polyp burden in post-colectomy patients at Wk. 13 and Wk. 25 Data Cutoff Date: 10-Sep-2026 1. Upper GI evaluable at week 13: n=13 of 16 efficacy evaluable patients; 2 patients had no upper GI anatomy and 1 did not have a Week 13 endoscopy (shown at Wk. 13 as an open square) 2. Upper GI evaluable at week 25: n=12 of 16 efficacy evaluable patients; 2 patients had no upper GI anatomy and 2 did not have Week 25 results at the data cutoff 3. Of the 11 patients with both Week 13 and Week 25 upper GI assessments Note: For any excisions at the week 13 endoscopy, the excised polyp burden was added back to the week 25 polyp burden before calculating the change from baseline.
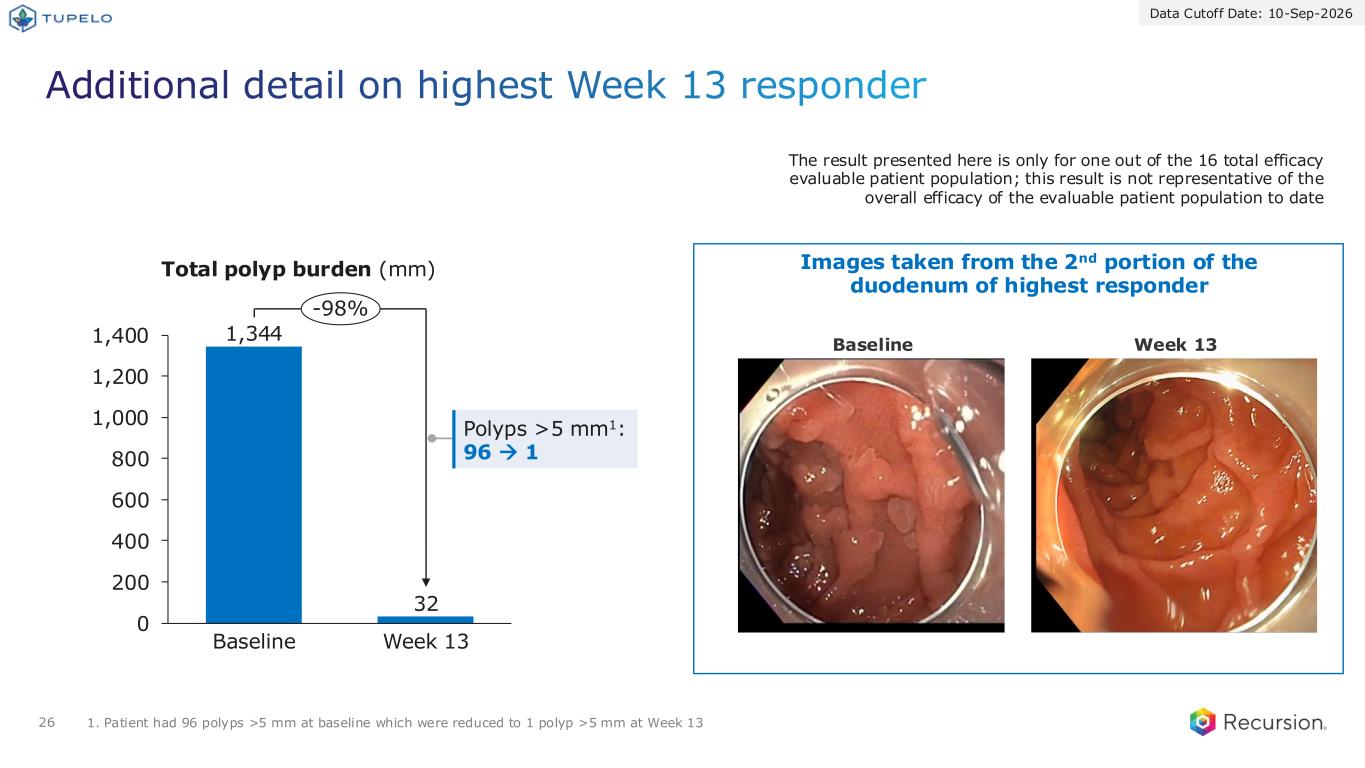
Additional detail on highest Week 13 responder Data Cutoff Date: 10-Sep-2026 26 The result presented here is only for one out of the 16 total efficacy evaluable patient population; this result is not representative of the overall efficacy of the evaluable patient population to date Images taken from the 2nd portion of the duodenum of highest responder Total polyp burden (mm) 1. Patient had 96 polyps >5 mm at baseline which were reduced to 1 polyp >5 mm at Week 13 Baseline Week 13 1,344 32 0 200 400 600 800 1,000 1,200 1,400 Baseline Week 13 -98% Polyps >5 mm1: 96 → 1
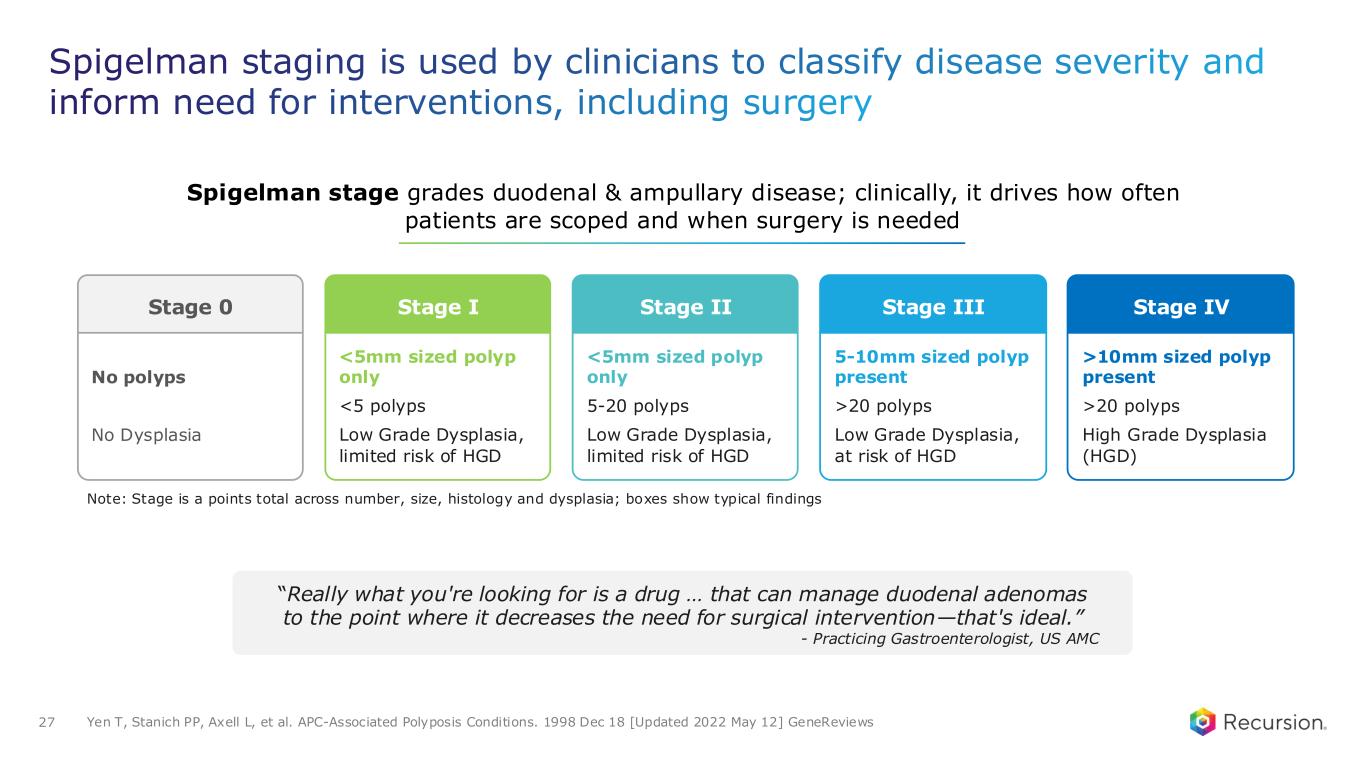
Spigelman staging is used by clinicians to classify disease severity and inform need for interventions, including surgery 27 “Really what you're looking for is a drug … that can manage duodenal adenomas to the point where it decreases the need for surgical intervention—that's ideal.” - Practicing Gastroenterologist, US AMC Spigelman stage grades duodenal & ampullary disease; clinically, it drives how often patients are scoped and when surgery is needed >10mm sized polyp present >20 polyps High Grade Dysplasia (HGD) Stage IV 5-10mm sized polyp present >20 polyps Low Grade Dysplasia, at risk of HGD Stage III <5mm sized polyp only 5-20 polyps Low Grade Dysplasia, limited risk of HGD Stage II <5mm sized polyp only <5 polyps Low Grade Dysplasia, limited risk of HGD Stage I Yen T, Stanich PP, Axell L, et al. APC-Associated Polyposis Conditions. 1998 Dec 18 [Updated 2022 May 12] GeneReviews No polyps No Dysplasia Stage 0 Note: Stage is a points total across number, size, histology and dysplasia; boxes show typical findings
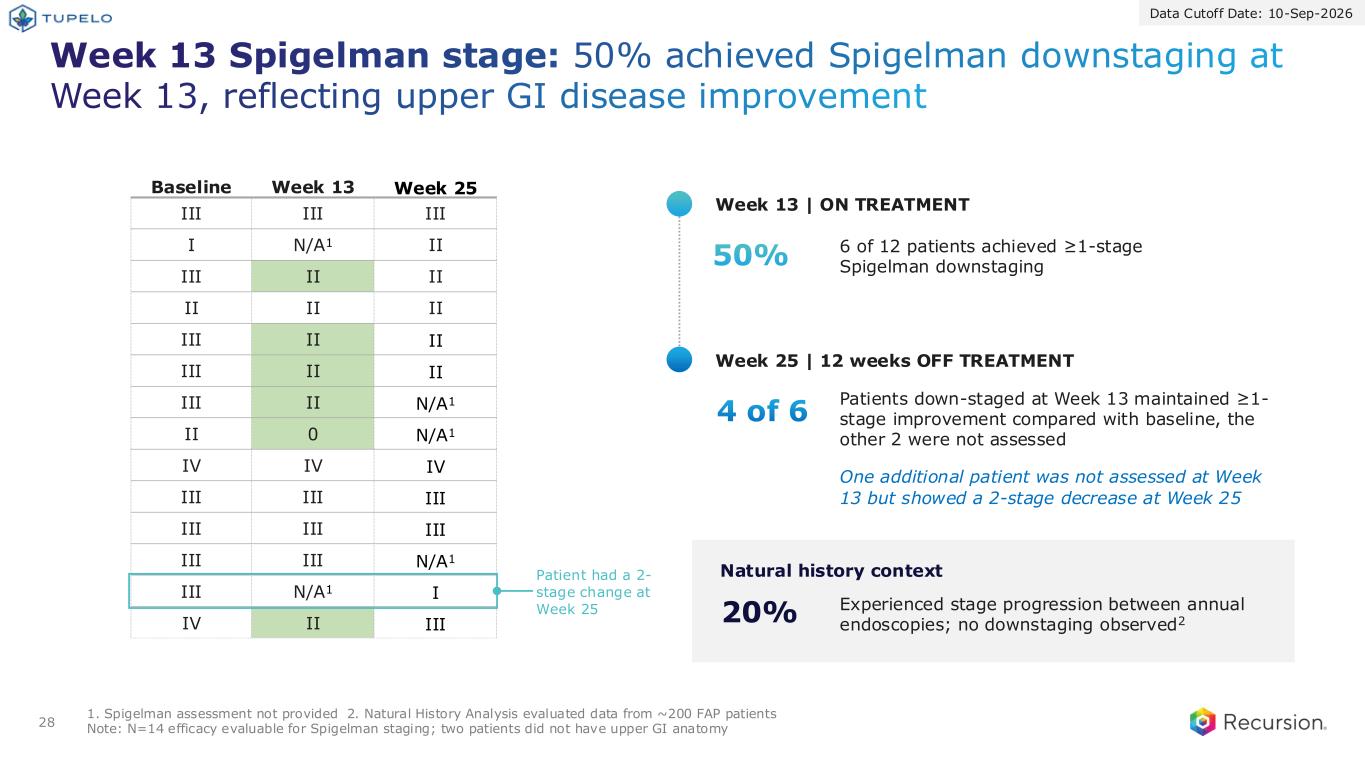
Week 13 Spigelman stage: 50% achieved Spigelman downstaging at Week 13, reflecting upper GI disease improvement 28 1. Spigelman assessment not provided 2. Natural History Analysis evaluated data from ~200 FAP patients Note: N=14 efficacy evaluable for Spigelman staging; two patients did not have upper GI anatomy 50% 4 of 6 Baseline Week 13 Week 25 III III III I N/A1 II III II II II II II III II II III II II III II N/A1 II 0 N/A1 IV IV IV III III III III III III III III N/A1 III N/A1 I IV II III 6 of 12 patients achieved ≥1-stage Spigelman downstaging Patients down-staged at Week 13 maintained ≥1- stage improvement compared with baseline, the other 2 were not assessed One additional patient was not assessed at Week 13 but showed a 2-stage decrease at Week 25 20% Experienced stage progression between annual endoscopies; no downstaging observed2 Patient had a 2- stage change at Week 25 Week 13 | ON TREATMENT Week 25 | 12 weeks OFF TREATMENT Natural history context Data Cutoff Date: 10-Sep-2026
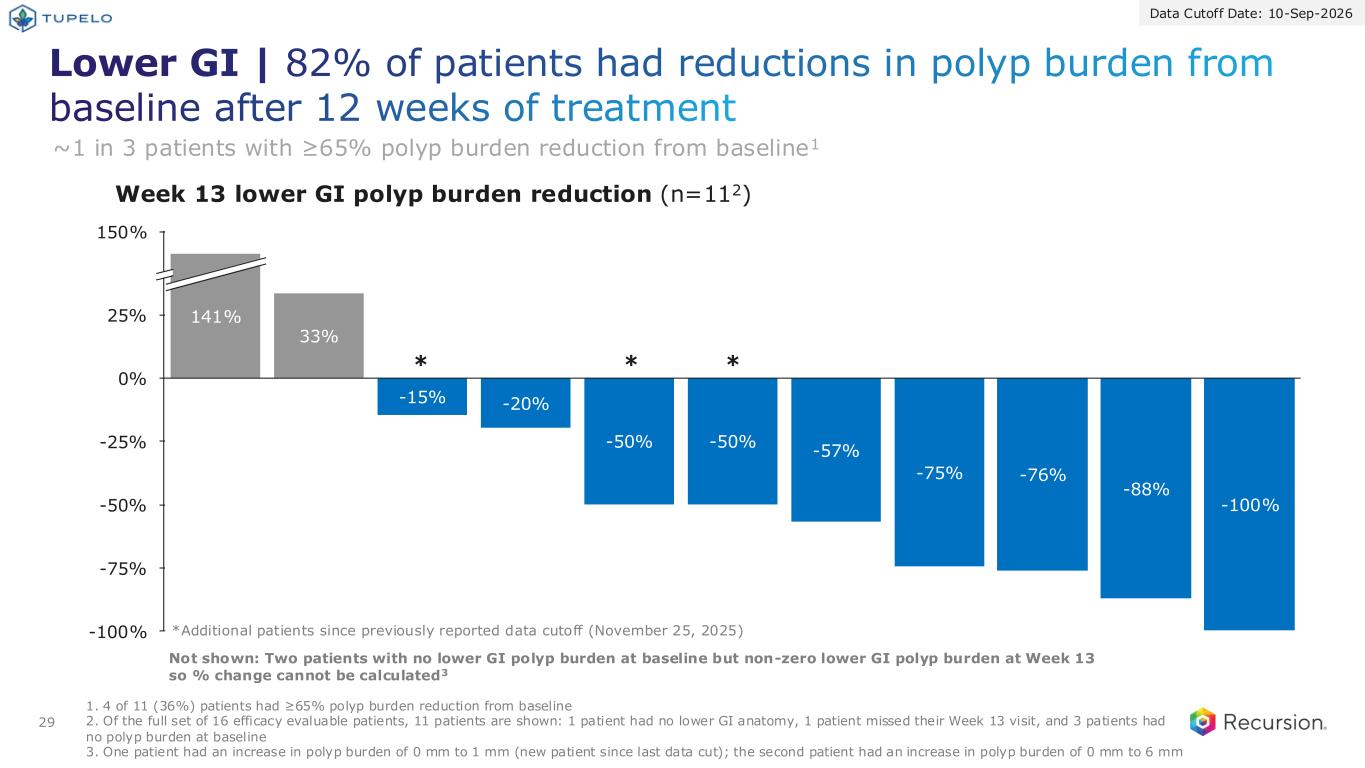
Lower GI | 82% of patients had reductions in polyp burden from baseline after 12 weeks of treatment 29 33% -15% -20% -50% -50% -57% -75% -76% -88% -100% -100% -75% -50% -25% 0% 25% 150% 141% *Additional patients since previously reported data cutoff (November 25, 2025) * ** 1. 4 of 11 (36%) patients had ≥65% polyp burden reduction from baseline 2. Of the full set of 16 efficacy evaluable patients, 11 patients are shown: 1 patient had no lower GI anatomy, 1 patient missed their Week 13 visit, and 3 patients had no polyp burden at baseline 3. One patient had an increase in polyp burden of 0 mm to 1 mm (new patient since last data cut); the second patient had an increase in polyp burden of 0 mm to 6 mm Week 13 lower GI polyp burden reduction (n=112) ~1 in 3 patients with ≥65% polyp burden reduction from baseline1 Data Cutoff Date: 10-Sep-2026 Not shown: Two patients with no lower GI polyp burden at baseline but non-zero lower GI polyp burden at Week 13 so % change cannot be calculated3
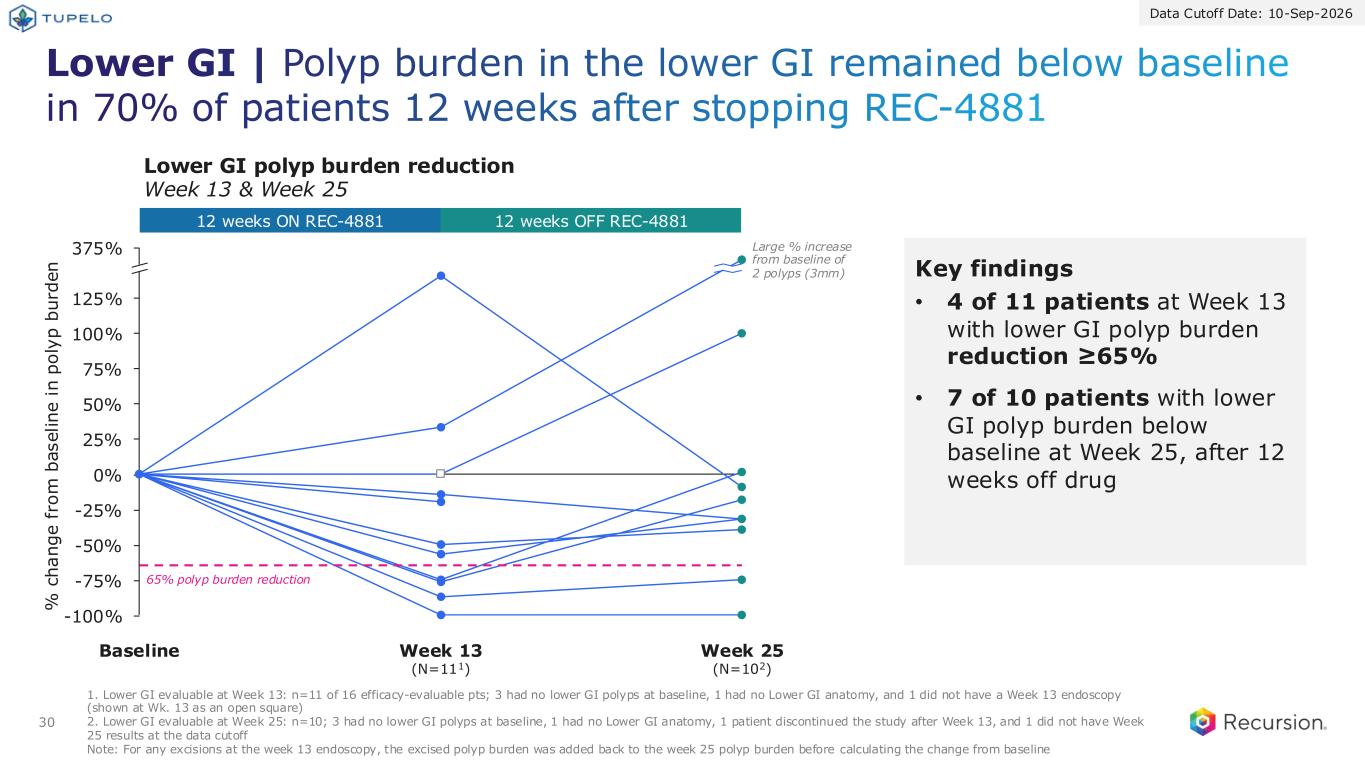
Lower GI | Polyp burden in the lower GI remained below baseline in 70% of patients 12 weeks after stopping REC-4881 30 12 weeks ON REC-4881 12 weeks OFF REC-4881 % c h a n g e f ro m b a s e li n e i n p o ly p b u rd e n Data Cutoff Date: 10-Sep-2026 65% polyp burden reduction 1. Lower GI evaluable at Week 13: n=11 of 16 efficacy-evaluable pts; 3 had no lower GI polyps at baseline, 1 had no Lower GI anatomy, and 1 did not have a Week 13 endoscopy (shown at Wk. 13 as an open square) 2. Lower GI evaluable at Week 25: n=10; 3 had no lower GI polyps at baseline, 1 had no Lower GI anatomy, 1 patient discontinued the study after Week 13, and 1 did not have Week 25 results at the data cutoff Note: For any excisions at the week 13 endoscopy, the excised polyp burden was added back to the week 25 polyp burden before calculating the change from baseline 100% 50% 75% 25% 0% -25% 125% -50% 375% -75% -100% Baseline Week 13 (N=111) Week 25 (N=102) Lower GI polyp burden reduction Week 13 & Week 25 Large % increase from baseline of 2 polyps (3mm) Key findings • 4 of 11 patients at Week 13 with lower GI polyp burden reduction ≥65% • 7 of 10 patients with lower GI polyp burden below baseline at Week 25, after 12 weeks off drug
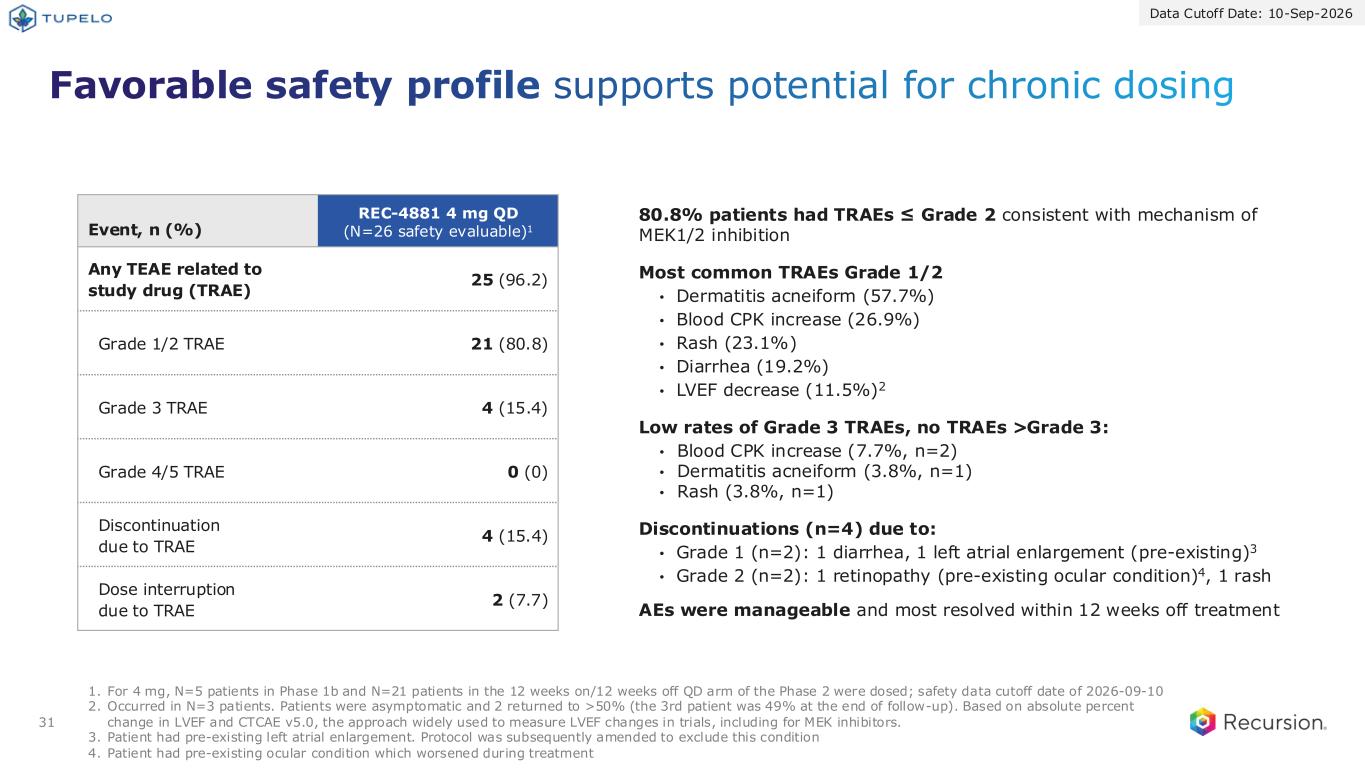
Favorable safety profile supports potential for chronic dosing 31 80.8% patients had TRAEs ≤ Grade 2 consistent with mechanism of MEK1/2 inhibition Most common TRAEs Grade 1/2 • Dermatitis acneiform (57.7%) • Blood CPK increase (26.9%) • Rash (23.1%) • Diarrhea (19.2%) • LVEF decrease (11.5%)2 Low rates of Grade 3 TRAEs, no TRAEs >Grade 3: • Blood CPK increase (7.7%, n=2) • Dermatitis acneiform (3.8%, n=1) • Rash (3.8%, n=1) Discontinuations (n=4) due to: • Grade 1 (n=2): 1 diarrhea, 1 left atrial enlargement (pre-existing)3 • Grade 2 (n=2): 1 retinopathy (pre-existing ocular condition)4, 1 rash AEs were manageable and most resolved within 12 weeks off treatment Event, n (%) REC-4881 4 mg QD (N=26 safety evaluable)1 Any TEAE related to study drug (TRAE) 25 (96.2) Grade 1/2 TRAE 21 (80.8) Grade 3 TRAE 4 (15.4) Grade 4/5 TRAE 0 (0) Discontinuation due to TRAE 4 (15.4) Dose interruption due to TRAE 2 (7.7) 1. For 4 mg, N=5 patients in Phase 1b and N=21 patients in the 12 weeks on/12 weeks off QD arm of the Phase 2 were dosed; safety data cutoff date of 2026-09-10 2. Occurred in N=3 patients. Patients were asymptomatic and 2 returned to >50% (the 3rd patient was 49% at the end of follow-up). Based on absolute percent change in LVEF and CTCAE v5.0, the approach widely used to measure LVEF changes in trials, including for MEK inhibitors. 3. Patient had pre-existing left atrial enlargement. Protocol was subsequently amended to exclude this condition 4. Patient had pre-existing ocular condition which worsened during treatment Data Cutoff Date: 10-Sep-2026
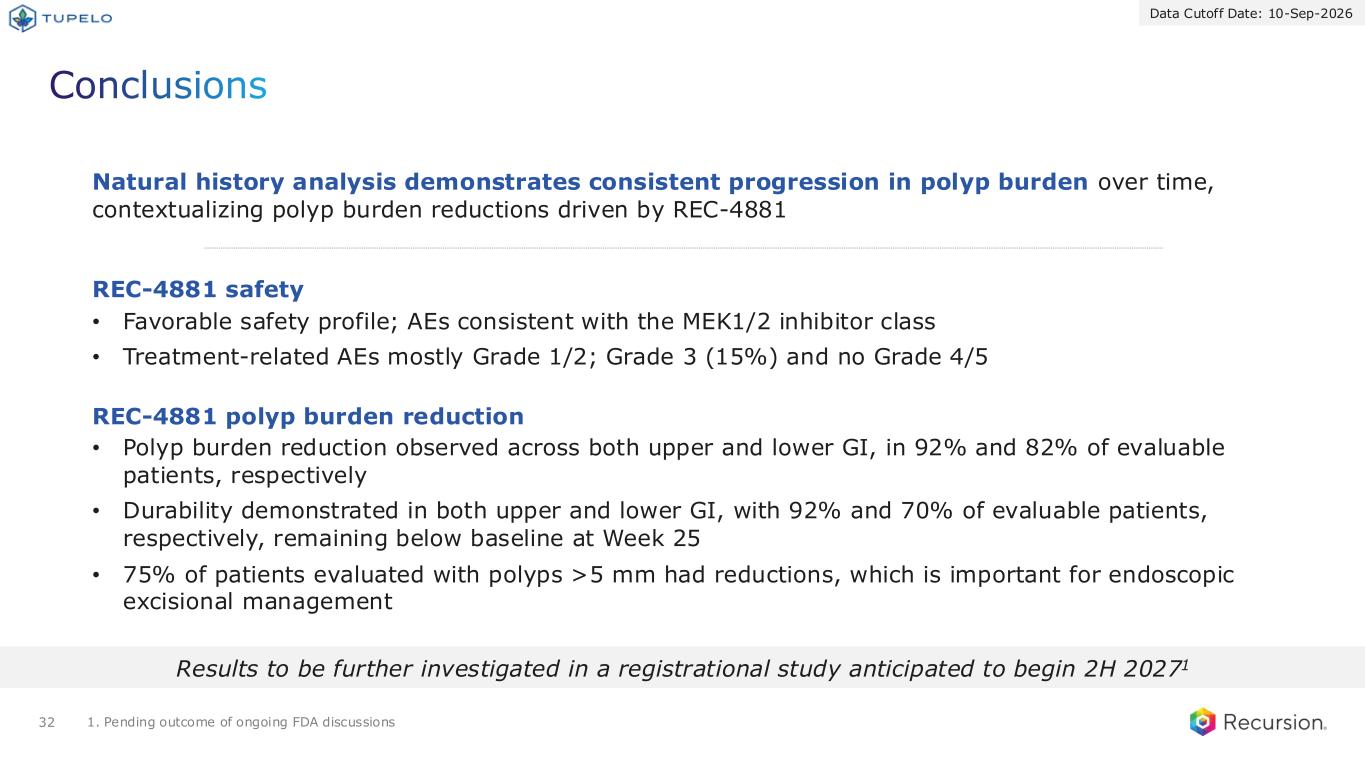
Conclusions 32 REC-4881 safety • Favorable safety profile; AEs consistent with the MEK1/2 inhibitor class • Treatment-related AEs mostly Grade 1/2; Grade 3 (15%) and no Grade 4/5 REC-4881 polyp burden reduction • Polyp burden reduction observed across both upper and lower GI, in 92% and 82% of evaluable patients, respectively • Durability demonstrated in both upper and lower GI, with 92% and 70% of evaluable patients, respectively, remaining below baseline at Week 25 • 75% of patients evaluated with polyps >5 mm had reductions, which is important for endoscopic excisional management Results to be further investigated in a registrational study anticipated to begin 2H 20271 1. Pending outcome of ongoing FDA discussions Natural history analysis demonstrates consistent progression in polyp burden over time, contextualizing polyp burden reductions driven by REC-4881 Data Cutoff Date: 10-Sep-2026
FAP Deep Dive Today’s news

KOL Panel: Today’s speakers Evelien Dekker, MD, PhD Head of Expert Clinic for Familial and Hereditary Polyposis and Colorectal Cancer, and Professor of Gastrointestinal Oncology, Amsterdam University Medical Center Bryson Katona, MD, PhD Director of GI Cancer Genetics Program, University of Pennsylvania Perelman School of Medicine • Practicing gastroenterologist specializing in gastrointestinal cancer genetics. • Research focuses on diagnosis, risk assessment, management, and biology of hereditary GI cancer predisposition syndromes. • Chair of the advisory board for the FAP research initiative. • TUPELO study investigator. • Practicing gastroenterologist and professor of gastrointestinal oncology. • Research focuses include quality and advanced techniques in colonoscopy, and endoscopic treatment modalities for gastrointestinal polyps and early colorectal cancer. • Specializes in colorectal cancer screening and surveillance, with an interest in various populations, including patients with FAP. • PI of Natural History Registry study, AUMC. 34
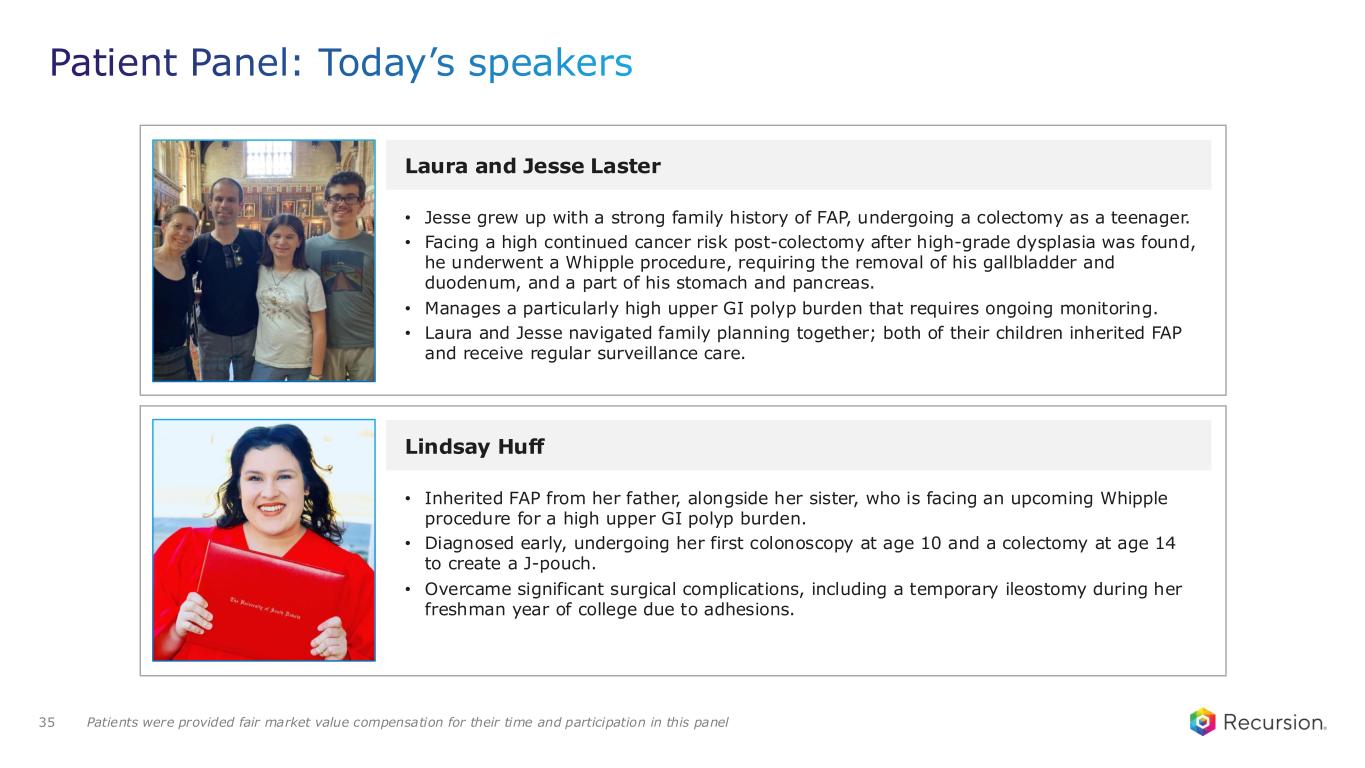
Patient Panel: Today’s speakers Laura and Jesse Laster Lindsay Huff • Inherited FAP from her father, alongside her sister, who is facing an upcoming Whipple procedure for a high upper GI polyp burden. • Diagnosed early, undergoing her first colonoscopy at age 10 and a colectomy at age 14 to create a J-pouch. • Overcame significant surgical complications, including a temporary ileostomy during her freshman year of college due to adhesions. • Jesse grew up with a strong family history of FAP, undergoing a colectomy as a teenager. • Facing a high continued cancer risk post-colectomy after high-grade dysplasia was found, he underwent a Whipple procedure, requiring the removal of his gallbladder and duodenum, and a part of his stomach and pancreas. • Manages a particularly high upper GI polyp burden that requires ongoing monitoring. • Laura and Jesse navigated family planning together; both of their children inherited FAP and receive regular surveillance care. Patients were provided fair market value compensation for their time and participation in this panel35

REC-1245 First-in-class RBM39 degrader Translating proof to products
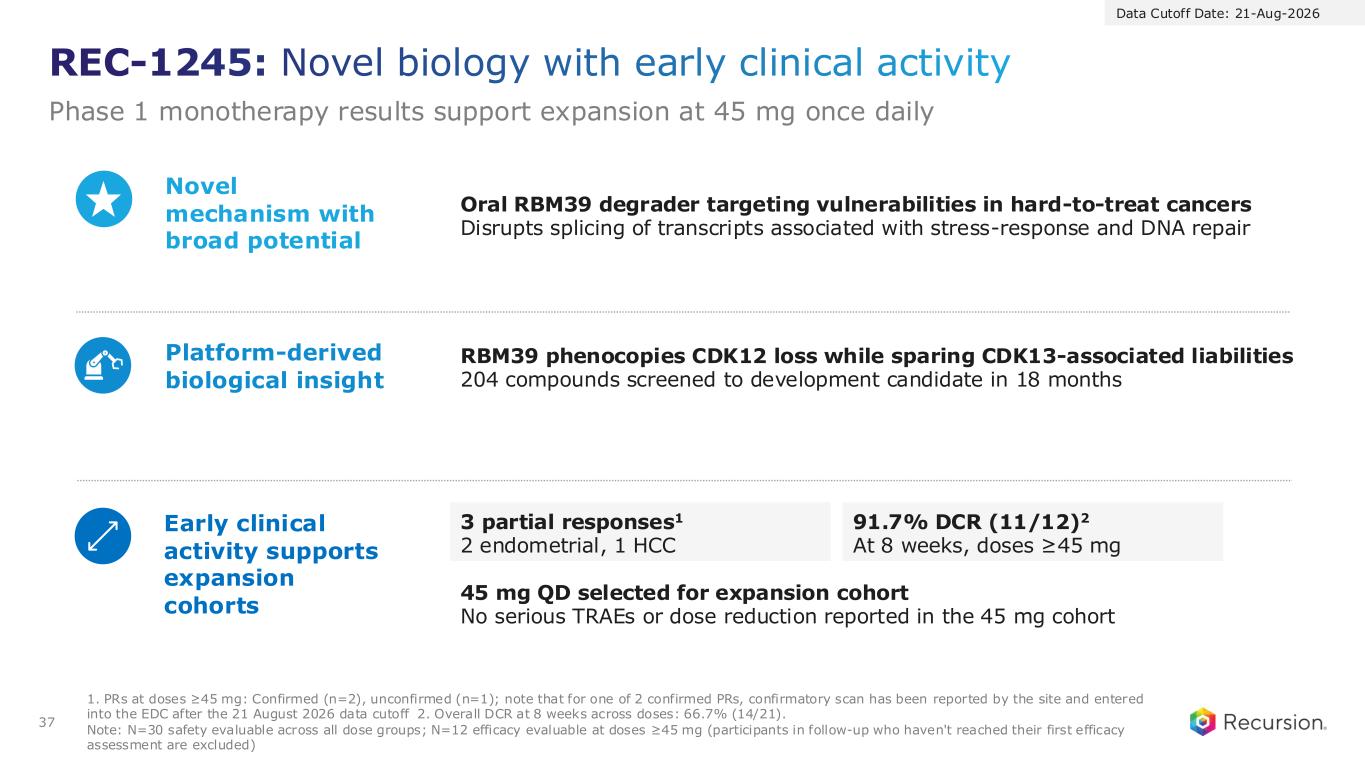
REC-1245: Novel biology with early clinical activity Phase 1 monotherapy results support expansion at 45 mg once daily 37 Oral RBM39 degrader targeting vulnerabilities in hard-to-treat cancers Disrupts splicing of transcripts associated with stress-response and DNA repair 3 partial responses1 2 endometrial, 1 HCC Novel mechanism with broad potential Platform-derived biological insight Early clinical activity supports expansion cohorts 1. PRs at doses ≥45 mg: Confirmed (n=2), unconfirmed (n=1); note that for one of 2 confirmed PRs, confirmatory scan has been reported by the site and entered into the EDC after the 21 August 2026 data cutoff 2. Overall DCR at 8 weeks across doses: 66.7% (14/21). Note: N=30 safety evaluable across all dose groups; N=12 efficacy evaluable at doses ≥45 mg (participants in follow-up who haven't reached their first efficacy assessment are excluded) 91.7% DCR (11/12)2 At 8 weeks, doses ≥45 mg 45 mg QD selected for expansion cohort No serious TRAEs or dose reduction reported in the 45 mg cohort Data Cutoff Date: 21-Aug-2026 RBM39 phenocopies CDK12 loss while sparing CDK13-associated liabilities 204 compounds screened to development candidate in 18 months
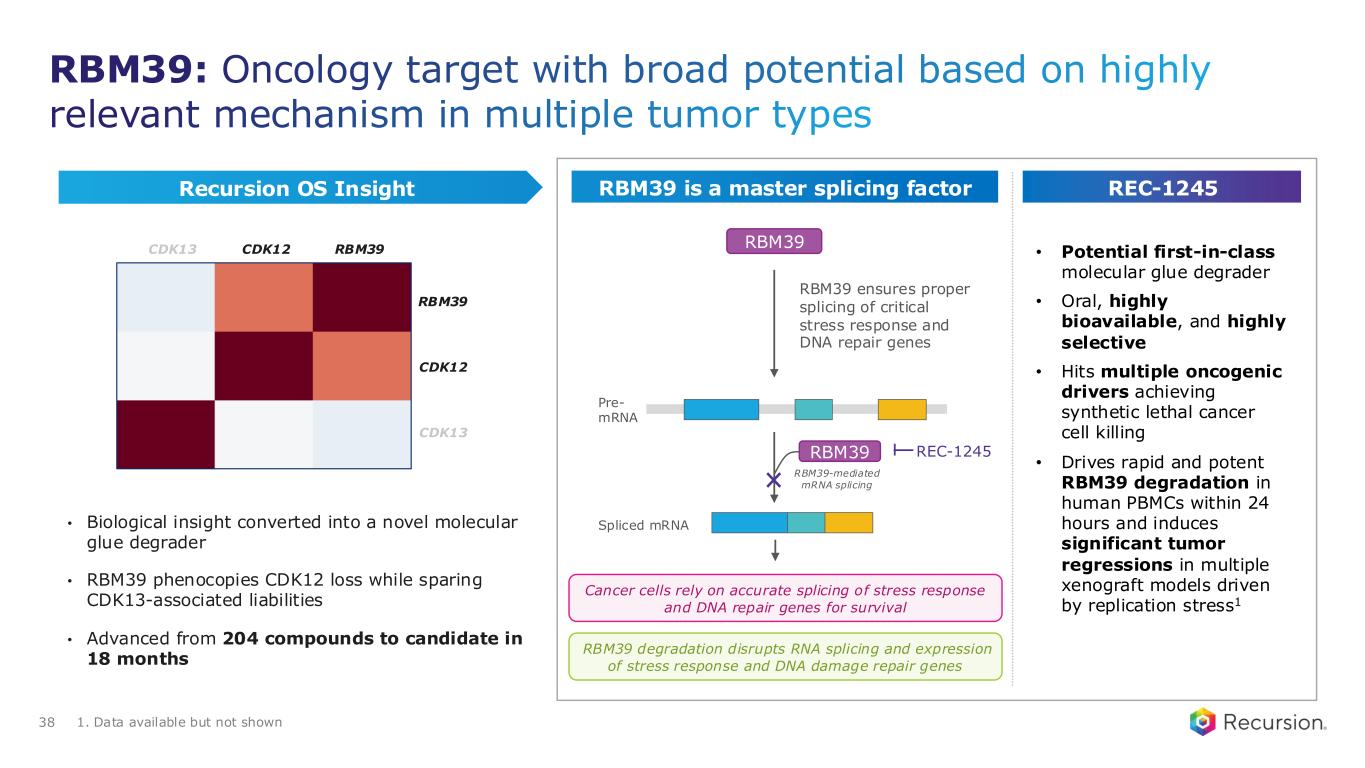
• Potential first-in-class molecular glue degrader • Oral, highly bioavailable, and highly selective • Hits multiple oncogenic drivers achieving synthetic lethal cancer cell killing • Drives rapid and potent RBM39 degradation in human PBMCs within 24 hours and induces significant tumor regressions in multiple xenograft models driven by replication stress1 RBM39 Pre- mRNA RBM39-mediated mRNA splicing Spliced mRNA Cancer cells rely on accurate splicing of stress response and DNA repair genes for survival RBM39 ensures proper splicing of critical stress response and DNA repair genes RBM39 RBM39: Oncology target with broad potential based on highly relevant mechanism in multiple tumor types • Biological insight converted into a novel molecular glue degrader • RBM39 phenocopies CDK12 loss while sparing CDK13-associated liabilities • Advanced from 204 compounds to candidate in 18 months 38 Recursion OS Insight RBM39 is a master splicing factor REC-1245 RBM39 degradation disrupts RNA splicing and expression of stress response and DNA damage repair genes 1. Data available but not shown CDK12 RBM39CDK13 RBM39 CDK12 CDK13 REC-1245
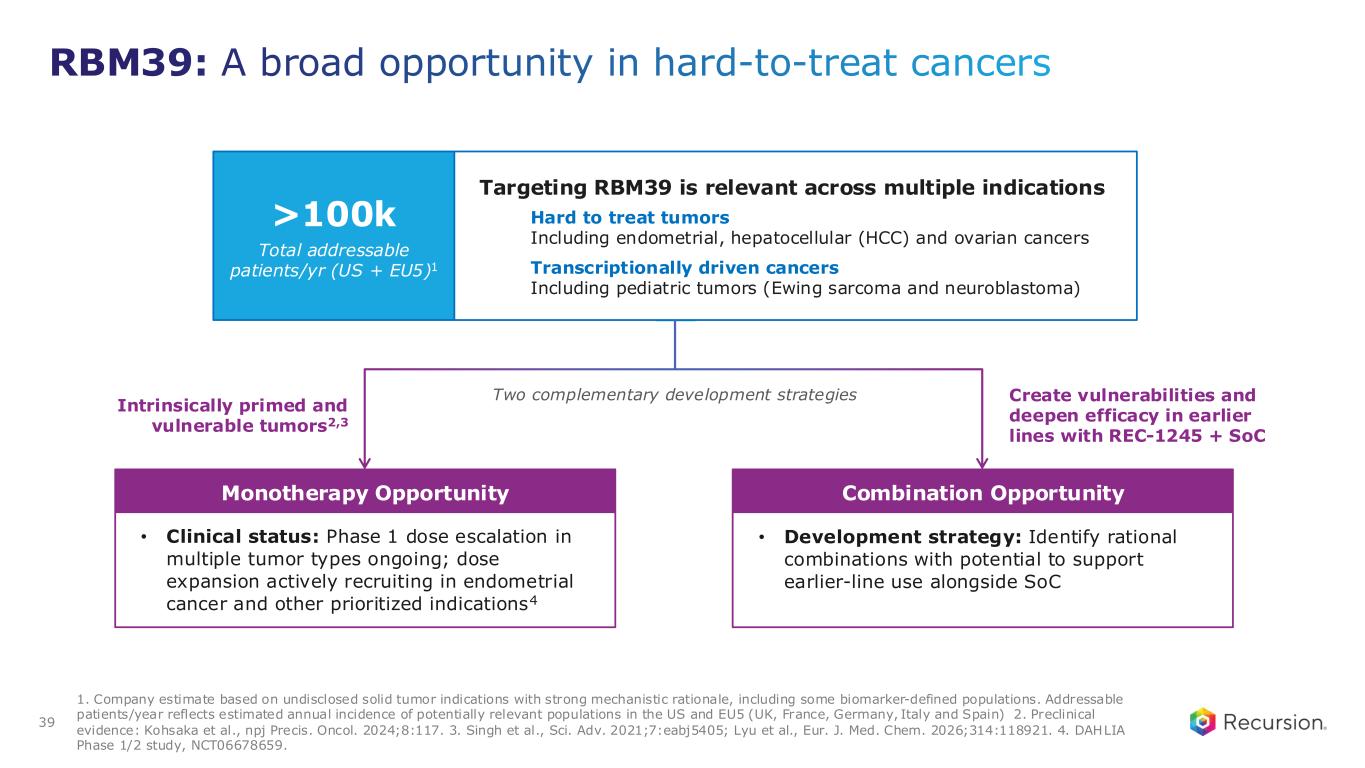
Monotherapy Opportunity Combination Opportunity RBM39: A broad opportunity in hard-to-treat cancers Targeting RBM39 is relevant across multiple indications Hard to treat tumors Including endometrial, hepatocellular (HCC) and ovarian cancers Transcriptionally driven cancers Including pediatric tumors (Ewing sarcoma and neuroblastoma) >100k Total addressable patients/yr (US + EU5)1 Two complementary development strategies Intrinsically primed and vulnerable tumors2,3 Create vulnerabilities and deepen efficacy in earlier lines with REC-1245 + SoC • Clinical status: Phase 1 dose escalation in multiple tumor types ongoing; dose expansion actively recruiting in endometrial cancer and other prioritized indications4 • Development strategy: Identify rational combinations with potential to support earlier-line use alongside SoC 1. Company estimate based on undisclosed solid tumor indications with strong mechanistic rationale, including some biomarker-defined populations. Addressable patients/year reflects estimated annual incidence of potentially relevant populations in the US and EU5 (UK, France, Germany, Italy and Spain) 2. Preclinical evidence: Kohsaka et al., npj Precis. Oncol. 2024;8:117. 3. Singh et al., Sci. Adv. 2021;7:eabj5405; Lyu et al., Eur. J. Med. Chem. 2026;314:118921. 4. DAHLIA Phase 1/2 study, NCT06678659. 39
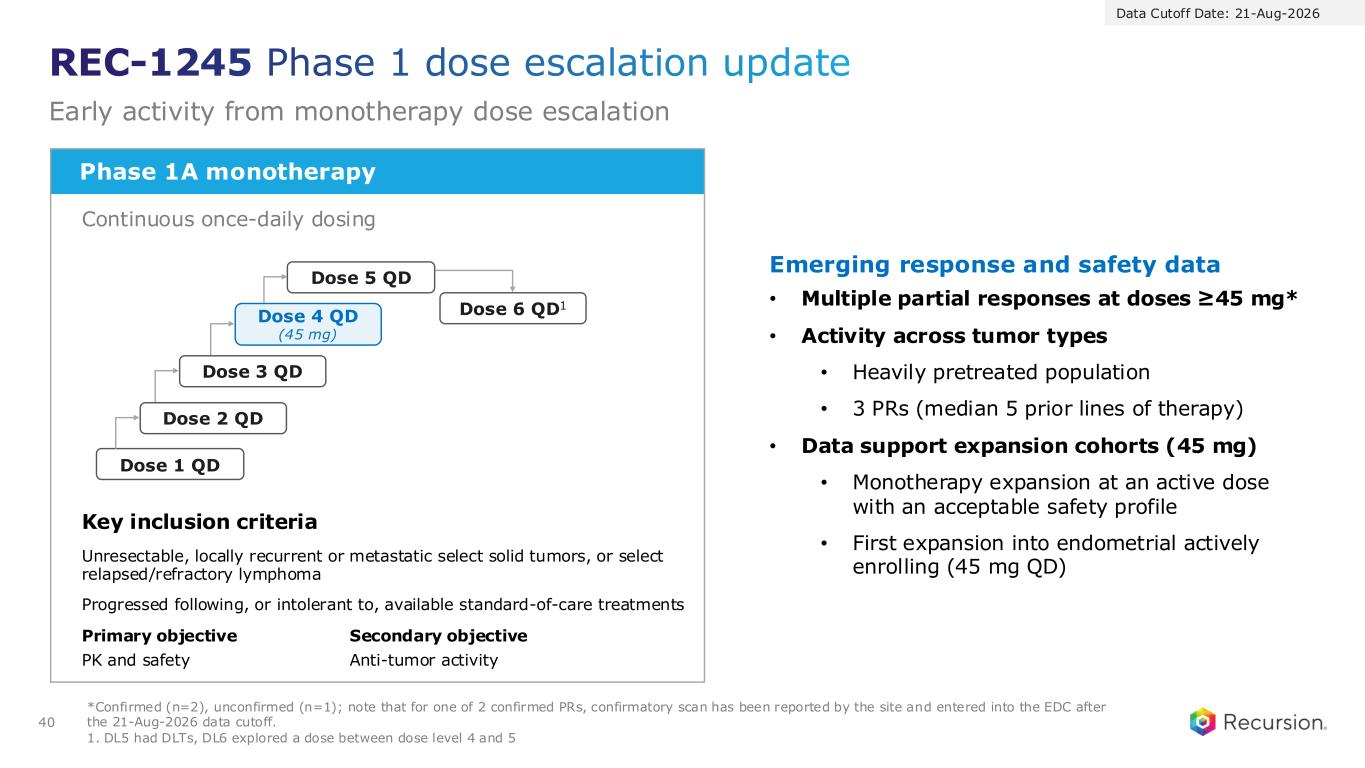
Phase 1A monotherapy Continuous once-daily dosing Key inclusion criteria Unresectable, locally recurrent or metastatic select solid tumors, or select relapsed/refractory lymphoma Progressed following, or intolerant to, available standard-of-care treatments Primary objective PK and safety Secondary objective Anti-tumor activity *Confirmed (n=2), unconfirmed (n=1); note that for one of 2 confirmed PRs, confirmatory scan has been reported by the site and entered into the EDC after the 21-Aug-2026 data cutoff. 1. DL5 had DLTs, DL6 explored a dose between dose level 4 and 5 REC-1245 Phase 1 dose escalation update Early activity from monotherapy dose escalation 40 Emerging response and safety data • Multiple partial responses at doses ≥45 mg* • Activity across tumor types • Heavily pretreated population • 3 PRs (median 5 prior lines of therapy) • Data support expansion cohorts (45 mg) • Monotherapy expansion at an active dose with an acceptable safety profile • First expansion into endometrial actively enrolling (45 mg QD) Dose 1 QD Dose 2 QD Dose 3 QD Dose 4 QD (45 mg) Dose 6 QD1 Dose 5 QD Data Cutoff Date: 21-Aug-2026
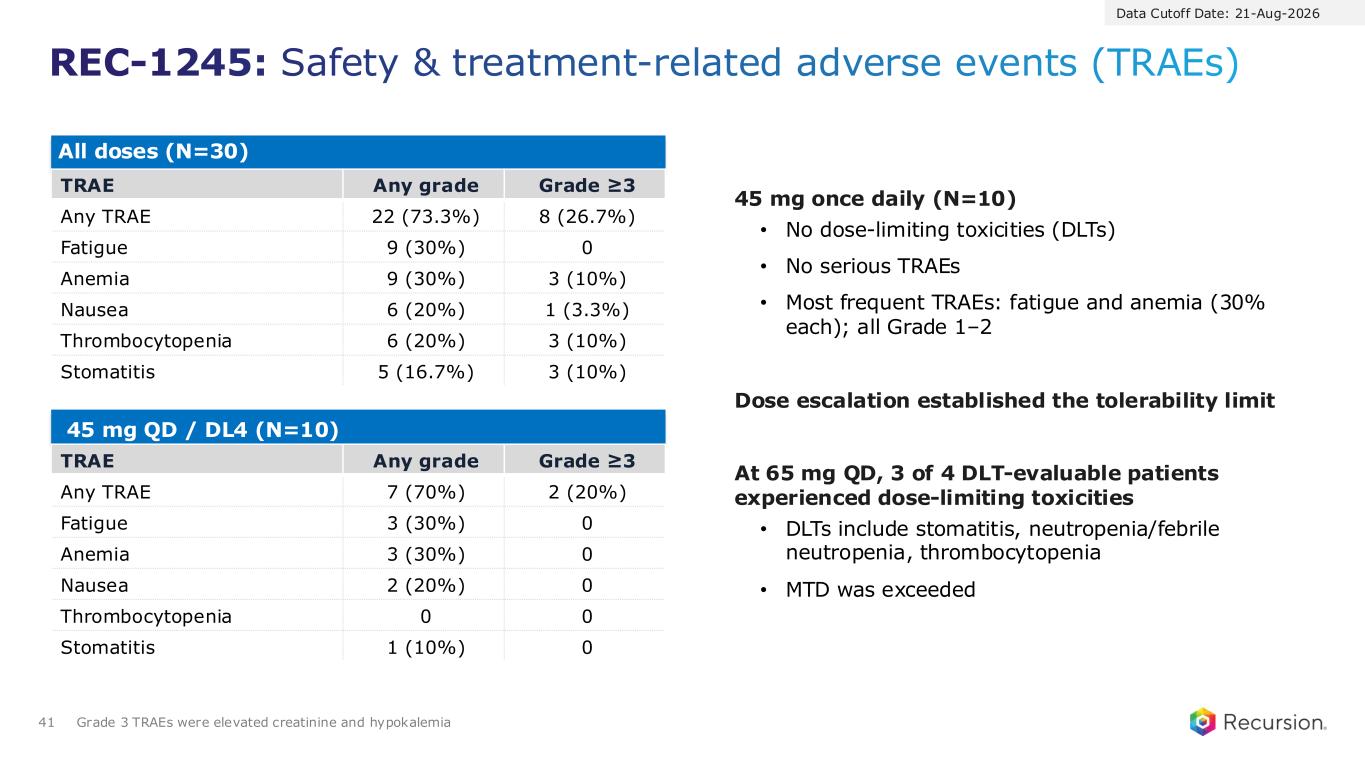
All doses (N=30) TRAE Any grade Grade ≥3 Any TRAE 22 (73.3%) 8 (26.7%) Fatigue 9 (30%) 0 Anemia 9 (30%) 3 (10%) Nausea 6 (20%) 1 (3.3%) Thrombocytopenia 6 (20%) 3 (10%) Stomatitis 5 (16.7%) 3 (10%) 45 mg QD / DL4 (N=10) TRAE Any grade Grade ≥3 Any TRAE 7 (70%) 2 (20%) Fatigue 3 (30%) 0 Anemia 3 (30%) 0 Nausea 2 (20%) 0 Thrombocytopenia 0 0 Stomatitis 1 (10%) 0 REC-1245: Safety & treatment-related adverse events (TRAEs) 41 Grade 3 TRAEs were elevated creatinine and hypokalemia 45 mg once daily (N=10) • No dose-limiting toxicities (DLTs) • No serious TRAEs • Most frequent TRAEs: fatigue and anemia (30% each); all Grade 1–2 Dose escalation established the tolerability limit At 65 mg QD, 3 of 4 DLT-evaluable patients experienced dose-limiting toxicities • DLTs include stomatitis, neutropenia/febrile neutropenia, thrombocytopenia • MTD was exceeded Data Cutoff Date: 21-Aug-2026
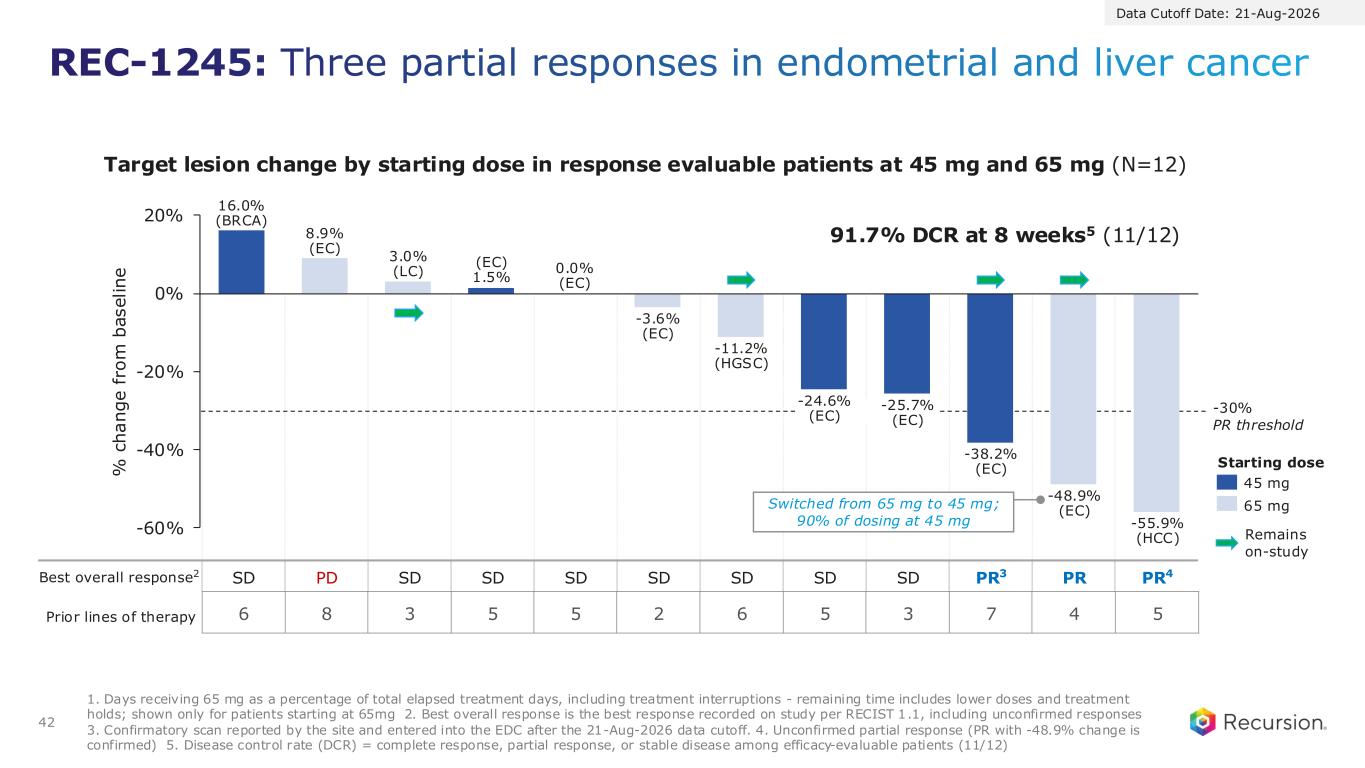
Best overall response2 SD PD SD SD SD SD SD SD SD PR3 PR PR4 REC-1245: Three partial responses in endometrial and liver cancer 42 -60% -40% -20% 0% 20% 16.0% (BRCA) 8.9% (EC) 3.0% (LC) (EC) 1.5% 0.0% (EC) -3.6% (EC) -11.2% (HGSC) -24.6% (EC) -25.7% (EC) -38.2% (EC) -48.9% (EC) -55.9% (HCC) 45 mg 65 mg % c h a n g e f ro m b a s e li n e Remains on-study Target lesion change by starting dose in response evaluable patients at 45 mg and 65 mg (N=12) -30% PR threshold 1. Days receiving 65 mg as a percentage of total elapsed treatment days, including treatment interruptions - remaining time includes lower doses and treatment holds; shown only for patients starting at 65mg 2. Best overall response is the best response recorded on study per RECIST 1.1, including unconfirmed responses 3. Confirmatory scan reported by the site and entered into the EDC after the 21-Aug-2026 data cutoff. 4. Unconfirmed partial response (PR with -48.9% change is confirmed) 5. Disease control rate (DCR) = complete response, partial response, or stable disease among efficacy-evaluable patients (11/12) 91.7% DCR at 8 weeks5 (11/12) Switched from 65 mg to 45 mg; 90% of dosing at 45 mg Starting dose 6 8 3 5 5 2 6 5 3 7 4 5Prior lines of therapy Data Cutoff Date: 21-Aug-2026
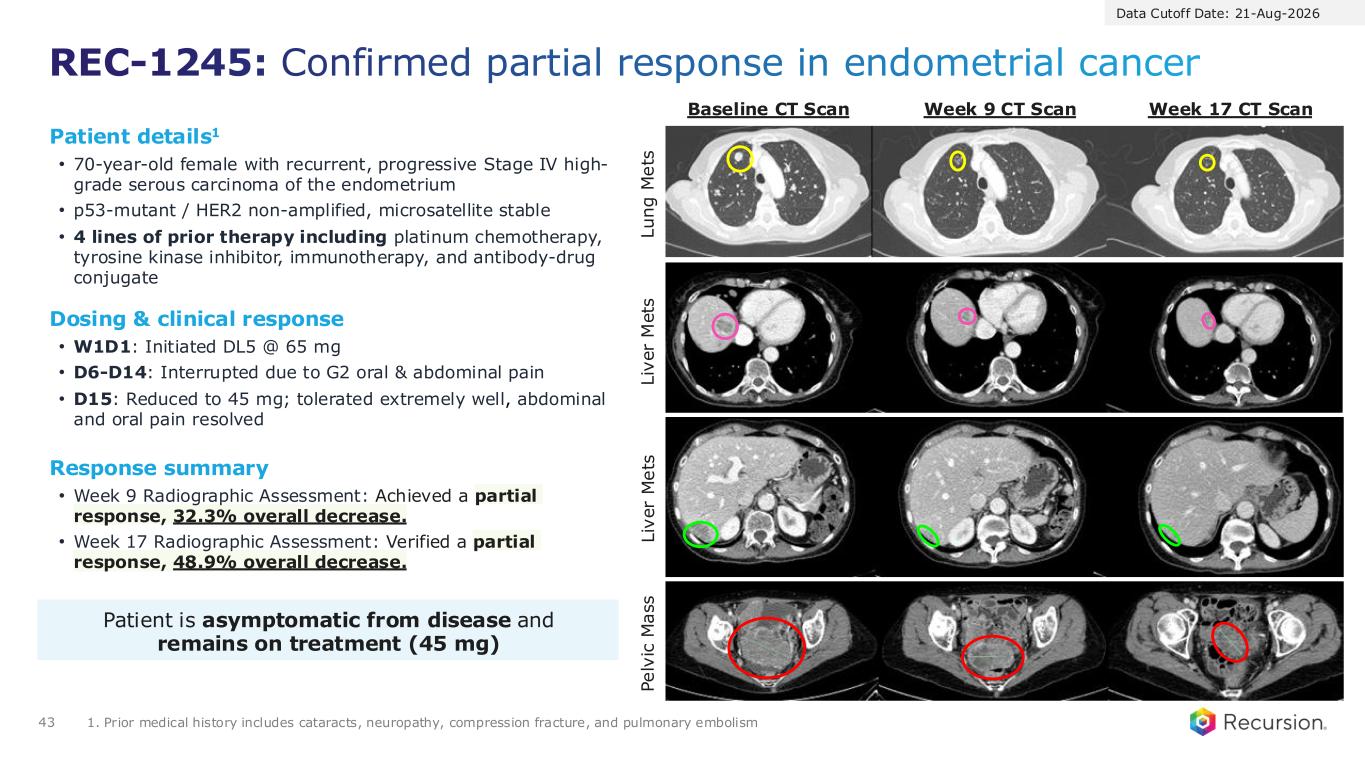
REC-1245: Confirmed partial response in endometrial cancer 43 1. Prior medical history includes cataracts, neuropathy, compression fracture, and pulmonary embolism Response summary • Week 9 Radiographic Assessment: Achieved a partial response, 32.3% overall decrease. • Week 17 Radiographic Assessment: Verified a partial response, 48.9% overall decrease. Patient details1 • 70-year-old female with recurrent, progressive Stage IV high- grade serous carcinoma of the endometrium • p53-mutant / HER2 non-amplified, microsatellite stable • 4 lines of prior therapy including platinum chemotherapy, tyrosine kinase inhibitor, immunotherapy, and antibody-drug conjugate Dosing & clinical response • W1D1: Initiated DL5 @ 65 mg • D6-D14: Interrupted due to G2 oral & abdominal pain • D15: Reduced to 45 mg; tolerated extremely well, abdominal and oral pain resolved Patient is asymptomatic from disease and remains on treatment (45 mg) L iv e r M e ts P e lv ic M a s s L u n g M e ts L iv e r M e ts Baseline CT Scan Week 9 CT Scan Week 17 CT Scan Data Cutoff Date: 21-Aug-2026
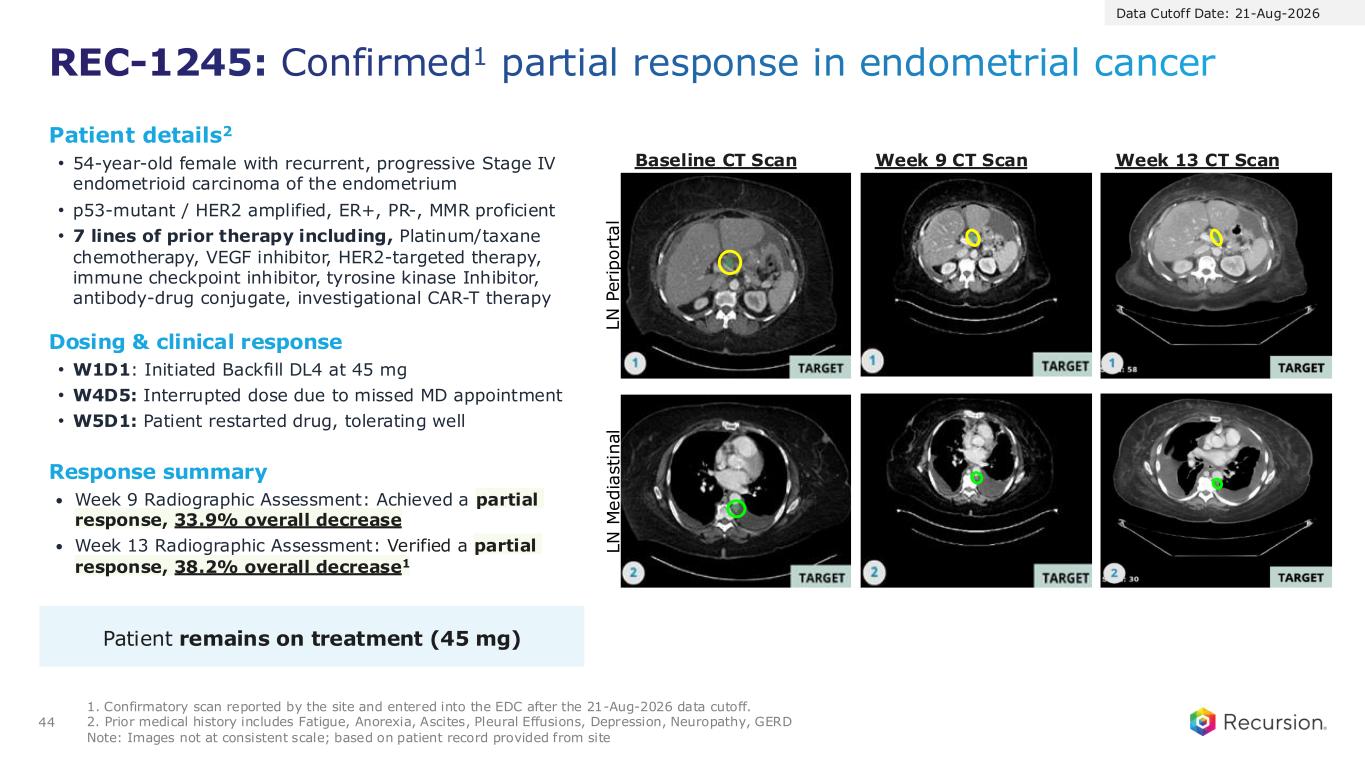
REC-1245: Confirmed1 partial response in endometrial cancer 44 1. Confirmatory scan reported by the site and entered into the EDC after the 21-Aug-2026 data cutoff. 2. Prior medical history includes Fatigue, Anorexia, Ascites, Pleural Effusions, Depression, Neuropathy, GERD Note: Images not at consistent scale; based on patient record provided from site Response summary • Week 9 Radiographic Assessment: Achieved a partial response, 33.9% overall decrease • Week 13 Radiographic Assessment: Verified a partial response, 38.2% overall decrease1 Patient details2 • 54-year-old female with recurrent, progressive Stage IV endometrioid carcinoma of the endometrium • p53-mutant / HER2 amplified, ER+, PR-, MMR proficient • 7 lines of prior therapy including, Platinum/taxane chemotherapy, VEGF inhibitor, HER2-targeted therapy, immune checkpoint inhibitor, tyrosine kinase Inhibitor, antibody-drug conjugate, investigational CAR-T therapy Dosing & clinical response • W1D1: Initiated Backfill DL4 at 45 mg • W4D5: Interrupted dose due to missed MD appointment • W5D1: Patient restarted drug, tolerating well Patient remains on treatment (45 mg) L N P e ri p o rt a l L N M e d ia s ti n a l Baseline CT Scan Week 9 CT Scan Week 13 CT Scan Data Cutoff Date: 21-Aug-2026
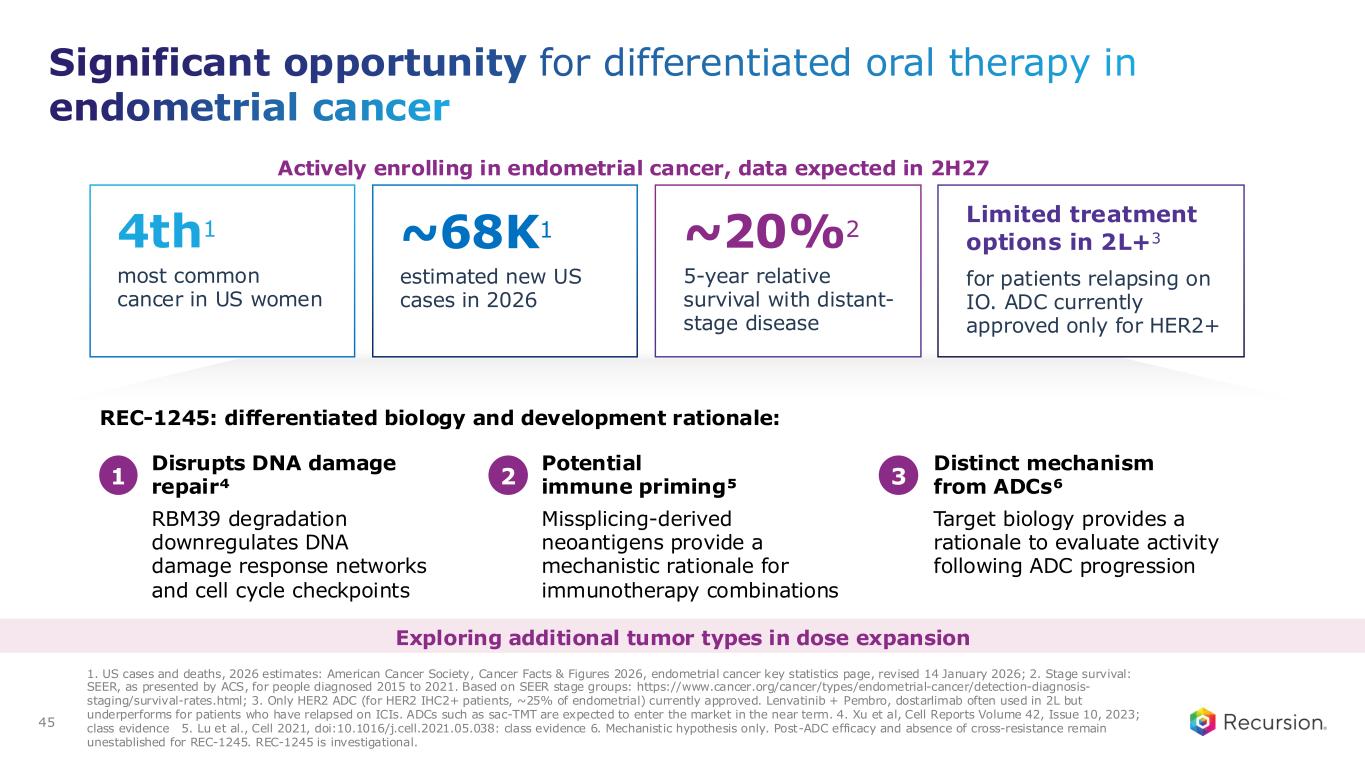
most common cancer in US women REC-1245: differentiated biology and development rationale: Disrupts DNA damage repair⁴ Potential immune priming⁵ Distinct mechanism from ADCs⁶ RBM39 degradation downregulates DNA damage response networks and cell cycle checkpoints Missplicing-derived neoantigens provide a mechanistic rationale for immunotherapy combinations Target biology provides a rationale to evaluate activity following ADC progression 1. US cases and deaths, 2026 estimates: American Cancer Society, Cancer Facts & Figures 2026, endometrial cancer key statistics page, revised 14 January 2026; 2. Stage survival: SEER, as presented by ACS, for people diagnosed 2015 to 2021. Based on SEER stage groups: https://www.cancer.org/cancer/types/endometrial-cancer/detection-diagnosis- staging/survival-rates.html; 3. Only HER2 ADC (for HER2 IHC2+ patients, ~25% of endometrial) currently approved. Lenvatinib + Pembro, dostarlimab often used in 2L but underperforms for patients who have relapsed on ICIs. ADCs such as sac-TMT are expected to enter the market in the near term. 4. Xu et al, Cell Reports Volume 42, Issue 10, 2023; class evidence 5. Lu et al., Cell 2021, doi:10.1016/j.cell.2021.05.038: class evidence 6. Mechanistic hypothesis only. Post-ADC efficacy and absence of cross-resistance remain unestablished for REC-1245. REC-1245 is investigational. Significant opportunity for differentiated oral therapy in endometrial cancer 45 4th1 estimated new US cases in 2026 ~68K1 5-year relative survival with distant- stage disease ~20%2 for patients relapsing on IO. ADC currently approved only for HER2+ Limited treatment options in 2L+3 1 2 3 Actively enrolling in endometrial cancer, data expected in 2H27 Exploring additional tumor types in dose expansion

Financials & Looking ahead
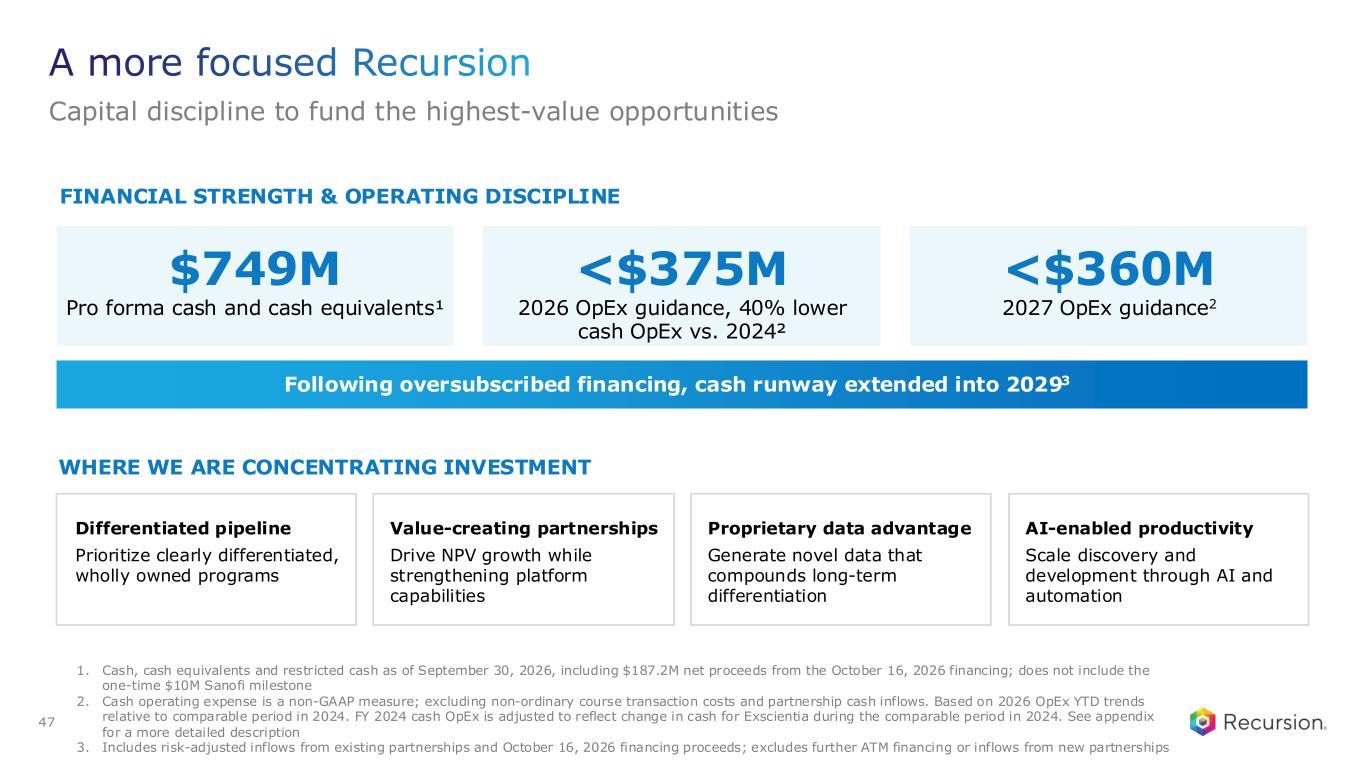
FINANCIAL STRENGTH & OPERATING DISCIPLINE $749M Pro forma cash and cash equivalents¹ <$375M 2026 OpEx guidance, 40% lower cash OpEx vs. 2024² Following oversubscribed financing, cash runway extended into 20293 WHERE WE ARE CONCENTRATING INVESTMENT Differentiated pipeline Prioritize clearly differentiated, wholly owned programs Value-creating partnerships Drive NPV growth while strengthening platform capabilities Proprietary data advantage Generate novel data that compounds long-term differentiation AI-enabled productivity Scale discovery and development through AI and automation A more focused Recursion Capital discipline to fund the highest-value opportunities 47 1. Cash, cash equivalents and restricted cash as of September 30, 2026, including $187.2M net proceeds from the October 16, 2026 financing; does not include the one-time $10M Sanofi milestone 2. Cash operating expense is a non-GAAP measure; excluding non-ordinary course transaction costs and partnership cash inflows. Based on 2026 OpEx YTD trends relative to comparable period in 2024. FY 2024 cash OpEx is adjusted to reflect change in cash for Exscientia during the comparable period in 2024. See appendix for a more detailed description 3. Includes risk-adjusted inflows from existing partnerships and October 16, 2026 financing proceeds; excludes further ATM financing or inflows from new partnerships <$360M 2027 OpEx guidance2
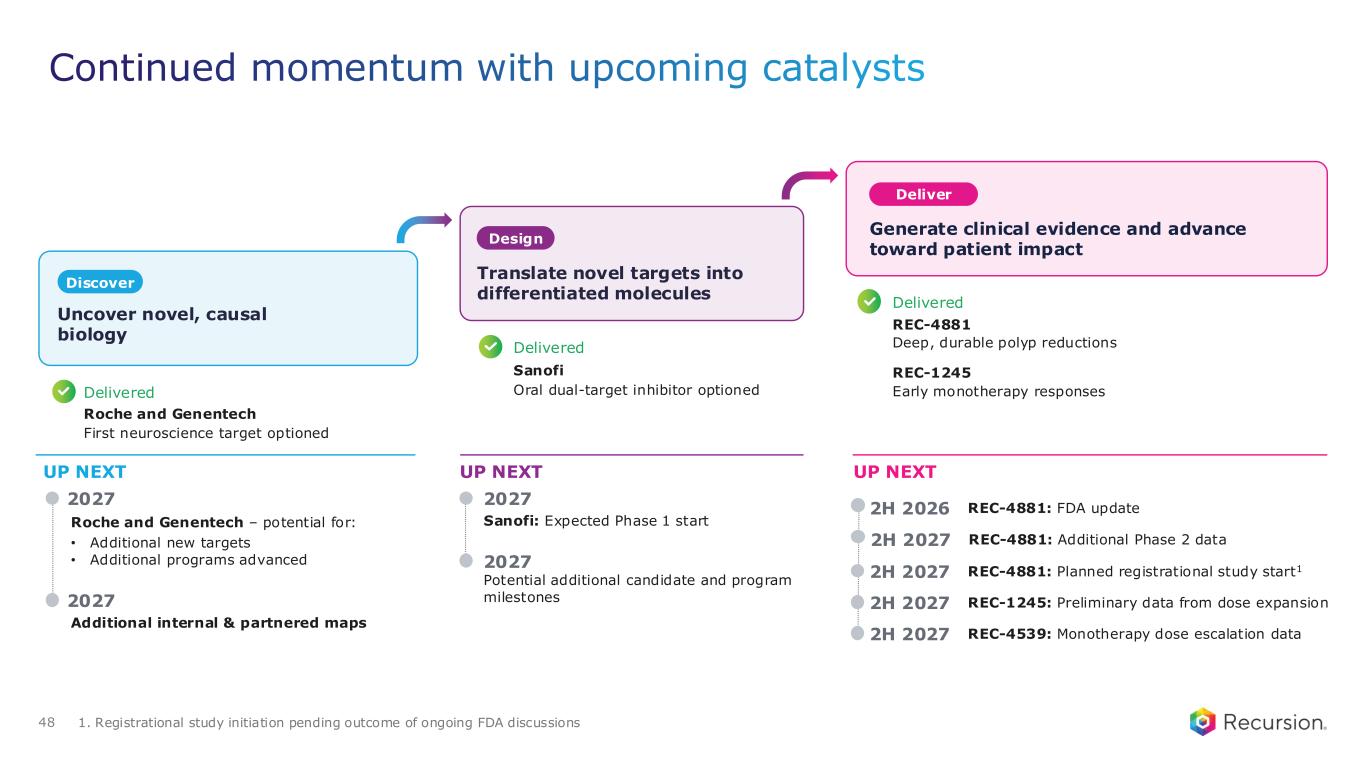
Sanofi: Expected Phase 1 start Continued momentum with upcoming catalysts 1. Registrational study initiation pending outcome of ongoing FDA discussions UP NEXT UP NEXT UP NEXT 2027 2027 2027 Potential additional candidate and program milestones 2H 2026 REC-4881: FDA update 2H 2027 REC-4881: Additional Phase 2 data 2H 2027 REC-4881: Planned registrational study start1 2H 2027 REC-1245: Preliminary data from dose expansion 2H 2027 REC-4539: Monotherapy dose escalation data Delivered Roche and Genentech First neuroscience target optioned Delivered Sanofi Oral dual-target inhibitor optioned Delivered REC-4881 Deep, durable polyp reductions REC-1245 Early monotherapy responses Uncover novel, causal biology Discover Design Translate novel targets into differentiated molecules Deliver Generate clinical evidence and advance toward patient impact Roche and Genentech – potential for: • Additional new targets • Additional programs advanced Additional internal & partnered maps 2027 48

49

50 THANK YOU


Non-GAAP Financial Measures To supplement our financial statements prepared in accordance with U.S. GAAP, we monitor and consider operating cash expense, which is a non-GAAP financial measure. We define operating cash expense as the net cash used in operating activities, excluding non-ordinary course transaction costs and partnership cash inflows. This non-GAAP financial measure is not based on any standardized methodology prescribed by U.S. GAAP and is not necessarily comparable to similarly- titled measures presented by other companies. We believe operating cash expense to be a liquidity measure that provides useful information to management and investors about the amount of cash consumed by the operations of the business. A limitation of using this non-U.S. GAAP measure is that operating cash expense does not represent the total change in cash and cash equivalents for the period because it excludes cash provided by or used for other investing and financing activities. We account for this limitation by providing information about our capital expenditures and other investing and financing activities in the statements of cash flows in our financial statements. Additionally, we reconciled operating cash expense to net cash used in operating activities, the most directly comparable U.S. GAAP financial measure. In addition, it is important to note that other companies, including companies in our industry, may not use operating cash expense, may calculate operating cash expense in a different manner than we do or may use other financial measures to evaluate their performance, all of which could reduce the usefulness of operating cash expense as a comparative measure. Because of these limitations, operating cash expense should not be considered in isolation from, or as a substitute for, financial information prepared in accordance with U.S. GAAP. Appendix 52