Exhibit 99.2
| EMPOWERING PATIENTS THROUGH THERAPEUTIC INNOVATION October 27, 2026 ATI-052 Phase 1b Primary Analysis Results Atopic Dermatitis and Asthma |
| 2 Any statements contained in this presentation that do not describe historical facts may constitute forward-looking statements as that term is defined in the Private Securities Litigation Reform Act of 1995. These statements may be identified by words such as “anticipate,” “believe,” “expect,” “intend,” “may,” “plan,” “potential,” “will,” and similar expressions, and are based on Aclaris’ current beliefs and expectations. These forward-looking statements include expectations regarding the therapeutic potential of ATI-052, an investigational bispecific antibody, including the potential for ATI-052 to be best-in-class and have best-in-class attributes, the potential to increase the efficacy ceiling and show superior activity compared to other therapies, the potential for ATI-052 to have up to quarterly dosing, the potential for synergy of TSLP and IL-4Rα, the market opportunity for ATI-052, and the development of ATI-052 and Aclaris’ other product candidates, including the potential targets and indications Aclaris may pursue, the timing and number of regulatory filings, the design of future clinical trials, the timing for the initiation of clinical trials, and the availability and timing of data from clinical trials. These statements involve risks and uncertainties that could cause actual results to differ materially from those reflected in such statements. Risks and uncertainties that may cause actual results to differ materially include uncertainties inherent in the conduct of clinical trials, potential changes to interim, topline and preliminary data as more subject data become available, Aclaris’ reliance on third parties over which it may not always have full control, Aclaris’ ability to enter into strategic partnerships on commercially reasonable terms, the uncertainty regarding the macroeconomic environment and other risks and uncertainties that are described in the “Risk Factors” section of Aclaris’ Annual Report on Form 10-K for the year ended December 31, 2025, and other filings Aclaris makes with the U.S. Securities and Exchange Commission from time to time. These documents are available under the “SEC Filings” page of the “Investors” section of Aclaris’ website at www.aclaristx.com. Any forward-looking statements speak only as of the date of this presentation and are based on information available to Aclaris as of the date of this presentation, and Aclaris assumes no obligation to, and does not intend to, update any forward-looking statements, whether as a result of new information, future events or otherwise. Tradenames, trademarks and service marks of other companies appearing in this presentation are the property of their respective owners. This presentation also contains estimates and other statistical data made by independent parties and by us relating to market size and other data about our industry. These data involve a number of assumptions and limitations, and you are cautioned not to give undue weight to such estimates. In addition, projections, assumptions and estimates of our future performance and the future performance of the markets in which we operate are necessarily subject to a high degree of uncertainty and risk. All future development, clinical, and regulatory timelines are expectations, are based on current beliefs and assumptions, and are subject to change based on a variety of factors. Disclaimer and Cautionary Note Regarding Forward-Looking Statements |

| 3 4x More potent than dupilumab + tezepelumab combined $19B+1 In annual sales across the mechanisms it targets ATI-052: Potential Best-in-Class Bispecific mAb Phase 1b POC Results Validate Preclinical Potency Differentiation OVERVIEW: PROOF-OF-CONCEPT RESULTS 400+ hours Up to 116x longer residence time on TSLP than comparator antibodies Combines two significant mechanisms in one molecule: anti-TSLP, anti-IL-4Rα Demonstrated potential for additivity/synergy of targets Proof-of-Concept Achieved in Atopic Dermatitis (AD) & Asthma Modulated all three TH cell endotypes: Th1, Th2, Th17 Potential to raise efficacy ceiling + provide rapid response Favorable tolerability profile observed Up to Quarterly Dosing potential 1. Regeneron Pharmaceuticals, Q4 and Full Year 2025 Financial and Operating Results, Jan. 30, 2026 (FY’25 Dupixent® annual sales) and AstraZeneca, Full Year and Q4 2025 Results, Feb. 10, 2026 (FY‘25 Tezspire® annual sales). |

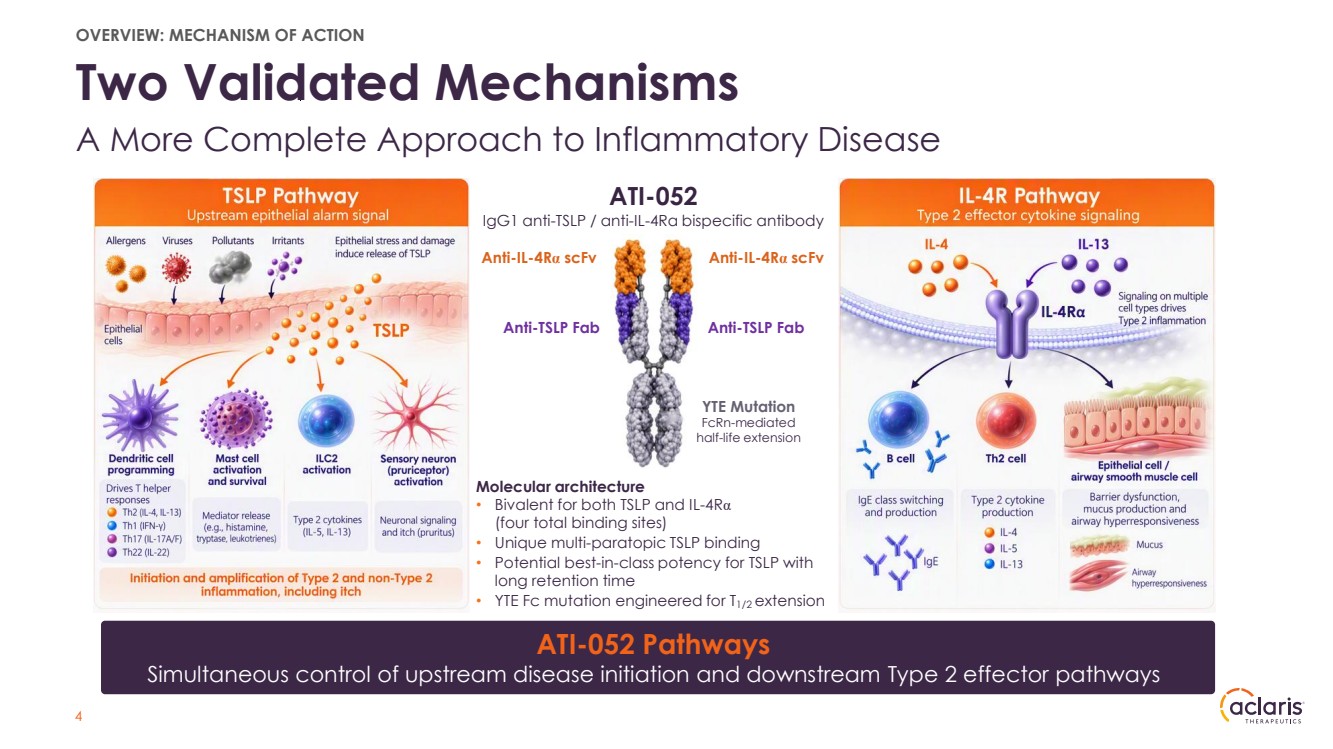
| 4 OVERVIEW: MECHANISM OF ACTION Two Validated Mechanisms A More Complete Approach to Inflammatory Disease ATI-052 Pathways Simultaneous control of upstream disease initiation and downstream Type 2 effector pathways ATI-052 IgG1 anti-TSLP / anti-IL-4Rα bispecific antibody Molecular architecture • Bivalent for both TSLP and IL-4Rα (four total binding sites) • Unique multi-paratopic TSLP binding • Potential best-in-class potency for TSLP with long retention time • YTE Fc mutation engineered for T1/2 extension Anti-IL-4Rα scFv Anti-IL-4Rα scFv Anti-TSLP Fab Anti-TSLP Fab YTE Mutation FcRn-mediated half-life extension |
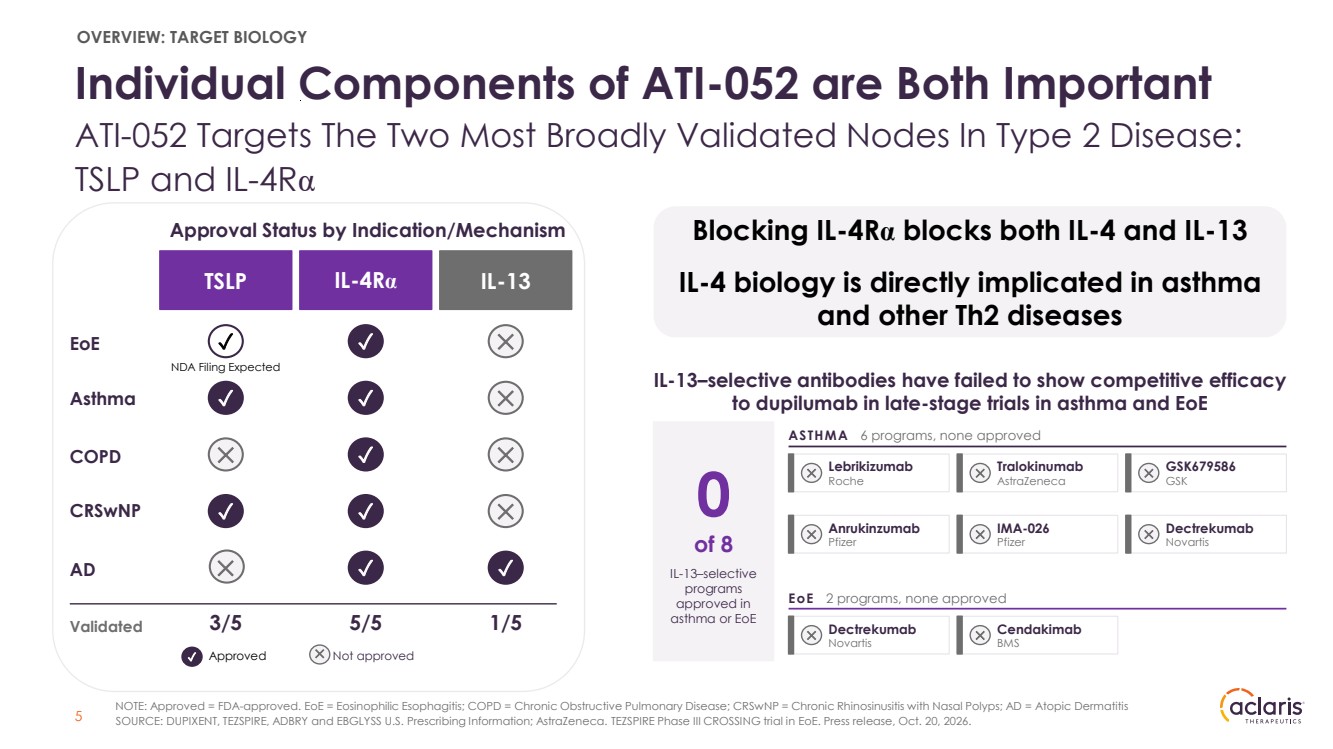
| Individual Components of ATI-052 are Both Important ATI-052 Targets The Two Most Broadly Validated Nodes In Type 2 Disease: TSLP and IL-4Rα Approval Status by Indication/Mechanism TSLP IL-4Rα IL-13 EoE ✓ ✓ ✕ Asthma ✓ ✓ ✕ COPD ✕ ✓ ✕ CRSwNP ✓ ✓ ✕ AD ✓ ✓ Validated 3/5 5/5 1/5 ✓ Approved ✕ Not approved IL-13–selective antibodies have failed to show competitive efficacy to dupilumab in late-stage trials in asthma and EoE 0 of 8 IL-13–selective programs approved in asthma or EoE ASTHMA 6 programs, none approved ✕ Lebrikizumab Roche ✕ Tralokinumab AstraZeneca ✕ GSK679586 GSK ✕ Anrukinzumab Pfizer ✕ IMA-026 Pfizer ✕ Dectrekumab Novartis EoE 2 programs, none approved ✕ Dectrekumab Novartis ✕ Cendakimab BMS SOURCE: DUPIXENT, TEZSPIRE, ADBRY and EBGLYSS U.S. Prescribing Information; AstraZeneca. TEZSPIRE Phase III CROSSING trial in EoE. Press release, Oct. 20, 2026. OVERVIEW: TARGET BIOLOGY NOTE: Approved = FDA-approved. EoE = Eosinophilic Esophagitis; COPD = Chronic Obstructive Pulmonary Disease; CRSwNP = Chronic Rhinosinusitis with Nasal Polyps; AD = Atopic Dermatitis Blocking IL-4Rα blocks both IL-4 and IL-13 IL-4 biology is directly implicated in asthma and other Th2 diseases 5 NDA Filing Expected ✕ |
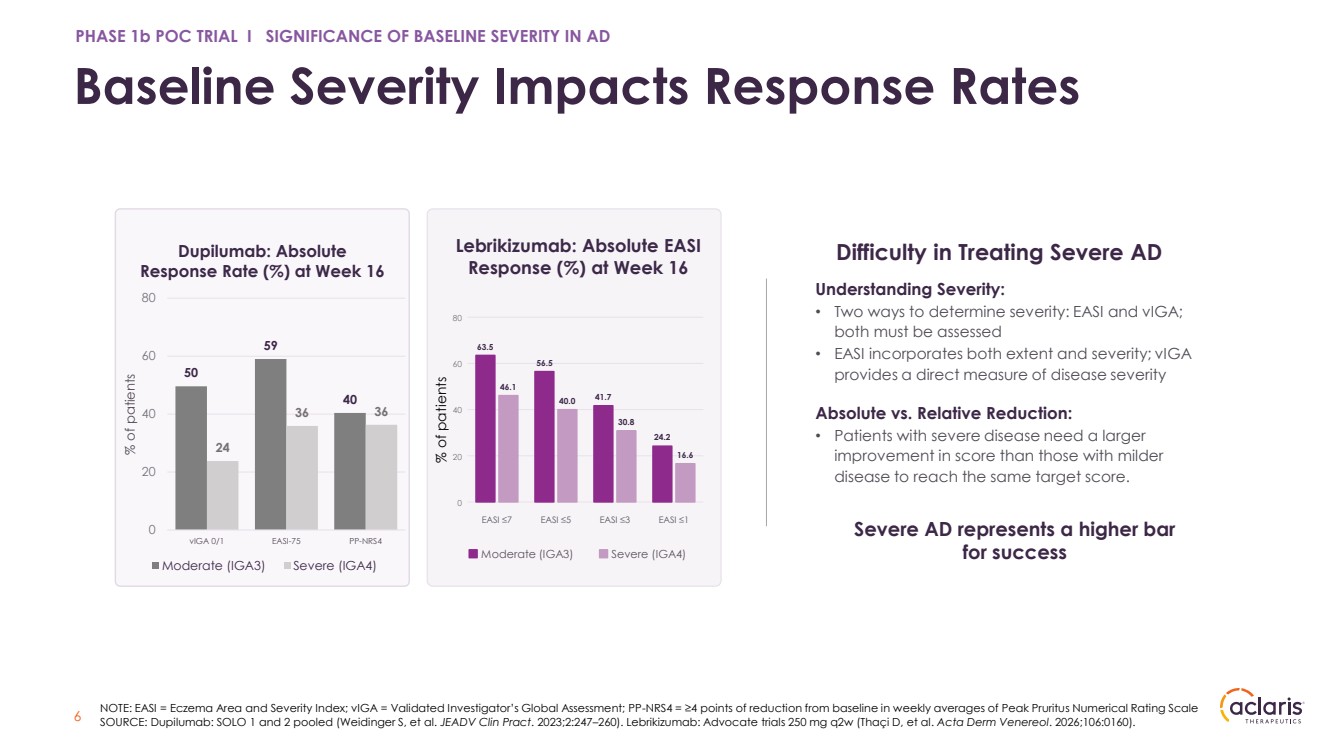
| Lebrikizumab: Absolute EASI Response (%) at Week 16 0 20 40 60 80 63.5 46.1 EASI ≤7 56.5 40.0 EASI ≤5 41.7 30.8 EASI ≤3 24.2 16.6 EASI ≤1 Moderate (IGA3) Severe (IGA4) Baseline Severity Impacts Response Rates PHASE 1b POC TRIAL I SIGNIFICANCE OF BASELINE SEVERITY IN AD % of patients Difficulty in Treating Severe AD Understanding Severity: • Two ways to determine severity: EASI and vIGA; both must be assessed • EASI incorporates both extent and severity; vIGA provides a direct measure of disease severity Absolute vs. Relative Reduction: • Patients with severe disease need a larger improvement in score than those with milder disease to reach the same target score. Severe AD represents a higher bar for success NOTE: EASI = Eczema Area and Severity Index; vIGA = Validated Investigator’s Global Assessment; PP-NRS4 = ≥4 points of reduction from baseline in weekly averages of Peak Pruritus Numerical Rating Scale SOURCE: Dupilumab: SOLO 1 and 2 pooled (Weidinger S, et al. JEADV Clin Pract. 2023;2:247–260). Lebrikizumab: Advocate trials 250 mg q2w (Thaçi D, et al. Acta Derm Venereol. 2026;106:0160). 50 59 40 24 36 36 0 20 40 60 80 vIGA 0/1 EASI-75 PP-NRS4 % of patients Dupilumab: Absolute Response Rate (%) at Week 16 Moderate (IGA3) Severe (IGA4) 6 |
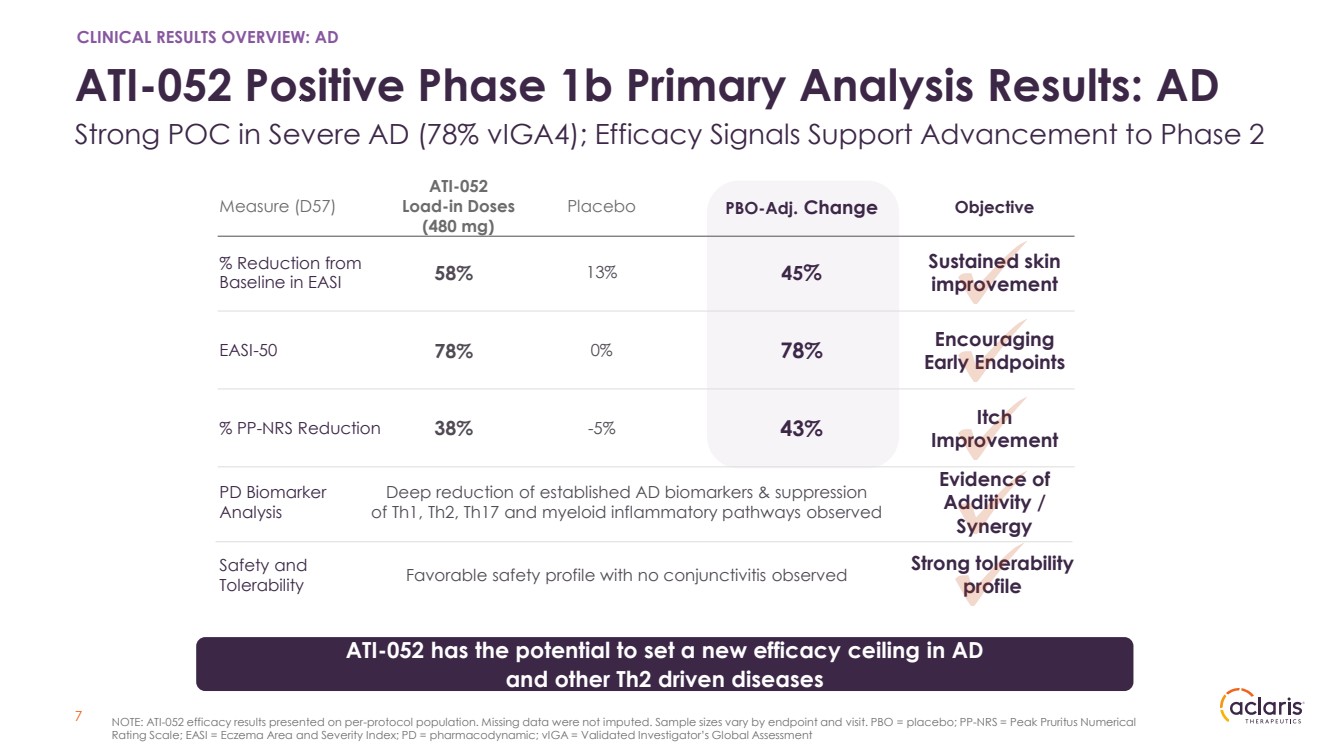
| ATI-052 Positive Phase 1b Primary Analysis Results: AD Strong POC in Severe AD (78% vIGA4); Efficacy Signals Support Advancement to Phase 2 CLINICAL RESULTS OVERVIEW: AD Favorable safety profile with no conjunctivitis observed ATI-052 has the potential to set a new efficacy ceiling in AD and other Th2 driven diseases Measure (D57) ATI-052 Load-in Doses (480 mg) Placebo % Reduction from Baseline in EASI 58% 13% 45% EASI-50 78% 0% 78% % PP-NRS Reduction 38% -5% 43% NOTE: ATI-052 efficacy results presented on per-protocol population. Missing data were not imputed. Sample sizes vary by endpoint and visit. PBO = placebo; PP-NRS = Peak Pruritus Numerical Rating Scale; EASI = Eczema Area and Severity Index; PD = pharmacodynamic; vIGA = Validated Investigator’s Global Assessment Sustained skin improvement Encouraging Early Endpoints Itch Improvement PBO-Adj. Change Objective PD Biomarker Analysis Deep reduction of established AD biomarkers & suppression of Th1, Th2, Th17 and myeloid inflammatory pathways observed Evidence of Additivity / Synergy 7 Safety and Tolerability Strong tolerability profile |
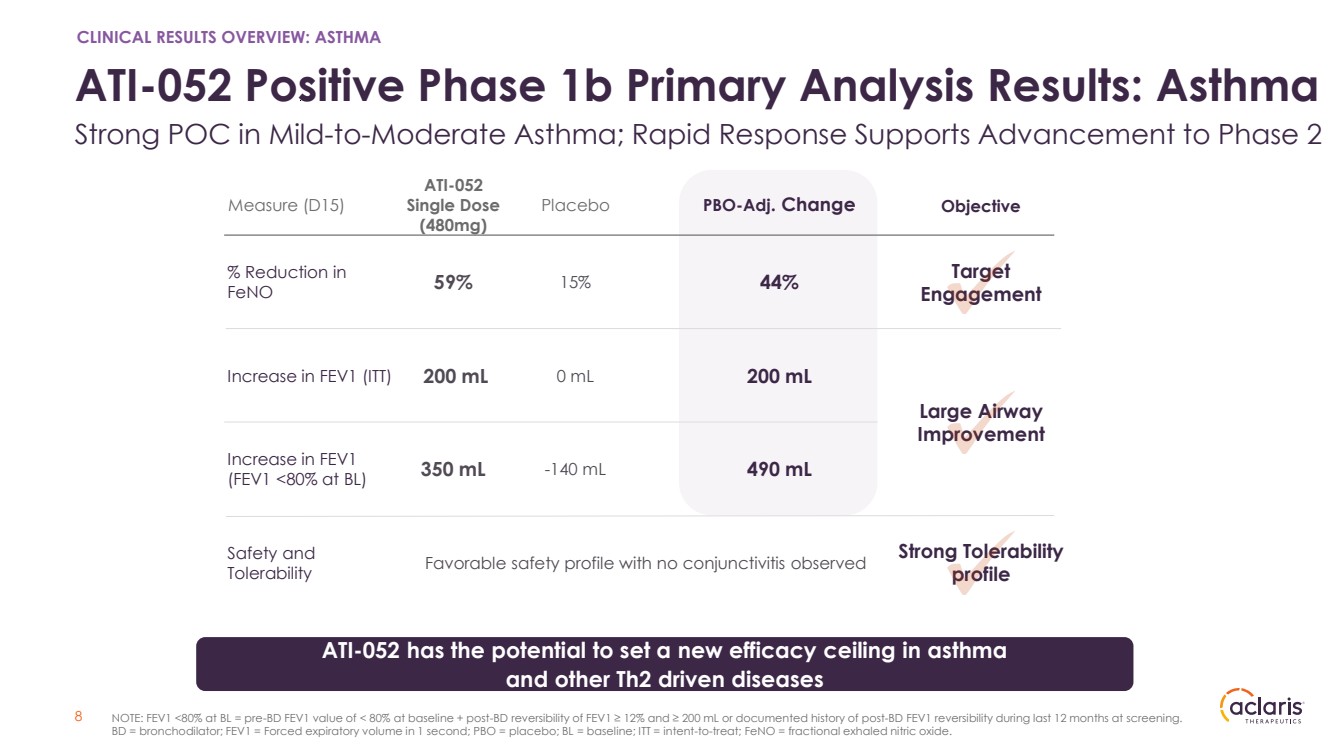
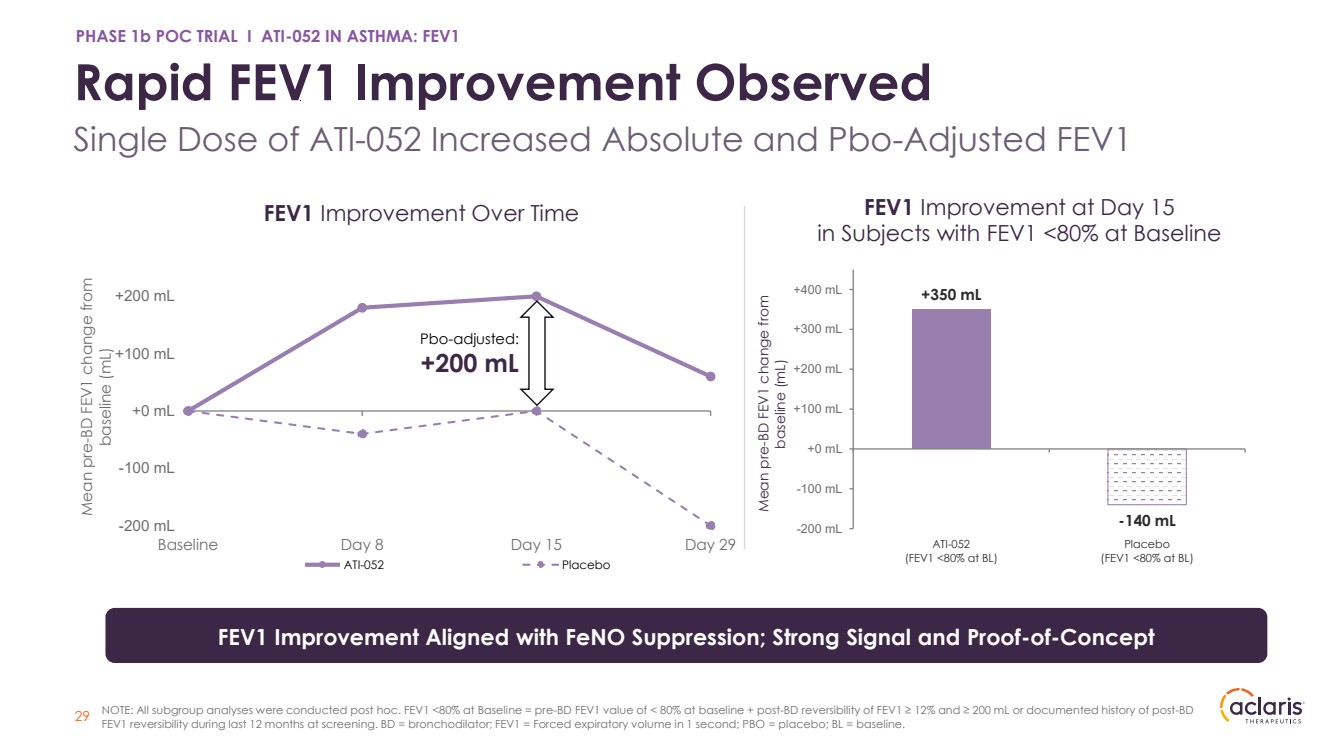
| ATI-052 Positive Phase 1b Primary Analysis Results: Asthma Strong POC in Mild-to-Moderate Asthma; Rapid Response Supports Advancement to Phase 2 CLINICAL RESULTS OVERVIEW: ASTHMA Measure (D15) ATI-052 Single Dose (480mg) Placebo PBO-Adj. Change % Reduction in FeNO 59% 15% 44% 200 mL 0 mL 200 mL Increase in FEV1 (FEV1 <80% at BL) 350 mL -140 mL 490 mL NOTE: FEV1 <80% at BL = pre-BD FEV1 value of < 80% at baseline + post-BD reversibility of FEV1 ≥ 12% and ≥ 200 mL or documented history of post-BD FEV1 reversibility during last 12 months at screening. BD = bronchodilator; FEV1 = Forced expiratory volume in 1 second; PBO = placebo; BL = baseline; ITT = intent-to-treat; FeNO = fractional exhaled nitric oxide. Target Engagement Large Airway Improvement Objective 8 Increase in FEV1 (ITT) Favorable safety profile with no conjunctivitis observed Safety and Tolerability Strong Tolerability profile ATI-052 has the potential to set a new efficacy ceiling in asthma and other Th2 driven diseases |
| ATI-052 POC in Atopic Dermatitis (AD) Data cutoff date: August 20, 2026 |
| 10 Screening/ Washout Randomization 3:1 Active to Placebo Primary Endpoint Safety and tolerability Phase 1b POC Trial in Severe Atopic Dermatitis 14 AD Patients Placebo Q1wk (five doses) ATI-052 Q1wk (five doses, 480 mg) 12-week follow-up Day 57 (Week 8) Primary analysis Other Endpoints AD clinical efficacy assessments (EASI, PP-NRS, etc.) PD endpoints measured by assays including lesional and non-lesional skin tape strips CLINICAL STRATEGY: ATI-052 IN AD Location United States: Multi-site Strategy First signal-finding clinical trial to assess the efficacy of load-in doses only (no doses after week 4) in severe AD patient population Load-in Injections Wk0 Wk1 Wk2 Wk3 Wk4 NOTE: EASI = Eczema Area and Severity Index; PP-NRS = Peak Pruritus Numerical Rating Scale |
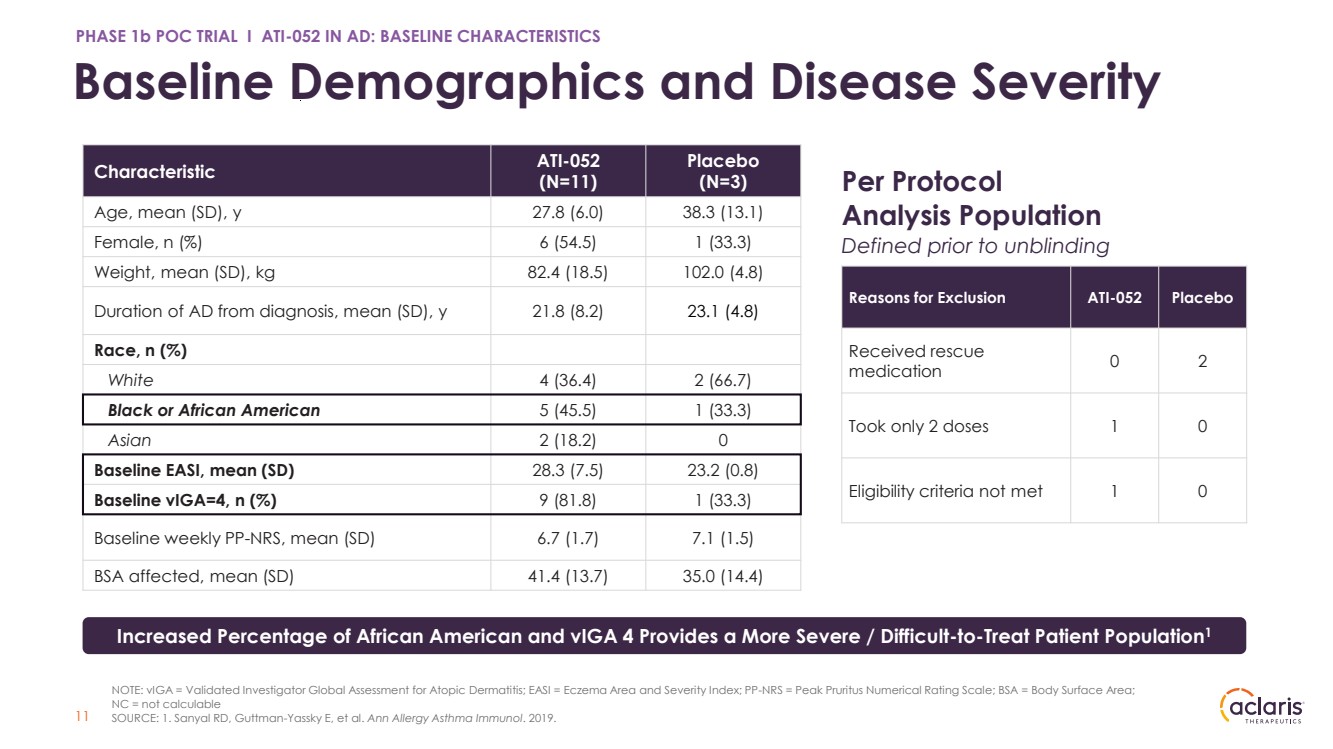
| Baseline Demographics and Disease Severity 11 PHASE 1b POC TRIAL I ATI-052 IN AD: BASELINE CHARACTERISTICS Increased Percentage of African American and vIGA 4 Provides a More Severe / Difficult-to-Treat Patient Population1 SOURCE: 1. Sanyal RD, Guttman-Yassky E, et al. Ann Allergy Asthma Immunol. 2019. NOTE: vIGA = Validated Investigator Global Assessment for Atopic Dermatitis; EASI = Eczema Area and Severity Index; PP-NRS = Peak Pruritus Numerical Rating Scale; BSA = Body Surface Area; NC = not calculable Characteristic ATI-052 (N=11) Placebo (N=3) Age, mean (SD), y 27.8 (6.0) 38.3 (13.1) Female, n (%) 6 (54.5) 1 (33.3) Weight, mean (SD), kg 82.4 (18.5) 102.0 (4.8) Duration of AD from diagnosis, mean (SD), y 21.8 (8.2) 23.1 (4.8) Race, n (%) White 4 (36.4) 2 (66.7) Black or African American 5 (45.5) 1 (33.3) Asian 2 (18.2) 0 Baseline EASI, mean (SD) 28.3 (7.5) 23.2 (0.8) Baseline vIGA=4, n (%) 9 (81.8) 1 (33.3) Baseline weekly PP-NRS, mean (SD) 6.7 (1.7) 7.1 (1.5) BSA affected, mean (SD) 41.4 (13.7) 35.0 (14.4) Reasons for Exclusion ATI-052 Placebo Received rescue medication 0 2 Took only 2 doses 1 0 Eligibility criteria not met 1 0 Per Protocol Analysis Population Defined prior to unblinding |
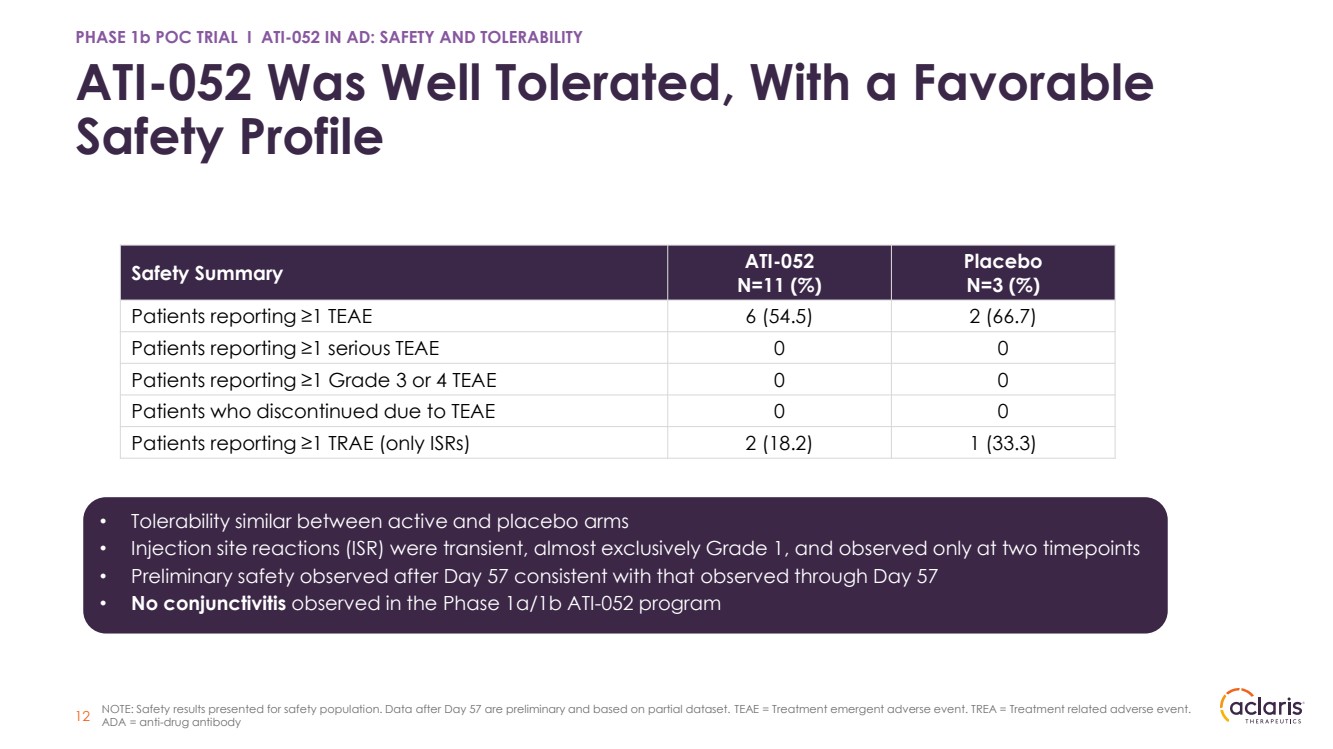
| ATI-052 Was Well Tolerated, With a Favorable Safety Profile 12 Safety Summary ATI-052 N=11 (%) Placebo N=3 (%) Patients reporting ≥1 TEAE 6 (54.5) 2 (66.7) Patients reporting ≥1 serious TEAE 0 0 Patients reporting ≥1 Grade 3 or 4 TEAE 0 0 Patients who discontinued due to TEAE 0 0 Patients reporting ≥1 TRAE (only ISRs) 2 (18.2) 1 (33.3) PHASE 1b POC TRIAL I ATI-052 IN AD: SAFETY AND TOLERABILITY • Tolerability similar between active and placebo arms • Injection site reactions (ISR) were transient, almost exclusively Grade 1, and observed only at two timepoints • Preliminary safety observed after Day 57 consistent with that observed through Day 57 • No conjunctivitis observed in the Phase 1a/1b ATI-052 program NOTE: Safety results presented for safety population. Data after Day 57 are preliminary and based on partial dataset. TEAE = Treatment emergent adverse event. TREA = Treatment related adverse event. ADA = anti-drug antibody |
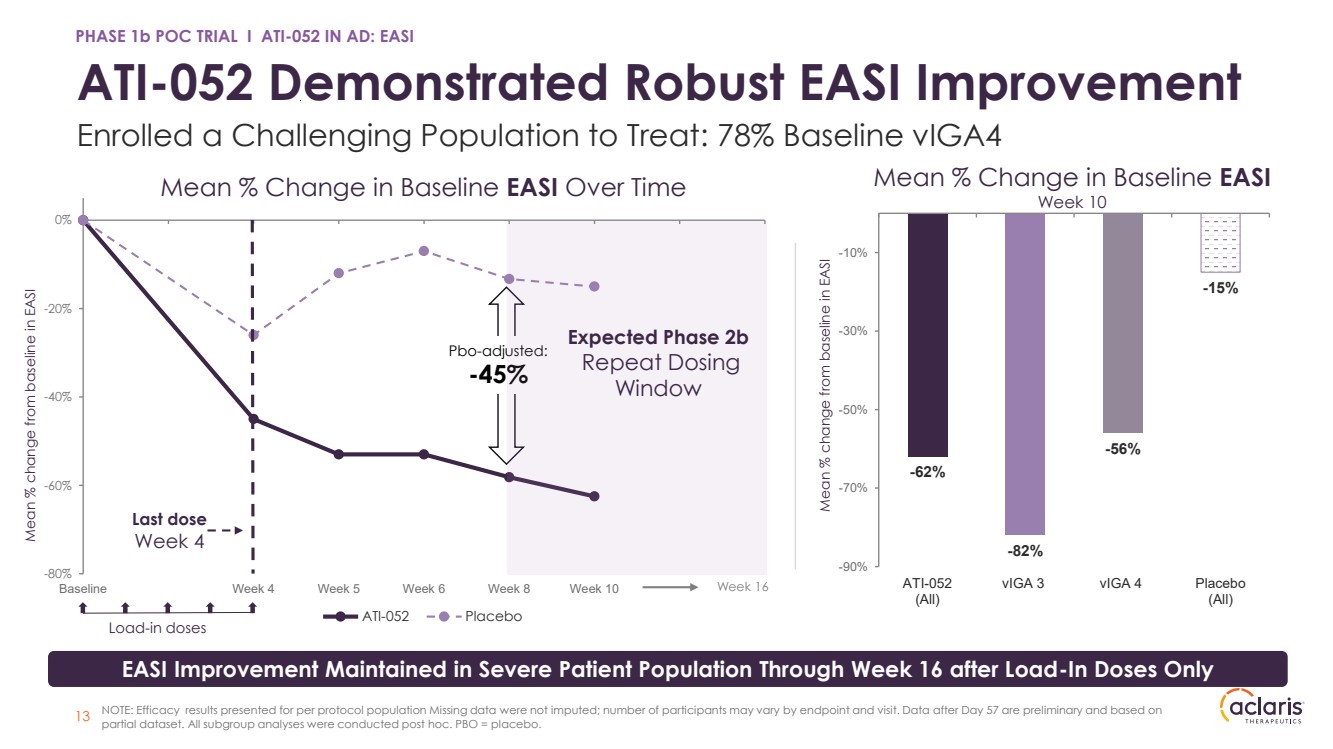
| -80% -60% -40% -20% 0% Baseline Week 4 Week 5 Week 6 Week 8 Week 10 ATI-052 Placebo ATI-052 Demonstrated Robust EASI Improvement Enrolled a Challenging Population to Treat: 78% Baseline vIGA4 Mean % Change in Baseline EASI Over Time Mean % Change in Baseline EASI Week 10 -62% -82% -56% -15% -90% -70% -50% -30% -10% ATI-052 (All) vIGA 3 vIGA 4 Placebo (All) EASI Improvement Maintained in Severe Patient Population Through Week 16 after Load-In Doses Only Pbo-adjusted: -45% Last dose Week 4 13 Week 16 PHASE 1b POC TRIAL I ATI-052 IN AD: EASI Expected Phase 2b Repeat Dosing Window Mean % change from baseline in EASI NOTE: Efficacy results presented for per protocol population Missing data were not imputed; number of participants may vary by endpoint and visit. Data after Day 57 are preliminary and based on partial dataset. All subgroup analyses were conducted post hoc. PBO = placebo. Load-in doses Mean % change from baseline in EASI |
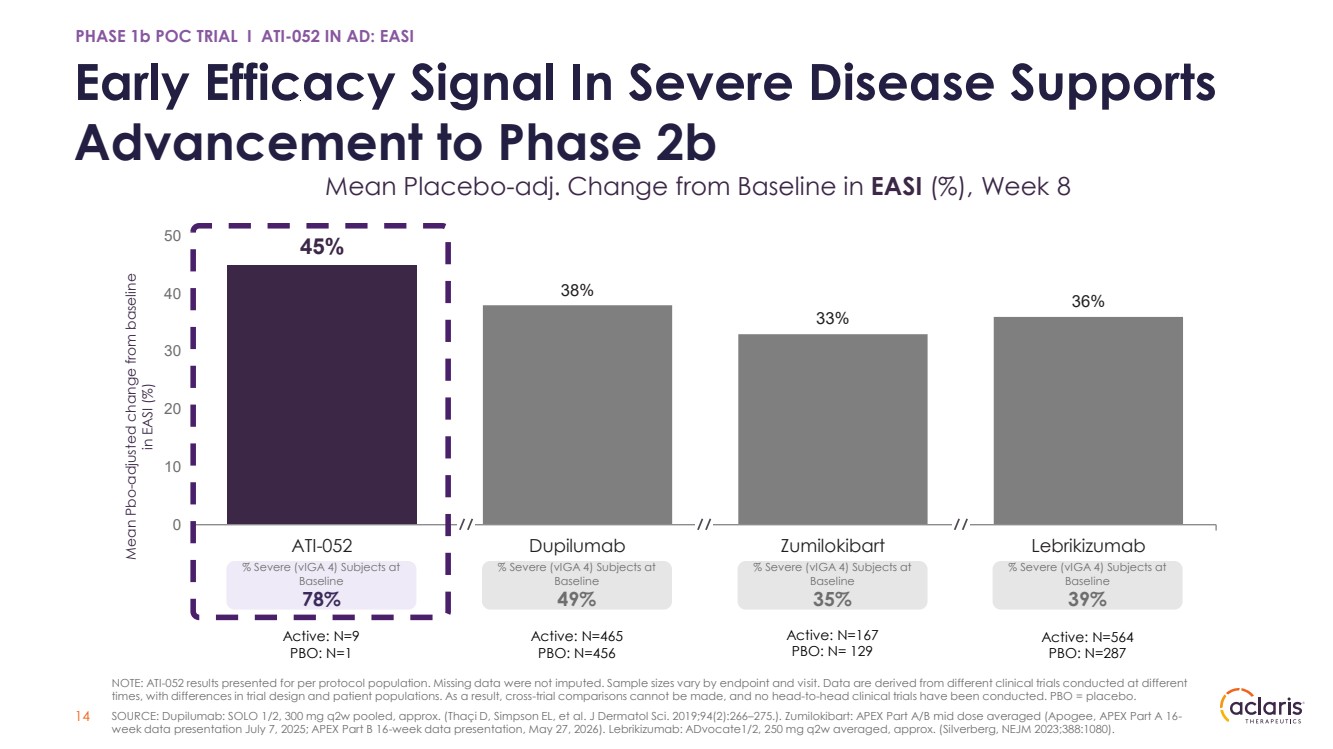
| Early Efficacy Signal In Severe Disease Supports Advancement to Phase 2b 45% 38% 33% 36% 0 10 20 30 40 50 ATI-052 Dupilumab Zumilokibart Lebrikizumab % Severe (vIGA 4) Subjects at Baseline 78% PHASE 1b POC TRIAL I ATI-052 IN AD: EASI 14 % Severe (vIGA 4) Subjects at Baseline 49% % Severe (vIGA 4) Subjects at Baseline 35% % Severe (vIGA 4) Subjects at Baseline 39% SOURCE: Dupilumab: SOLO 1/2, 300 mg q2w pooled, approx. (Thaçi D, Simpson EL, et al. J Dermatol Sci. 2019;94(2):266–275.). Zumilokibart: APEX Part A/B mid dose averaged (Apogee, APEX Part A 16- week data presentation July 7, 2025; APEX Part B 16-week data presentation, May 27, 2026). Lebrikizumab: ADvocate1/2, 250 mg q2w averaged, approx. (Silverberg, NEJM 2023;388:1080). NOTE: ATI-052 results presented for per protocol population. Missing data were not imputed. Sample sizes vary by endpoint and visit. Data are derived from different clinical trials conducted at different times, with differences in trial design and patient populations. As a result, cross-trial comparisons cannot be made, and no head-to-head clinical trials have been conducted. PBO = placebo. Mean Placebo-adj. Change from Baseline in EASI (%), Week 8 Mean Pbo-adjusted change from baseline in EASI (%) Active: N=564 PBO: N=287 Active: N=167 PBO: N= 129 Active: N=465 PBO: N=456 Active: N=9 PBO: N=1 |
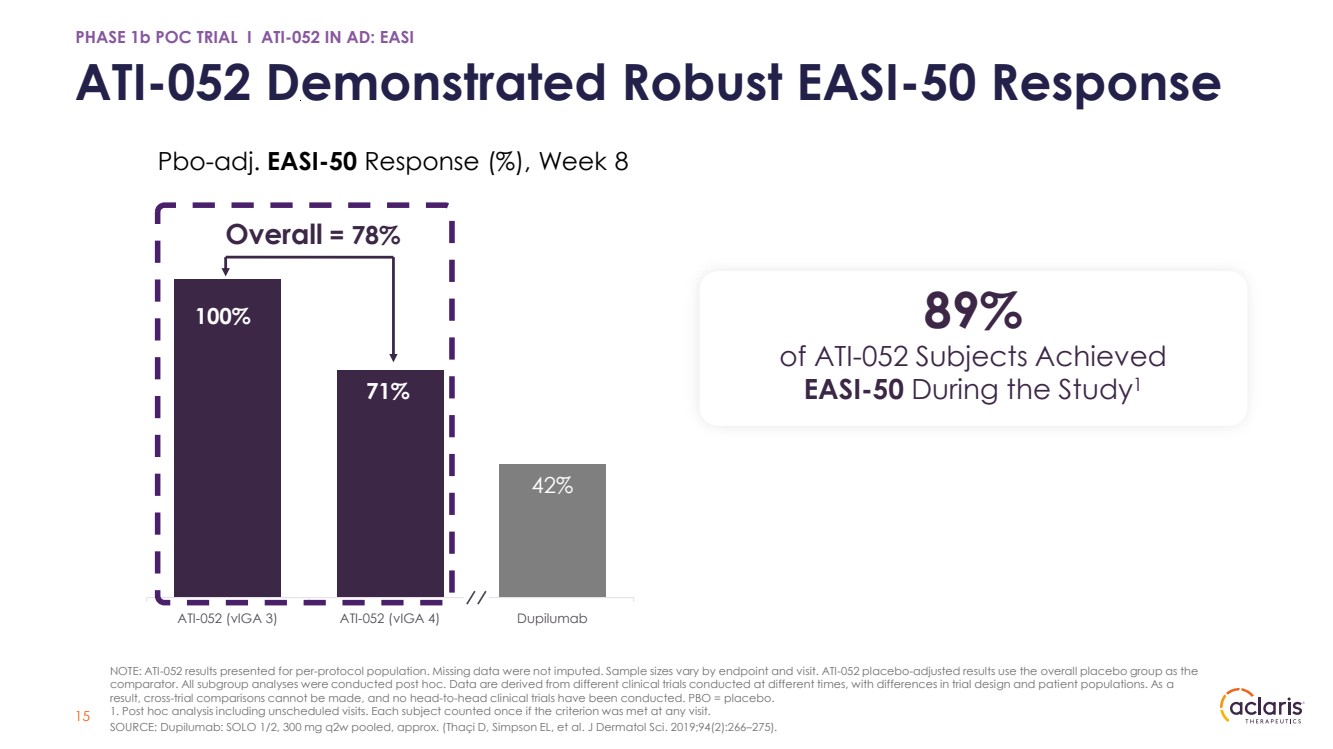
| 15 ATI-052 Demonstrated Robust EASI-50 Response 100% 71% 42% ATI-052 (vIGA 3) ATI-052 (vIGA 4) Dupilumab SOURCE: Dupilumab: SOLO 1/2, 300 mg q2w pooled, approx. (Thaçi D, Simpson EL, et al. J Dermatol Sci. 2019;94(2):266–275). PHASE 1b POC TRIAL I ATI-052 IN AD: EASI Overall = 78% Pbo-adj. EASI-50 Response (%), Week 8 89% of ATI-052 Subjects Achieved EASI-50 During the Study1 NOTE: ATI-052 results presented for per-protocol population. Missing data were not imputed. Sample sizes vary by endpoint and visit. ATI-052 placebo-adjusted results use the overall placebo group as the comparator. All subgroup analyses were conducted post hoc. Data are derived from different clinical trials conducted at different times, with differences in trial design and patient populations. As a result, cross-trial comparisons cannot be made, and no head-to-head clinical trials have been conducted. PBO = placebo. 1. Post hoc analysis including unscheduled visits. Each subject counted once if the criterion was met at any visit. |
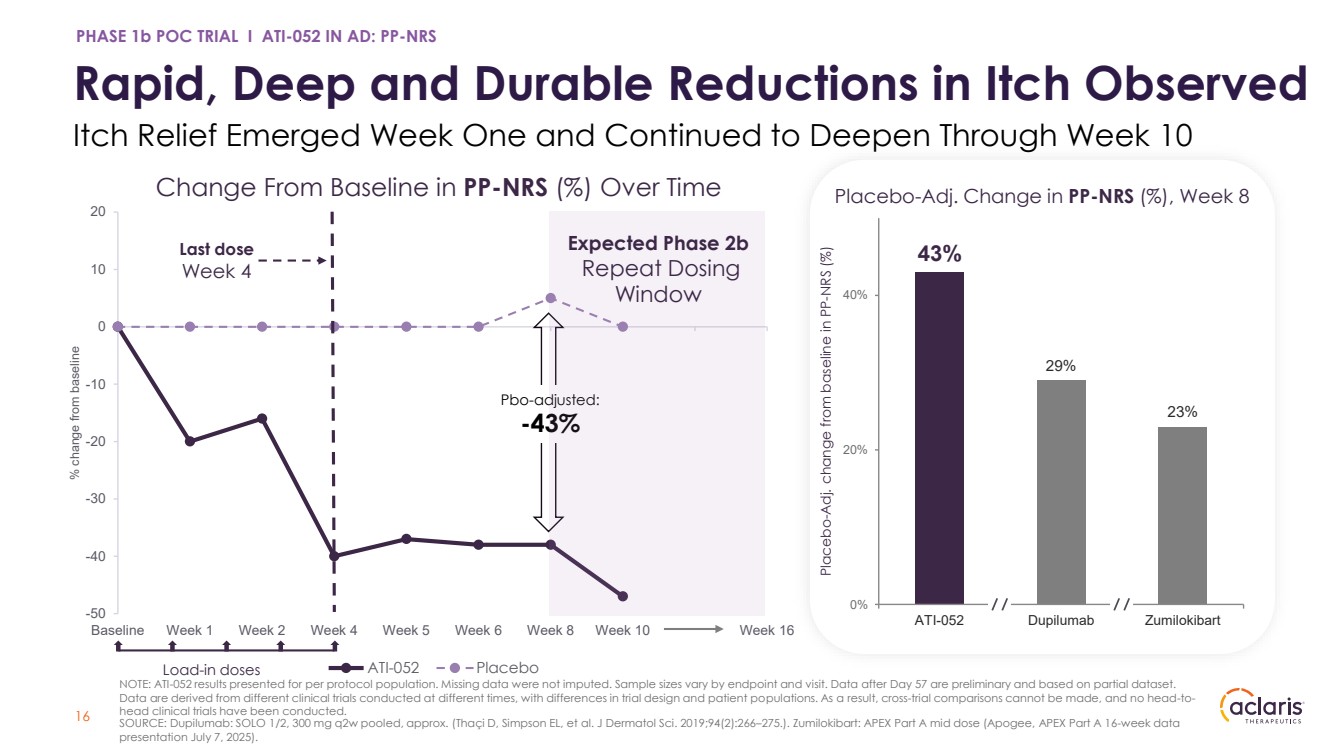
| -50 -40 -30 -20 -10 0 10 20 Baseline Week 1 Week 2 Week 4 Week 5 Week 6 Week 8 Week 10 Week 16 % change from baseline ATI-052 Placebo PHASE 1b POC TRIAL I ATI-052 IN AD: PP-NRS Rapid, Deep and Durable Reductions in Itch Observed Itch Relief Emerged Week One and Continued to Deepen Through Week 10 16 SOURCE: Dupilumab: SOLO 1/2, 300 mg q2w pooled, approx. (Thaçi D, Simpson EL, et al. J Dermatol Sci. 2019;94(2):266–275.). Zumilokibart: APEX Part A mid dose (Apogee, APEX Part A 16-week data presentation July 7, 2025). Pbo-adjusted: -43% Placebo-Adj. Change in PP-NRS (%), Week 8 43% 29% 23% 0% 20% 40% ATI-052 Dupilumab Zumilokibart Change From Baseline in PP-NRS (%) Over Time Last dose Week 4 Expected Phase 2b Repeat Dosing Window NOTE: ATI-052 results presented for per protocol population. Missing data were not imputed. Sample sizes vary by endpoint and visit. Data after Day 57 are preliminary and based on partial dataset. Data are derived from different clinical trials conducted at different times, with differences in trial design and patient populations. As a result, cross-trial comparisons cannot be made, and no head-to-head clinical trials have been conducted. Placebo-Adj. change from baseline in PP-NRS (%) Load-in doses |
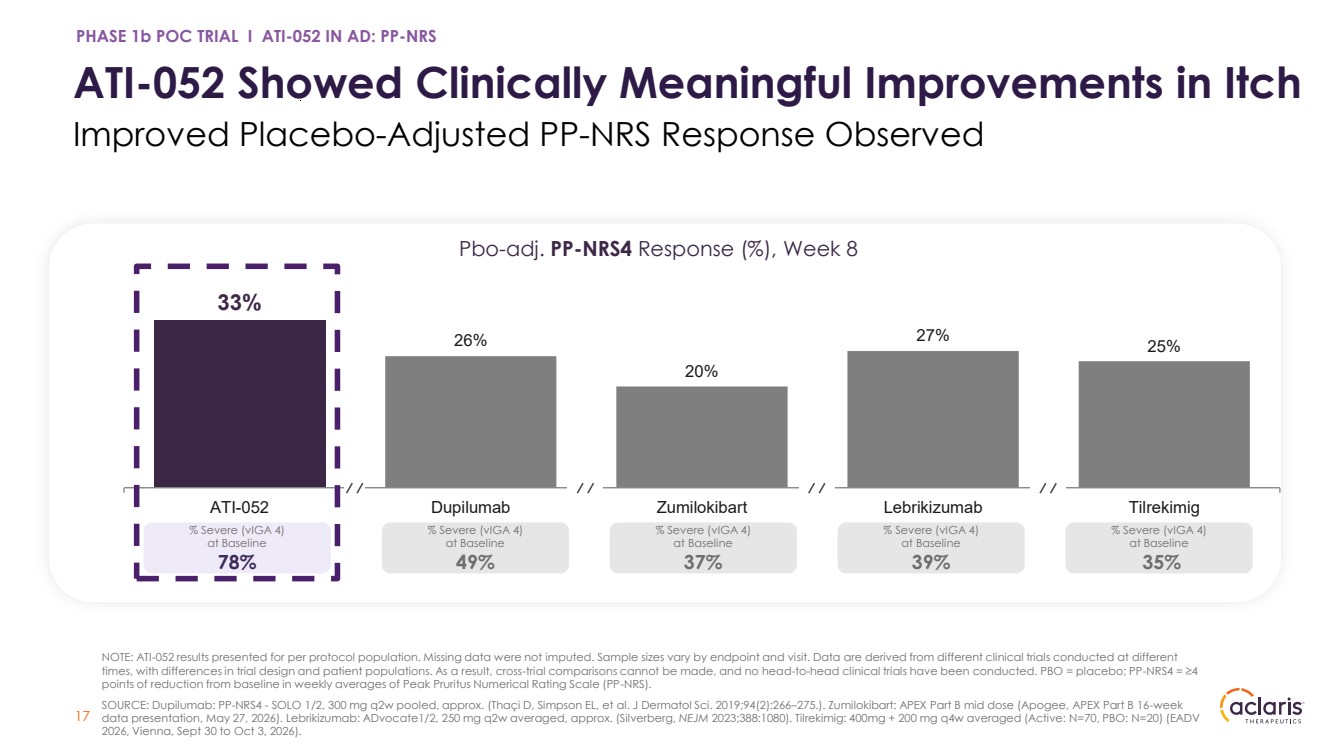
| PHASE 1b POC TRIAL I ATI-052 IN AD: PP-NRS 17 SOURCE: Dupilumab: PP-NRS4 - SOLO 1/2, 300 mg q2w pooled, approx. (Thaçi D, Simpson EL, et al. J Dermatol Sci. 2019;94(2):266–275.). Zumilokibart: APEX Part B mid dose (Apogee, APEX Part B 16-week data presentation, May 27, 2026). Lebrikizumab: ADvocate1/2, 250 mg q2w averaged, approx. (Silverberg, NEJM 2023;388:1080). Tilrekimig: 400mg + 200 mg q4w averaged (Active: N=70, PBO: N=20) (EADV 2026, Vienna, Sept 30 to Oct 3, 2026). 33% 26% 20% 27% 25% ATI-052 Dupilumab Zumilokibart Lebrikizumab Tilrekimig % Severe (vIGA 4) at Baseline 78% % Severe (vIGA 4) at Baseline 35% % Severe (vIGA 4) at Baseline 49% % Severe (vIGA 4) at Baseline 37% % Severe (vIGA 4) at Baseline 39% Pbo-adj. PP-NRS4 Response (%), Week 8 ATI-052 Showed Clinically Meaningful Improvements in Itch Improved Placebo-Adjusted PP-NRS Response Observed NOTE: ATI-052 results presented for per protocol population. Missing data were not imputed. Sample sizes vary by endpoint and visit. Data are derived from different clinical trials conducted at different times, with differences in trial design and patient populations. As a result, cross-trial comparisons cannot be made, and no head-to-head clinical trials have been conducted. PBO = placebo; PP-NRS4 = ≥4 points of reduction from baseline in weekly averages of Peak Pruritus Numerical Rating Scale (PP-NRS). |
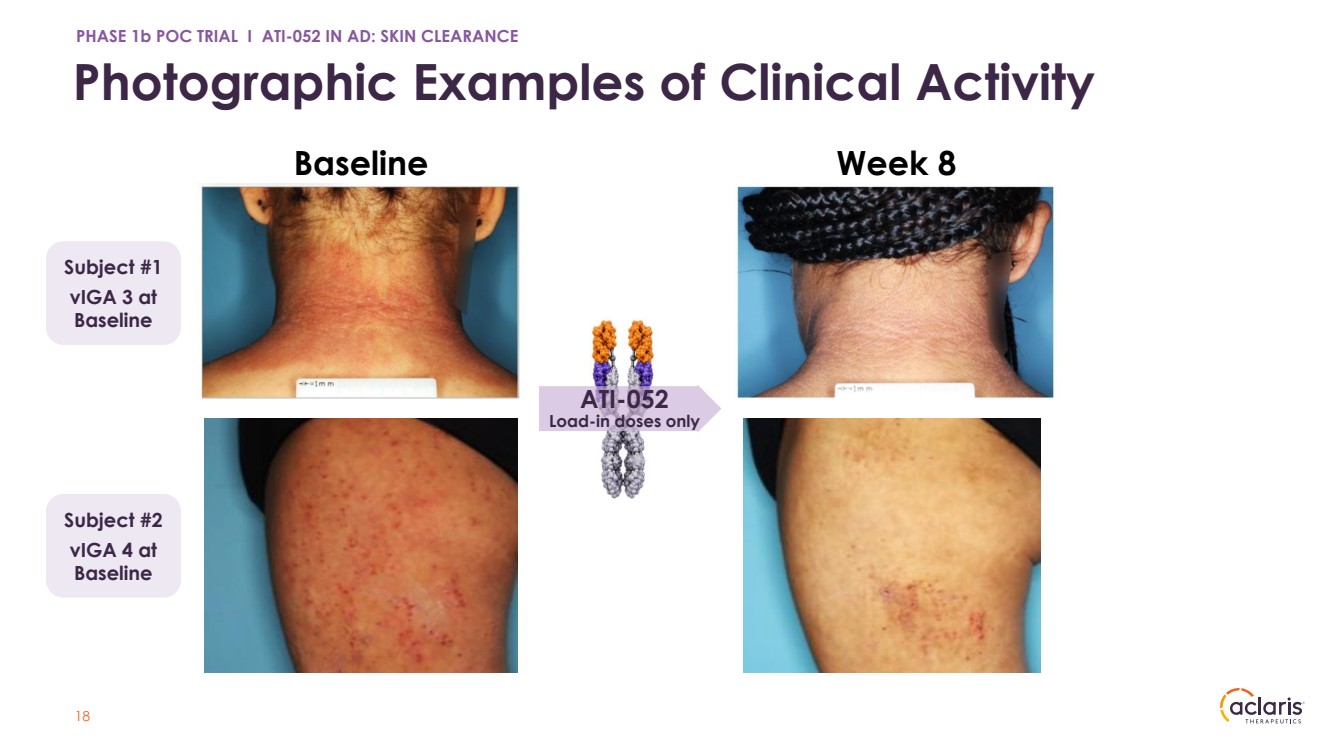
| Photographic Examples of Clinical Activity 18 PHASE 1b POC TRIAL I ATI-052 IN AD: SKIN CLEARANCE Baseline Week 8 ATI-052 Load-in doses only Subject #1 vIGA 3 at Baseline Subject #2 vIGA 4 at Baseline |
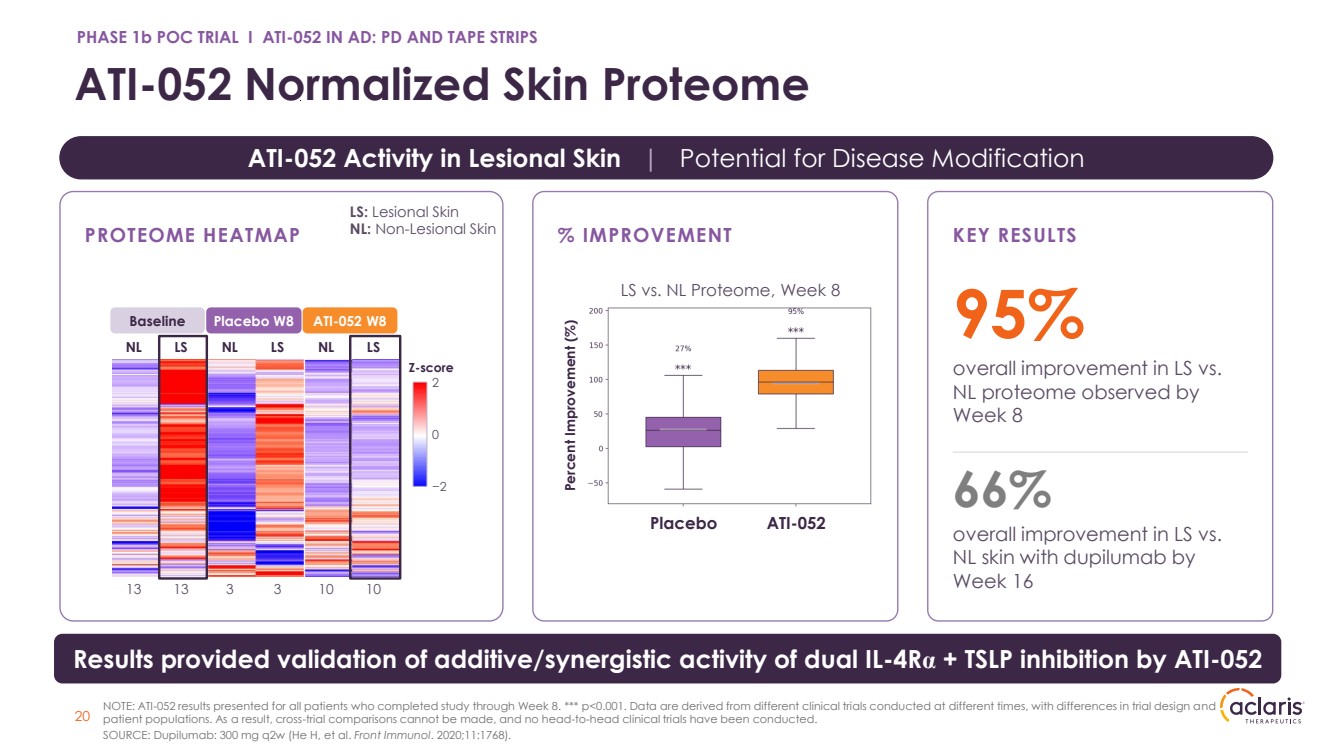
| Potential Best-in-Class Pharmacodynamic Profile TSLP + IL-4Rα | Evidence of Potential Additivity/Synergy Between Targets Broad Pathway Modulation Marked downregulation of inflammatory mediators pertinent to AD observed Pathways modulated Th1 Th2 Th17/Th22 Fibrosis Itch Normalization of Skin Proteome Immune protein expression in lesional skin closely resembled non-lesional skin Proteome shift Lesional → Non-lesional Pronounced Biomarker Reduction Pronounced reduction of established dupilumab biomarkers observed Additional suppression Th1 Th17 Myeloid 19 PHASE 1b POC TRIAL I ATI-052 IN AD: PD AND TAPE STRIPS DR. EMMA GUTTMAN LAB· MT SINAI Skin Tape Strip Analysis O-link proteomics (300+ analytes) INTERNAL ANALYSIS Endogenous Serum Biomarkers (MSD-Select) CCL17/TARC, IL-5 Innate |

| PHASE 1b POC TRIAL I ATI-052 IN AD: PD AND TAPE STRIPS ATI-052 Normalized Skin Proteome ATI-052 Activity in Lesional Skin | Potential for Disease Modification KEY RESULTS 95% overall improvement in LS vs. NL proteome observed by Week 8 66% overall improvement in LS vs. NL skin with dupilumab by Week 16 % IMPROVEMENT Percent Improvement (%) Placebo ATI-052 LS vs. NL Proteome, Week 8 PROTEOME HEATMAP Results provided validation of additive/synergistic activity of dual IL-4Rα + TSLP inhibition by ATI-052 NOTE: ATI-052 results presented for all patients who completed study through Week 8. *** p<0.001. Data are derived from different clinical trials conducted at different times, with differences in trial design and patient populations. As a result, cross-trial comparisons cannot be made, and no head-to-head clinical trials have been conducted. SOURCE: Dupilumab: 300 mg q2w (He H, et al. Front Immunol. 2020;11:1768). 20 Baseline NL LS Placebo W8 NL LS ATI-052 W8 NL LS n 13 13 3 3 10 10 Z-score 2 0 −2 LS: Lesional Skin NL: Non-Lesional Skin |
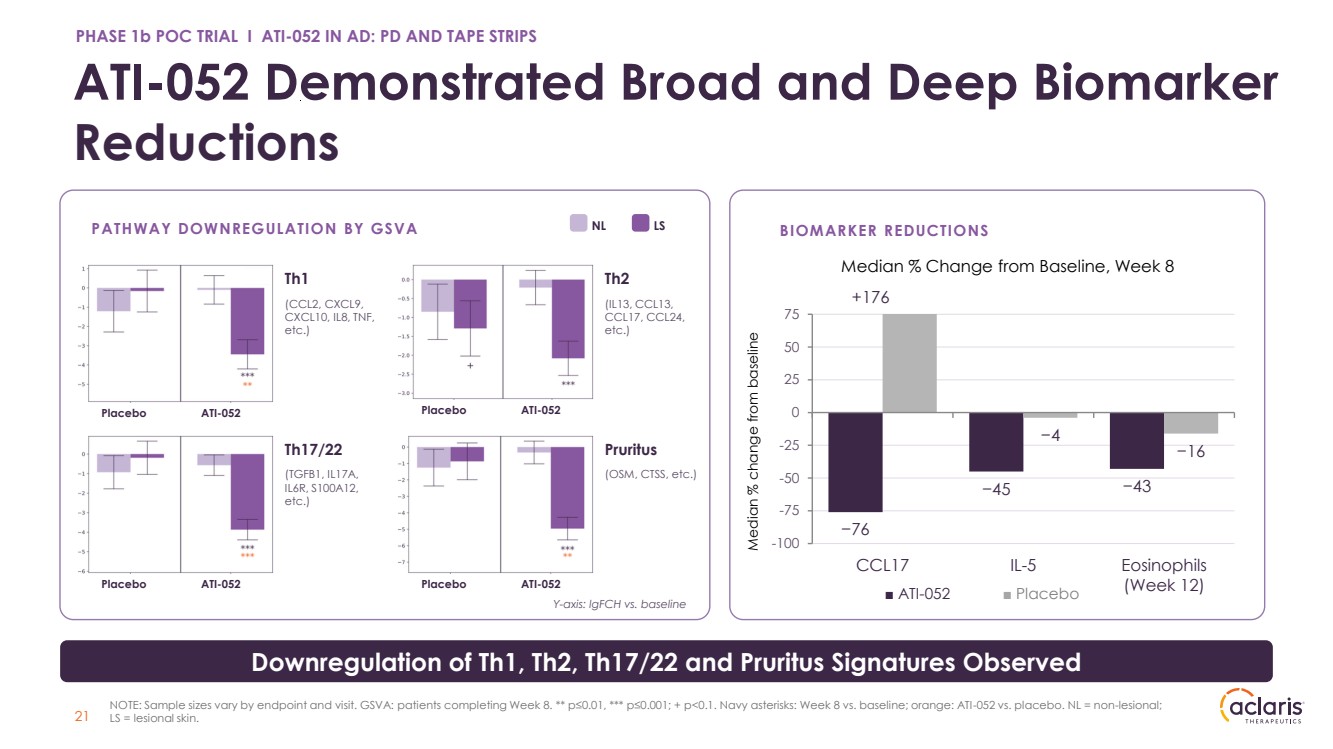
| ATI-052 Demonstrated Broad and Deep Biomarker Reductions Median % Change from Baseline, Week 8 −76 −45 −43 −4 −16 -100 -75 -50 -25 0 25 50 75 CCL17 IL-5 Eosinophils (Week 12) NOTE: Sample sizes vary by endpoint and visit. GSVA: patients completing Week 8. ** p≤0.01, *** p≤0.001; + p<0.1. Navy asterisks: Week 8 vs. baseline; orange: ATI-052 vs. placebo. NL = non-lesional; LS = lesional skin. PHASE 1b POC TRIAL I ATI-052 IN AD: PD AND TAPE STRIPS Median % change from baseline +176 21 PATHWAY DOWNREGULATION BY GSVA NL LS Placebo ATI-052 Th1 (CCL2, CXCL9, CXCL10, IL8, TNF, etc.) Placebo ATI-052 Th2 (IL13, CCL13, CCL17, CCL24, etc.) Placebo ATI-052 Th17/22 (TGFB1, IL17A, IL6R, S100A12, etc.) Placebo ATI-052 Pruritus (OSM, CTSS, etc.) Y-axis: lgFCH vs. baseline BIOMARKER REDUCTIONS ■ ATI-052 ■ Placebo Downregulation of Th1, Th2, Th17/22 and Pruritus Signatures Observed |
| ATI-052 POC in Asthma Data cutoff date: September 24, 2026 |

| 23 Placebo (single dose) ATI-052 (single dose, 480 mg) Screening/ Washout Six-week follow-up Randomization 3:1 Active to Placebo Primary analysis through Day 29 Primary Endpoint Safety and tolerability Phase 1b POC Trial in Asthma 16 Patients Key Clinical Efficacy Assessment: FEV1, AX Other endpoints PD assessments: FeNO, Blood Eos, TARC (CCL17), Periostin, Cytokines CLINICAL STRATEGY I ATI-052 IN ASTHMA Location United States and Europe: Multi-site Strategy Clinical trial to assess a single dose of ATI-052 in a mild-to-moderate asthma population NOTE: FEV1 = Forced Expiratory Volume in 1 Second; FeNO = Fractional Exhaled Nitric Oxide; AX = Area of Reactance. Single Injection |

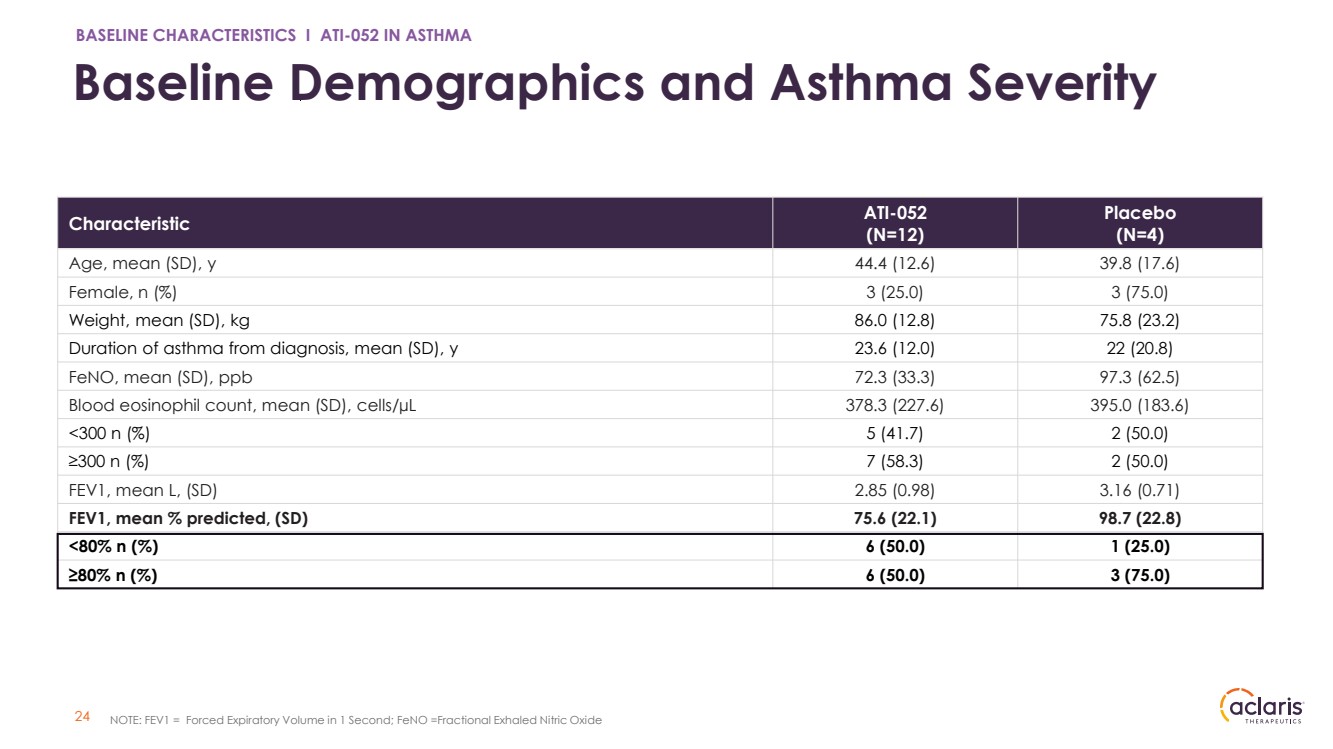
| 24 Characteristic ATI-052 (N=12) Placebo (N=4) Age, mean (SD), y 44.4 (12.6) 39.8 (17.6) Female, n (%) 3 (25.0) 3 (75.0) Weight, mean (SD), kg 86.0 (12.8) 75.8 (23.2) Duration of asthma from diagnosis, mean (SD), y 23.6 (12.0) 22 (20.8) FeNO, mean (SD), ppb 72.3 (33.3) 97.3 (62.5) Blood eosinophil count, mean (SD), cells/µL 378.3 (227.6) 395.0 (183.6) <300 n (%) 5 (41.7) 2 (50.0) ≥300 n (%) 7 (58.3) 2 (50.0) FEV1, mean L, (SD) 2.85 (0.98) 3.16 (0.71) FEV1, mean % predicted, (SD) 75.6 (22.1) 98.7 (22.8) <80% n (%) 6 (50.0) 1 (25.0) ≥80% n (%) 6 (50.0) 3 (75.0) BASELINE CHARACTERISTICS I ATI-052 IN ASTHMA Baseline Demographics and Asthma Severity NOTE: FEV1 = Forced Expiratory Volume in 1 Second; FeNO =Fractional Exhaled Nitric Oxide |
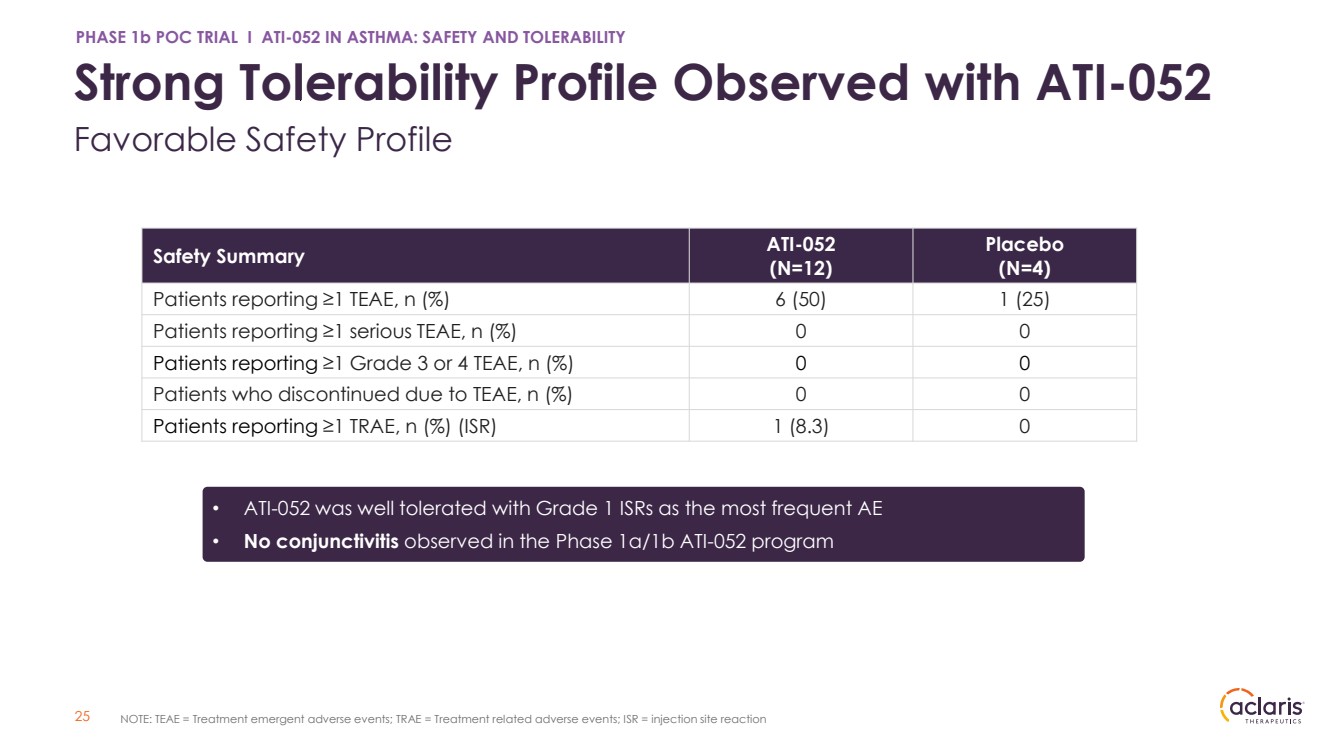
| Strong Tolerability Profile Observed with ATI-052 Favorable Safety Profile 25 Safety Summary ATI-052 (N=12) Placebo (N=4) Patients reporting ≥1 TEAE, n (%) 6 (50) 1 (25) Patients reporting ≥1 serious TEAE, n (%) 0 0 Patients reporting ≥1 Grade 3 or 4 TEAE, n (%) 0 0 Patients who discontinued due to TEAE, n (%) 0 0 Patients reporting ≥1 TRAE, n (%) (ISR) 1 (8.3) 0 • ATI-052 was well tolerated with Grade 1 ISRs as the most frequent AE • No conjunctivitis observed in the Phase 1a/1b ATI-052 program PHASE 1b POC TRIAL I ATI-052 IN ASTHMA: SAFETY AND TOLERABILITY NOTE: TEAE = Treatment emergent adverse events; TRAE = Treatment related adverse events; ISR = injection site reaction |
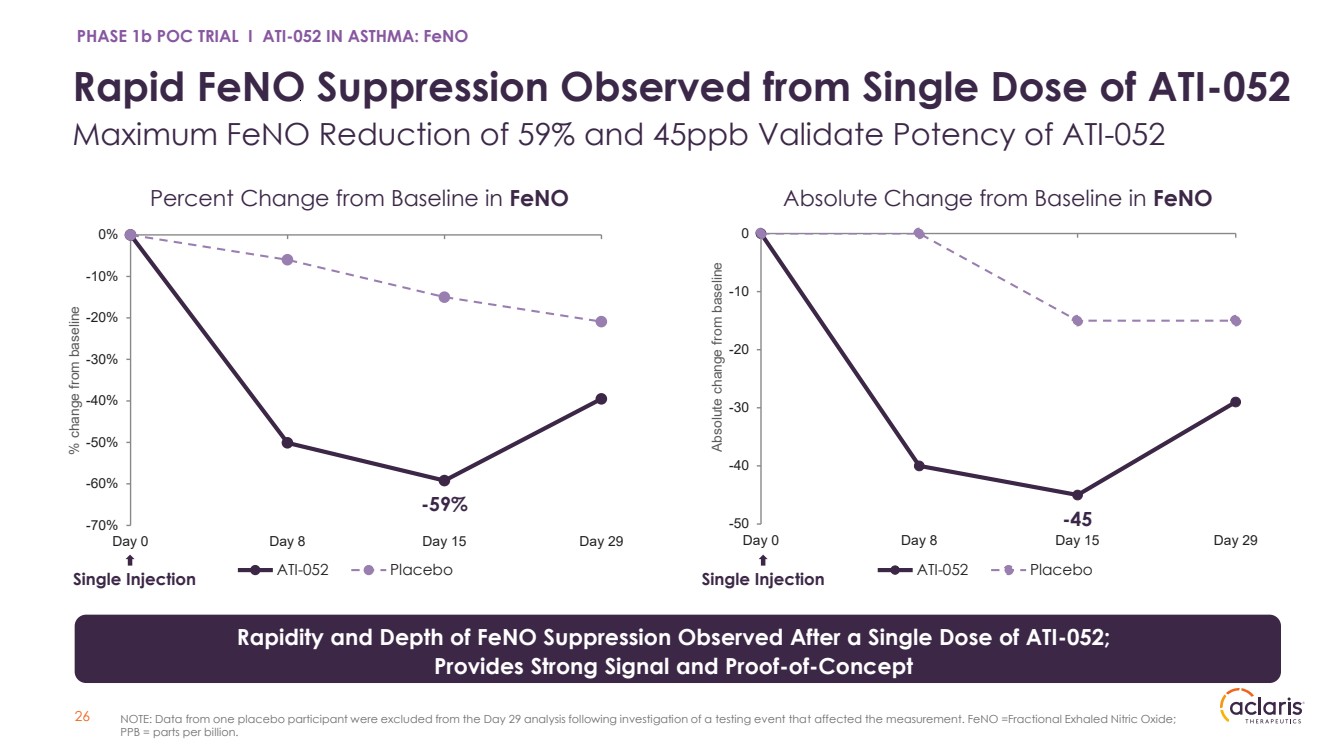
| Rapid FeNO Suppression Observed from Single Dose of ATI-052 Maximum FeNO Reduction of 59% and 45ppb Validate Potency of ATI-052 26 -59% -70% -60% -50% -40% -30% -20% -10% 0% Day 0 Day 8 Day 15 Day 29 % change from baseline ATI-052 Placebo -50 -45 -40 -30 -20 -10 0 Day 0 Day 8 Day 15 Day 29 Absolute change from baseline ATI-052 Placebo Percent Change from Baseline in FeNO Absolute Change from Baseline in FeNO PHASE 1b POC TRIAL I ATI-052 IN ASTHMA: FeNO Rapidity and Depth of FeNO Suppression Observed After a Single Dose of ATI-052; Provides Strong Signal and Proof-of-Concept Single Injection Single Injection NOTE: Data from one placebo participant were excluded from the Day 29 analysis following investigation of a testing event that affected the measurement. FeNO =Fractional Exhaled Nitric Oxide; PPB = parts per billion. |
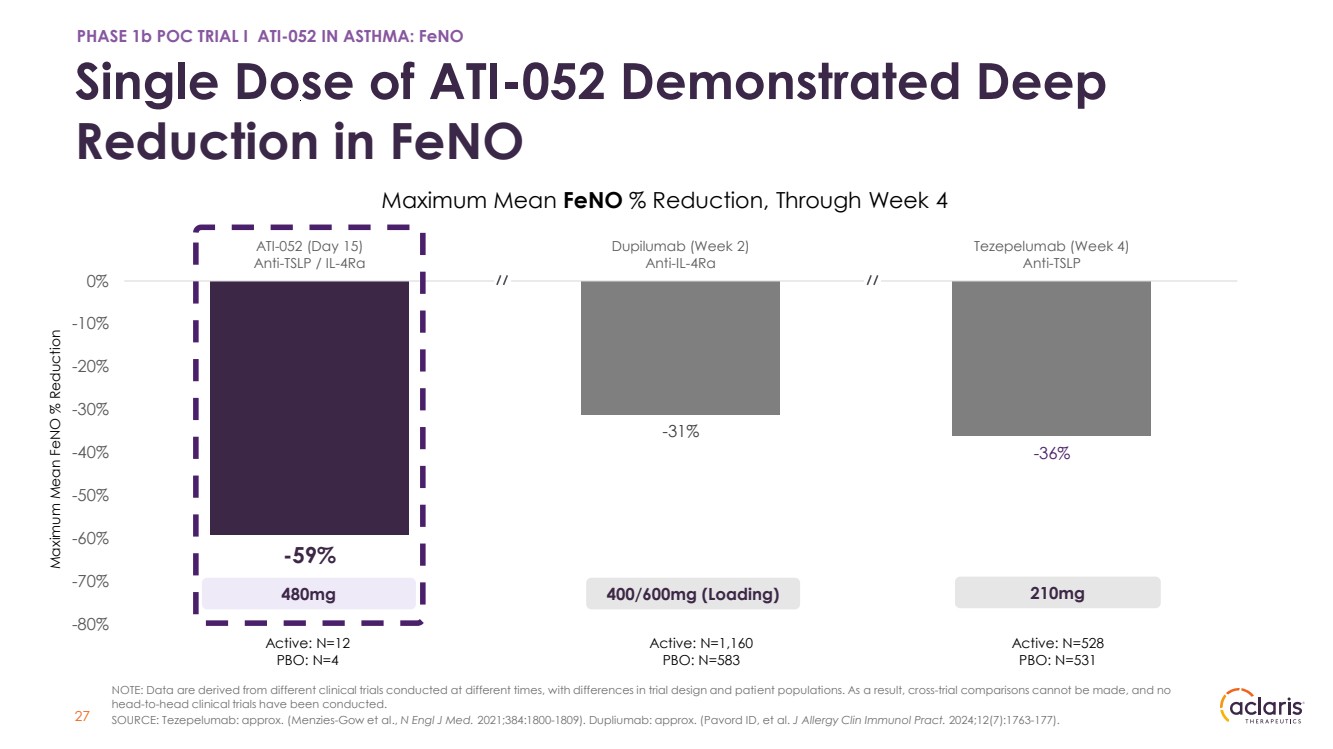
| -59% -31% -36% -80% -70% -60% -50% -40% -30% -20% -10% 0% ATI-052 (Day 15) Anti-TSLP / IL-4Rα Dupilumab (Week 2) Anti-IL-4Rα Tezepelumab (Week 4) Anti-TSLP Single Dose of ATI-052 Demonstrated Deep Reduction in FeNO PHASE 1b POC TRIAL I ATI-052 IN ASTHMA: FeNO Maximum Mean FeNO % Reduction, Through Week 4 27 NOTE: Data are derived from different clinical trials conducted at different times, with differences in trial design and patient populations. As a result, cross-trial comparisons cannot be made, and no head-to-head clinical trials have been conducted. 480mg 400/600mg (Loading) 210mg Maximum Mean FeNO % Reduction SOURCE: Tezepelumab: approx. (Menzies-Gow et al., N Engl J Med. 2021;384:1800-1809). Dupliumab: approx. (Pavord ID, et al. J Allergy Clin Immunol Pract. 2024;12(7):1763-177). Active: N=1,160 PBO: N=583 Active: N=528 PBO: N=531 Active: N=12 PBO: N=4 |
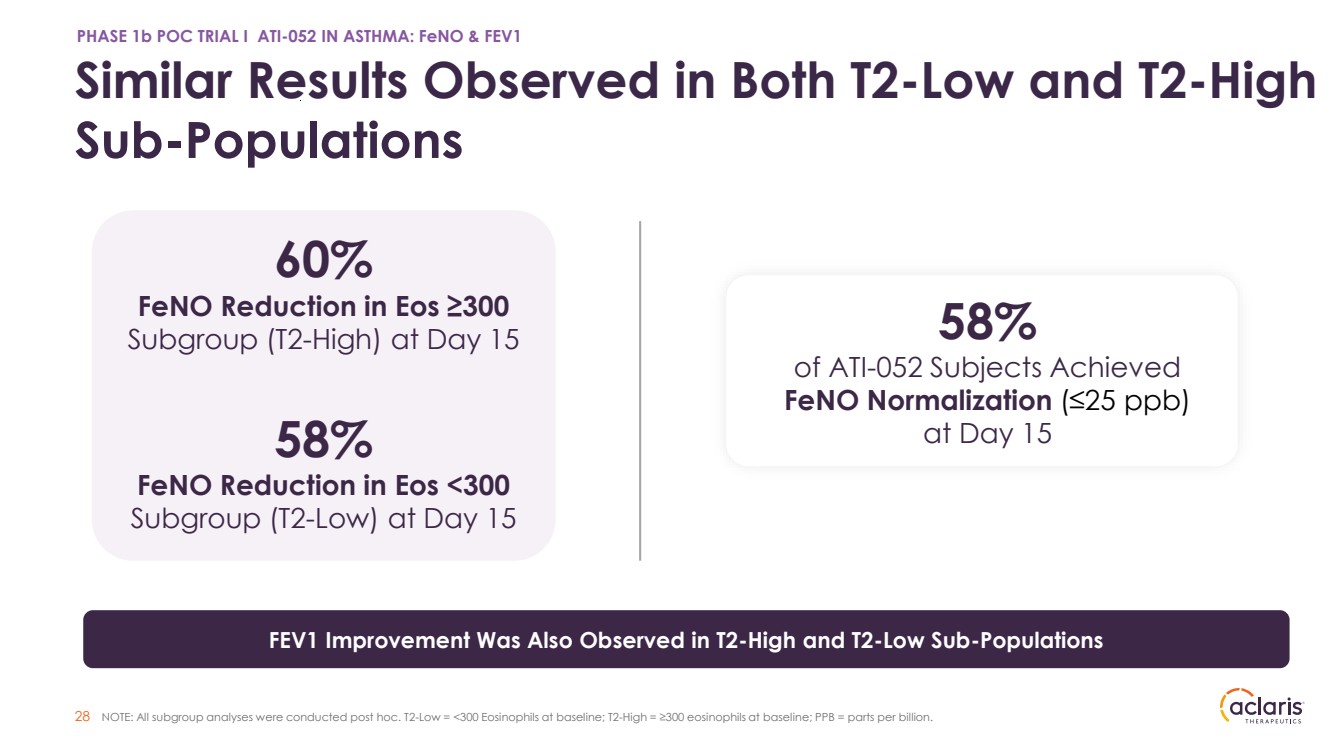
| Similar Results Observed in Both T2-Low and T2-High Sub-Populations PHASE 1b POC TRIAL I ATI-052 IN ASTHMA: FeNO & FEV1 28 NOTE: All subgroup analyses were conducted post hoc. T2-Low = <300 Eosinophils at baseline; T2-High = ≥300 eosinophils at baseline; PPB = parts per billion. 58% of ATI-052 Subjects Achieved FeNO Normalization (≤25 ppb) at Day 15 60% FeNO Reduction in Eos ≥300 Subgroup (T2-High) at Day 15 58% FeNO Reduction in Eos <300 Subgroup (T2-Low) at Day 15 FEV1 Improvement Was Also Observed in T2-High and T2-Low Sub-Populations |
| -200 mL -100 mL +0 mL +100 mL +200 mL Baseline Day 8 Day 15 Day 29 Mean pre-BD FEV1 change from baseline (mL) ATI-052 Placebo FEV1 Improvement Over Time FEV1 Improvement at Day 15 in Subjects with FEV1 <80% at Baseline +350 mL -140 mL -200 mL -100 mL +0 mL +100 mL +200 mL +300 mL +400 mL ATI-052 (FEV1 <80% at BL) Placebo (FEV1 <80% at BL) 29 NOTE: All subgroup analyses were conducted post hoc. FEV1 <80% at Baseline = pre-BD FEV1 value of < 80% at baseline + post-BD reversibility of FEV1 ≥ 12% and ≥ 200 mL or documented history of post-BD FEV1 reversibility during last 12 months at screening. BD = bronchodilator; FEV1 = Forced expiratory volume in 1 second; PBO = placebo; BL = baseline. FEV1 Improvement Aligned with FeNO Suppression; Strong Signal and Proof-of-Concept PHASE 1b POC TRIAL I ATI-052 IN ASTHMA: FEV1 Rapid FEV1 Improvement Observed Single Dose of ATI-052 Increased Absolute and Pbo-Adjusted FEV1 Pbo-adjusted: +200 mL Mean pre-BD FEV1 change from baseline (mL) |
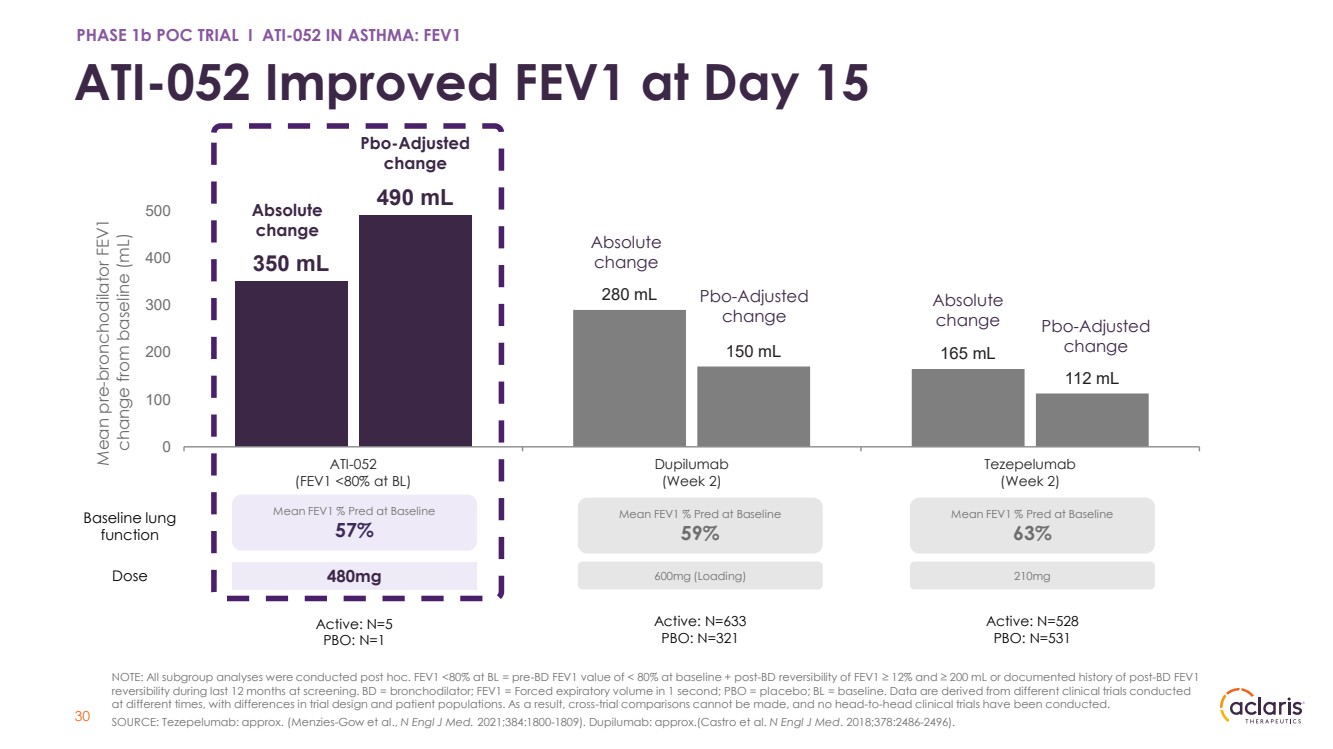
| PHASE 1b POC TRIAL I ATI-052 IN ASTHMA: FEV1 SOURCE: Tezepelumab: approx. (Menzies-Gow et al., N Engl J Med. 2021;384:1800-1809). Dupilumab: approx.(Castro et al. N Engl J Med. 2018;378:2486-2496). NOTE: All subgroup analyses were conducted post hoc. FEV1 <80% at BL = pre-BD FEV1 value of < 80% at baseline + post-BD reversibility of FEV1 ≥ 12% and ≥ 200 mL or documented history of post-BD FEV1 reversibility during last 12 months at screening. BD = bronchodilator; FEV1 = Forced expiratory volume in 1 second; PBO = placebo; BL = baseline. Data are derived from different clinical trials conducted at different times, with differences in trial design and patient populations. As a result, cross-trial comparisons cannot be made, and no head-to-head clinical trials have been conducted. ATI-052 Improved FEV1 at Day 15 350 mL 280 mL 165 mL 490 mL 150 mL 112 mL 0 100 200 300 400 500 ATI-052 (FEV1 <80% at BL) Dupilumab (Week 2) Tezepelumab (Week 2) Mean pre-bronchodilator FEV1 change from baseline (mL) Mean FEV1 % Pred at Baseline 63% Mean FEV1 % Pred at Baseline 59% Mean FEV1 % Pred at Baseline 57% 480mg 600mg (Loading) 210mg Baseline lung function Dose Active: N=633 PBO: N=321 Active: N=528 PBO: N=531 Active: N=5 PBO: N=1 Absolute change Pbo-Adjusted change Absolute change Pbo-Adjusted change Absolute change Pbo-Adjusted change 30 |
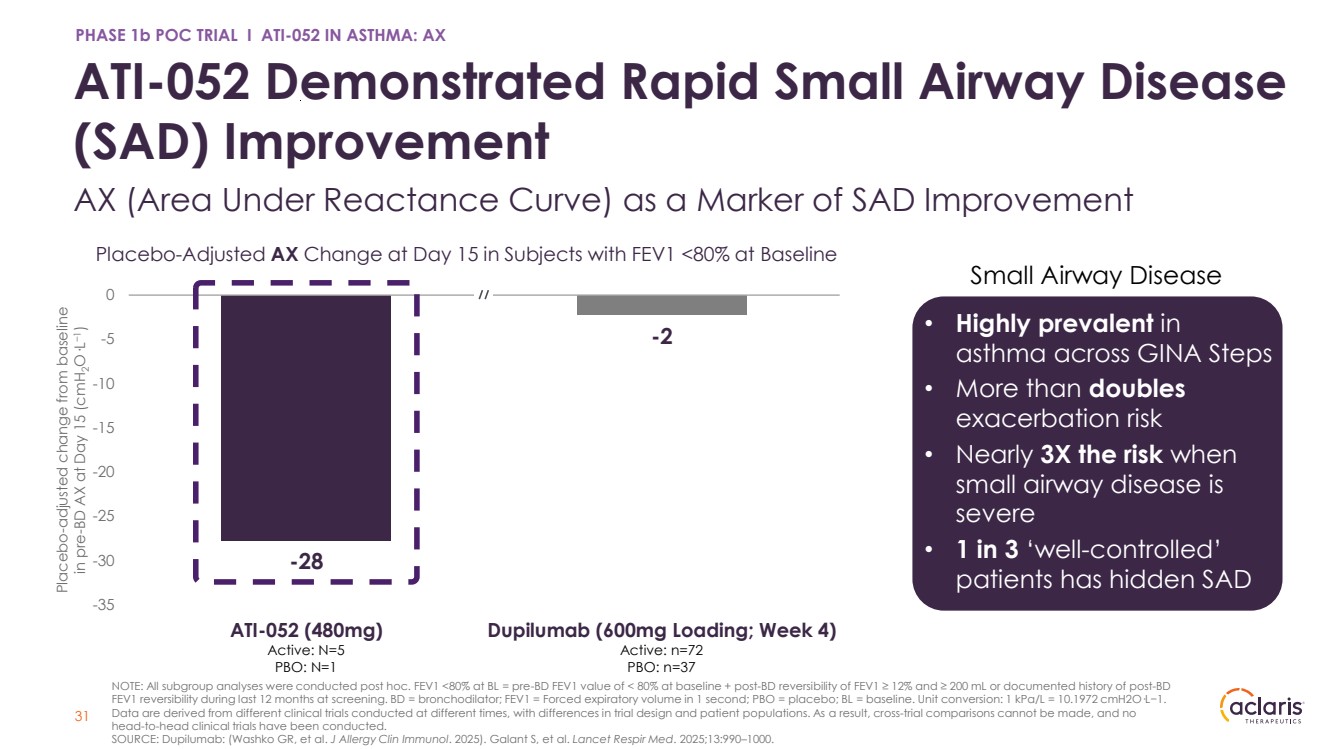
| -28 -2 -35 -30 -25 -20 -15 -10 -5 0 ATI-052 (480mg) Dupilumab (600mg Loading; Week 4) Placebo-adjusted change from baseline in pre-BD AX at Day 15 (cmH O·L 2 −1 ) 31 PHASE 1b POC TRIAL I ATI-052 IN ASTHMA: AX ATI-052 Demonstrated Rapid Small Airway Disease (SAD) Improvement AX (Area Under Reactance Curve) as a Marker of SAD Improvement • Highly prevalent in asthma across GINA Steps • More than doubles exacerbation risk • Nearly 3X the risk when small airway disease is severe • 1 in 3 ‘well-controlled’ patients has hidden SAD NOTE: All subgroup analyses were conducted post hoc. FEV1 <80% at BL = pre-BD FEV1 value of < 80% at baseline + post-BD reversibility of FEV1 ≥ 12% and ≥ 200 mL or documented history of post-BD FEV1 reversibility during last 12 months at screening. BD = bronchodilator; FEV1 = Forced expiratory volume in 1 second; PBO = placebo; BL = baseline. Unit conversion: 1 kPa/L = 10.1972 cmH2O·L−1. Data are derived from different clinical trials conducted at different times, with differences in trial design and patient populations. As a result, cross-trial comparisons cannot be made, and no head-to-head clinical trials have been conducted. SOURCE: Dupilumab: (Washko GR, et al. J Allergy Clin Immunol. 2025). Galant S, et al. Lancet Respir Med. 2025;13:990–1000. Placebo-Adjusted AX Change at Day 15 in Subjects with FEV1 <80% at Baseline Active: N=5 PBO: N=1 Active: n=72 PBO: n=37 Small Airway Disease |
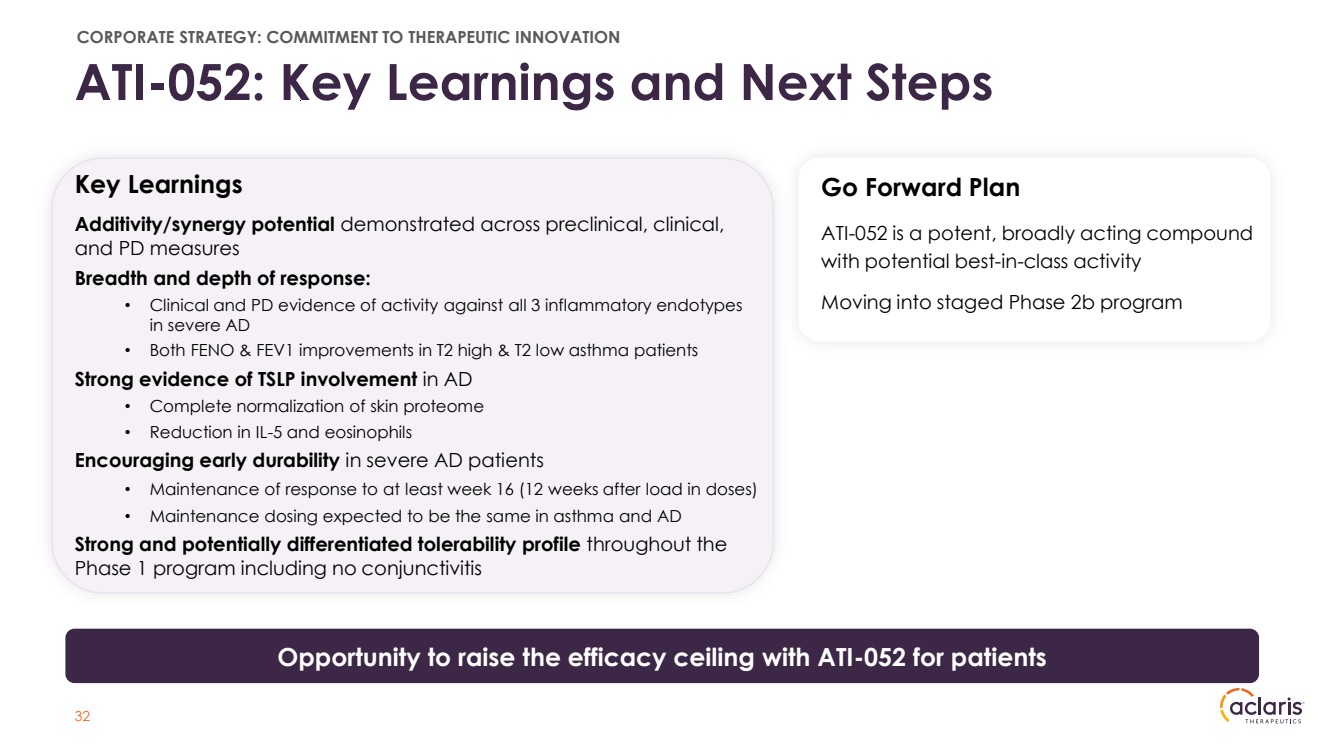
| Key Learnings Additivity/synergy potential demonstrated across preclinical, clinical, and PD measures Breadth and depth of response: • Clinical and PD evidence of activity against all 3 inflammatory endotypes in severe AD • Both FENO & FEV1 improvements in T2 high & T2 low asthma patients Strong evidence of TSLP involvement in AD • Complete normalization of skin proteome • Reduction in IL-5 and eosinophils Encouraging early durability in severe AD patients • Maintenance of response to at least week 16 (12 weeks after load in doses) • Maintenance dosing expected to be the same in asthma and AD Strong and potentially differentiated tolerability profile throughout the Phase 1 program including no conjunctivitis 32 ATI-052: Key Learnings and Next Steps Go Forward Plan ATI-052 is a potent, broadly acting compound with potential best-in-class activity Moving into staged Phase 2b program CORPORATE STRATEGY: COMMITMENT TO THERAPEUTIC INNOVATION Opportunity to raise the efficacy ceiling with ATI-052 for patients |
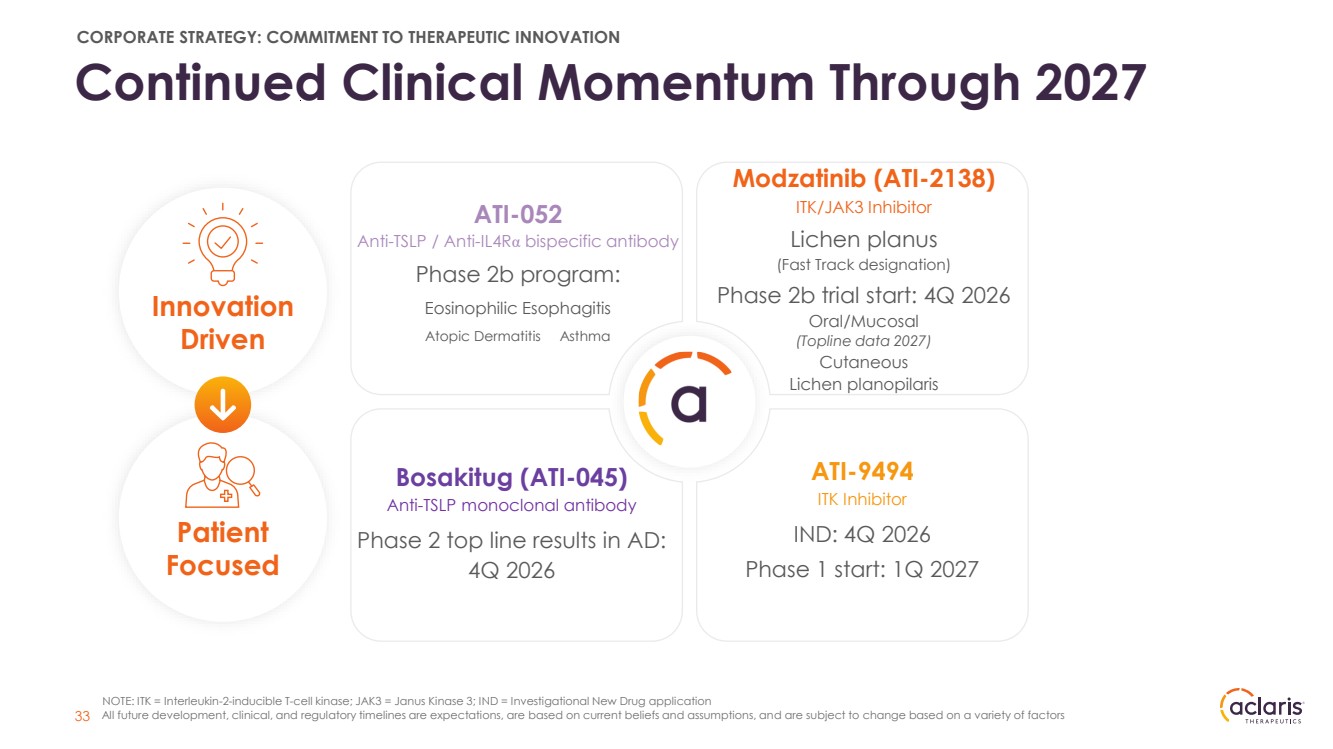
| Continued Clinical Momentum Through 2027 Bosakitug (ATI-045) Anti-TSLP monoclonal antibody Phase 2 top line results in AD: 4Q 2026 ATI-052 Anti-TSLP / Anti-IL4Rα bispecific antibody Phase 2b program: Eosinophilic Esophagitis Atopic Dermatitis Asthma Modzatinib (ATI-2138) ITK/JAK3 Inhibitor Lichen planus (Fast Track designation) Phase 2b trial start: 4Q 2026 Oral/Mucosal (Topline data 2027) Cutaneous Lichen planopilaris ATI-9494 ITK Inhibitor IND: 4Q 2026 Phase 1 start: 1Q 2027 Innovation Driven Patient Focused 33 All future development, clinical, and regulatory timelines are expectations, are based on current beliefs and assumptions, and are subject to change based on a variety of factors CORPORATE STRATEGY: COMMITMENT TO THERAPEUTIC INNOVATION NOTE: ITK = Interleukin-2-inducible T-cell kinase; JAK3 = Janus Kinase 3; IND = Investigational New Drug application |
| EMPOWERING PATIENTS THROUGH THERAPEUTIC INNOVATION October 27, 2026 ATI-052 Phase 1b Primary Analysis Results Atopic Dermatitis and Asthma |