
Exhibit 99.2 PDAC Investor Presentation October 23, 2026

Disclaimer and safe harbor statement Certain statements in this presentation may be considered forward-looking statements. All statements other than statements of historical fact are statements that could be deemed forward-looking statements, including all statements regarding the intent, belief, or current expectation of Tango Therapeutics, Inc. (Tango) and members of the Tango senior management team. Forward-looking statements are not purely historical and may be accompanied by terminology such as “may”, “should”, “expect”, “intend”, “will”, “plan”, “path”, “achievable”, “milestones”, “goal”, “forecast”, “estimate”, “potential”, “anticipate”, “believe”, “predict”, or “continue”, or the negatives of these terms or variations of them or similar terminology. For example, express or implied statements concerning the following include or constitute forward-looking statements: the potential anticipated benefits, tolerability, efficacy and therapeutic profile of Tango's PRMT5 inhibitors, as both standalone treatments and in combination with RAS(ON)-inhibitors; Tango’s belief that it has a competitive advantage; Tango’s regulatory plans and expectations, including its expectation that the combination of vopimetostat and RAS inhibitors could (i) support a pivotal study in first line pancreatic cancer and an innovative and fast path to potential first line approvals and accelerated second line approval for pancreatic cancer and (ii) inform Tango’s development strategy in MTAP wild-type pancreatic cancer and other cancers; Tango’s expected cash runway; Tango’s plans for future trials and clinical milestones, including combination trials, and the design, initiation and the release of clinical data, and timing related thereto, for vopimetostat and TNG456, including with RAS(ON) inhibitors for vopimetostat; Tango’s expectations regarding its ability to secure sufficient clinical supply of daraxonrasib for its planned Phase 3 clinical trial evaluating vopimetostat with daraxonrasib; Tango’s expectations around regulatory communications and decisions related to its product candidates and clinical trials (including combination studies), including interactions with the U.S. Food and Drug Administration (FDA) and other regulatory authorities; the expected benefits of Tango’s development candidates and other product candidates (including for combination studies); Tango’s expectations around the size and value of the potential patient population for PRMT5 inhibitors (including for pancreatic cancers); potential market opportunity for Tango’s product candidates, if approved; potential combination strategies and uses for PRMT5 inhibitors, including vopimetostat and TNG456; and the development and regulatory plans for the PRMT5 franchise, including potential expansion into MTAP wild type tumors and other cancers. Such forward-looking statements are subject to risks, uncertainties, and other factors which could cause actual results to differ materially from those expressed or implied by such forward looking statements. These forward-looking statements are based upon estimates and assumptions that, while considered reasonable by Tango and its management at the time of this presentation, are inherently uncertain. New risks and uncertainties may emerge from time to time, and it is not possible to predict all risks and uncertainties. Factors that may cause actual results to differ materially from current expectations include, but are not limited to: the benefits of product candidates seen in preclinical tests and analyses and clinical trials may not be evident when tested in later preclinical studies or in clinical trials or when used in broader patient populations (if approved for commercial sale); future clinical trial data releases may differ materially from initial, interim, updated, or final data from Tango’s current and future clinical trials; Tango has limited experience with conducting clinical trials (and does and will rely on third parties to operate its clinical trials) and may not be able to commence or progress its clinical trials when expected, may not be able to continue dosing, initiate dose escalation and/or dose expansion on anticipated timelines (or at all), and may not generate or report clinical trial results (including final, initial, interim, updated clinical trial results or additional safety and efficacy data and the establishment of proof-of-mechanism and proof-of-concept) in the anticipated timeframe (or at all); Tango’s pipeline products may not be safe and/or effective in humans; Tango may utilize cash resources more quickly than anticipated; Tango will need to raise capital in the future and if it is unable to raise capital when needed or on attractive terms (or at all), Tango would be forced to delay, reduce, or eliminate or discontinue some development programs or future commercialization efforts (which may delay filing of investigational new drug applications, dosing patients, initiation of dose expansion, reporting clinical trial results and filing new drug applications); the expected benefits of Tango’s product candidates in patients as single agents and/or in combination may not be realized; Tango may experience delays or difficulties in the initiation, enrollment, or dosing of patients in clinical trials or the announcement of initial, interim, or final clinical trial results; Tango’s product candidates may cause adverse or other undesirable side effects (or may not show requisite efficacy) that could, among other things, delay or prevent regulatory approval; Tango’s dependence on or a limited number third parties for conducting clinical trials and supplying and producing drug substance and drug product (including drug substance, which is currently sole sourced); Tango’s ability to enter into additional collaboration and supply agreements and to acquire, license, or otherwise obtain rights to additional products, product candidates, or molecules; government regulation may negatively impact Tango's business, including the potential approval of the BIOSECURE Act; the impact of trade restrictions such as sanctions, tariffs, reciprocal and retaliatory tariffs, legal actions or enforcement and inflation or interest rates on Tango’s business, financial condition, and results of operations; inadequate funding for or disruptions at the FDA or other government agencies may slow the time necessary for new drugs to be reviewed and/or approved or prevent these agencies from performing business functions on which the operation of Tango’s business may rely (which could negatively impact Tango’s business). Additional information concerning risks, uncertainties and assumptions can be found in Tango’s filings with the U.S. Securities and Exchange Commission (SEC), including the risk factors referenced in Tango’s Annual Report on Form 10-K for the year ended December 31, 2025, as may be supplemented and/or modified by its most recent Quarterly Report on Form 10-Q or other filings Tango may make with the SEC from time to time. You should not place undue reliance on forward-looking statements in this presentation, which speak only as of the date they are made and are qualified in their entirety by reference to the cautionary statements herein. Tango specifically disclaims any duty to update these forward-looking statements. Certain information contained in this Presentation relates to or is based on studies, publications, surveys and Tango’s own internal estimates and research. In addition, market data included in this presentation involve assumptions and limitations, and there can be no guarantee as to the accuracy or reliability of such assumption. Finally, while Tango believes its internal research is reliable, such research has not been verified by any independent source.

Agenda for today Introduction Malte Peters, MD | President and Chief Executive Officer Vopimetostat + daraxonrasib combination data update Brian Wolpin, MD | Dana-Farber Cancer Institute & Harvard Medical School Vopimetostat registration and expansion strategy in PDAC Adam Crystal, MD, PhD | President of Research and Development Malte Peters, MD Brian Wolpin, MD, MPH Upcoming milestones and financial highlights Matthew Gall | Chief Financial Officer Conclusion Malte Peters | Chief Executive Officer Q&A Adam Crystal, MD, PhD Matthew Gall All 3

Introduction Malte Peters, MD, President and Chief Executive Officer 4
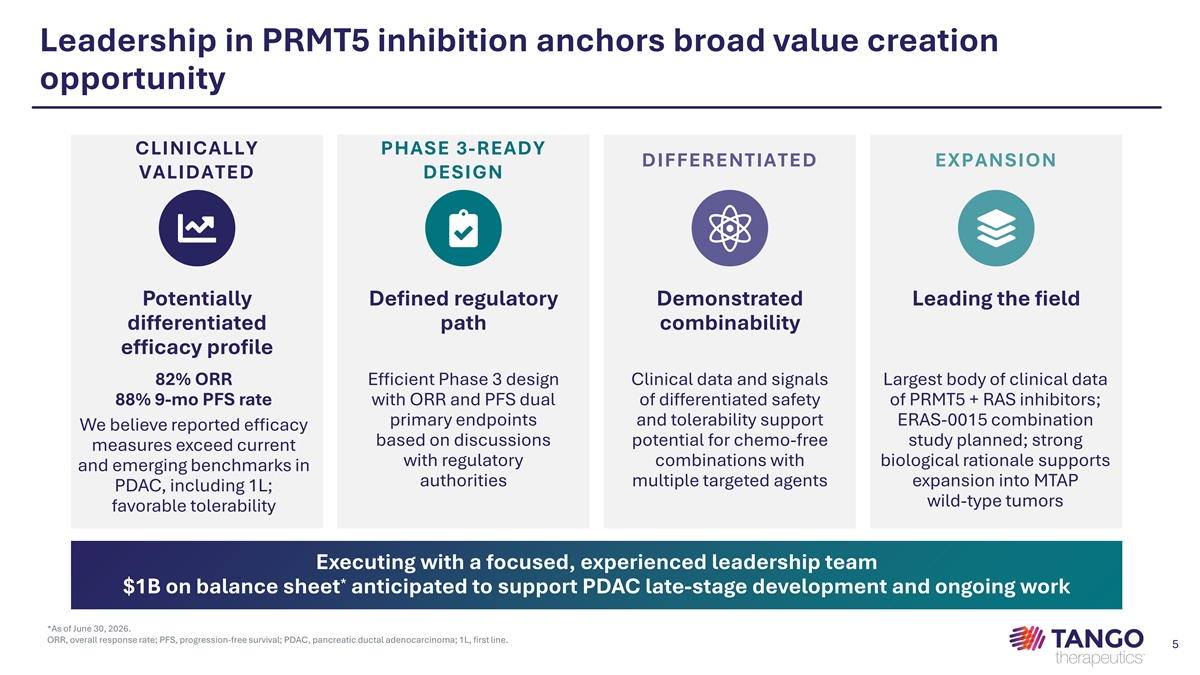
Leadership in PRMT5 inhibition anchors broad value creation opportunity CLINICALLY PHASE 3-READY DIFFERENTIATED EXPANSION VALIDATED DESIGN Potentially Defined regulatory Demonstrated Leading the field differentiated path combinability efficacy profile 82% ORR Efficient Phase 3 design Clinical data and signals Largest body of clinical data 88% 9-mo PFS rate with ORR and PFS dual of differentiated safety of PRMT5 + RAS inhibitors; primary endpoints and tolerability support ERAS-0015 combination We believe reported efficacy based on discussions potential for chemo-free study planned; strong measures exceed current with regulatory combinations with biological rationale supports and emerging benchmarks in authorities multiple targeted agents expansion into MTAP PDAC, including 1L; wild-type tumors favorable tolerability Executing with a focused, experienced leadership team * $1B on balance sheet anticipated to support PDAC late-stage development and ongoing work *As of June 30, 2026. ORR, overall response rate; PFS, progression-free survival; PDAC, pancreatic ductal adenocarcinoma; 1L, first line. 5
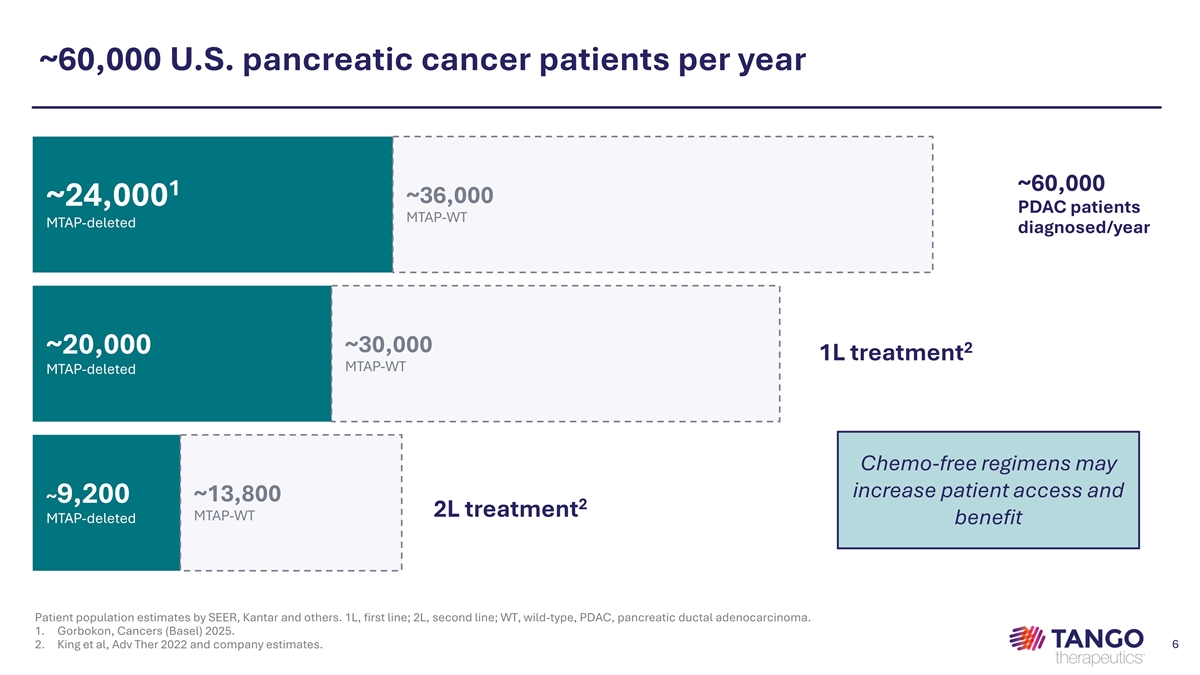
~60,000 U.S. pancreatic cancer patients per year ~60,000 1 ~36,000 ~24,000 PDAC patients MTAP-WT MTAP-deleted diagnosed/year ~30,000 2 ~20,000 1L treatment MTAP-WT MTAP-deleted Chemo-free regimens may increase patient access and ~13,800 ~9,200 2 2L treatment MTAP-WT MTAP-deleted benefit Patient population estimates by SEER, Kantar and others. 1L, first line; 2L, second line; WT, wild-type, PDAC, pancreatic ductal adenocarcinoma. 1. Gorbokon, Cancers (Basel) 2025. 2. King et al, Adv Ther 2022 and company estimates. 6

Brian Wolpin is a leader in the study and treatment of pancreatic cancer v Professor of Medicine, Harvard Medical School v Robert T. & Judith B. Hale Chair in Pancreatic Cancer, Dana-Farber Cancer Institute v Director, Hale Family Center for Pancreatic Cancer Research and Gastrointestinal Cancer Center, Dana-Farber Cancer Institute v Director, Dana-Farber – Lustgarten Foundation Dedicated Laboratory for Pancreatic Cancer Research v Medical oncologist with clinical specialty in pancreatic cancer v Research laboratory dedicated to the investigation of pancreatic ductal adenocarcinoma (PDAC) biology and treatment 7

Vopimetostat + daraxonrasib combination data update Brian Wolpin, MD, MPH Dana-Farber Cancer Institute & Harvard Medical School 8
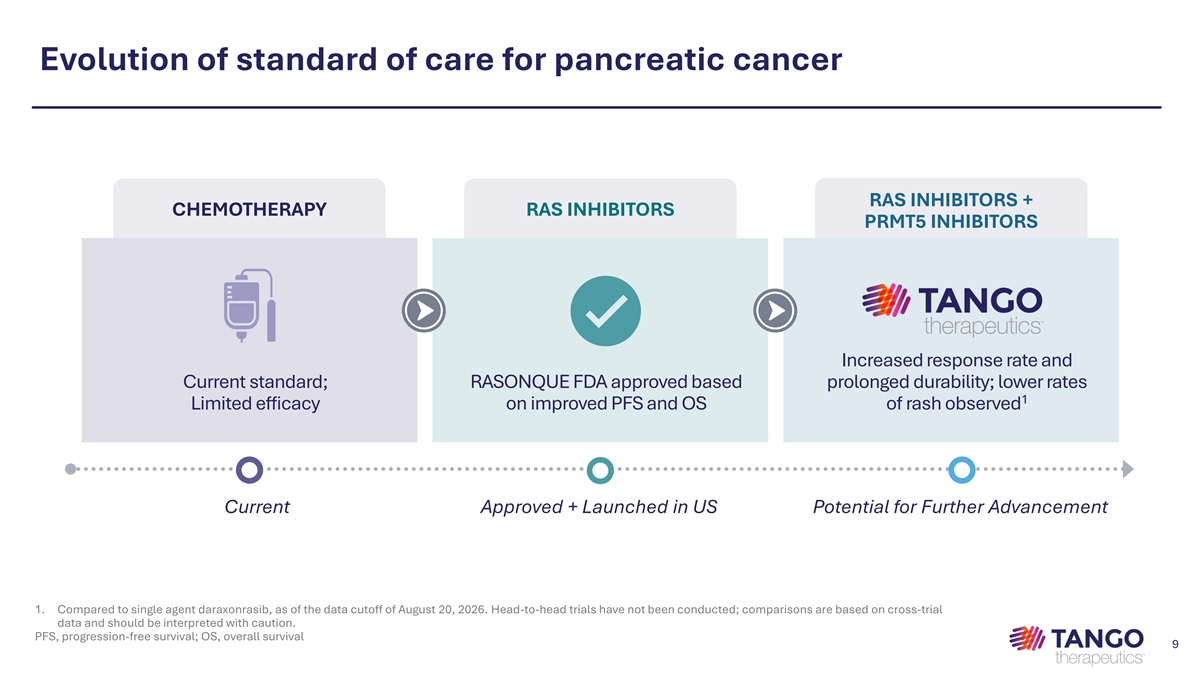
Evolution of standard of care for pancreatic cancer RAS INHIBITORS + CHEMOTHERAPY RAS INHIBITORS PRMT5 INHIBITORS Increased response rate and Current standard; RASONQUE FDA approved based prolonged durability; lower rates 1 Limited efficacy on improved PFS and OS of rash observed Current Approved + Launched in US Potential for Further Advancement 1. Compared to single agent daraxonrasib, as of the data cutoff of August 20, 2026. Head-to-head trials have not been conducted; comparisons are based on cross-trial data and should be interpreted with caution. PFS, progression-free survival; OS, overall survival 9
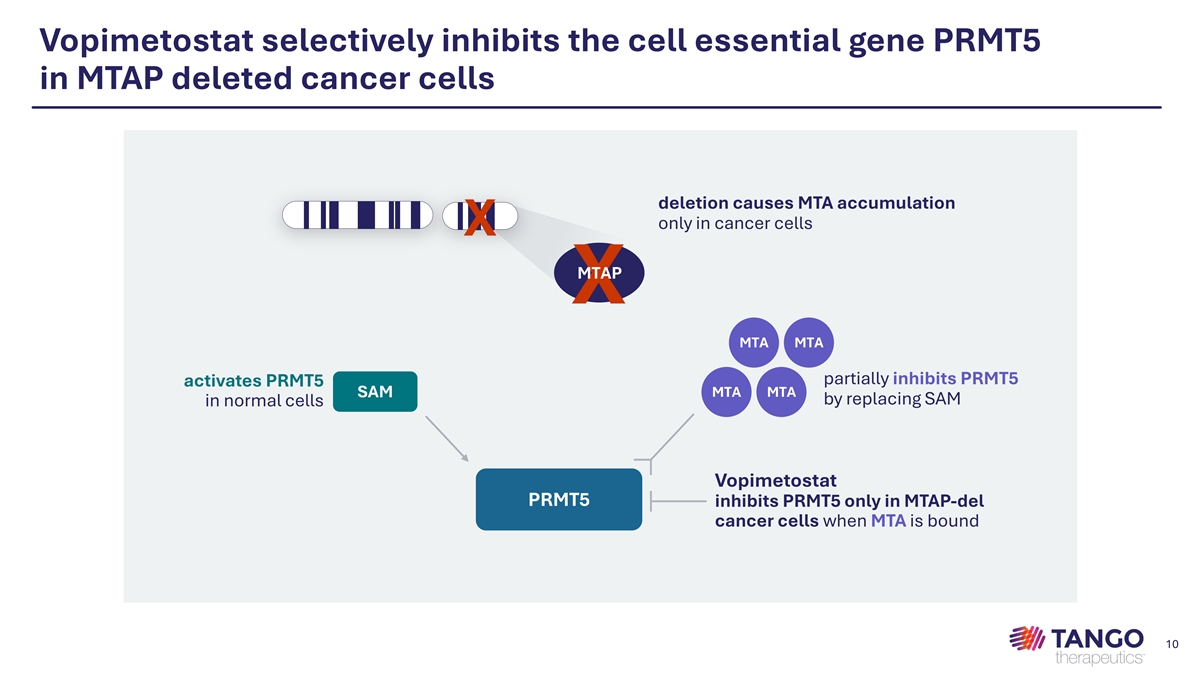
Vopimetostat selectively inhibits the cell essential gene PRMT5 in MTAP deleted cancer cells deletion causes MTA accumulation only in cancer cells X MTAP X MTA MTA partially inhibits PRMT5 activates PRMT5 SAM MTA MTA by replacing SAM in normal cells Vopimetostat PRMT5 inhibits PRMT5 only in MTAP-del cancer cells when MTA is bound 10
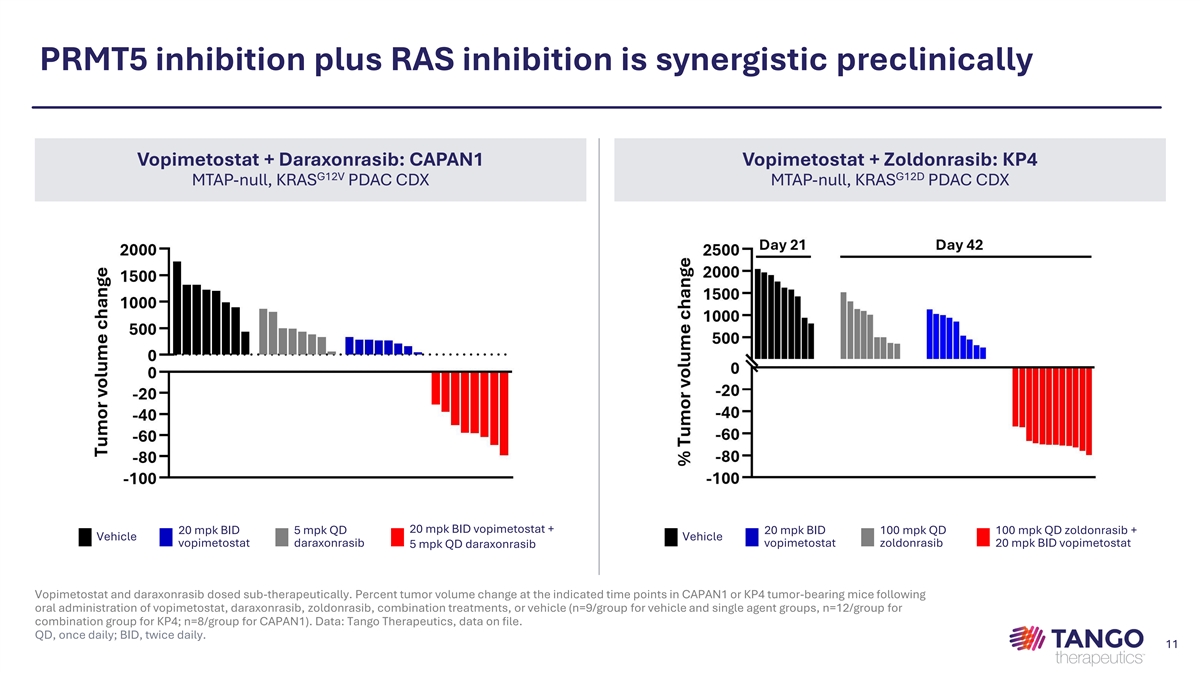
PRMT5 inhibition plus RAS inhibition is synergistic preclinically Vopimetostat + Daraxonrasib: CAPAN1 Vopimetostat + Zoldonrasib: KP4 G12V G12D MTAP-null, KRAS PDAC CDX MTAP-null, KRAS PDAC CDX 20 mpk BID vopimetostat + 20 mpk BID 5 mpk QD 20 mpk BID 100 mpk QD 100 mpk QD zoldonrasib + Vehicle Vehicle vopimetostat daraxonrasib vopimetostat zoldonrasib 20 mpk BID vopimetostat 5 mpk QD daraxonrasib Vopimetostat and daraxonrasib dosed sub-therapeutically. Percent tumor volume change at the indicated time points in CAPAN1 or KP4 tumor-bearing mice following oral administration of vopimetostat, daraxonrasib, zoldonrasib, combination treatments, or vehicle (n=9/group for vehicle and single agent groups, n=12/group for combination group for KP4; n=8/group for CAPAN1). Data: Tango Therapeutics, data on file. 11 QD, once daily; BID, twice daily. 11
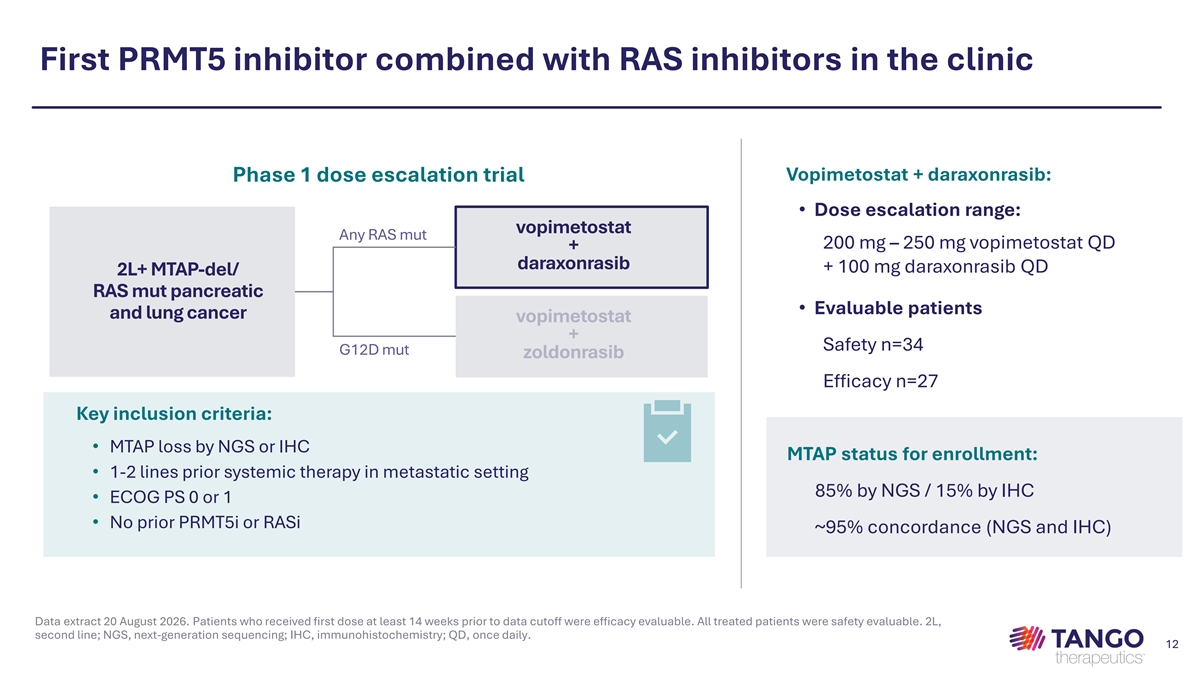
First PRMT5 inhibitor combined with RAS inhibitors in the clinic Vopimetostat + daraxonrasib: Phase 1 dose escalation trial • Dose escalation range: vopimetostat Any RAS mut 200 mg – 250 mg vopimetostat QD + daraxonrasib + 100 mg daraxonrasib QD 2L+ MTAP-del/ RAS mut pancreatic • Evaluable patients and lung cancer vopimetostat + Safety n=34 G12D mut zoldonrasib Efficacy n=27 Key inclusion criteria: • MTAP loss by NGS or IHC MTAP status for enrollment: • 1-2 lines prior systemic therapy in metastatic setting 85% by NGS / 15% by IHC • ECOG PS 0 or 1 • No prior PRMT5i or RASi ~95% concordance (NGS and IHC) Data extract 20 August 2026. Patients who received first dose at least 14 weeks prior to data cutoff were efficacy evaluable. All treated patients were safety evaluable. 2L, second line; NGS, next-generation sequencing; IHC, immunohistochemistry; QD, once daily. 12
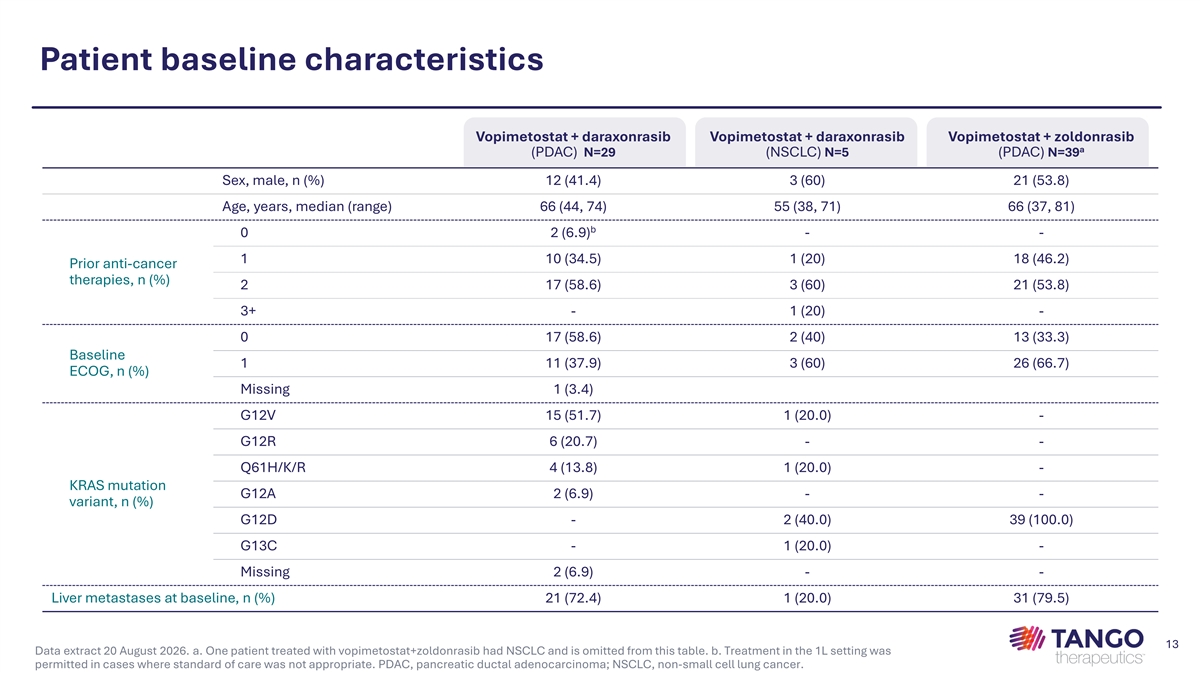
Patient baseline characteristics Vopimetostat + daraxonrasib Vopimetostat + daraxonrasib Vopimetostat + zoldonrasib a (PDAC) N=29 (NSCLC) N=5 (PDAC) N=39 Sex, male, n (%) 12 (41.4) 3 (60) 21 (53.8) Age, years, median (range) 66 (44, 74) 55 (38, 71) 66 (37, 81) b 0 2 (6.9) - - 1 10 (34.5) 1 (20) 18 (46.2) Prior anti-cancer therapies, n (%) 2 17 (58.6) 3 (60) 21 (53.8) 3+ - 1 (20) - 0 17 (58.6) 2 (40) 13 (33.3) Baseline 1 11 (37.9) 3 (60) 26 (66.7) ECOG, n (%) Missing 1 (3.4) G12V 15 (51.7) 1 (20.0) - G12R 6 (20.7) - - Q61H/K/R 4 (13.8) 1 (20.0) - KRAS mutation G12A 2 (6.9) - - variant, n (%) G12D - 2 (40.0) 39 (100.0) G13C - 1 (20.0) - Missing 2 (6.9) - - Liver metastases at baseline, n (%) 21 (72.4) 1 (20.0) 31 (79.5) 13 Data extract 20 August 2026. a. One patient treated with vopimetostat+zoldonrasib had NSCLC and is omitted from this table. b. Treatment in the 1L setting was permitted in cases where standard of care was not appropriate. PDAC, pancreatic ductal adenocarcinoma; NSCLC, non-small cell lung cancer.
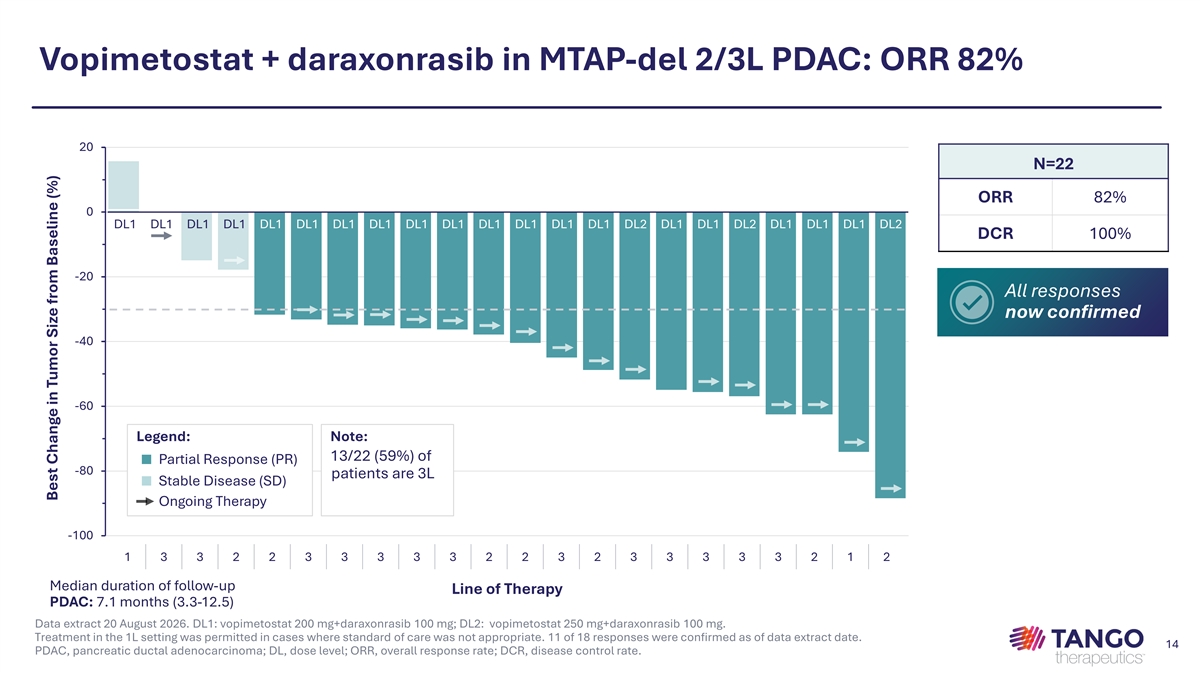
Vopimetostat + daraxonrasib in MTAP-del 2/3L PDAC: ORR 82% 20 N=22 ORR 82% 0 DL1 DL1 DL1 DL1 DL1 DL1 DL1 DL1 DL1 DL1 DL1 DL1 DL1 DL1 DL2 DL1 DL1 DL2 DL1 DL1 DL1 DL2 DCR 100% -20 All responses now confirmed -40 -60 Legend: Note: 13/22 (59%) of ■ Partial Response (PR) -80 patients are 3L ■ Stable Disease (SD) Ongoing Therapy -100 1 3 3 2 2 3 3 3 3 3 2 2 3 2 3 3 3 3 3 2 1 2 Median duration of follow-up Line of Therapy PDAC: 7.1 months (3.3-12.5) Data extract 20 August 2026. DL1: vopimetostat 200 mg+daraxonrasib 100 mg; DL2: vopimetostat 250 mg+daraxonrasib 100 mg. Treatment in the 1L setting was permitted in cases where standard of care was not appropriate. 11 of 18 responses were confirmed as of data extract date. 14 PDAC, pancreatic ductal adenocarcinoma; DL, dose level; ORR, overall response rate; DCR, disease control rate. Best Change in Tumor Size from Baseline (%)
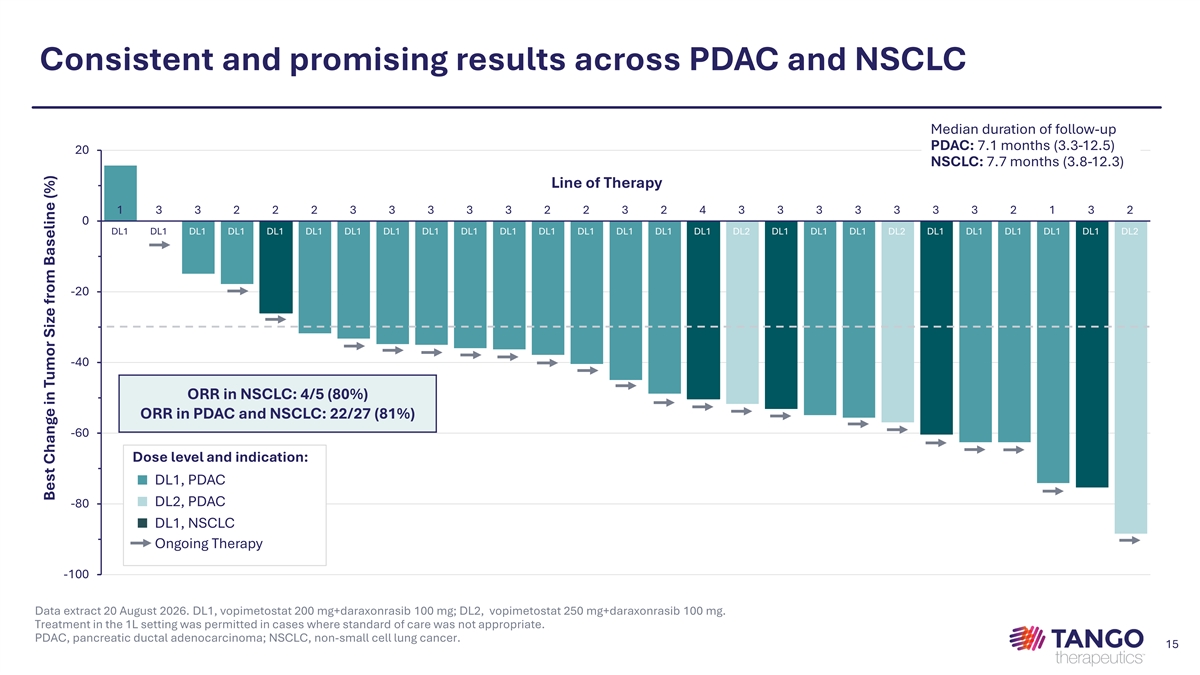
Consistent and promising results across PDAC and NSCLC Median duration of follow-up PDAC: 7.1 months (3.3-12.5) 20 NSCLC: 7.7 months (3.8-12.3) Line of Therapy 1 3 3 2 2 2 3 3 3 3 3 2 2 3 2 4 3 3 3 3 3 3 3 2 1 3 2 0 DL1 DL1 DL1 DL1 DL1 DL1 DL1 DL1 DL1 DL1 DL1 DL1 DL1 DL1 DL1 DL1 DL2 DL1 DL1 DL1 DL2 DL1 DL1 DL1 DL1 DL1 DL2 -20 -40 ORR in NSCLC: 4/5 (80%) ORR in PDAC and NSCLC: 22/27 (81%) -60 Dose level and indication: ■ DL1, PDAC ■ DL2, PDAC -80 ■ DL1, NSCLC Ongoing Therapy -100 Data extract 20 August 2026. DL1, vopimetostat 200 mg+daraxonrasib 100 mg; DL2, vopimetostat 250 mg+daraxonrasib 100 mg. Treatment in the 1L setting was permitted in cases where standard of care was not appropriate. PDAC, pancreatic ductal adenocarcinoma; NSCLC, non-small cell lung cancer. 15 Best Change in Tumor Size from Baseline (%)
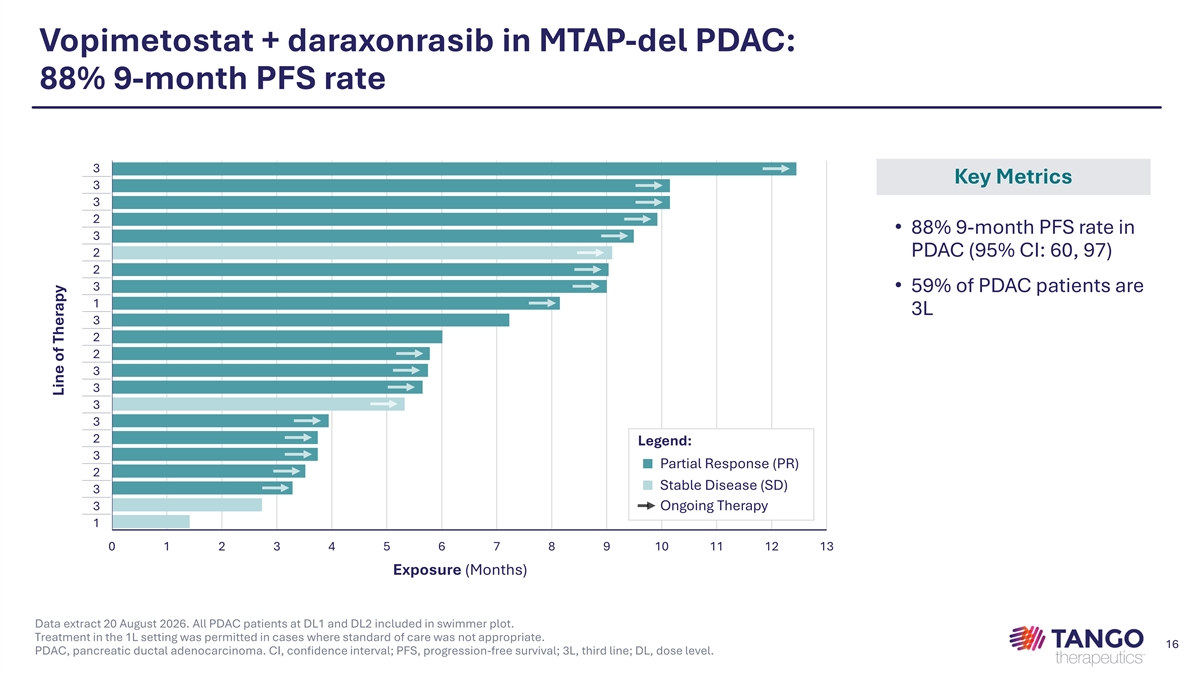
Vopimetostat + daraxonrasib in MTAP-del PDAC: 88% 9-month PFS rate 3 Key Metrics 3 3 2 • 88% 9-month PFS rate in 3 2 PDAC (95% CI: 60, 97) 2 3 • 59% of PDAC patients are 1 3L 3 2 2 3 3 3 3 2 Legend: 3 ■ Partial Response (PR) 2 ■ Stable Disease (SD) 3 3 Ongoing Therapy 1 0 1 2 3 4 5 6 7 8 9 10 11 12 13 Exposure (Months) Data extract 20 August 2026. All PDAC patients at DL1 and DL2 included in swimmer plot. Treatment in the 1L setting was permitted in cases where standard of care was not appropriate. 16 PDAC, pancreatic ductal adenocarcinoma. CI, confidence interval; PFS, progression-free survival; 3L, third line; DL, dose level. Line of Therapy
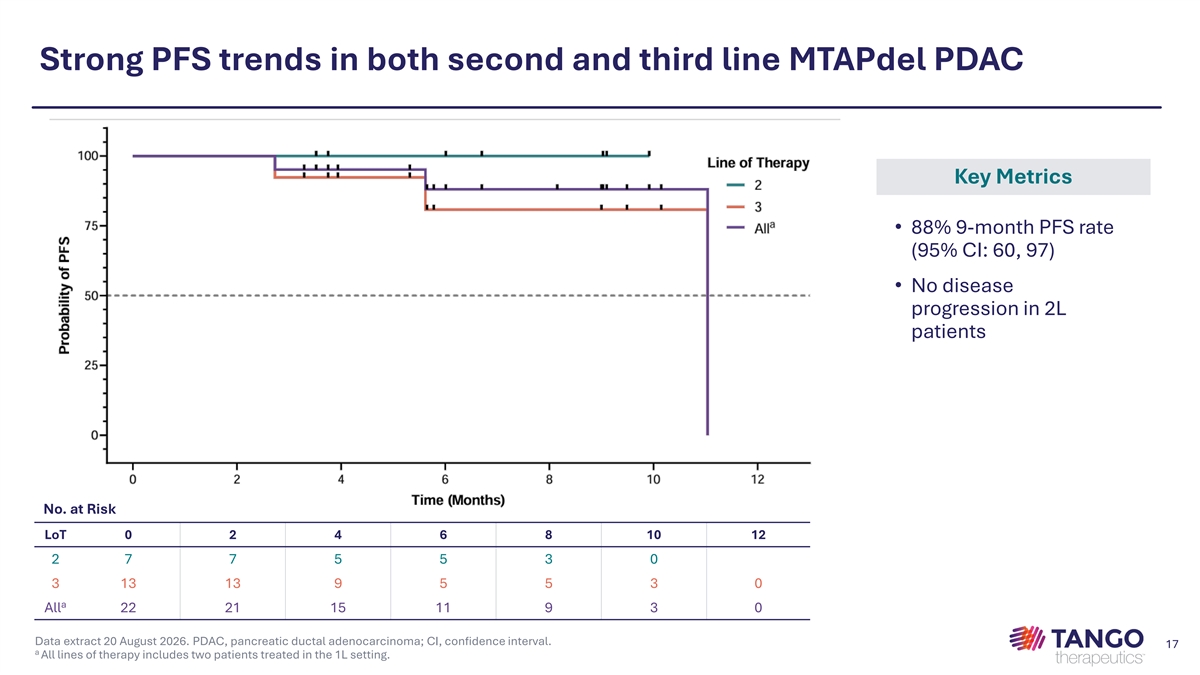
Strong PFS trends in both second and third line MTAPdel PDAC Key Metrics • 88% 9-month PFS rate (95% CI: 60, 97) • No disease progression in 2L patients No. at Risk LoT 0 2 4 6 8 10 12 2 7 7 5 5 3 0 3 13 13 9 5 5 3 0 a All 22 21 15 11 9 3 0 Data extract 20 August 2026. PDAC, pancreatic ductal adenocarcinoma; CI, confidence interval. 17 a All lines of therapy includes two patients treated in the 1L setting.
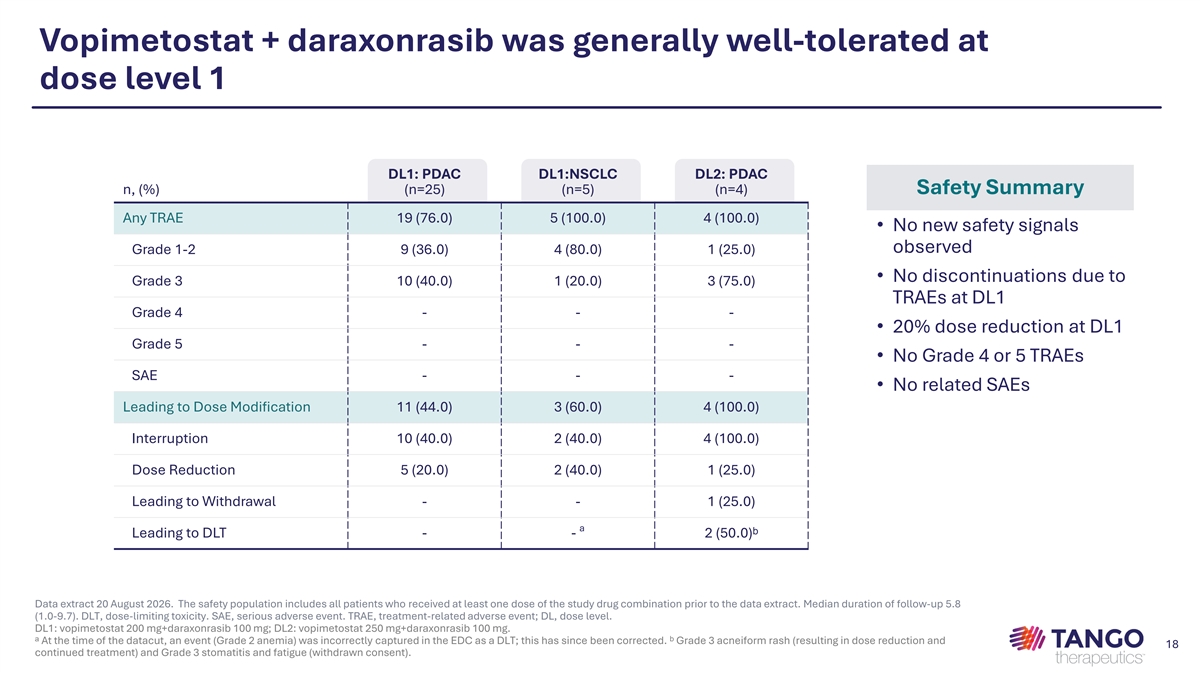
Vopimetostat + daraxonrasib was generally well-tolerated at dose level 1 DL1: PDAC DL1:NSCLC DL2: PDAC n, (%) (n=25) (n=5) (n=4) Safety Summary Any TRAE 19 (76.0) 5 (100.0) 4 (100.0) • No new safety signals observed Grade 1-2 9 (36.0) 4 (80.0) 1 (25.0) • No discontinuations due to Grade 3 10 (40.0) 1 (20.0) 3 (75.0) TRAEs at DL1 Grade 4 - - - • 20% dose reduction at DL1 Grade 5 - - - • No Grade 4 or 5 TRAEs SAE - - - • No related SAEs Leading to Dose Modification 11 (44.0) 3 (60.0) 4 (100.0) Interruption 10 (40.0) 2 (40.0) 4 (100.0) Dose Reduction 5 (20.0) 2 (40.0) 1 (25.0) Leading to Withdrawal - - 1 (25.0) a Leading to DLT - - 2 (50.0)ᵇ Data extract 20 August 2026. The safety population includes all patients who received at least one dose of the study drug combination prior to the data extract. Median duration of follow-up 5.8 (1.0-9.7). DLT, dose-limiting toxicity. SAE, serious adverse event. TRAE, treatment-related adverse event; DL, dose level. DL1: vopimetostat 200 mg+daraxonrasib 100 mg; DL2: vopimetostat 250 mg+daraxonrasib 100 mg. ᵃ At the time of the datacut, an event (Grade 2 anemia) was incorrectly captured in the EDC as a DLT; this has since been corrected. ᵇ Grade 3 acneiform rash (resulting in dose reduction and 18 continued treatment) and Grade 3 stomatitis and fatigue (withdrawn consent).
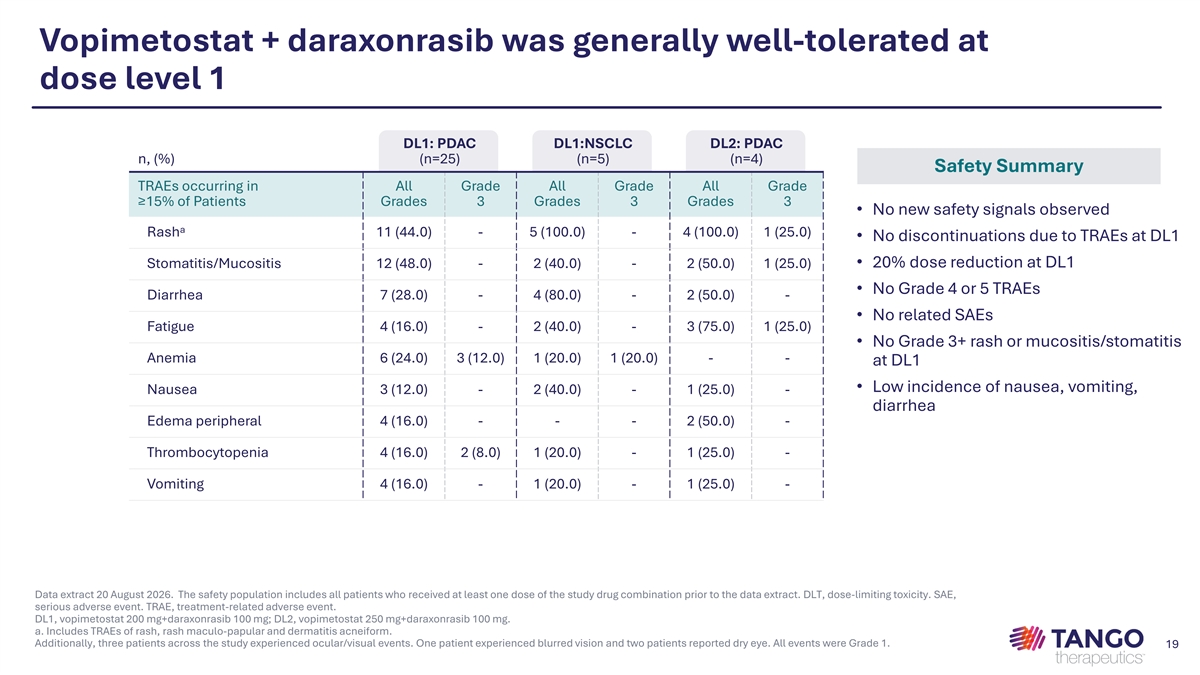
Vopimetostat + daraxonrasib was generally well-tolerated at dose level 1 DL1: PDAC DL1:NSCLC DL2: PDAC n, (%) (n=25) (n=5) (n=4) Safety Summary TRAEs occurring in All Grade All Grade All Grade ≥15% of Patients Grades 3 Grades 3 Grades 3 • No new safety signals observed a Rash 11 (44.0) - 5 (100.0) - 4 (100.0) 1 (25.0) • No discontinuations due to TRAEs at DL1 • 20% dose reduction at DL1 Stomatitis/Mucositis 12 (48.0) - 2 (40.0) - 2 (50.0) 1 (25.0) • No Grade 4 or 5 TRAEs Diarrhea 7 (28.0) - 4 (80.0) - 2 (50.0) - • No related SAEs Fatigue 4 (16.0) - 2 (40.0) - 3 (75.0) 1 (25.0) • No Grade 3+ rash or mucositis/stomatitis Anemia 6 (24.0) 3 (12.0) 1 (20.0) 1 (20.0) - - at DL1 • Low incidence of nausea, vomiting, Nausea 3 (12.0) - 2 (40.0) - 1 (25.0) - diarrhea Edema peripheral 4 (16.0) - - - 2 (50.0) - Thrombocytopenia 4 (16.0) 2 (8.0) 1 (20.0) - 1 (25.0) - Vomiting 4 (16.0) - 1 (20.0) - 1 (25.0) - Data extract 20 August 2026. The safety population includes all patients who received at least one dose of the study drug combination prior to the data extract. DLT, dose-limiting toxicity. SAE, serious adverse event. TRAE, treatment-related adverse event. DL1, vopimetostat 200 mg+daraxonrasib 100 mg; DL2, vopimetostat 250 mg+daraxonrasib 100 mg. a. Includes TRAEs of rash, rash maculo-papular and dermatitis acneiform. Additionally, three patients across the study experienced ocular/visual events. One patient experienced blurred vision and two patients reported dry eye. All events were Grade 1. 19
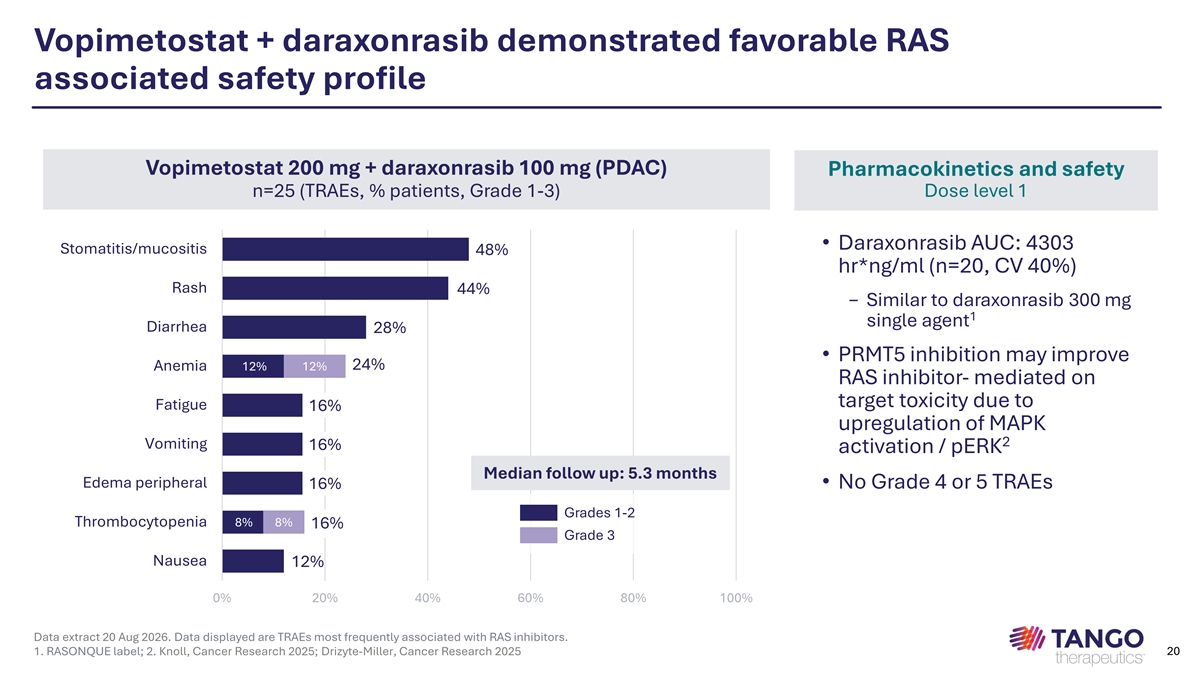
Vopimetostat + daraxonrasib demonstrated favorable RAS associated safety profile Vopimetostat 200 mg + daraxonrasib 100 mg (PDAC) Pharmacokinetics and safety n=25 (TRAEs, % patients, Grade 1-3) Dose level 1 • Daraxonrasib AUC: 4303 Stomatitis/mucositis 48% hr*ng/ml (n=20, CV 40%) Rash 44% − Similar to daraxonrasib 300 mg 1 single agent Diarrhea 28% • PRMT5 inhibition may improve 24% Anemia 12% 12% RAS inhibitor- mediated on target toxicity due to Fatigue 16% upregulation of MAPK 2 Vomiting 16% activation / pERK Median follow up: 5.3 months Edema peripheral 16% • No Grade 4 or 5 TRAEs Grades 1-2 Thrombocytopenia 8% 8% 16% Grade 3 Nausea 12% 0% 20% 40% 60% 80% 100% Data extract 20 Aug 2026. Data displayed are TRAEs most frequently associated with RAS inhibitors. 1. RASONQUE label; 2. Knoll, Cancer Research 2025; Drizyte-Miller, Cancer Research 2025 20
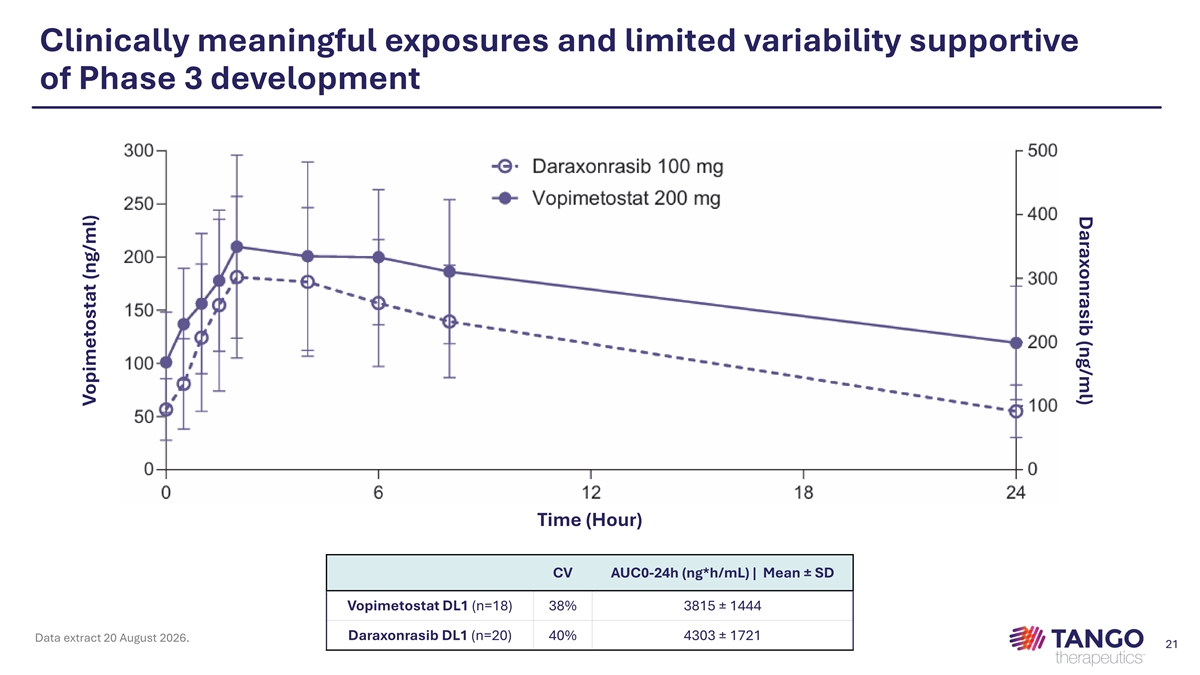
Daraxonrasib (ng/ml) Clinically meaningful exposures and limited variability supportive of Phase 3 development Time (Hour) CV AUC0-24h (ng*h/mL) | Mean ± SD Vopimetostat DL1 (n=18) 38% 3815 ± 1444 Daraxonrasib DL1 (n=20) 40% 4303 ± 1721 Data extract 20 August 2026. 21 Vopimetostat (ng/ml)

Vopimetostat registration path Adam Crystal, MD, PhD, President of Research and Development 22
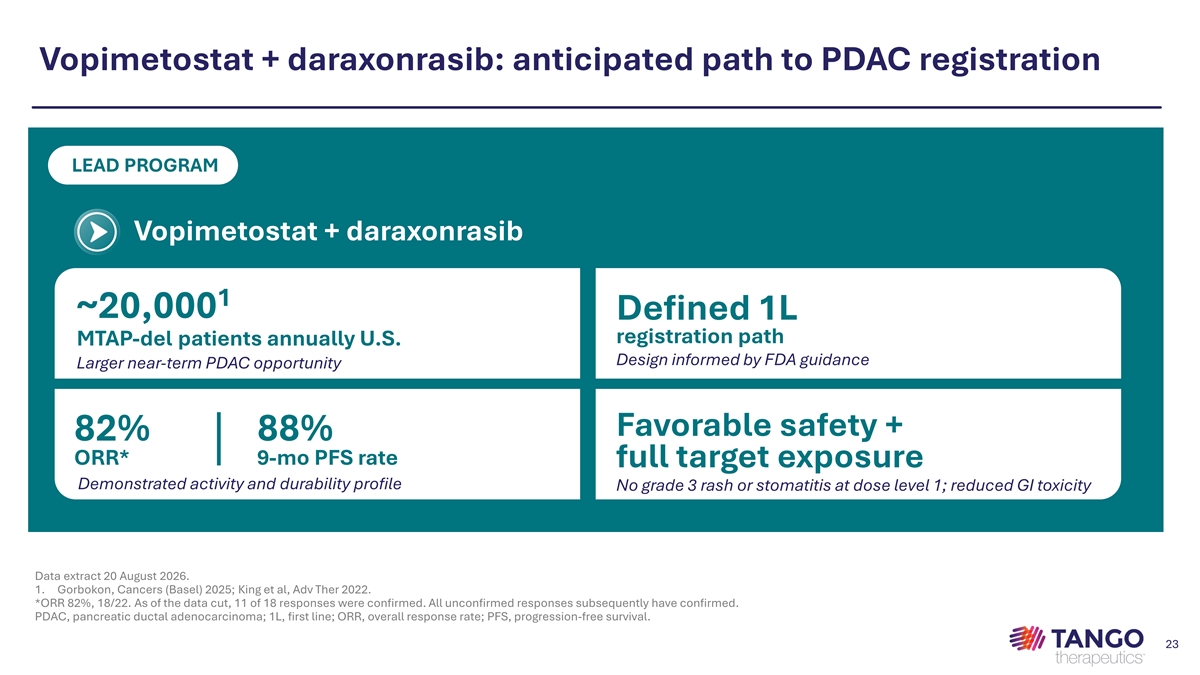
Vopimetostat + daraxonrasib: anticipated path to PDAC registration LEAD PROGRAM Vopimetostat + daraxonrasib 1 ~20,000 Defined 1L registration path MTAP-del patients annually U.S. Design informed by FDA guidance Larger near-term PDAC opportunity Favorable safety + 82% 88% ORR* 9-mo PFS rate full target exposure Demonstrated activity and durability profile No grade 3 rash or stomatitis at dose level 1; reduced GI toxicity Data extract 20 August 2026. 1. Gorbokon, Cancers (Basel) 2025; King et al, Adv Ther 2022. *ORR 82%, 18/22. As of the data cut, 11 of 18 responses were confirmed. All unconfirmed responses subsequently have confirmed. PDAC, pancreatic ductal adenocarcinoma; 1L, first line; ORR, overall response rate; PFS, progression-free survival. 23
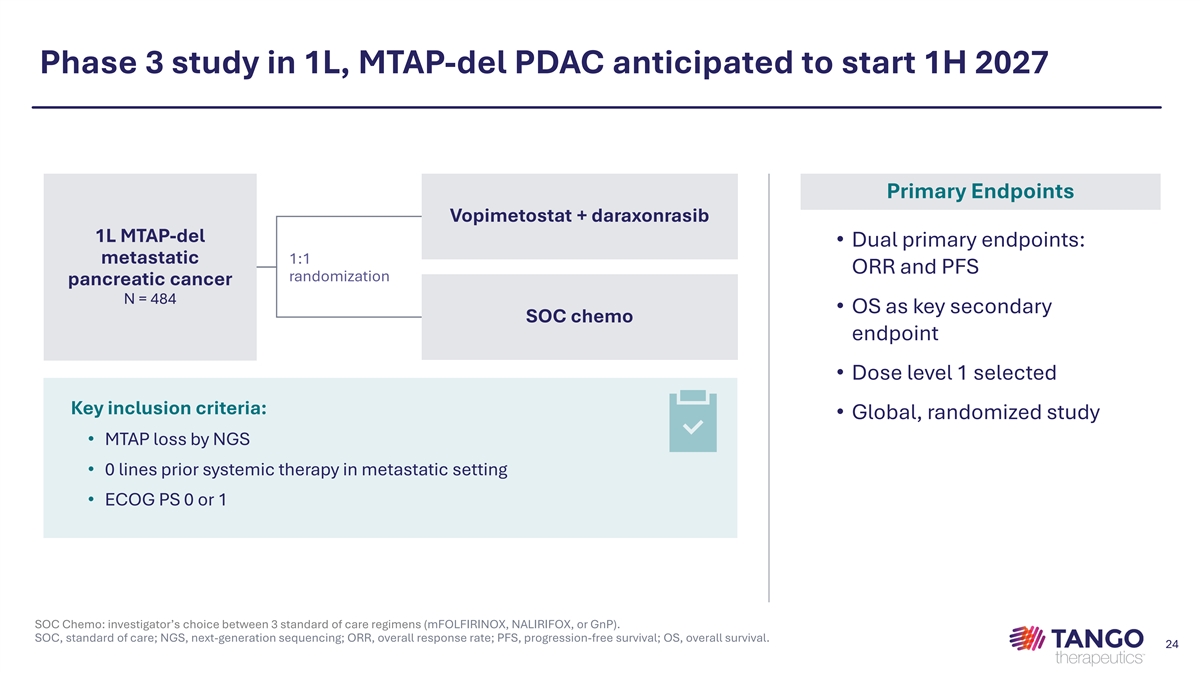
Phase 3 study in 1L, MTAP-del PDAC anticipated to start 1H 2027 Primary Endpoints Vopimetostat + daraxonrasib 1L MTAP-del • Dual primary endpoints: metastatic 1:1 ORR and PFS randomization pancreatic cancer N = 484 • OS as key secondary SOC chemo endpoint • Dose level 1 selected Key inclusion criteria: • Global, randomized study • MTAP loss by NGS • 0 lines prior systemic therapy in metastatic setting • ECOG PS 0 or 1 SOC Chemo: investigator’s choice between 3 standard of care regimens (mFOLFIRINOX, NALIRIFOX, or GnP). SOC, standard of care; NGS, next-generation sequencing; ORR, overall response rate; PFS, progression-free survival; OS, overall survival. 24
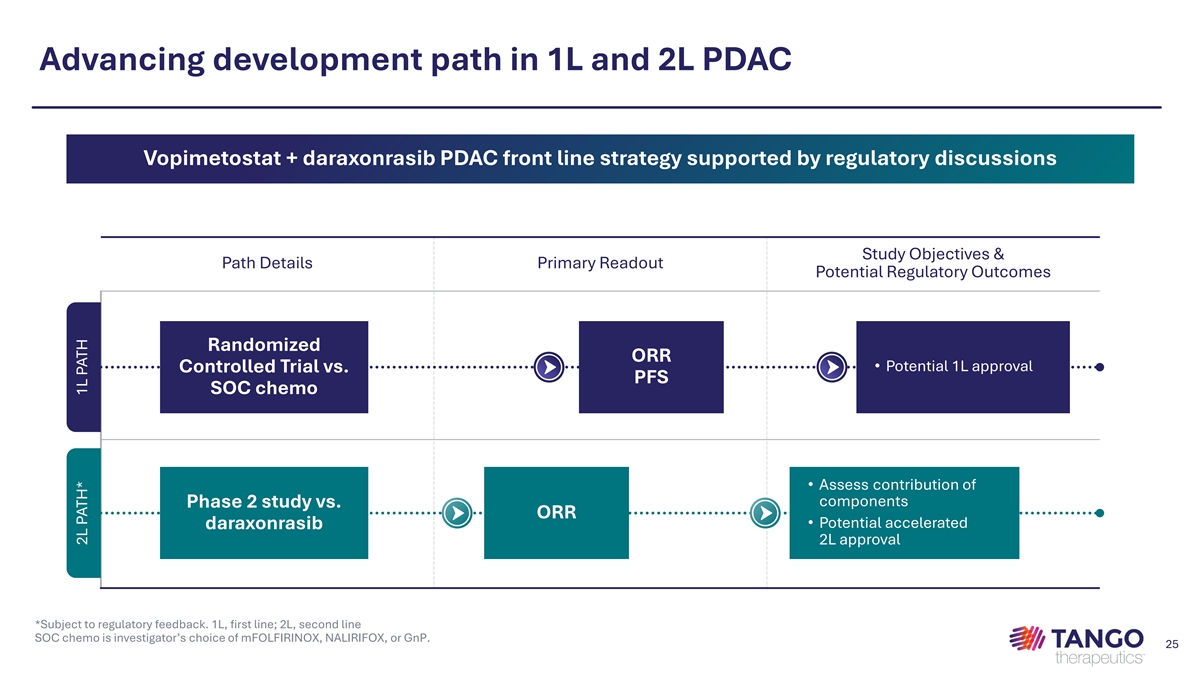
Advancing development path in 1L and 2L PDAC Vopimetostat + daraxonrasib PDAC front line strategy supported by regulatory discussions Study Objectives & Path Details Primary Readout Potential Regulatory Outcomes Randomized ORR • Potential 1L approval Controlled Trial vs. PFS SOC chemo • Assess contribution of components Phase 2 study vs. ORR • Potential accelerated daraxonrasib 2L approval *Subject to regulatory feedback. 1L, first line; 2L, second line SOC chemo is investigator’s choice of mFOLFIRINOX, NALIRIFOX, or GnP. 25 2L PATH* 1L PATH

Leadership in PRMT5 inhibition Adam Crystal, MD, PhD 26
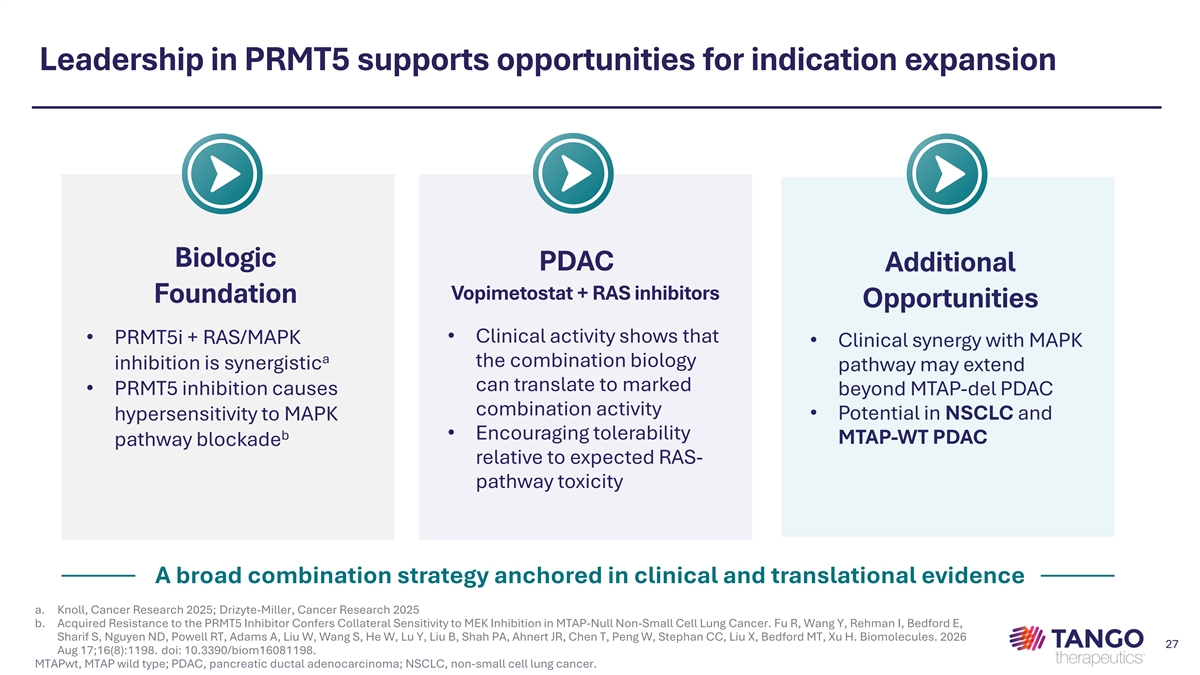
Leadership in PRMT5 supports opportunities for indication expansion Biologic PDAC Additional Vopimetostat + RAS inhibitors Foundation Opportunities • Clinical activity shows that • PRMT5i + RAS/MAPK • Clinical synergy with MAPK a the combination biology inhibition is synergistic pathway may extend can translate to marked • PRMT5 inhibition causes beyond MTAP-del PDAC combination activity • Potential in NSCLC and hypersensitivity to MAPK b • Encouraging tolerability MTAP-WT PDAC pathway blockade relative to expected RAS- pathway toxicity A broad combination strategy anchored in clinical and translational evidence a. Knoll, Cancer Research 2025; Drizyte-Miller, Cancer Research 2025 b. Acquired Resistance to the PRMT5 Inhibitor Confers Collateral Sensitivity to MEK Inhibition in MTAP-Null Non-Small Cell Lung Cancer. Fu R, Wang Y, Rehman I, Bedford E, Sharif S, Nguyen ND, Powell RT, Adams A, Liu W, Wang S, He W, Lu Y, Liu B, Shah PA, Ahnert JR, Chen T, Peng W, Stephan CC, Liu X, Bedford MT, Xu H. Biomolecules. 2026 27 Aug 17;16(8):1198. doi: 10.3390/biom16081198. MTAPwt, MTAP wild type; PDAC, pancreatic ductal adenocarcinoma; NSCLC, non-small cell lung cancer.
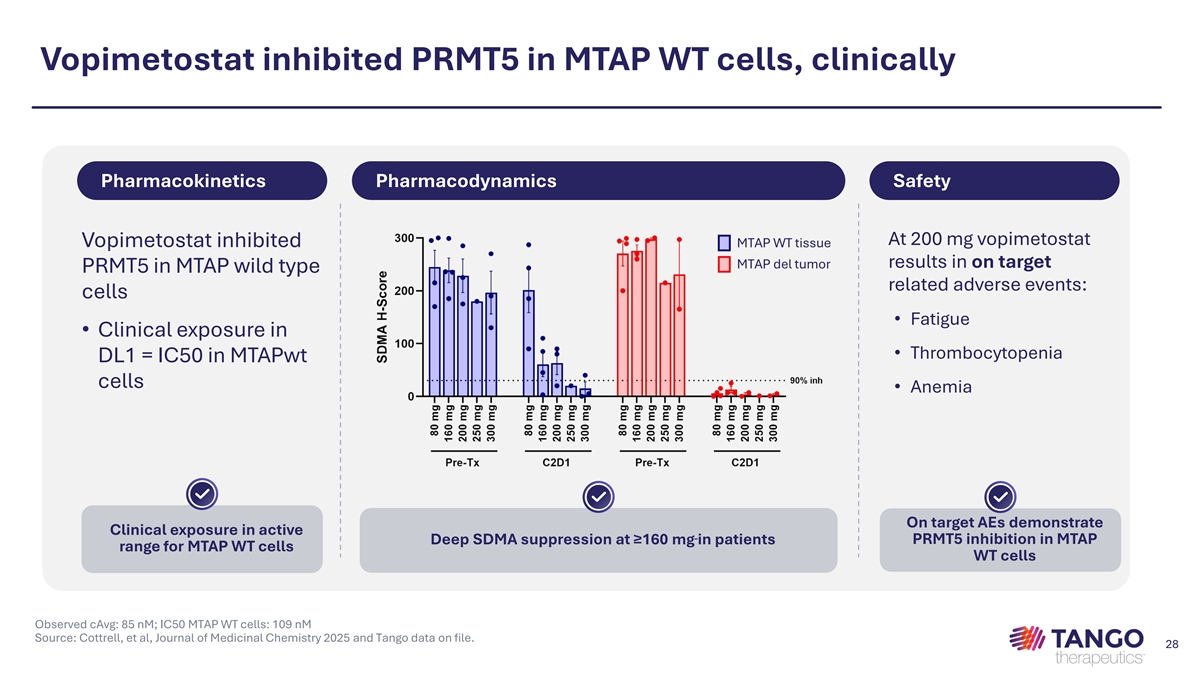
Vopimetostat inhibited PRMT5 in MTAP WT cells, clinically Pharmacokinetics Pharmacodynamics Safety At 200 mg vopimetostat Vopimetostat inhibited MTAP WT tissue results in on target MTAP del tumor PRMT5 in MTAP wild type related adverse events: cells • Fatigue • Clinical exposure in • Thrombocytopenia DL1 = IC50 in MTAPwt cells • Anemia On target AEs demonstrate Clinical exposure in active PRMT5 inhibition in MTAP Deep SDMA suppression at ≥160 mg in patients range for MTAP WT cells WT cells Observed cAvg: 85 nM; IC50 MTAP WT cells: 109 nM Source: Cottrell, et al, Journal of Medicinal Chemistry 2025 and Tango data on file. 28
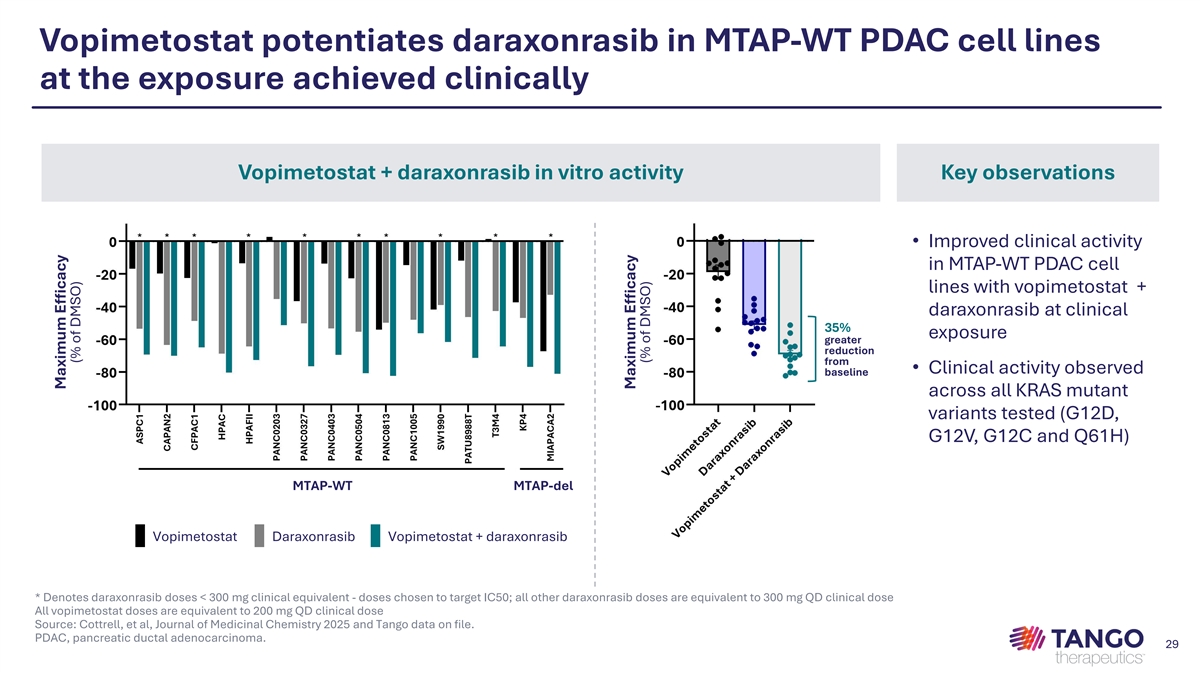
Vopimetostat potentiates daraxonrasib in MTAP-WT PDAC cell lines at the exposure achieved clinically Vopimetostat + daraxonrasib in vitro activity Key observations • Improved clinical activity in MTAP-WT PDAC cell lines with vopimetostat + daraxonrasib at clinical 35% exposure greater reduction from • Clinical activity observed baseline across all KRAS mutant variants tested (G12D, G12V, G12C and Q61H) MTAP-WT MTAP-del Vopimetostat Daraxonrasib Vopimetostat + daraxonrasib * Denotes daraxonrasib doses < 300 mg clinical equivalent - doses chosen to target IC50; all other daraxonrasib doses are equivalent to 300 mg QD clinical dose All vopimetostat doses are equivalent to 200 mg QD clinical dose Source: Cottrell, et al, Journal of Medicinal Chemistry 2025 and Tango data on file. PDAC, pancreatic ductal adenocarcinoma. 29 Maximum Efficacy (% of DMSO) Maximum Efficacy (% of DMSO)
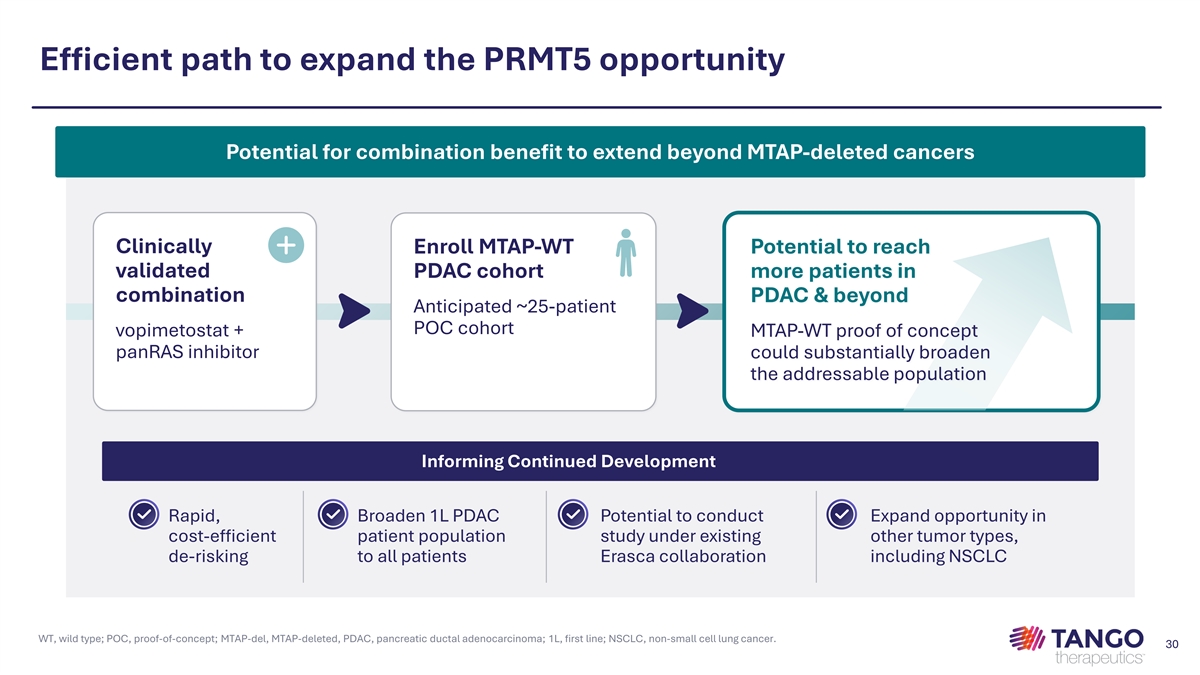
Efficient path to expand the PRMT5 opportunity Potential for combination benefit to extend beyond MTAP-deleted cancers Clinically Enroll MTAP-WT Potential to reach validated PDAC cohort more patients in combination PDAC & beyond Anticipated ~25-patient POC cohort vopimetostat + MTAP-WT proof of concept panRAS inhibitor could substantially broaden the addressable population Informing Continued Development Rapid, Broaden 1L PDAC Potential to conduct Expand opportunity in cost-efficient patient population study under existing other tumor types, de-risking to all patients Erasca collaboration including NSCLC WT, wild type; POC, proof-of-concept; MTAP-del, MTAP-deleted, PDAC, pancreatic ductal adenocarcinoma; 1L, first line; NSCLC, non-small cell lung cancer. 30

Upcoming milestones and financial highlights Matthew Gall, Chief Financial Officer 31

Near-term anticipated milestones support advancement of vopimetostat clinical development and efficient expansion opportunities Advance NSCLC Expand RAS Opportunity Advance Lead PDAC Program development strategy 2H26 1H27 January 2027 Initiate Phase 1/2 Initiate Phase 3 vopimetostat + Release TNG456 monotherapy data vopimetostat + ERAS-0015 daraxonrasib Brain-penetrant PRMT5 inhibitor in MTAP-del PDAC or MTAP-del, Front line, MTAP-del PDAC NSCLC, glioblastoma and other cancers RAS-mutant NSCLC DATA READOUT 1H27 January 2027 Initiate Phase 1/2 vopimetostat + Release vopimetostat RAS combination study monotherapy data 2L, MTAP-wild type PDAC NSCLC DATA READOUT $1.0B cash and investments as of June 30, 2026, expected to support PDAC late-stage development and ongoing work 2L, second line; MTAP-del, MTAP-deleted; WT, wild type; NSCLC, non-small cell lung cancer. 32

Conclusion Malte Peters, MD, President and Chief Executive Officer 33
Compelling PDAC data support our registration strategy and broader franchise potential VALIDATED REGISTRATION- LAUNCH BROADER CLINICAL PROFILE DIRECTED PREPARATION VOPIMETOSTAT DEVELOPMENT FRANCHISE POTENTIAL Compelling activity, Focus shifts from Organizational Combinability and MTAP-WT durability and establishing the signal readiness, leadership biology support a broader tolerability reinforce to executing on a team in place, key long-term opportunity confidence in the defined pivotal path activities underway beyond the lead clinical profile MTAP-del PDAC program MTAP-del, MTAP-deleted; WT, wild type; PDAC, pancreatic ductal adenocarcinoma. 34
