
Exhibit 99.1 Enozertinib Program Update October 23, 2026

Forward-Looking Statements This presentation contains forward-looking statements that involve substantial risks and uncertainties. All statements other than statements of historical facts contained in this presentation, including statements regarding ORIC Pharmaceuticals, Inc.’s (“ORIC”, “we”, “us” or “our”) future financial condition, results of operations, business strategy and plans, and objectives of management for future operations, as well as statements regarding industry trends, are forward-looking statements. In some cases, you can identify forward-looking statements by terminology such as “anticipate,” “believe,” “continue,” “could,” “estimate,” “expect,” “intend,” “may,” “plan,” “potentially,” “predict,” “should,” “will” or the negative of these terms or other similar expressions. Forward-looking statements contained in this presentation also include, but are not limited to, statements regarding: the potential best-in-class profile of enozertinib; our development plans and timelines for enozertinib; the potential advantages of, and commercial opportunities for, enozertinib; and enozertinib clinical outcomes, which may materially change as patient enrollment continues or more patient data becomes available; the expected timing of reporting data from our clinical trials. We have based these forward-looking statements largely on our current expectations and projections about future events and trends that we believe may affect our financial condition, results of operations, business strategy and financial needs. These forward-looking statements are subject to a number of risks, uncertainties and assumptions, including, among other things: the timing of the initiation, progress and results of our preclinical studies and clinical trials; risks associated with the process of developing and commercializing drugs that are safe and effective for use in humans and operating as a clinical stage company; negative impacts of health emergencies, economic instability or international conflicts on our operations, including clinical trials; the potential for current or future clinical trials of product candidates to differ from preclinical, initial, interim, preliminary or expected results; our ability to advance product candidates into, and successfully complete, clinical trials; the timing or likelihood of regulatory filings and approvals; changes in our plans to develop and commercialize our product candidates; our estimates of the number of patients who suffer from the diseases we are targeting and the number of patients that may enroll in our clinical trials; the commercializing of our product candidates, if approved; our ability to successfully manufacture and supply our product candidates for clinical trials and for commercial use, if approved; potential benefits and costs of strategic arrangements, licensing and/or collaborations; the risk of the occurrence of any event, change or other circumstance that could give rise to the termination of our license or collaboration agreements; our estimates regarding expenses, future revenue, capital requirements and needs for financing and our ability to obtain capital; the sufficiency of our existing cash and investments to fund our future operating expenses and capital expenditure requirements; our ability to retain the continued service of our key personnel and to identify, hire and retain additional qualified professionals; the implementation of our business model and strategic plans for our business and product candidates; the scope of protection we are able to establish and maintain for intellectual property rights, product candidates and our pipeline; our ability to contract with third-party contract research organizations, suppliers and manufacturers and their ability to perform adequately; the pricing, coverage and reimbursement of our product candidates, if approved; developments relating to our competitors and our industry, including competing product candidates and therapies; regulatory developments in the United States and foreign countries; general economic and market conditions; and the other risks, uncertainties and assumptions discussed in the public filings we have made and will make with the Securities and Exchange Commission (“SEC”). These risks are not exhaustive. New risk factors emerge from time to time and it is not possible for our management to predict all risk factors, nor can we assess the impact of all factors on our business or the extent to which any factor, or combination of factors, may cause actual results to differ materially from those contained in, or implied by, any forward-looking statements. You should not rely upon forward-looking statements as predictions of future events. Although we believe that the expectations reflected in the forward-looking statements are reasonable, we cannot guarantee future results, levels of activity, performance or achievements. This presentation also contains estimates and other statistical data made by independent parties and by us relating to market size and other data about our industry. This data involves a number of assumptions and limitations, and you are cautioned not to give undue weight to such data and estimates. In addition, projections, assumptions and estimates of our future performance and the future performance of the markets in which we operate are necessarily subject to a high degree of uncertainty and risk. Except as required by law, we undertake no obligation to update any statements in this presentation for any reason after the date of this presentation. We have filed Current Reports on Form 8-K, Quarterly Reports on Form 10-Q, Annual Reports on Form 10-K, and other documents with the SEC. You should read these documents for more complete information about us. You may obtain these documents for free by visiting EDGAR on the SEC website at www.sec.gov. This presentation discusses our product candidates that are under preclinical or clinical study, and which have not yet been approved for marketing by the U.S. Food and Drug Administration. No representation is made as to the safety or effectiveness of our product candidates for the therapeutic use for which they are being studied. 2

Enozertinib Program Update Agenda • Executive Summary • Preclinical Differentiation • ESMO 2026 Clinical Data Highlights and Next Steps • KOL Perspectives on Enozertinib • Commercial Potential ORIC Participants Guest KOL • Jacob Chacko, Chief Executive Officer • Dr. Joshua Sabari, Assistant Professor of Medicine at NYU Grossman • Lori Friedman, Chief Scientific Officer – Enozertinib Trial Investigator • Pratik Multani, Chief Medical Officer • Dominic Piscitelli, Chief Financial Officer • Matt Panuwat, Chief Business Officer • Keith Lui, SVP Commercial and Medical Affairs 3

Executive Summary

Enozertinib Establishes Potential Best-in-Class Profile in 1L EGFR Atypical NSCLC, with Data Supporting Rapid Advancement to Phase 3 Executive Summary • 1L EGFR Atypical NSCLC is a >$2.5bn market opportunity in the US alone and lacks a best-in-class therapy with meaningful systemic efficacy, compelling CNS activity, and favorable tolerability • In a global 1L EGFR Atypical population with over double the rate of baseline CNS disease as competitor datasets, including untreated CNS metastases, enozertinib raises the efficacy benchmarks by achieving: – 84% confirmed systemic ORR – 70% confirmed CNS ORR, with multiple complete responses – 88% 6-month landmark PFS • Competitive safety profile: no significant off-target toxicity and no treatment-related discontinuations • ORIC plans to initiate Redwood-1, a global Phase 3 trial in 1L EGFR Atypical NSCLC, in 1H 2027 Source: Ahn et al. ESMO (2026) and ORIC data on file. 5
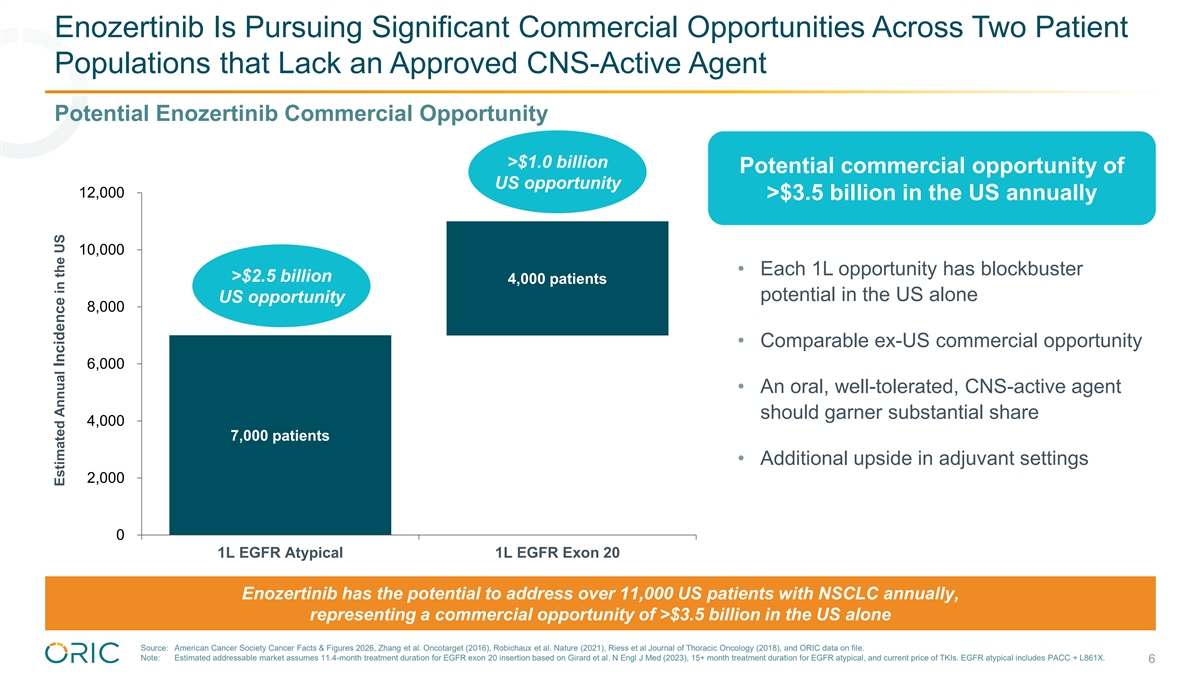
Enozertinib Is Pursuing Significant Commercial Opportunities Across Two Patient Populations that Lack an Approved CNS-Active Agent Potential Enozertinib Commercial Opportunity >$1.0 billion Potential commercial opportunity of US opportunity 12,000 >$3.5 billion in the US annually 10,000 • Each 1L opportunity has blockbuster >$2.5 billion 4,000 patients potential in the US alone US opportunity 8,000 • Comparable ex-US commercial opportunity 6,000 • An oral, well-tolerated, CNS-active agent should garner substantial share 4,000 7,000 patients • Additional upside in adjuvant settings 2,000 0 1L EGFR Atypical 1L EGFR Exon 20 Enozertinib has the potential to address over 11,000 US patients with NSCLC annually, representing a commercial opportunity of >$3.5 billion in the US alone Source: American Cancer Society Cancer Facts & Figures 2026, Zhang et al. Oncotarget (2016), Robichaux et al. Nature (2021), Riess et al Journal of Thoracic Oncology (2018), and ORIC data on file. Note: Estimated addressable market assumes 11.4-month treatment duration for EGFR exon 20 insertion based on Girard et al. N Engl J Med (2023), 15+ month treatment duration for EGFR atypical, and current price of TKIs. EGFR atypical includes PACC + L861X. 6 Estimated Annual Incidence in the US
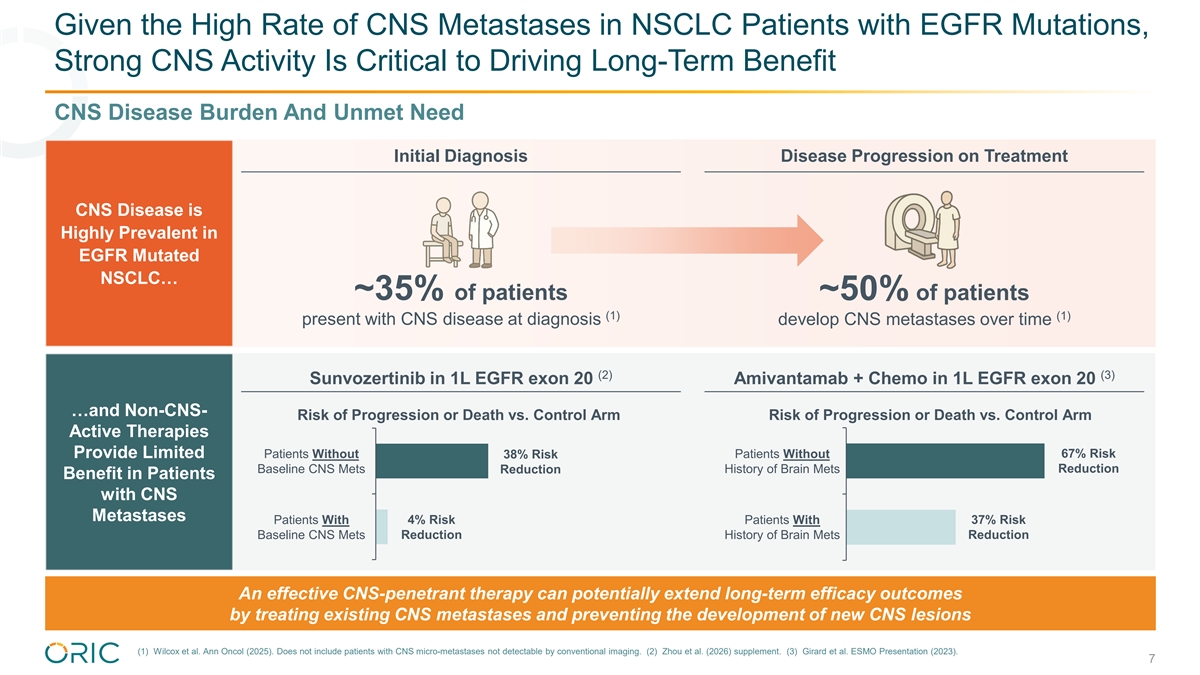
Given the High Rate of CNS Metastases in NSCLC Patients with EGFR Mutations, Strong CNS Activity Is Critical to Driving Long-Term Benefit CNS Disease Burden And Unmet Need Initial Diagnosis Disease Progression on Treatment CNS Disease is Highly Prevalent in EGFR Mutated NSCLC… ~35% of patients ~50% of patients (1) (1) present with CNS disease at diagnosis develop CNS metastases over time (2) (3) Sunvozertinib in 1L EGFR exon 20 Amivantamab + Chemo in 1L EGFR exon 20 …and Non-CNS- Risk of Progression or Death vs. Control Arm Risk of Progression or Death vs. Control Arm Active Therapies 67% Risk Provide Limited Patients Without 38% Risk Patients Without Reduction Baseline CNS Mets Reduction History of Brain Mets Benefit in Patients with CNS Metastases Patients With 4% Risk Patients With 37% Risk Baseline CNS Mets Reduction History of Brain Mets Reduction An effective CNS-penetrant therapy can potentially extend long-term efficacy outcomes by treating existing CNS metastases and preventing the development of new CNS lesions (1) Wilcox et al. Ann Oncol (2025). Does not include patients with CNS micro-metastases not detectable by conventional imaging. (2) Zhou et al. (2026) supplement. (3) Girard et al. ESMO Presentation (2023). 7

Best-in-Class TKIs with Compelling CNS Activity Are Approved Across Multiple NSCLC Drivers, but Not Yet for EGFR Atypical and Exon 20 NSCLC Selected Examples of Best-in-Class TKIs in NSCLC by Driver Mutation EGFR EGFR Atypical ALK RET ROS1 (1) Classical and EGFR Exon 20 Meaningful systemic efficacy No agent yet Compelling combines all CNS activity attributes Well-tolerated Best-in-class profiles ? with 1L approval / There are no approved CNS-active, best-in-class therapies for EGFR atypical and exon 20 insertion mutations in NSCLC (1) Ex19del or L858R. 8
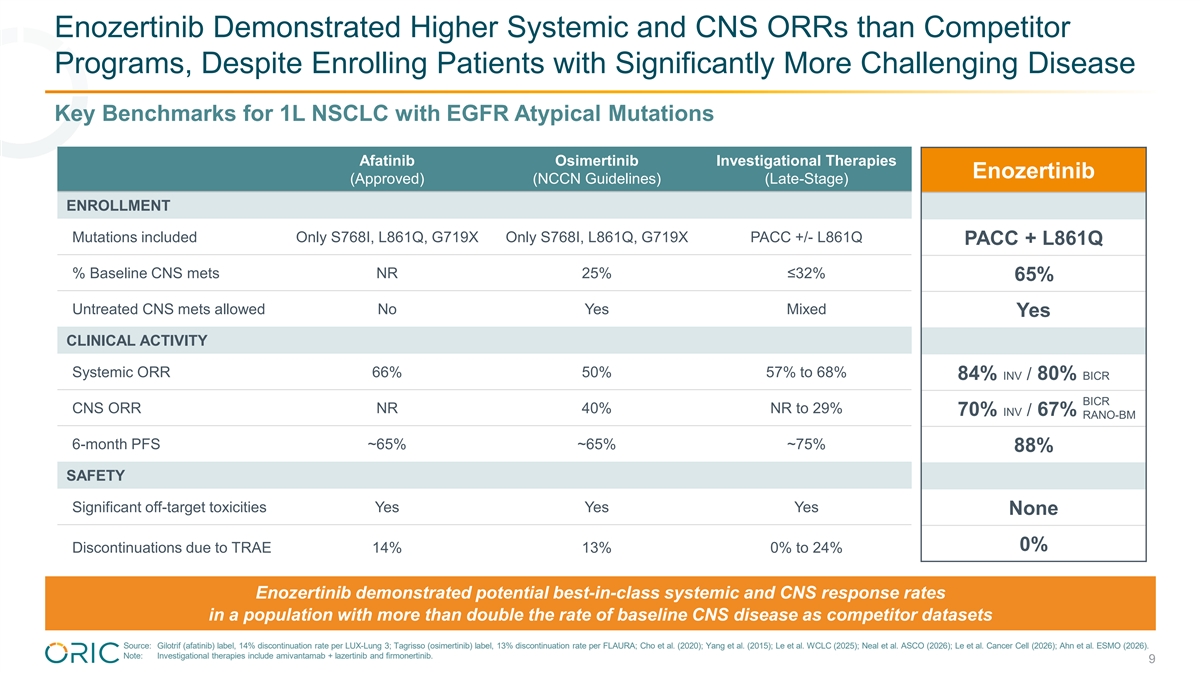
Enozertinib Demonstrated Higher Systemic and CNS ORRs than Competitor Programs, Despite Enrolling Patients with Significantly More Challenging Disease Key Benchmarks for 1L NSCLC with EGFR Atypical Mutations Afatinib Osimertinib Investigational Therapies Enozertinib (Approved) (NCCN Guidelines) (Late-Stage) ENROLLMENT Mutations included Only S768I, L861Q, G719X Only S768I, L861Q, G719X PACC +/- L861Q PACC + L861Q % Baseline CNS mets NR 25% ≤32% 65% Untreated CNS mets allowed No Yes Mixed Yes CLINICAL ACTIVITY Systemic ORR 66% 50% 57% to 68% 84% INV / 80% BICR BICR CNS ORR NR 40% NR to 29% 70% INV / 67% BICR RANO-BM 6-month PFS ~65% ~65% ~75% 88% SAFETY Significant off-target toxicities Yes Yes Yes None 0% Discontinuations due to TRAE 14% 13% 0% to 24% Enozertinib demonstrated potential best-in-class systemic and CNS response rates in a population with more than double the rate of baseline CNS disease as competitor datasets Source: Gilotrif (afatinib) label, 14% discontinuation rate per LUX-Lung 3; Tagrisso (osimertinib) label, 13% discontinuation rate per FLAURA; Cho et al. (2020); Yang et al. (2015); Le et al. WCLC (2025); Neal et al. ASCO (2026); Le et al. Cancer Cell (2026); Ahn et al. ESMO (2026). Note: Investigational therapies include amivantamab + lazertinib and firmonertinib. 9
Preclinical Differentiation
Enozertinib Is a Promising Candidate for NSCLC Patients with EGFR Atypical Mutations, Including Those with CNS Metastases Enozertinib Target Candidate Profile Enozertinib Preclinical Profile • Robust in vitro potency & in vivo efficacy Validated with Clinical Data against a breadth of EGFR mutations Robust Potency • Exquisite selectivity that limits potential for off-target toxicity Exquisite Selectivity Potency: meaningful systemic ORR ü Selectivity: no significant off-target toxicity ü • High brain exposure and intracranial tumor regression in preclinical studies CNS-penetrance: compelling CNS ORR ü Highly Brain Penetrant Enozertinib is a potential best-in-class inhibitor of EGFR atypical mutations, with superior potency and selectivity, and excellent brain-penetrance driving intracranial responses 11
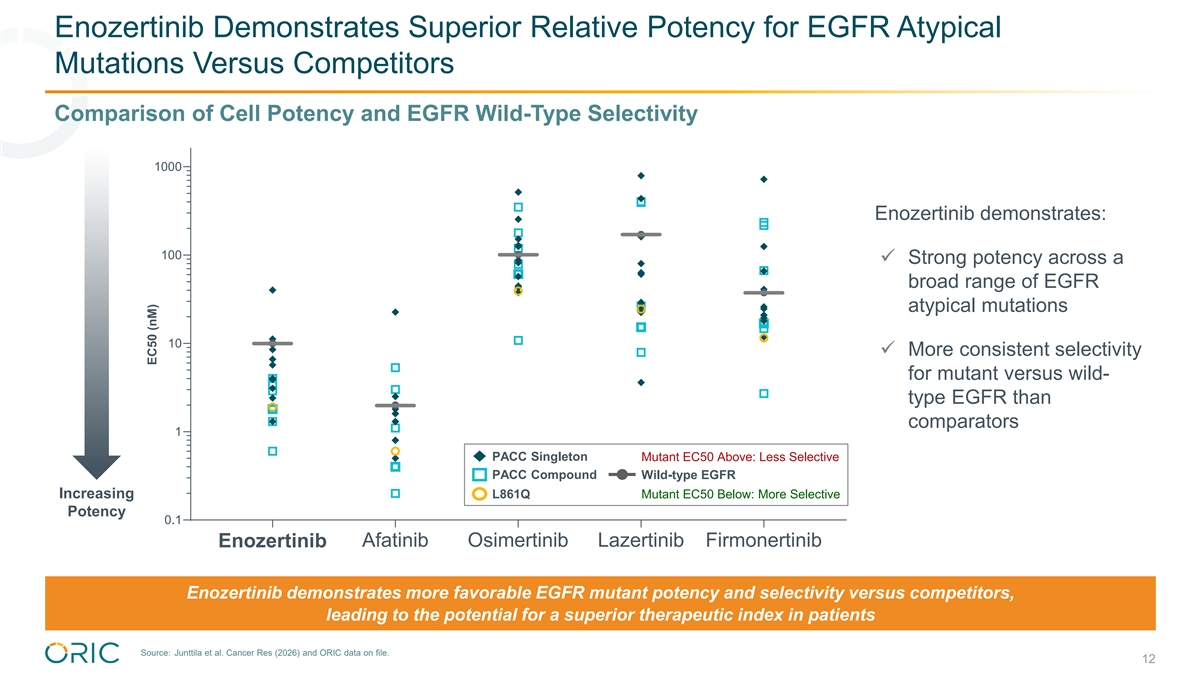
Enozertinib Demonstrates Superior Relative Potency for EGFR Atypical Mutations Versus Competitors Comparison of Cell Potency and EGFR Wild-Type Selectivity 1000 Enozertinib demonstrates: 100 ü Strong potency across a broad range of EGFR atypical mutations 10 ü More consistent selectivity for mutant versus wild- type EGFR than comparators 1 PACC Singleton Mutant EC50 Above: Less Selective PACC Compound Wild-type EGFR Increasing L861Q Mutant EC50 Below: More Selective Potency 0.1 Enozertinib Afatinib Osimertinib Lazertinib Firmonertinib Enozertinib demonstrates more favorable EGFR mutant potency and selectivity versus competitors, leading to the potential for a superior therapeutic index in patients Source: Junttila et al. Cancer Res (2026) and ORIC data on file. 12 EC50 (nM)
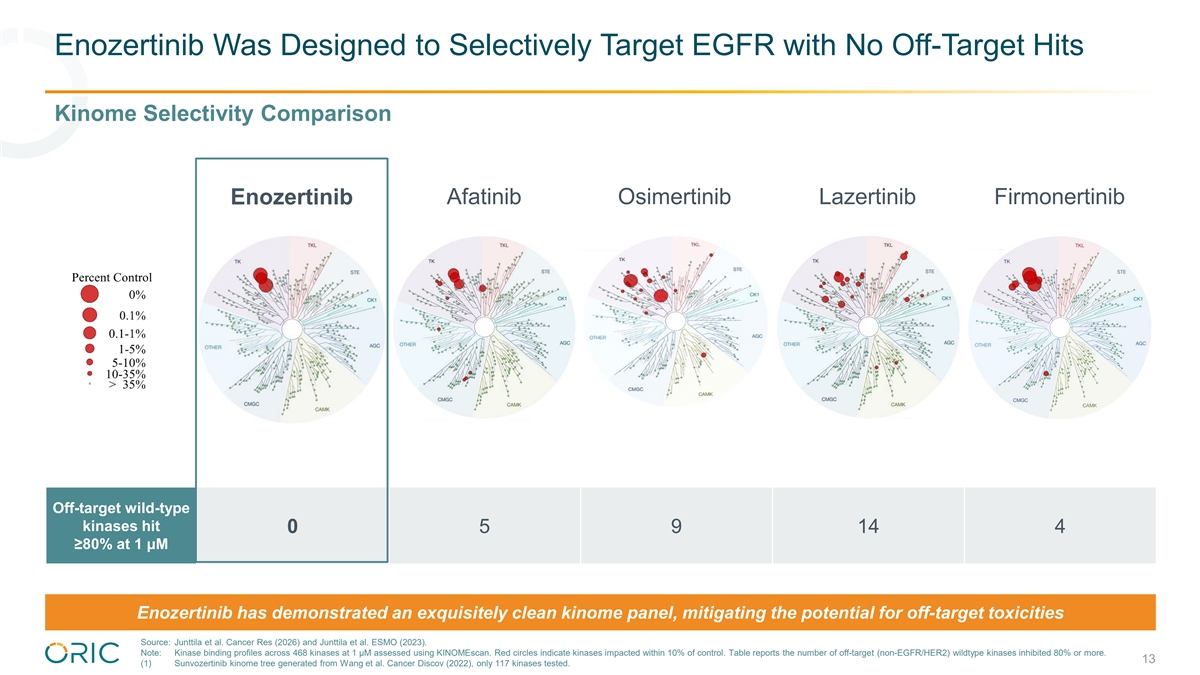
Enozertinib Was Designed to Selectively Target EGFR with No Off-Target Hits Kinome Selectivity Comparison Enozertinib Afatinib Osimertinib Lazertinib Firmonertinib Off-target wild-type kinases hit 0 5 9 14 4 ≥80% at 1 μM Enozertinib has demonstrated an exquisitely clean kinome panel, mitigating the potential for off-target toxicities Source: Junttila et al. Cancer Res (2026) and Junttila et al. ESMO (2023). Note: Kinase binding profiles across 468 kinases at 1 μM assessed using KINOMEscan. Red circles indicate kinases impacted within 10% of control. Table reports the number of off-target (non-EGFR/HER2) wildtype kinases inhibited 80% or more. 13 (1) Sunvozertinib kinome tree generated from Wang et al. Cancer Discov (2022), only 117 kinases tested.
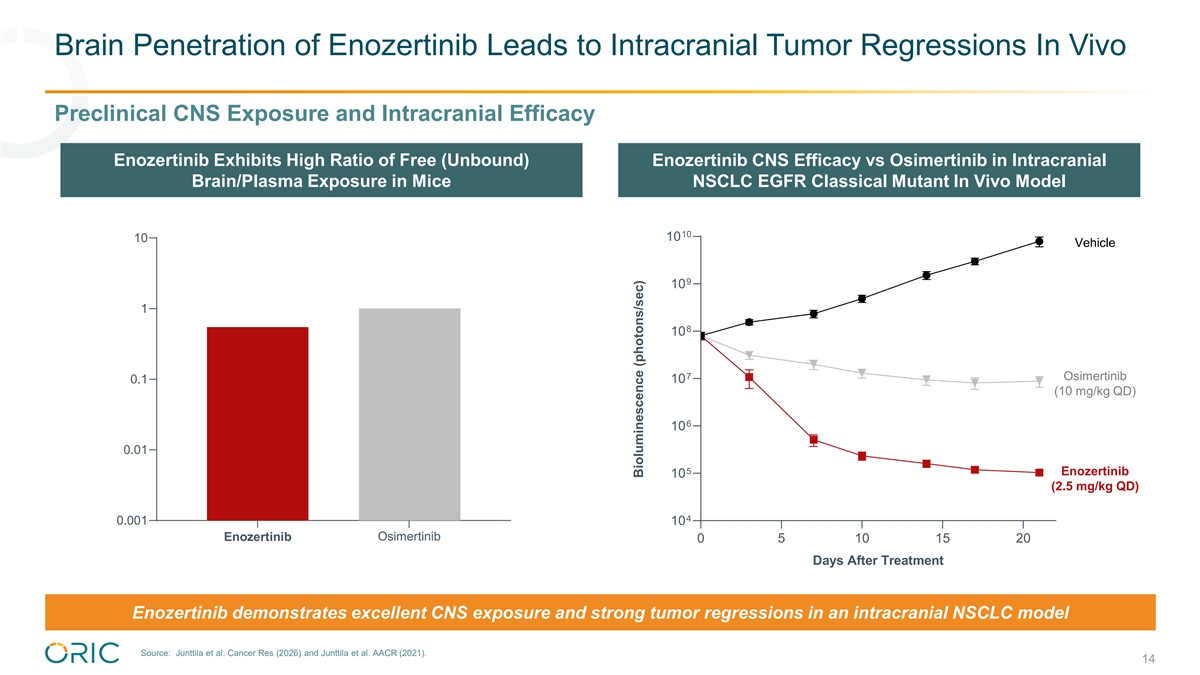
Brain Penetration of Enozertinib Leads to Intracranial Tumor Regressions In Vivo Preclinical CNS Exposure and Intracranial Efficacy Enozertinib Exhibits High Ratio of Free (Unbound) Enozertinib CNS Efficacy vs Osimertinib in Intracranial Brain/Plasma Exposure in Mice NSCLC EGFR Classical Mutant In Vivo Model 10 10 10 Vehicle 9 10 1 8 10 7 Osimertinib 0.1 10 (10 mg/kg QD) 6 10 0.01 5 Enozertinib 10 (2.5 mg/kg QD) 4 0.001 10 Enozertinib Osimertinib 0 5 10 15 20 Days After Treatment Enozertinib demonstrates excellent CNS exposure and strong tumor regressions in an intracranial NSCLC model Source: Junttila et al. Cancer Res (2026) and Junttila et al. AACR (2021). 14 Bioluminescence (photons/sec)

ESMO 2026 Clinical Data Highlights
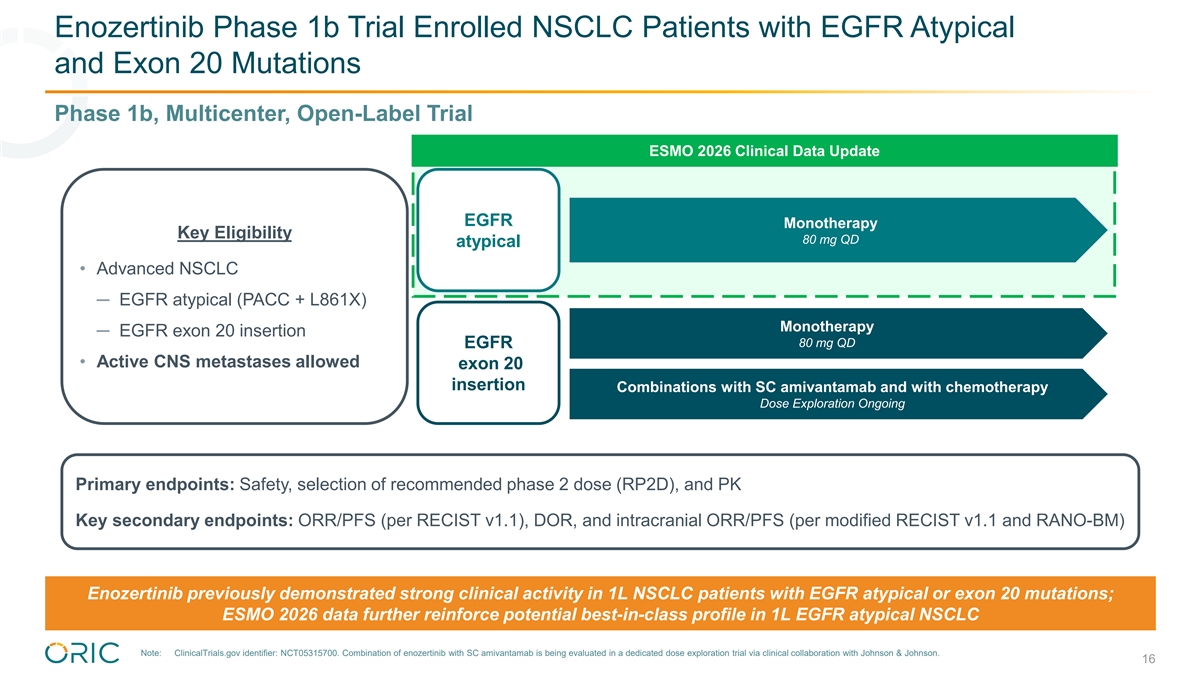
Enozertinib Phase 1b Trial Enrolled NSCLC Patients with EGFR Atypical and Exon 20 Mutations Phase 1b, Multicenter, Open-Label Trial ESMO 2026 Clinical Data Update EGFR Monotherapy Key Eligibility 80 mg QD atypical • Advanced NSCLC ─ EGFR atypical (PACC + L861X) Monotherapy ─ EGFR exon 20 insertion 80 mg QD EGFR • Active CNS metastases allowed exon 20 insertion Combinations with SC amivantamab and with chemotherapy Dose Exploration Ongoing Primary endpoints: Safety, selection of recommended phase 2 dose (RP2D), and PK Key secondary endpoints: ORR/PFS (per RECIST v1.1), DOR, and intracranial ORR/PFS (per modified RECIST v1.1 and RANO-BM) Enozertinib previously demonstrated strong clinical activity in 1L NSCLC patients with EGFR atypical or exon 20 mutations; ESMO 2026 data further reinforce potential best-in-class profile in 1L EGFR atypical NSCLC Note: ClinicalTrials.gov identifier: NCT05315700. Combination of enozertinib with SC amivantamab is being evaluated in a dedicated dose exploration trial via clinical collaboration with Johnson & Johnson. 16
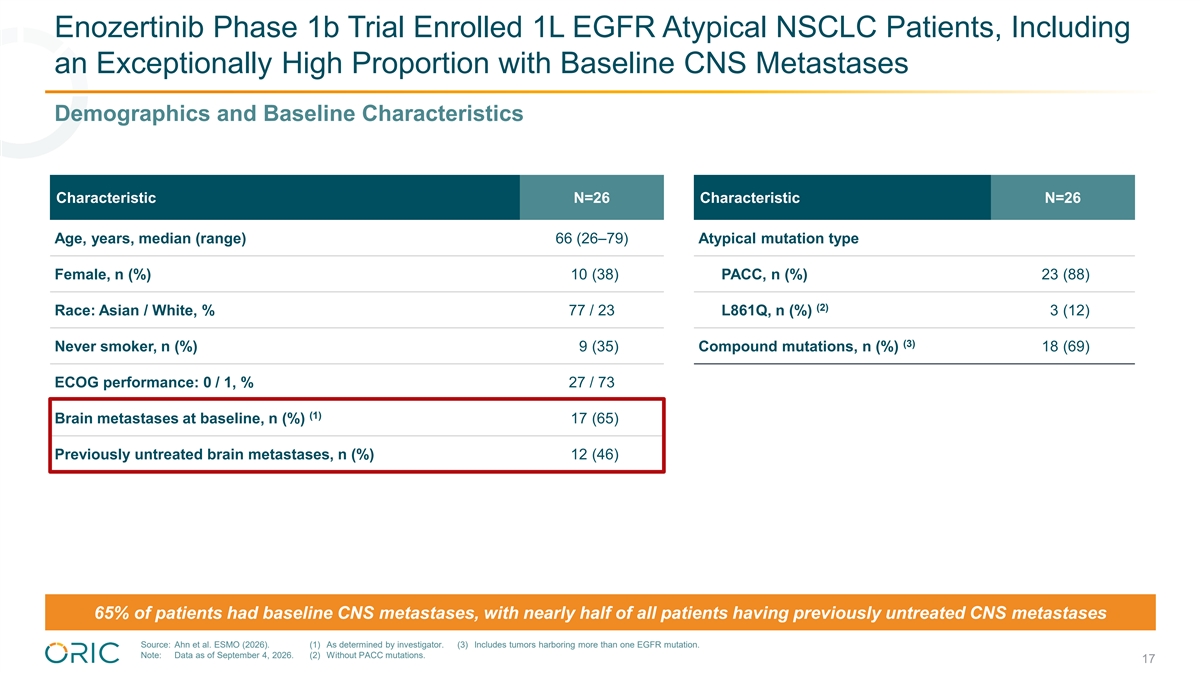
Enozertinib Phase 1b Trial Enrolled 1L EGFR Atypical NSCLC Patients, Including an Exceptionally High Proportion with Baseline CNS Metastases Demographics and Baseline Characteristics Characteristic N=26 Characteristic N=26 Age, years, median (range) 66 (26–79) Atypical mutation type Female, n (%) 10 (38) PACC, n (%) 23 (88) (2) Race: Asian / White, % 77 / 23 L861Q, n (%) 3 (12) (3) Never smoker, n (%) 9 (35) Compound mutations, n (%) 18 (69) ECOG performance: 0 / 1, % 27 / 73 (1) Brain metastases at baseline, n (%) 17 (65) Previously untreated brain metastases, n (%) 12 (46) 65% of patients had baseline CNS metastases, with nearly half of all patients having previously untreated CNS metastases Source: Ahn et al. ESMO (2026). (1) As determined by investigator. (3) Includes tumors harboring more than one EGFR mutation. Note: Data as of September 4, 2026. (2) Without PACC mutations. 17
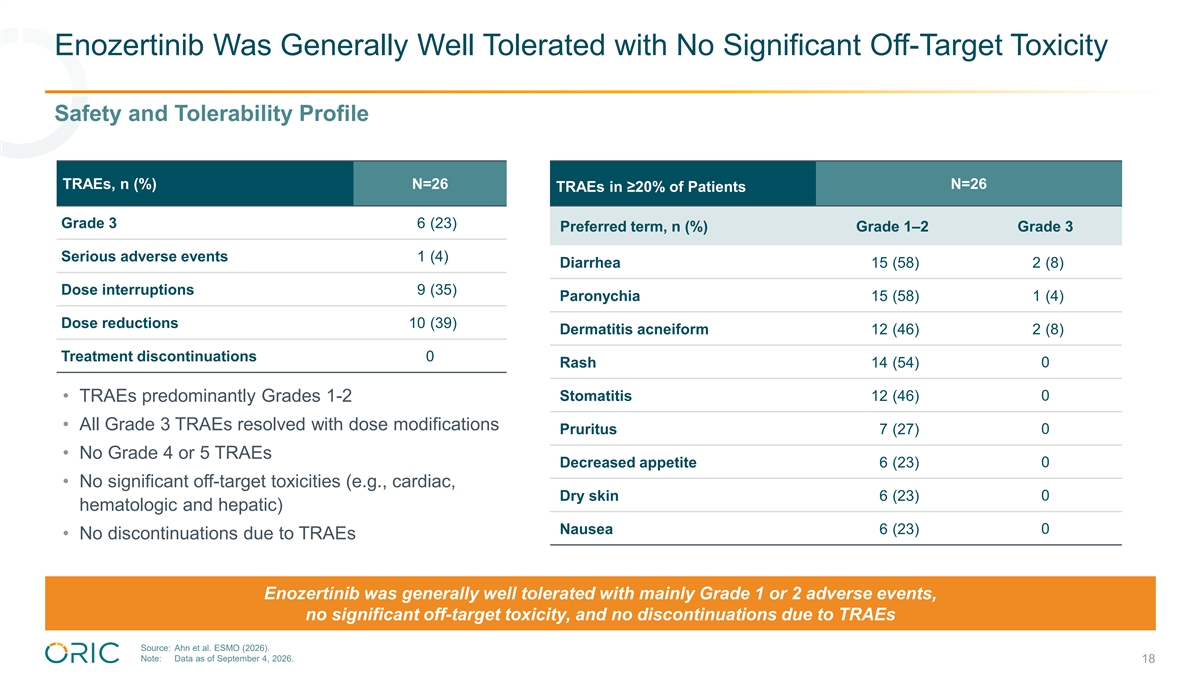
Enozertinib Was Generally Well Tolerated with No Significant Off-Target Toxicity Safety and Tolerability Profile TRAEs, n (%) N=26 N=26 TRAEs in ≥20% of Patients Grade 3 6 (23) Preferred term, n (%) Grade 1–2 Grade 3 Serious adverse events 1 (4) Diarrhea 15 (58) 2 (8) Dose interruptions 9 (35) Paronychia 15 (58) 1 (4) Dose reductions 10 (39) Dermatitis acneiform 12 (46) 2 (8) Treatment discontinuations 0 Rash 14 (54) 0 Stomatitis 12 (46) 0 • TRAEs predominantly Grades 1-2 • All Grade 3 TRAEs resolved with dose modifications 0 Pruritus 7 (27) • No Grade 4 or 5 TRAEs Decreased appetite 6 (23) 0 • No significant off-target toxicities (e.g., cardiac, Dry skin 6 (23) 0 hematologic and hepatic) Nausea 6 (23) 0 • No discontinuations due to TRAEs Enozertinib was generally well tolerated with mainly Grade 1 or 2 adverse events, no significant off-target toxicity, and no discontinuations due to TRAEs Source: Ahn et al. ESMO (2026). Note: Data as of September 4, 2026. 18
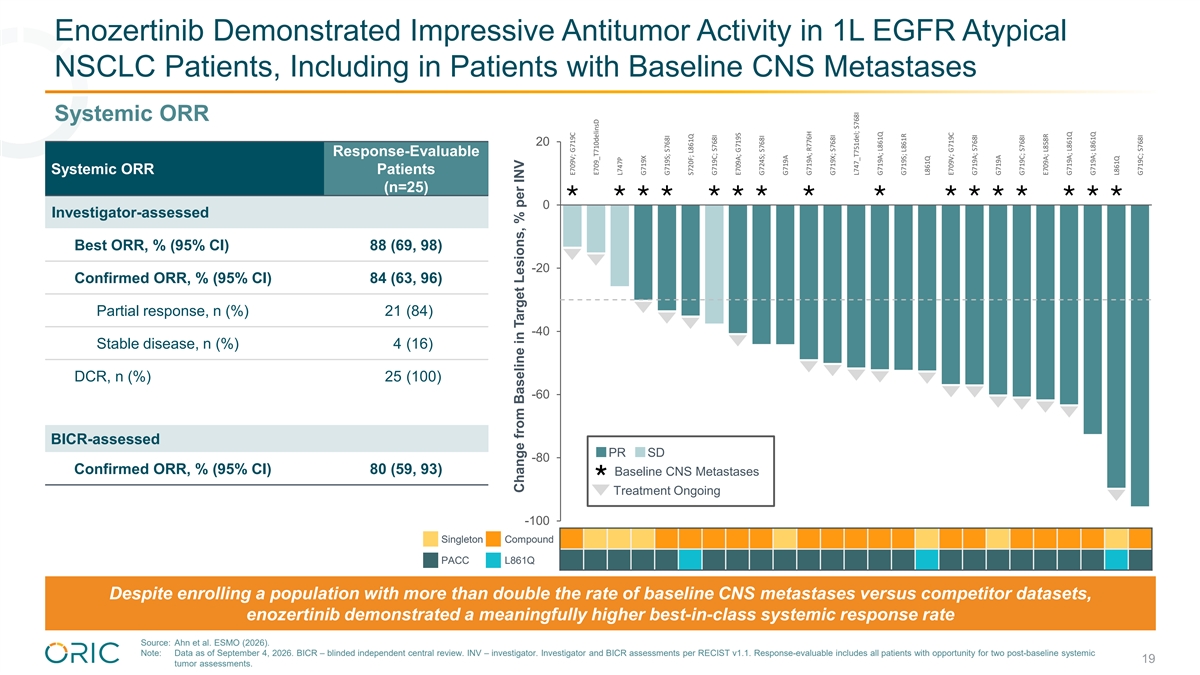
Enozertinib Demonstrated Impressive Antitumor Activity in 1L EGFR Atypical NSCLC Patients, Including in Patients with Baseline CNS Metastases Systemic ORR 20 Response-Evaluable Systemic ORR Patients (n=25) ×××××××××××××××× 0 Investigator-assessed Best ORR, % (95% CI) 88 (69, 98) • • -20 Confirmed ORR, % (95% CI) 84 (63, 96) • Partial response, n (%) 21 (84) • • -40 • Stable disease, n (%) 4 (16) • • • • • DCR, n (%) 25 (100) • • -60 • • • • BICR-assessed PR SD -80 Confirmed ORR, % (95% CI) 80 (59, 93) Ø Baseline CNS Metastases Treatment Ongoing • -100 Singleton Compound PACC L861Q Despite enrolling a population with more than double the rate of baseline CNS metastases versus competitor datasets, enozertinib demonstrated a meaningfully higher best-in-class systemic response rate Source: Ahn et al. ESMO (2026). Note: Data as of September 4, 2026. BICR – blinded independent central review. INV – investigator. Investigator and BICR assessments per RECIST v1.1. Response-evaluable includes all patients with opportunity for two post-baseline systemic 19 tumor assessments. Change from Baseline in Target Lesions, % per INV E709V; G719C E709_T710delinsD L747P G719X G719S; S768I S720F; L861Q G719C; S768I E709A; G719S G724S; S768I G719A G719A; R776H G719X; S768I L747_T751del; S768I G719A; L861Q G719S; L861R L861Q E709V; G719C G719A; S768I G719A G719C; S768I E709A; L858R G719A; L861Q G719A; L861Q L861Q G719C; S768I
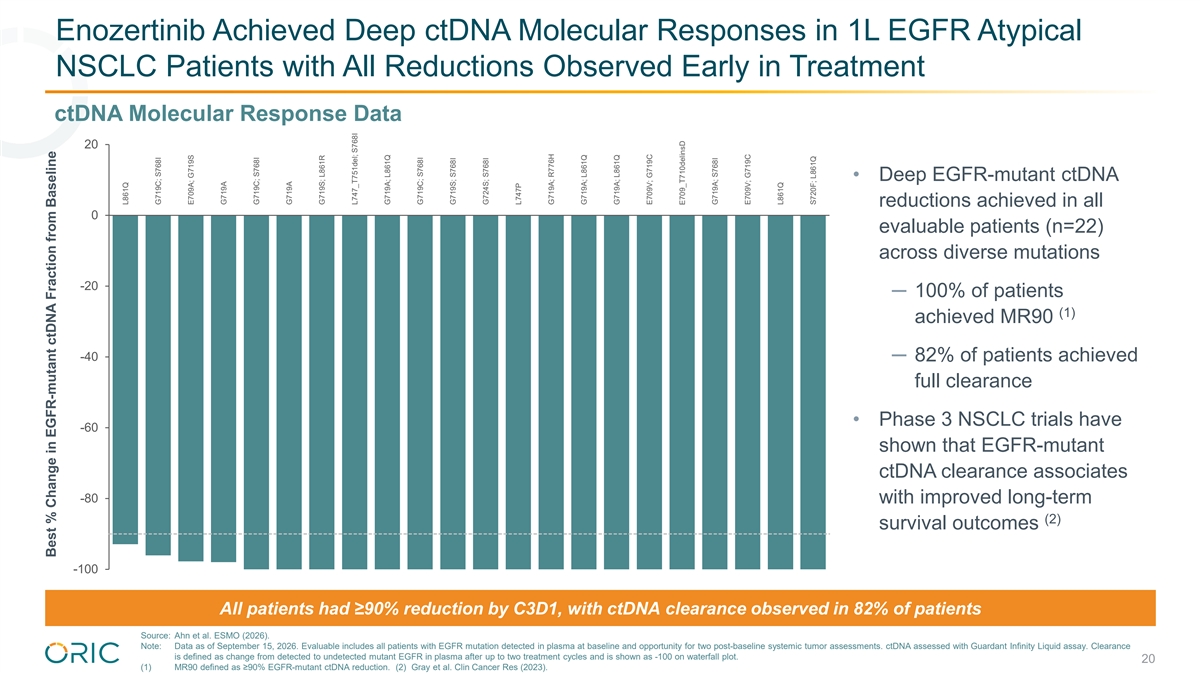
Enozertinib Achieved Deep ctDNA Molecular Responses in 1L EGFR Atypical NSCLC Patients with All Reductions Observed Early in Treatment ctDNA Molecular Response Data 20 • Deep EGFR-mutant ctDNA reductions achieved in all 0 evaluable patients (n=22) across diverse mutations -20 ─ 100% of patients (1) achieved MR90 -40 ─ 82% of patients achieved full clearance • Phase 3 NSCLC trials have -60 shown that EGFR-mutant ctDNA clearance associates -80 with improved long-term (2) survival outcomes -100 All patients had ≥90% reduction by C3D1, with ctDNA clearance observed in 82% of patients Source: Ahn et al. ESMO (2026). Note: Data as of September 15, 2026. Evaluable includes all patients with EGFR mutation detected in plasma at baseline and opportunity for two post-baseline systemic tumor assessments. ctDNA assessed with Guardant Infinity Liquid assay. Clearance is defined as change from detected to undetected mutant EGFR in plasma after up to two treatment cycles and is shown as -100 on waterfall plot. 20 (1) MR90 defined as ≥90% EGFR-mutant ctDNA reduction. (2) Gray et al. Clin Cancer Res (2023). Best % Change in EGFR-mutant ctDNA Fraction from Baseline L861Q G719C; S768I E709A; G719S G719A G719C; S768I G719A G719S; L861R L747_T751del; S768I G719A; L861Q G719C; S768I G719S; S768I G724S; S768I L747P G719A; R776H G719A; L861Q G719A; L861Q E709V; G719C E709_T710delinsD G719A; S768I E709V; G719C L861Q S720F; L861Q
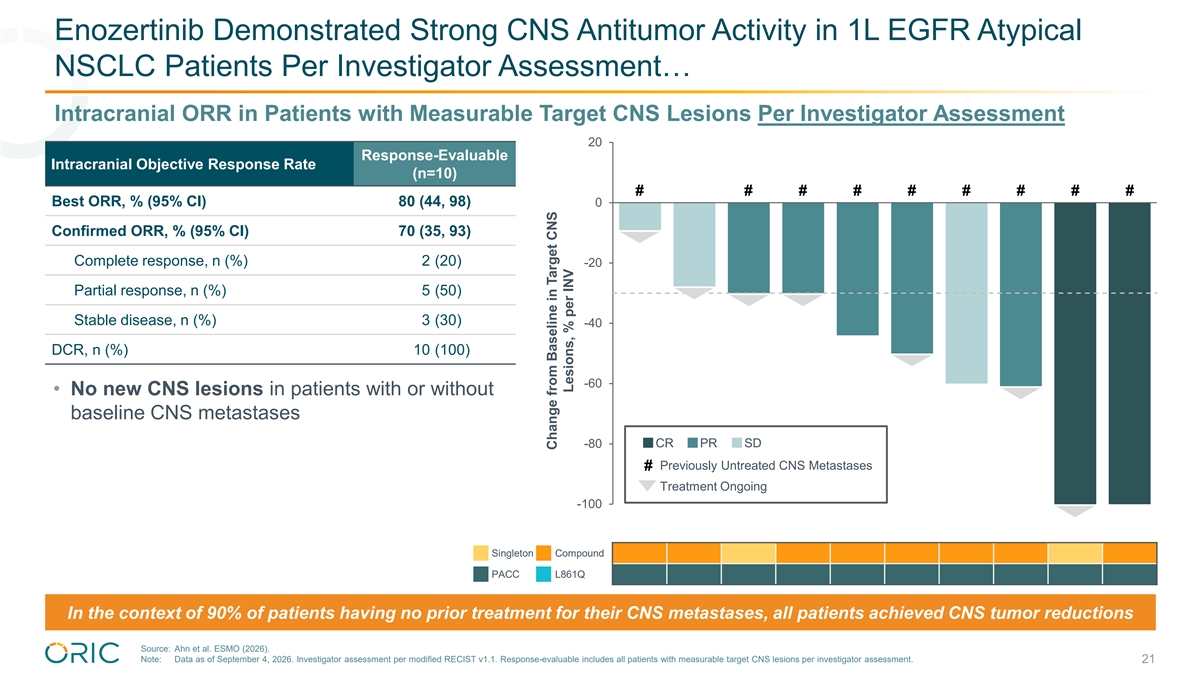
Enozertinib Demonstrated Strong CNS Antitumor Activity in 1L EGFR Atypical NSCLC Patients Per Investigator Assessment… Intracranial ORR in Patients with Measurable Target CNS Lesions Per Investigator Assessment 20 Response-Evaluable Intracranial Objective Response Rate (n=10) # # # # # # # # # Best ORR, % (95% CI) 80 (44, 98) 0 Confirmed ORR, % (95% CI) 70 (35, 93) • Complete response, n (%) 2 (20) -20 Partial response, n (%) 5 (50) • • • Stable disease, n (%) 3 (30) -40 DCR, n (%) 10 (100) • -60 • No new CNS lesions in patients with or without • baseline CNS metastases -80 CR PR SD Previously Untreated CNS Metastases # Treatment Ongoing -100 • Singleton Compound PACC L861Q In the context of 90% of patients having no prior treatment for their CNS metastases, all patients achieved CNS tumor reductions Source: Ahn et al. ESMO (2026). Note: Data as of September 4, 2026. Investigator assessment per modified RECIST v1.1. Response-evaluable includes all patients with measurable target CNS lesions per investigator assessment. 21 Change from Baseline in Target CNS Lesions, % per INV
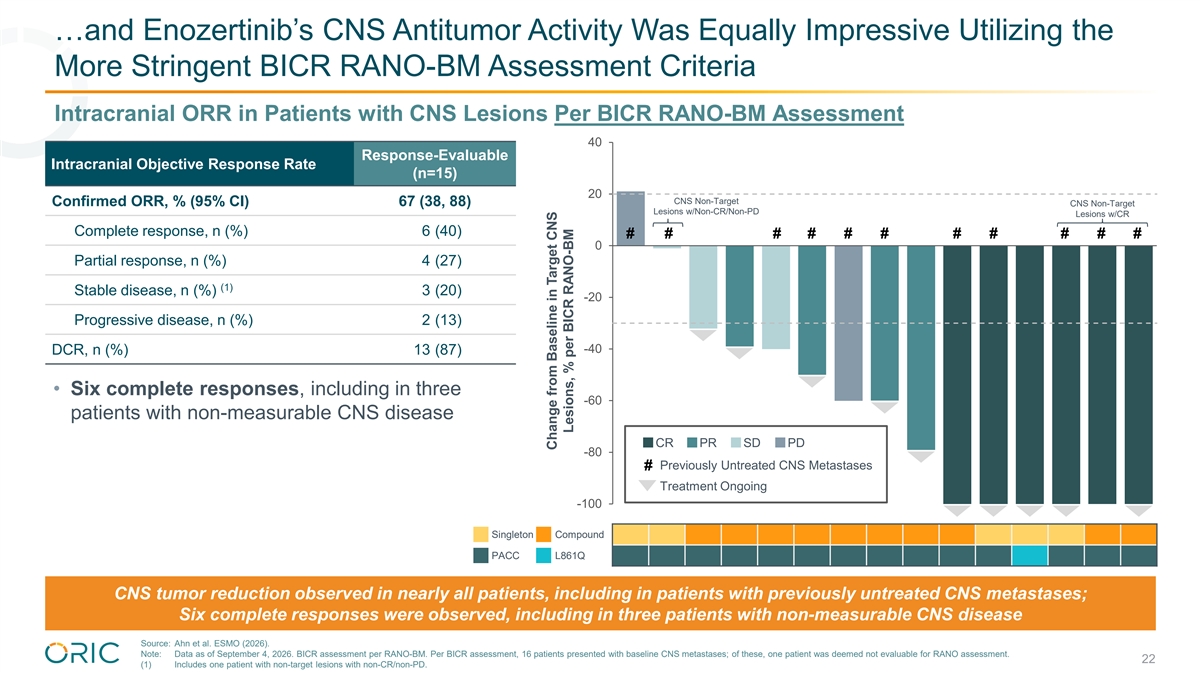
…and Enozertinib’s CNS Antitumor Activity Was Equally Impressive Utilizing the More Stringent BICR RANO-BM Assessment Criteria Intracranial ORR in Patients with CNS Lesions Per BICR RANO-BM Assessment 40 Response-Evaluable Intracranial Objective Response Rate (n=15) 20 CNS Non-Target Confirmed ORR, % (95% CI) 67 (38, 88) CNS Non-Target Lesions w/Non-CR/Non-PD Lesions w/CR Complete response, n (%) 6 (40) # # # # # # # # # # # 0 Partial response, n (%) 4 (27) (1) Stable disease, n (%) 3 (20) -20 Progressive disease, n (%) 2 (13) • -40 DCR, n (%) 13 (87) • • • Six complete responses, including in three -60 • patients with non-measurable CNS disease CR PR SD PD -80 • Previously Untreated CNS Metastases # Treatment Ongoing -100 • • • • • Singleton Compound PACC L861Q CNS tumor reduction observed in nearly all patients, including in patients with previously untreated CNS metastases; Six complete responses were observed, including in three patients with non-measurable CNS disease Source: Ahn et al. ESMO (2026). Note: Data as of September 4, 2026. BICR assessment per RANO-BM. Per BICR assessment, 16 patients presented with baseline CNS metastases; of these, one patient was deemed not evaluable for RANO assessment. 22 (1) Includes one patient with non-target lesions with non-CR/non-PD. Change from Baseline in Target CNS Lesions, % per BICR RANO-BM
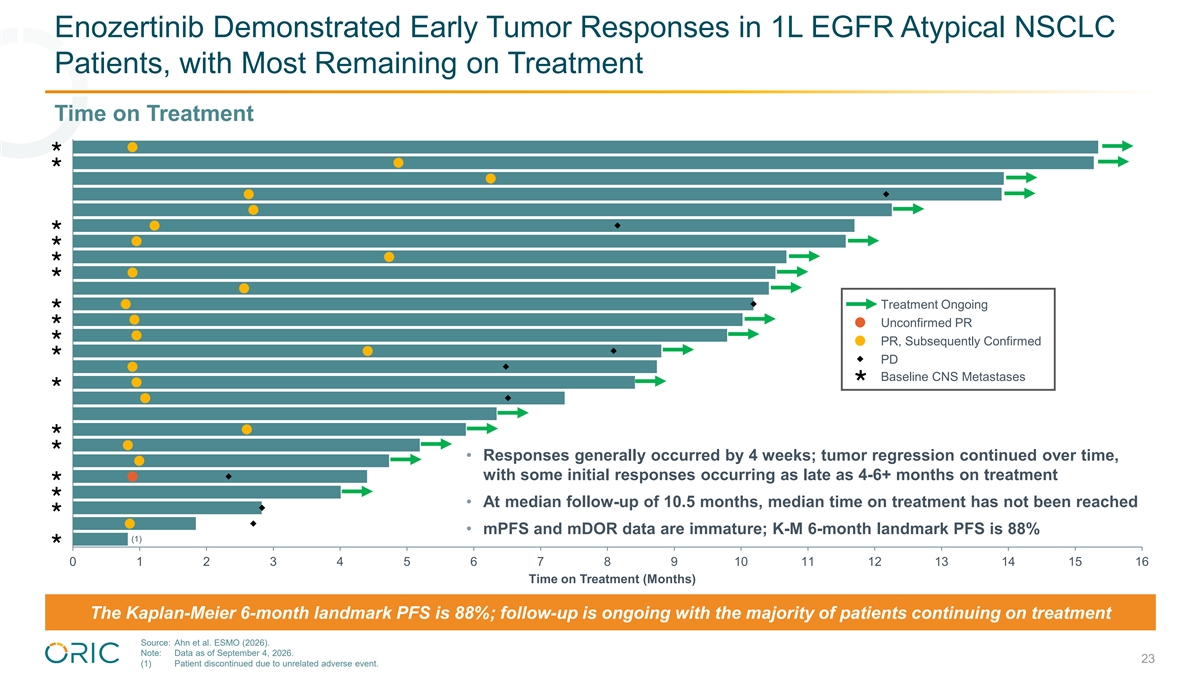
Enozertinib Demonstrated Early Tumor Responses in 1L EGFR Atypical NSCLC Patients, with Most Remaining on Treatment Time on Treatment × × × × × × × Treatment Ongoing × Unconfirmed PR × PR, Subsequently Confirmed × PD Ø Baseline CNS Metastases × × × • Responses generally occurred by 4 weeks; tumor regression continued over time, × with some initial responses occurring as late as 4-6+ months on treatment × • At median follow-up of 10.5 months, median time on treatment has not been reached × • mPFS and mDOR data are immature; K-M 6-month landmark PFS is 88% (1) × 0 1 2 3 4 5 6 7 8 9 10 11 12 13 14 15 16 Time on Treatment (Months) The Kaplan-Meier 6-month landmark PFS is 88%; follow-up is ongoing with the majority of patients continuing on treatment Source: Ahn et al. ESMO (2026). Note: Data as of September 4, 2026. 23 (1) Patient discontinued due to unrelated adverse event.
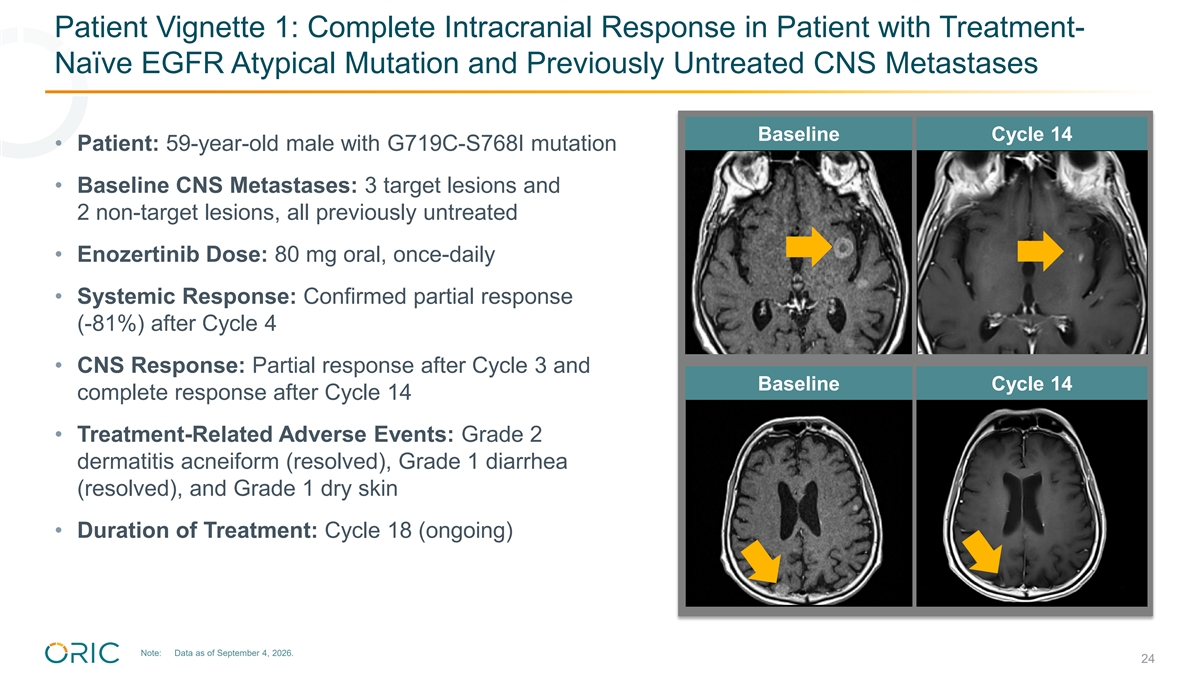
Patient Vignette 1: Complete Intracranial Response in Patient with Treatment- Naïve EGFR Atypical Mutation and Previously Untreated CNS Metastases Baseline Cycle 14 • Patient: 59-year-old male with G719C-S768I mutation • Baseline CNS Metastases: 3 target lesions and 2 non-target lesions, all previously untreated • Enozertinib Dose: 80 mg oral, once-daily • Systemic Response: Confirmed partial response (-81%) after Cycle 4 • CNS Response: Partial response after Cycle 3 and Baseline Cycle 14 complete response after Cycle 14 • Treatment-Related Adverse Events: Grade 2 dermatitis acneiform (resolved), Grade 1 diarrhea (resolved), and Grade 1 dry skin • Duration of Treatment: Cycle 18 (ongoing) Note: Data as of September 4, 2026. 24
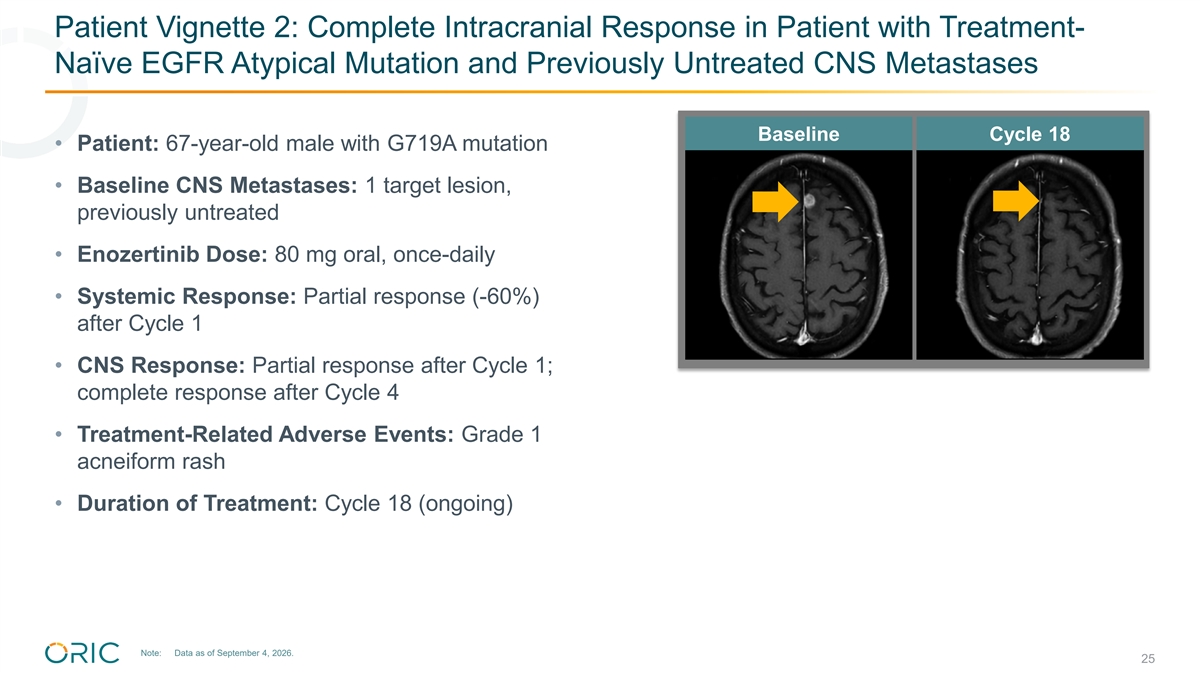
Patient Vignette 2: Complete Intracranial Response in Patient with Treatment- Naïve EGFR Atypical Mutation and Previously Untreated CNS Metastases Baseline Cycle 18 • Patient: 67-year-old male with G719A mutation • Baseline CNS Metastases: 1 target lesion, previously untreated • Enozertinib Dose: 80 mg oral, once-daily • Systemic Response: Partial response (-60%) after Cycle 1 • CNS Response: Partial response after Cycle 1; complete response after Cycle 4 • Treatment-Related Adverse Events: Grade 1 acneiform rash • Duration of Treatment: Cycle 18 (ongoing) Note: Data as of September 4, 2026. 25
Next Steps in 1L EGFR Atypical
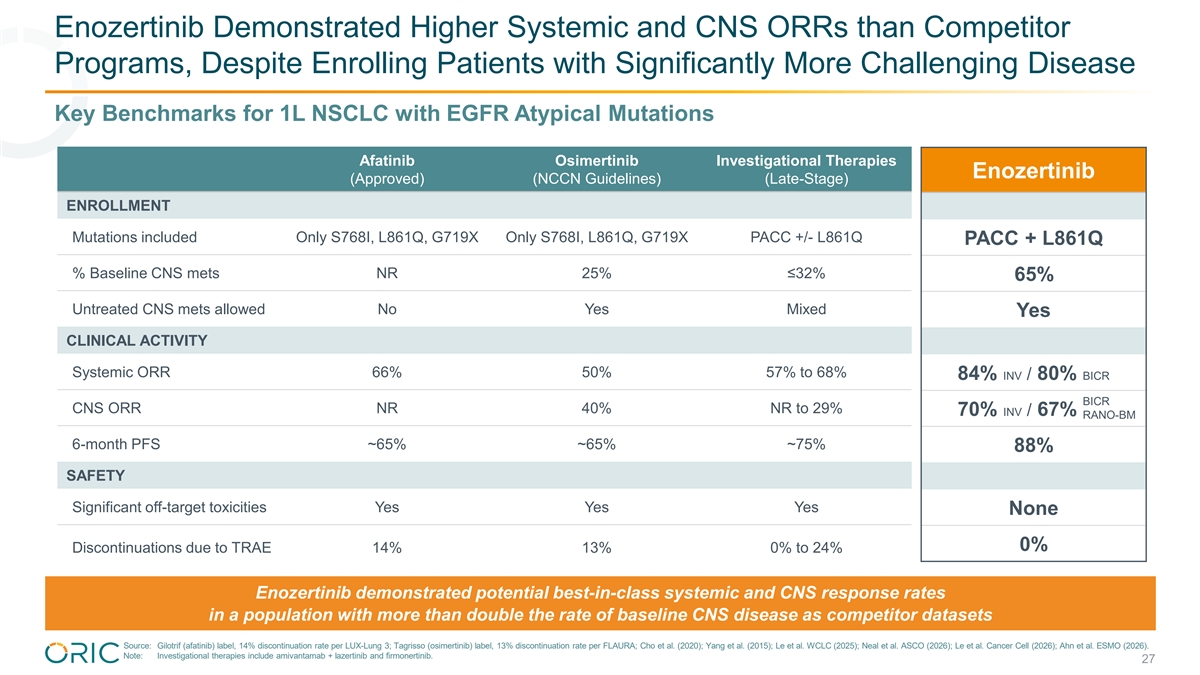
Enozertinib Demonstrated Higher Systemic and CNS ORRs than Competitor Programs, Despite Enrolling Patients with Significantly More Challenging Disease Key Benchmarks for 1L NSCLC with EGFR Atypical Mutations Afatinib Osimertinib Investigational Therapies Enozertinib (Approved) (NCCN Guidelines) (Late-Stage) ENROLLMENT Mutations included Only S768I, L861Q, G719X Only S768I, L861Q, G719X PACC +/- L861Q PACC + L861Q % Baseline CNS mets NR 25% ≤32% 65% Untreated CNS mets allowed No Yes Mixed Yes CLINICAL ACTIVITY Systemic ORR 66% 50% 57% to 68% 84% INV / 80% BICR BICR CNS ORR NR 40% NR to 29% 70% INV / 67% BICR RANO-BM 6-month PFS ~65% ~65% ~75% 88% SAFETY Significant off-target toxicities Yes Yes Yes None 0% Discontinuations due to TRAE 14% 13% 0% to 24% Enozertinib demonstrated potential best-in-class systemic and CNS response rates in a population with more than double the rate of baseline CNS disease as competitor datasets Source: Gilotrif (afatinib) label, 14% discontinuation rate per LUX-Lung 3; Tagrisso (osimertinib) label, 13% discontinuation rate per FLAURA; Cho et al. (2020); Yang et al. (2015); Le et al. WCLC (2025); Neal et al. ASCO (2026); Le et al. Cancer Cell (2026); Ahn et al. ESMO (2026). Note: Investigational therapies include amivantamab + lazertinib and firmonertinib. 27
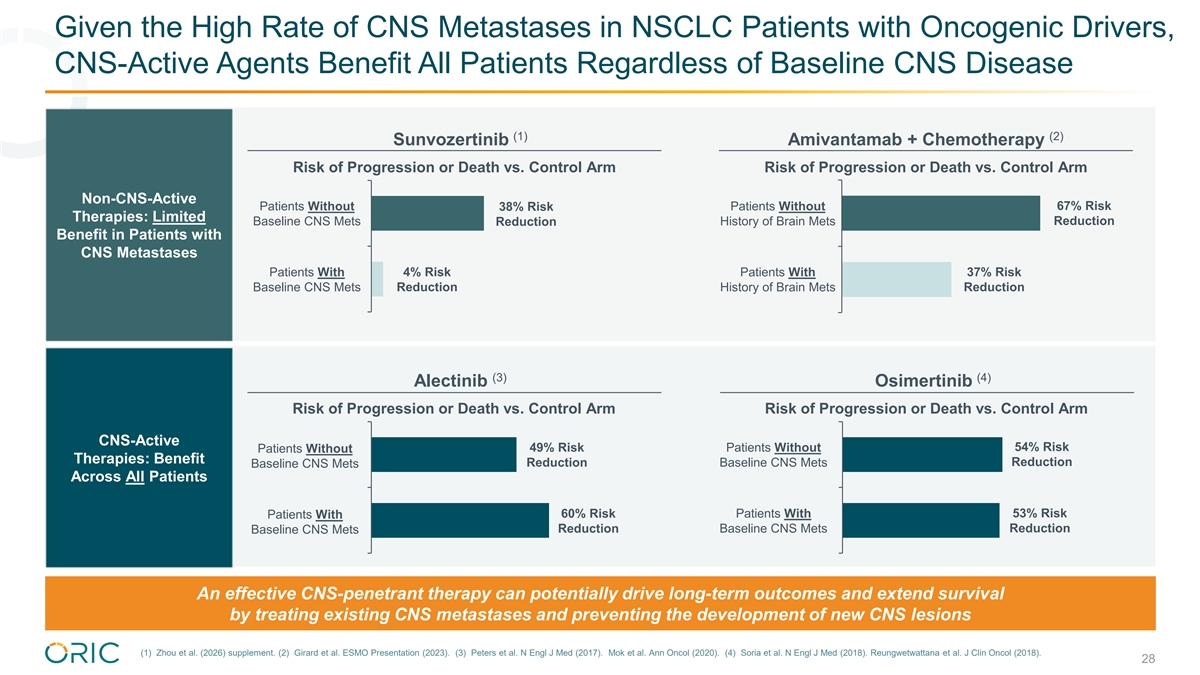
Given the High Rate of CNS Metastases in NSCLC Patients with Oncogenic Drivers, CNS-Active Agents Benefit All Patients Regardless of Baseline CNS Disease (1) (2) Sunvozertinib Amivantamab + Chemotherapy Risk of Progression or Death vs. Control Arm Risk of Progression or Death vs. Control Arm Non-CNS-Active Patients Without Patients Without 67% Risk 38% Risk Therapies: Limited Baseline CNS Mets History of Brain Mets Reduction Reduction Benefit in Patients with CNS Metastases Patients With 4% Risk Patients With 37% Risk Baseline CNS Mets Reduction History of Brain Mets Reduction (3) (4) Alectinib Osimertinib Risk of Progression or Death vs. Control Arm Risk of Progression or Death vs. Control Arm CNS-Active 54% Risk Patients Without 49% Risk Patients Without Therapies: Benefit Reduction Baseline CNS Mets Reduction Baseline CNS Mets Across All Patients 60% Risk Patients With 53% Risk Patients With Reduction Baseline CNS Mets Reduction Baseline CNS Mets An effective CNS-penetrant therapy can potentially drive long-term outcomes and extend survival by treating existing CNS metastases and preventing the development of new CNS lesions (1) Zhou et al. (2026) supplement. (2) Girard et al. ESMO Presentation (2023). (3) Peters et al. N Engl J Med (2017). Mok et al. Ann Oncol (2020). (4) Soria et al. N Engl J Med (2018). Reungwetwattana et al. J Clin Oncol (2018). 28
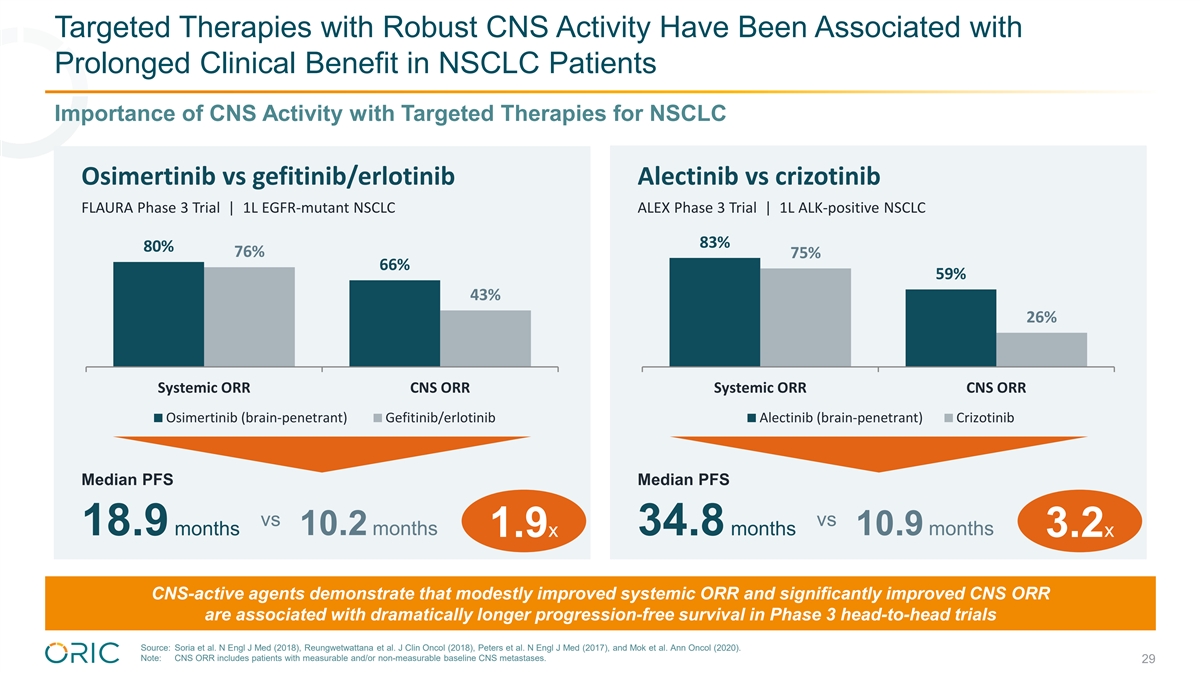
Targeted Therapies with Robust CNS Activity Have Been Associated with Prolonged Clinical Benefit in NSCLC Patients Importance of CNS Activity with Targeted Therapies for NSCLC Osimertinib vs gefitinib/erlotinib Alectinib vs crizotinib FLAURA Phase 3 Trial | 1L EGFR-mutant NSCLC ALEX Phase 3 Trial | 1L ALK-positive NSCLC 83% 80% 76% 75% 66% 59% 43% 26% Systemic ORR CNS ORR Systemic ORR CNS ORR Osimertinib (brain-penetrant) Gefitinib/erlotinib Alectinib (brain-penetrant) Crizotinib Median PFS Median PFS vs vs 1.9x 3.2x 18.9 months 10.2 months 34.8 months 10.9 months 1.9x 3.2x CNS-active agents demonstrate that modestly improved systemic ORR and significantly improved CNS ORR are associated with dramatically longer progression-free survival in Phase 3 head-to-head trials Source: Soria et al. N Engl J Med (2018), Reungwetwattana et al. J Clin Oncol (2018), Peters et al. N Engl J Med (2017), and Mok et al. Ann Oncol (2020). Note: CNS ORR includes patients with measurable and/or non-measurable baseline CNS metastases. 29
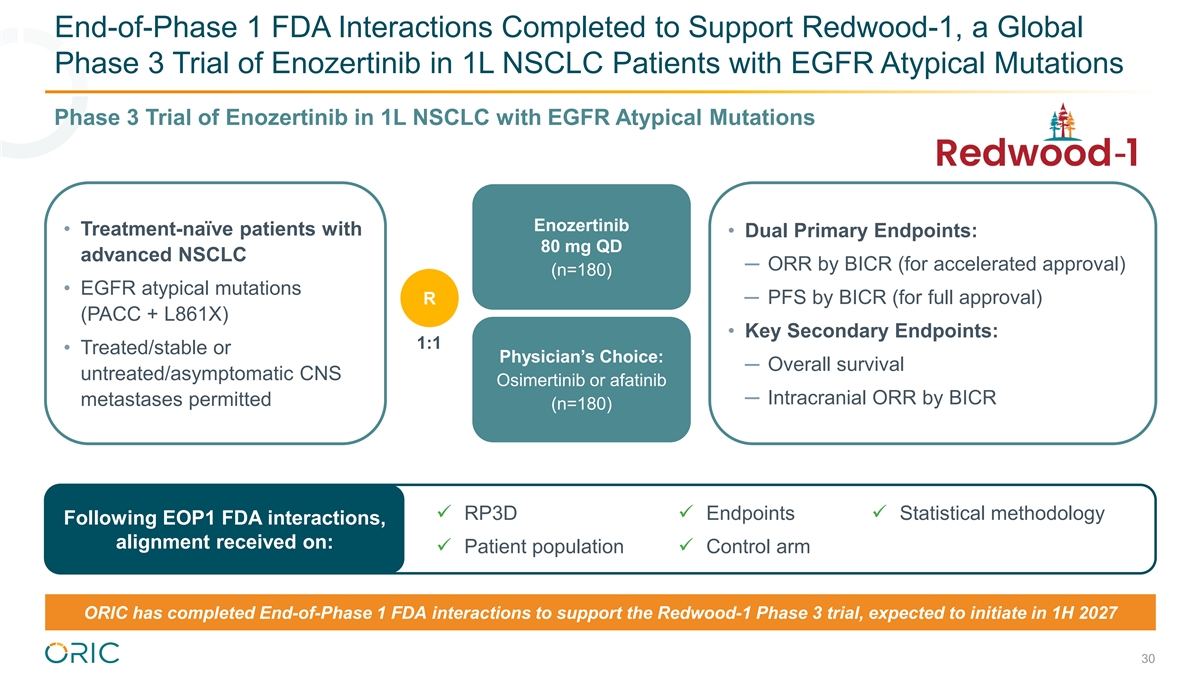
End-of-Phase 1 FDA Interactions Completed to Support Redwood-1, a Global Phase 3 Trial of Enozertinib in 1L NSCLC Patients with EGFR Atypical Mutations Phase 3 Trial of Enozertinib in 1L NSCLC with EGFR Atypical Mutations Enozertinib • Treatment-naïve patients with • Dual Primary Endpoints: 80 mg QD advanced NSCLC ─ ORR by BICR (for accelerated approval) (n=180) • EGFR atypical mutations ─ PFS by BICR (for full approval) R (PACC + L861X) • Key Secondary Endpoints: 1:1 • Treated/stable or Physician’s Choice: ─ Overall survival untreated/asymptomatic CNS Osimertinib or afatinib ─ Intracranial ORR by BICR metastases permitted (n=180) ü RP3Dü Endpointsü Statistical methodology Following EOP1 FDA interactions, alignment received on: ü Patient populationü Control arm ORIC has completed End-of-Phase 1 FDA interactions to support the Redwood-1 Phase 3 trial, expected to initiate in 1H 2027 30
KOL Perspectives on Enozertinib
KOL Perspectives on Enozertinib Discussion with Dr. Joshua Sabari, Enozertinib Trial Investigator Guest KOL Biography Topics of Discussion Joshua Sabari, MD • Unmet need in the EGFR atypical • Thoracic medical oncologist at NYU landscape Langone Health and Assistant Professor of Medicine at NYU Grossman • Experience with enozertinib and • Investigator across multiple clinical trials commentary on Phase 1b data evaluating targeted therapies and immuno-therapies • Enozertinib in the context of the • Author or co-author on over 70 peer-reviewed publications current development landscape • After receiving his MD from Rutgers, Dr. Sabari completed his Internal Medicine Residency at Montefiore Medical Center, and • Next steps for enozertinib a Medical Oncology Fellowship at Memorial Sloan Kettering development Cancer Center 32

Commercial Potential

Enozertinib Is Initially Pursuing a Significant Addressable Market in 1L EGFR Atypical NSCLC Enozertinib Total Addressable Market in 1L EGFR Atypical NSCLC US Annual Incidence Best-in-Class Profile That Achieves Total Addressable Leadership Market Share 7,000 Market: ü Meaningful systemic activity Duration >$2.5 billion US opportunity ü Compelling CNS activity 15+ Months ü Durable clinical benefit >$5.0 billion Price Global opportunity ü Well-tolerated profile Current TKI Pricing 1L EGFR atypical NSCLC is an attractive market opportunity for a CNS-penetrant agent that extends durability; Enozertinib is positioned to potentially capture substantial market share with a best-in-class profile Source: American Cancer Society Cancer Facts & Figures 2026, Zhang et al. Oncotarget (2016), Robichaux et al. Nature (2021), and ORIC data on file. Note: EGFR atypical includes PACC + L861X. 34
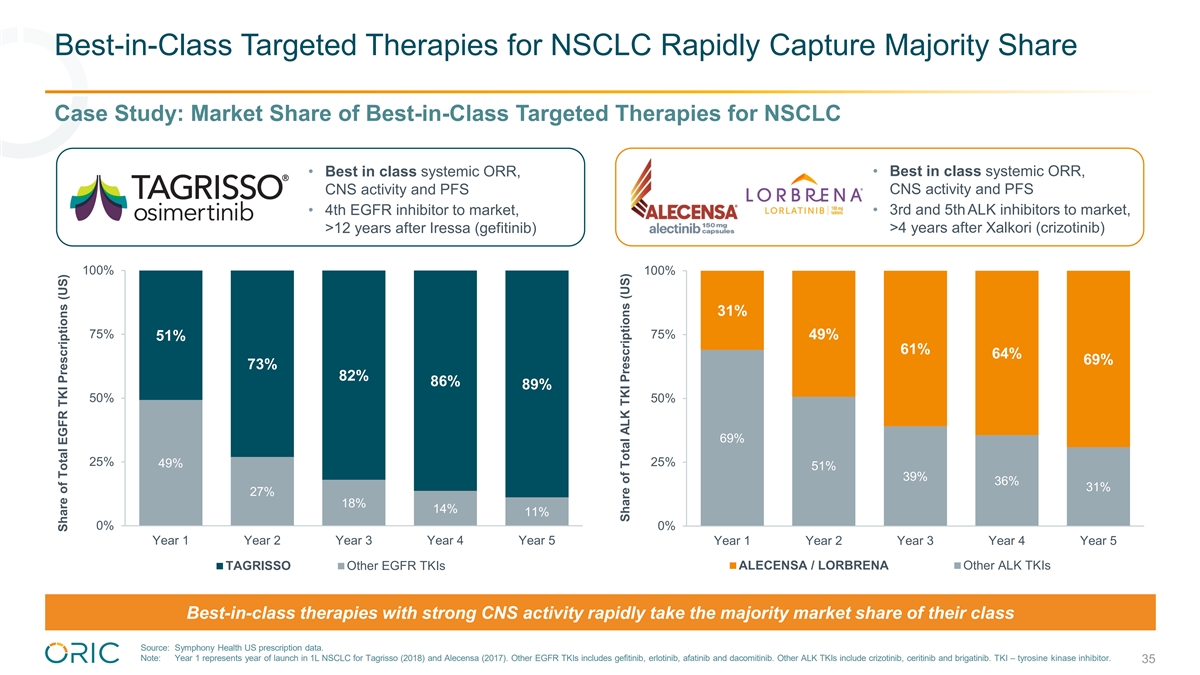
Best-in-Class Targeted Therapies for NSCLC Rapidly Capture Majority Share Case Study: Market Share of Best-in-Class Targeted Therapies for NSCLC • Best in class systemic ORR, • Best in class systemic ORR, CNS activity and PFS CNS activity and PFS • 4th EGFR inhibitor to market, • 3rd and 5thALK inhibitors to market, >4 years after Xalkori (crizotinib) >12 years after Iressa (gefitinib) 100% 100% 31% 75% 75% 49% 51% 61% 64% 69% 73% 82% 86% 89% 50% 50% 69% 25% 25% 49% 51% 39% 36% 31% 27% 18% 14% 11% 0% 0% Year 1 Year 2 Year 3 Year 4 Year 5 Year 1 Year 2 Year 3 Year 4 Year 5 TAGRISSO Other EGFR TKIs ALECENSA / LORBRENA Other ALK TKIs Best-in-class therapies with strong CNS activity rapidly take the majority market share of their class Source: Symphony Health US prescription data. Note: Year 1 represents year of launch in 1L NSCLC for Tagrisso (2018) and Alecensa (2017). Other EGFR TKIs includes gefitinib, erlotinib, afatinib and dacomitinib. Other ALK TKIs include crizotinib, ceritinib and brigatinib. TKI – tyrosine kinase inhibitor. 35 Share of Total EGFR TKI Prescriptions (US) Share of Total ALK TKI Prescriptions (US)
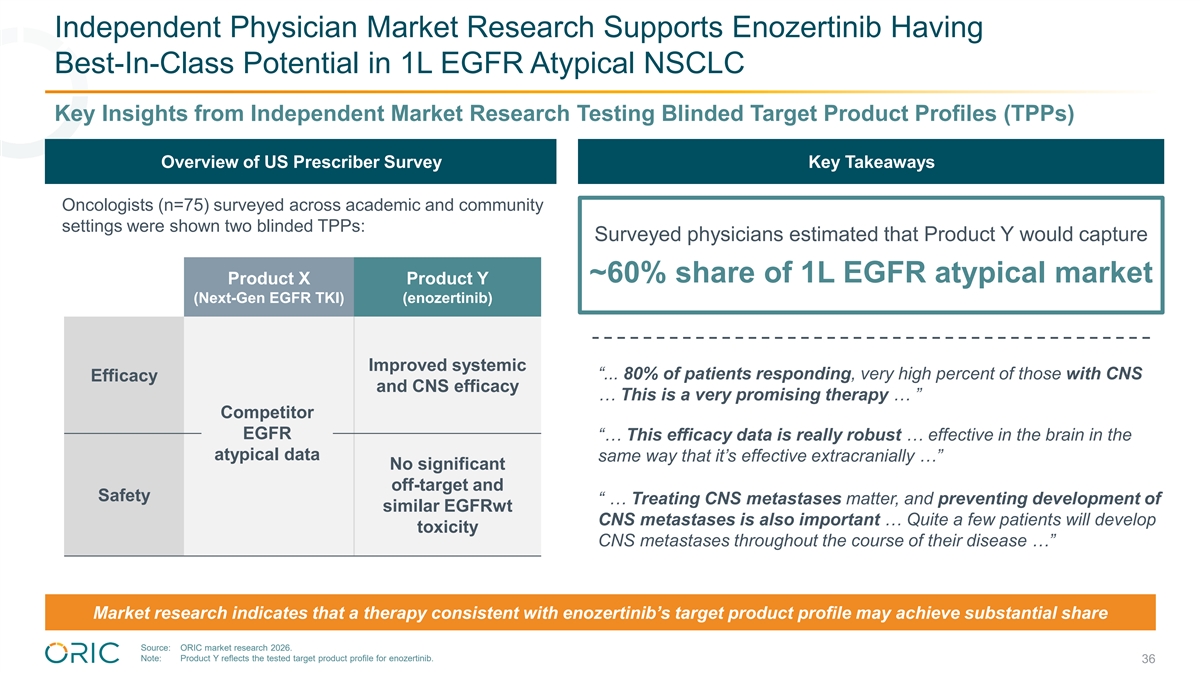
Independent Physician Market Research Supports Enozertinib Having Best-In-Class Potential in 1L EGFR Atypical NSCLC Key Insights from Independent Market Research Testing Blinded Target Product Profiles (TPPs) Overview of US Prescriber Survey Key Takeaways Oncologists (n=75) surveyed across academic and community settings were shown two blinded TPPs: Surveyed physicians estimated that Product Y would capture ~60% share of 1L EGFR atypical market Product X Product Y (Next-Gen EGFR TKI) (enozertinib) Improved systemic “... 80% of patients responding, very high percent of those with CNS Efficacy and CNS efficacy … This is a very promising therapy … ” Competitor EGFR “… This efficacy data is really robust … effective in the brain in the atypical data same way that it’s effective extracranially …” No significant off-target and Safety “ … Treating CNS metastases matter, and preventing development of similar EGFRwt CNS metastases is also important … Quite a few patients will develop toxicity CNS metastases throughout the course of their disease …” Market research indicates that a therapy consistent with enozertinib’s target product profile may achieve substantial share Source: ORIC market research 2026. Note: Product Y reflects the tested target product profile for enozertinib. 36

Executive Summary and Next Steps

Enozertinib Establishes Potential Best-in-Class Profile in 1L EGFR Atypical NSCLC, with Data Supporting Rapid Advancement to Phase 3 Executive Summary • 1L EGFR Atypical NSCLC is a >$2.5bn market opportunity in the US alone and lacks a best-in-class therapy with meaningful systemic efficacy, compelling CNS activity, and favorable tolerability • In a global 1L EGFR Atypical population with over double the rate of baseline CNS disease as competitor datasets, including untreated CNS metastases, enozertinib raises the efficacy benchmarks by achieving: – 84% confirmed systemic ORR – 70% confirmed CNS ORR, with multiple complete responses – 88% 6-month landmark PFS • Competitive safety profile: no significant off-target toxicity and no treatment-related discontinuations • ORIC plans to initiate Redwood-1, a global Phase 3 trial in 1L EGFR Atypical NSCLC, in 1H 2027 Source: Ahn et al. ESMO (2026) and ORIC data on file. 38
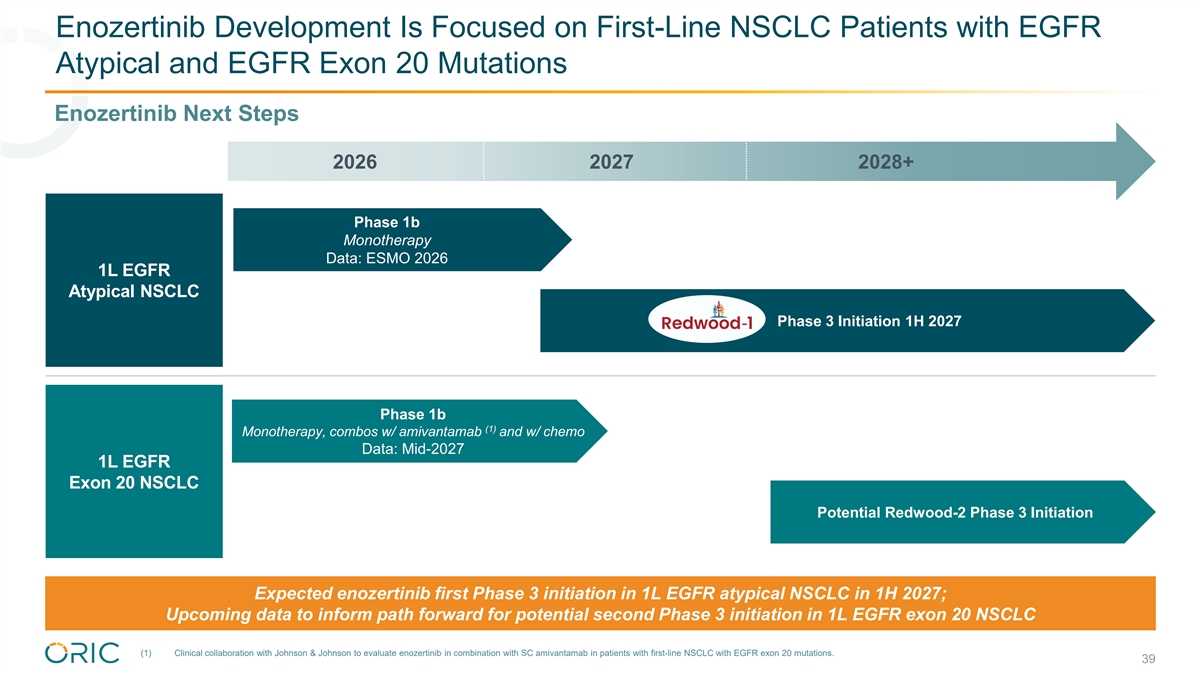
Enozertinib Development Is Focused on First-Line NSCLC Patients with EGFR Atypical and EGFR Exon 20 Mutations Enozertinib Next Steps 2026 2027 2028+ Phase 1b Monotherapy Data: ESMO 2026 1L EGFR Atypical NSCLC Phase 3 Initiation 1H 2027 Phase 1b (1) Monotherapy, combos w/ amivantamab and w/ chemo Data: Mid-2027 1L EGFR Exon 20 NSCLC Potential Redwood-2 Phase 3 Initiation Expected enozertinib first Phase 3 initiation in 1L EGFR atypical NSCLC in 1H 2027; Upcoming data to inform path forward for potential second Phase 3 initiation in 1L EGFR exon 20 NSCLC (1) Clinical collaboration with Johnson & Johnson to evaluate enozertinib in combination with SC amivantamab in patients with first-line NSCLC with EGFR exon 20 mutations. 39

Thank You