

Study ‘304’ Part A Phase 3 Topline Data in Males with Mild-to-Moderate Pattern Hair Loss October 2026 OCTOBER 2026

agenda 3 1 Opening Remarks 2 Study ‘304’ Results 3 KOL Discussion 4 VDPHL01 Commercial Opportunity 5 Closing Remarks 6 Q&A Reid Waldman, M.D. Chief Executive Officer, Veradermics Mark Neumann Chief Commercial & Strategy Officer, Veradermics Dominic Carrano Chief Financial Officer, Veradermics Michael Payette, M.D., M.B.A. Co-Founder, Central Connecticut Dermatology MANE Speakers Joined by OCTOBER 2026

This presentation contains forward-looking statements that involve substantial risks and uncertainties. All statements other than historical factual information are forward-looking statements, including without limitation statements regarding our product development activities for VDPHL01 and ongoing clinical trials; the ability of clinical trials to demonstrate safety and efficacy of VDPHL01; the beneficial characteristics, and the potential safety, efficacy and therapeutic effects of VDPHL01; our ability to develop and advance our potential future product candidates and programs; our ability to pursue and execute our strategy for our indications, business, programs and technology; our ability to leverage existing programs and to progress additional programs, the timing of investigational new drug application submissions; the timing of and our ability to obtain and maintain regulatory approval of our product candidates; our ability to compete with companies currently selling, marketing or engaged in the development of treatments for diseases that our product candidates are designed to target, including pattern hair loss (PHL); our estimates regarding the size and growth potential of the commercial opportunity for VDPHL01 and our current product candidates or other product candidates we may identify and pursue, and our ability to serve those markets; objectives for future operations and other estimates contained herein. In some cases, you can identify forward-looking statements because they contain words such as “may,” “will,” “shall,” “should,” “expect,” “plan,” “anticipate,” “could,” “intend,” “target,” “project,” “contemplate,” “believe,” “estimate,” “predict,” “potential” or “continue” or the negative of these words or other similar expressions that concern our expectations, strategy, plans or intentions, although not all forward-looking statements are accompanied by such words. Forward-looking statements are based on assumptions and assessments made by our management in light of their experience and perceptions of historical trends, current conditions, expected future developments and other factors they believe to be appropriate, and speak only as of the date of this presentation. Disclaimer 4 Forward-looking statements involve known and unknown risks, uncertainties and other factors that may cause our actual results, performance or other events to be materially different from any future results, performance or other events expressed or implied by the forward-looking statements, including the risks and uncertainties identified in the "Risk Factors" section of our Quarterly Report on Form 10-Q for the period ended June 30, 2026, and subsequent filings with the U.S. Securities and Exchange Commission. Given these uncertainties, you should not place undue reliance on forward-looking statements. Our actual future results, performance or other events may be materially different from what we expect. Except as required by law, we assume no obligation to update these forward-looking statements, or to update the reasons actual results could differ materially from those anticipated in these forward-looking statements, even if new information becomes available in the future. Market data and industry information used throughout this presentation are based on management’s knowledge of the industry and the good faith estimates of management. We also relied, to the extent available, upon management’s review of independent industry surveys and publications and other publicly available information prepared by a number of third-party sources. All of the market data and industry information used in this presentation involves a number of assumptions and limitations, and you are cautioned not to give undue weight to such estimates. Although we believe that these sources are reliable as of their respective dates, we cannot guarantee the accuracy or completeness of this information, and we have not independently verified this information. Projections, assumptions and estimates of our future performance and the future performance of the industry in which we operate are necessarily subject to a high degree of uncertainty and risk due to a variety of factors. These and other factors could cause results to differ materially from those expressed in our estimates and beliefs and in the estimates prepared by independent parties. The trademarks included herein are the property of the owners thereof and are used for reference purposes only. Such use should not be construed as an endorsement of such products. This presentation discusses potential future product candidates that are investigational only and have not yet been approved for marketing by the U.S. Food and Drug Administration. No representation is made as to the safety or effectiveness of these potential future product candidates for the use for which such potential future product candidates are being studied. OCTOBER 2026
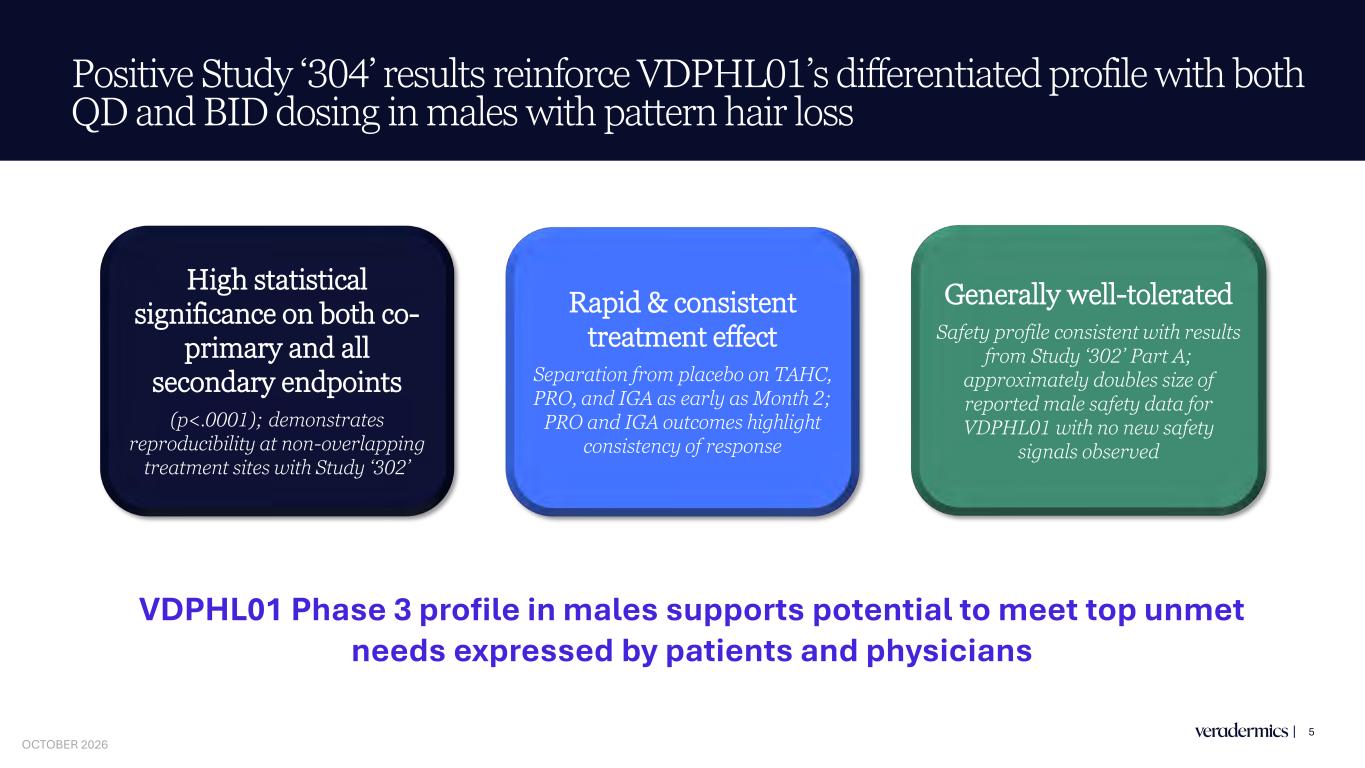
Positive Study ‘304’ results reinforce VDPHL01’s differentiated profile with both QD and BID dosing in males with pattern hair loss 5 High statistical significance on both co- primary and all secondary endpoints (p<.0001); demonstrates reproducibility at non-overlapping treatment sites with Study ‘302’ Rapid & consistent treatment effect Separation from placebo on TAHC, PRO, and IGA as early as Month 2; PRO and IGA outcomes highlight consistency of response Generally well-tolerated Safety profile consistent with results from Study ‘302’ Part A; approximately doubles size of reported male safety data for VDPHL01 with no new safety signals observed VDPHL01 Phase 3 profile in males supports potential to meet top unmet needs expressed by patients and physicians OCTOBER 2026
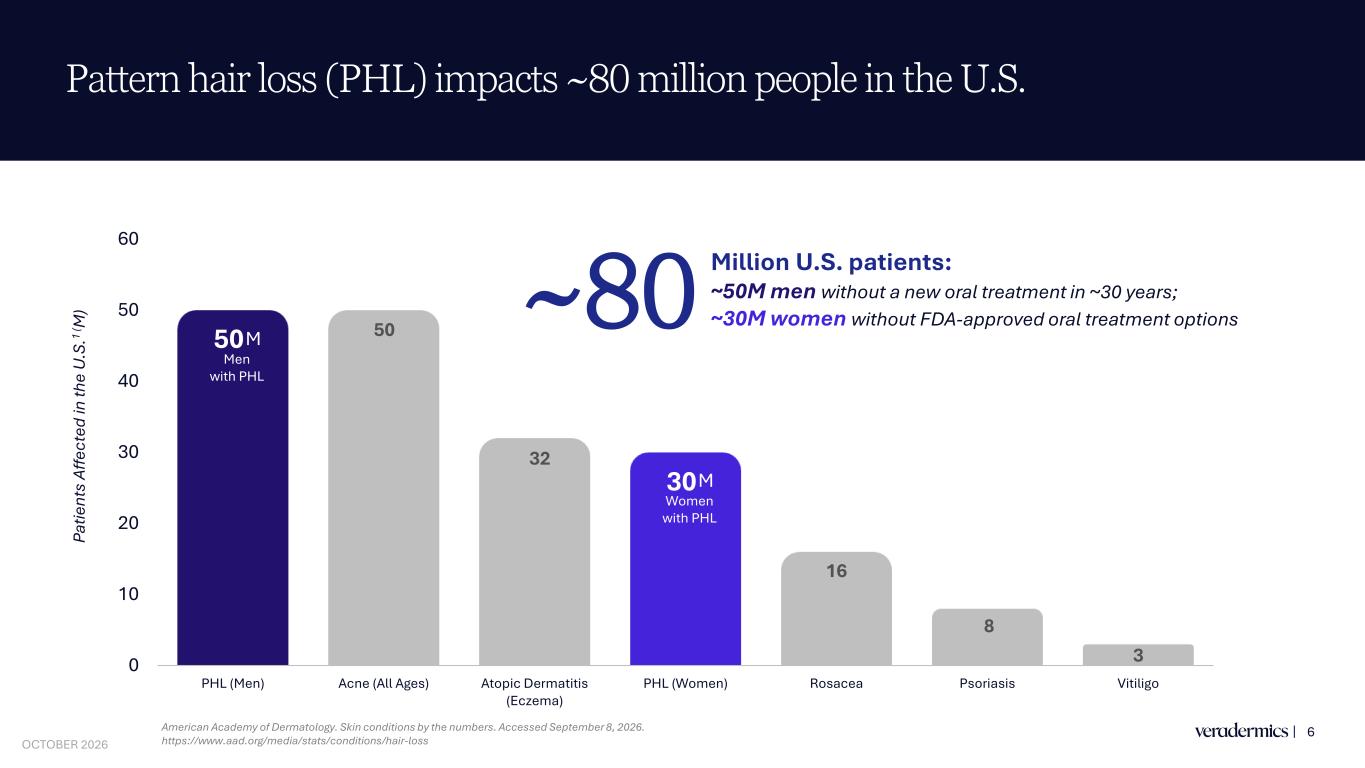
50 50 32 30 16 8 30 10 20 30 40 50 60 PHL (Men) Acne (All Ages) Atopic Dermatitis (Eczema) PHL (Women) Rosacea Psoriasis Vitiligo Pattern hair loss (PHL) impacts ~80 million people in the U.S. 6 M Men with PHL Pa tie nt s Af fe ct ed in th e U .S .1 ( M ) American Academy of Dermatology. Skin conditions by the numbers. Accessed September 8, 2026. https://www.aad.org/media/stats/conditions/hair-loss M Women with PHL Million U.S. patients: ~50M men without a new oral treatment in ~30 years; ~30M women without FDA-approved oral treatment options~80 OCTOBER 2026
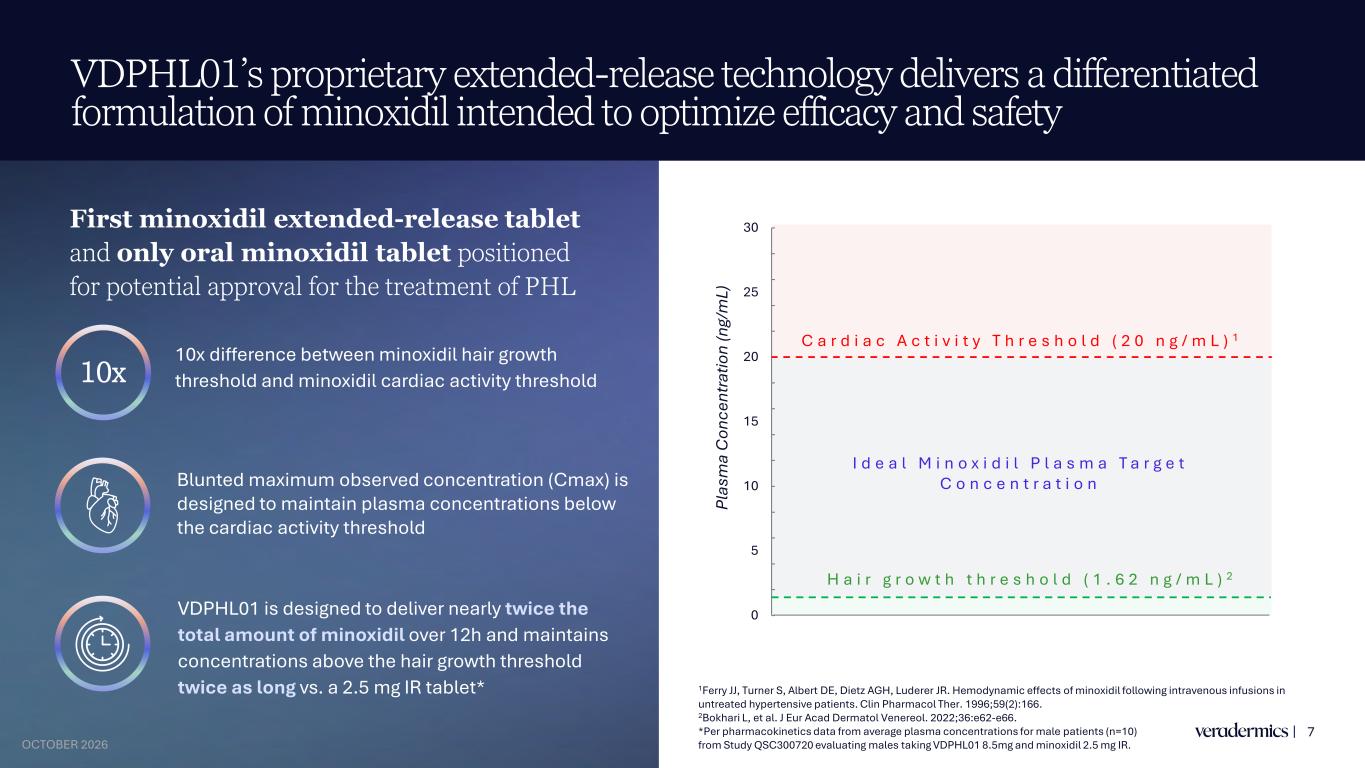
VDPHL01’s proprietary extended-release technology delivers a differentiated formulation of minoxidil intended to optimize efficacy and safety 7 10x difference between minoxidil hair growth threshold and minoxidil cardiac activity threshold VDPHL01 is designed to deliver nearly twice the total amount of minoxidil over 12h and maintains concentrations above the hair growth threshold twice as long vs. a 2.5 mg IR tablet* First minoxidil extended-release tablet and only oral minoxidil tablet positioned for potential approval for the treatment of PHL 10x Blunted maximum observed concentration (Cmax) is designed to maintain plasma concentrations below the cardiac activity threshold 1Ferry JJ, Turner S, Albert DE, Dietz AGH, Luderer JR. Hemodynamic effects of minoxidil following intravenous infusions in untreated hypertensive patients. Clin Pharmacol Ther. 1996;59(2):166. 2Bokhari L, et al. J Eur Acad Dermatol Venereol. 2022;36:e62-e66. *Per pharmacokinetics data from average plasma concentrations for male patients (n=10) from Study QSC300720 evaluating males taking VDPHL01 8.5mg and minoxidil 2.5 mg IR. 0 5 10 15 20 25 30 Pl as m a C on ce nt ra tio n (n g/ m L) C a r d i a c A c t i v i t y T h r e s h o l d ( 2 0 n g / m L ) 1 H a i r g r o w t h t h r e s h o l d ( 1 . 6 2 n g / m L ) 2 I d e a l M i n o x i d i l P l a s m a T a r g e t C o n c e n t r a t i o n OCTOBER 2026
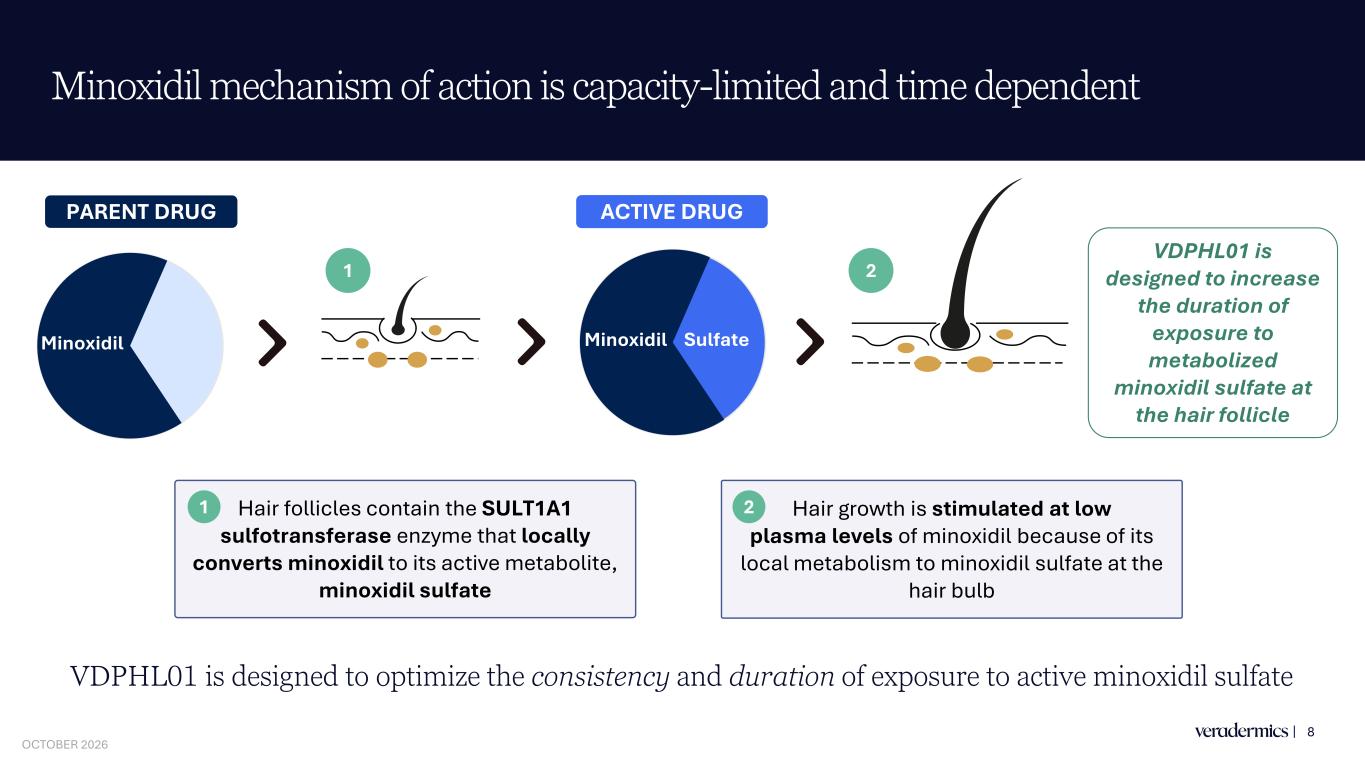
Minoxidil mechanism of action is capacity-limited and time dependent 8 Minoxidil Hair follicles contain the SULT1A1 sulfotransferase enzyme that locally converts minoxidil to its active metabolite, minoxidil sulfate Hair growth is stimulated at low plasma levels of minoxidil because of its local metabolism to minoxidil sulfate at the hair bulb 2 VDPHL01 is designed to increase the duration of exposure to metabolized minoxidil sulfate at the hair follicle PARENT DRUG ACTIVE DRUG 1 1 2 Minoxidil Sulfate VDPHL01 is designed to optimize the consistency and duration of exposure to active minoxidil sulfate OCTOBER 2026

VDPHL01 represents a late-stage opportunity in PHL 9 • Phase 3 registration-directed study in females • Parallel in-trial Phase 2 component to further assess PRO endpoints in the Phase 3 portion of the study. • Fully enrolled; Part A topline data readout anticipated in 1H27 • Second Phase 3 registration-directed study in males • Part A topline data announced today • Phase 3 registration-directed study in males • Parallel in-trial Phase 2 component to further assess patient reported outcome (PRO) endpoints in Studies ‘302’ & ‘304’ • Positive topline data from Part A of Study ‘302’ announced April 2026; Part B topline data readout anticipated in 2H26 Study ‘302’ Phase 2/3 trial evaluated VDPHL01 in 519 males with pattern hair loss Study ‘304’ Phase 3 trial evaluating VDPHL01 in 536 males with pattern hair loss Study ‘306’ Phase 2/3 trial evaluating VDPHL01 in 556 females with pattern hair loss OCTOBER 2026
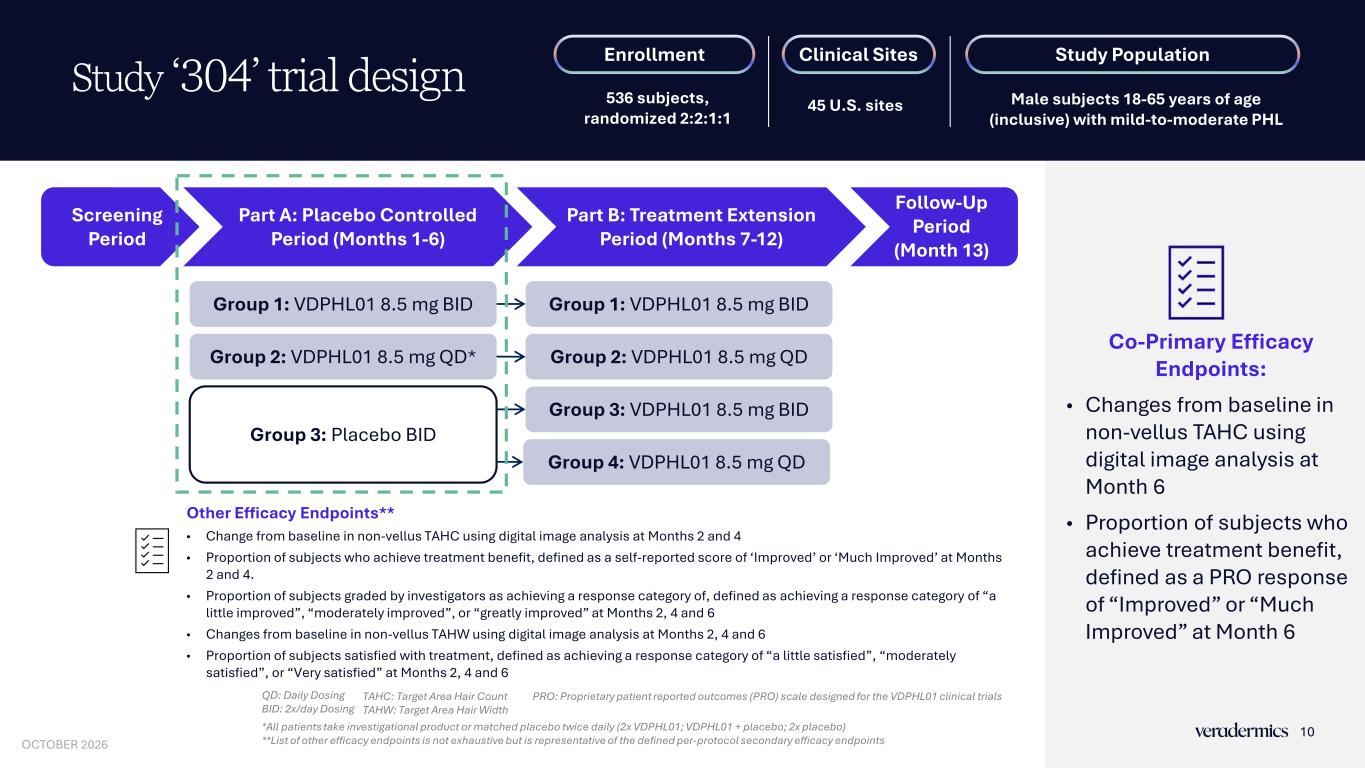
Co-Primary Efficacy Endpoints: • Changes from baseline in non-vellus TAHC using digital image analysis at Month 6 • Proportion of subjects who achieve treatment benefit, defined as a PRO response of “Improved” or “Much Improved” at Month 6 Study ‘304’ trial design QD: Daily Dosing BID: 2x/day Dosing *All patients take investigational product or matched placebo twice daily (2x VDPHL01; VDPHL01 + placebo; 2x placebo) **List of other efficacy endpoints is not exhaustive but is representative of the defined per-protocol secondary efficacy endpoints TAHC: Target Area Hair Count TAHW: Target Area Hair Width PRO: Proprietary patient reported outcomes (PRO) scale designed for the VDPHL01 clinical trials Other Efficacy Endpoints** • Change from baseline in non-vellus TAHC using digital image analysis at Months 2 and 4 • Proportion of subjects who achieve treatment benefit, defined as a self-reported score of ‘Improved’ or ‘Much Improved’ at Months 2 and 4. • Proportion of subjects graded by investigators as achieving a response category of, defined as achieving a response category of “a little improved”, “moderately improved”, or “greatly improved” at Months 2, 4 and 6 • Changes from baseline in non-vellus TAHW using digital image analysis at Months 2, 4 and 6 • Proportion of subjects satisfied with treatment, defined as achieving a response category of “a little satisfied”, “moderately satisfied”, or “Very satisfied” at Months 2, 4 and 6 Enrollment 536 subjects, randomized 2:2:1:1 Clinical Sites 45 U.S. sites Study Population Male subjects 18-65 years of age (inclusive) with mild-to-moderate PHL Screening Period Part A: Placebo Controlled Period (Months 1-6) Part B: Treatment Extension Period (Months 7-12) Group 1: VDPHL01 8.5 mg BID Group 2: VDPHL01 8.5 mg QD* Group 3: Placebo BID Group 1: VDPHL01 8.5 mg BID Group 2: VDPHL01 8.5 mg QD Group 3: VDPHL01 8.5 mg BID Group 4: VDPHL01 8.5 mg QD Follow-Up Period (Month 13) 10 OCTOBER 2026
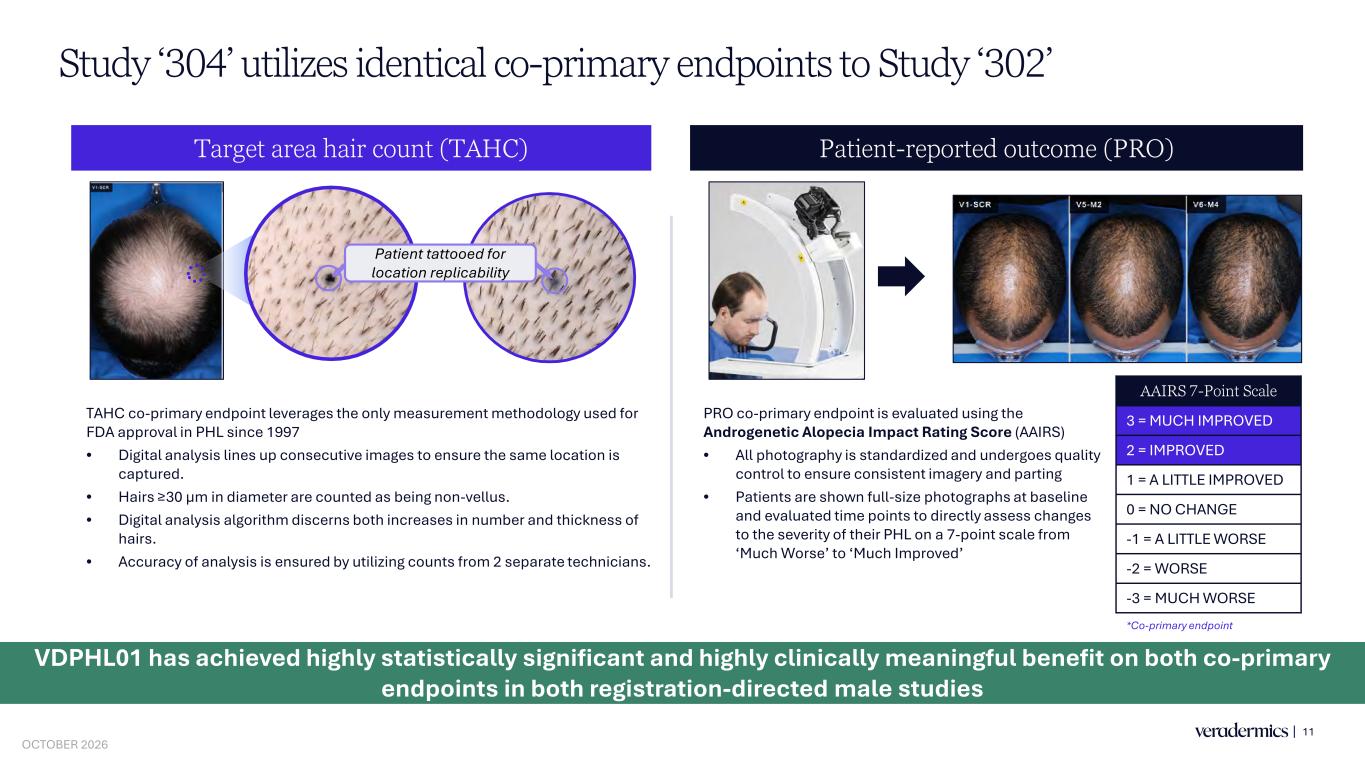
TAHC co-primary endpoint leverages the only measurement methodology used for FDA approval in PHL since 1997 • Digital analysis lines up consecutive images to ensure the same location is captured. • Hairs ≥30 μm in diameter are counted as being non-vellus. • Digital analysis algorithm discerns both increases in number and thickness of hairs. • Accuracy of analysis is ensured by utilizing counts from 2 separate technicians. Study ‘304’ utilizes identical co-primary endpoints to Study ‘302’ Target area hair count (TAHC) Patient-reported outcome (PRO) 11 Patient tattooed for location replicability PRO co-primary endpoint is evaluated using the Androgenetic Alopecia Impact Rating Score (AAIRS) • All photography is standardized and undergoes quality control to ensure consistent imagery and parting • Patients are shown full-size photographs at baseline and evaluated time points to directly assess changes to the severity of their PHL on a 7-point scale from ‘Much Worse’ to ‘Much Improved’ AAIRS 7-Point Scale 3 = MUCH IMPROVED 2 = IMPROVED 1 = A LITTLE IMPROVED 0 = NO CHANGE -1 = A LITTLE WORSE -2 = WORSE -3 = MUCH WORSE *Co-primary endpoint VDPHL01 has achieved highly statistically significant and highly clinically meaningful benefit on both co-primary endpoints in both registration-directed male studies OCTOBER 2026
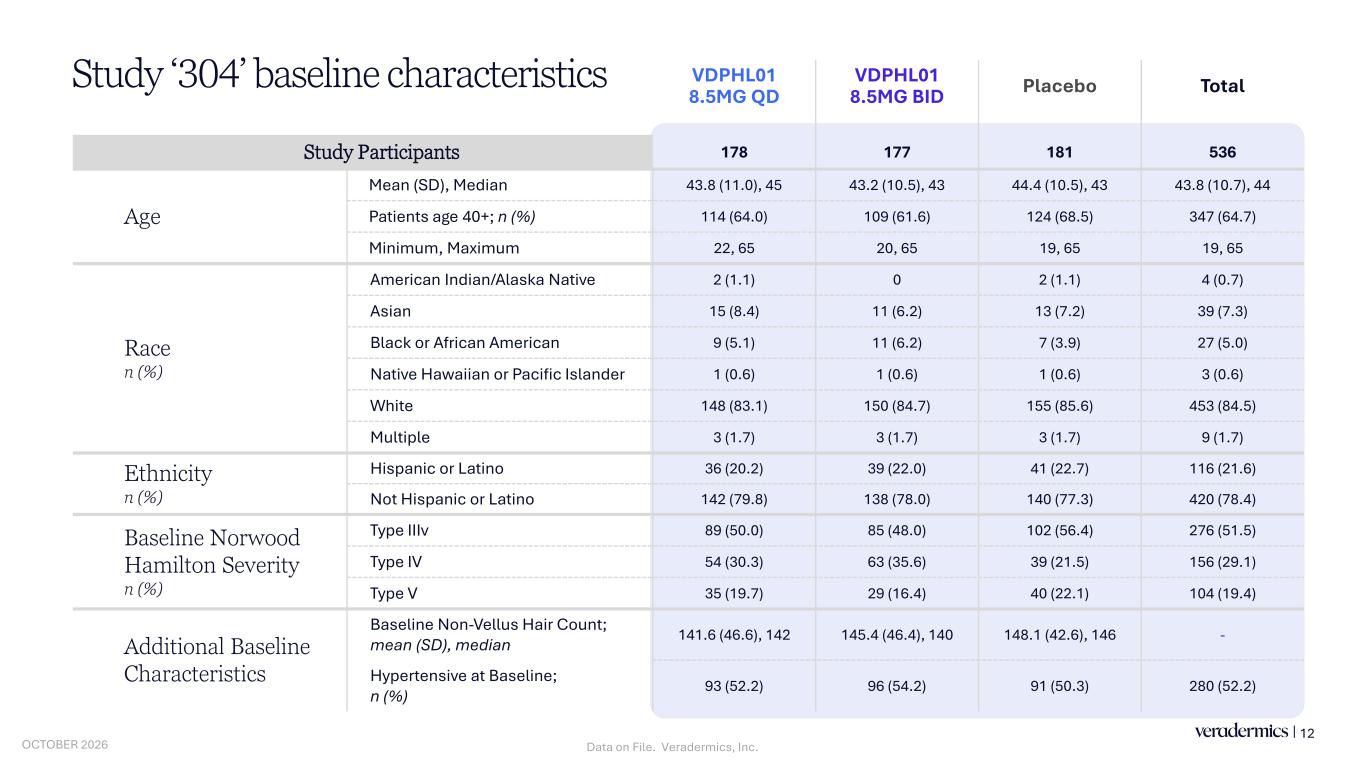
VDPHL01 8.5MG QD VDPHL01 8.5MG BID Placebo Total Study Participants 178 177 181 536 Age Mean (SD), Median 43.8 (11.0), 45 43.2 (10.5), 43 44.4 (10.5), 43 43.8 (10.7), 44 Patients age 40+; n (%) 114 (64.0) 109 (61.6) 124 (68.5) 347 (64.7) Minimum, Maximum 22, 65 20, 65 19, 65 19, 65 Race n (%) American Indian/Alaska Native 2 (1.1) 0 2 (1.1) 4 (0.7) Asian 15 (8.4) 11 (6.2) 13 (7.2) 39 (7.3) Black or African American 9 (5.1) 11 (6.2) 7 (3.9) 27 (5.0) Native Hawaiian or Pacific Islander 1 (0.6) 1 (0.6) 1 (0.6) 3 (0.6) White 148 (83.1) 150 (84.7) 155 (85.6) 453 (84.5) Multiple 3 (1.7) 3 (1.7) 3 (1.7) 9 (1.7) Ethnicity n (%) Hispanic or Latino 36 (20.2) 39 (22.0) 41 (22.7) 116 (21.6) Not Hispanic or Latino 142 (79.8) 138 (78.0) 140 (77.3) 420 (78.4) Baseline Norwood Hamilton Severity n (%) Type IIIv 89 (50.0) 85 (48.0) 102 (56.4) 276 (51.5) Type IV 54 (30.3) 63 (35.6) 39 (21.5) 156 (29.1) Type V 35 (19.7) 29 (16.4) 40 (22.1) 104 (19.4) Additional Baseline Characteristics Baseline Non-Vellus Hair Count; mean (SD), median 141.6 (46.6), 142 145.4 (46.4), 140 148.1 (42.6), 146 - Hypertensive at Baseline; n (%) 93 (52.2) 96 (54.2) 91 (50.3) 280 (52.2) Study ‘304’ baseline characteristics 12 Data on File. Veradermics, Inc.OCTOBER 2026
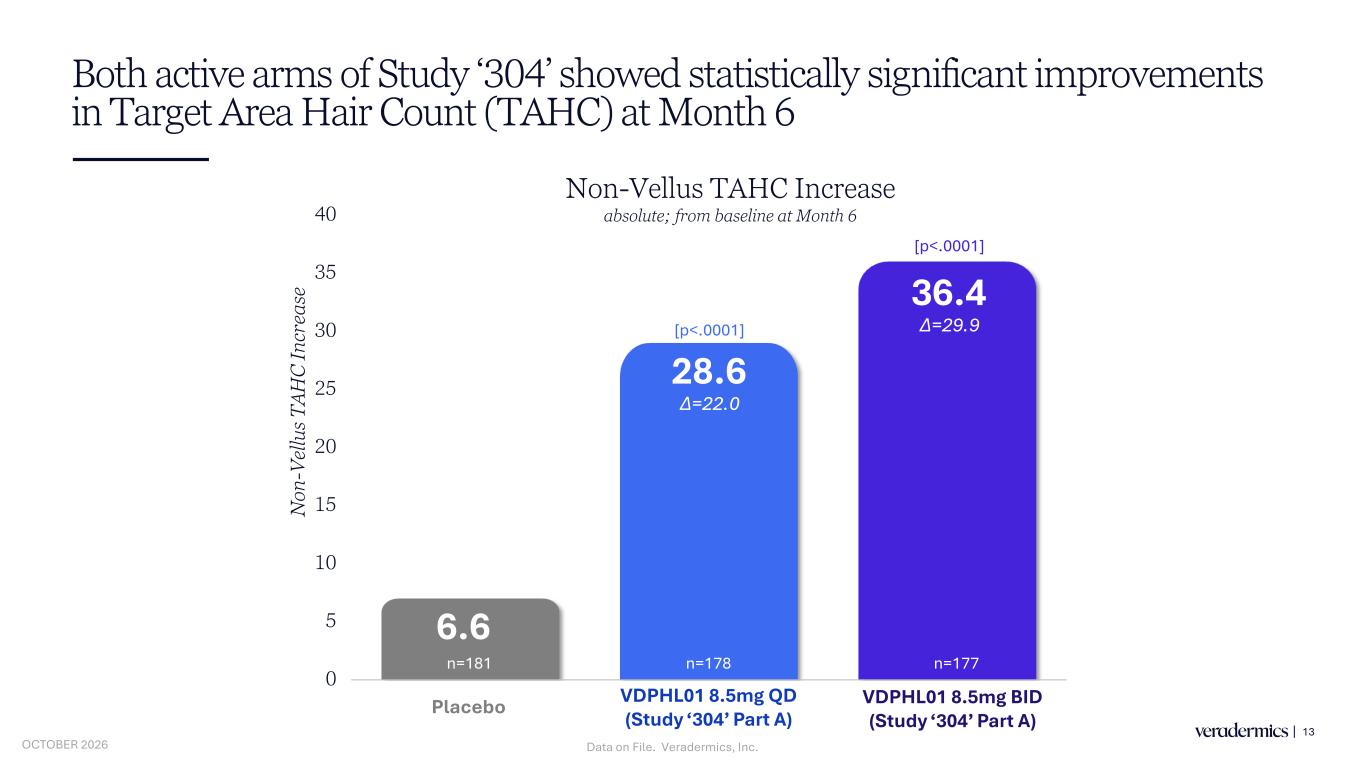
Both active arms of Study ‘304’ showed statistically significant improvements in Target Area Hair Count (TAHC) at Month 6 13 6.6 28.6 36.4 0 5 10 15 20 25 30 35 40 Placebo VDPHL01 8.5mg QD VDPHL01 8.5mg BID N on -V el lu s T AH C In cr ea se Non-Vellus TAHC Increase absolute; from baseline at Month 6 ∆=22.0 ∆=29.9[p<.0001] [p<.0001] Placebo n=178 n=177n=181 VDPHL01 8.5 g QD (Study ‘304’ Part A) VD 8.5mg BID (Study ‘304’ Part A) Data on File. Veradermics, Inc.OCTOBER 2026
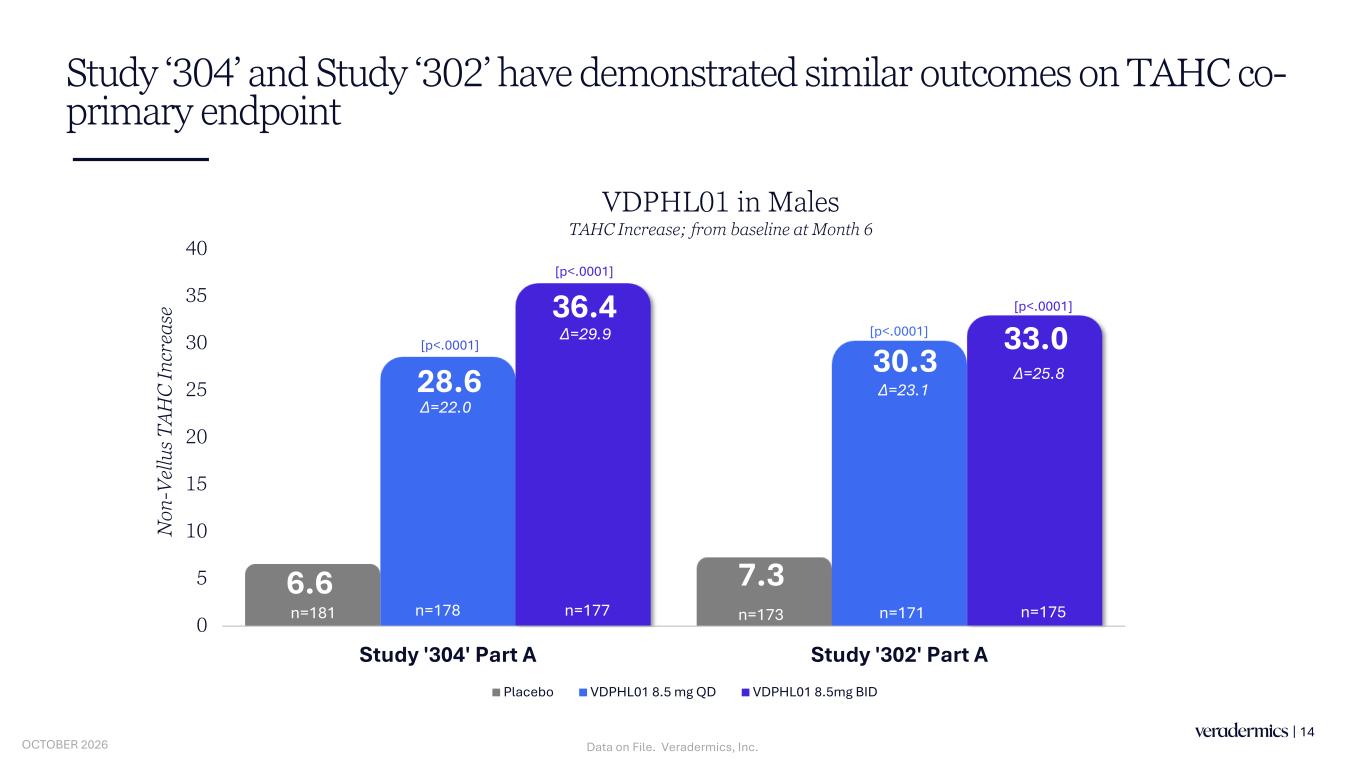
6.6 7.3 28.6 30.3 36.4 33.0 0 5 10 15 20 25 30 35 40 Study '304' Part A Study '302' Part A N on -V el lu s T AH C In cr ea se Placebo VDPHL01 8.5 mg QD VDPHL01 8.5mg BID Study ‘304’ and Study ‘302’ have demonstrated similar outcomes on TAHC co- primary endpoint 14 VDPHL01 in Males TAHC Increase; from baseline at Month 6 [p<.0001] [p<.0001] ∆=25.8 ∆=23.1 ∆=22.0 ∆=29.9 [p<.0001] [p<.0001] n=178 n=177n=181 n=173 n=175n=171 Data on File. Veradermics, Inc.OCTOBER 2026
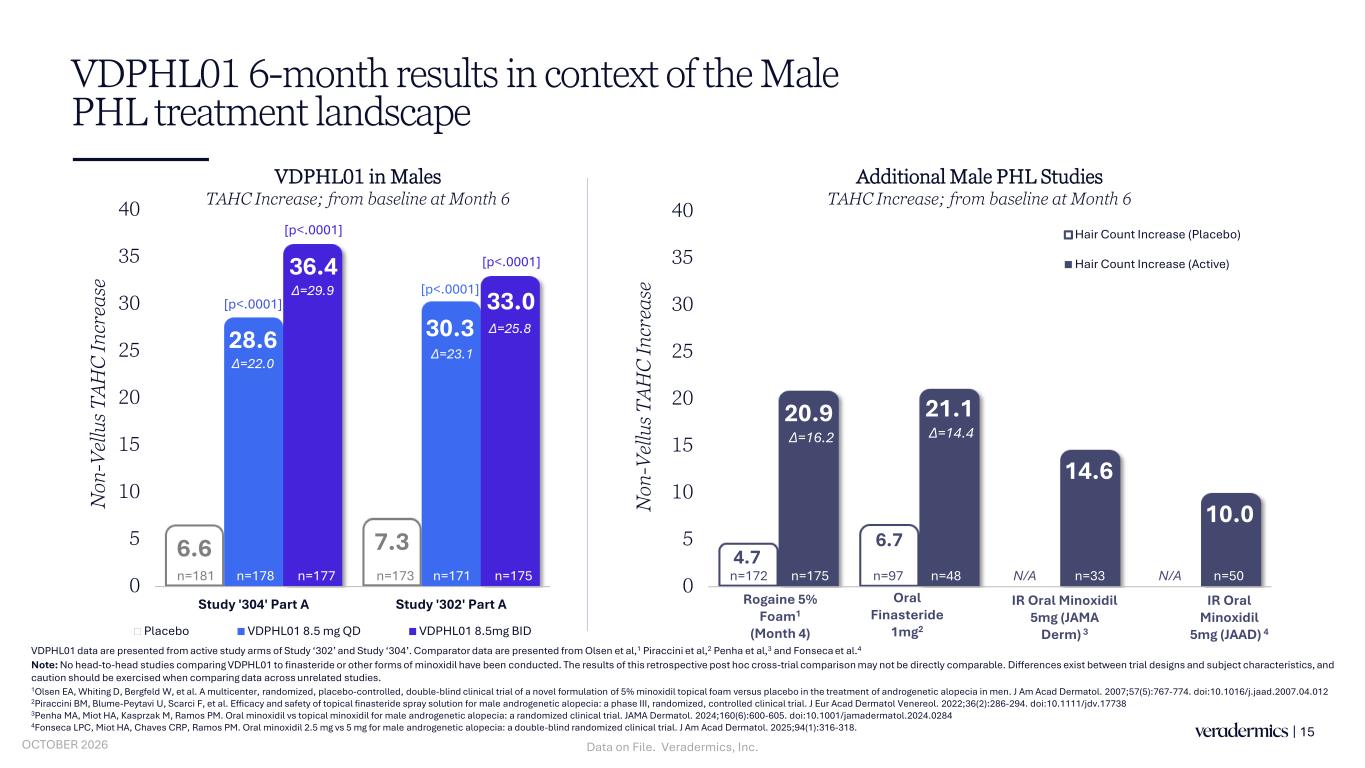
4.7 6.7 20.9 21.1 14.6 10.0 0 5 10 15 20 25 30 35 40 Rogaine 5% Foam (Males; Month 4) Oral Finasteride IR Oral Minoxidil 5mg (JAMA Derm) IR Oral Minoxidil 5mg (JAAD) N on -V el lu s T AH C In cr ea se Hair Count Increase (Placebo) Hair Count Increase (Active) VDPHL01 6-month results in context of the Male PHL treatment landscape 15 VDPHL01 data are presented from active study arms of Study ‘302’ and Study ‘304’. Comparator data are presented from Olsen et al,1 Piraccini et al,2 Penha et al,3 and Fonseca et al.4 Note: No head-to-head studies comparing VDPHL01 to finasteride or other forms of minoxidil have been conducted. The results of this retrospective post hoc cross-trial comparison may not be directly comparable. Differences exist between trial designs and subject characteristics, and caution should be exercised when comparing data across unrelated studies. 1Olsen EA, Whiting D, Bergfeld W, et al. A multicenter, randomized, placebo-controlled, double-blind clinical trial of a novel formulation of 5% minoxidil topical foam versus placebo in the treatment of androgenetic alopecia in men. J Am Acad Dermatol. 2007;57(5):767-774. doi:10.1016/j.jaad.2007.04.012 2Piraccini BM, Blume-Peytavi U, Scarci F, et al. Efficacy and safety of topical finasteride spray solution for male androgenetic alopecia: a phase III, randomized, controlled clinical trial. J Eur Acad Dermatol Venereol. 2022;36(2):286-294. doi:10.1111/jdv.17738 3Penha MA, Miot HA, Kasprzak M, Ramos PM. Oral minoxidil vs topical minoxidil for male androgenetic alopecia: a randomized clinical trial. JAMA Dermatol. 2024;160(6):600-605. doi:10.1001/jamadermatol.2024.0284 4Fonseca LPC, Miot HA, Chaves CRP, Ramos PM. Oral minoxidil 2.5 mg vs 5 mg for male androgenetic alopecia: a double-blind randomized clinical trial. J Am Acad Dermatol. 2025;94(1):316-318. Oral Finasteride 1mg2 IR Oral Minoxidil 5mg (JAMA Derm) 3 IR Oral Minoxidil 5mg (JAAD) 4 Additional Male PHL Studies TAHC Increase; from baseline at Month 6 VDPHL01 in Males TAHC Increase; from baseline at Month 6 ∆=16.2 ∆=14.4 Rogaine 5% Foam1 (Month 4) N/A N/An=97n=172 n=50n=33n=175 n=48 6.6 7.3 28.6 30.3 36.4 33.0 0 5 10 15 20 25 30 35 40 Study '304' Part A Study '302' Part A N on -V el lu s T AH C In cr ea se Placebo VDPHL01 8.5 mg QD VDPHL01 8.5mg BID [p<.0001] [p<.0001] ∆=25.8 ∆=23.1 ∆=22.0 ∆=29.9 [p<.0001] n=175 [p<.0001] n=178 n=177n=181 n=173 n=171 Data on File. Veradermics, Inc.OCTOBER 2026
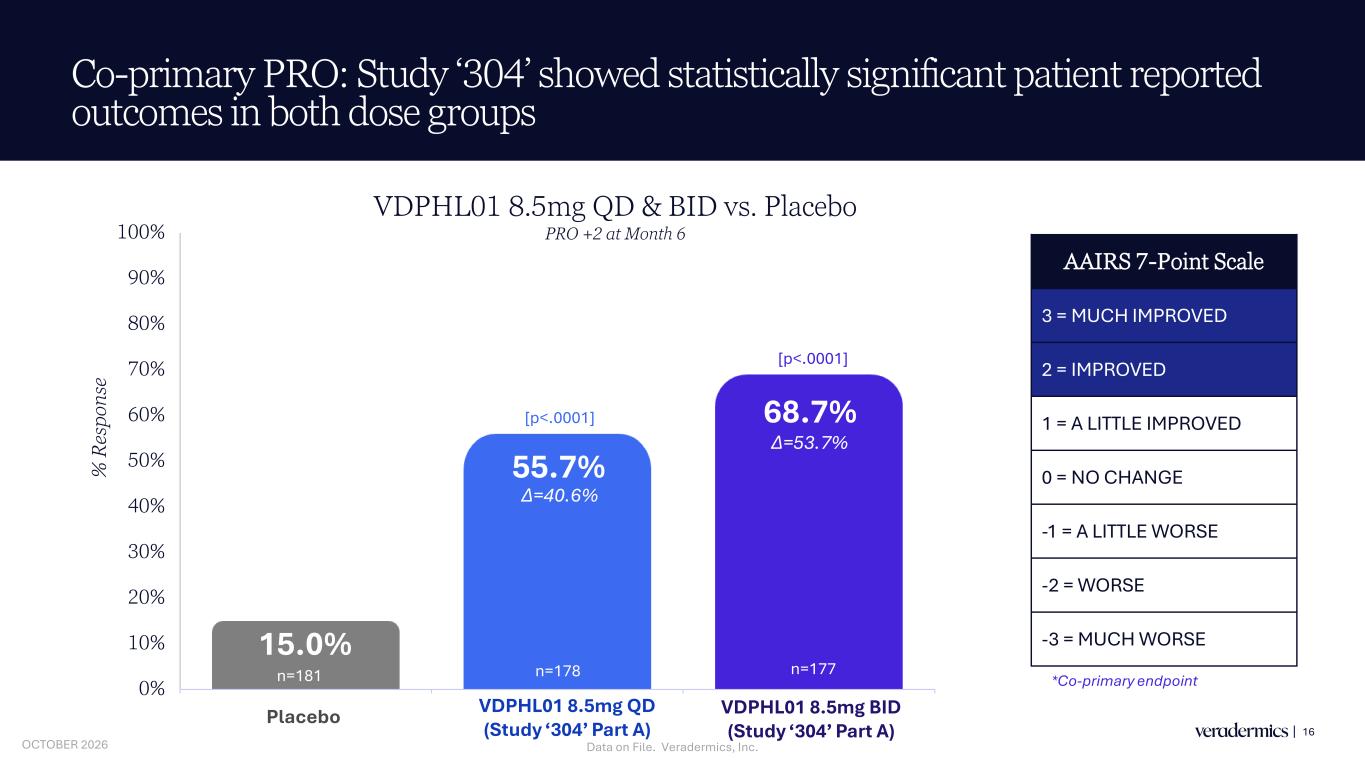
Co-primary PRO: Study ‘304’ showed statistically significant patient reported outcomes in both dose groups 16 15.0% 55.7% 68.7% 0% 10% 20% 30% 40% 50% 60% 70% 80% 90% 100% Placebo VDPHL01 8.5mg QD VDPHL01 8.5mg BID % R es po ns e AAIRS 7-Point Scale 3 = MUCH IMPROVED 2 = IMPROVED 1 = A LITTLE IMPROVED 0 = NO CHANGE -1 = A LITTLE WORSE -2 = WORSE -3 = MUCH WORSE ∆=53.7% ∆=40.6% [p<.0001] [p<.0001] *Co-primary endpointn=181 Placebo VDPHL01 8.5mg QD & BID vs. Placebo PRO +2 at Month 6 n=178 n=177 VDPH 1 8.5mg QD (Study ‘304’ Part A) VDPHL01 8.5mg BID (Study ‘304’ Part A) Data on File. Veradermics, Inc.OCTOBER 2026
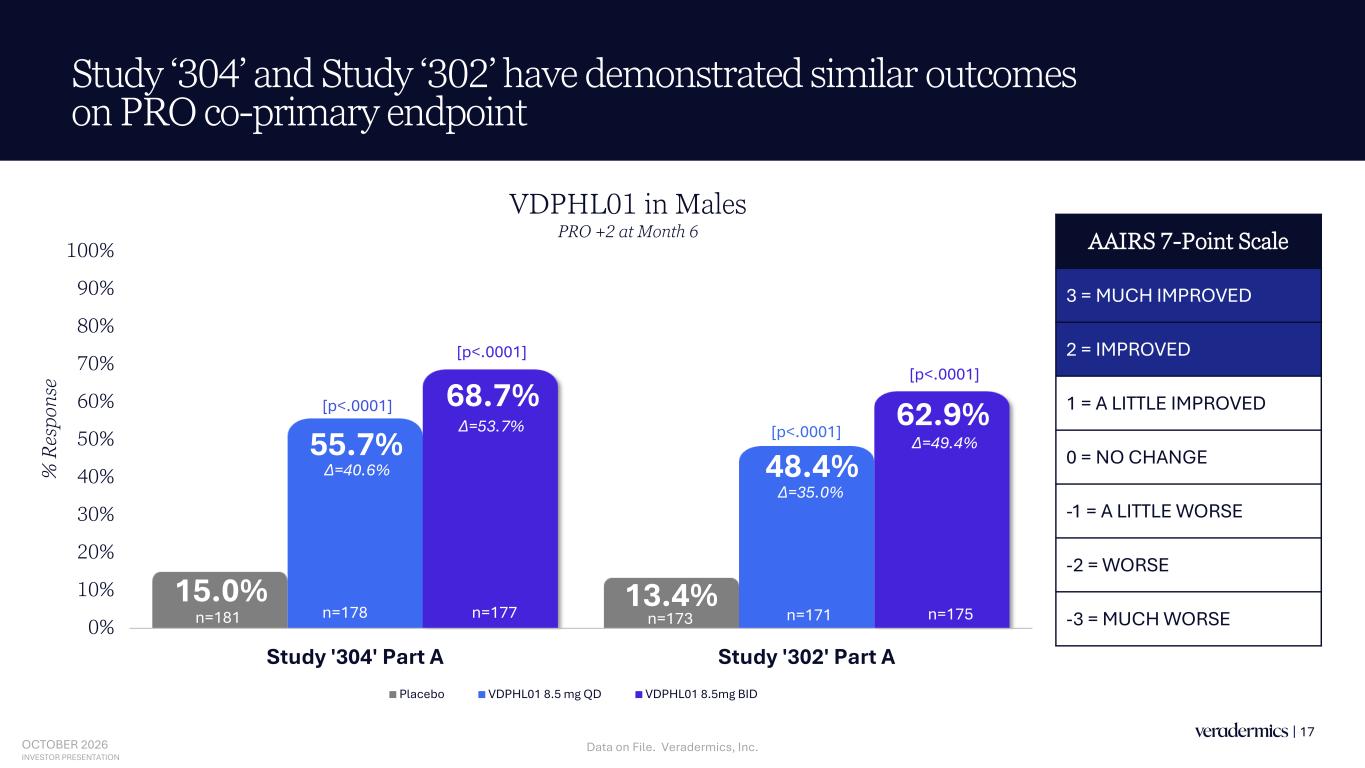
15.0% 13.4% 55.7% 48.4% 68.7% 62.9% 0% 10% 20% 30% 40% 50% 60% 70% 80% 90% 100% Study '304' Part A Study '302' Part A % R es po ns e Placebo VDPHL01 8.5 mg QD VDPHL01 8.5mg BID Study ‘304’ and Study ‘302’ have demonstrated similar outcomes on PRO co-primary endpoint 17 VDPHL01 in Males PRO +2 at Month 6 [p<.0001] [p<.0001] [p<.0001] [p<.0001] n=178 n=177n=181 n=173 n=175n=171 ∆=40.6% ∆=35.0% ∆=49.4% ∆=53.7% AAIRS 7-Point Scale 3 = MUCH IMPROVED 2 = IMPROVED 1 = A LITTLE IMPROVED 0 = NO CHANGE -1 = A LITTLE WORSE -2 = WORSE -3 = MUCH WORSE OCTOBER 2026 INVESTOR PRESENTATION Data on File. Veradermics, Inc.
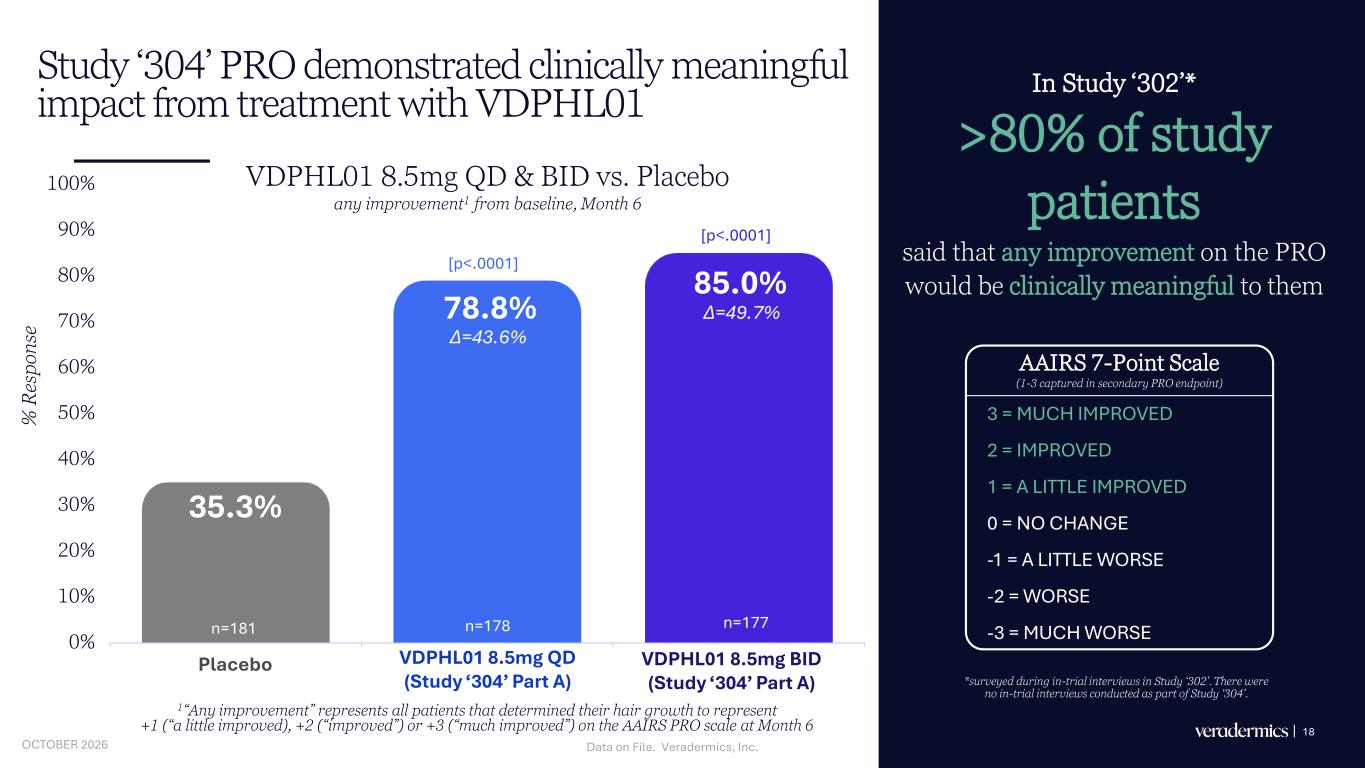
Study ‘304’ PRO demonstrated clinically meaningful impact from treatment with VDPHL01 In Study ‘302’* >80% of study patients said that any improvement on the PRO would be clinically meaningful to them 18 35.3% 78.8% 85.0% 0% 10% 20% 30% 40% 50% 60% 70% 80% 90% 100% Placebo VDPHL01 8.5mg QD VDPHL01 8.5mg BID % R es po ns e 1“Any improvement” represents all patients that determined their hair growth to represent +1 (“a little improved), +2 (“improved”) or +3 (“much improved”) on the AAIRS PRO scale at Month 6 AAIRS 7-Point Scale (1-3 captured in secondary PRO endpoint) 3 = MUCH IMPROVED 2 = IMPROVED 1 = A LITTLE IMPROVED 0 = NO CHANGE -1 = A LITTLE WORSE -2 = WORSE -3 = MUCH WORSE ∆=43.6% [p<.0001] *surveyed during in-trial interviews in Study ‘302’. There were no in-trial interviews conducted as part of Study ‘304’. [p<.0001] n=181 n=178 n=177 VDPHL01 8.5mg QD & BID vs. Placebo any improvement1 from baseline, Month 6 Placebo VDPHL01 .5mg QD (Study ‘304’ Part A) VDPHL01 8. g BID (Study ‘304’ Part A) ∆=49.7% Data on File. Veradermics, Inc.OCTOBER 2026
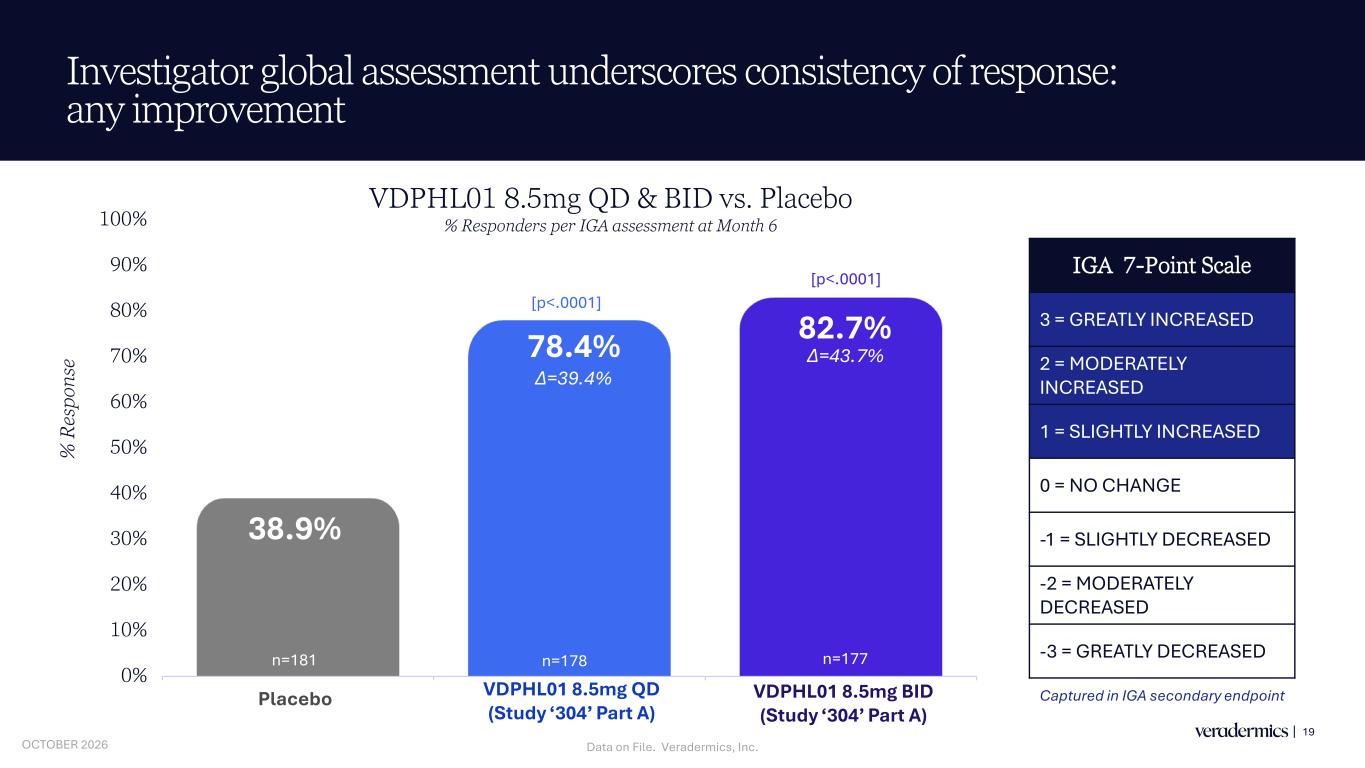
Investigator global assessment underscores consistency of response: any improvement 19 38.9% 78.4% 82.7% 0% 10% 20% 30% 40% 50% 60% 70% 80% 90% 100% Placebo VDPHL01 8.5mg QD VDPHL01 8.5mg BID % R es po ns e ∆=43.7% ∆=39.4% [p<.0001] [p<.0001] IGA 7-Point Scale 3 = GREATLY INCREASED 2 = MODERATELY INCREASED 1 = SLIGHTLY INCREASED 0 = NO CHANGE -1 = SLIGHTLY DECREASED -2 = MODERATELY DECREASED -3 = GREATLY DECREASED Captured in IGA secondary endpoint VDPHL01 8.5mg QD & BID vs. Placebo % Responders per IGA assessment at Month 6 Placebo VDPHL0 .5mg QD (Study ‘304’ Part A) VDPHL0 .5mg BID (Study ‘304’ Part A) n=181 n=178 n=177 Data on File. Veradermics, Inc.OCTOBER 2026
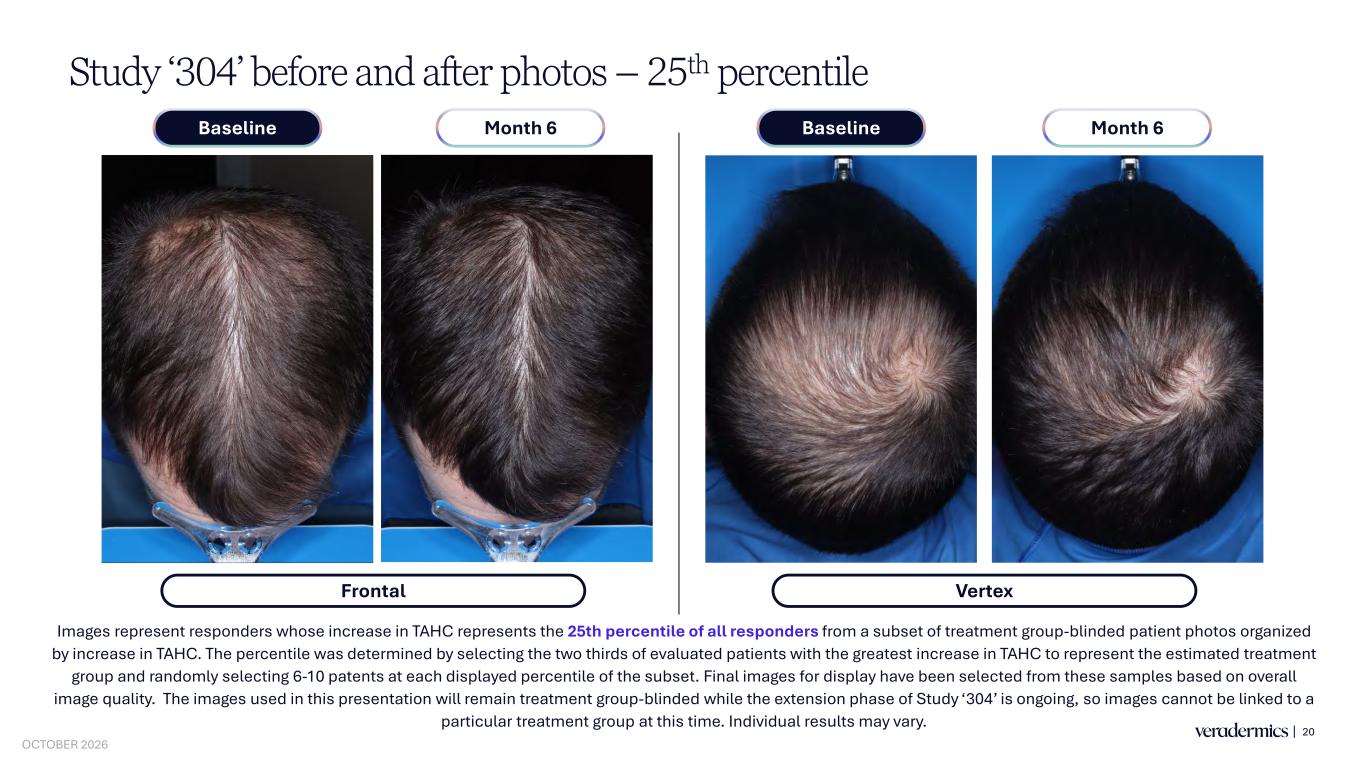
Study ‘304’ before and after photos – 25th percentile 20 Images represent responders whose increase in TAHC represents the 25th percentile of all responders from a subset of treatment group-blinded patient photos organized by increase in TAHC. The percentile was determined by selecting the two thirds of evaluated patients with the greatest increase in TAHC to represent the estimated treatment group and randomly selecting 6-10 patents at each displayed percentile of the subset. Final images for display have been selected from these samples based on overall image quality. The images used in this presentation will remain treatment group-blinded while the extension phase of Study ‘304’ is ongoing, so images cannot be linked to a particular treatment group at this time. Individual results may vary. Frontal Month 6Baseline Month 6Baseline Vertex OCTOBER 2026
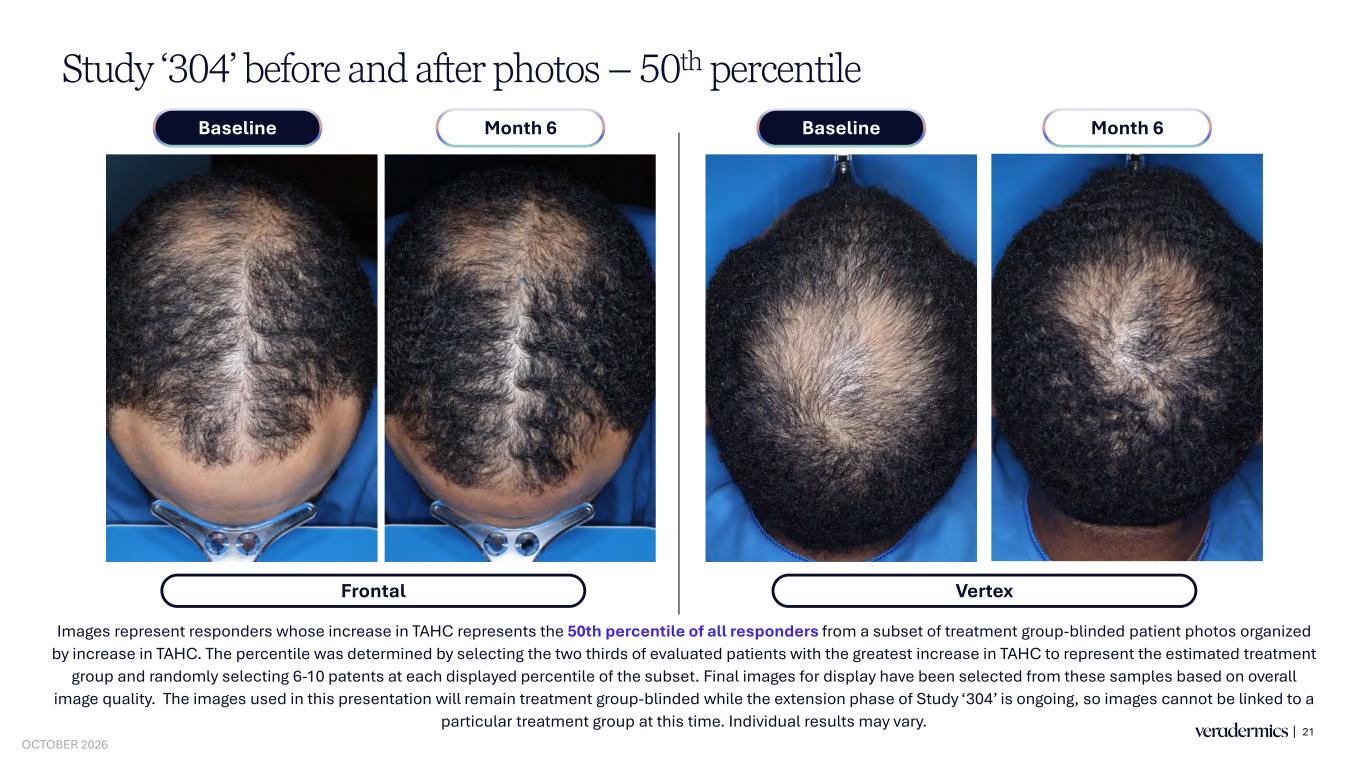
Study ‘304’ before and after photos – 50th percentile 21 Images represent responders whose increase in TAHC represents the 50th percentile of all responders from a subset of treatment group-blinded patient photos organized by increase in TAHC. The percentile was determined by selecting the two thirds of evaluated patients with the greatest increase in TAHC to represent the estimated treatment group and randomly selecting 6-10 patents at each displayed percentile of the subset. Final images for display have been selected from these samples based on overall image quality. The images used in this presentation will remain treatment group-blinded while the extension phase of Study ‘304’ is ongoing, so images cannot be linked to a particular treatment group at this time. Individual results may vary. Frontal Month 6Baseline Month 6Baseline Vertex OCTOBER 2026
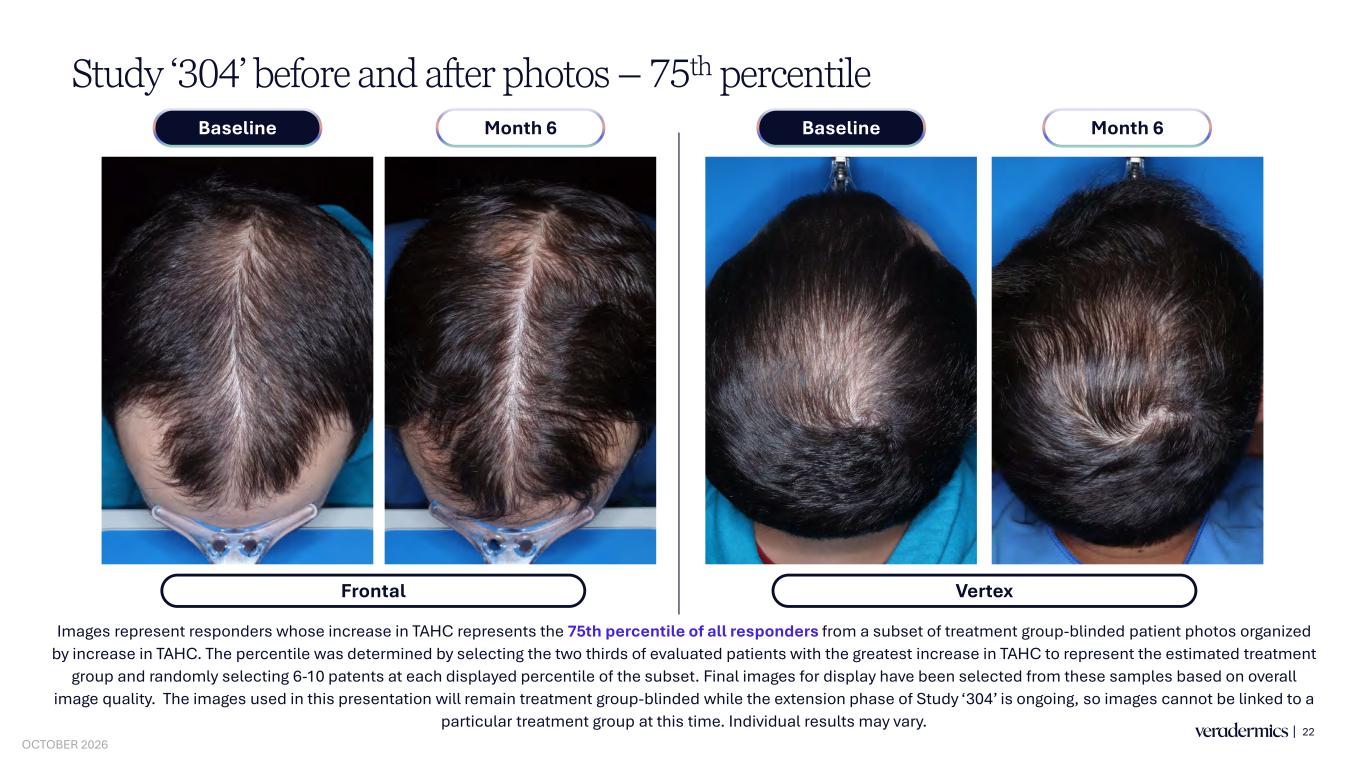
Study ‘304’ before and after photos – 75th percentile 22 Images represent responders whose increase in TAHC represents the 75th percentile of all responders from a subset of treatment group-blinded patient photos organized by increase in TAHC. The percentile was determined by selecting the two thirds of evaluated patients with the greatest increase in TAHC to represent the estimated treatment group and randomly selecting 6-10 patents at each displayed percentile of the subset. Final images for display have been selected from these samples based on overall image quality. The images used in this presentation will remain treatment group-blinded while the extension phase of Study ‘304’ is ongoing, so images cannot be linked to a particular treatment group at this time. Individual results may vary. Frontal Month 6Baseline Month 6Baseline Vertex OCTOBER 2026

Independent Frontal Photographic Review (IPR-IFA) 23 OCTOBER 2026
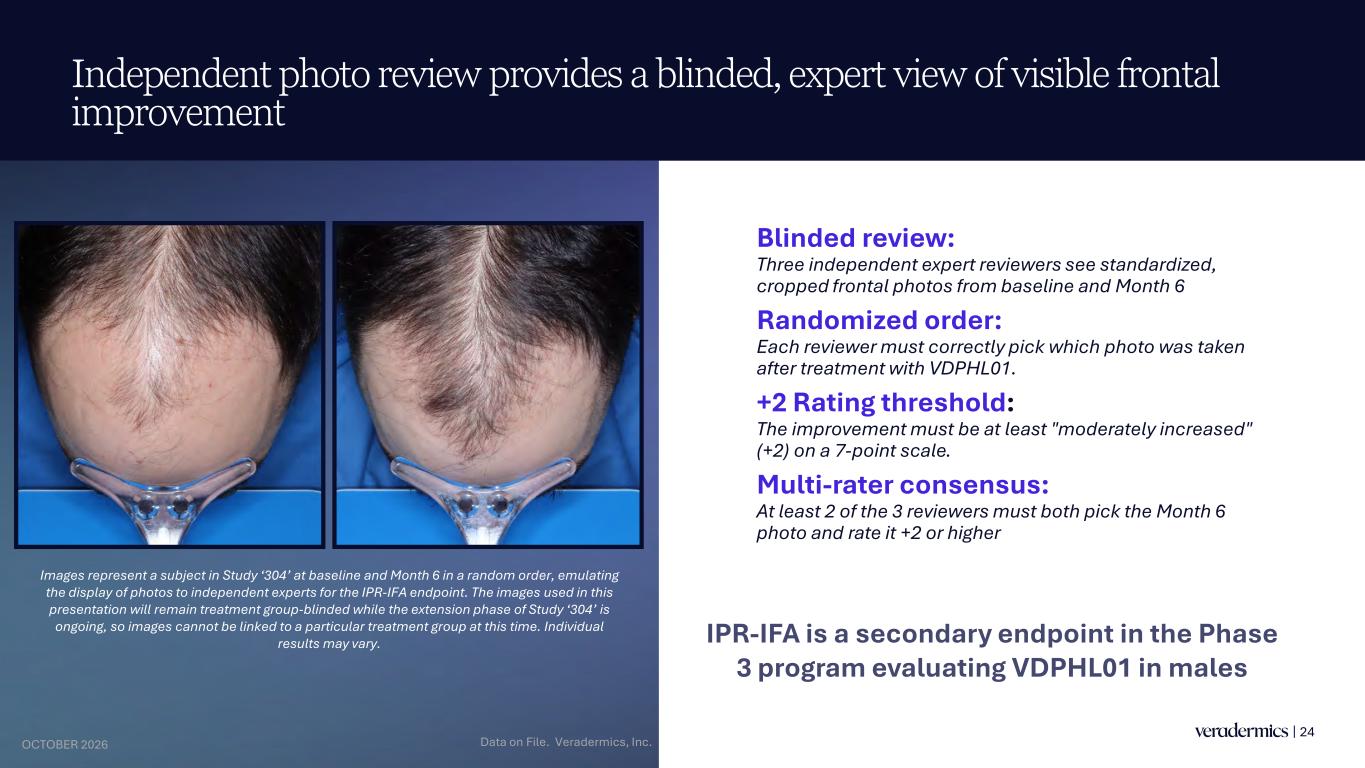
Independent photo review provides a blinded, expert view of visible frontal improvement 24 Images represent a subject in Study ‘304’ at baseline and Month 6 in a random order, emulating the display of photos to independent experts for the IPR-IFA endpoint. The images used in this presentation will remain treatment group-blinded while the extension phase of Study ‘304’ is ongoing, so images cannot be linked to a particular treatment group at this time. Individual results may vary. Blinded review: Three independent expert reviewers see standardized, cropped frontal photos from baseline and Month 6 Randomized order: Each reviewer must correctly pick which photo was taken after treatment with VDPHL01. +2 Rating threshold: The improvement must be at least "moderately increased" (+2) on a 7-point scale. Multi-rater consensus: At least 2 of the 3 reviewers must both pick the Month 6 photo and rate it +2 or higher IPR-IFA is a secondary endpoint in the Phase 3 program evaluating VDPHL01 in males Data on File. Veradermics, Inc.OCTOBER 2026
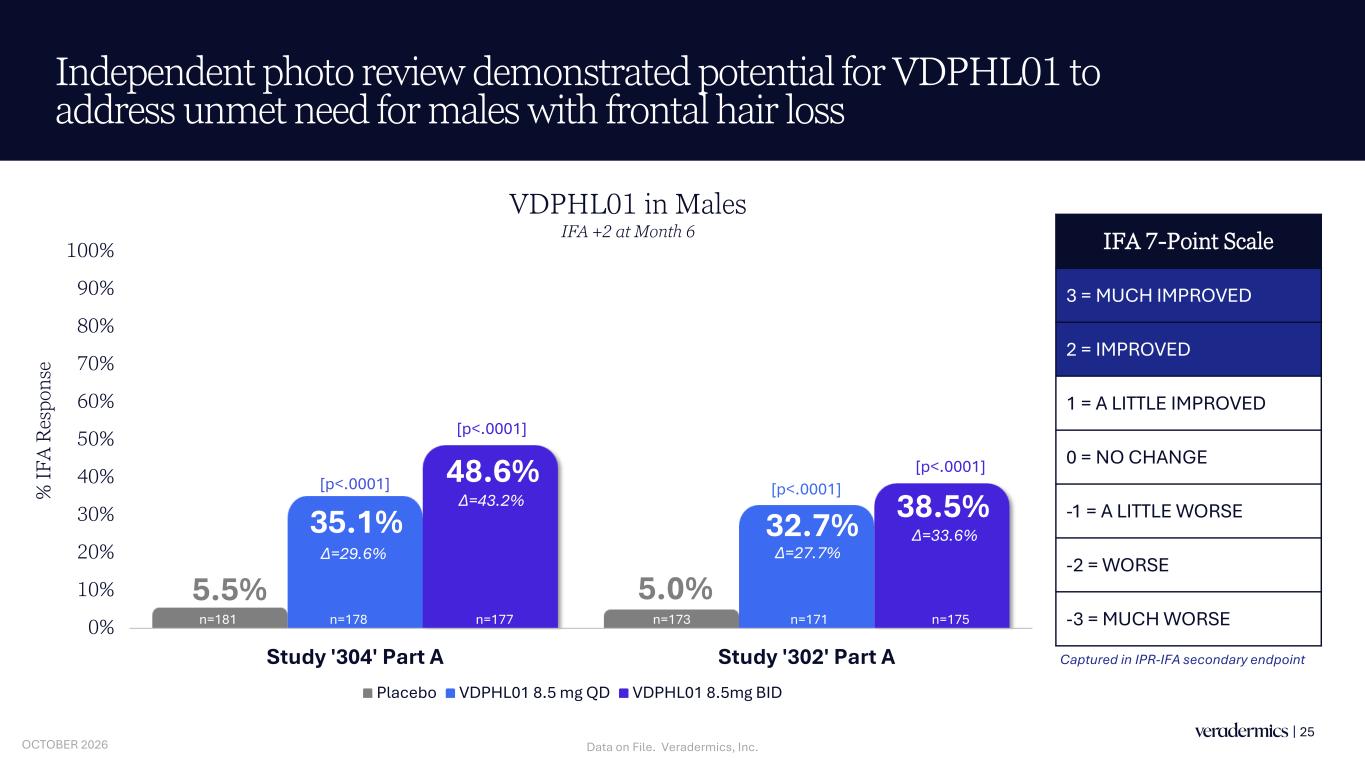
5.5% 5.0% 35.1% 32.7% 48.6% 38.5% 0% 10% 20% 30% 40% 50% 60% 70% 80% 90% 100% Study '304' Part A Study '302' Part A % IF A R es po ns e Placebo VDPHL01 8.5 mg QD VDPHL01 8.5mg BID Independent photo review demonstrated potential for VDPHL01 to address unmet need for males with frontal hair loss 25 VDPHL01 in Males IFA +2 at Month 6 [p<.0001] [p<.0001] [p<.0001] [p<.0001] n=178 n=177n=181 n=173 n=175n=171 ∆=43.2% ∆=27.7% ∆=33.6% ∆=29.6% IFA 7-Point Scale 3 = MUCH IMPROVED 2 = IMPROVED 1 = A LITTLE IMPROVED 0 = NO CHANGE -1 = A LITTLE WORSE -2 = WORSE -3 = MUCH WORSE Captured in IPR-IFA secondary endpoint Data on File. Veradermics, Inc.OCTOBER 2026

Study ‘304’ Safety and Tolerability Overview 26 OCTOBER 2026

Study ‘304’ demonstrated that VDPHL01 was generally well-tolerated, similar to Study ‘302’ results • No treatment-related SAEs • No adverse events of special interest (AESI) of cardiac origin • Overall TEAE rates in active treatment arms were similar to Study ‘302’; generally tolerable and occurred at low to mid single digit rates • No clinically significant differences in heart rate, blood pressure, or ECG changes compared to placebo • Lack of observed shedding 27 OCTOBER 2026
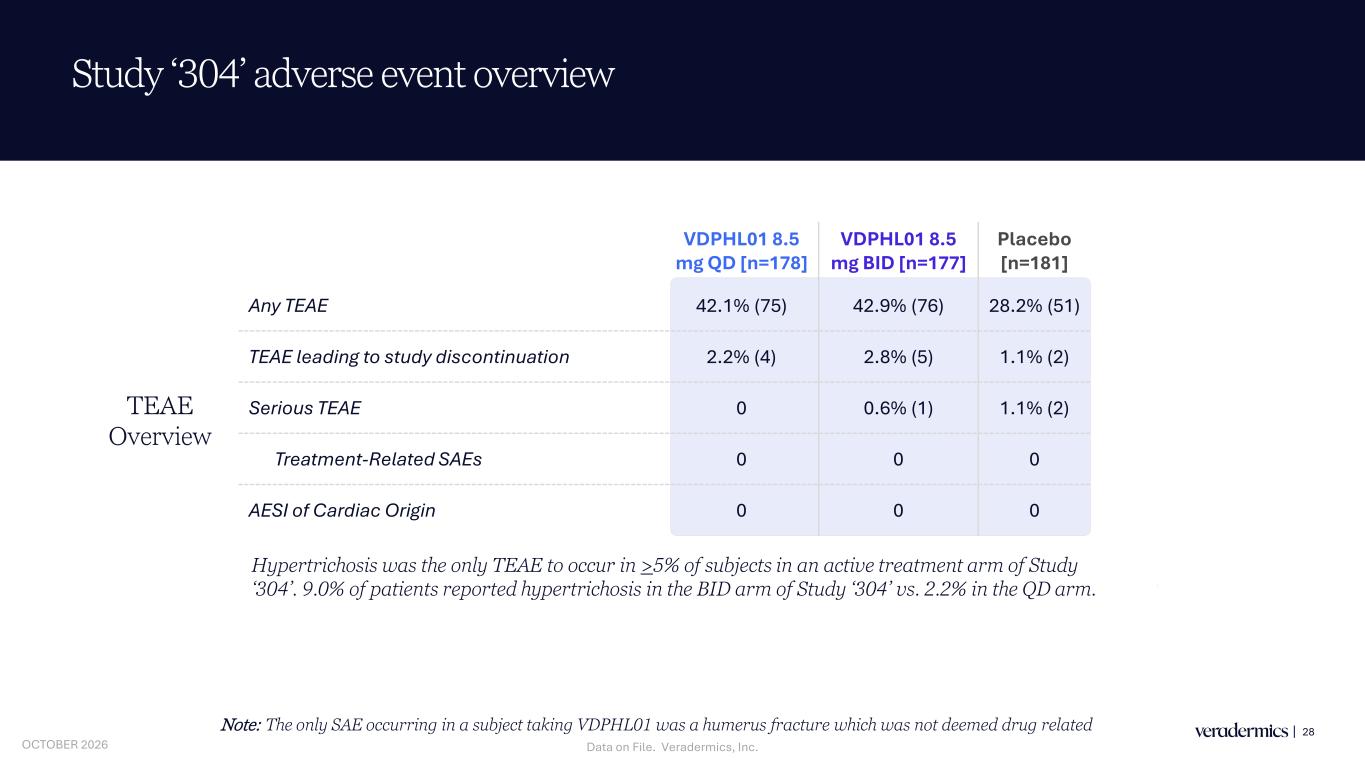
VDPHL01 8.5 mg QD [n=178] VDPHL01 8.5 mg BID [n=177] Placebo [n=181] Any TEAE 42.1% (75) 42.9% (76) 28.2% (51) TEAE leading to study discontinuation 2.2% (4) 2.8% (5) 1.1% (2) Serious TEAE 0 0.6% (1) 1.1% (2) Treatment-Related SAEs 0 0 0 AESI of Cardiac Origin 0 0 0 TEAE Overview Study ‘304’ adverse event overview 28Note: The only SAE occurring in a subject taking VDPHL01 was a humerus fracture which was not deemed drug related Hypertrichosis was the only TEAE to occur in >5% of subjects in an active treatment arm of Study ‘304’. 9.0% of patients reported hypertrichosis in the BID arm of Study ‘304’ vs. 2.2% in the QD arm. Data on File. Veradermics, Inc.OCTOBER 2026
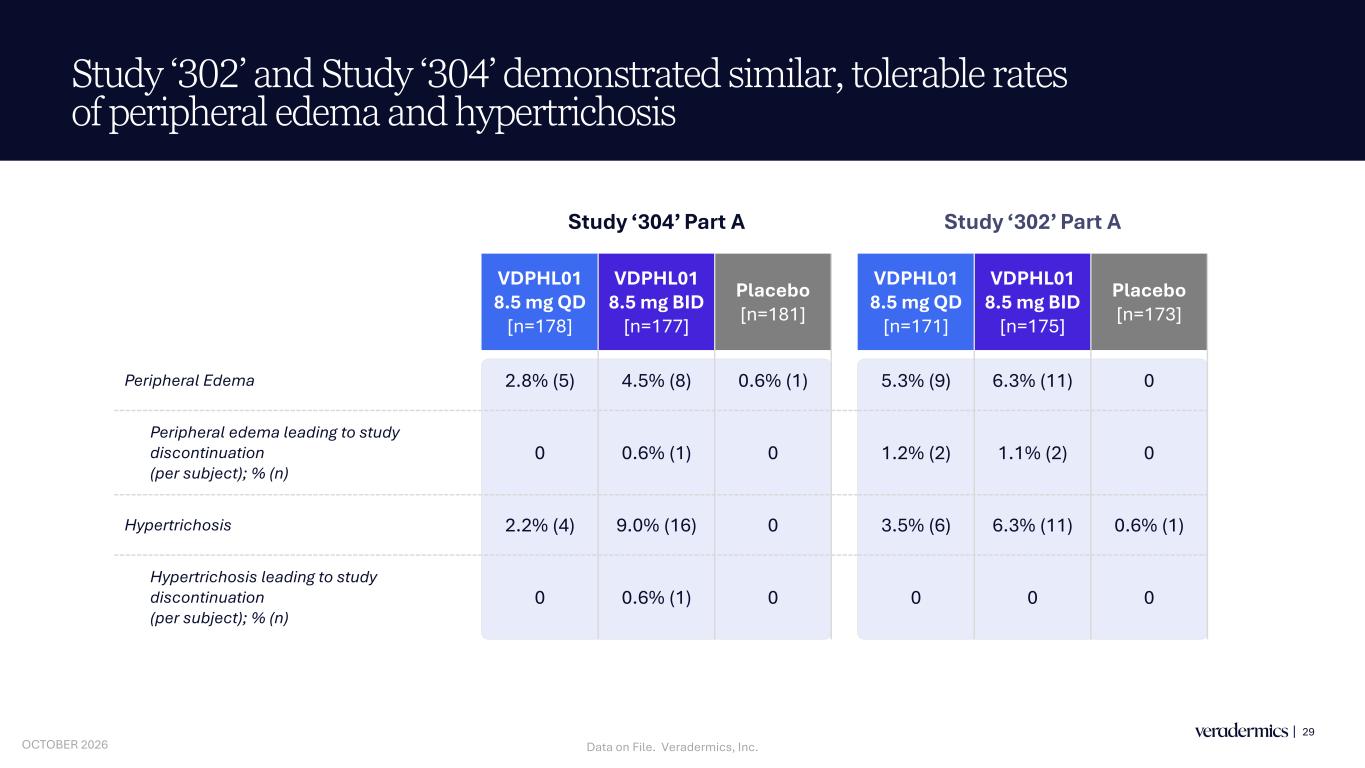
Study ‘302’ Part A VDPHL01 8.5 mg QD [n=171] VDPHL01 8.5 mg BID [n=175] Placebo [n=173] 5.3% (9) 6.3% (11) 0 1.2% (2) 1.1% (2) 0 3.5% (6) 6.3% (11) 0.6% (1) 0 0 0 Study ‘304’ Part A VDPHL01 8.5 mg QD [n=178] VDPHL01 8.5 mg BID [n=177] Placebo [n=181] Peripheral Edema 2.8% (5) 4.5% (8) 0.6% (1) Peripheral edema leading to study discontinuation (per subject); % (n) 0 0.6% (1) 0 Hypertrichosis 2.2% (4) 9.0% (16) 0 Hypertrichosis leading to study discontinuation (per subject); % (n) 0 0.6% (1) 0 Study ‘302’ and Study ‘304’ demonstrated similar, tolerable rates of peripheral edema and hypertrichosis 29 Data on File. Veradermics, Inc.OCTOBER 2026

VDPHL01 clinical profile demonstrated in Study ‘304’ supports a potential new standard of care for pattern hair loss 30 Fast Consistent Intense Generally Well-Tolerated Convenient Oral Administration 78.8% - 85% of subjects reported improvement in hair coverage at Month 6; 55.7% - 68.7% of subjects reported ‘improved’ or ‘much improved’ at Month 6 (QD/BID) Average non-vellus hair count change of 28.6 - 36.4 hairs/cm2 (QD/BID) at Month 6 No treatment-related SAEs; no AESIs of cardiac origin; AE-related discontinuation rates favorable vs. existing oral PHL therapies Favorable vs. topical alternatives1 Superiority vs. placebo on TAHC and IGA from Month 2 onwards 1Supported by third-party research ✓ ✓ ✓ ✓ ✓ Data on File. Veradermics, Inc.OCTOBER 2026

KOL Discussion Michael Payette, M.D., M.B.A. Co-Founder, Central Connecticut Dermatology 31 OCTOBER 2026

Study '304' Clinical Trial Topline: Results from Market Opinion Study October 2026 Presented by: Mark Neumann, Chief Commercial and Strategy Officer OCTOBER 2026

33 Objective: understand whether the VDPHL01 Phase 3 male PHL profile will substantially grow the prescription market by expanding and deepening the prescriber base. OCTOBER 2026
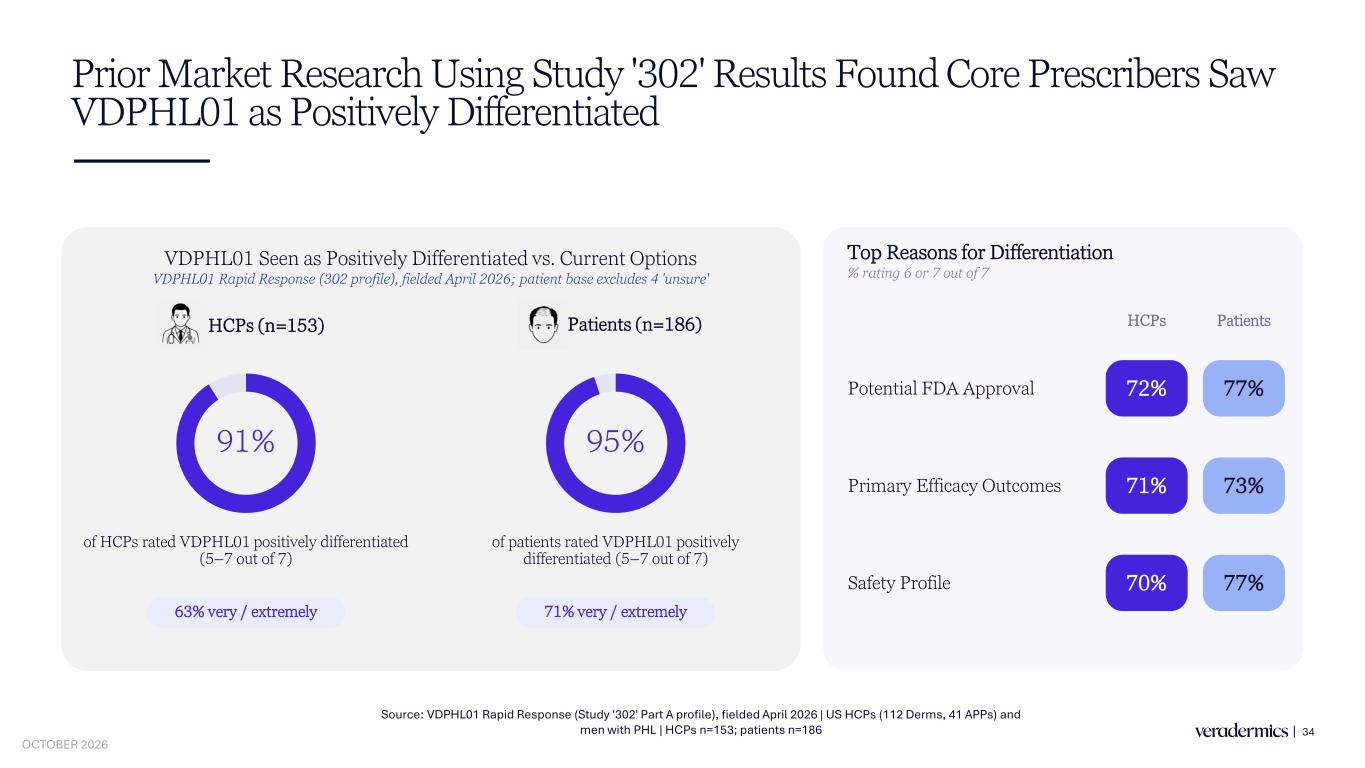
Prior Market Research Using Study '302' Results Found Core Prescribers Saw VDPHL01 as Positively Differentiated 34 Source: VDPHL01 Rapid Response (Study '302' Part A profile), fielded April 2026 | US HCPs (112 Derms, 41 APPs) and men with PHL | HCPs n=153; patients n=186 VDPHL01 Seen as Positively Differentiated vs. Current Options VDPHL01 Rapid Response (302 profile), fielded April 2026; patient base excludes 4 'unsure' 91% of HCPs rated VDPHL01 positively differentiated (5–7 out of 7) 95% of patients rated VDPHL01 positively differentiated (5–7 out of 7) 63% very / extremely 71% very / extremely Patients (n=186) Top Reasons for Differentiation % rating 6 or 7 out of 7 HCPs Patients Potential FDA Approval 72% 77% Primary Efficacy Outcomes 71% 73% Safety Profile 70% 77% HCPs (n=153) OCTOBER 2026
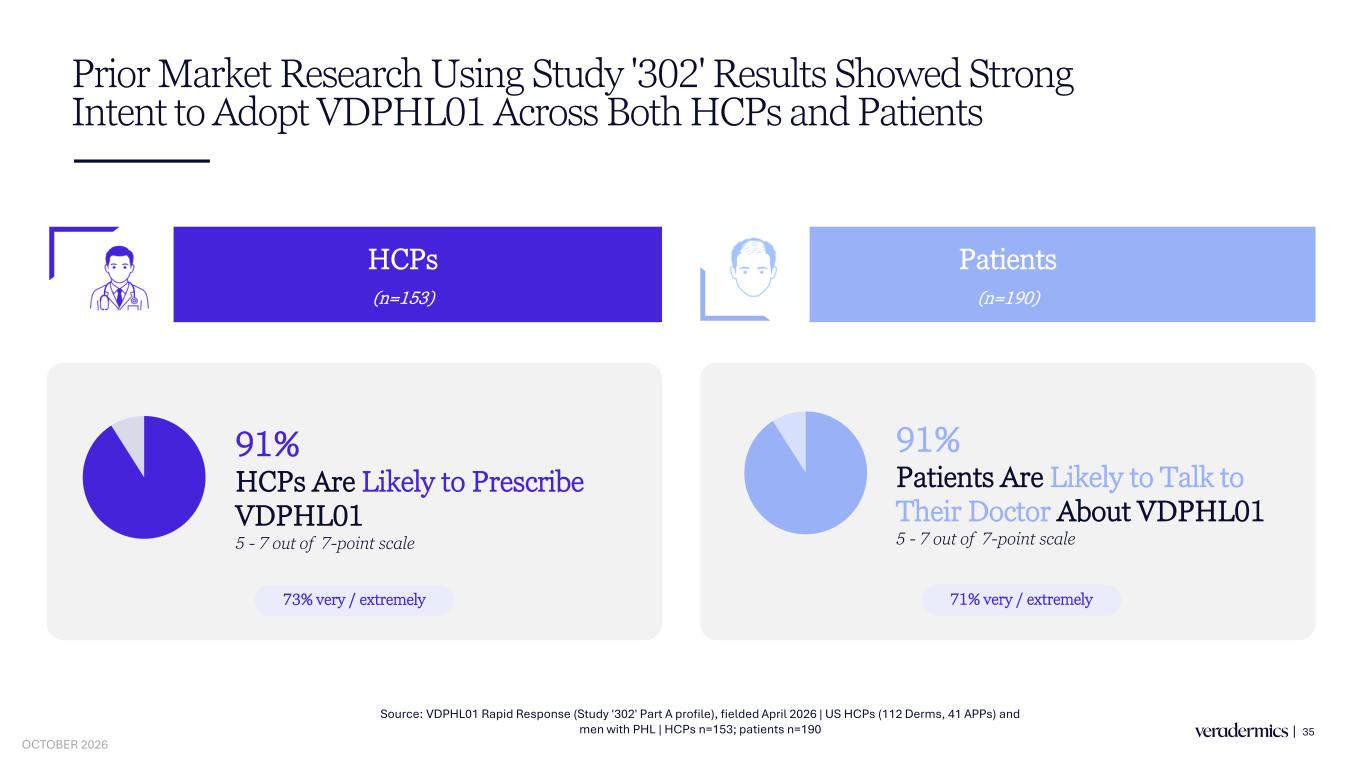
Prior Market Research Using Study '302' Results Showed Strong Intent to Adopt VDPHL01 Across Both HCPs and Patients 35 HCPs (n=153) Patients (n=190) 91% Patients Are Likely to Talk to Their Doctor About VDPHL01 5 - 7 out of 7-point scale 91% HCPs Are Likely to Prescribe VDPHL01 5 - 7 out of 7-point scale Source: VDPHL01 Rapid Response (Study '302' Part A profile), fielded April 2026 | US HCPs (112 Derms, 41 APPs) and men with PHL | HCPs n=153; patients n=190 73% very / extremely 71% very / extremely OCTOBER 2026
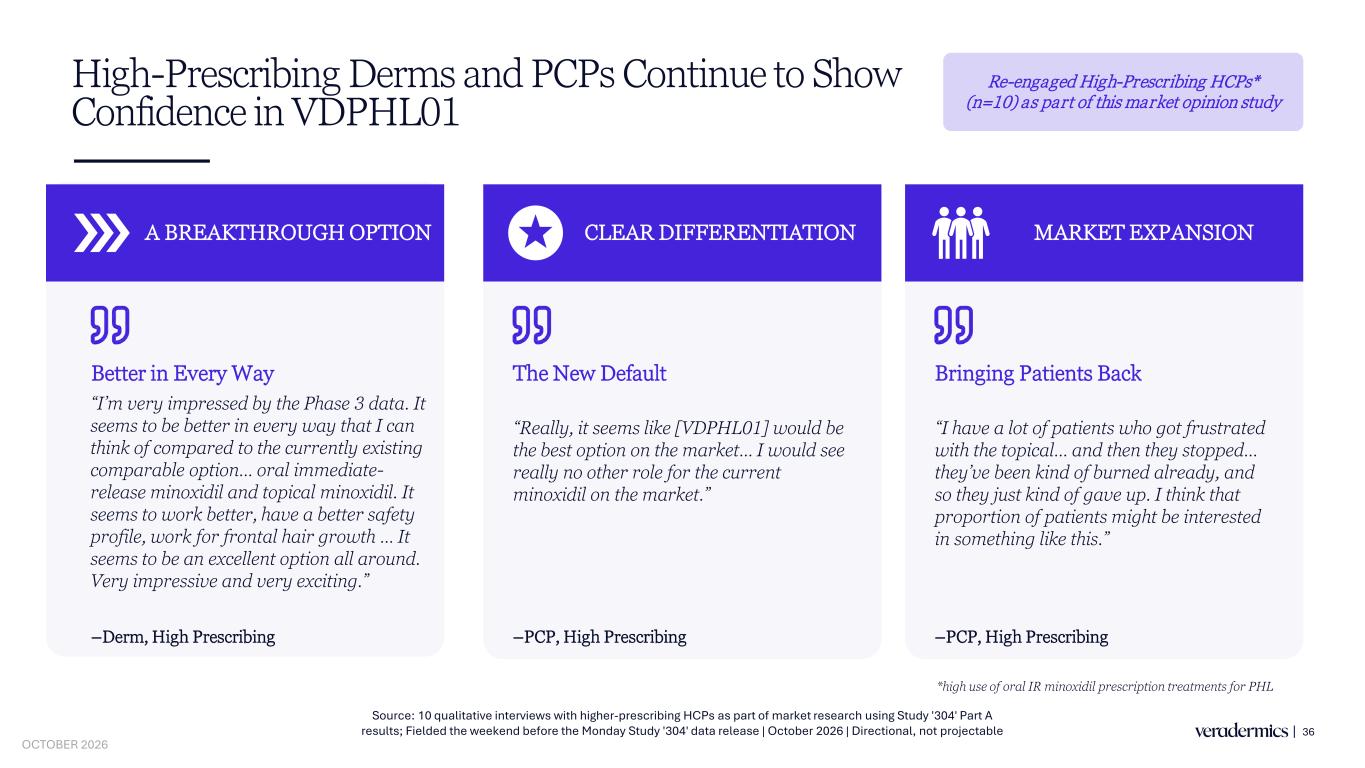
High-Prescribing Derms and PCPs Continue to Show Confidence in VDPHL01 36 A BREAKTHROUGH OPTION –Derm, High Prescribing CLEAR DIFFERENTIATION –PCP, High Prescribing MARKET EXPANSION –PCP, High Prescribing Source: 10 qualitative interviews with higher-prescribing HCPs as part of market research using Study '304' Part A results; Fielded the weekend before the Monday Study '304' data release | October 2026 | Directional, not projectable “I’m very impressed by the Phase 3 data. It seems to be better in every way that I can think of compared to the currently existing comparable option… oral immediate- release minoxidil and topical minoxidil. It seems to work better, have a better safety profile, work for frontal hair growth … It seems to be an excellent option all around. Very impressive and very exciting.” “Really, it seems like [VDPHL01] would be the best option on the market… I would see really no other role for the current minoxidil on the market.” “I have a lot of patients who got frustrated with the topical… and then they stopped… they’ve been kind of burned already, and so they just kind of gave up. I think that proportion of patients might be interested in something like this.” Better in Every Way The New Default Bringing Patients Back Re-engaged High-Prescribing HCPs* (n=10) as part of this market opinion study *high use of oral IR minoxidil prescription treatments for PHL OCTOBER 2026
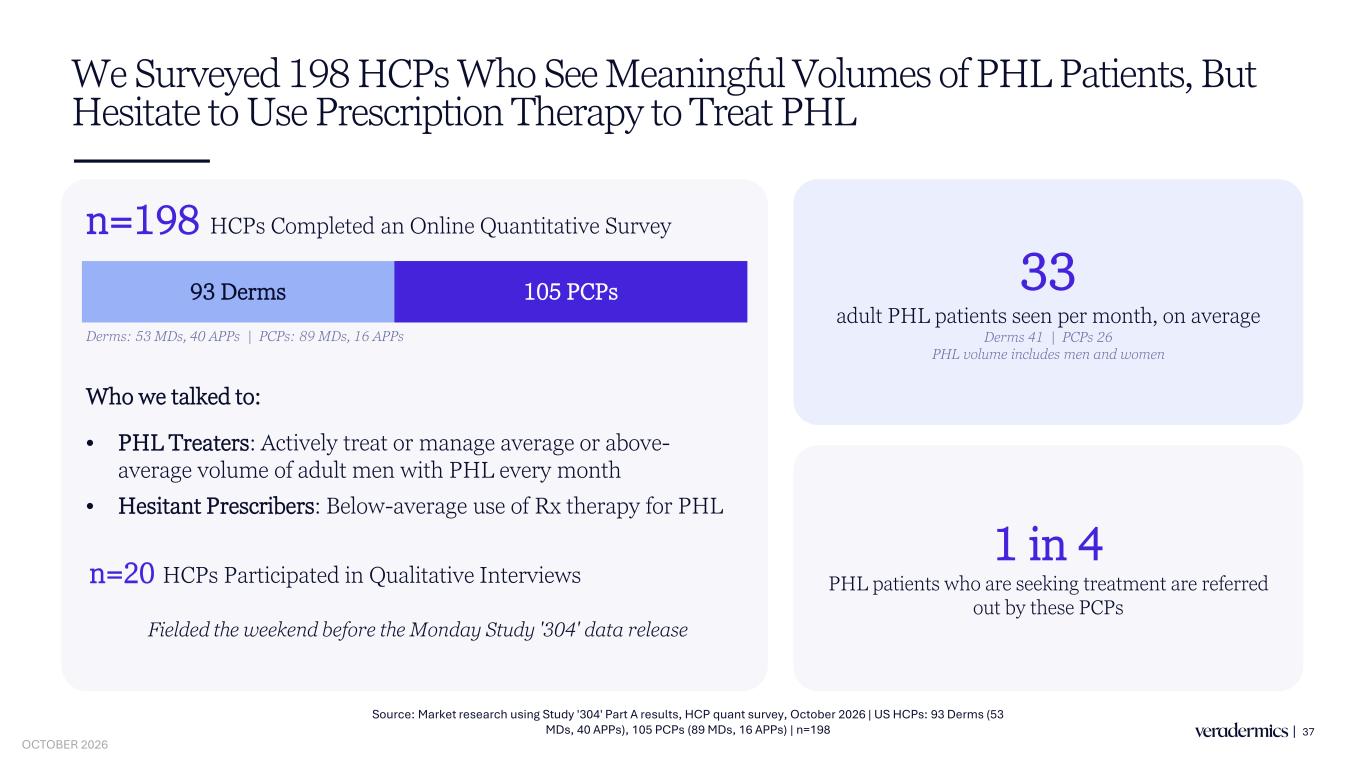
We Surveyed 198 HCPs Who See Meaningful Volumes of PHL Patients, But Hesitate to Use Prescription Therapy to Treat PHL 37 n=198 HCPs Completed an Online Quantitative Survey 93 Derms 105 PCPs Derms: 53 MDs, 40 APPs | PCPs: 89 MDs, 16 APPs Who we talked to: • PHL Treaters: Actively treat or manage average or above- average volume of adult men with PHL every month • Hesitant Prescribers: Below-average use of Rx therapy for PHL 33 adult PHL patients seen per month, on average Derms 41 | PCPs 26 PHL volume includes men and women 1 in 4 PHL patients who are seeking treatment are referred out by these PCPs n=20 HCPs Participated in Qualitative Interviews Fielded the weekend before the Monday Study '304' data release Source: Market research using Study '304' Part A results, HCP quant survey, October 2026 | US HCPs: 93 Derms (53 MDs, 40 APPs), 105 PCPs (89 MDs, 16 APPs) | n=198 OCTOBER 2026
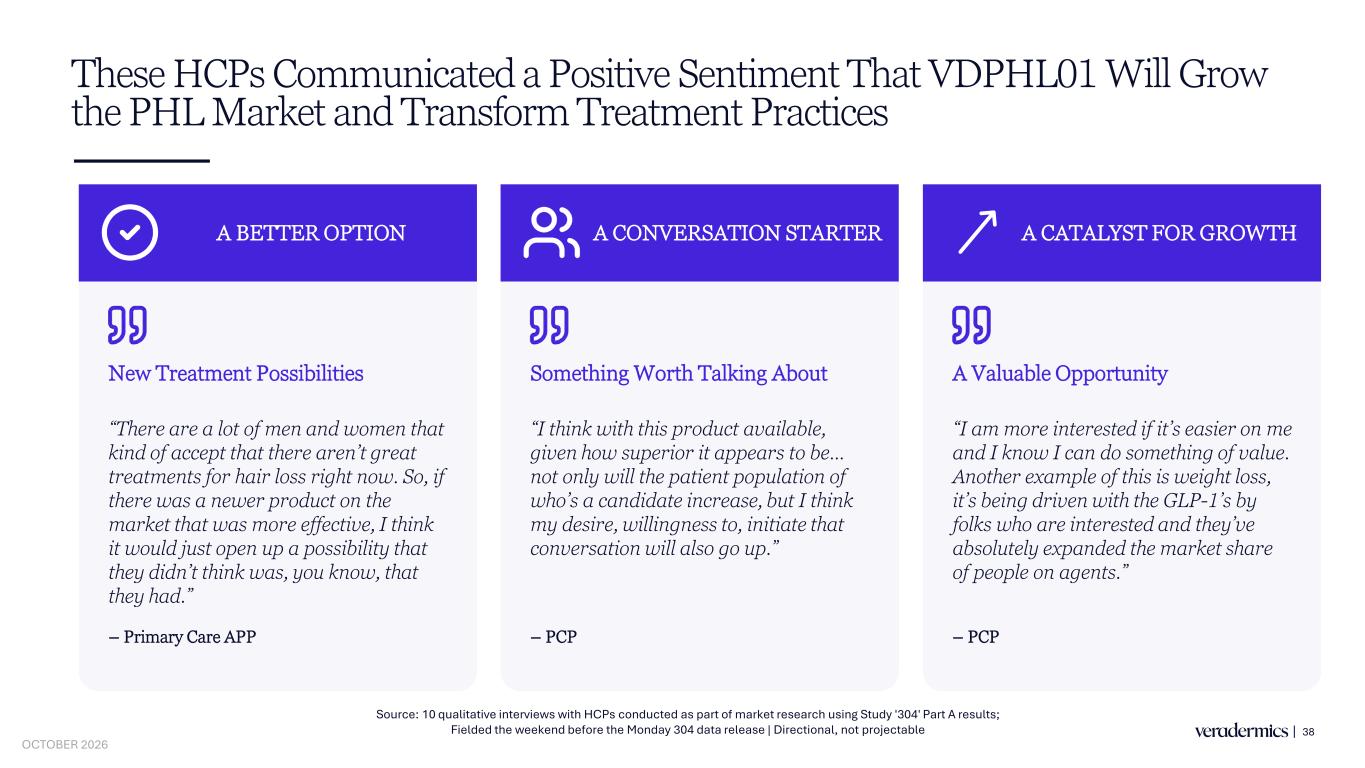
These HCPs Communicated a Positive Sentiment That VDPHL01 Will Grow the PHL Market and Transform Treatment Practices 38 Source: 10 qualitative interviews with HCPs conducted as part of market research using Study '304' Part A results; Fielded the weekend before the Monday 304 data release | Directional, not projectable A BETTER OPTION New Treatment Possibilities “There are a lot of men and women that kind of accept that there aren’t great treatments for hair loss right now. So, if there was a newer product on the market that was more effective, I think it would just open up a possibility that they didn’t think was, you know, that they had.” – Primary Care APP A CONVERSATION STARTER Something Worth Talking About “I think with this product available, given how superior it appears to be… not only will the patient population of who’s a candidate increase, but I think my desire, willingness to, initiate that conversation will also go up.” – PCP A CATALYST FOR GROWTH A Valuable Opportunity “I am more interested if it’s easier on me and I know I can do something of value. Another example of this is weight loss, it’s being driven with the GLP-1’s by folks who are interested and they’ve absolutely expanded the market share of people on agents.” – PCP OCTOBER 2026
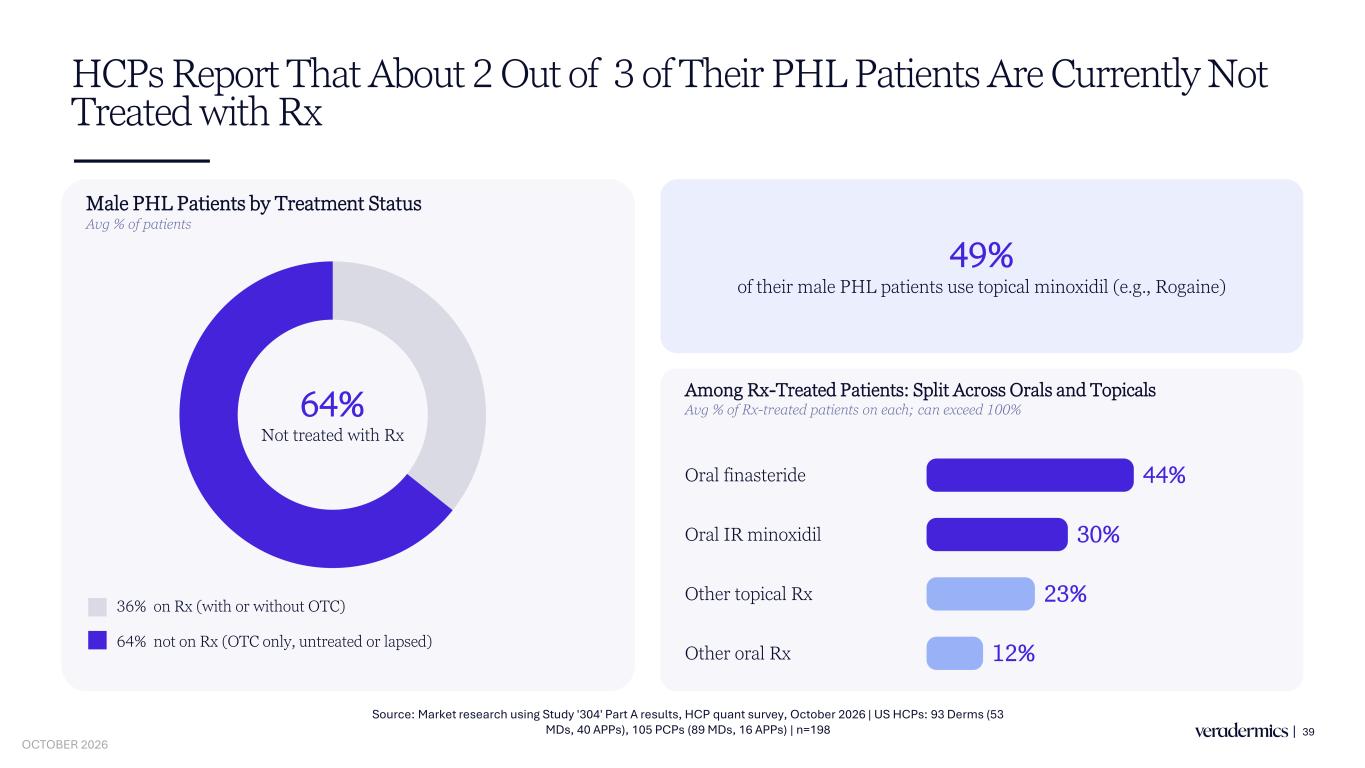
HCPs Report That About 2 Out of 3 of Their PHL Patients Are Currently Not Treated with Rx 39 Male PHL Patients by Treatment Status Avg % of patients 49% of their male PHL patients use topical minoxidil (e.g., Rogaine) Among Rx-Treated Patients: Split Across Orals and Topicals Avg % of Rx-treated patients on each; can exceed 100% Oral finasteride 44% Oral IR minoxidil 30% Other topical Rx 23% Other oral Rx 12% 64% Not treated with Rx 36% on Rx (with or without OTC) 64% not on Rx (OTC only, untreated or lapsed) Source: Market research using Study '304' Part A results, HCP quant survey, October 2026 | US HCPs: 93 Derms (53 MDs, 40 APPs), 105 PCPs (89 MDs, 16 APPs) | n=198 OCTOBER 2026
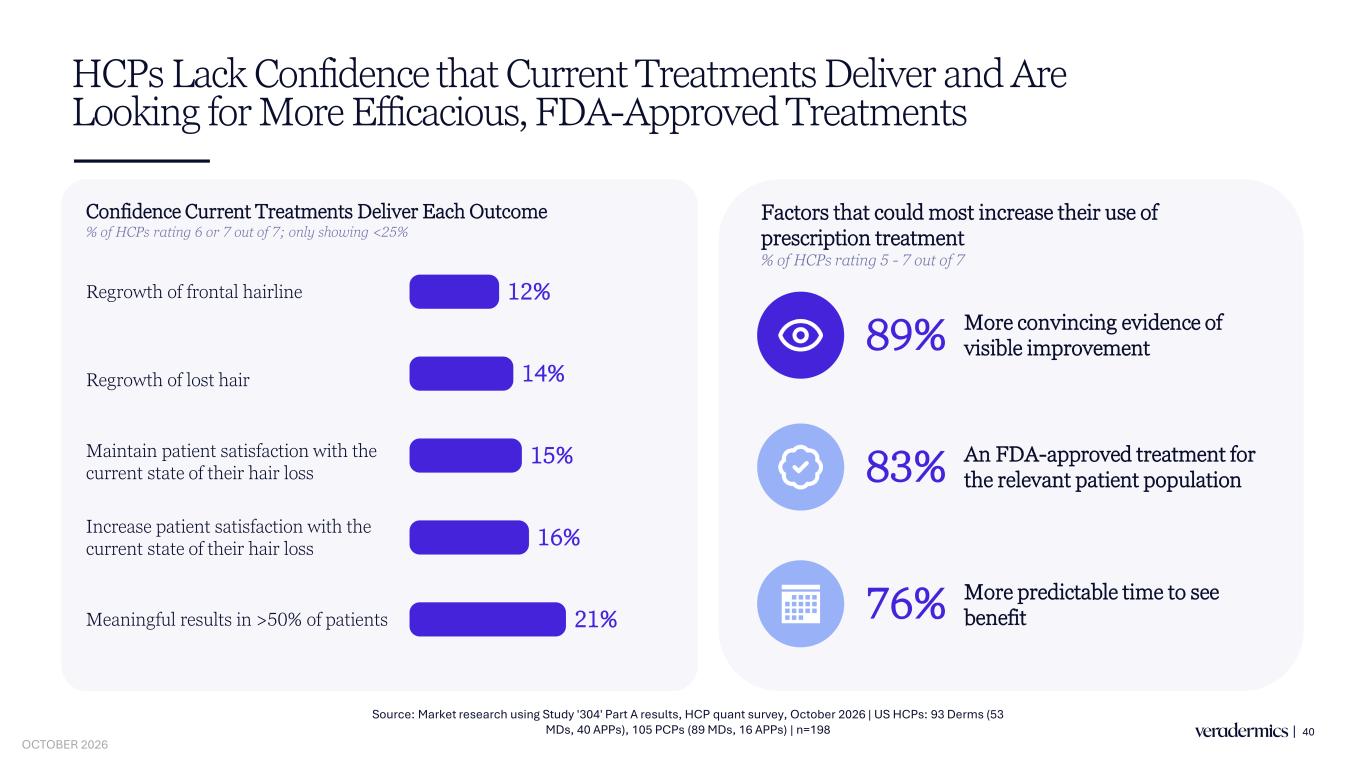
HCPs Lack Confidence that Current Treatments Deliver and Are Looking for More Efficacious, FDA-Approved Treatments 40 Confidence Current Treatments Deliver Each Outcome % of HCPs rating 6 or 7 out of 7; only showing <25% Regrowth of frontal hairline 12% Regrowth of lost hair 14% Meaningful results in >50% of patients 21% Maintain patient satisfaction with the current state of their hair loss 15% Increase patient satisfaction with the current state of their hair loss 16% Source: Market research using Study '304' Part A results, HCP quant survey, October 2026 | US HCPs: 93 Derms (53 MDs, 40 APPs), 105 PCPs (89 MDs, 16 APPs) | n=198 89% More convincing evidence of visible improvement 83% An FDA-approved treatment for the relevant patient population 76% More predictable time to see benefit Factors that could most increase their use of prescription treatment % of HCPs rating 5 - 7 out of 7 OCTOBER 2026
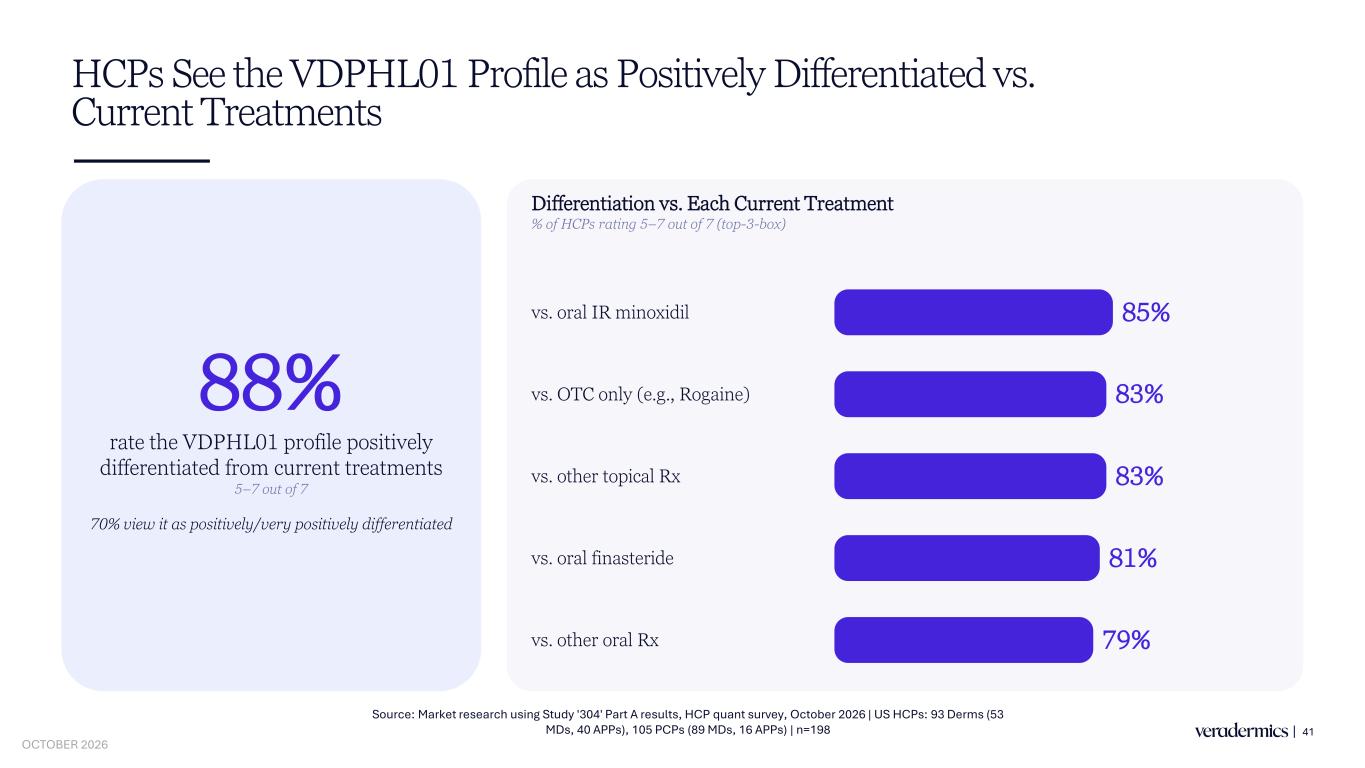
HCPs See the VDPHL01 Profile as Positively Differentiated vs. Current Treatments 41 88% rate the VDPHL01 profile positively differentiated from current treatments 5–7 out of 7 70% view it as positively/very positively differentiated Differentiation vs. Each Current Treatment % of HCPs rating 5–7 out of 7 (top-3-box) vs. oral IR minoxidil 85% vs. OTC only (e.g., Rogaine) 83% vs. other topical Rx 83% vs. oral finasteride 81% vs. other oral Rx 79% Source: Market research using Study '304' Part A results, HCP quant survey, October 2026 | US HCPs: 93 Derms (53 MDs, 40 APPs), 105 PCPs (89 MDs, 16 APPs) | n=198 OCTOBER 2026
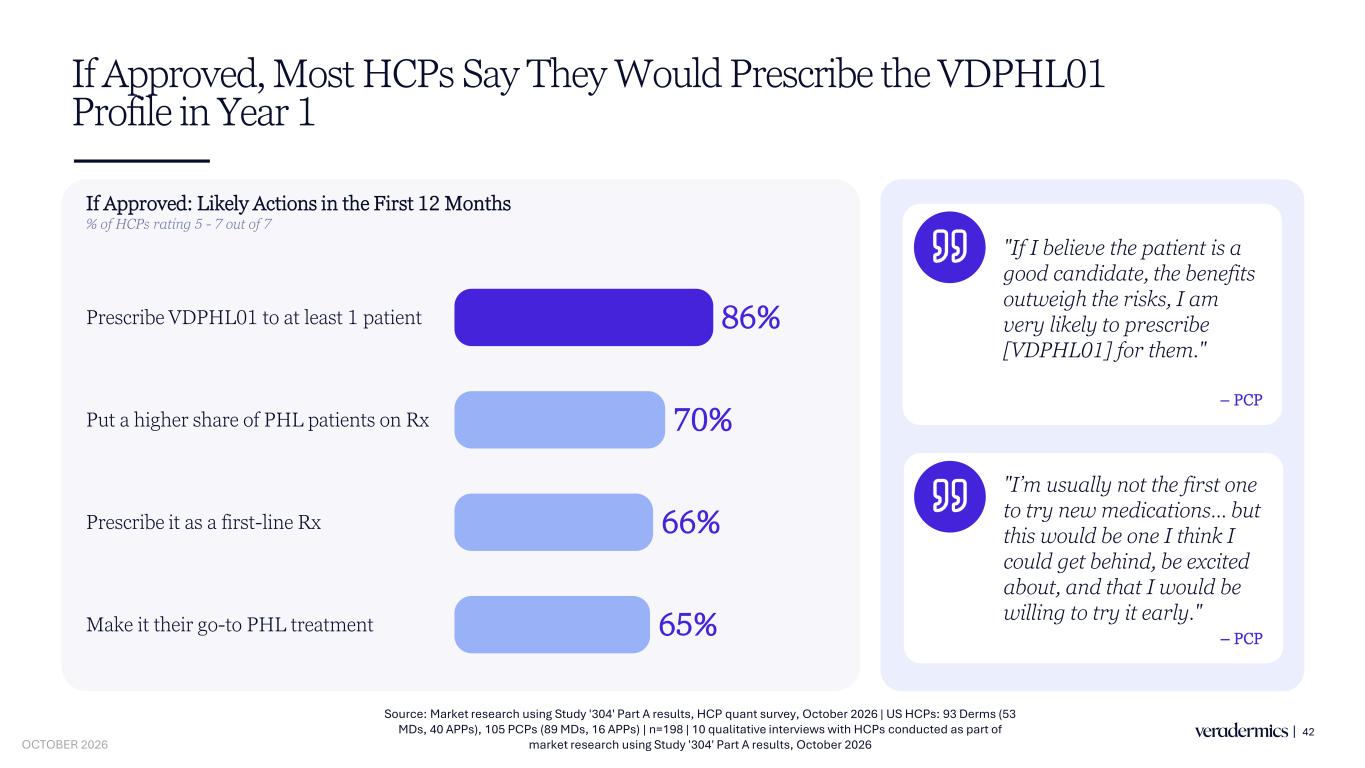
If Approved, Most HCPs Say They Would Prescribe the VDPHL01 Profile in Year 1 42 If Approved: Likely Actions in the First 12 Months % of HCPs rating 5 - 7 out of 7 Prescribe VDPHL01 to at least 1 patient 86% Prescribe it as a first-line Rx 66% Put a higher share of PHL patients on Rx 70% Make it their go-to PHL treatment 65% – PCP "If I believe the patient is a good candidate, the benefits outweigh the risks, I am very likely to prescribe [VDPHL01] for them." "I’m usually not the first one to try new medications… but this would be one I think I could get behind, be excited about, and that I would be willing to try it early." – PCP Source: Market research using Study '304' Part A results, HCP quant survey, October 2026 | US HCPs: 93 Derms (53 MDs, 40 APPs), 105 PCPs (89 MDs, 16 APPs) | n=198 | 10 qualitative interviews with HCPs conducted as part of market research using Study '304' Part A results, October 2026 OCTOBER 2026
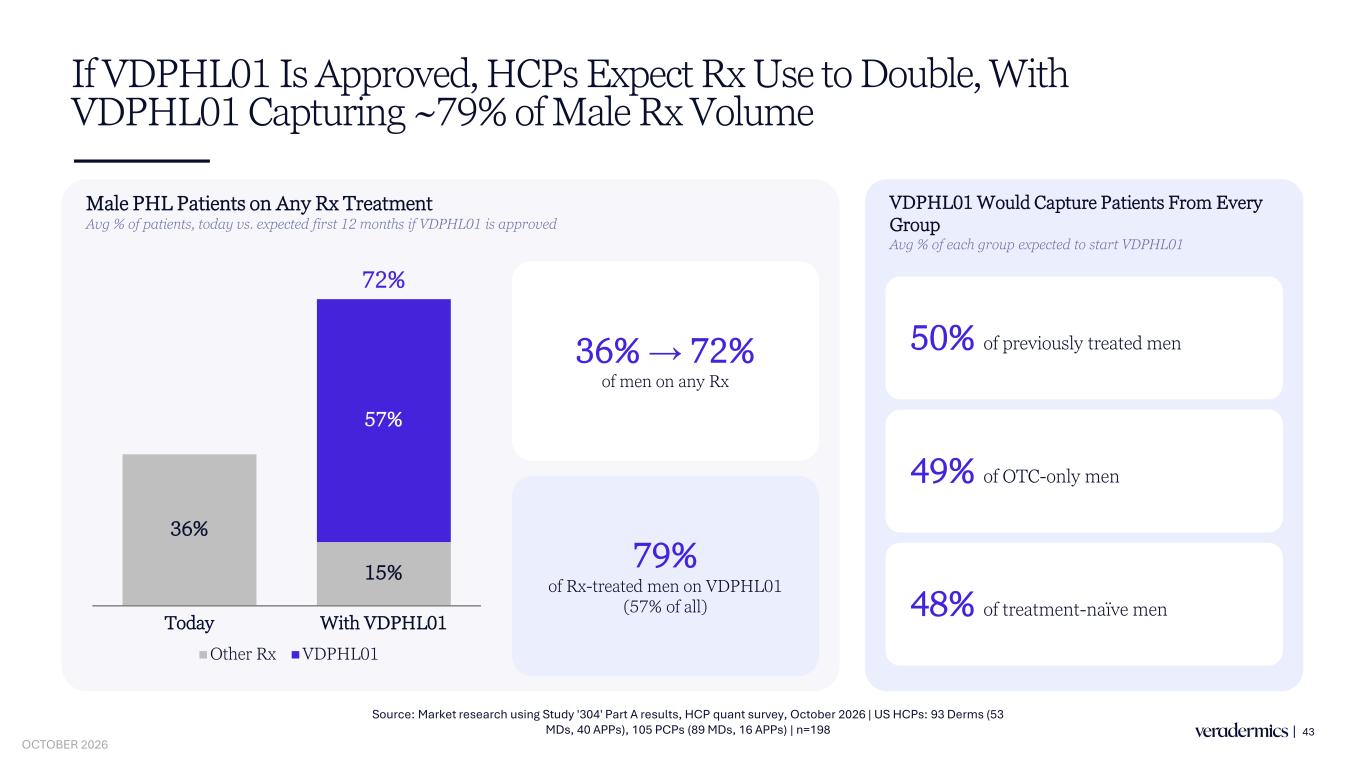
If VDPHL01 Is Approved, HCPs Expect Rx Use to Double, With VDPHL01 Capturing ~79% of Male Rx Volume 43 Male PHL Patients on Any Rx Treatment Avg % of patients, today vs. expected first 12 months if VDPHL01 is approved 36% 15% 57% Today With VDPHL01 Other Rx VDPHL01 36% → 72% of men on any Rx 79% of Rx-treated men on VDPHL01 (57% of all) VDPHL01 Would Capture Patients From Every Group Avg % of each group expected to start VDPHL01 48% of treatment-naïve men 50% of previously treated men 49% of OTC-only men Source: Market research using Study '304' Part A results, HCP quant survey, October 2026 | US HCPs: 93 Derms (53 MDs, 40 APPs), 105 PCPs (89 MDs, 16 APPs) | n=198 72% OCTOBER 2026
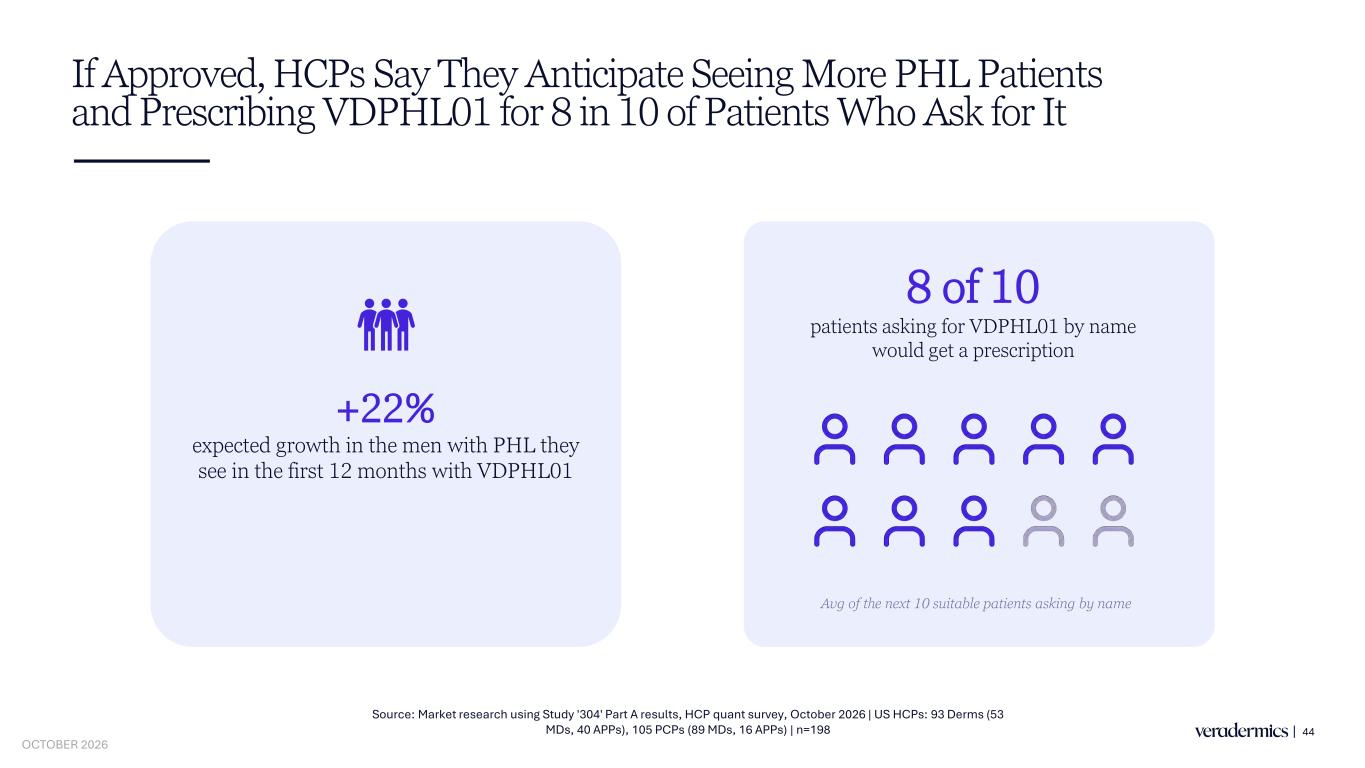
If Approved, HCPs Say They Anticipate Seeing More PHL Patients and Prescribing VDPHL01 for 8 in 10 of Patients Who Ask for It 44 +22% expected growth in the men with PHL they see in the first 12 months with VDPHL01 8 of 10 patients asking for VDPHL01 by name would get a prescription Avg of the next 10 suitable patients asking by name Source: Market research using Study '304' Part A results, HCP quant survey, October 2026 | US HCPs: 93 Derms (53 MDs, 40 APPs), 105 PCPs (89 MDs, 16 APPs) | n=198 OCTOBER 2026
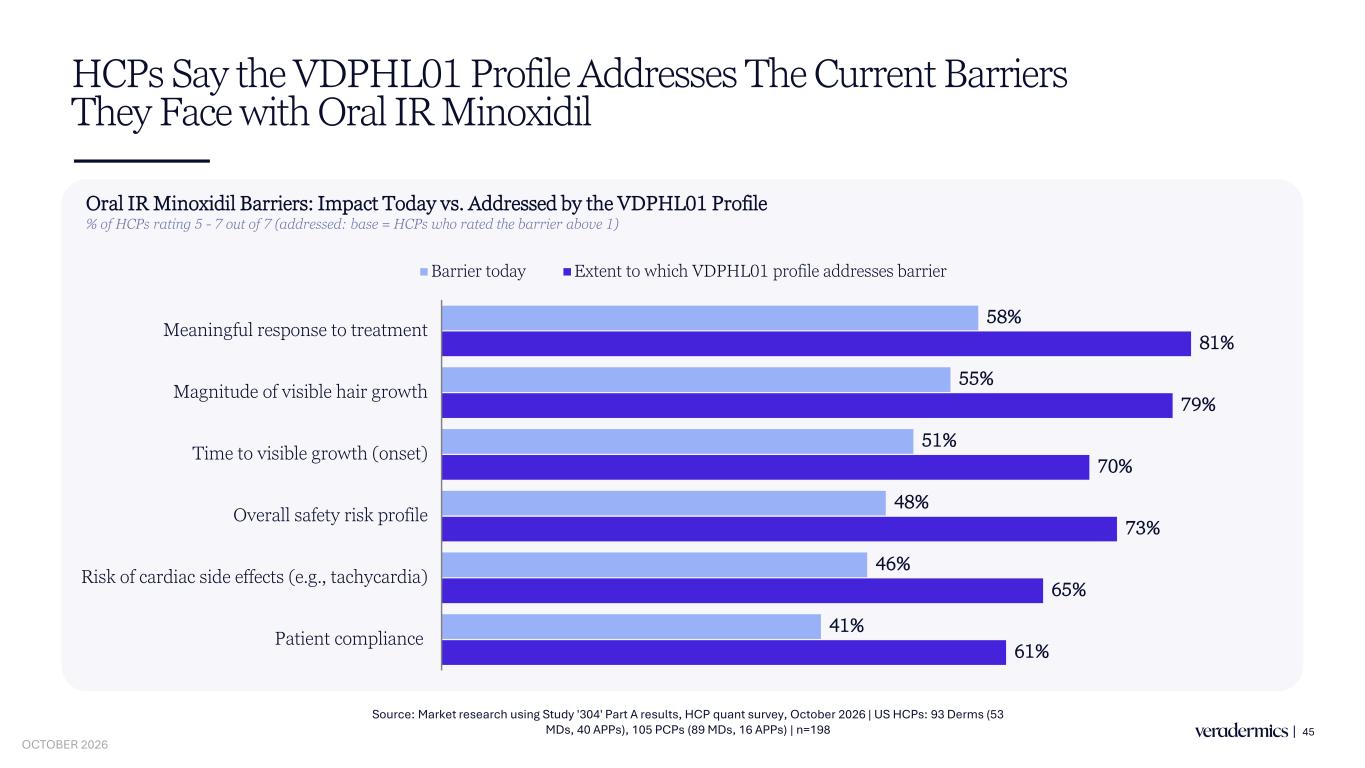
HCPs Say the VDPHL01 Profile Addresses The Current Barriers They Face with Oral IR Minoxidil 45 Oral IR Minoxidil Barriers: Impact Today vs. Addressed by the VDPHL01 Profile % of HCPs rating 5 - 7 out of 7 (addressed: base = HCPs who rated the barrier above 1) 58% 55% 51% 48% 46% 41% 81% 79% 70% 73% 65% 61% Meaningful response to treatment Magnitude of visible hair growth Time to visible growth (onset) Overall safety risk profile Risk of cardiac side effects (e.g., tachycardia) Patient compliance Barrier today Extent to which VDPHL01 profile addresses barrier Source: Market research using Study '304' Part A results, HCP quant survey, October 2026 | US HCPs: 93 Derms (53 MDs, 40 APPs), 105 PCPs (89 MDs, 16 APPs) | n=198 OCTOBER 2026
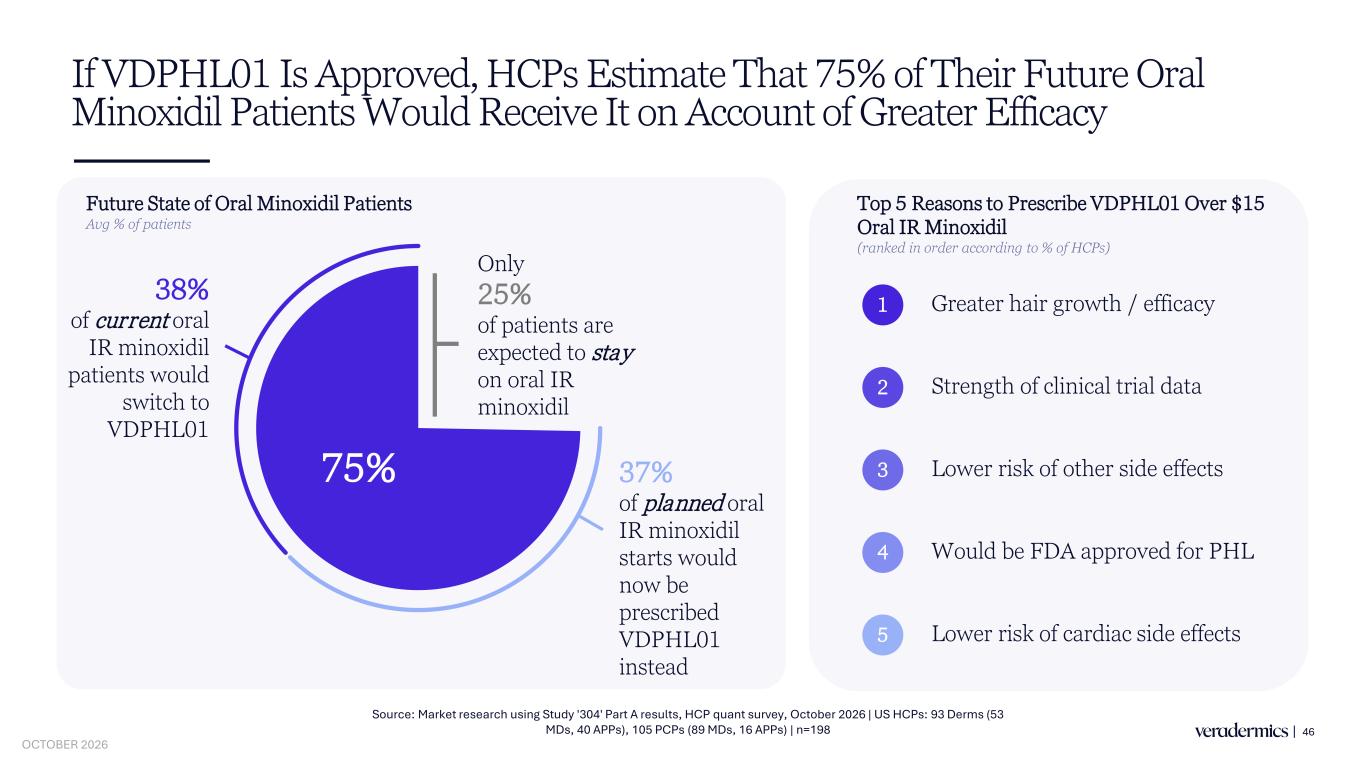
If VDPHL01 Is Approved, HCPs Estimate That 75% of Their Future Oral Minoxidil Patients Would Receive It on Account of Greater Efficacy 46 Future State of Oral Minoxidil Patients Avg % of patients 75% 38% of current oral IR minoxidil patients would switch to VDPHL01 Top 5 Reasons to Prescribe VDPHL01 Over $15 Oral IR Minoxidil (ranked in order according to % of HCPs) Greater hair growth / efficacy1 Strength of clinical trial data2 Lower risk of other side effects3 Would be FDA approved for PHL4 Lower risk of cardiac side effects5 Source: Market research using Study '304' Part A results, HCP quant survey, October 2026 | US HCPs: 93 Derms (53 MDs, 40 APPs), 105 PCPs (89 MDs, 16 APPs) | n=198 37% of planned oral IR minoxidil starts would now be prescribed VDPHL01 instead Only 25% of patients are expected to stay on oral IR minoxidil OCTOBER 2026
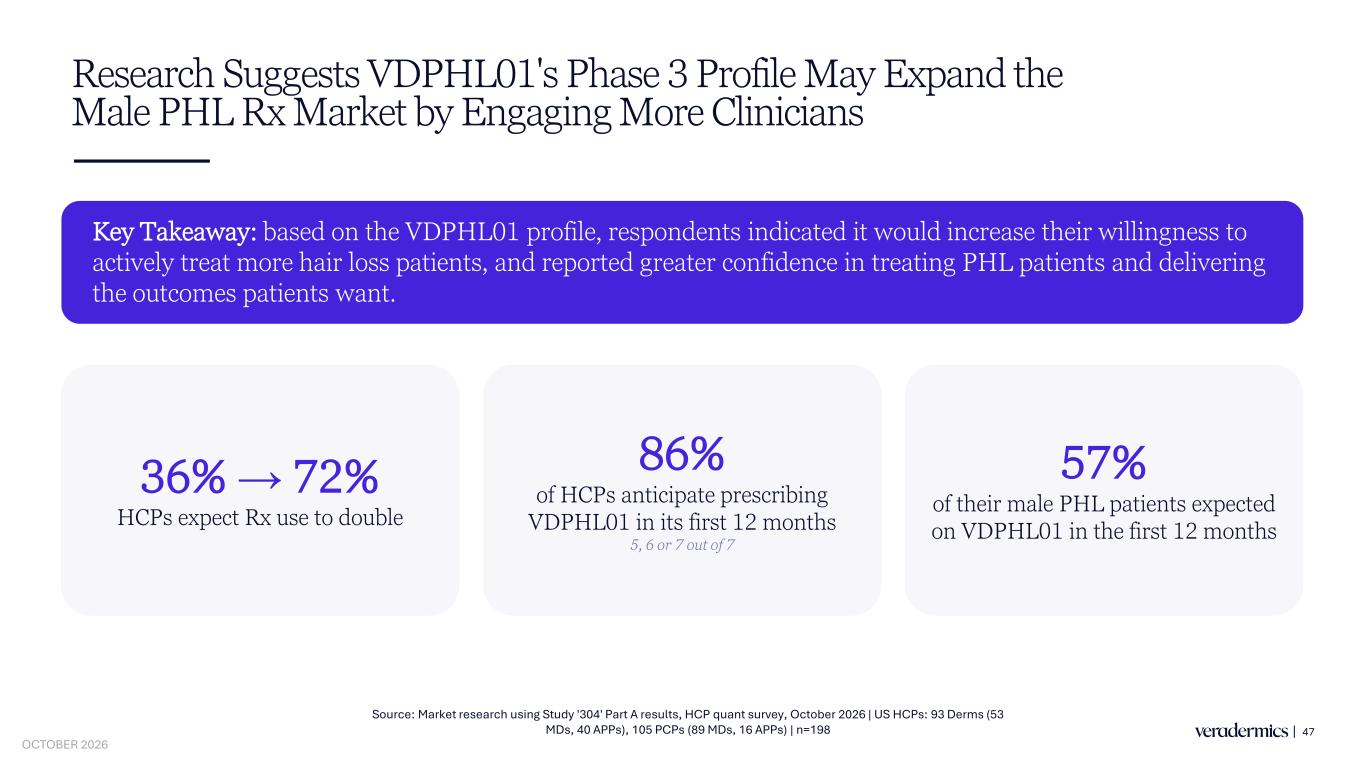
Research Suggests VDPHL01's Phase 3 Profile May Expand the Male PHL Rx Market by Engaging More Clinicians 47 Key Takeaway: based on the VDPHL01 profile, respondents indicated it would increase their willingness to actively treat more hair loss patients, and reported greater confidence in treating PHL patients and delivering the outcomes patients want. 86% of HCPs anticipate prescribing VDPHL01 in its first 12 months 5, 6 or 7 out of 7 57% of their male PHL patients expected on VDPHL01 in the first 12 months 36% → 72% HCPs expect Rx use to double Source: Market research using Study '304' Part A results, HCP quant survey, October 2026 | US HCPs: 93 Derms (53 MDs, 40 APPs), 105 PCPs (89 MDs, 16 APPs) | n=198 OCTOBER 2026

Closing Remarks 48 OCTOBER 2026
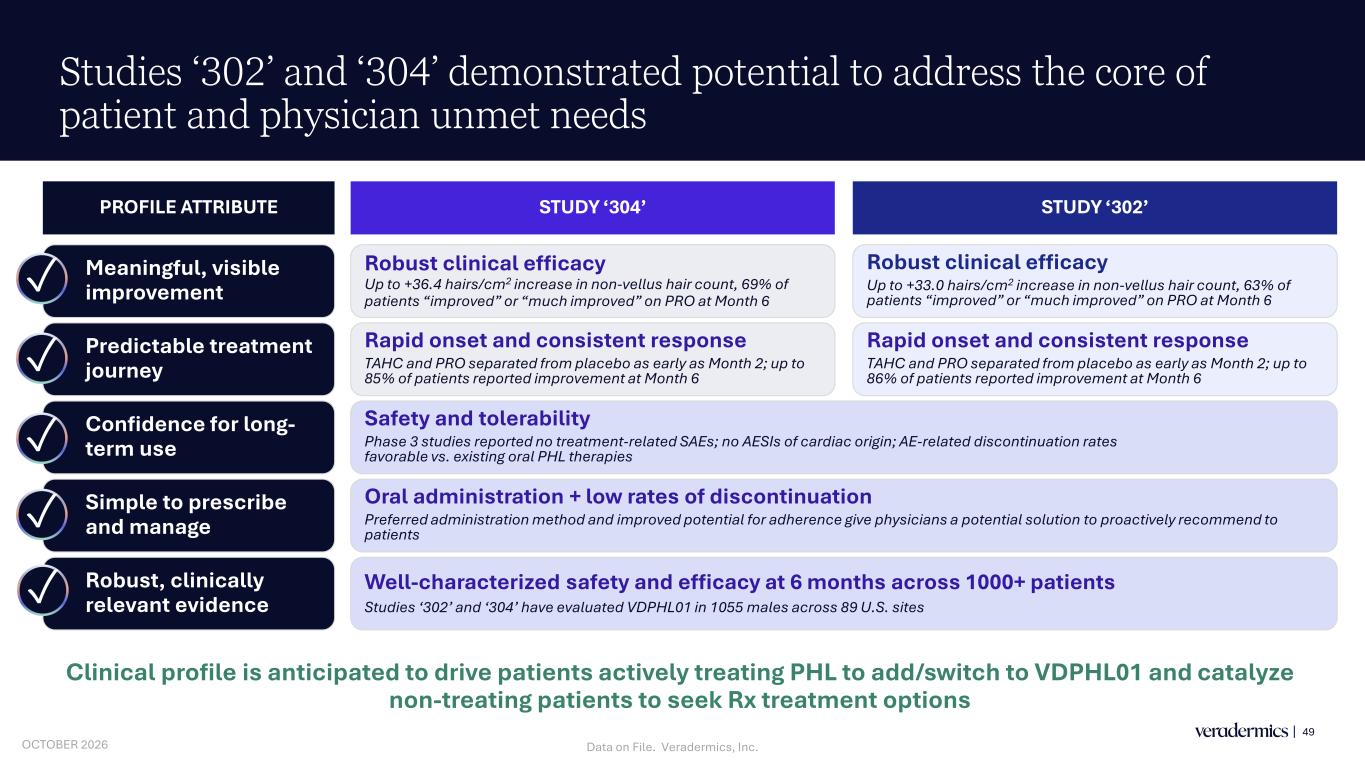
Studies ‘302’ and ‘304’ demonstrated potential to address the core of patient and physician unmet needs 49 PROFILE ATTRIBUTE STUDY ‘302’STUDY ‘304’ Meaningful, visible improvement✓ Robust clinical efficacy Up to +33.0 hairs/cm2 increase in non-vellus hair count, 63% of patients “improved” or “much improved” on PRO at Month 6 Robust clinical efficacy Up to +36.4 hairs/cm2 increase in non-vellus hair count, 69% of patients “improved” or “much improved” on PRO at Month 6 Predictable treatment journey✓ Rapid onset and consistent response TAHC and PRO separated from placebo as early as Month 2; up to 86% of patients reported improvement at Month 6 Rapid onset and consistent response TAHC and PRO separated from placebo as early as Month 2; up to 85% of patients reported improvement at Month 6 Confidence for long- term use✓ Safety and tolerability Phase 3 studies reported no treatment-related SAEs; no AESIs of cardiac origin; AE-related discontinuation rates favorable vs. existing oral PHL therapies Simple to prescribe and manage✓ Oral administration + low rates of discontinuation Preferred administration method and improved potential for adherence give physicians a potential solution to proactively recommend to patients Robust, clinically relevant evidence✓ Well-characterized safety and efficacy at 6 months across 1000+ patients Studies ‘302’ and ‘304’ have evaluated VDPHL01 in 1055 males across 89 U.S. sites Clinical profile is anticipated to drive patients actively treating PHL to add/switch to VDPHL01 and catalyze non-treating patients to seek Rx treatment options Data on File. Veradermics, Inc.OCTOBER 2026
