
CORPORATE PRESENTATION OCTOBER 2026 Exhibit 99.1

DISCLAIMERS The information in this Presentation has been prepared by IRulya Therapeutics Inc. (formerly Quince Therapeutics, Inc., “IRulya”, and the “company”) and contains information pertaining to the business and operations of the company. The information contained in this Presentation: (a) is provided as at the date hereof, is subject to change without notice, and is based on publicly available data, internally developed data as well as third party information from other sources; (b) does not purport to contain all the information that may be necessary or desirable to fully and accurately evaluate an investment in the company; (c) is not to be considered a recommendation by the company that any person make an investment in the company; (d) is for information purposes only and shall not constitute an offer to buy, sell, issue or subscribe for, or the solicitation of an offer to buy, sell or issue, or subscribe for any securities of the company in any jurisdiction in which such offer solicitation or sale would be unlawful. Where any opinion or belief is expressed in this Presentation, it is based on certain assumptions and limitations and is an expression of present opinion or belief only. This Presentation should not be construed as legal, financial or tax advice to any individual, as each individual’s circumstances are different. This Presentation is for informational purposes only and should not be considered a solicitation or recommendation to purchase, sell or hold a security. Certain matters discussed in this Presentation may contain forward-looking statements that are, by their nature, subject to significant risks and uncertainties. Forward-looking statements can be identified by words such as “may,” “will,” “should,” “would,” “could,” “believe,” “expect,” ‘anticipate,” “intend,” “plan,” “continue,” “seek,” “estimate,” “potential” or the negative of these terms or other similar terms. Forward-looking statements in this Presentation include, but are not limited to, statements about: the company’s product candidates, in particular LAM-001, and the potential benefits thereof, including the potential benefits of LAM-001 across exercise capacity, pulmonary hemodynamics, cardiac stress and lung function and six minute walk distance (6MWD) and pulmonary vascular resistance (PVR); planned and ongoing pre-clinical and clinical studies, including the timing for data readouts and future development milestones; expected regulatory approval pathways; the market opportunity and patient population for LAM-001 in pulmonary hypertension associated with interstitial lung disease (PH-ILD), bronchiolitis obliterans syndrome (BOS) and sarcoidosis associated pulmonary hypertension (SAPH); and expectations regarding patent protection and exclusivity for the company’s product candidates. Such forward-looking statements reflect the current views of the company’s management regarding future events; they are not guarantees of future performance. These forward-looking statements involve significant risks and uncertainties that could cause actual results to differ materially and adversely from results expressed or implied by this Presentation, including, amongst others: the ability of the company’s clinical trials to demonstrate acceptable safety and efficacy of its product candidates and other positive results; clinical results may not be indicative of results that may be observed in the future, including in larger patient populations; the progress of the company’s preclinical studies and clinical trials; risks related to clinical development and regulatory approval of the company’s product candidates, including potential delays in the commencement, enrollment and completion of clinical trials; the ability of the company to obtain sufficient additional capital to further advance its clinical programs; the size of the market opportunities for the company’s product candidates; competition in the company’s industry; the rate and degree of market acceptance of the company’s product candidates as compared to alternative therapies; changes in applicable laws or regulations; the ability of the company to realize the anticipated benefits from the acquisition of Orphai Therapeutics (“Orphai”) and the concurrent private transactions; investors in the private placement or former Orphai warrant holders may not exercise their warrants and the company may not receive any additional proceeds therefrom; the impacts of general macroeconomic and geopolitical conditions to the company’s business and financial position; and other risks and uncertainties from time to time described in IRulya’s Quarterly Report on Form 10-Q for the quarter ended June 30, 2026, filed with the U.S. Securities and Exchange Commission (“SEC”) on August 14, 2026, including those under the “Risk Factors” section therein, and in IRulya’s other filings with SEC. The company assumes no obligation to update any forward-looking information contained in this Presentation. Certain information contained in this Presentation are related to or are based on studies, publications and other data obtained from third party sources as well as our own internal estimates and research. While the company believes that such third-party sources are reliable, there can be no assurance as to the accuracy or completeness of the indicated information. The company has not independently verified the information provided by such third-party sources. This Presentation may contain trademarks, service marks, trade names and copyrights of other companies, which are the property of their respective owners. Solely for convenience, some of the trademarks, service marks, trade names and copyrights referred to in this Presentation may be listed without the TM, SM, © or ® symbols, but the company will assert, to the fullest extent under applicable law, the rights of the owners to these trademarks, service marks, trade names and copyrights.

INVESTMENT HIGHLIGHTS Rare disease focused, clinical-staged biotechnology company developing a novel, once-daily, inhaled, disease modifying rapamycin formulation (LAM-001) across multiple Phase 2 programs: PH-ILD (~200K US/EU)1 –Current therapies are limited to vasodilation, not disease modifying2. Promising Ph 2a data on top of standard of care presented ATS 2026; Ph 2b expected to initiate mid-2026. BOS (~30K US/EU)3 - Severe complication of and leading cause of death post lung transplantation4. Positive, retrospective data from clinical utilization of oral rapamycin support an ongoing Ph 2 trial with data expected 1Q 2027. SAPH (~60K US/EU)5 - Severe complication of sarcoidosis with no approved therapy (PH WHO group 5). Ph 2 trial expected to initiate in 4Q 2026, supported by proof-of-concept clinical efficacy data from completed PH study. Efficient 505(b)2 development pathway for lead program (LAM-001), with strong IP coverage expected to the mid 2040's US/EU Orphan Disease Status granted for multiple indications Supportive FDA feedback from end of Phase 2 and pre-IND meetings Represents estimated patient population in the US and EU: Wijsenbeek 2020 DOI: 10.1056/NEJMra2005230, Ang 2024 https://doi.org/10.1016/j.chest.2024.04.025 Shlobin 2024 https://doi.org/10.1002/pul2.12310 Represents estimated patient population in the US and EU at projected launch: US HRSA Data, Kulkarni 2018:doi: 10.1016/j.healun.2018.09.016 and Company estimates Ehrsam 2021 doi.org/10.1016/j.healun.2021.01.887 Represents estimated patient population in the US and EU: American Lung Association Data, Duong 2018, https://doi.org/10.1097/CPM.0000000000000252

LAM-001 2026 2027 2028 ESTIMATED US/EU MARKET ANTICIPATED DATA READOUTS Pulmonary Hypertension-Interstitial Lung Disease (PH-ILD) ~200k 1Q-28 Bronchiolitis Obliterans Syndrome (BOS) ~30k 1Q-27 Sarcoidosis Associated PH (SAPH) ~60k 4Q-28 IRULYA PIPELINE AND ANTICIPATED MILESTONES Anticipated Data Readout Phase 2B (PH-ILD) Phase 2 (IIT) Phase 2 (IIT)
* Systemic bioavailability of 14 – 18% due to poor aqueous solubility, high molecular weight, extensive first‑pass metabolism, variable gastrointestinal conditions, food effects, and P‑glycoprotein-mediated efflux Sirolimus (Rapamycin) prescribing information, NIH NLM; Revised 5/2026 LIMITATIONS OF ORAL RAPAMYCIN SYSTEMIC EXPOSURE WITH SIGNIFICANT SAFETY RISKS: Oral Rapamune® Key Label Warnings and Precautions: Angioedema, Fluid Accumulation and Impairment of Wound Healing, Hyperlipidemia, Decline in Renal Function, Proteinuria, Latent Viral Infections, Male Infertility, Embryo-Fetal Toxicity LIMITED LUNG EXPOSURE: Systemic toxicity limits oral dosing levels and may preclude sufficient lung exposure LOW AND VARIABLE ORAL BIOAVAILABILITY*: Requiring inconvenient plasma monitoring and frequent dose adjustments We believe these limitations preclude the adoption of oral rapamycin in pulmonary diseases where the mTOR pathway has been clearly implicated

Based on non-clinical and clinical studies conducted by the Company, Sirolimus (Rapamycin) prescribing information. NIH NLM; Revised 5/2026 No head-to-head clinical trials have been conducted evaluating LAM-001 and Rapamycin. Differences exist between study or trial designs and participant characteristics, and caution should be exercised when comparing data across studies SOLUTION: LAM-001 DESIGNED FOR IMPROVED PULMONARY DELIVERY OF RAPAMYCIN TARGETED DELIVERY: Direct lung delivery à higher local exposure versus oral or nebulized formulations IDEAL PHYSICAL CHEMICAL PROPERTIES FOR LUNG DELIVERY: Enhanced lung exposure and potential improved efficacy in pulmonary diseases MINIMIZED SYSTEMIC EXPOSURE AND WELL-TOLERATED SAFETY PROFILE: Reduced systemic side effects compared to oral rapamycin CONVENIENT ADMINISTRATION: Easy-to-use once-a-day dry powder inhaler (DPI) designed to enhance patient compliance; fixed dose with no need for blood level monitoring (required with oral rapamycin due to low and variable oral bioavailability)
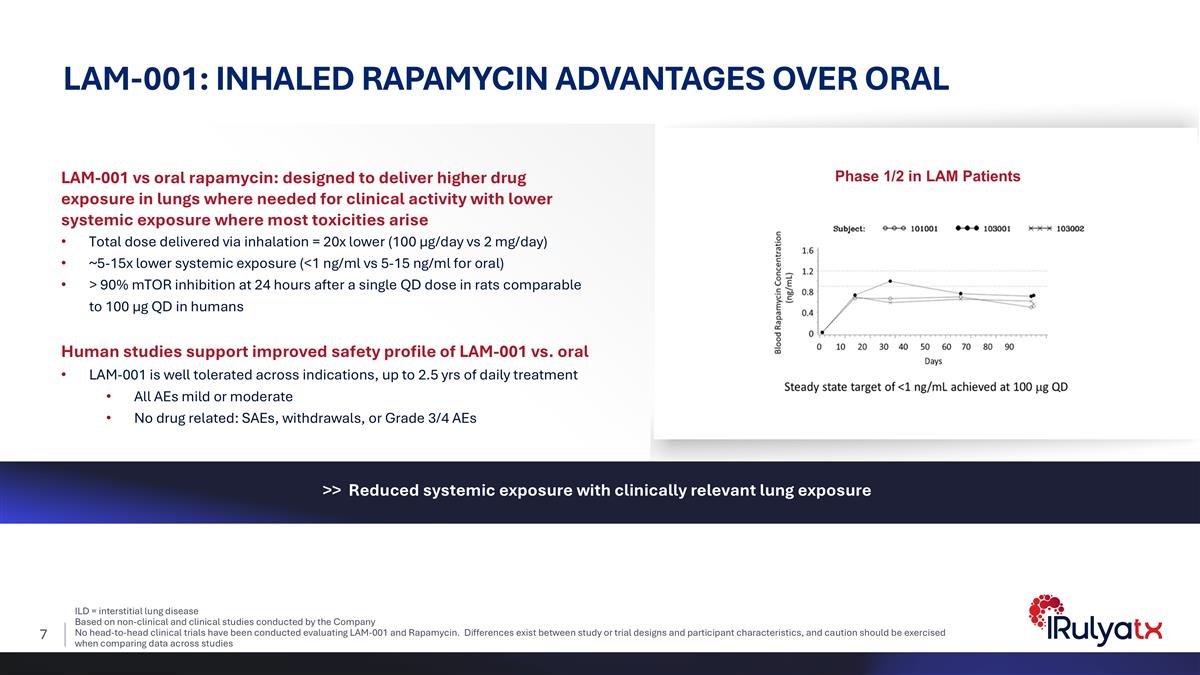
ILD = interstitial lung disease Based on non-clinical and clinical studies conducted by the Company No head-to-head clinical trials have been conducted evaluating LAM-001 and Rapamycin. Differences exist between study or trial designs and participant characteristics, and caution should be exercised when comparing data across studies LAM-001: INHALED RAPAMYCIN ADVANTAGES OVER ORAL Phase 1/2 in LAM Patients LAM-001 vs oral rapamycin: designed to deliver higher drug exposure in lungs where needed for clinical activity with lower systemic exposure where most toxicities arise Total dose delivered via inhalation = 20x lower (100 µg/day vs 2 mg/day) ~5-15x lower systemic exposure (<1 ng/ml vs 5-15 ng/ml for oral) > 90% mTOR inhibition at 24 hours after a single QD dose in rats comparable to 100 µg QD in humans Human studies support improved safety profile of LAM-001 vs. oral LAM-001 is well tolerated across indications, up to 2.5 yrs of daily treatment All AEs mild or moderate No drug related: SAEs, withdrawals, or Grade 3/4 AEs >> Reduced systemic exposure with clinically relevant lung exposure

LAM-001: GROUP 3 PULMONARY HYPERTENSION (PH-ILD)
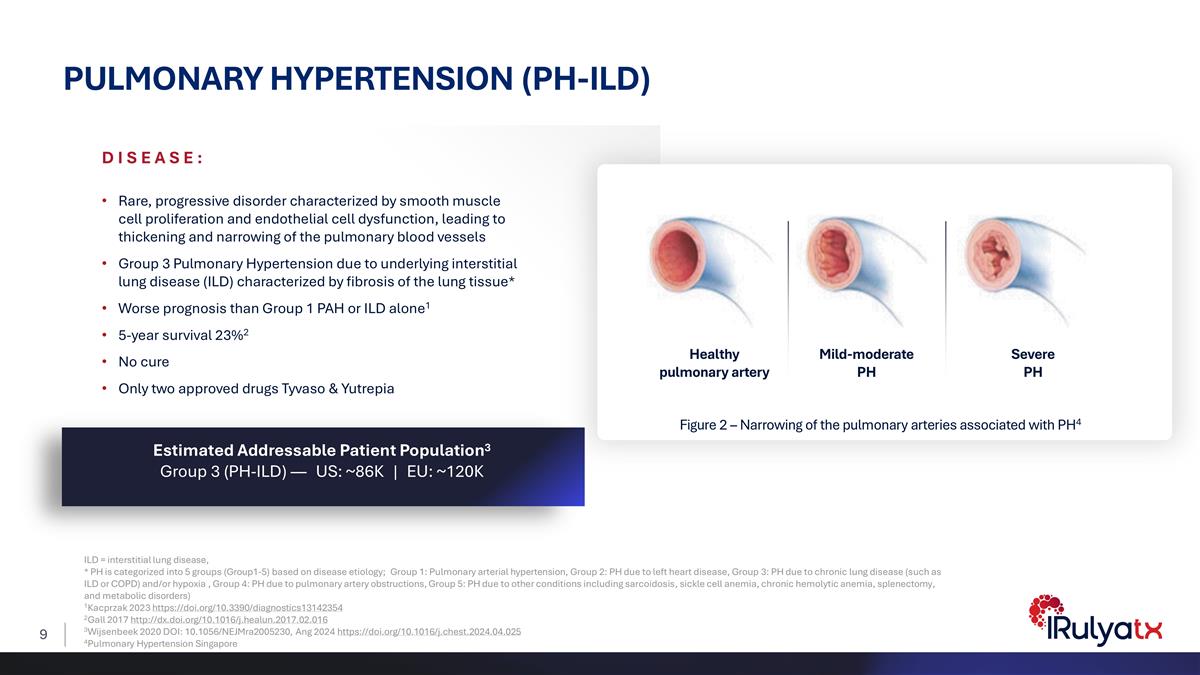
PULMONARY HYPERTENSION (PH-ILD) DISEASE: Rare, progressive disorder characterized by smooth muscle cell proliferation and endothelial cell dysfunction, leading to thickening and narrowing of the pulmonary blood vessels Group 3 Pulmonary Hypertension due to underlying interstitial lung disease (ILD) characterized by fibrosis of the lung tissue* Worse prognosis than Group 1 PAH or ILD alone1 5-year survival 23%2 No cure Only two approved drugs Tyvaso & Yutrepia Estimated Addressable Patient Population3 Group 3 (PH-ILD) — US: ~86K | EU: ~120K Figure 2 – Narrowing of the pulmonary arteries associated with PH4 Mild-moderate PH Healthy pulmonary artery Severe PH ILD = interstitial lung disease, * PH is categorized into 5 groups (Group1-5) based on disease etiology; Group 1: Pulmonary arterial hypertension, Group 2: PH due to left heart disease, Group 3: PH due to chronic lung disease (such as ILD or COPD) and/or hypoxia , Group 4: PH due to pulmonary artery obstructions, Group 5: PH due to other conditions including sarcoidosis, sickle cell anemia, chronic hemolytic anemia, splenectomy, and metabolic disorders) 1Kacprzak 2023 https://doi.org/10.3390/diagnostics13142354 2Gall 2017 http://dx.doi.org/10.1016/j.healun.2017.02.016 3Wijsenbeek 2020 DOI: 10.1056/NEJMra2005230, Ang 2024 https://doi.org/10.1016/j.chest.2024.04.025 4Pulmonary Hypertension Singapore
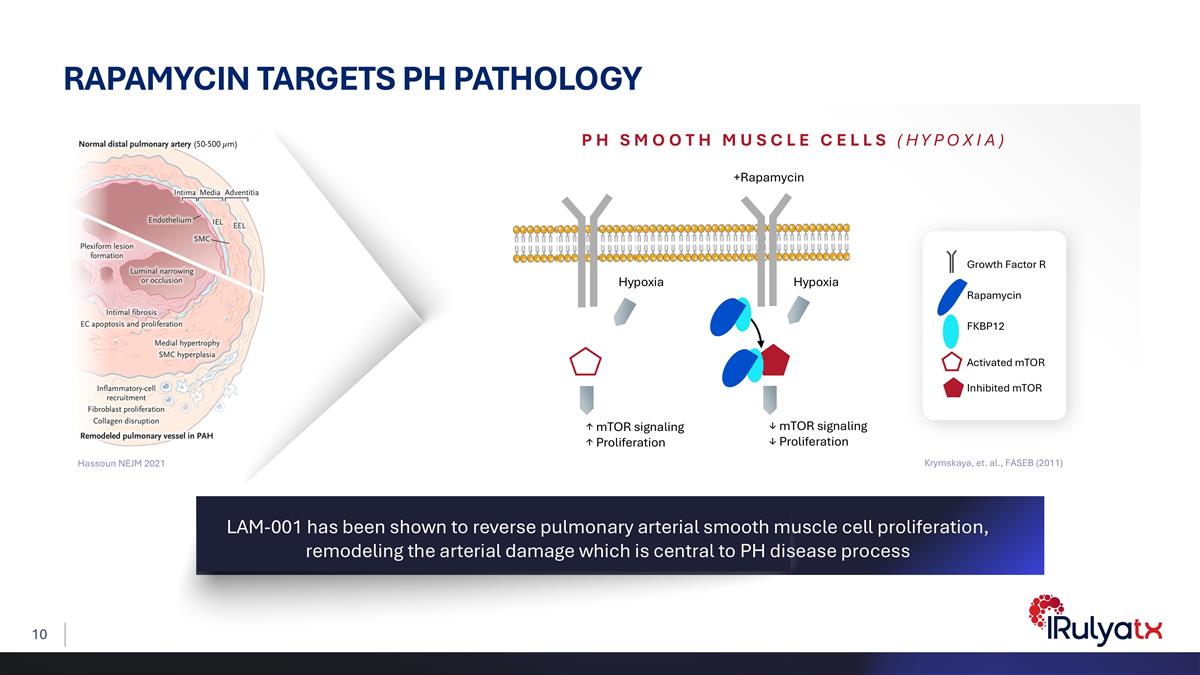
RAPAMYCIN TARGETS PH PATHOLOGY PH SMOOTH MUSCLE CELLS (HYPOXIA) Rapamycin FKBP12 Activated mTOR Inhibited mTOR ↑ mTOR signaling ↑ Proliferation ↓ mTOR signaling ↓ Proliferation Hypoxia Hypoxia +Rapamycin Krymskaya, et. al., FASEB (2011) Growth Factor R Hassoun NEJM 2021 LAM-001 has been shown to reverse pulmonary arterial smooth muscle cell proliferation, remodeling the arterial damage which is central to PH disease process
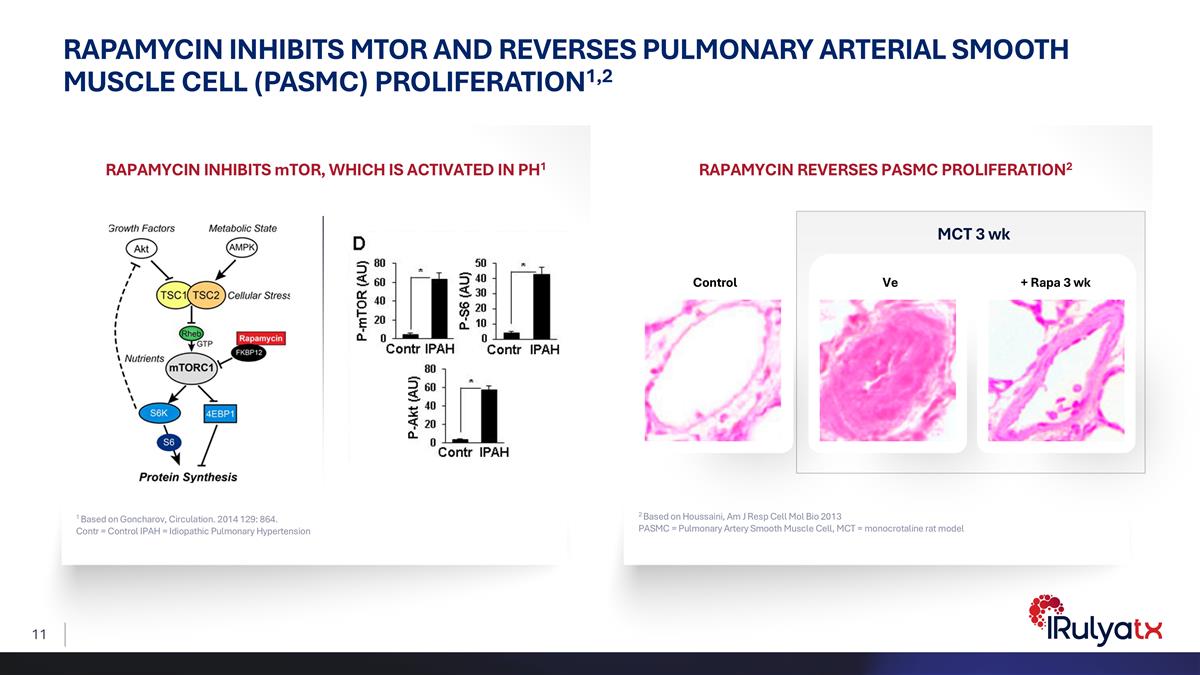
RAPAMYCIN REVERSES PASMC PROLIFERATION2 RAPAMYCIN INHIBITS MTOR AND REVERSES PULMONARY ARTERIAL SMOOTH MUSCLE CELL (PASMC) PROLIFERATION1,2 2 Based on Houssaini, Am J Resp Cell Mol Bio 2013 PASMC = Pulmonary Artery Smooth Muscle Cell, MCT = monocrotaline rat model MCT 3 wk Ve + Rapa 3 wk Control 1 Based on Goncharov, Circulation. 2014 129: 864. Contr = Control IPAH = Idiopathic Pulmonary Hypertension RAPAMYCIN INHIBITS mTOR, WHICH IS ACTIVATED IN PH1
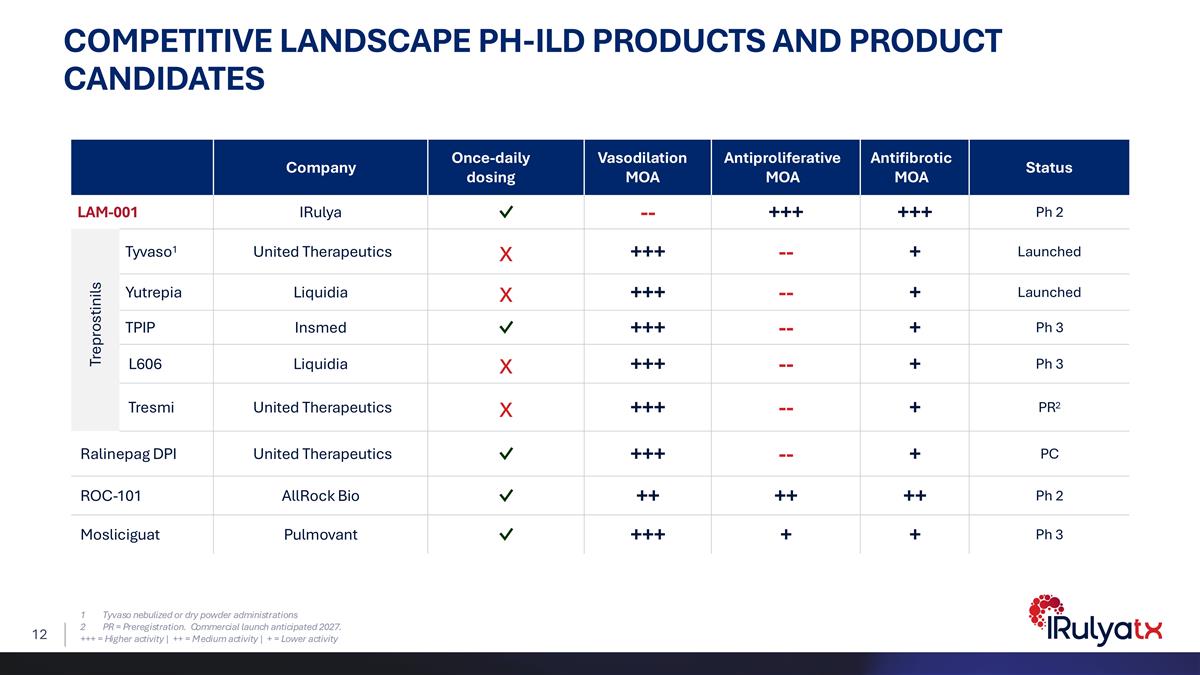
Tyvaso nebulized or dry powder administrations PR = Preregistration. Commercial launch anticipated 2027. +++ = Higher activity | ++ = Medium activity | + = Lower activity COMPETITIVE LANDSCAPE PH-ILD PRODUCTS AND PRODUCT CANDIDATES Company Once-daily dosing Vasodilation MOA Antiproliferative MOA Antifibrotic MOA Status LAM-001 IRulya ✓ -- +++ +++ Ph 2 Treprostinils Tyvaso1 United Therapeutics x +++ -- + Launched Yutrepia Liquidia x +++ -- + Launched TPIP Insmed ✓ +++ -- + Ph 3 L606 Liquidia x +++ -- + Ph 3 Tresmi United Therapeutics x +++ -- + PR2 Ralinepag DPI United Therapeutics ✓ +++ -- + PC ROC-101 AllRock Bio ✓ ++ ++ ++ Ph 2 Mosliciguat Pulmovant ✓ +++ + + Ph 3

1iCPET is a diagnostic procedure in which patients undergo pulmonary and radial artery catheterization in conjunction with a bicycle exercise test to directly measure cardiac and pulmonary function during exercise. Bradley A. Maron, Barbara A. Cockrill, Aaron B. Waxman, David M. Systrom “Invasive Cardiopulmonary Exercise Test” Circulation 2013, 1157-1164 PVR = Pulmonary Vascular Resistance, 6MWD = 6 Minute Walk Distance, NT-proBNP = N-terminal pro-B-type natriuretic peptide PHASE 2a TRIAL OF LAM-001 IN GROUP 1 PAH AND GROUP 3 PH DESIGN Open Label; 24 wks; 4 sites; Invasive Cardiopulmonary Exercise Testing (iCPET)1 INCLUSION >18 yo; WHO Functional Class III; Group 1 PAH and Group 3 PH; symptomatic despite background Rx PRIMARY ENDPOINTS Peak oxygen uptake (VO2 max), Safety, Tolerability SECONDARY ENDPOINTS PVR, 6MWD, WHO functional class EXPLORATORY ENDPOINT NT-proBNP AARON B. WAXMAN, MD, PhD Principal Investigator 10 patients; Open label 100 µg LAM-001 qd + SOC Week 0 Week 24 iCPET1 iCPET1 DATA PRESENTED AT ATS MAY 2026
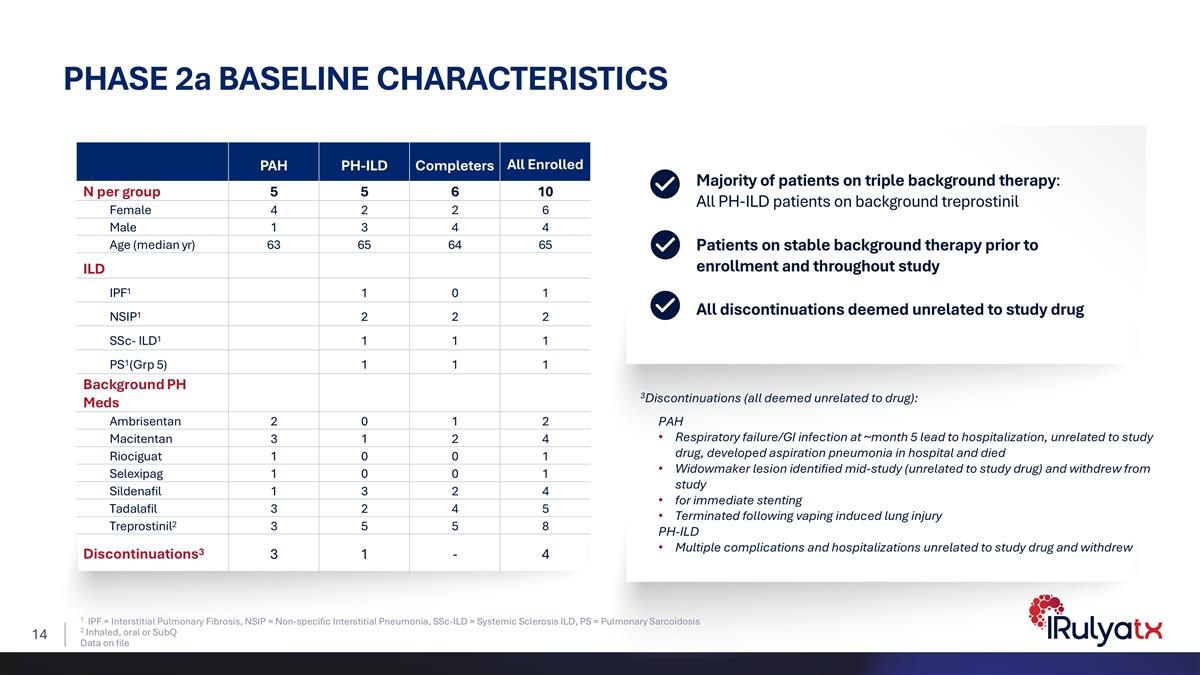
1 IPF = Interstitial Pulmonary Fibrosis, NSIP = Non-specific Interstitial Pneumonia, SSc-ILD = Systemic Sclerosis ILD, PS = Pulmonary Sarcoidosis 2 Inhaled, oral or SubQ Data on file PHASE 2a BASELINE CHARACTERISTICS PAH PH-ILD Completers All Enrolled N per group 5 5 6 10 Female 4 2 2 6 Male 1 3 4 4 Age (median yr) 63 65 64 65 ILD IPF1 1 0 1 NSIP1 2 2 2 SSc- ILD1 1 1 1 PS1(Grp 5) 1 1 1 Background PH Meds Ambrisentan 2 0 1 2 Macitentan 3 1 2 4 Riociguat 1 0 0 1 Selexipag 1 0 0 1 Sildenafil 1 3 2 4 Tadalafil 3 2 4 5 Treprostinil2 3 5 5 8 Discontinuations3 3 1 - 4 Majority of patients on triple background therapy: All PH-ILD patients on background treprostinil Patients on stable background therapy prior to enrollment and throughout study All discontinuations deemed unrelated to study drug 3Discontinuations (all deemed unrelated to drug): PAH Respiratory failure/GI infection at ~month 5 lead to hospitalization, unrelated to study drug, developed aspiration pneumonia in hospital and died Widowmaker lesion identified mid-study (unrelated to study drug) and withdrew from study for immediate stenting Terminated following vaping induced lung injury PH-ILD Multiple complications and hospitalizations unrelated to study drug and withdrew
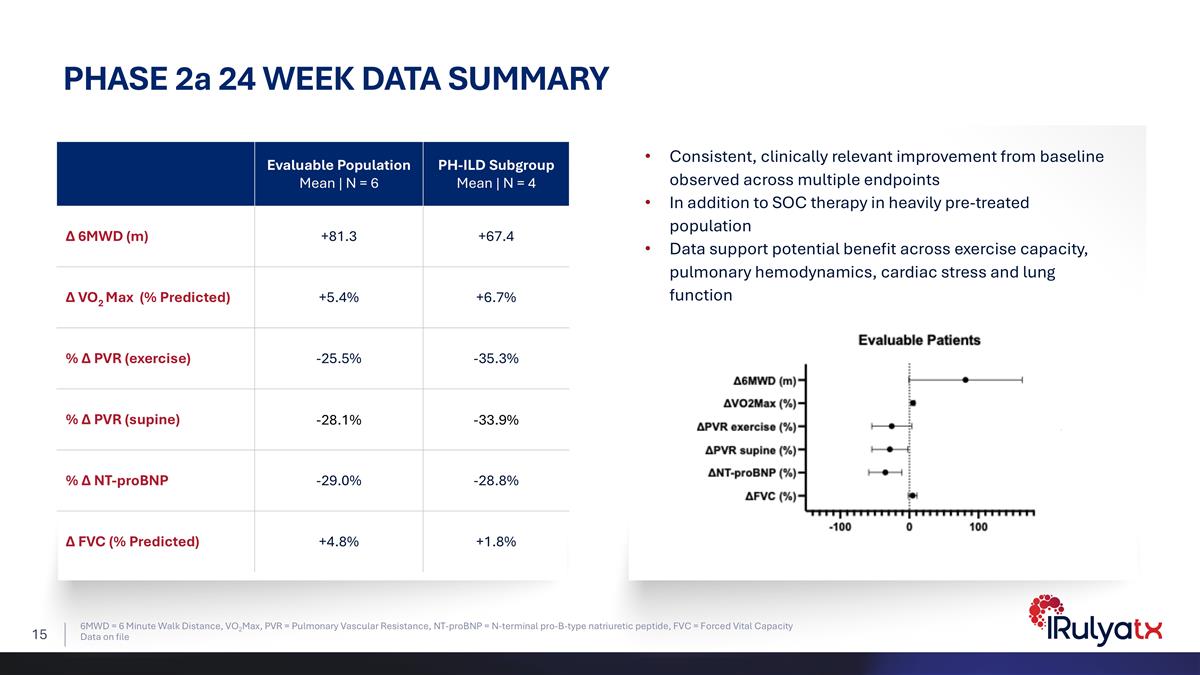
Consistent, clinically relevant improvement from baseline observed across multiple endpoints In addition to SOC therapy in heavily pre-treated population Data support potential benefit across exercise capacity, pulmonary hemodynamics, cardiac stress and lung function 6MWD = 6 Minute Walk Distance, VO2Max, PVR = Pulmonary Vascular Resistance, NT-proBNP = N-terminal pro-B-type natriuretic peptide, FVC = Forced Vital Capacity Data on file PHASE 2a 24 WEEK DATA SUMMARY Evaluable Population Mean | N = 6 PH-ILD Subgroup Mean | N = 4 Δ 6MWD (m) +81.3 +67.4 Δ VO2 Max (% Predicted) +5.4% +6.7% % Δ PVR (exercise) -25.5% -35.3% % Δ PVR (supine) -28.1% -33.9% % Δ NT-proBNP -29.0% -28.8% Δ FVC (% Predicted) +4.8% +1.8%
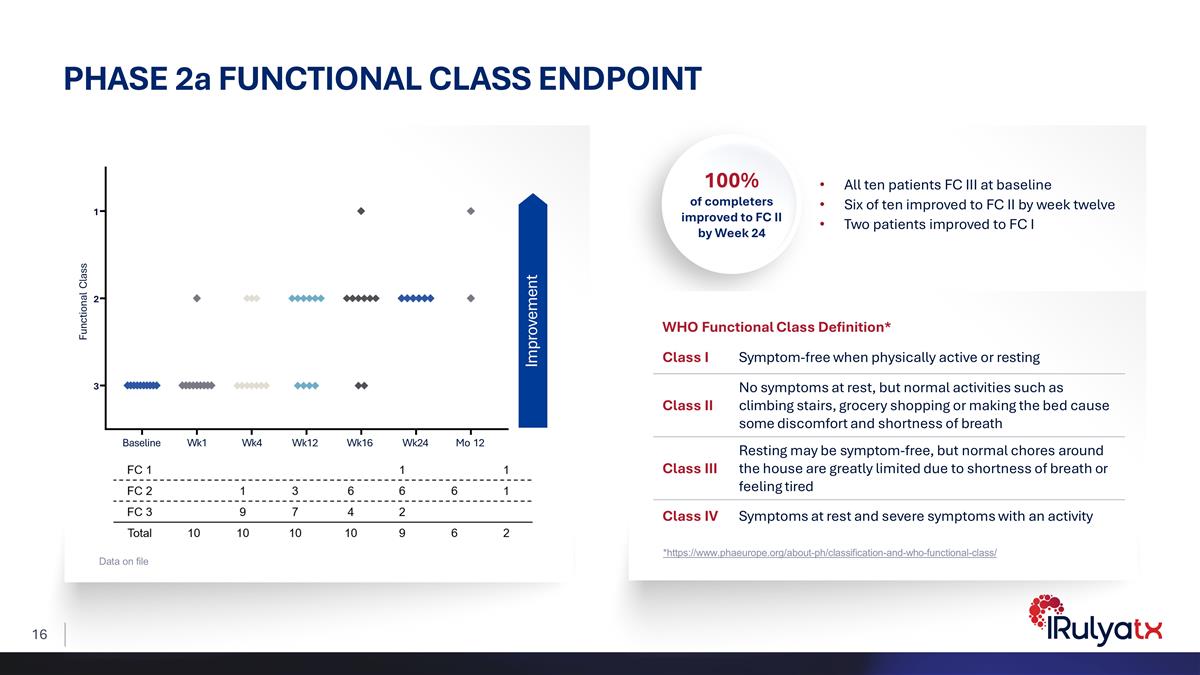
Data on file PHASE 2a FUNCTIONAL CLASS ENDPOINT All ten patients FC III at baseline Six of ten improved to FC II by week twelve Two patients improved to FC I Baseline Wk1 Wk4 Wk12 Wk16 Wk24 Mo 12 1 2 3 Functional Class Improvement 100% of completers improved to FC II by Week 24 WHO Functional Class Definition* Class I Symptom-free when physically active or resting Class II No symptoms at rest, but normal activities such as climbing stairs, grocery shopping or making the bed cause some discomfort and shortness of breath Class III Resting may be symptom-free, but normal chores around the house are greatly limited due to shortness of breath or feeling tired Class IV Symptoms at rest and severe symptoms with an activity *https://www.phaeurope.org/about-ph/classification-and-who-functional-class/

AEs = Adverse Events, SAEs = Serious Adverse Event Data on file SAFETY SUMMARY THROUGH 24-WEEKS DRUG RELATED AEs Grade 1 Productive Cough (n = 1) - Resolving Grade 2 Cough (n = 1) - Not Resolved Grade 1 Gingivitis (n = 1) - Resolving NO DOSE INTERRUPTIONS DUE TO AEs NO DISCONTINUATIONS DUE TO DRUG NO DRUG- RELATED SAEs LAM-001 WAS WELL TOLERATED

1Compared to +31.1m placebo adj. improvement in the Tyvaso INCREASE Phase 3 study: Waxman 2021 DOI: 10.1056/NEJMoa2008470 No head-to-head clinical trials have been conducted evaluating LAM-001 and Tyvaso. Differences exist between study or trial designs and participant characteristics, and caution should be exercised when comparing data across studies PHASE 2a EFFICACY AND SAFETY SUMMARY LAM-001 well tolerated No dose interruptions due to AE No discontinuations due to drug No drug related SAE Drug related AEs N = 2 cough (Grade 1, 2) N = 1 gingivitis (Grade 1) COMPELLING CLINICAL ACTIVITY FAVORABLE TOLERABILITY PH-ILD patients +67m improvement observed in 6MWD compares favorably to existing therapies1 Benefit seen on top of standard of care in heavily pretreated population Consistent signals of patient benefit seen across multiple measures
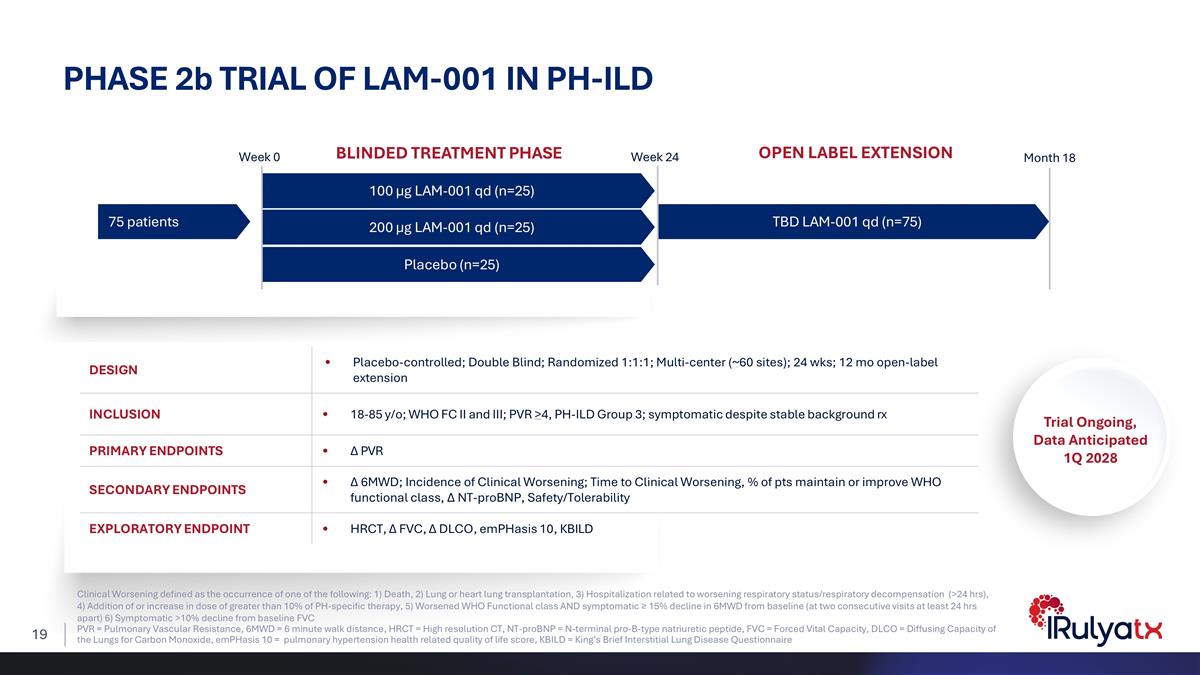
Clinical Worsening defined as the occurrence of one of the following: 1) Death, 2) Lung or heart lung transplantation, 3) Hospitalization related to worsening respiratory status/respiratory decompensation (>24 hrs), 4) Addition of or increase in dose of greater than 10% of PH-specific therapy, 5) Worsened WHO Functional class AND symptomatic ≥ 15% decline in 6MWD from baseline (at two consecutive visits at least 24 hrs apart) 6) Symptomatic >10% decline from baseline FVC PVR = Pulmonary Vascular Resistance, 6MWD = 6 minute walk distance, HRCT = High resolution CT, NT-proBNP = N-terminal pro-B-type natriuretic peptide, FVC = Forced Vital Capacity, DLCO = Diffusing Capacity of the Lungs for Carbon Monoxide, emPHasis 10 = pulmonary hypertension health related quality of life score, KBILD = King’s Brief Interstitial Lung Disease Questionnaire PHASE 2b TRIAL OF LAM-001 IN PH-ILD Trial Ongoing, Data Anticipated 1Q 2028 100 µg LAM-001 qd (n=25) 200 µg LAM-001 qd (n=25) Placebo (n=25) TBD LAM-001 qd (n=75) 75 patients Month 18 BLINDED TREATMENT PHASE Week 0 OPEN LABEL EXTENSION Week 24 DESIGN Placebo-controlled; Double Blind; Randomized 1:1:1; Multi-center (~60 sites); 24 wks; 12 mo open-label extension INCLUSION 18-85 y/o; WHO FC II and III; PVR >4, PH-ILD Group 3; symptomatic despite stable background rx PRIMARY ENDPOINTS Δ PVR SECONDARY ENDPOINTS Δ 6MWD; Incidence of Clinical Worsening; Time to Clinical Worsening, % of pts maintain or improve WHO functional class, Δ NT-proBNP, Safety/Tolerability EXPLORATORY ENDPOINT HRCT, Δ FVC, Δ DLCO, emPHasis 10, KBILD

LAM-001: BRONCHIOLITIS OBLITERANS (BOS)
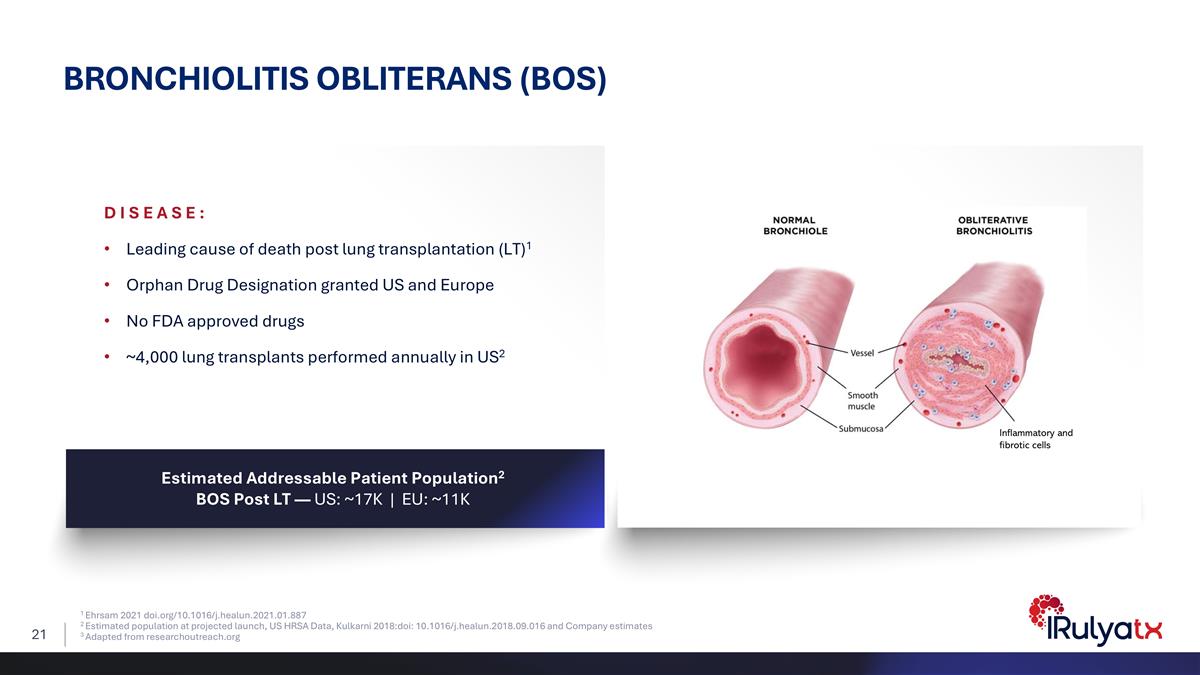
1 Ehrsam 2021 doi.org/10.1016/j.healun.2021.01.887 2 Estimated population at projected launch, US HRSA Data, Kulkarni 2018:doi: 10.1016/j.healun.2018.09.016 and Company estimates 3 Adapted from researchoutreach.org BRONCHIOLITIS OBLITERANS (BOS) BOS = Bronchiolitis Obliterans Syndrome3 Estimated Addressable Patient Population2 BOS Post LT — US: ~17K | EU: ~11K DISEASE: Leading cause of death post lung transplantation (LT)1 Orphan Drug Designation granted US and Europe No FDA approved drugs ~4,000 lung transplants performed annually in US2 Inflammatory and fibrotic cells Estimated Addressable Patient Population2 BOS Post LT — US: ~17K | EU: ~11K

BOS MAJOR UNMET NEED 11% BOS free survival at 10 yrs2 Median survival (or re-transplantation) post development of BOS post lung transplantation4 Median survival post lung transplantation1 BOS is the leading cause of death post lung transplantation3 6.2 YEARS #1 2.5 YEARS 1ISHLT Factsheet: https://www.ishlt.org/docs/default-source/default-document-library/ishlt_fast-facts.pdf Accessed 7/6/26 2Kulkarni 2018 https://doi.org/10.1016/j.healun.2018.09.016 3Ehrsam 2021 doi.org/10.1016/j.healun.2021.01.887 4Copeland 2010 doi: 10.1164/rccm.201002-0211OC
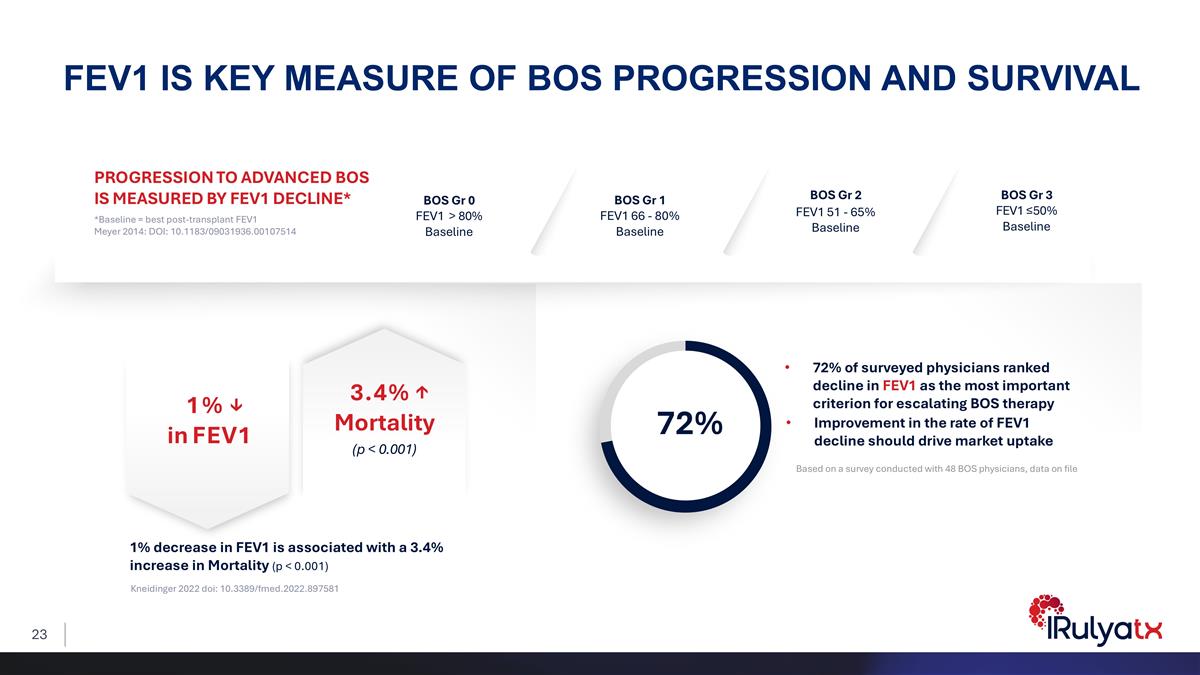
72% FEV1 IS KEY MEASURE OF BOS PROGRESSION AND SURVIVAL *Baseline = best post-transplant FEV1 Meyer 2014: DOI: 10.1183/09031936.00107514 Kneidinger 2022 doi: 10.3389/fmed.2022.897581 PROGRESSION TO ADVANCED BOS IS MEASURED BY FEV1 DECLINE* 1% decrease in FEV1 is associated with a 3.4% increase in Mortality (p < 0.001) 72% of surveyed physicians ranked decline in FEV1 as the most important criterion for escalating BOS therapy Improvement in the rate of FEV1 decline should drive market uptake Based on a survey conducted with 48 BOS physicians, data on file BOS Gr 1 FEV1 66 - 80% Baseline BOS Gr 0 FEV1 > 80% Baseline BOS Gr 2 FEV1 51 - 65% Baseline BOS Gr 3 FEV1 ≤50% Baseline 1% ↓ in FEV1 3.4% ↑ Mortality (p < 0.001)
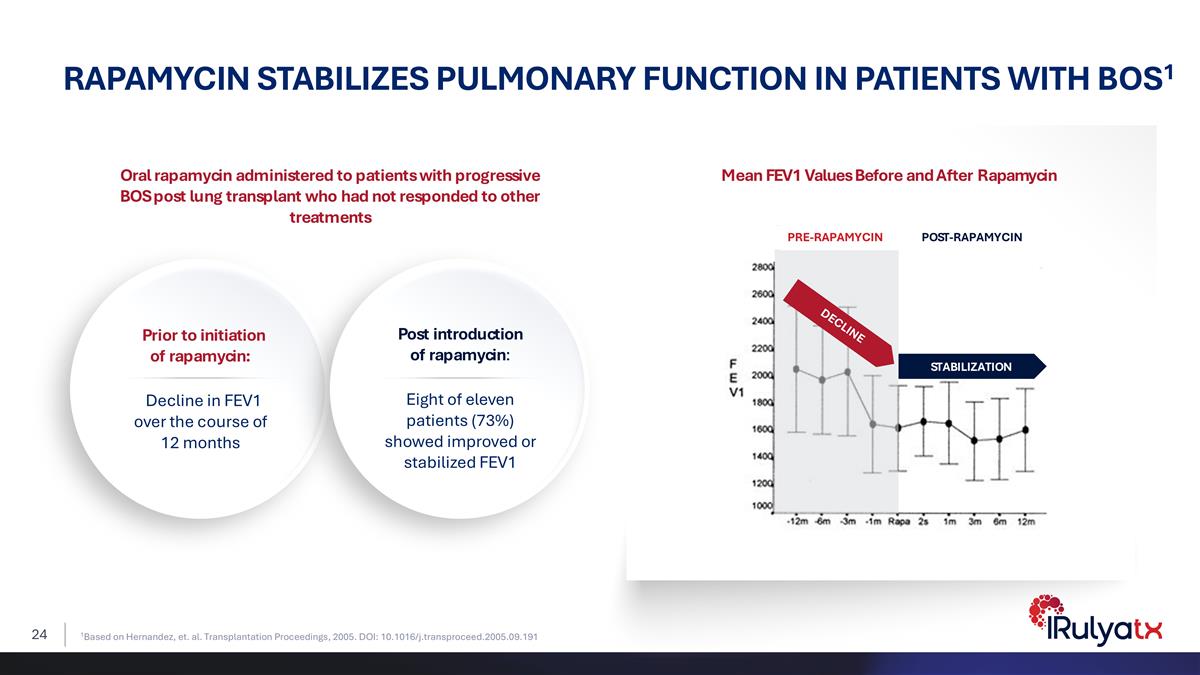
Oral rapamycin administered to patients with progressive BOS post lung transplant who had not responded to other treatments Mean FEV1 Values Before and After Rapamycin 1Based on Hernandez, et. al. Transplantation Proceedings, 2005. DOI: 10.1016/j.transproceed.2005.09.191 RAPAMYCIN STABILIZES PULMONARY FUNCTION IN PATIENTS WITH BOS1 PRE-RAPAMYCIN POST-RAPAMYCIN Prior to initiation of rapamycin: Decline in FEV1 over the course of 12 months Post introduction of rapamycin: Eight of eleven patients (73%) showed improved or stabilized FEV1 STABILIZATION DECLINE

DESIGN Randomized 1:1, Double Blind, Placebo controlled, 25 mo open-label extension, Investigator-initiated trial INCLUSION >18 yo; Newly diagnosed BOS (FEV1 51-85% of baseline, ≤ 12 mo from BOS diagnosis); ≥ 12 mo post Double lung transplant PRIMARY ENDPOINTS % Δ in FEV1 @ 48 wks (or at termination of therapy, whichever occurs first) SECONDARY ENDPOINTS Absolute Δ in FEV1 @ 48 wks*, Δ rate of progression in FEV1 @ 48 wks* vs pre-enrollment, PFS Level 1 (time to earliest to occur of: >10% decline in FEV1, death from respiratory failure or re-transplantation), Safety/Tolerability EXPLORATORY ENDPOINT 6MWD @ 48 wks*, PFS Level 2 (time to earliest to occur of: >20% decline in FEV1,death from respiratory failure or re-transplantation), Δ FEV1/FVC @ 48 wks*, SGRQ-C, PK, CLAD signature gene profiling @ 3 mo, mTOR pathway activation via BAL STATUS** Enrollment completed January 2026. An interim safety review was conducted in February 2026. Five of 19 subjects enrolled in the ongoing blinded study experienced a decline*** in FEV1 >10% at that time. Dosing continues. TRIAL FULLY ENROLLED, DATA ANTICIPATED 1Q 2027 100 µg LAM-001 qd Placebo 19 patients *Measured at 48 wks or at termination or treatment, whichever occurs first ** The interim clinical data presented herein are derived from an ongoing blinded study. Because the study remains blinded, the Company is unable to determine which patients received LAM-001 versus placebo. These interim data are preliminary, should be interpreted with caution, and are not indicative of the final results of the study. No conclusions regarding the efficacy or safety of LAM-001 should be drawn from these interim results. The actual results following unblinding may differ materially from the interim data presented herein. *** As measured in two consecutive visits FEV1 = Forced Expiratory Volume in 1 Second, PFS = Progression Free Survival, FVC = Forced Vital Capacity, SGRQ-C = St. George’s Respiratory Quesitonnaire, COPD, BAL = Bronchioalveolar Lavage PHASE 2 TRIAL OF LAM-001 IN BOS 100 µg LAM-001 qd Month 36 OPEN LABEL EXTENSION BLINDED TREATMENT PHASE Week 0 Week 48

LAM-001: SARCOIDOSIS ASSOCIATED PULMONARY HYPERTENSION (SAPH)
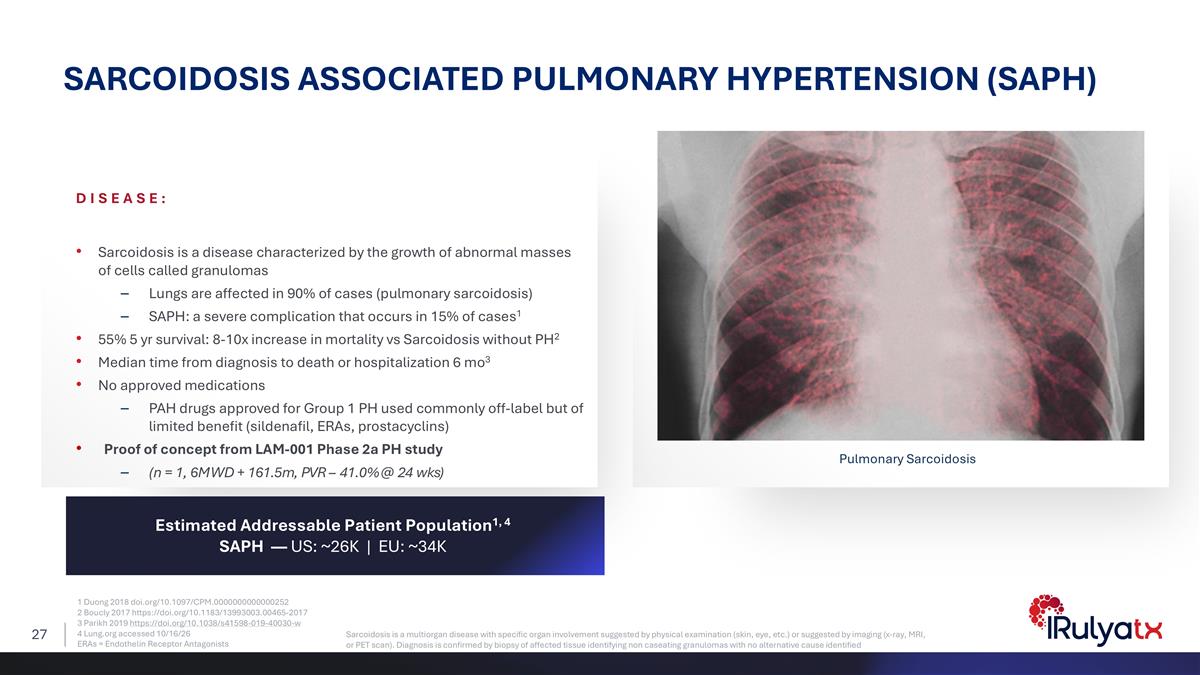
SARCOIDOSIS ASSOCIATED PULMONARY HYPERTENSION (SAPH) Pulmonary Sarcoidosis DISEASE: Sarcoidosis is a disease characterized by the growth of abnormal masses of cells called granulomas Lungs are affected in 90% of cases (pulmonary sarcoidosis) SAPH: a severe complication that occurs in 15% of cases1 55% 5 yr survival: 8-10x increase in mortality vs Sarcoidosis without PH2 Median time from diagnosis to death or hospitalization 6 mo3 No approved medications PAH drugs approved for Group 1 PH used commonly off-label but of limited benefit (sildenafil, ERAs, prostacyclins) Proof of concept from LAM-001 Phase 2a PH study (n = 1, 6MWD + 161.5m, PVR – 41.0% @ 24 wks) 1 Duong 2018 doi.org/10.1097/CPM.0000000000000252 2 Boucly 2017 https://doi.org/10.1183/13993003.00465-2017 3 Parikh 2019 https://doi.org/10.1038/s41598-019-40030-w 4 Lung.org accessed 10/16/26 ERAs = Endothelin Receptor Antagonists Sarcoidosis is a multiorgan disease with specific organ involvement suggested by physical examination (skin, eye, etc.) or suggested by imaging (x-ray, MRI, or PET scan). Diagnosis is confirmed by biopsy of affected tissue identifying non caseating granulomas with no alternative cause identified Estimated Addressable Patient Population1, 4 SAPH — US: ~26K | EU: ~34K
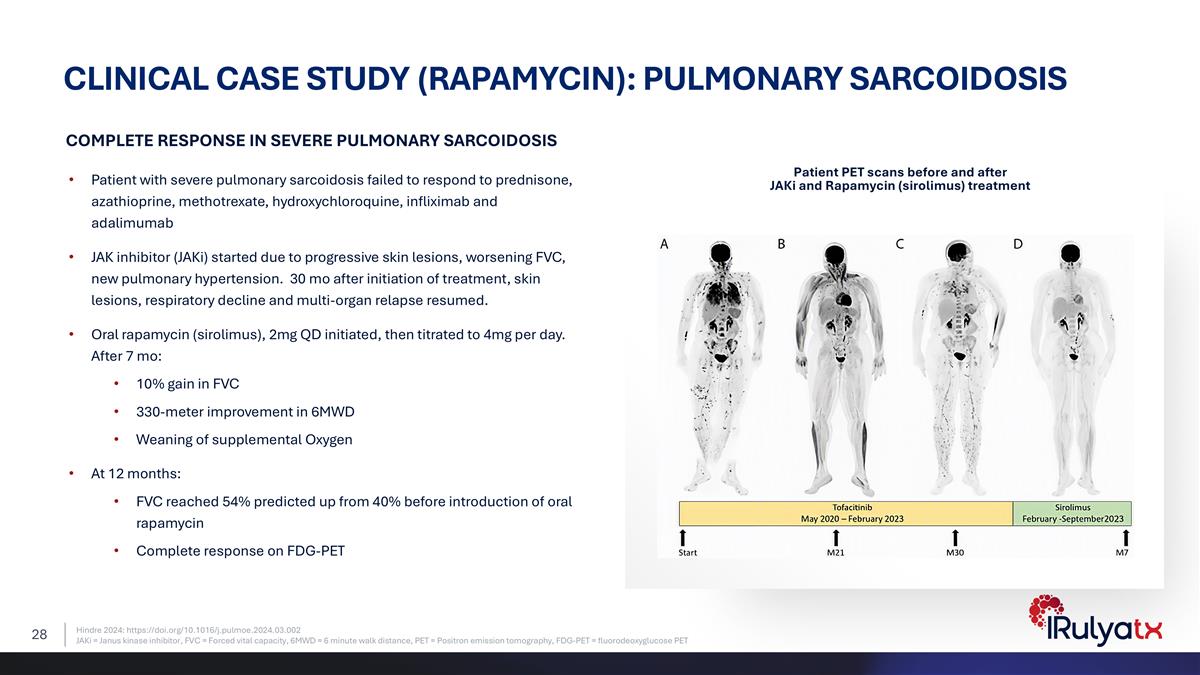
Patient PET scans before and after JAKi and Rapamycin (sirolimus) treatment Clinical Case Study (Rapamycin): Pulmonary Sarcoidosis Patient with severe pulmonary sarcoidosis failed to respond to prednisone, azathioprine, methotrexate, hydroxychloroquine, infliximab and adalimumab JAK inhibitor (JAKi) started due to progressive skin lesions, worsening FVC, new pulmonary hypertension. 30 mo after initiation of treatment, skin lesions, respiratory decline and multi-organ relapse resumed. Oral rapamycin (sirolimus), 2mg QD initiated, then titrated to 4mg per day. After 7 mo: 10% gain in FVC 330-meter improvement in 6MWD Weaning of supplemental Oxygen At 12 months: FVC reached 54% predicted up from 40% before introduction of oral rapamycin Complete response on FDG-PET Hindre 2024: https://doi.org/10.1016/j.pulmoe.2024.03.002 JAKi = Janus kinase inhibitor, FVC = Forced vital capacity, 6MWD = 6 minute walk distance, PET = Positron emission tomography, FDG-PET = fluorodeoxyglucose PET Complete Response in Severe Pulmonary Sarcoidosis
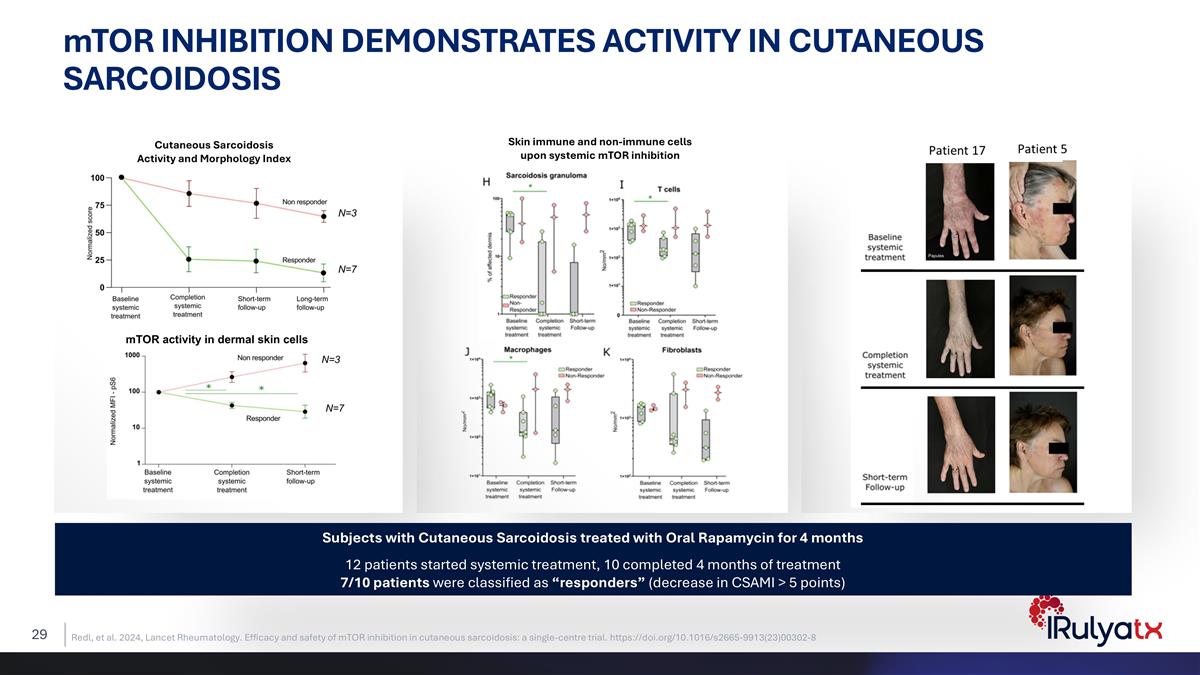
mTOR Inhibition Demonstrates Activity in Cutaneous Sarcoidosis N=3 N=7 N=3 N=7 Cutaneous Sarcoidosis Activity and Morphology Index mTOR activity in dermal skin cells Skin immune and non-immune cells upon systemic mTOR inhibition Subjects with Cutaneous Sarcoidosis treated with Oral Rapamycin for 4 months 12 patients started systemic treatment, 10 completed 4 months of treatment 7/10 patients were classified as “responders” (decrease in CSAMI > 5 points) Redl, et al. 2024, Lancet Rheumatology. Efficacy and safety of mTOR inhibition in cutaneous sarcoidosis: a single-centre trial. https://doi.org/10.1016/s2665-9913(23)00302-8
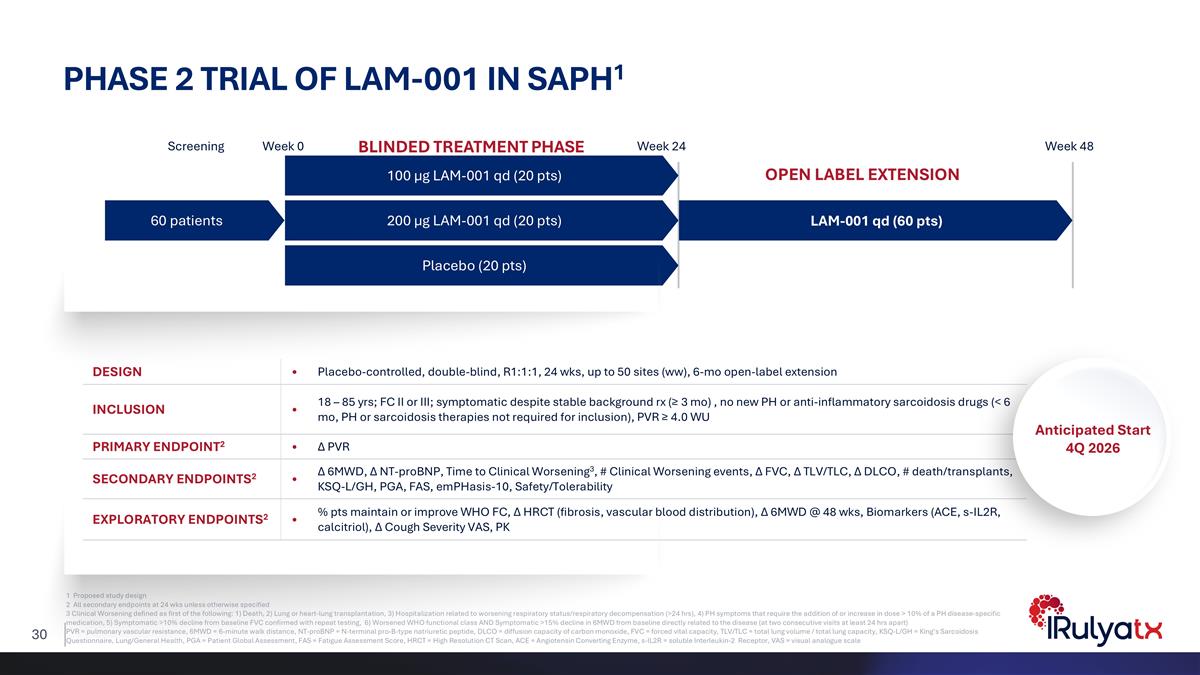
PHASE 2 TRIAL OF LAM-001 IN SAPH1 60 patients 100 µg LAM-001 qd (20 pts) 200 µg LAM-001 qd (20 pts) Placebo (20 pts) LAM-001 qd (60 pts) Screening Week 0 Week 24 Week 48 BLINDED TREATMENT PHASE OPEN LABEL EXTENSION 1 Proposed study design 2 All secondary endpoints at 24 wks unless otherwise specified 3 Clinical Worsening defined as first of the following: 1) Death, 2) Lung or heart-lung transplantation, 3) Hospitalization related to worsening respiratory status/respiratory decompensation (>24 hrs), 4) PH symptoms that require the addition of or increase in dose > 10% of a PH disease-specific medication, 5) Symptomatic >10% decline from baseline FVC confirmed with repeat testing, 6) Worsened WHO functional class AND Symptomatic >15% decline in 6MWD from baseline directly related to the disease (at two consecutive visits at least 24 hrs apart) PVR = pulmonary vascular resistance, 6MWD = 6-minute walk distance, NT-proBNP = N-terminal pro-B-type natriuretic peptide, DLCO = diffusion capacity of carbon monoxide, FVC = forced vital capacity, TLV/TLC = total lung volume / total lung capacity, KSQ-L/GH = King’s Sarcoidosis Questionnaire, Lung/General Health, PGA = Patient Global Assessment, FAS = Fatigue Assessment Score, HRCT = High Resolution CT Scan, ACE = Angiotensin Converting Enzyme, s-IL2R = soluble Interleukin-2 Receptor, VAS = visual analogue scale DESIGN • Placebo-controlled, double-blind, R1:1:1, 24 wks, up to 50 sites (ww), 6-mo open-label extension INCLUSION • 18 – 85 yrs; FC II or III; symptomatic despite stable background rx (≥ 3 mo) , no new PH or anti-inflammatory sarcoidosis drugs (< 6 mo, PH or sarcoidosis therapies not required for inclusion), PVR ≥ 4.0 WU PRIMARY ENDPOINT2 • Δ PVR SECONDARY ENDPOINTS2 • Δ 6MWD, Δ NT-proBNP, Time to Clinical Worsening3, # Clinical Worsening events, Δ FVC, Δ TLV/TLC, Δ DLCO, # death/transplants, KSQ-L/GH, PGA, FAS, emPHasis-10, Safety/Tolerability EXPLORATORY ENDPOINTS2 • % pts maintain or improve WHO FC, Δ HRCT (fibrosis, vascular blood distribution), Δ 6MWD @ 48 wks, Biomarkers (ACE, s-IL2R, calcitriol), Δ Cough Severity VAS, PK Anticipated Start 4Q 2026

IP, FINANCIAL, & MILESTONES

* Australia, Canada, Europe, Hong Kong, Israel, Japan, Mexico, New Zealand and South Korea. BROAD IP STRATEGY SUPPORTING LAM-001 EXCLUSIVITY FDA ORANGE BOOK AFFORDS PROTECTION FOR 3 TYPES OF PATENTS METHOD CLAIMS Method of Treatment (MoT) Use of composition Defined dosing regimens Specific indications 9 US AND 25 INTERNATIONAL PATENTS ISSUED* – EXPECTED EXCLUSIVITY INTO 2035 Pharmaceutical compositions on DPI formulation Methods of treating PH and chronic lung disease Pending Applications – Expected Exclusivity Into 2047 ORPHAN DRUG EXCLUSIVITY IN ADDITION TO PATENTS | 7 YEARS US / 10 YEARS EU MULTIFACETED IP AND EXCLUSIVITY STRATEGY Broad claims in all 3 categories Drug substance, drug product, and method Multiple patents expected to be Orange Book-listable Device exclusivity for the use of rapamycin in the RS01 dry powder inhaler device COMPOSITION CLAIMS Drug Substance (DS) Particle size Drug Product (DP) Formulation Delivery Dosage

\ WELL-CAPITALIZED WITH FUNDING FROM LEADING HEALTHCARE INVESTORS OVERSUBSCRIBED $115M UPFRONT FINANCING LED BY INCLUDING MAY 2026 FINANCING

ANTICIPATED MILESTONES 1Q27 LAM-001 BOS Phase 2 Data 1Q28 LAM-001 PH-ILD Phase 2b Data 4Q28 LAM-001 SAPH Phase 2 Data

THANK YOU OCTOBER 2026