
LUCIA Phase 3 Clinical Trial DURAVYU in Wet AMD Topline Results | October 2026 Exhibit 99.2

Legal Disclaimers Various statements made in this presentation are forward-looking, within the meaning of the U.S. Private Securities Litigation Reform Act of 1995, and are inherently subject to risks, uncertainties and potentially inaccurate assumptions. All statements that address activities, events or developments that we intend, expect, plan or believe may occur in the future, are forward-looking statements, including but not limited to statements regarding: our expectations regarding our clinical development and regulatory plans; our plans to conduct additional analyses to assess the potential of DURAVYU as a treatment for wet AMD; our belief regarding DURAVYU’s potential mechanistic edge as only TKI combining VEGF receptor blockade, IL-6/JAK1 anti-inflammatory and PDGF antifibrotic benefit; our belief that our Phase 3 DME COMO and CAPRI trial designs position DURAVYU for clinical and global regulatory and commercial success; our expectations regarding the timing of the availability of DME clinical data, including topline results for clinical trials in DME in the fourth quarter of 2027; our belief that DURAVYU has the potential to maintain patients with active disease with no supplemental anti-VEGF therapy for six months or longer; and other statements regarding the Company’s future plans, objectives, strategies and beliefs, including the use of future dates. Forward-looking statements by their nature address matters that are, to different degrees, uncertain. Uncertainties and risks may cause EyePoint’s actual results to be materially different than those expressed in or implied by EyePoint’s forward-looking statements. For EyePoint, these risks and uncertainties include the timing, progress and results of the Company’s clinical development activities; uncertainties and delays relating to communications with the U.S. Food and Drug Administration and the ability to obtain regulatory approval from FDA for the commercialization of DURAVYU; unanticipated costs and expenses; the Company’s cash and cash equivalents may not be sufficient to support its operating plan for as long as anticipated; the risk that results of clinical trials may not be predictive of future results, and interim and preliminary data are subject to further analysis and may change as more data becomes available; unexpected safety or efficacy data observed during clinical trials; uncertainties related to the regulatory authorization or approval process, and available development and regulatory pathways for approval of the Company’s product candidates; changes in the regulatory environment; disruptions at the FDA; changes in U.S. and international trade policies; changes in expected or existing competition; the success of current and future license agreements; our dependence on contract research organizations, and other outside vendors and service providers; product liability; the impact of general business and economic conditions; protection of our intellectual property and avoiding intellectual property infringement; retention of key personnel; delays, interruptions or failures in the manufacture and supply of our product candidates, including due to unanticipated regulatory compliance issues or warning letters relating to the Company’s manufacturing facilities; the availability of and the need for additional financing; our ability to obtain additional funding to support our clinical development programs; uncertainties regarding the FDA warning letter pertaining to the Company’s Watertown, Massachusetts manufacturing facility; and other factors described in our filings with the Securities and Exchange Commission (SEC). More detailed information on these and additional factors that could affect our actual results are described in our filings with the SEC, including our Annual Report on Form 10-K for the fiscal year ended December 31, 2025, as revised or supplemented by our Quarterly Reports on Form 10-Q and other documents filed with the SEC. We cannot guarantee that the results and other expectations expressed, anticipated or implied in any forward-looking statement will be realized. A variety of factors, including these risks, could cause our actual results and other expectations to differ materially from the anticipated results or other expectations expressed, anticipated or implied in our forward-looking statements. Should known or unknown risks materialize, or should underlying assumptions prove inaccurate, actual results could differ materially from past results and those anticipated, estimated or projected in the forward-looking statements. You should bear this in mind as you consider any forward-looking statements. Our forward-looking statements speak only as of the dates on which they are made. EyePoint undertakes no obligation to update or revise any forward-looking statement, whether as a result of new information, future events, or otherwise.

Introduction
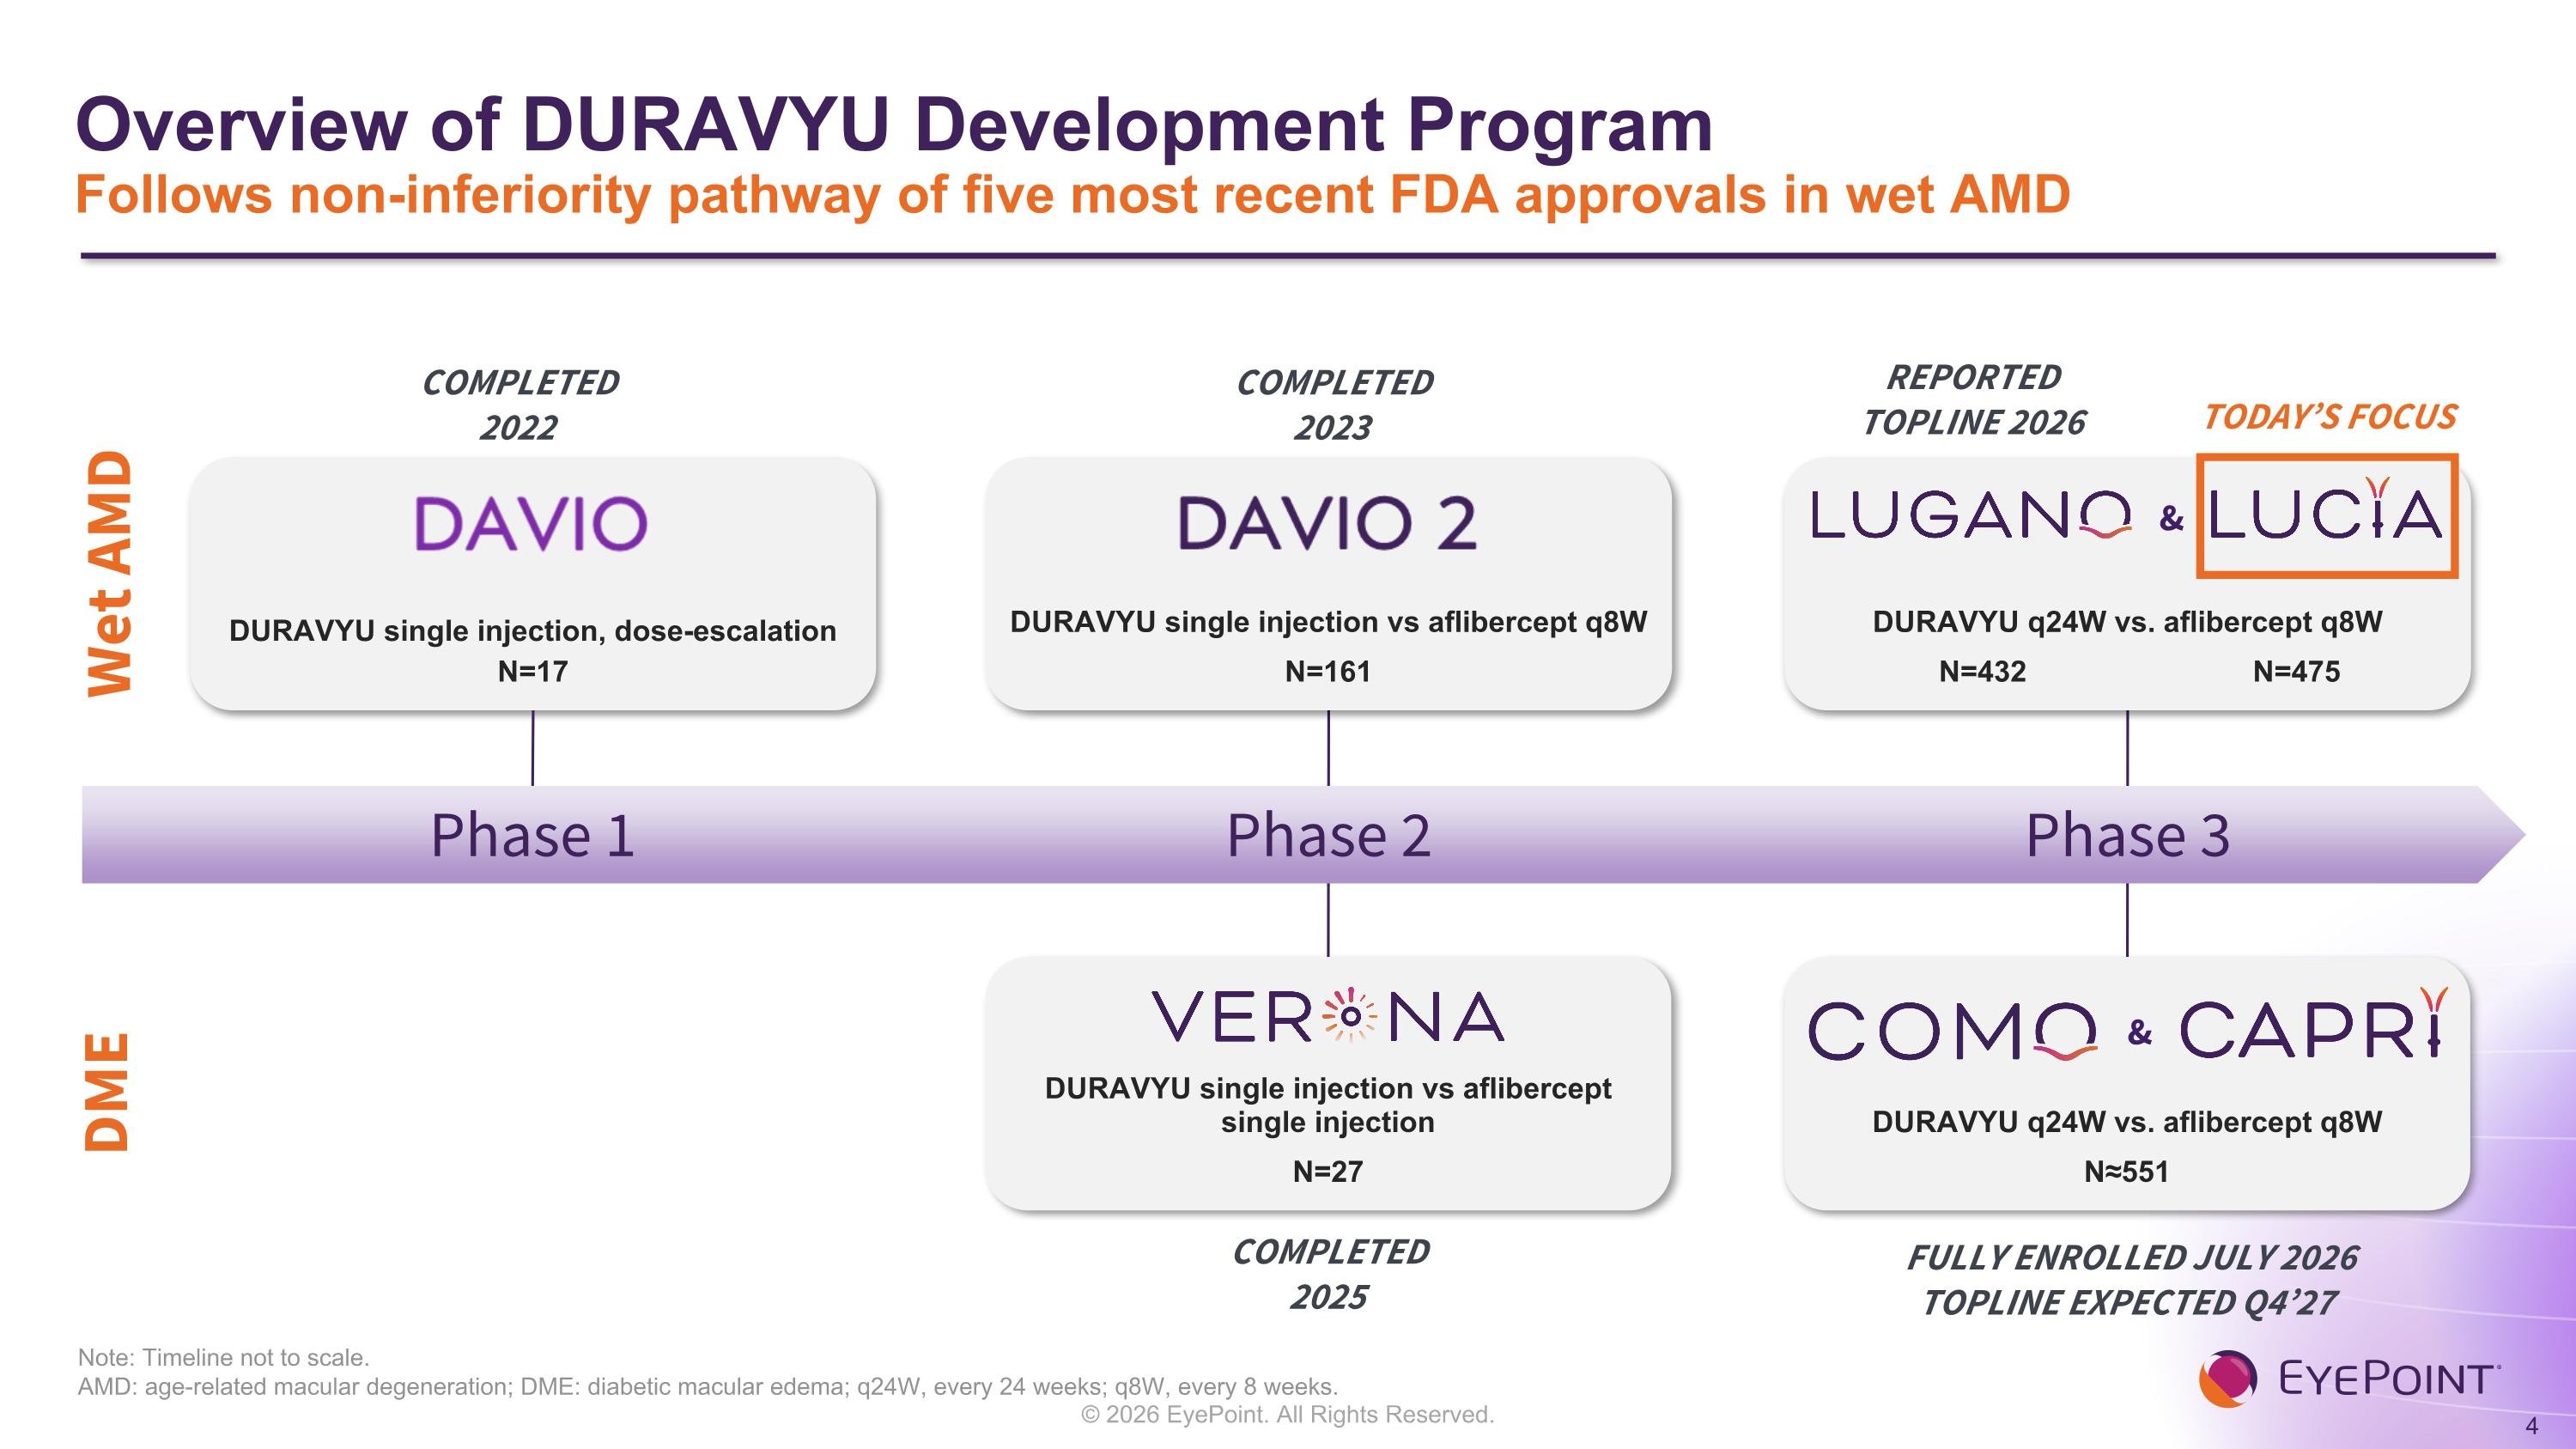
Overview of DURAVYU Development Program Follows non-inferiority pathway of five most recent FDA approvals in wet AMD Note: Timeline not to scale. AMD: age-related macular degeneration; DME: diabetic macular edema; q24W, every 24 weeks; q8W, every 8 weeks. Wet AMD DURAVYU single injection, dose-escalation N=17 Phase 1 COMPLETED 2022 DME Phase 2 COMPLETED 2023 COMPLETED 2025 DURAVYU single injection vs aflibercept single injection N=27 DURAVYU single injection vs aflibercept q8W N=161 Phase 3 FULLY ENROLLED JULY 2026 TOPLINE EXPECTED Q4’27 DURAVYU q24W vs. aflibercept q8W N≈551 & DURAVYU q24W vs. aflibercept q8W N=432 N=475 & REPORTED TOPLINE 2026 TODAY’S FOCUS
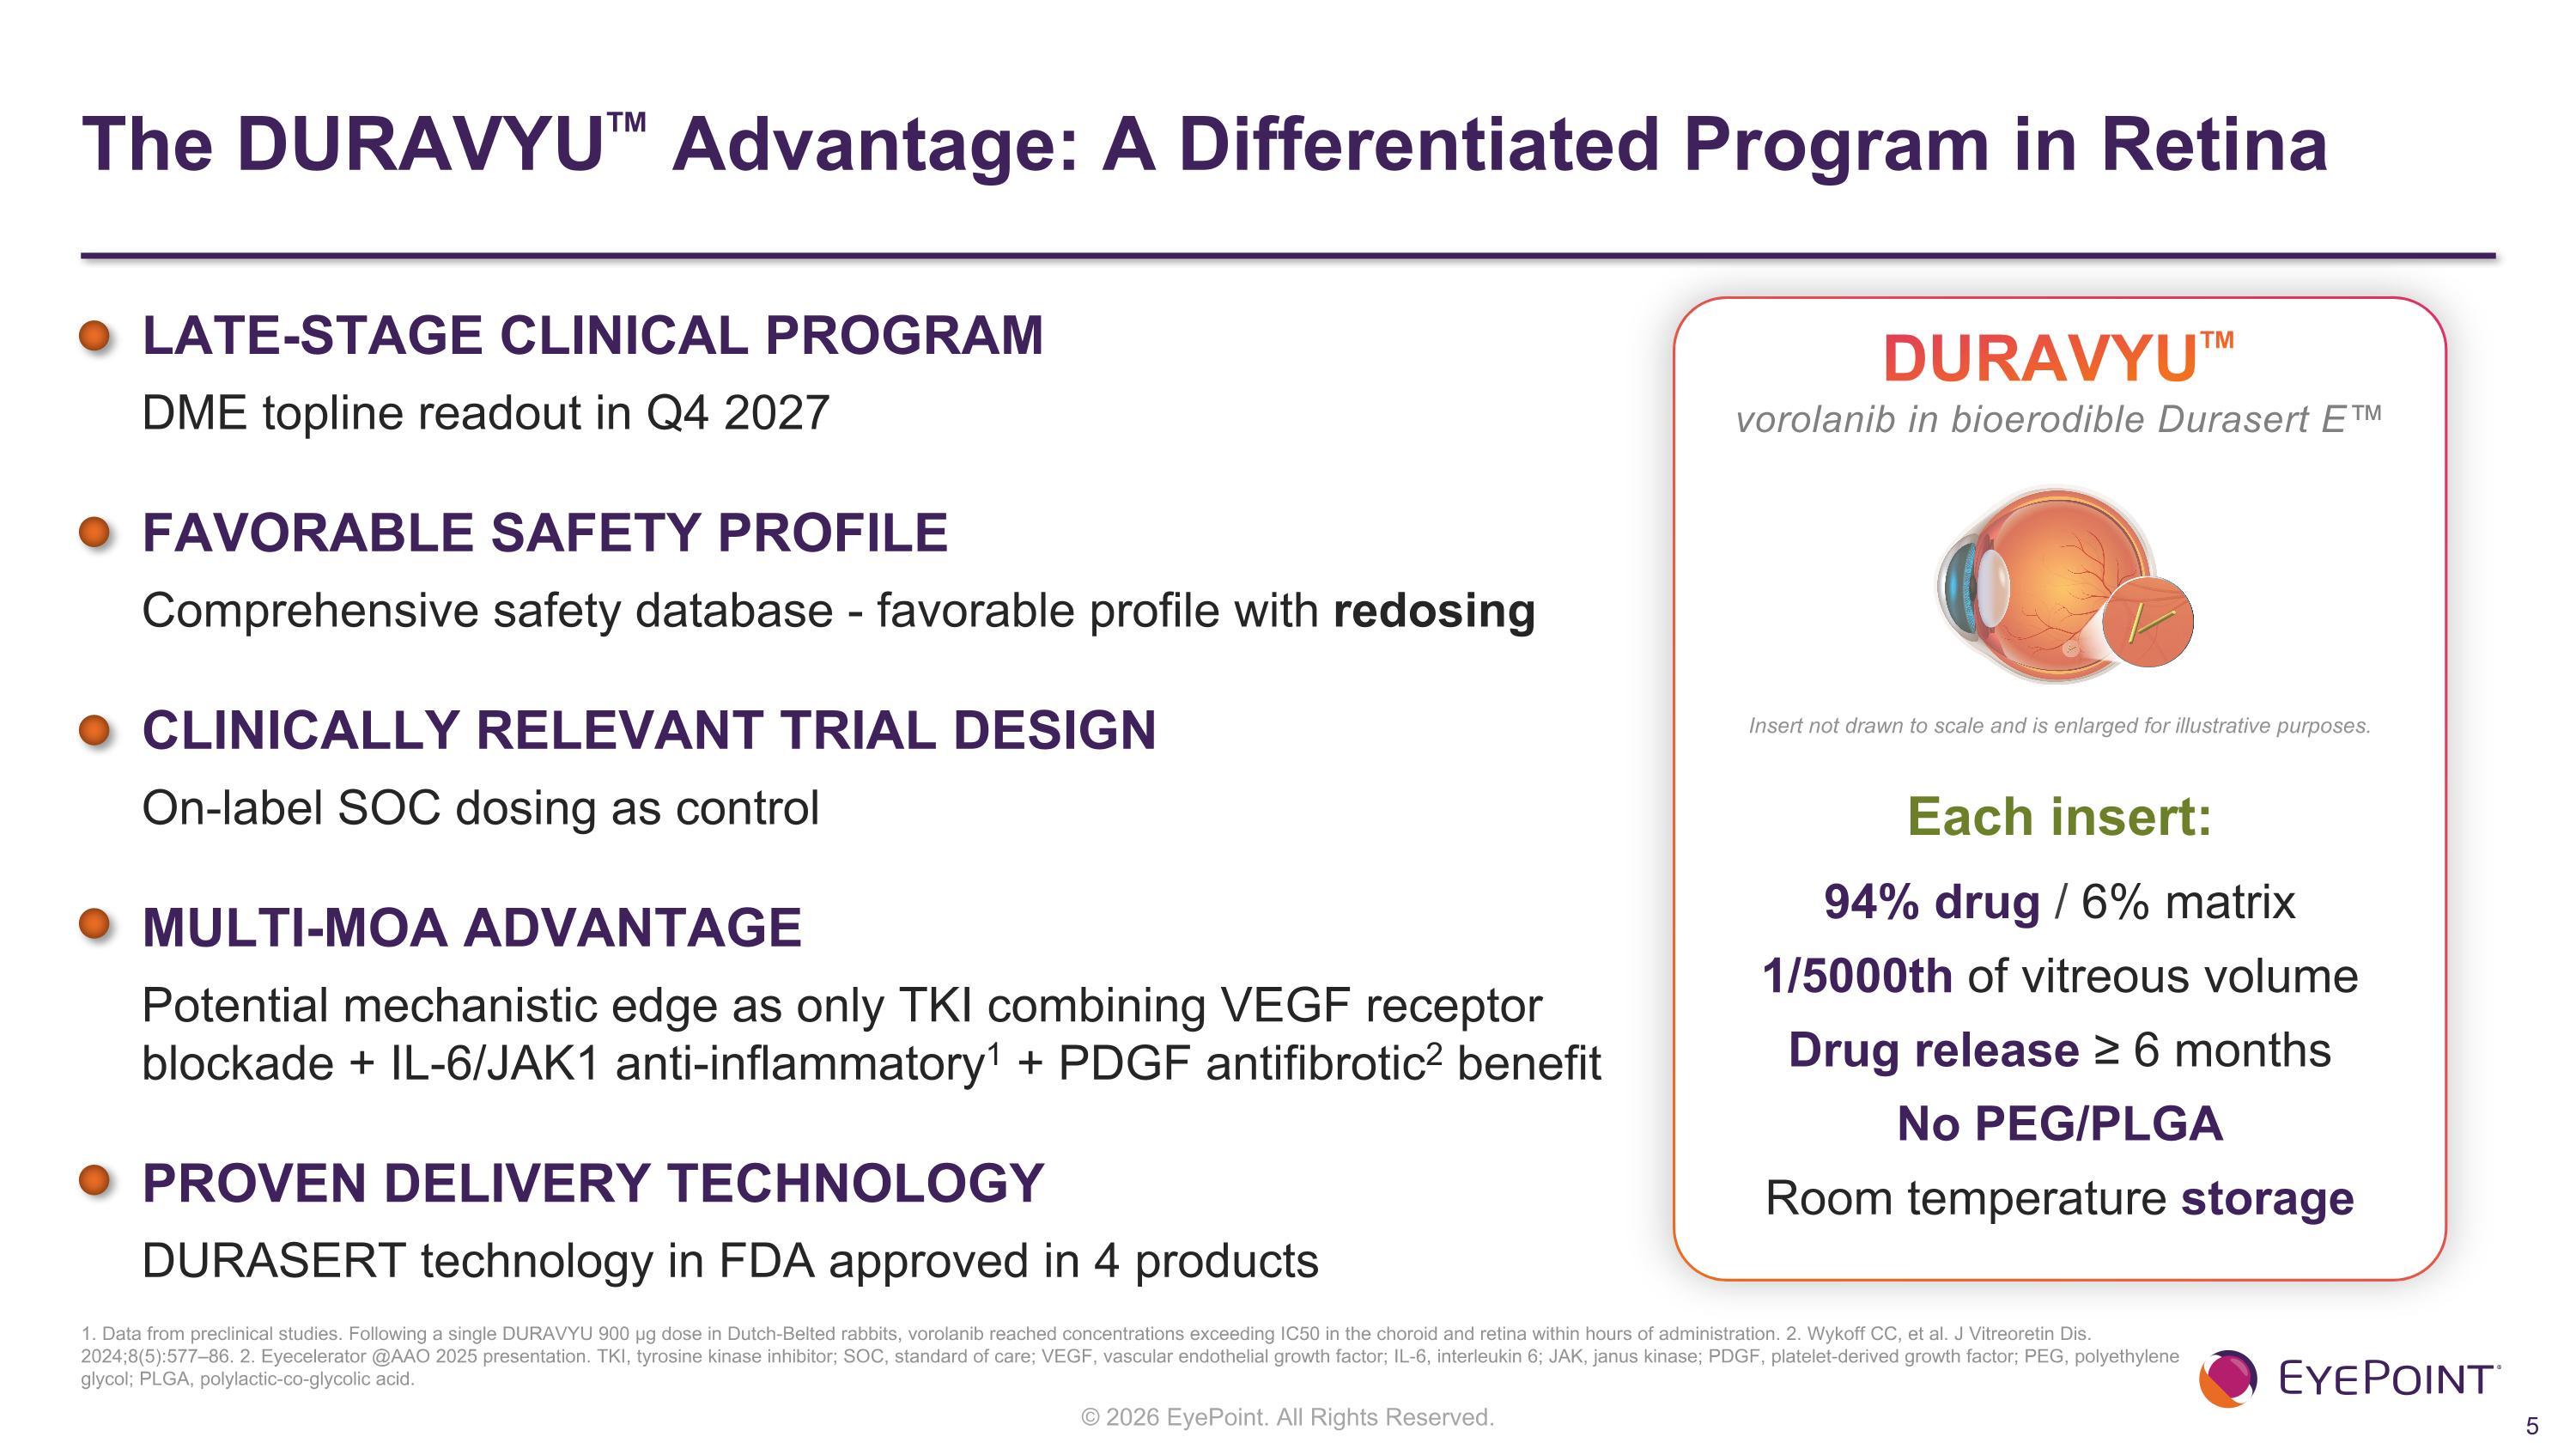
The DURAVYU™ Advantage: A Differentiated Program in Retina 1. Data from preclinical studies. Following a single DURAVYU 900 µg dose in Dutch-Belted rabbits, vorolanib reached concentrations exceeding IC50 in the choroid and retina within hours of administration. 2. Wykoff CC, et al. J Vitreoretin Dis. 2024;8(5):577–86. 2. Eyecelerator @AAO 2025 presentation. TKI, tyrosine kinase inhibitor; SOC, standard of care; VEGF, vascular endothelial growth factor; IL-6, interleukin 6; JAK, janus kinase; PDGF, platelet-derived growth factor; PEG, polyethylene glycol; PLGA, polylactic-co-glycolic acid. LATE-STAGE CLINICAL PROGRAM DME topline readout in Q4 2027 FAVORABLE SAFETY PROFILE Comprehensive safety database - favorable profile with redosing CLINICALLY RELEVANT TRIAL DESIGN On-label SOC dosing as control MULTI-MOA ADVANTAGE Potential mechanistic edge as only TKI combining VEGF receptor blockade + IL-6/JAK1 anti-inflammatory1 + PDGF antifibrotic2 benefit PROVEN DELIVERY TECHNOLOGY DURASERT technology in FDA approved in 4 products DURAVYU™ vorolanib in bioerodible Durasert E™ Each insert: 94% drug / 6% matrix 1/5000th of vitreous volume Drug release ≥ 6 months No PEG/PLGA Room temperature storage Insert not drawn to scale and is enlarged for illustrative purposes.
Summary AMD, age-related macular degeneration; Diabetic Macular Edema, DME. LUCIA did not meet primary endpoint of mean change in BCVA, despite visual improvement Meaningful reduction in treatment burden (nominal p-value <0.0001) with strong anatomic control demonstrates activity of DURAVYU Continued favorable safety profile with redosing Additional analyses ongoing to assess next steps for DURAVYU as a potential treatment for wet AMD Focused on DME program with ongoing, pivotal clinical trials (COMO & CAPRI) topline data readout expected in 4Q 2027

Phase 3 Wet AMD Program LUGANO and LUCIA Pivotal Trials
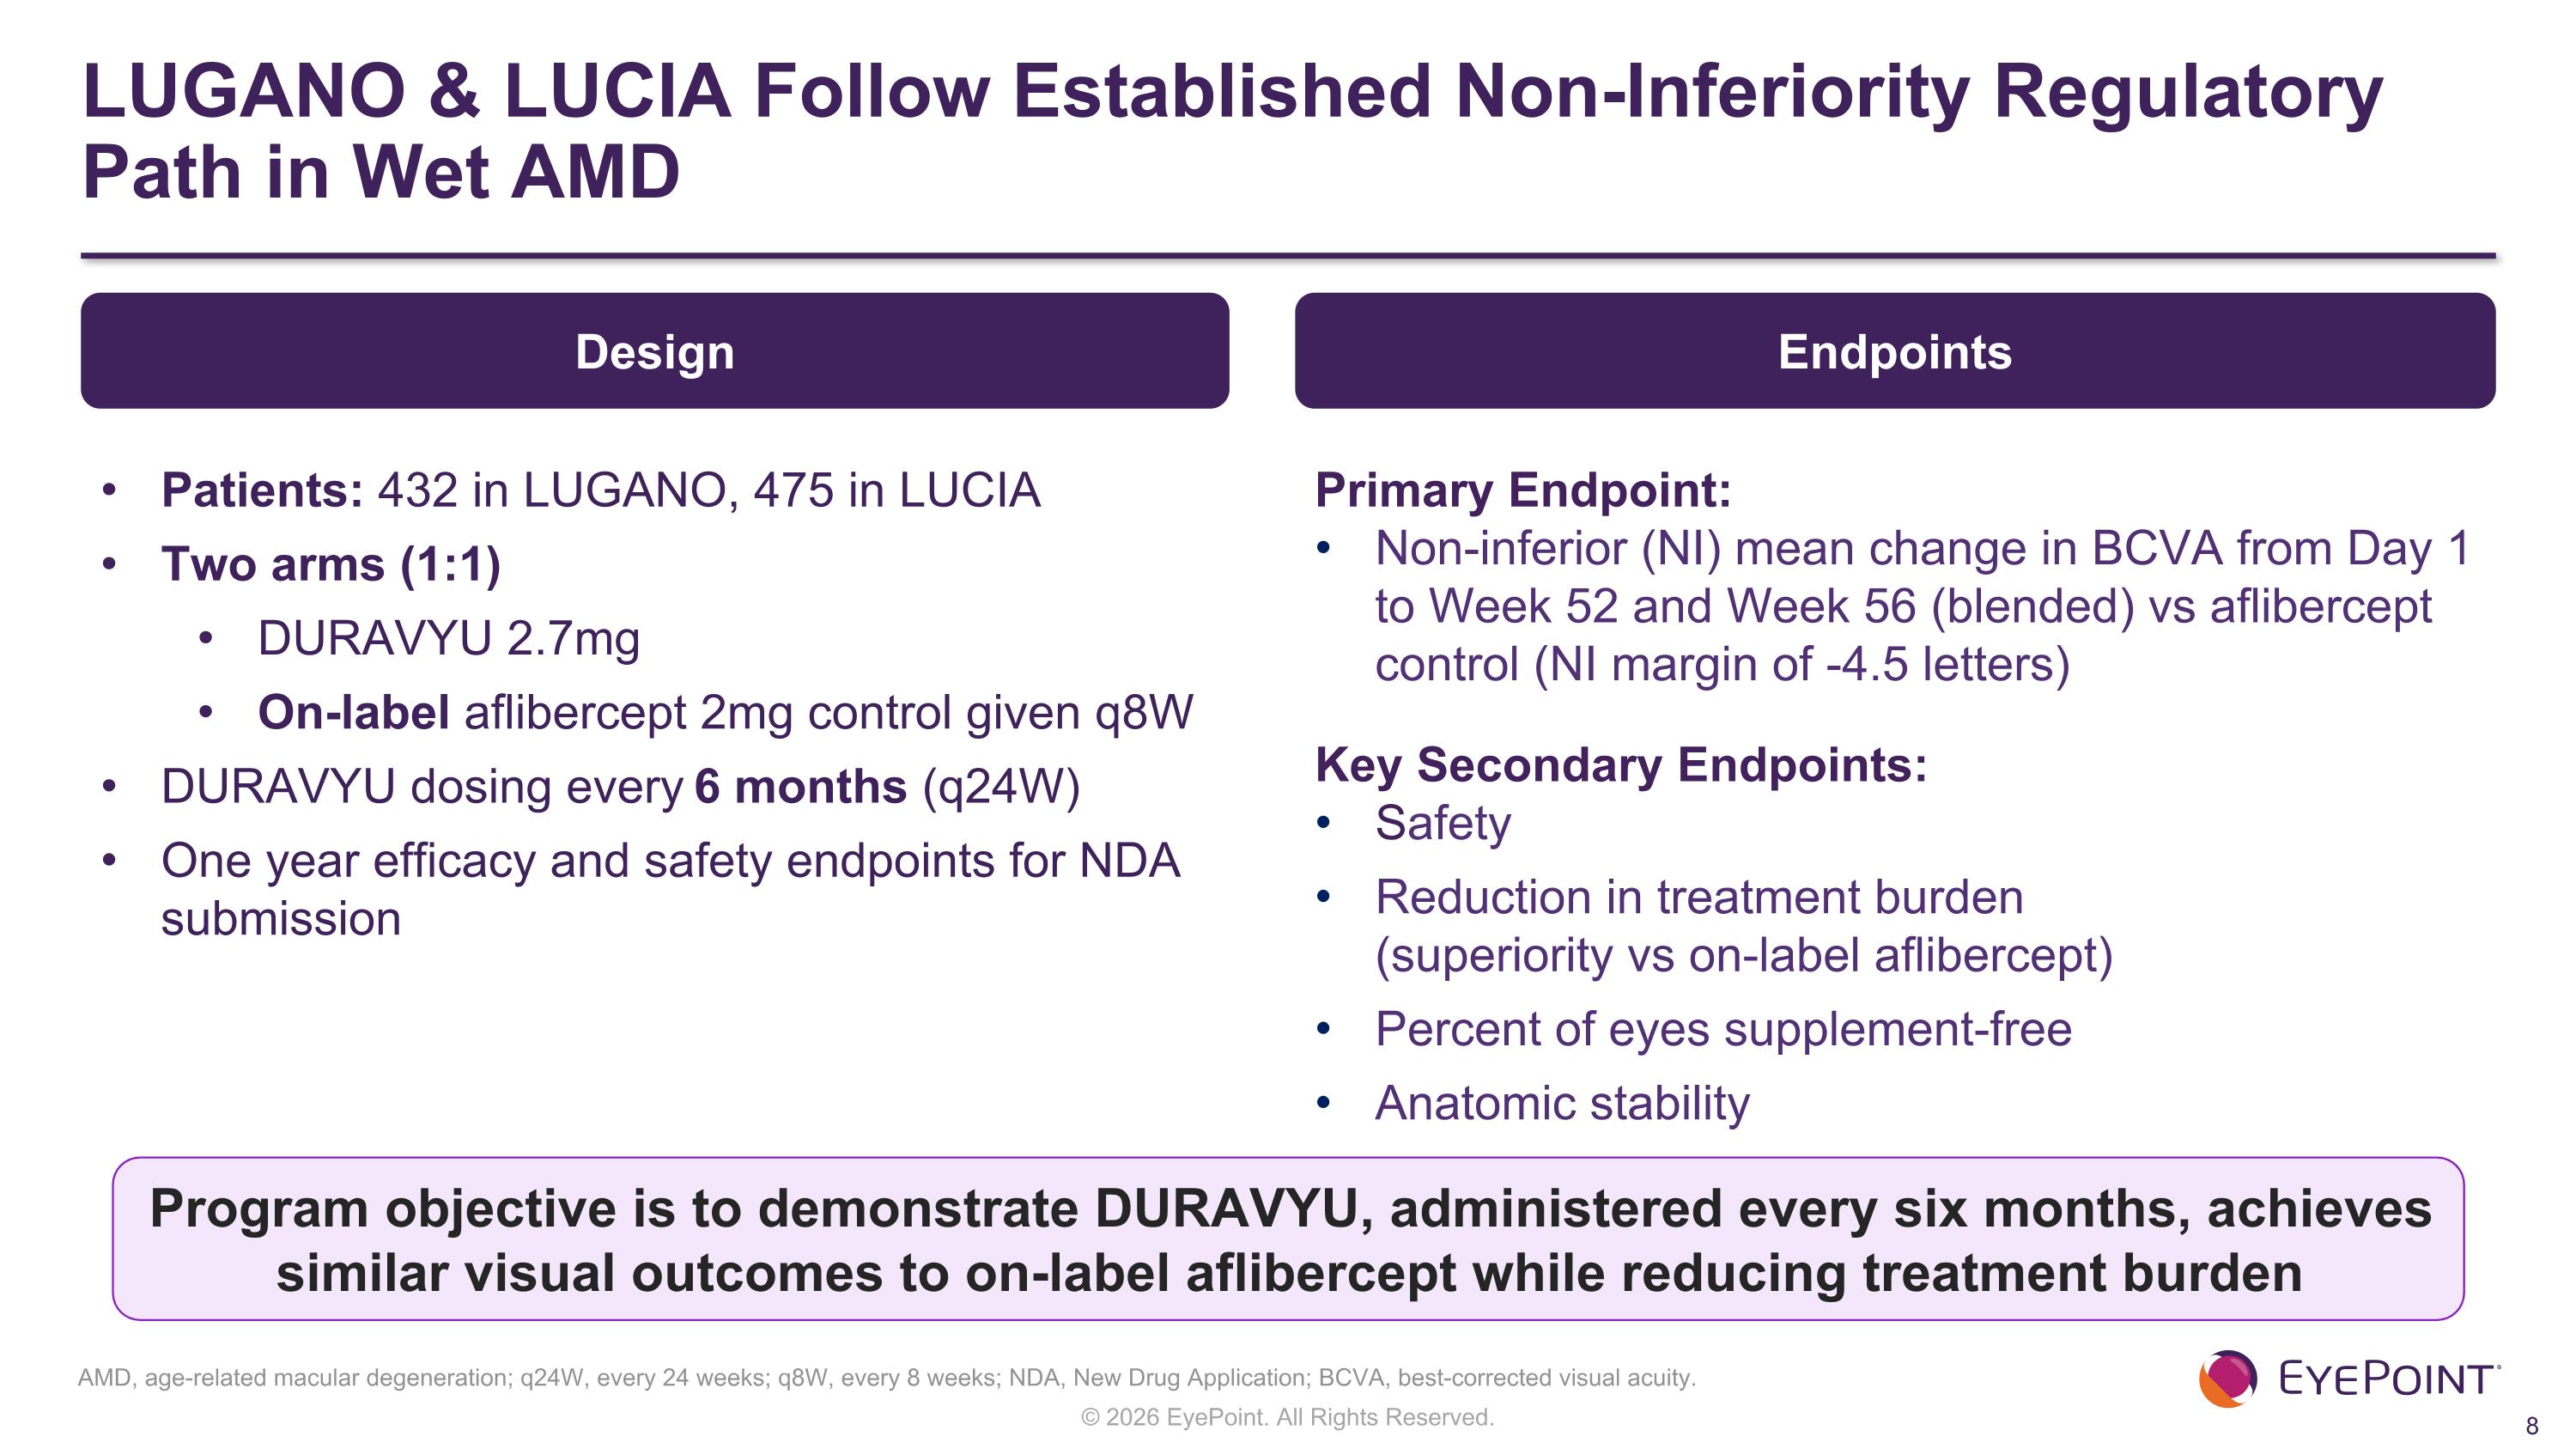
LUGANO & LUCIA Follow Established Non-Inferiority Regulatory Path in Wet AMD Endpoints Primary Endpoint: Non-inferior (NI) mean change in BCVA from Day 1 to Week 52 and Week 56 (blended) vs aflibercept control (NI margin of -4.5 letters) Key Secondary Endpoints: Safety Reduction in treatment burden (superiority vs on-label aflibercept) Percent of eyes supplement-free Anatomic stability Program objective is to demonstrate DURAVYU, administered every six months, achieves similar visual outcomes to on-label aflibercept while reducing treatment burden Design Patients: 432 in LUGANO, 475 in LUCIA Two arms (1:1) DURAVYU 2.7mg On-label aflibercept 2mg control given q8W DURAVYU dosing every 6 months (q24W) One year efficacy and safety endpoints for NDA submission AMD, age-related macular degeneration; q24W, every 24 weeks; q8W, every 8 weeks; NDA, New Drug Application; BCVA, best-corrected visual acuity.
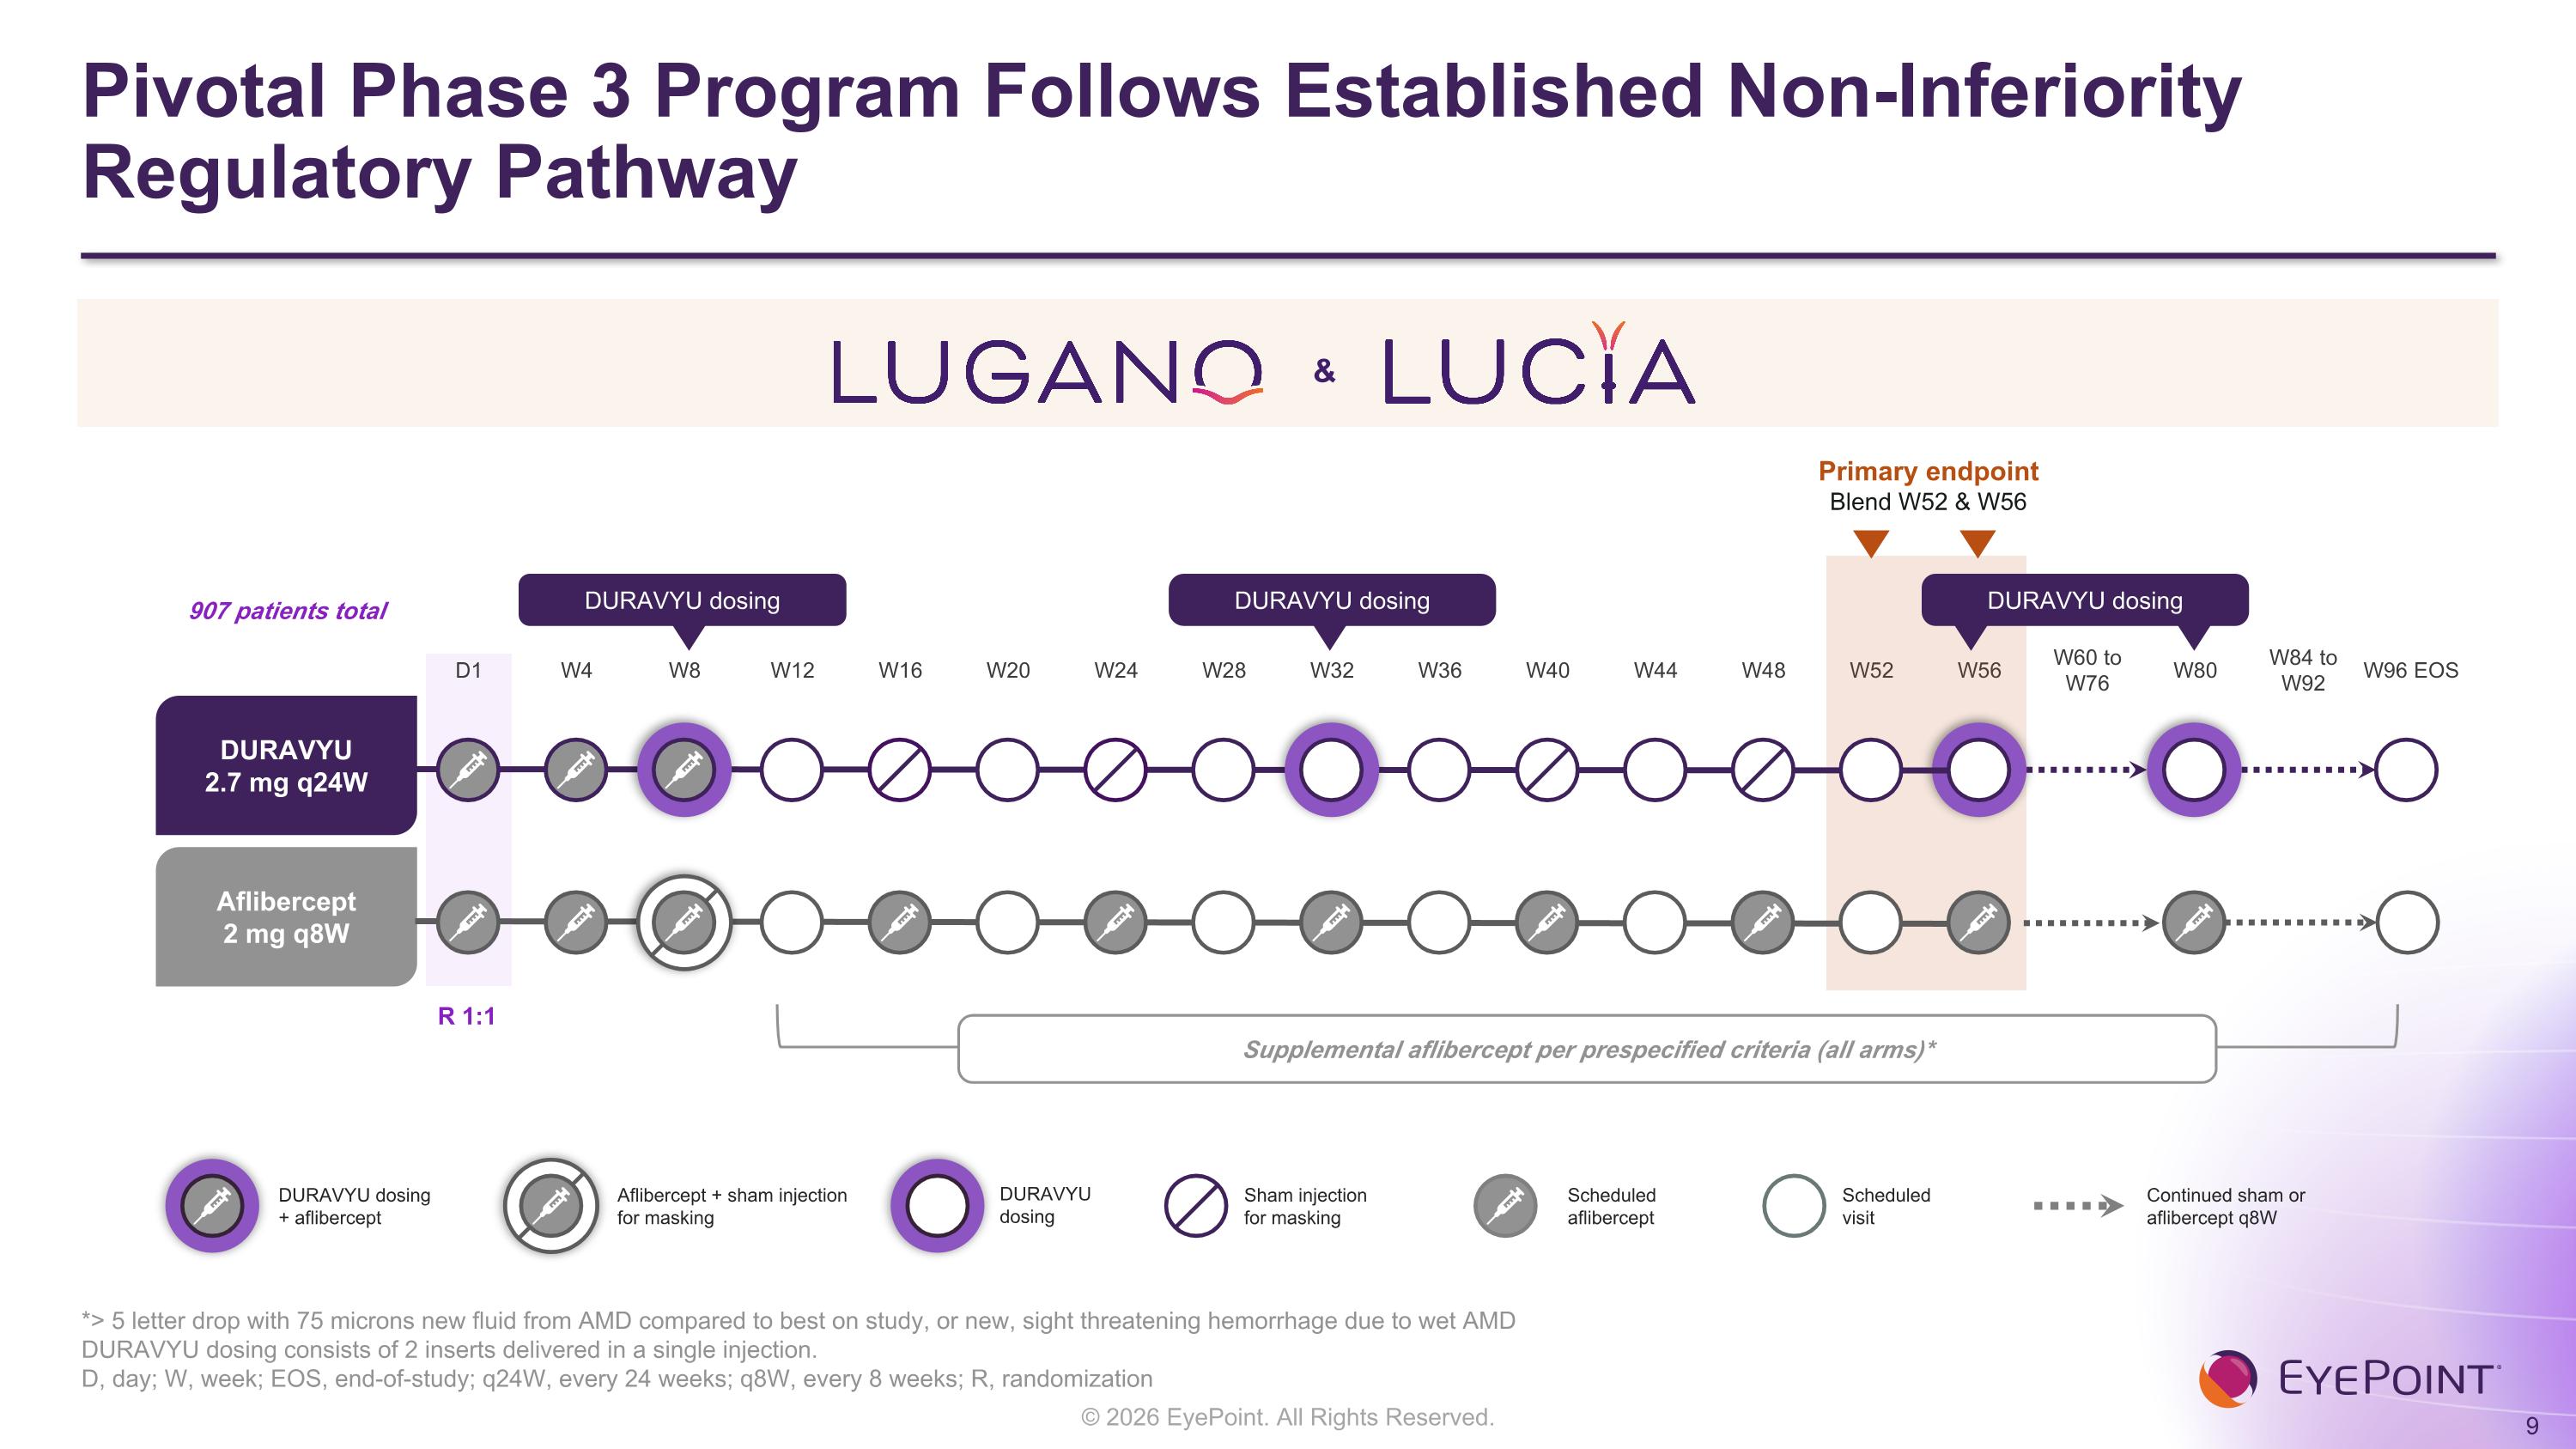
Pivotal Phase 3 Program Follows Established Non-Inferiority Regulatory Pathway *> 5 letter drop with 75 microns new fluid from AMD compared to best on study, or new, sight threatening hemorrhage due to wet AMD DURAVYU dosing consists of 2 inserts delivered in a single injection. D, day; W, week; EOS, end-of-study; q24W, every 24 weeks; q8W, every 8 weeks; R, randomization D1 W4 W8 W12 W16 W20 W24 W28 W32 W36 W40 W44 W48 W52 W56 W60 to W76 W80 W84 to W92 W96 EOS Primary endpoint Blend W52 & W56 DURAVYU 2.7 mg q24W Aflibercept 2 mg q8W DURAVYU dosing DURAVYU dosing DURAVYU dosing 907 patients total R 1:1 Supplemental aflibercept per prespecified criteria (all arms)* Scheduled aflibercept Scheduled visit Sham injection for masking Continued sham or aflibercept q8W DURAVYU dosing + aflibercept Aflibercept + sham injection for masking DURAVYU dosing &

LUCIA Topline Results Baseline Characteristics
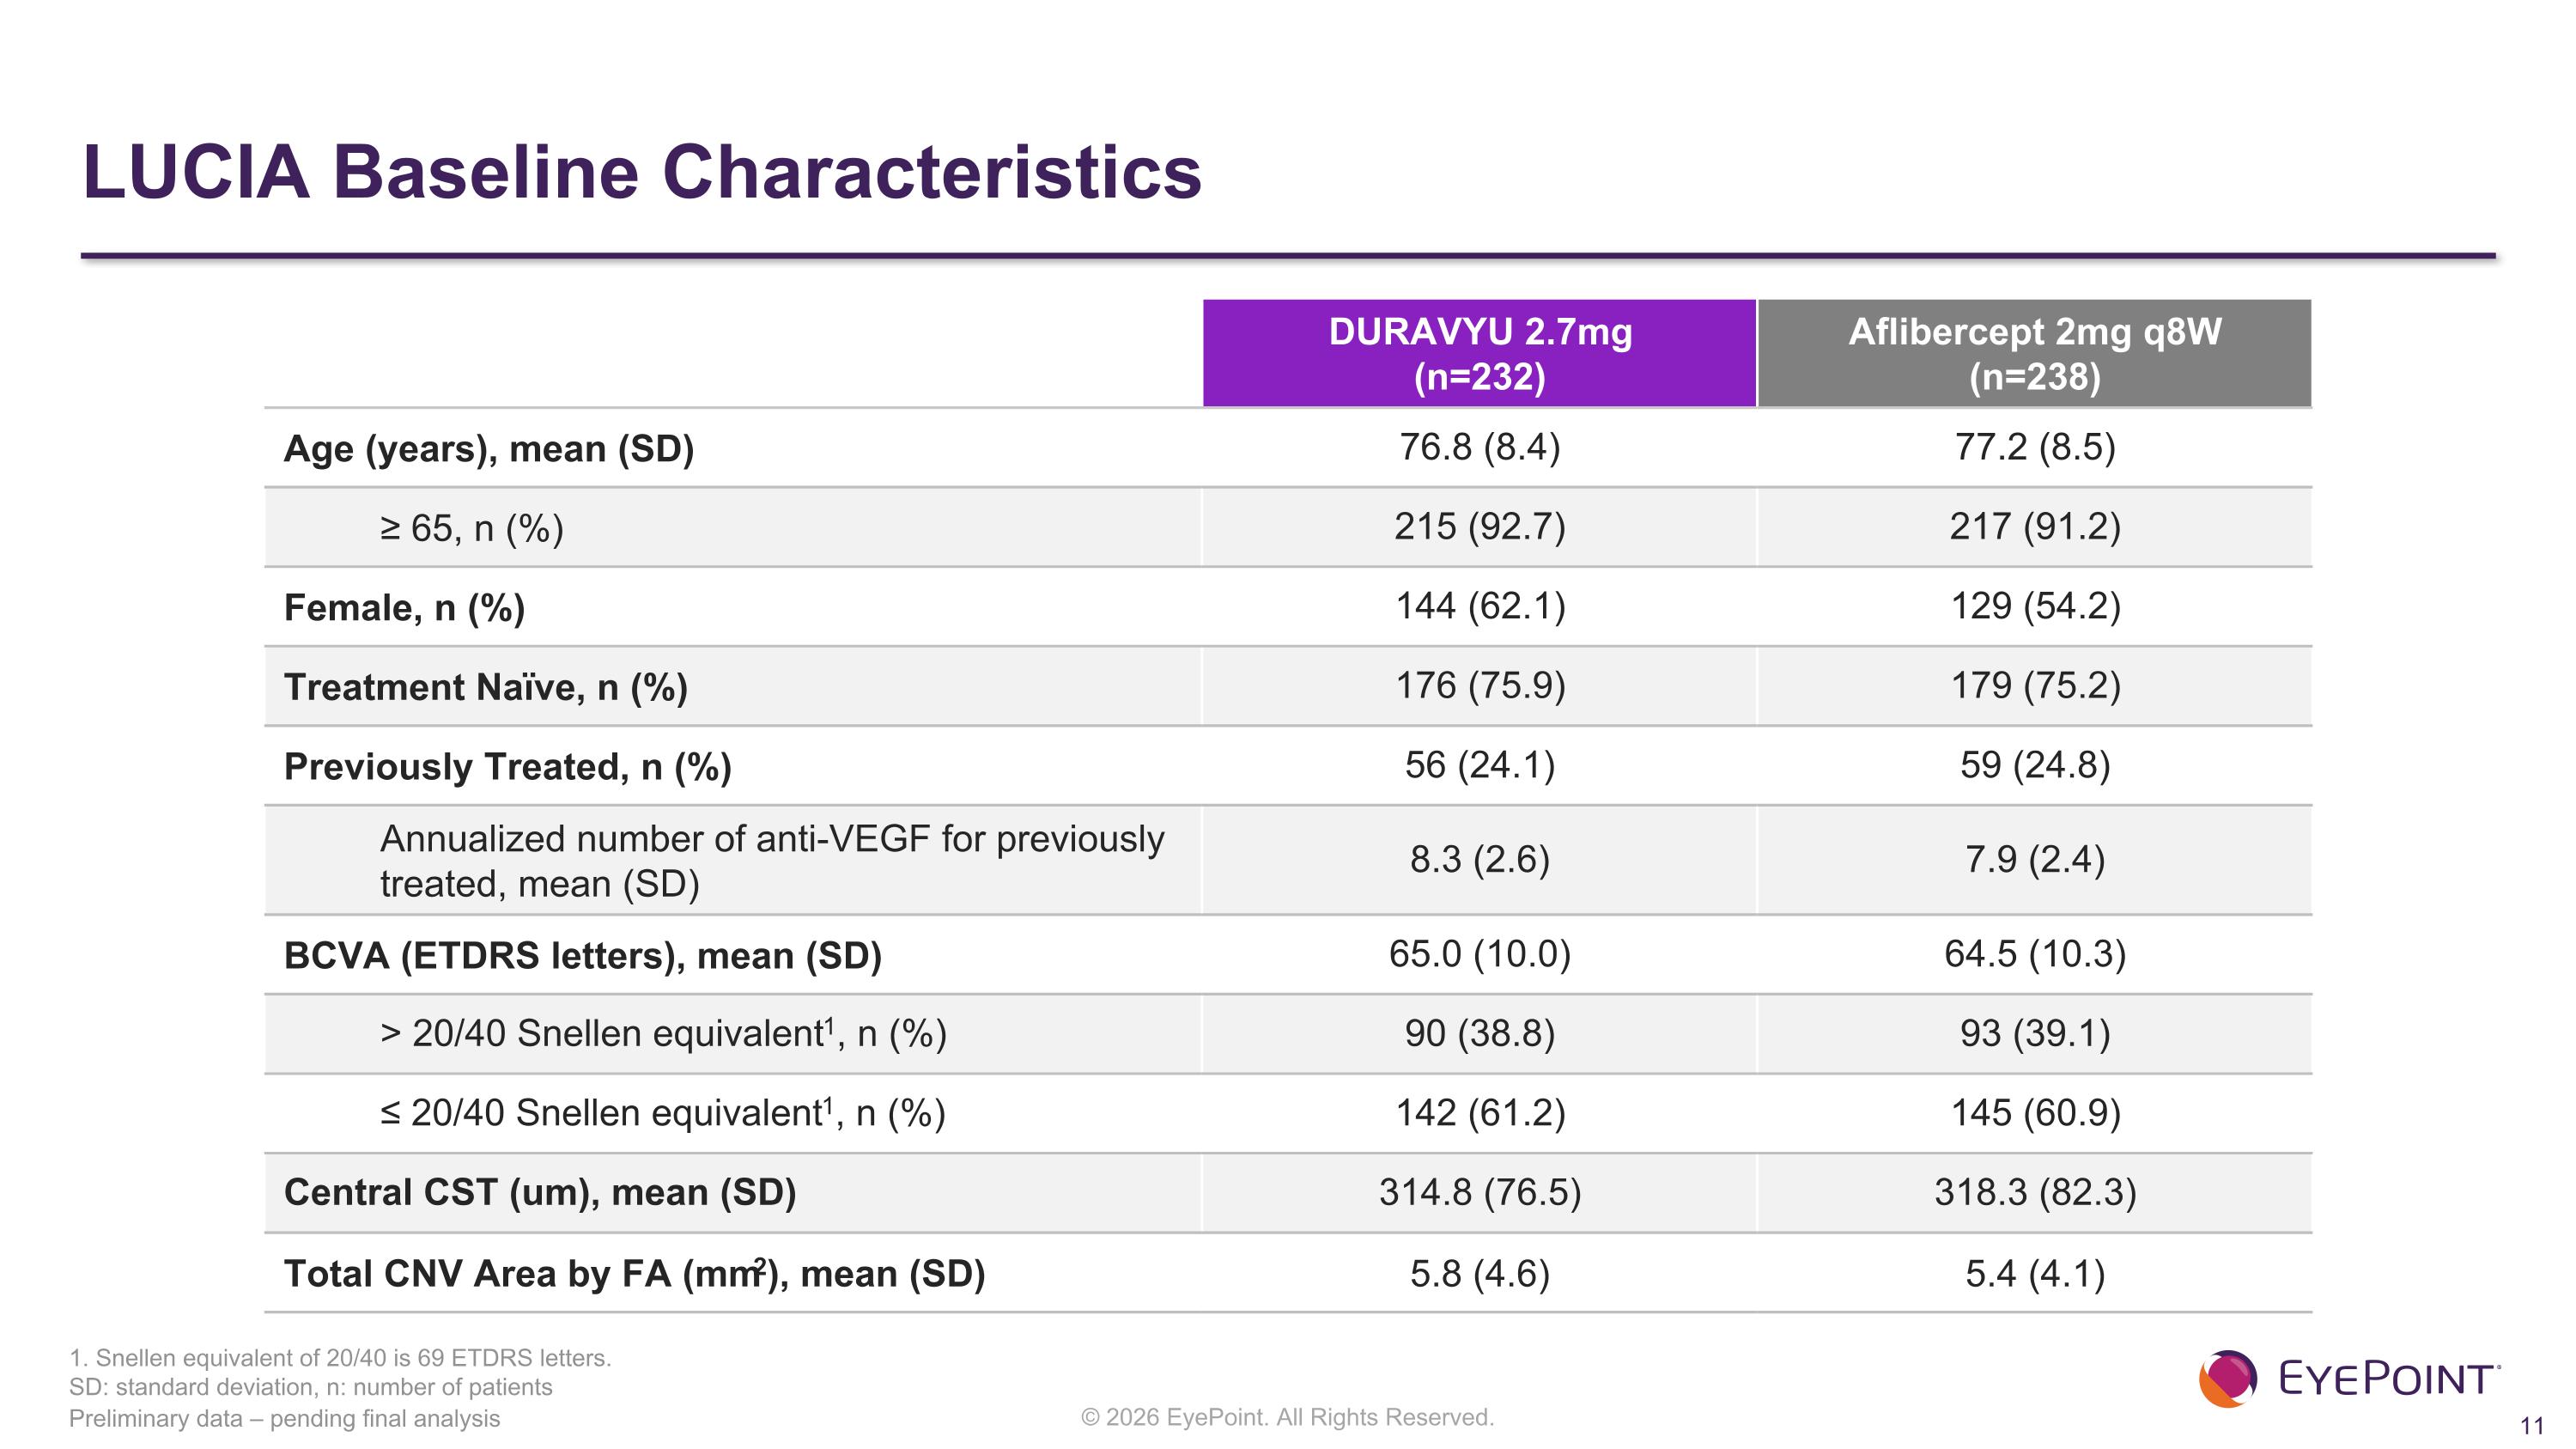
LUCIA Baseline Characteristics Preliminary data – pending final analysis DURAVYU 2.7mg (n=232) Aflibercept 2mg q8W (n=238) Age (years), mean (SD) 76.8 (8.4) 77.2 (8.5) ≥ 65, n (%) 215 (92.7) 217 (91.2) Female, n (%) 144 (62.1) 129 (54.2) Treatment Naïve, n (%) 176 (75.9) 179 (75.2) Previously Treated, n (%) 56 (24.1) 59 (24.8) Annualized number of anti-VEGF for previously treated, mean (SD) 8.3 (2.6) 7.9 (2.4) BCVA (ETDRS letters), mean (SD) 65.0 (10.0) 64.5 (10.3) > 20/40 Snellen equivalent1, n (%) 90 (38.8) 93 (39.1) ≤ 20/40 Snellen equivalent1, n (%) 142 (61.2) 145 (60.9) Central CST (um), mean (SD) 314.8 (76.5) 318.3 (82.3) Total CNV Area by FA (mm2), mean (SD) 5.8 (4.6) 5.4 (4.1) 1. Snellen equivalent of 20/40 is 69 ETDRS letters. SD: standard deviation, n: number of patients

LUCIA Topline Results Visual Acuity
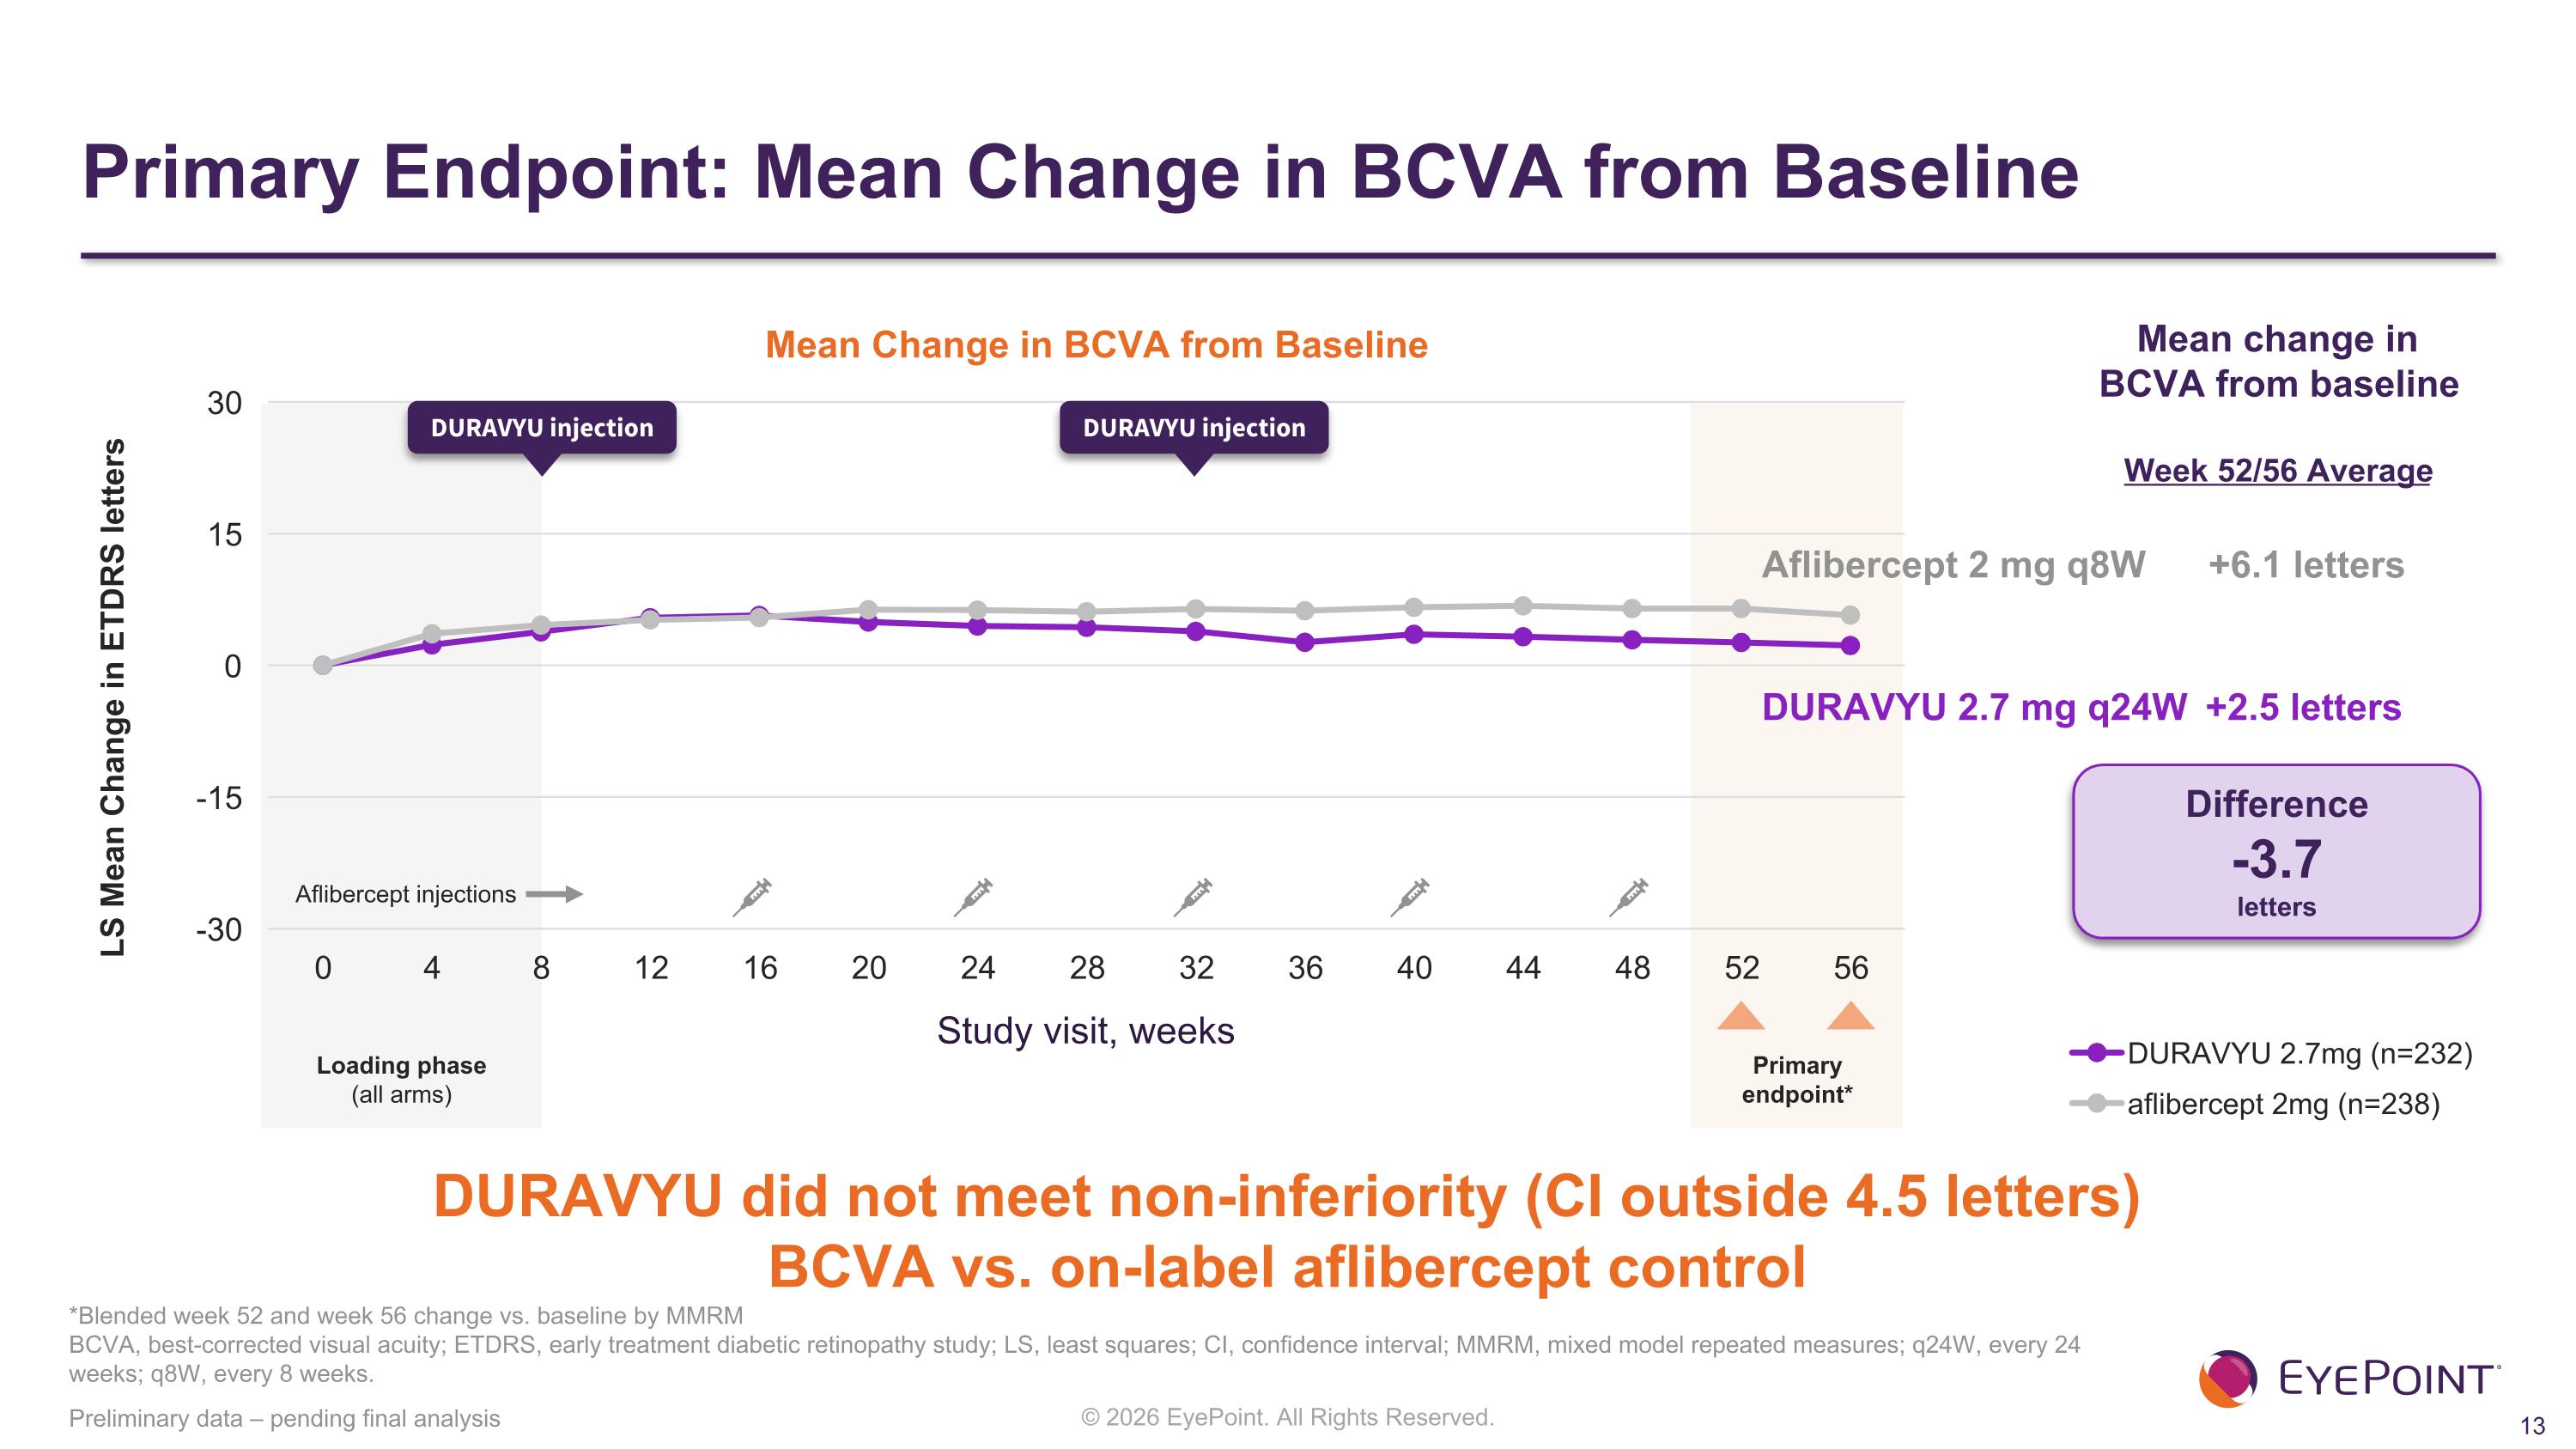
Primary Endpoint: Mean Change in BCVA from Baseline Preliminary data – pending final analysis LS Mean Change in ETDRS letters Mean Change in BCVA from Baseline Study visit, weeks Aflibercept 2 mg q8W +6.1 letters DURAVYU 2.7 mg q24W +2.5 letters Difference -3.7 letters *Blended week 52 and week 56 change vs. baseline by MMRM BCVA, best-corrected visual acuity; ETDRS, early treatment diabetic retinopathy study; LS, least squares; CI, confidence interval; MMRM, mixed model repeated measures; q24W, every 24 weeks; q8W, every 8 weeks. DURAVYU did not meet non-inferiority (CI outside 4.5 letters) BCVA vs. on-label aflibercept control Loading phase (all arms) DURAVYU injection DURAVYU injection Primary endpoint* Mean change in BCVA from baseline Week 52/56 Average Aflibercept injections

LUCIA Topline Results Reduction in Treatment Burden & Supplement-Free Rates
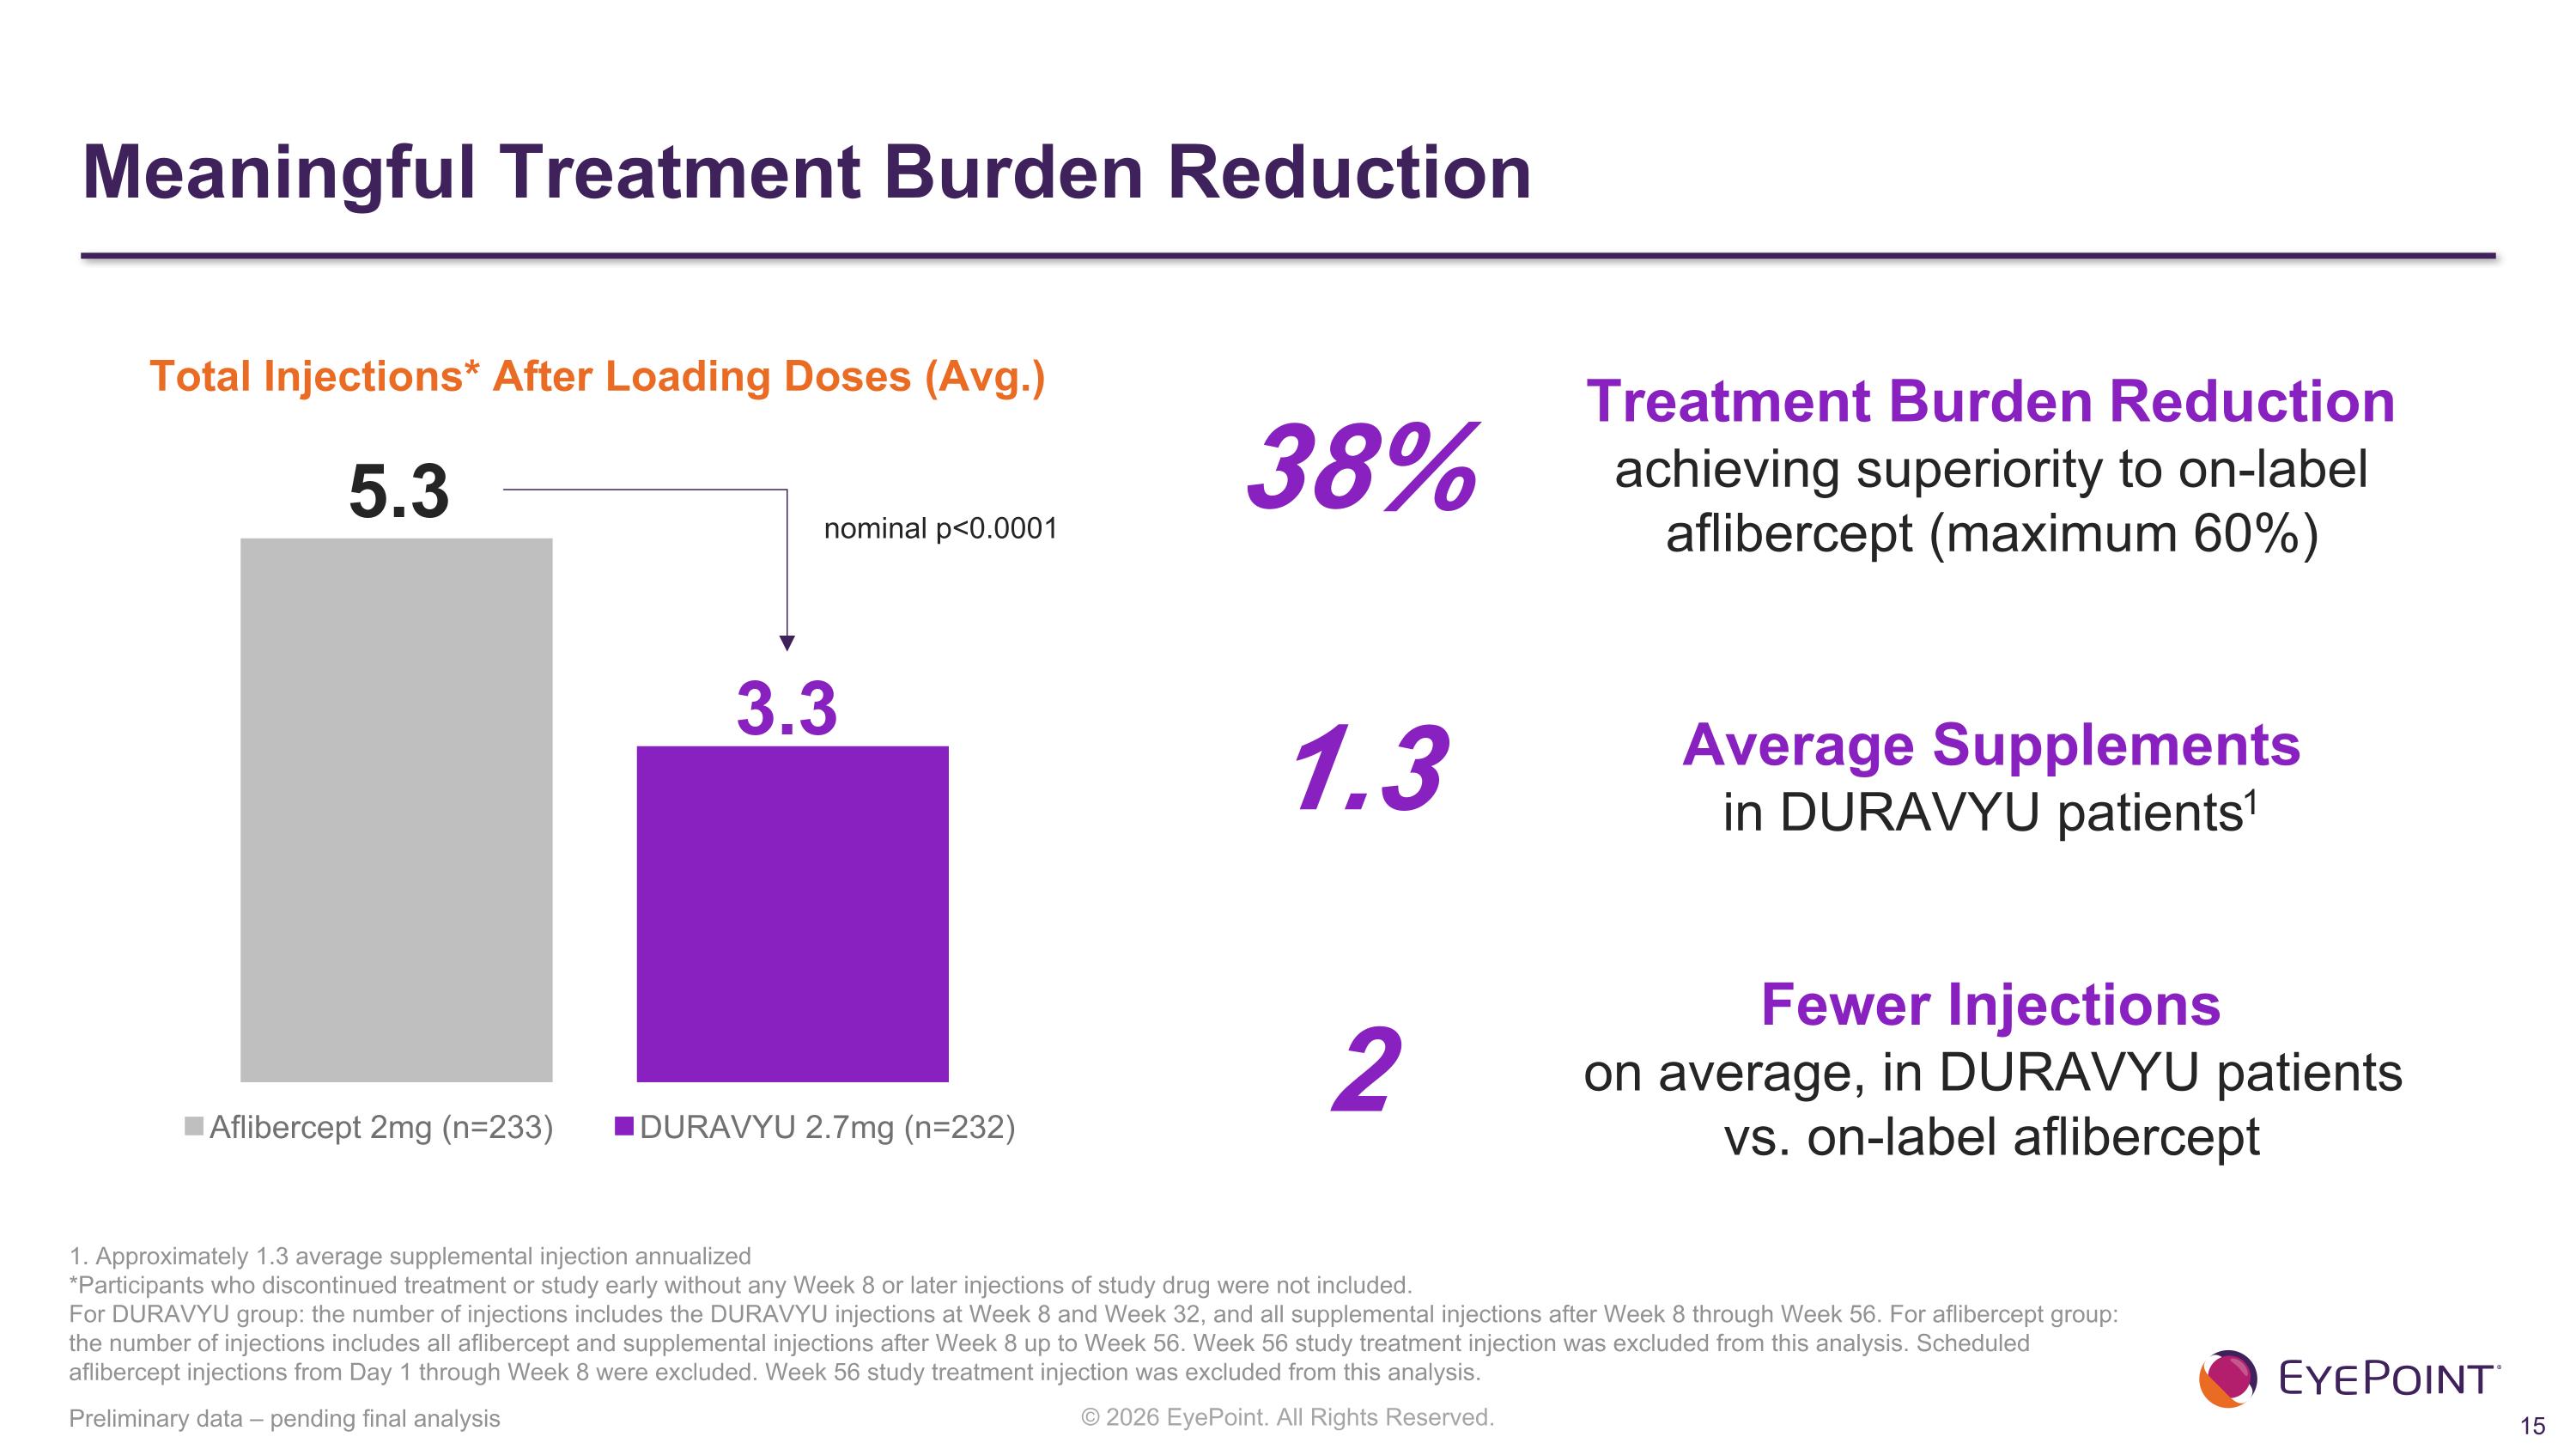
Average Supplements in DURAVYU patients1 Meaningful Treatment Burden Reduction Preliminary data – pending final analysis Total Injections* After Loading Doses (Avg.) 1. Approximately 1.3 average supplemental injection annualized *Participants who discontinued treatment or study early without any Week 8 or later injections of study drug were not included. For DURAVYU group: the number of injections includes the DURAVYU injections at Week 8 and Week 32, and all supplemental injections after Week 8 through Week 56. For aflibercept group: the number of injections includes all aflibercept and supplemental injections after Week 8 up to Week 56. Week 56 study treatment injection was excluded from this analysis. Scheduled aflibercept injections from Day 1 through Week 8 were excluded. Week 56 study treatment injection was excluded from this analysis. 5.3 3.3 Treatment Burden Reduction achieving superiority to on-label aflibercept (maximum 60%) 38% Fewer Injections on average, in DURAVYU patients vs. on-label aflibercept 1.3 2 nominal p<0.0001
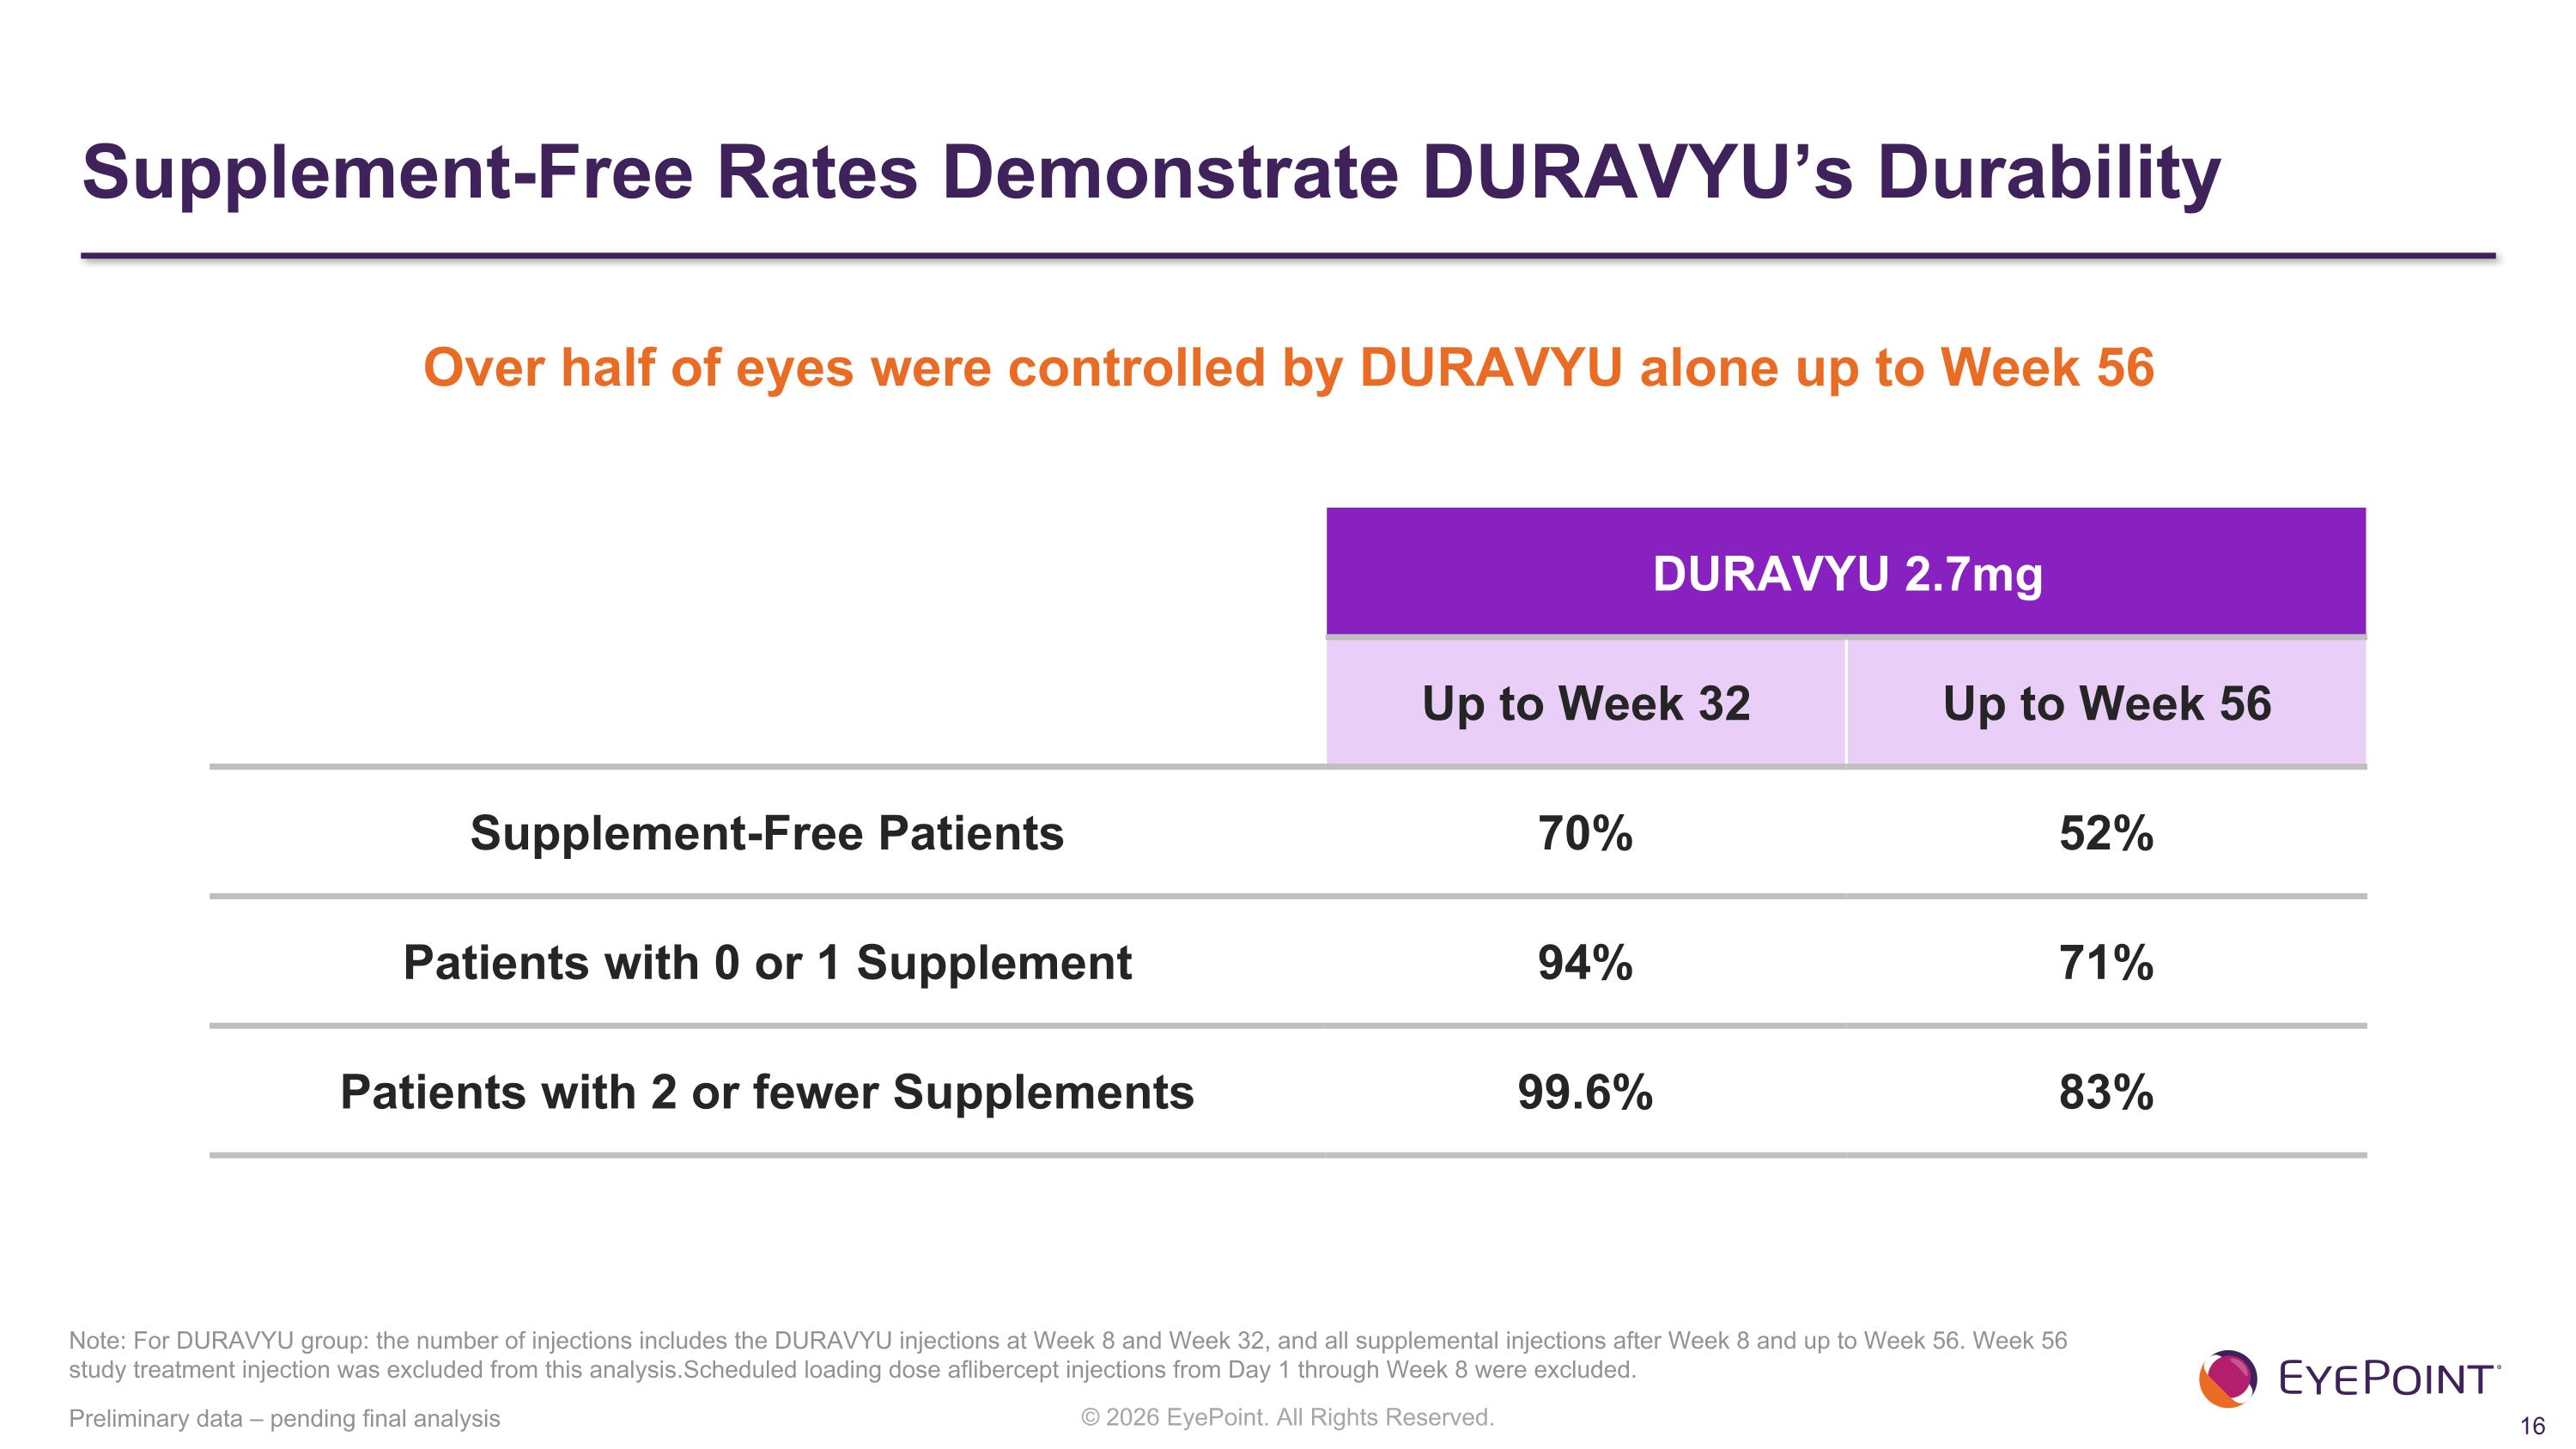
Supplement-Free Rates Demonstrate DURAVYU’s Durability Preliminary data – pending final analysis DURAVYU 2.7mg Up to Week 32 Up to Week 56 Supplement-Free Patients 70% 52% Patients with 0 or 1 Supplement 94% 71% Patients with 2 or fewer Supplements 99.6% 83% Note: For DURAVYU group: the number of injections includes the DURAVYU injections at Week 8 and Week 32, and all supplemental injections after Week 8 and up to Week 56. Week 56 study treatment injection was excluded from this analysis.Scheduled loading dose aflibercept injections from Day 1 through Week 8 were excluded. Over half of eyes were controlled by DURAVYU alone up to Week 56

LUCIA Topline Results Anatomic Control
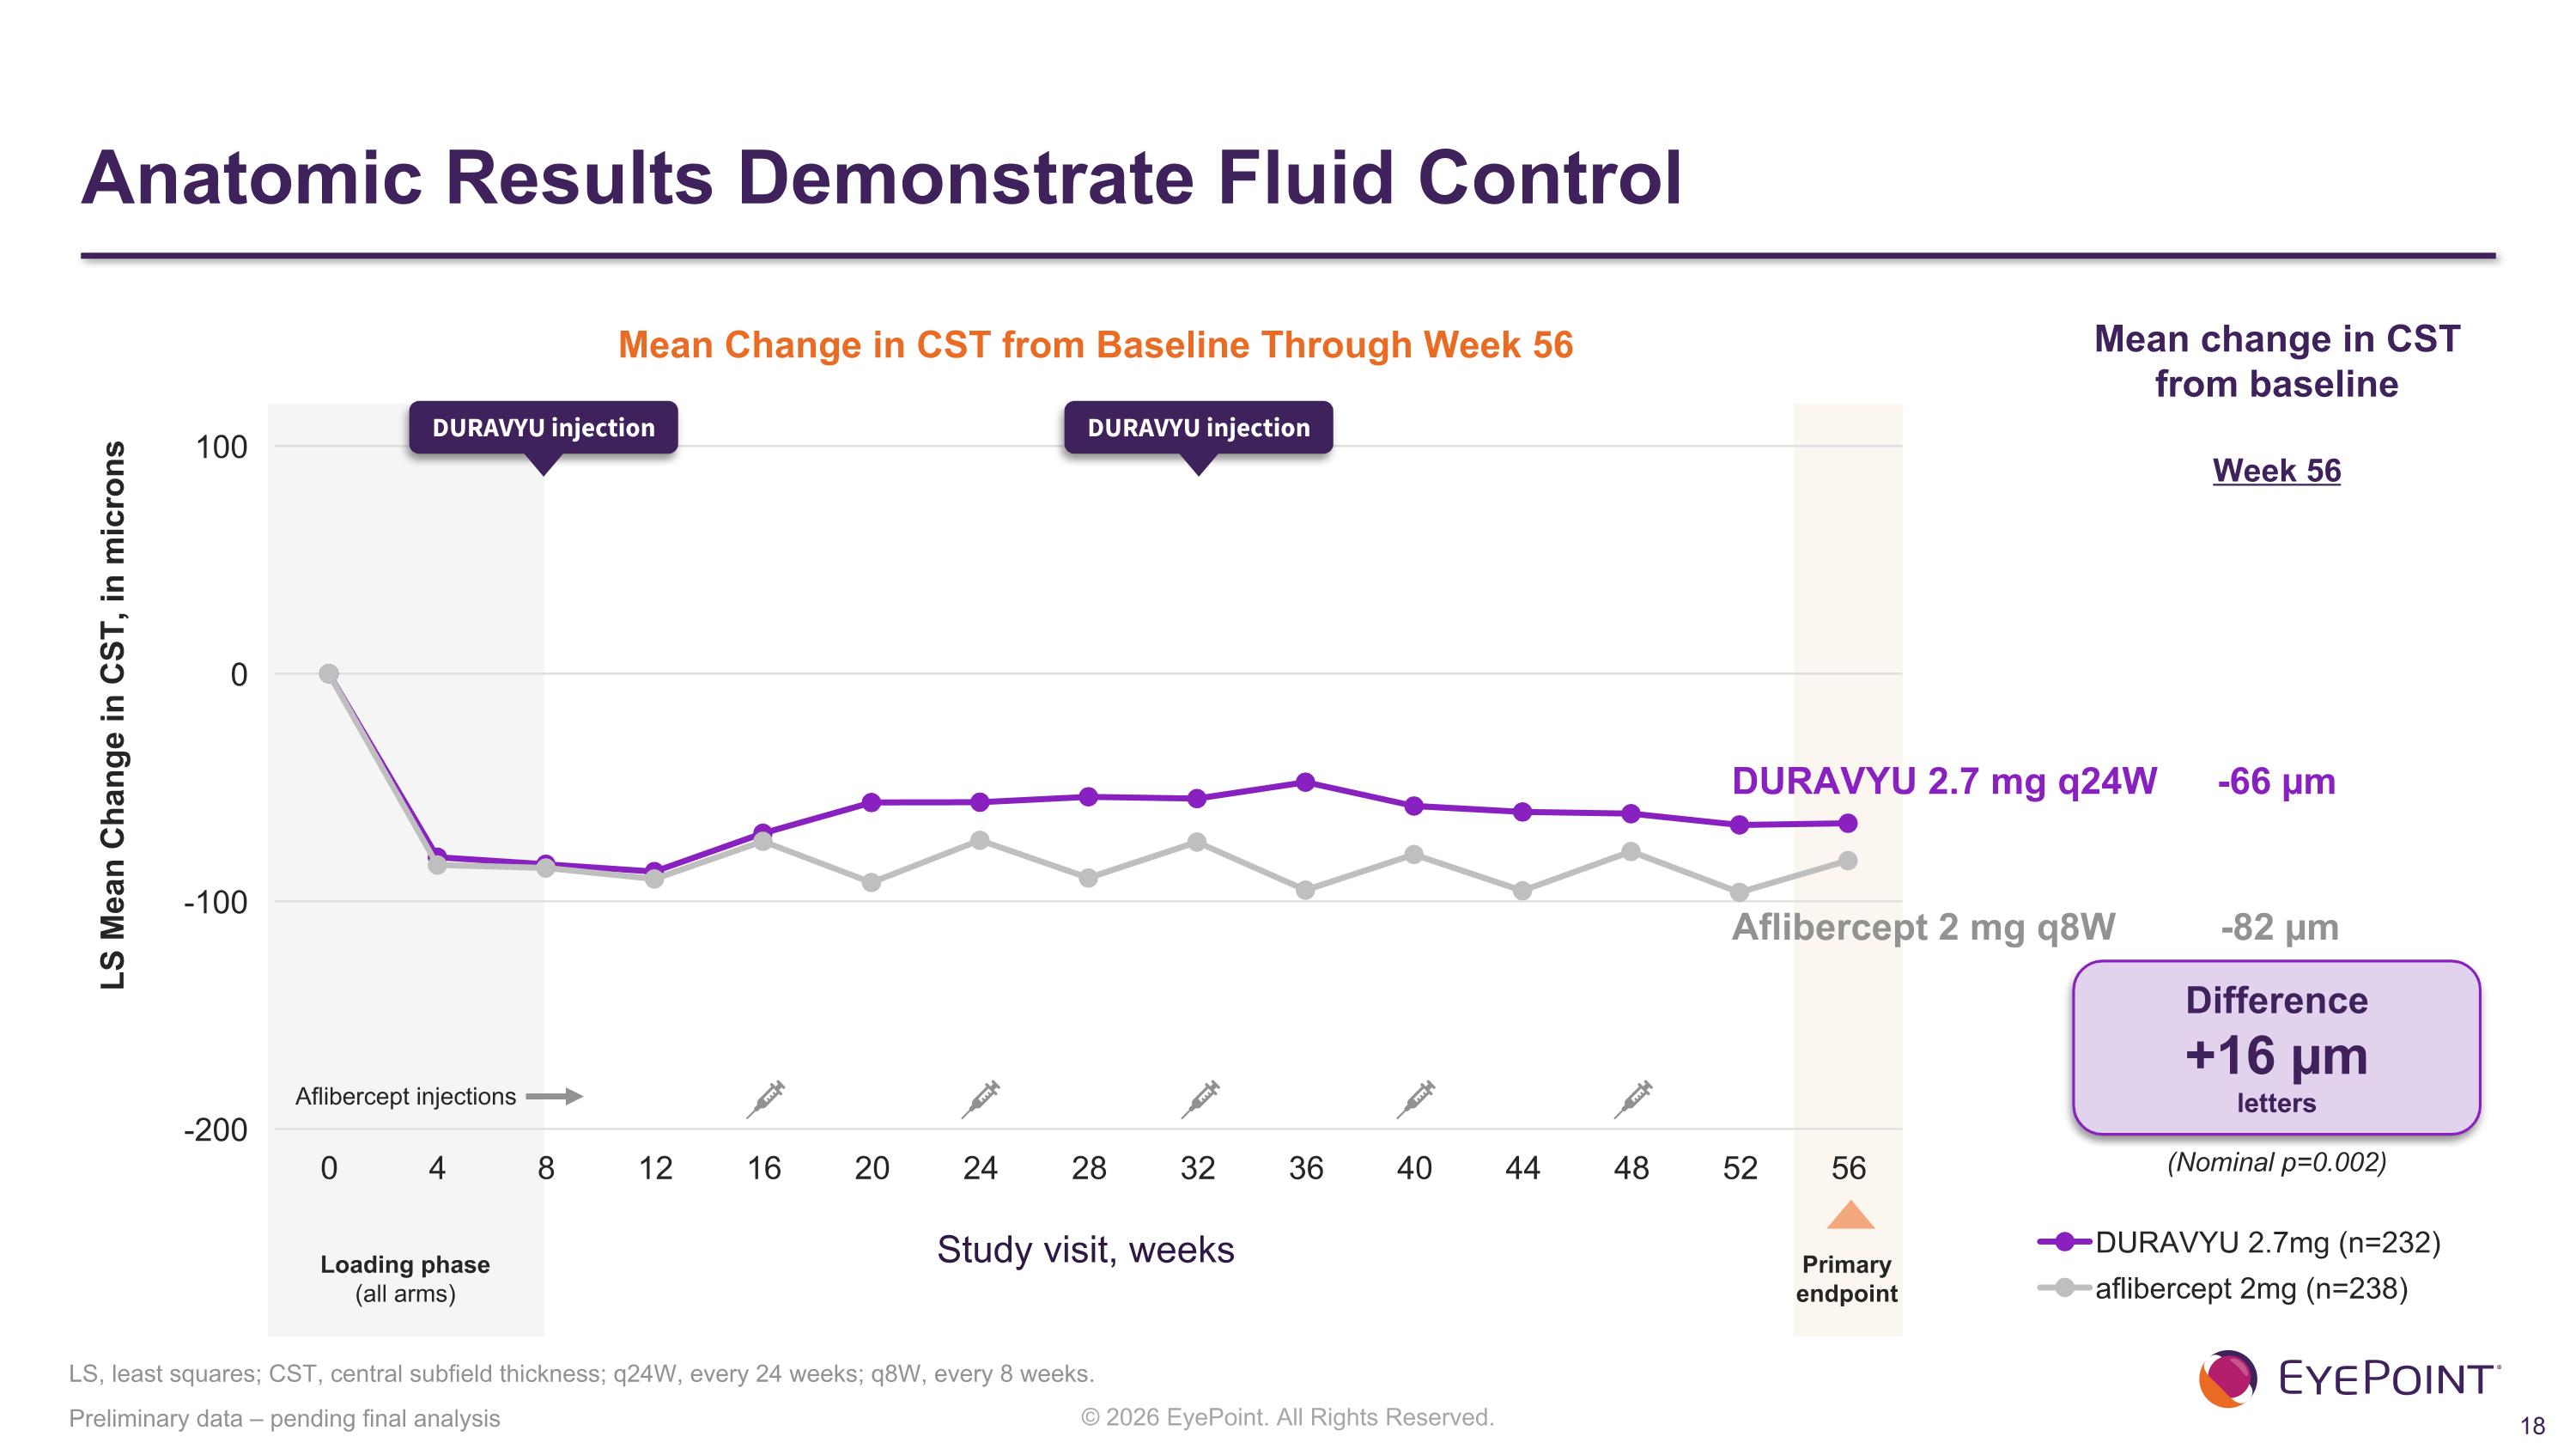
Anatomic Results Demonstrate Fluid Control LS, least squares; CST, central subfield thickness; q24W, every 24 weeks; q8W, every 8 weeks. Preliminary data – pending final analysis LS Mean Change in CST, in microns Mean Change in CST from Baseline Through Week 56 Study visit, weeks Aflibercept 2 mg q8W -82 µm DURAVYU 2.7 mg q24W -66 µm Difference +16 µm letters Loading phase (all arms) DURAVYU injection DURAVYU injection Primary endpoint Mean change in CST from baseline Week 56 Aflibercept injections (Nominal p=0.002)

LUCIA Topline Results Safety Data
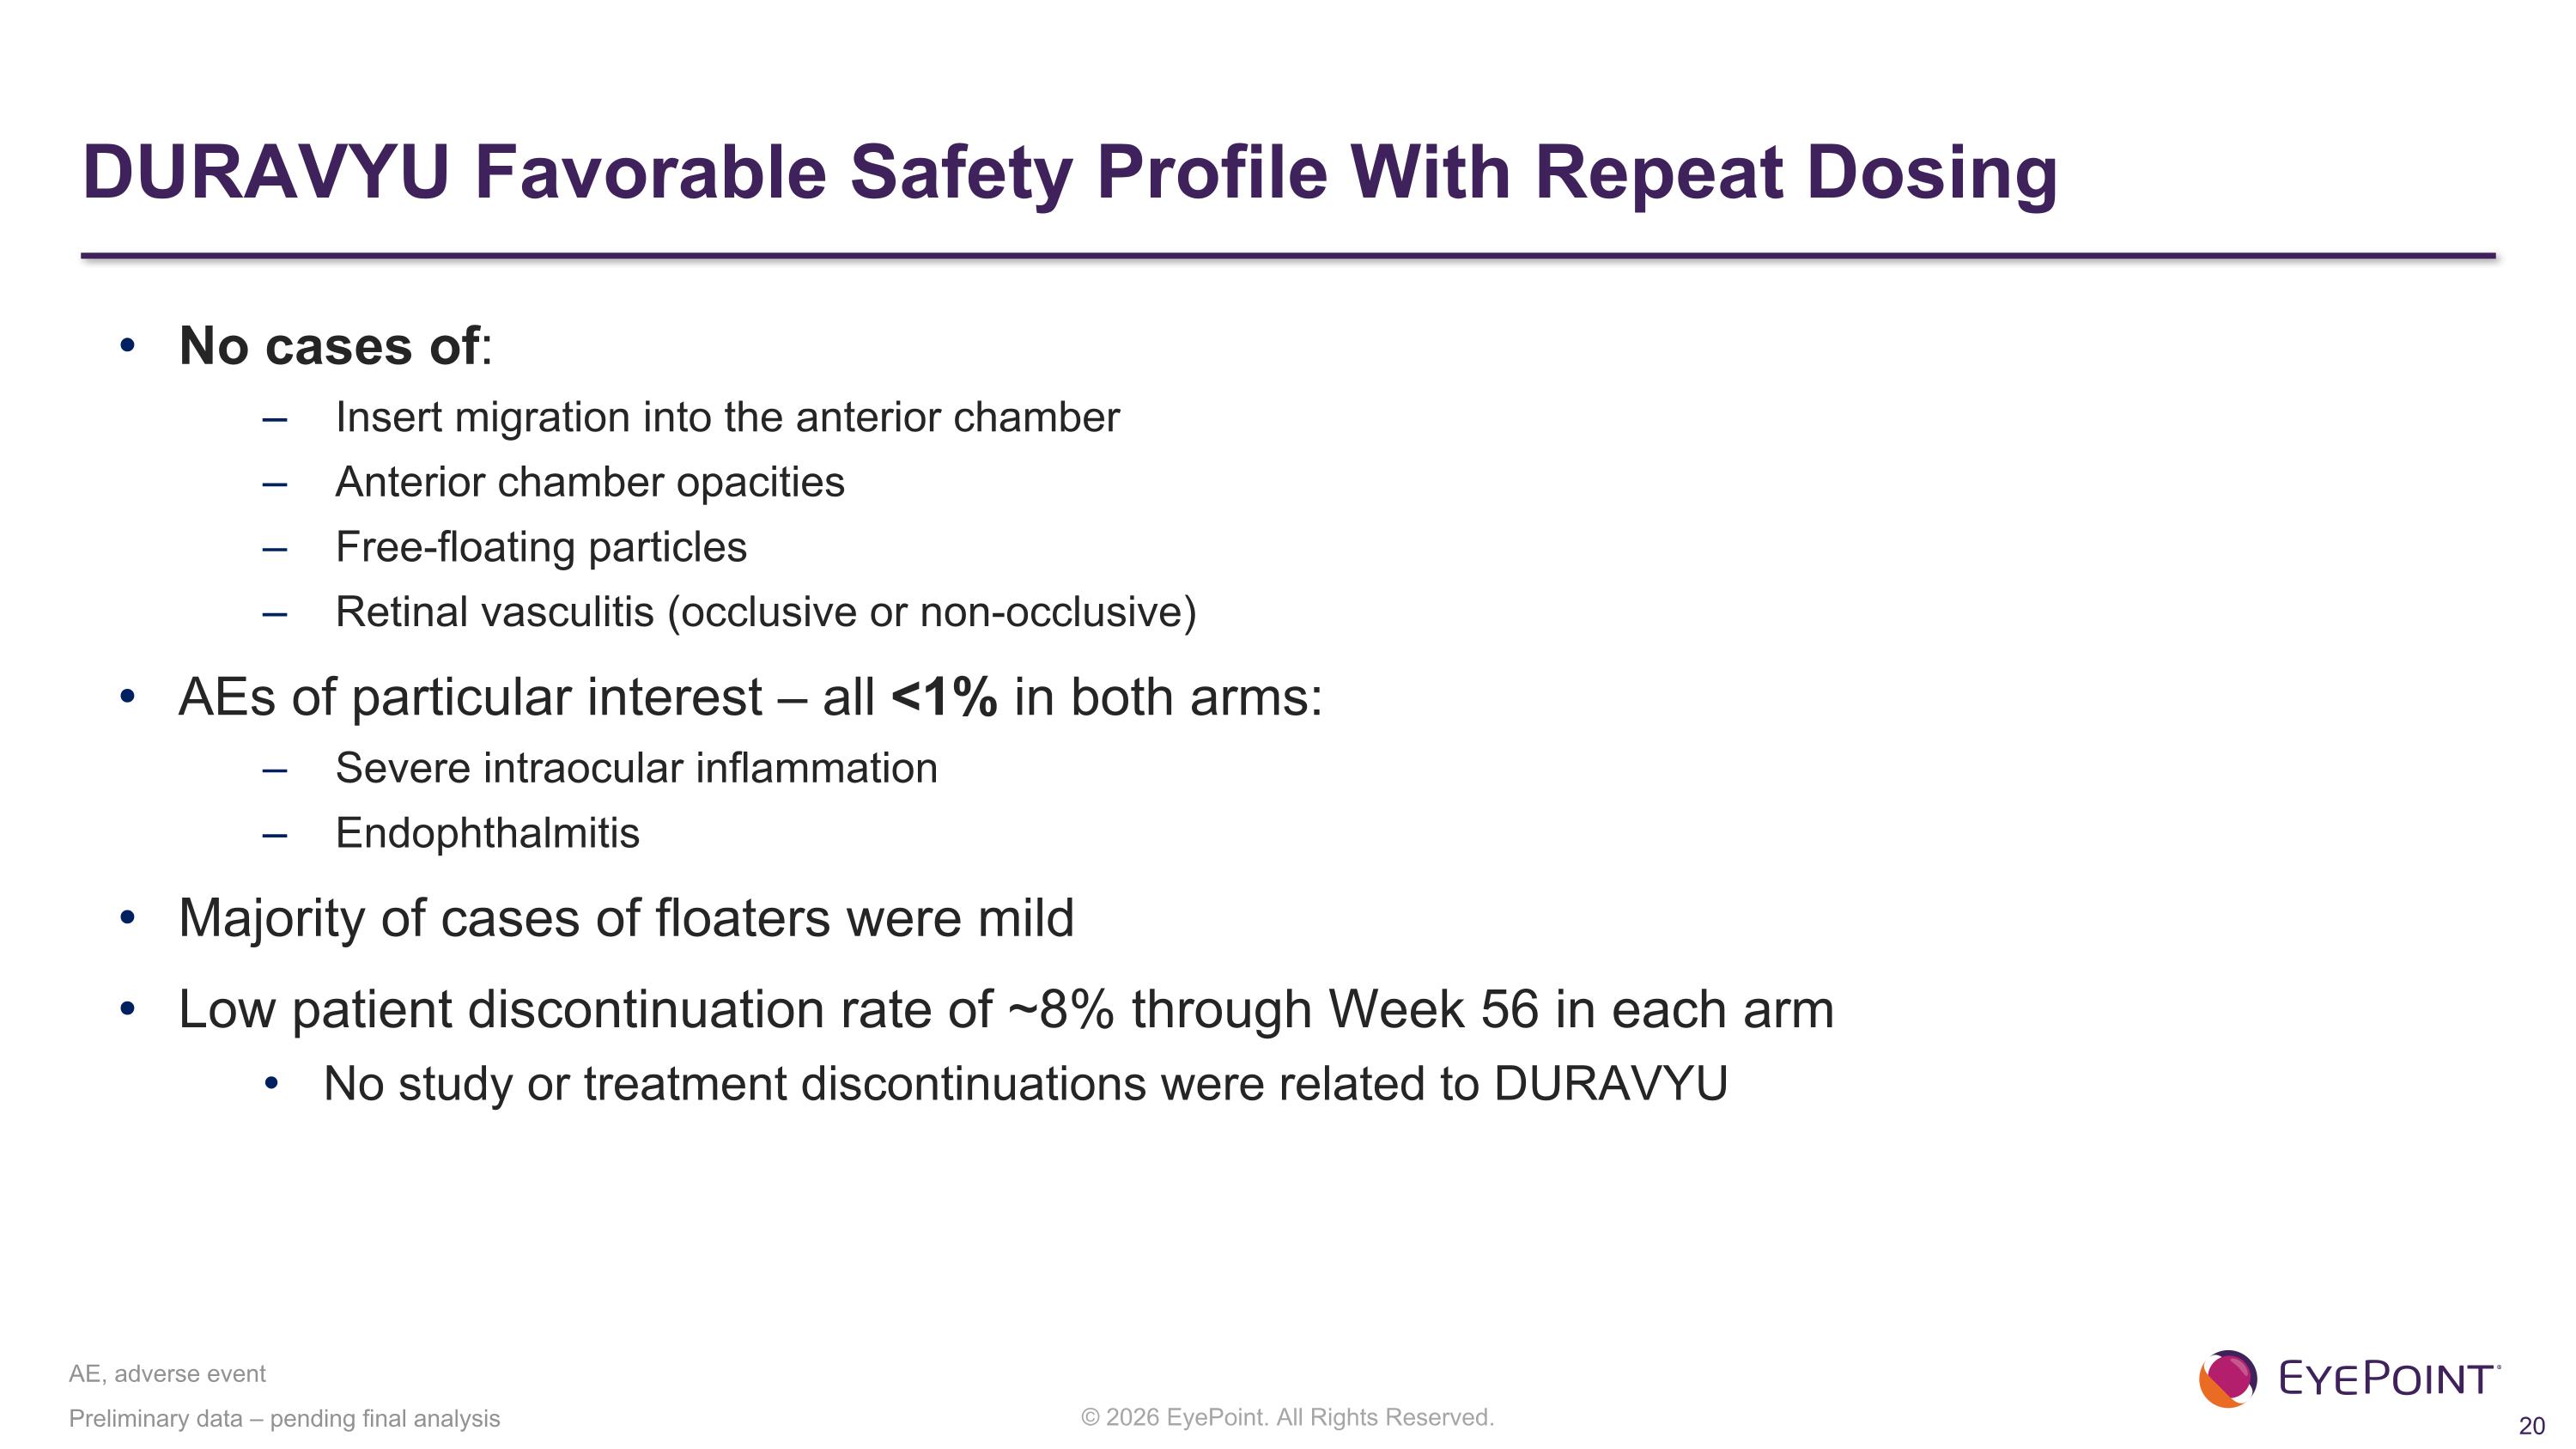
DURAVYU Favorable Safety Profile With Repeat Dosing No cases of: Insert migration into the anterior chamber Anterior chamber opacities Free-floating particles Retinal vasculitis (occlusive or non-occlusive) AEs of particular interest – all <1% in both arms: Severe intraocular inflammation Endophthalmitis Majority of cases of floaters were mild Low patient discontinuation rate of ~8% through Week 56 in each arm No study or treatment discontinuations were related to DURAVYU Preliminary data – pending final analysis AE, adverse event
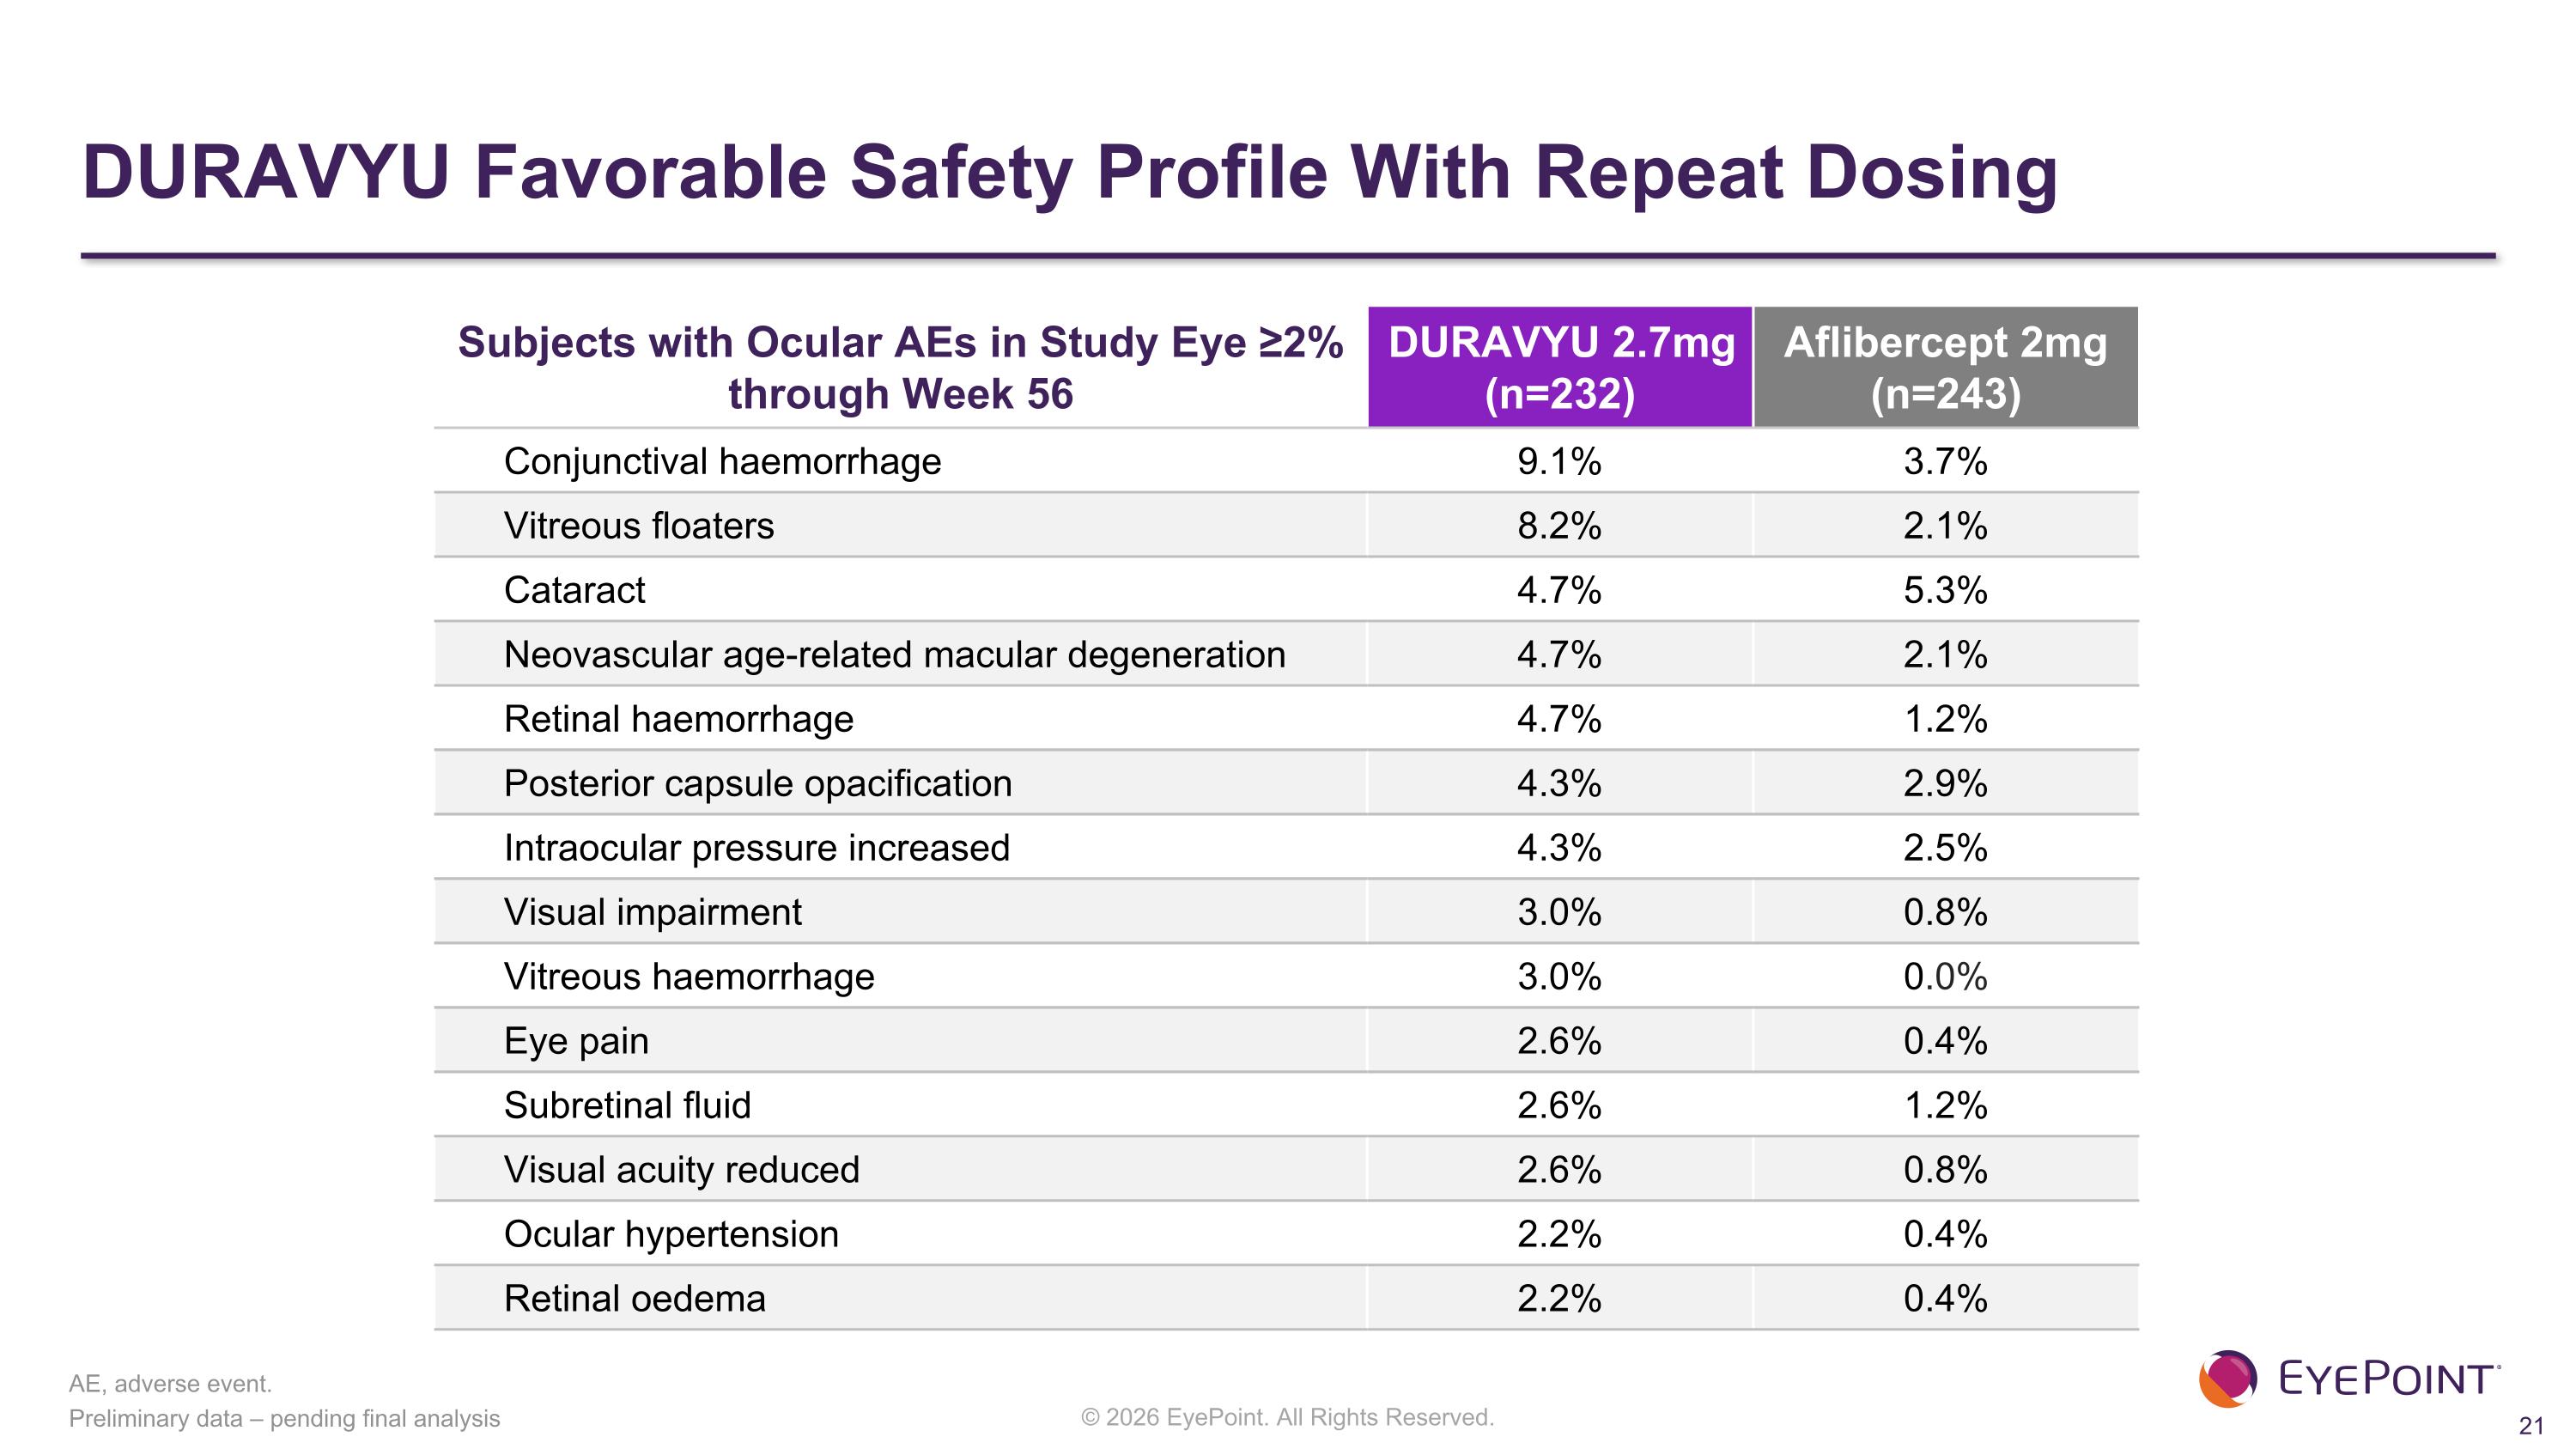
Subjects with Ocular AEs in Study Eye ≥2% through Week 56 DURAVYU 2.7mg (n=232) Aflibercept 2mg (n=243) Conjunctival haemorrhage 9.1% 3.7% Vitreous floaters 8.2% 2.1% Cataract 4.7% 5.3% Neovascular age-related macular degeneration 4.7% 2.1% Retinal haemorrhage 4.7% 1.2% Posterior capsule opacification 4.3% 2.9% Intraocular pressure increased 4.3% 2.5% Visual impairment 3.0% 0.8% Vitreous haemorrhage 3.0% 0.0% Eye pain 2.6% 0.4% Subretinal fluid 2.6% 1.2% Visual acuity reduced 2.6% 0.8% Ocular hypertension 2.2% 0.4% Retinal oedema 2.2% 0.4% Preliminary data – pending final analysis AE, adverse event. DURAVYU Favorable Safety Profile With Repeat Dosing

Pooled Results LUGANO and LUCIA
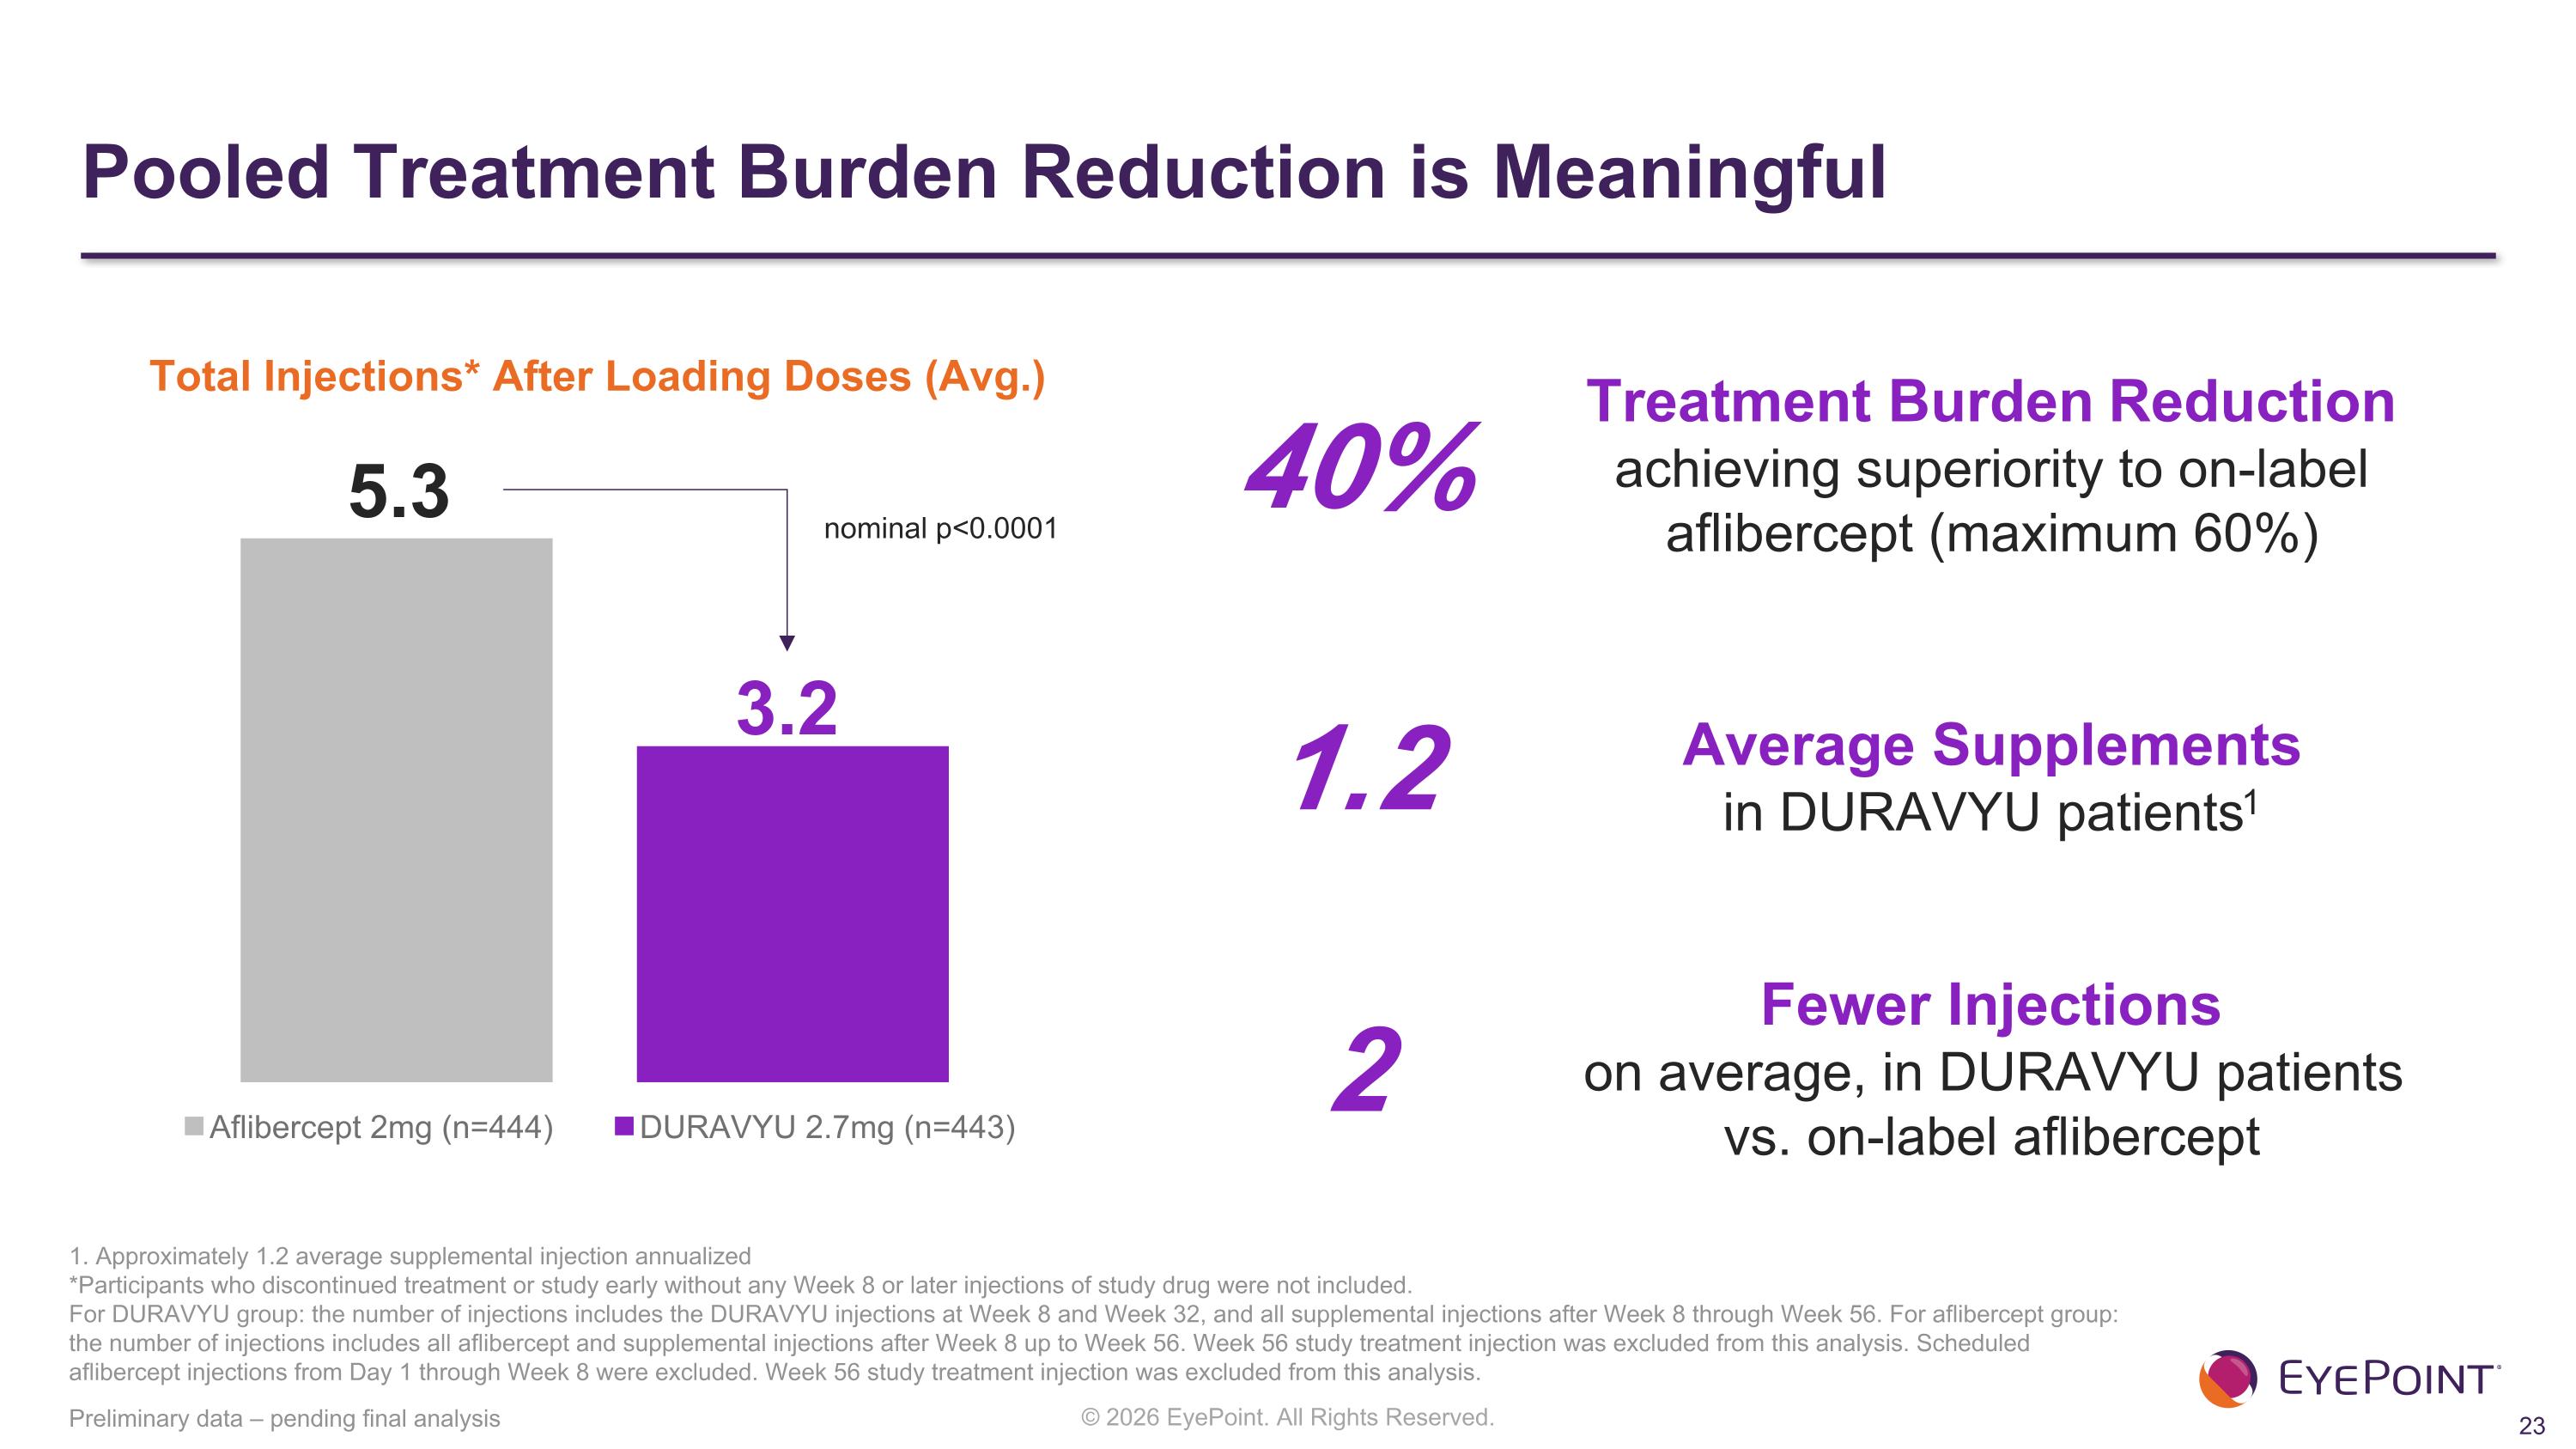
Average Supplements in DURAVYU patients1 Pooled Treatment Burden Reduction is Meaningful Preliminary data – pending final analysis Total Injections* After Loading Doses (Avg.) 5.3 3.2 Treatment Burden Reduction achieving superiority to on-label aflibercept (maximum 60%) 40% Fewer Injections on average, in DURAVYU patients vs. on-label aflibercept 1.2 2 nominal p<0.0001 1. Approximately 1.2 average supplemental injection annualized *Participants who discontinued treatment or study early without any Week 8 or later injections of study drug were not included. For DURAVYU group: the number of injections includes the DURAVYU injections at Week 8 and Week 32, and all supplemental injections after Week 8 through Week 56. For aflibercept group: the number of injections includes all aflibercept and supplemental injections after Week 8 up to Week 56. Week 56 study treatment injection was excluded from this analysis. Scheduled aflibercept injections from Day 1 through Week 8 were excluded. Week 56 study treatment injection was excluded from this analysis.
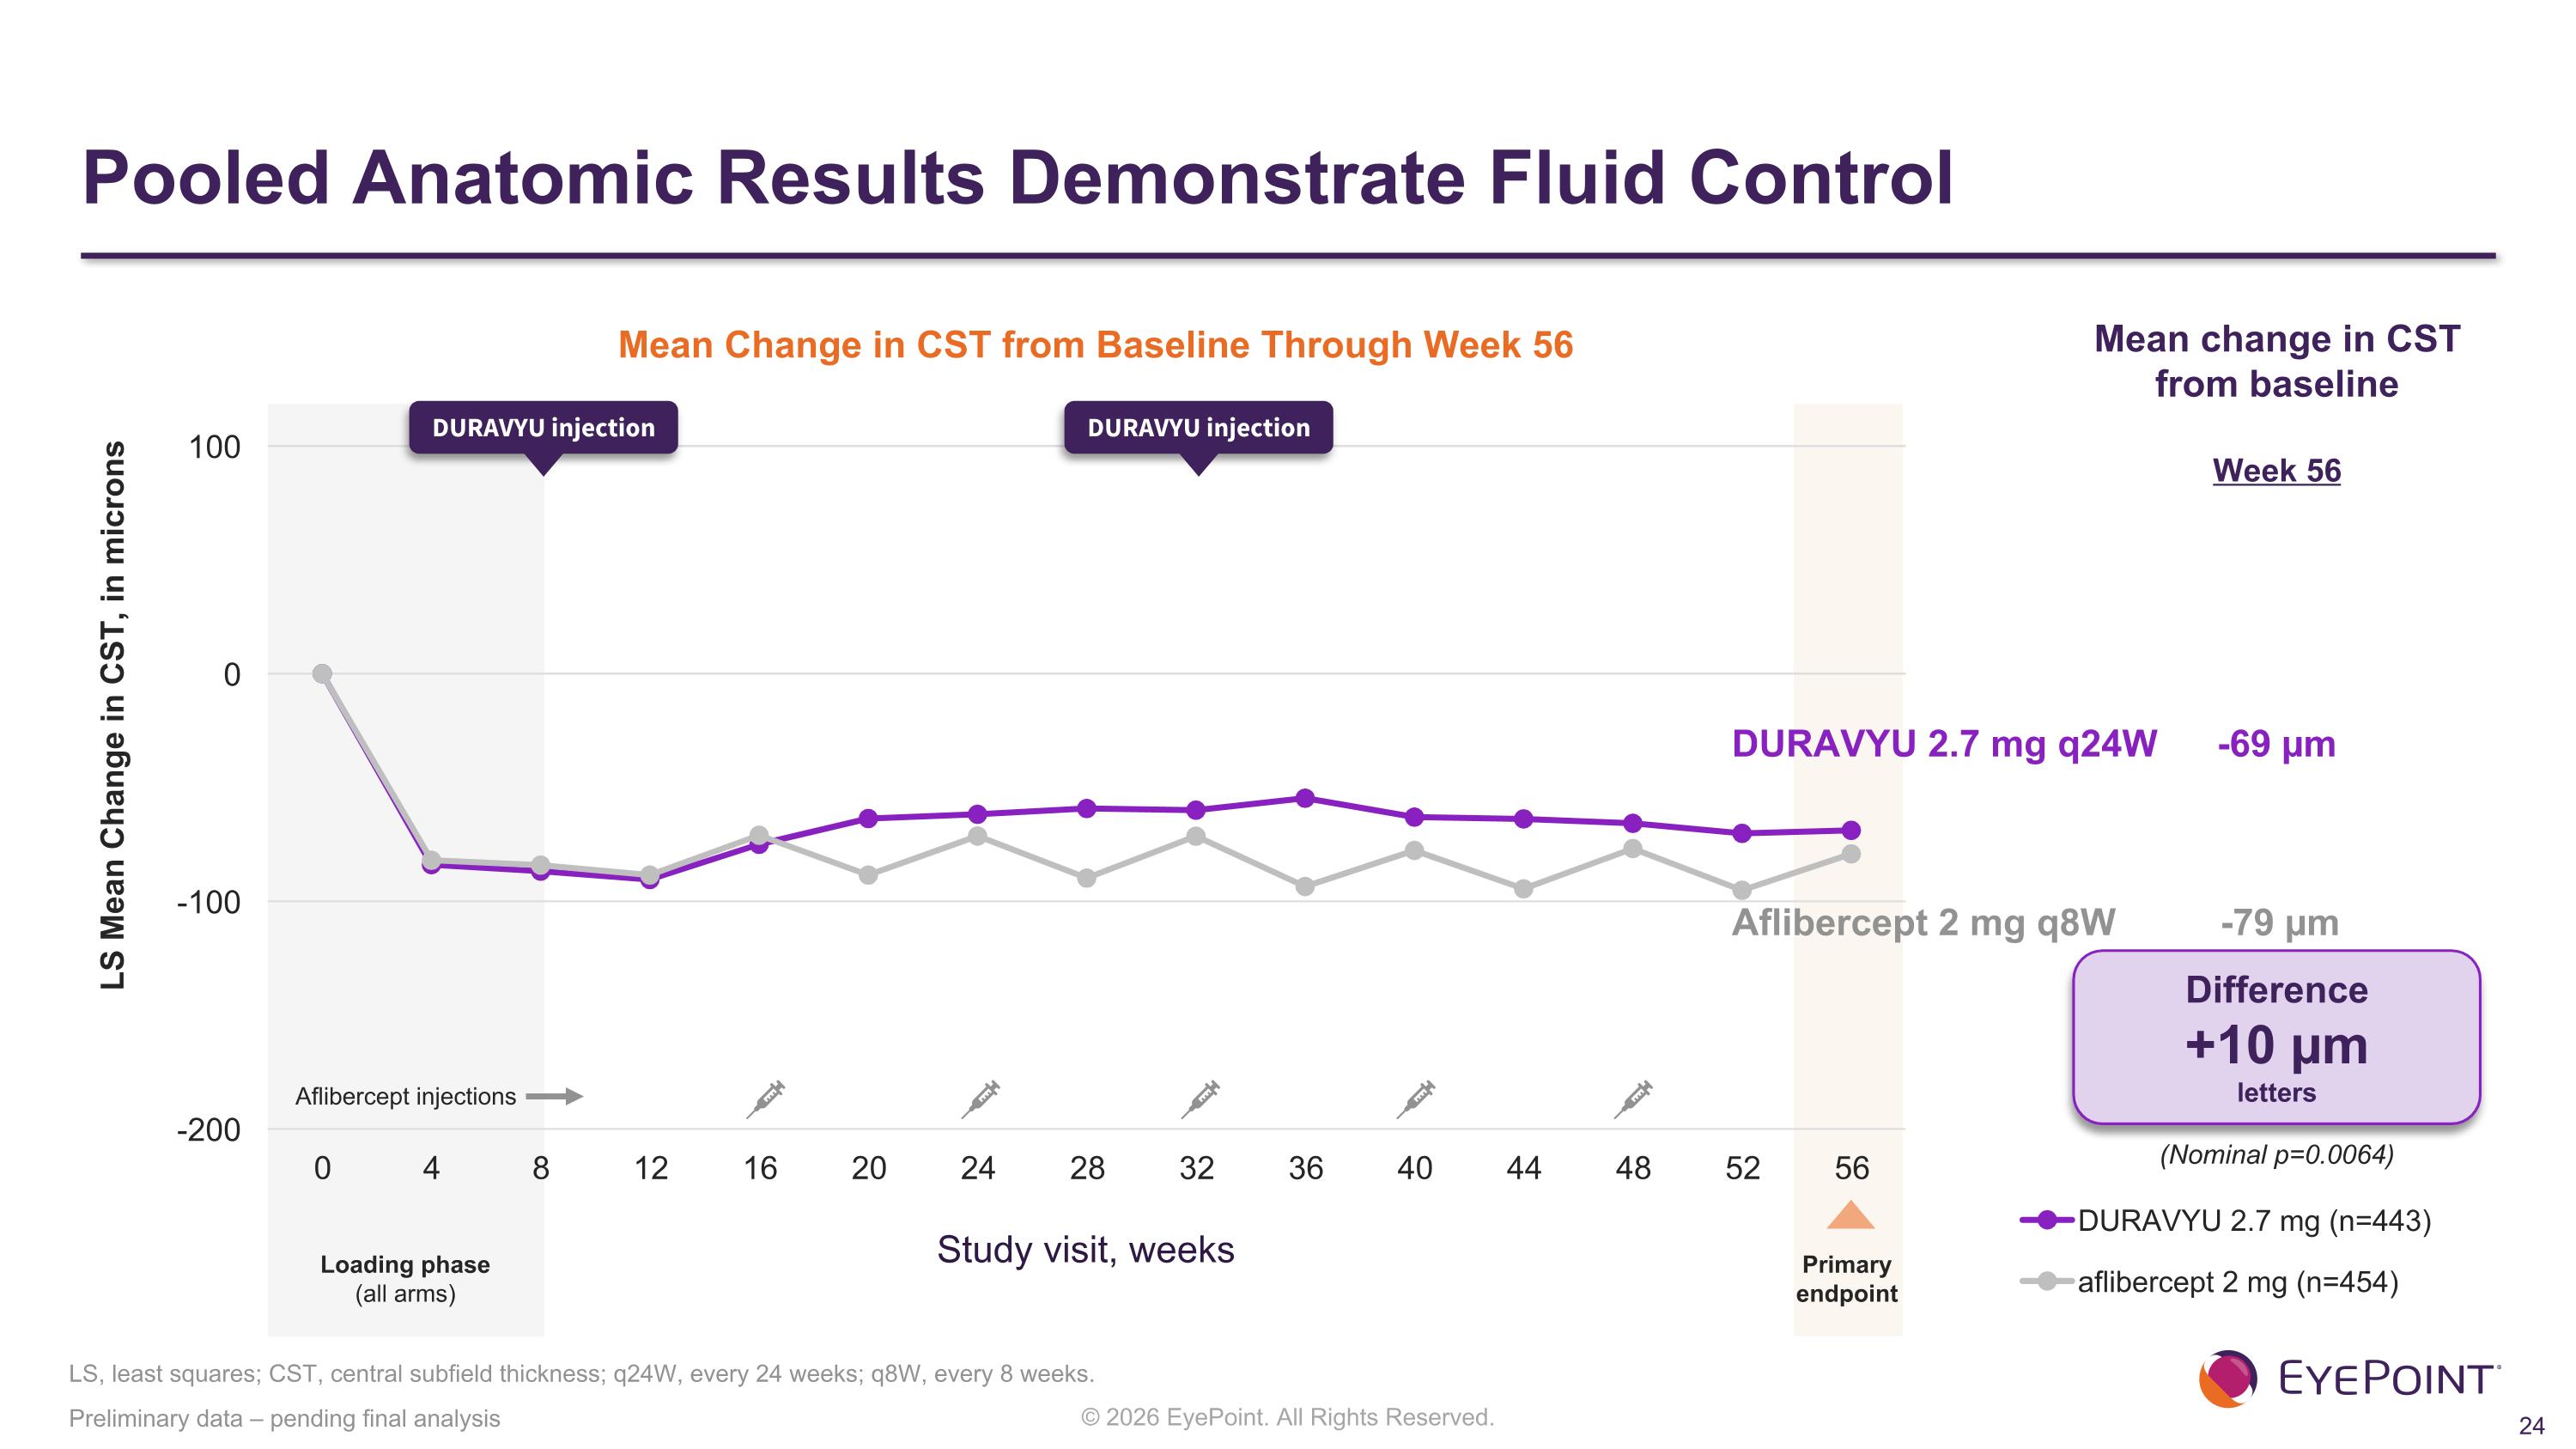
Pooled Anatomic Results Demonstrate Fluid Control Preliminary data – pending final analysis LS Mean Change in CST, in microns Mean Change in CST from Baseline Through Week 56 Study visit, weeks Aflibercept 2 mg q8W -79 µm DURAVYU 2.7 mg q24W -69 µm Difference +10 µm letters Loading phase (all arms) DURAVYU injection DURAVYU injection Mean change in CST from baseline Week 56 Aflibercept injections (Nominal p=0.0064) LS, least squares; CST, central subfield thickness; q24W, every 24 weeks; q8W, every 8 weeks. Primary endpoint
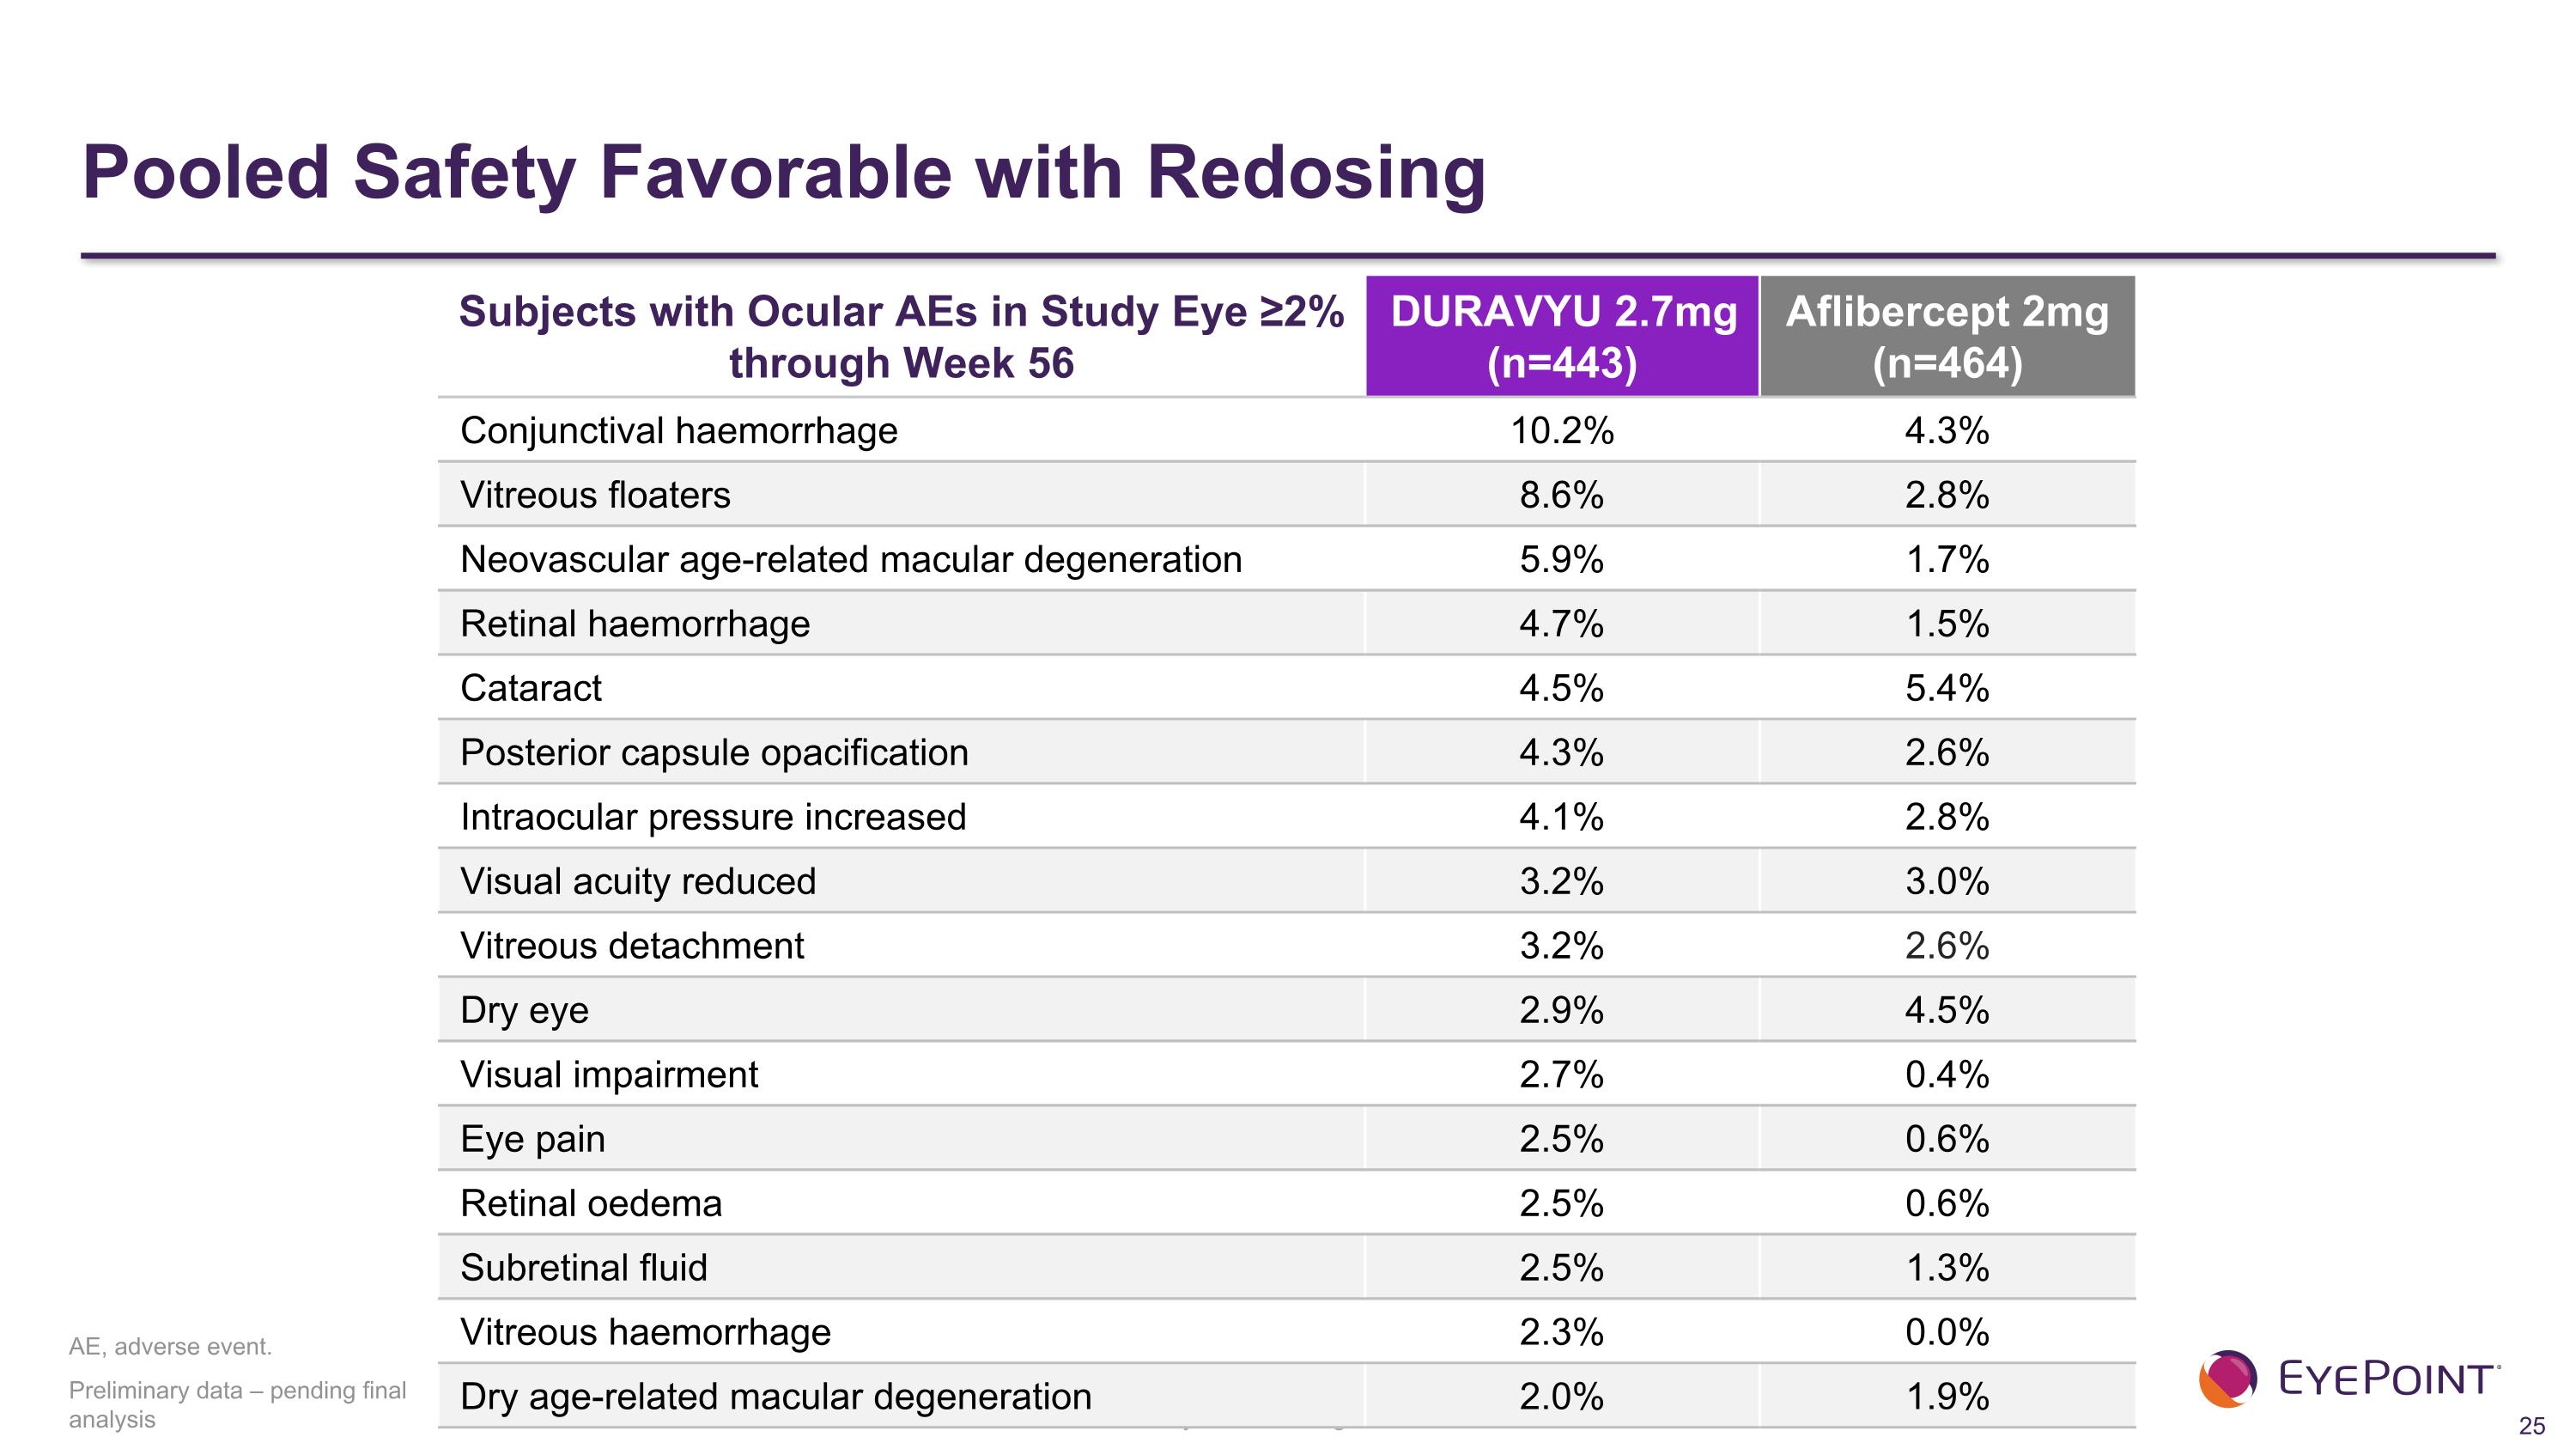
Preliminary data – pending final analysis Subjects with Ocular AEs in Study Eye ≥2% through Week 56 DURAVYU 2.7mg (n=443) Aflibercept 2mg (n=464) Conjunctival haemorrhage 10.2% 4.3% Vitreous floaters 8.6% 2.8% Neovascular age-related macular degeneration 5.9% 1.7% Retinal haemorrhage 4.7% 1.5% Cataract 4.5% 5.4% Posterior capsule opacification 4.3% 2.6% Intraocular pressure increased 4.1% 2.8% Visual acuity reduced 3.2% 3.0% Vitreous detachment 3.2% 2.6% Dry eye 2.9% 4.5% Visual impairment 2.7% 0.4% Eye pain 2.5% 0.6% Retinal oedema 2.5% 0.6% Subretinal fluid 2.5% 1.3% Vitreous haemorrhage 2.3% 0.0% Dry age-related macular degeneration 2.0% 1.9% AE, adverse event. Pooled Safety Favorable with Redosing

Review of DME Program
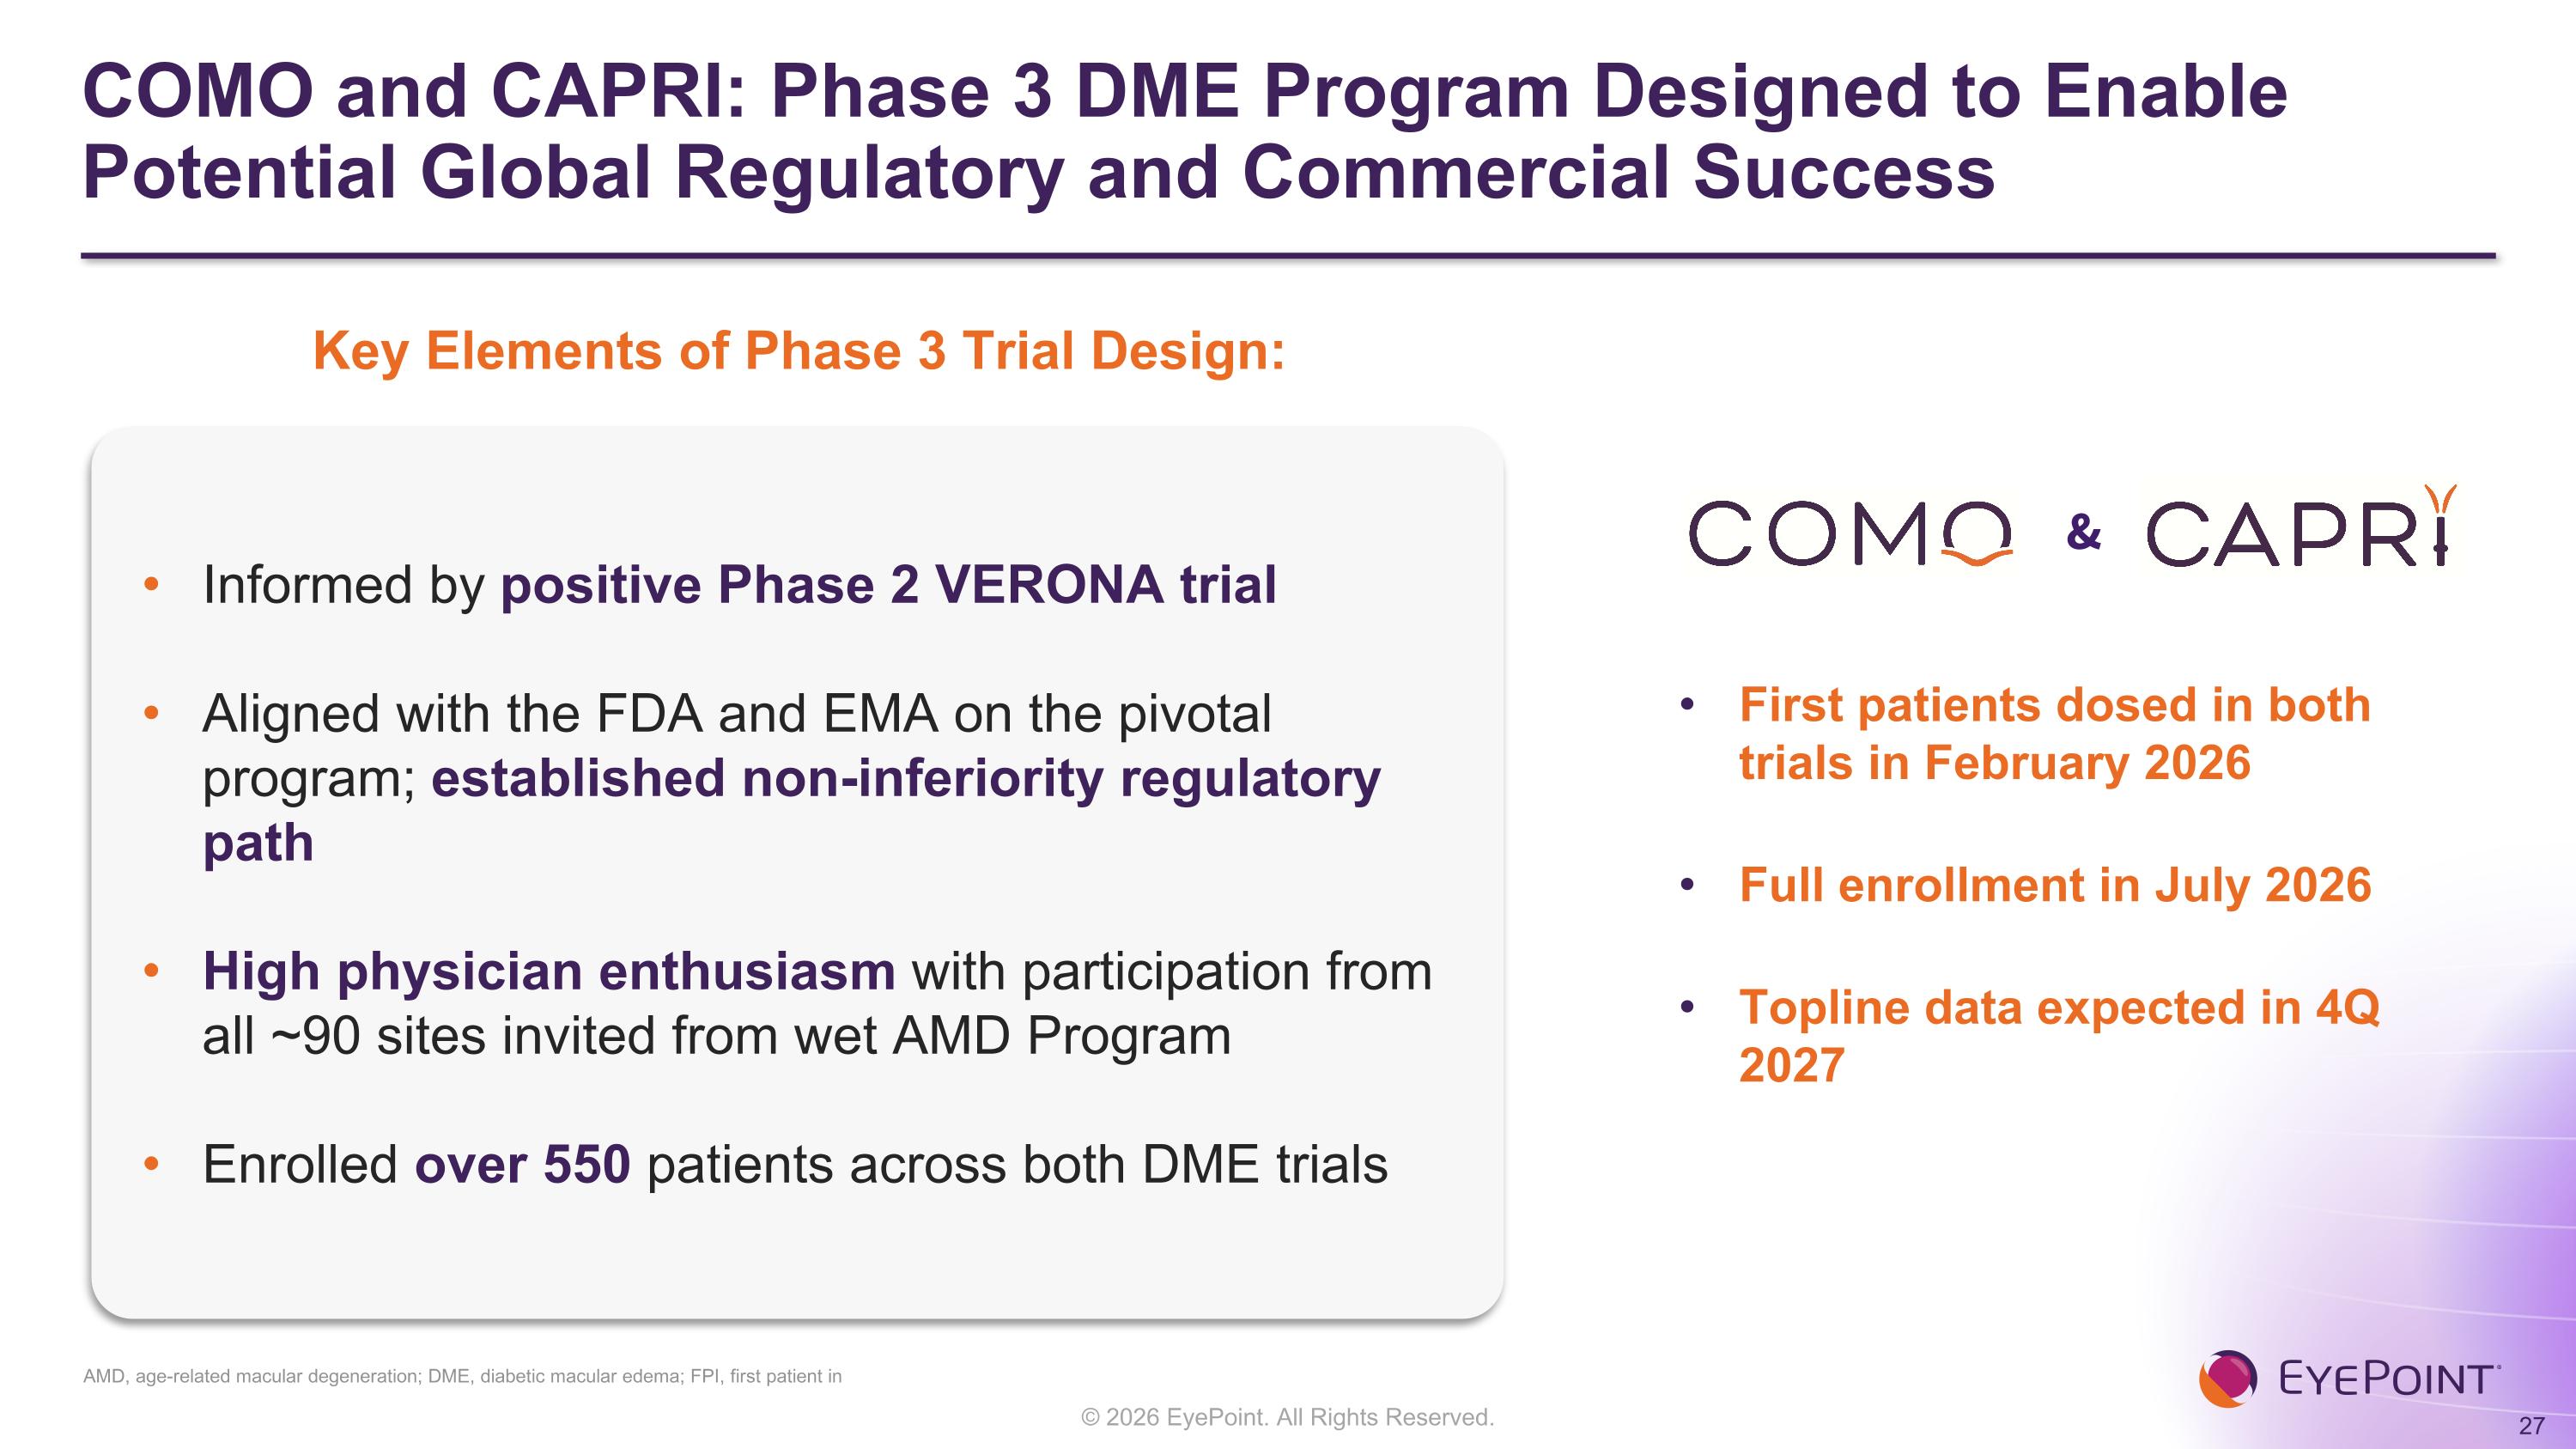
COMO and CAPRI: Phase 3 DME Program Designed to Enable Potential Global Regulatory and Commercial Success First patients dosed in both trials in February 2026 Full enrollment in July 2026 Topline data expected in 4Q 2027 Key Elements of Phase 3 Trial Design: Informed by positive Phase 2 VERONA trial Aligned with the FDA and EMA on the pivotal program; established non-inferiority regulatory path High physician enthusiasm with participation from all ~90 sites invited from wet AMD Program Enrolled over 550 patients across both DME trials & AMD, age-related macular degeneration; DME, diabetic macular edema; FPI, first patient in
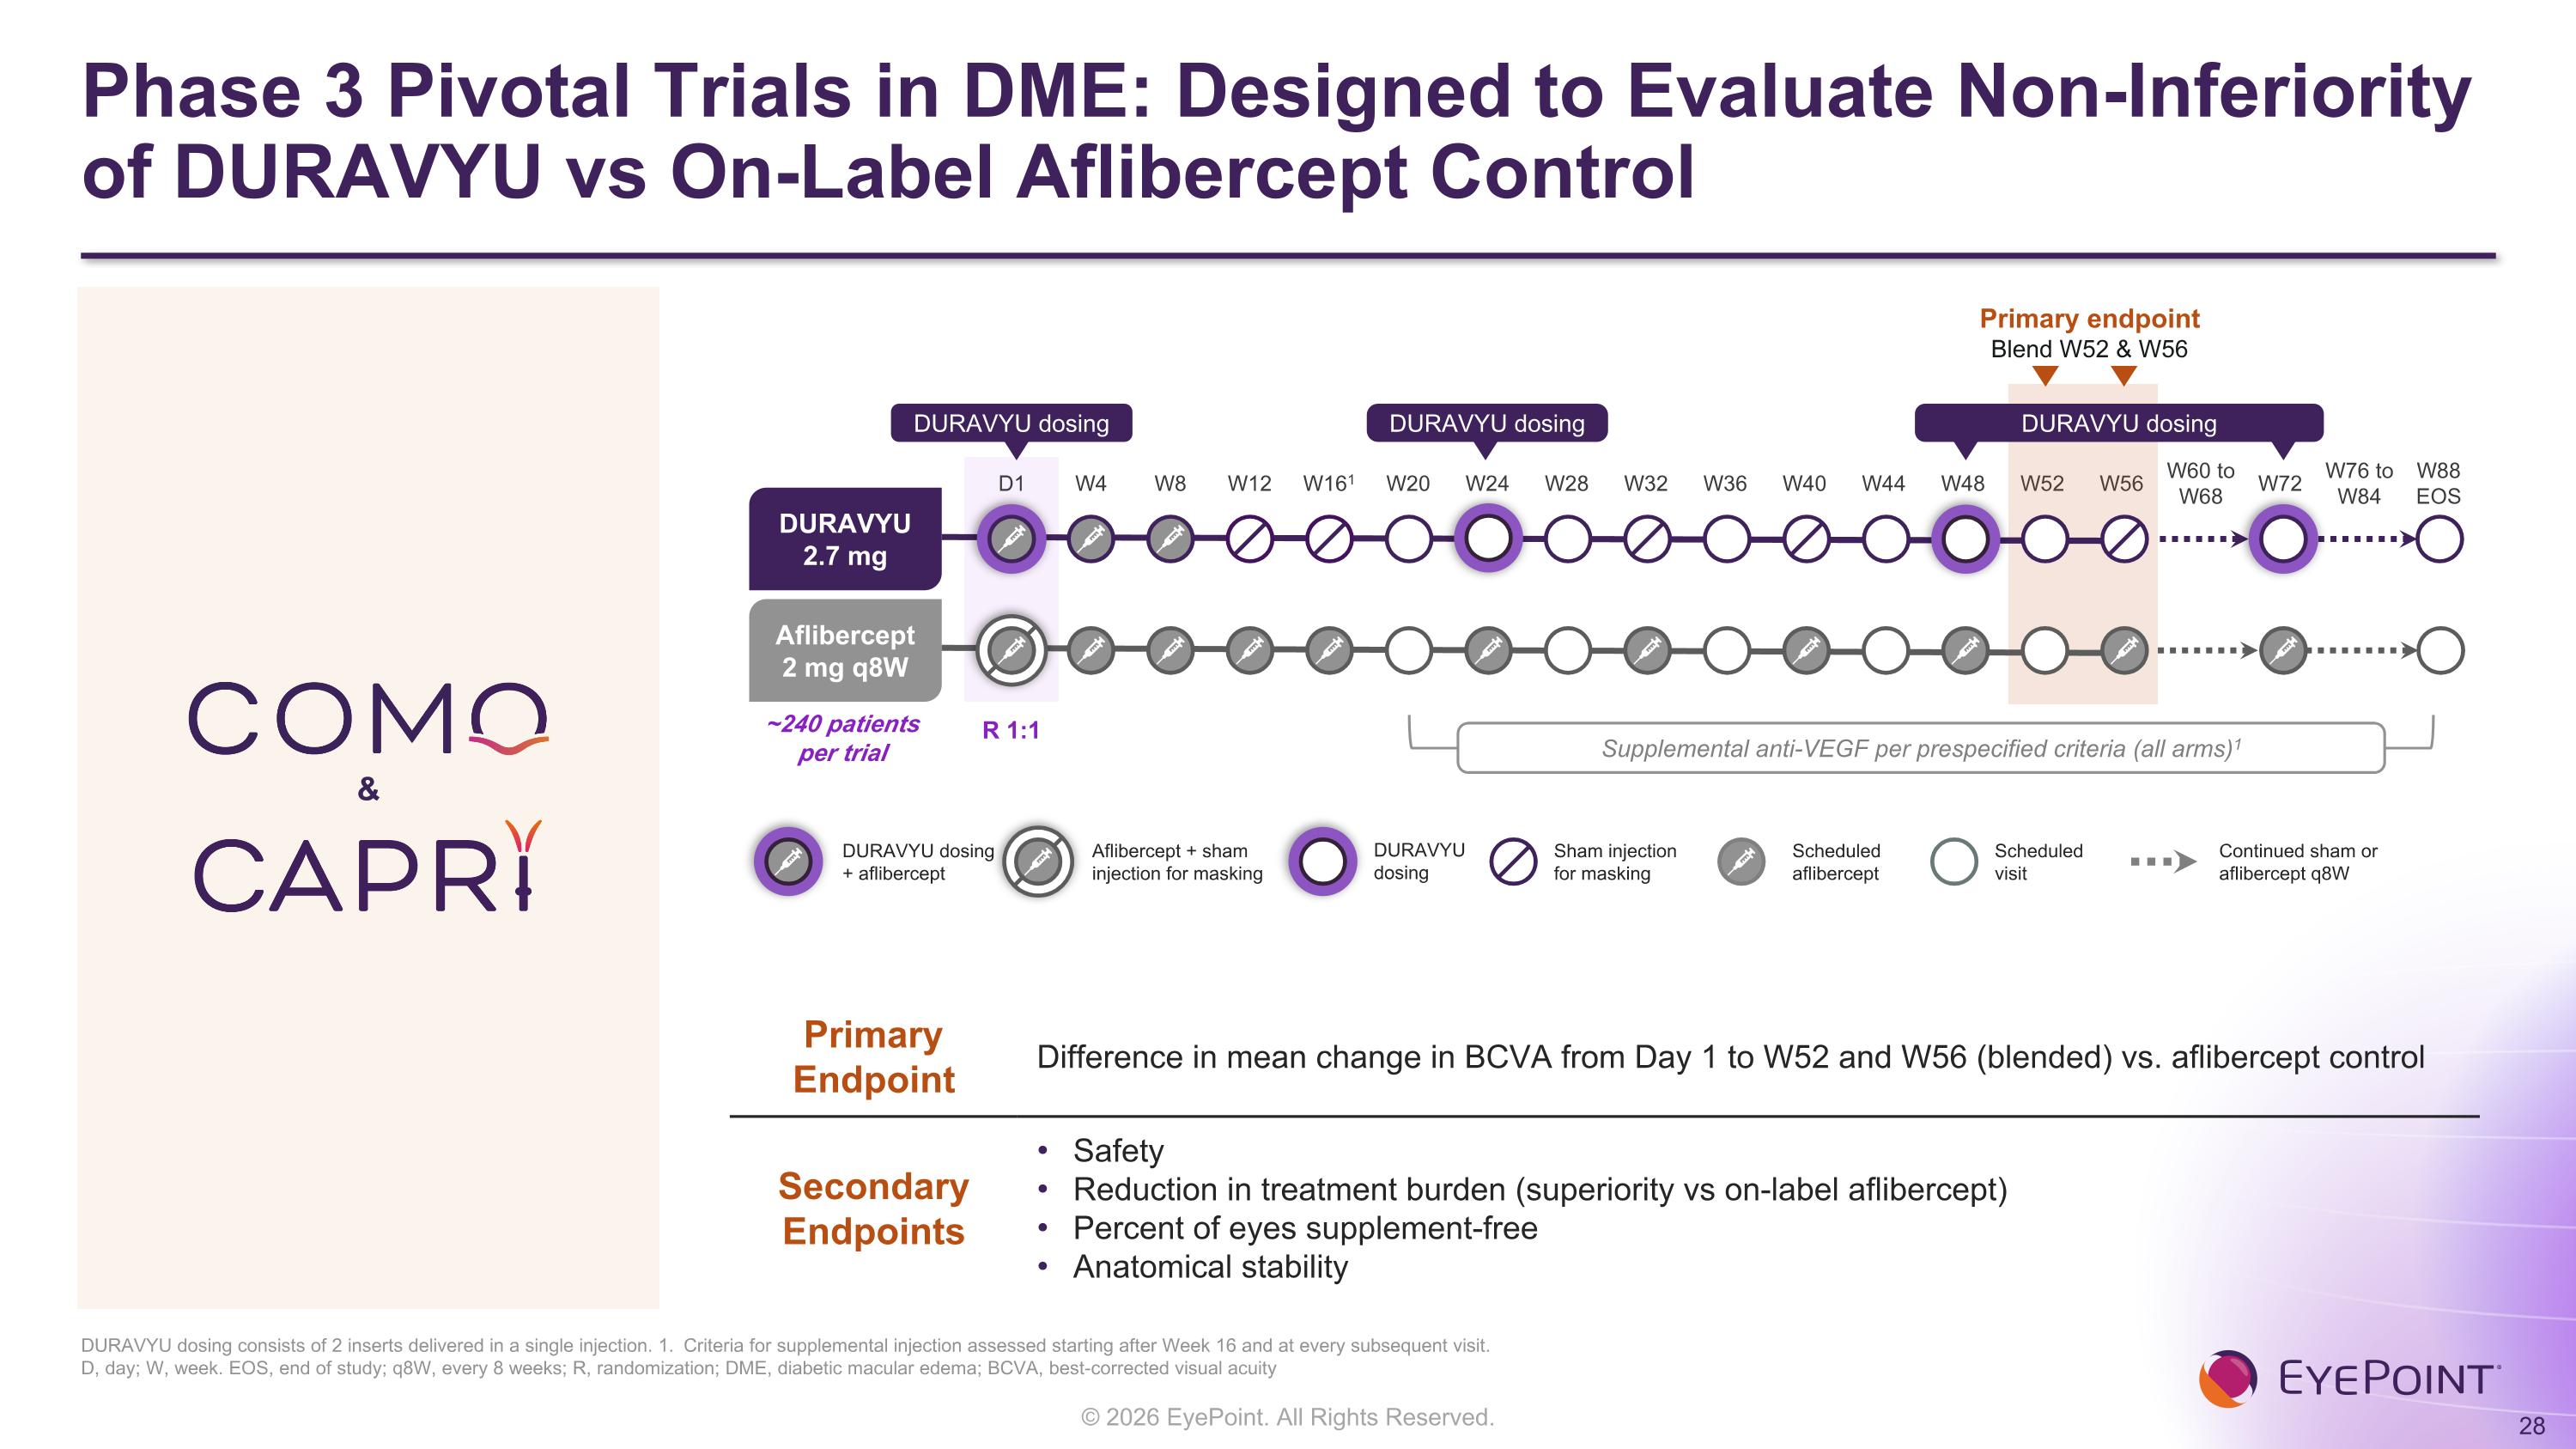
Phase 3 Pivotal Trials in DME: Designed to Evaluate Non-Inferiority of DURAVYU vs On-Label Aflibercept Control D1 W4 W8 W12 W161 W20 W24 W28 W32 W36 W40 W44 W48 W52 W56 W60 to W68 W72 W76 to W84 W88 EOS Primary endpoint Blend W52 & W56 DURAVYU 2.7 mg Aflibercept 2 mg q8W DURAVYU dosing DURAVYU dosing DURAVYU dosing ~240 patients per trial R 1:1 Supplemental anti-VEGF per prespecified criteria (all arms)1 Scheduled aflibercept Scheduled visit Sham injection for masking Continued sham or aflibercept q8W DURAVYU dosing + aflibercept Aflibercept + sham injection for masking DURAVYU dosing Primary Endpoint Difference in mean change in BCVA from Day 1 to W52 and W56 (blended) vs. aflibercept control Secondary Endpoints Safety Reduction in treatment burden (superiority vs on-label aflibercept) Percent of eyes supplement-free Anatomical stability DURAVYU dosing consists of 2 inserts delivered in a single injection. 1. Criteria for supplemental injection assessed starting after Week 16 and at every subsequent visit. D, day; W, week. EOS, end of study; q8W, every 8 weeks; R, randomization; DME, diabetic macular edema; BCVA, best-corrected visual acuity &
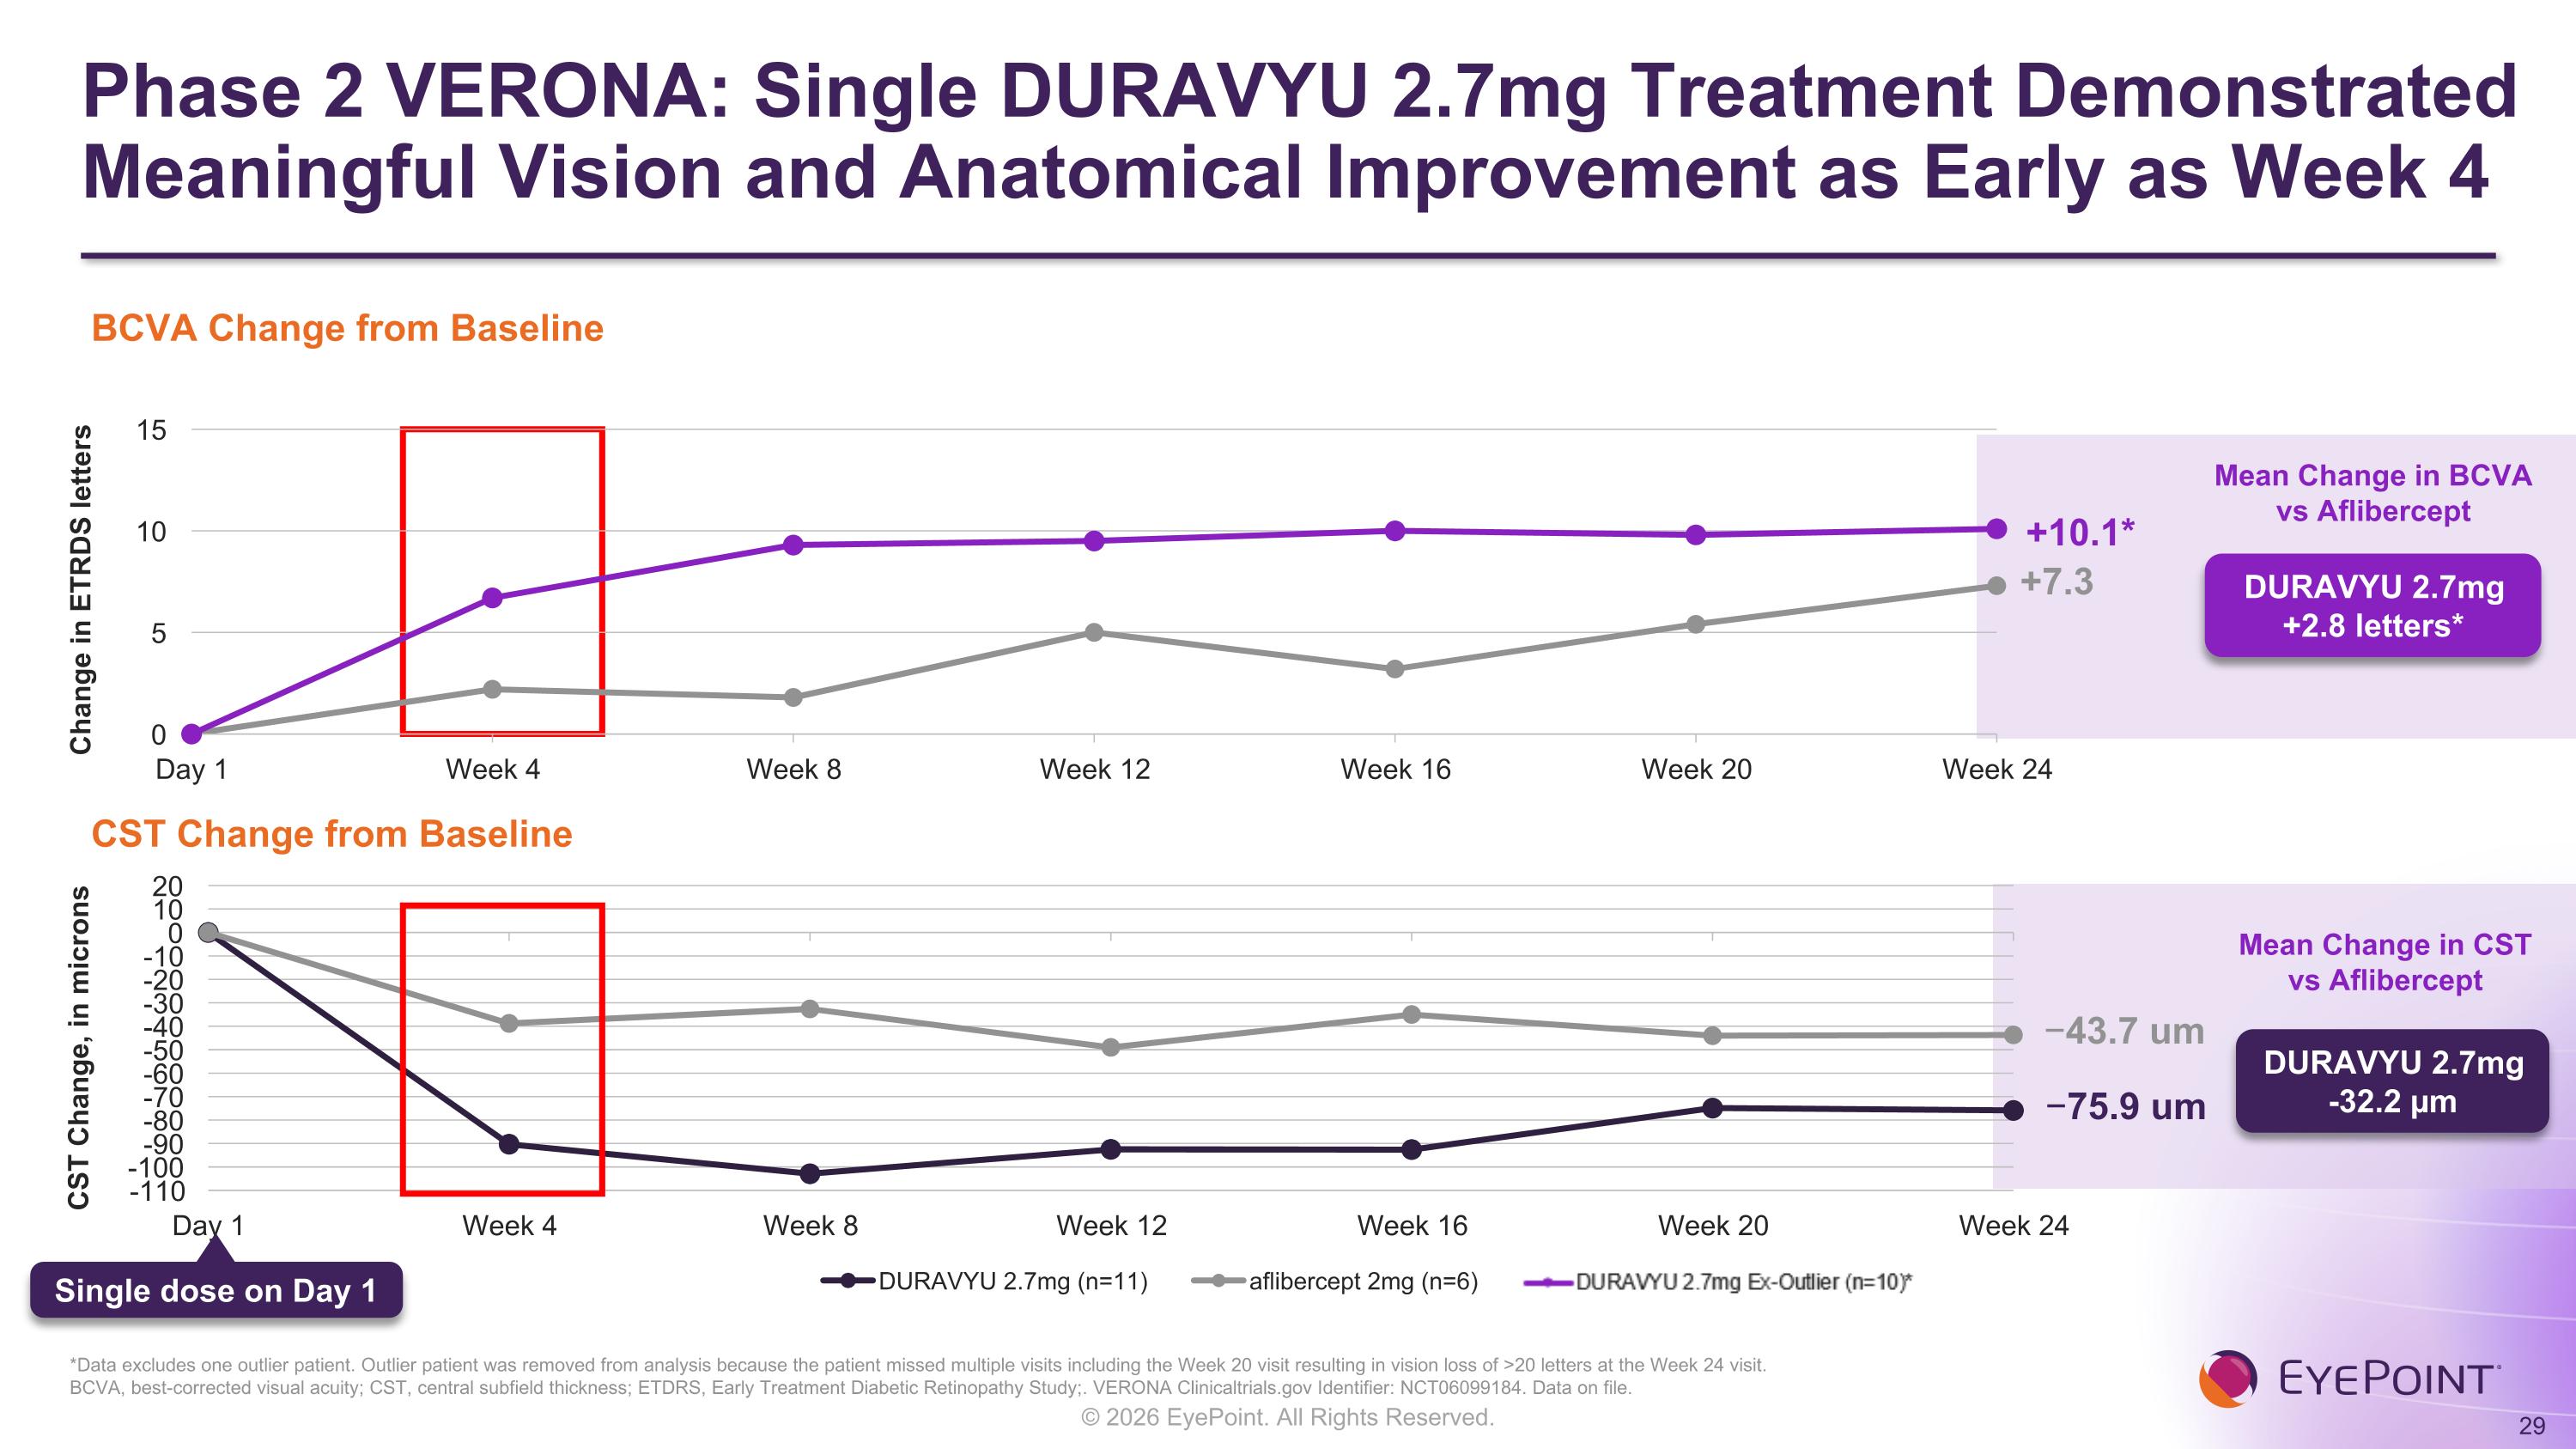
DURAVYU 2.7mg +2.8 letters* Phase 2 VERONA: Single DURAVYU 2.7mg Treatment Demonstrated Meaningful Vision and Anatomical Improvement as Early as Week 4 BCVA, best-corrected visual acuity; CST, central subfield thickness; ETDRS, Early Treatment Diabetic Retinopathy Study;. VERONA Clinicaltrials.gov Identifier: NCT06099184. Data on file. Mean Change in BCVA vs Aflibercept +7.3 −75.9 um −43.7 um Mean Change in CST vs Aflibercept DURAVYU 2.7mg -32.2 µm Single dose on Day 1 BCVA Change from Baseline CST Change from Baseline +10.1* *Data excludes one outlier patient. Outlier patient was removed from analysis because the patient missed multiple visits including the Week 20 visit resulting in vision loss of >20 letters at the Week 24 visit. Change in ETRDS letters
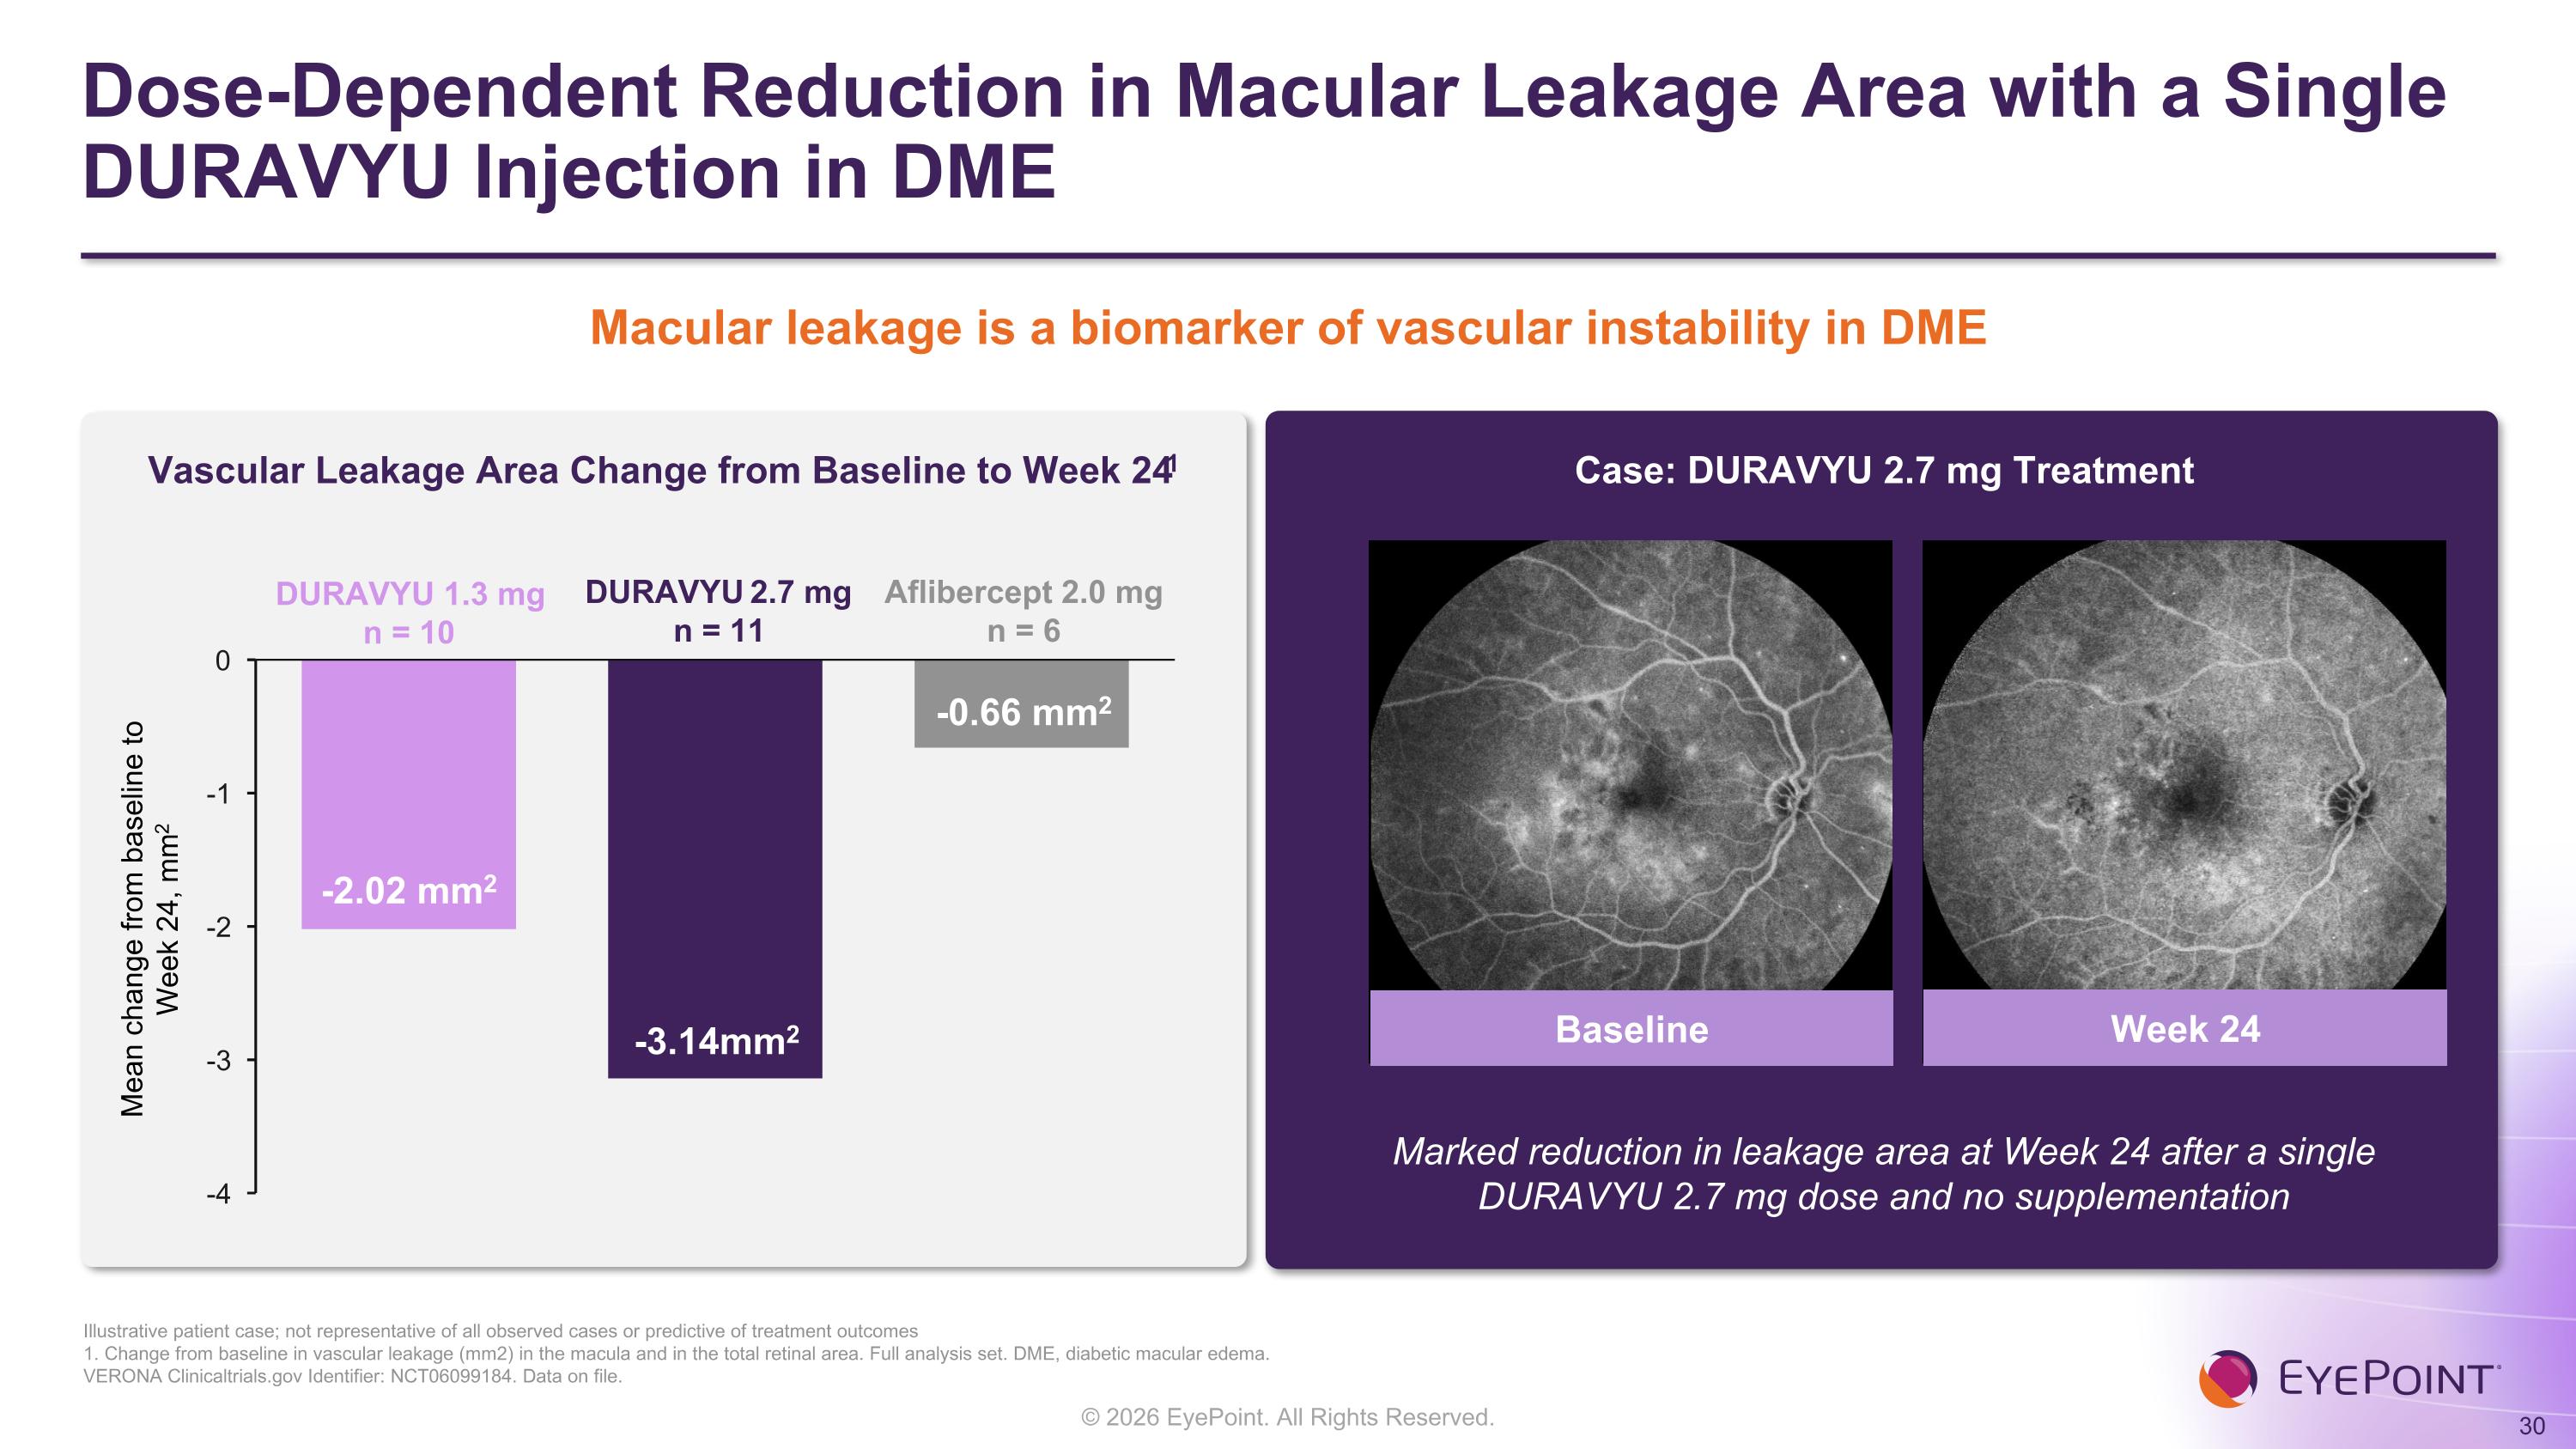
Dose-Dependent Reduction in Macular Leakage Area with a Single DURAVYU Injection in DME Illustrative patient case; not representative of all observed cases or predictive of treatment outcomes 1. Change from baseline in vascular leakage (mm2) in the macula and in the total retinal area. Full analysis set. DME, diabetic macular edema. VERONA Clinicaltrials.gov Identifier: NCT06099184. Data on file. Vascular Leakage Area Change from Baseline to Week 241 Case: DURAVYU 2.7 mg Treatment Mean change from baseline to Week 24, mm2 DURAVYU 1.3 mg n = 10 Baseline Week 24 Marked reduction in leakage area at Week 24 after a single DURAVYU 2.7 mg dose and no supplementation DURAVYU 2.7 mg n = 11 Aflibercept 2.0 mg n = 6 Macular leakage is a biomarker of vascular instability in DME -2.02 mm2 -3.14mm2 -0.66 mm2
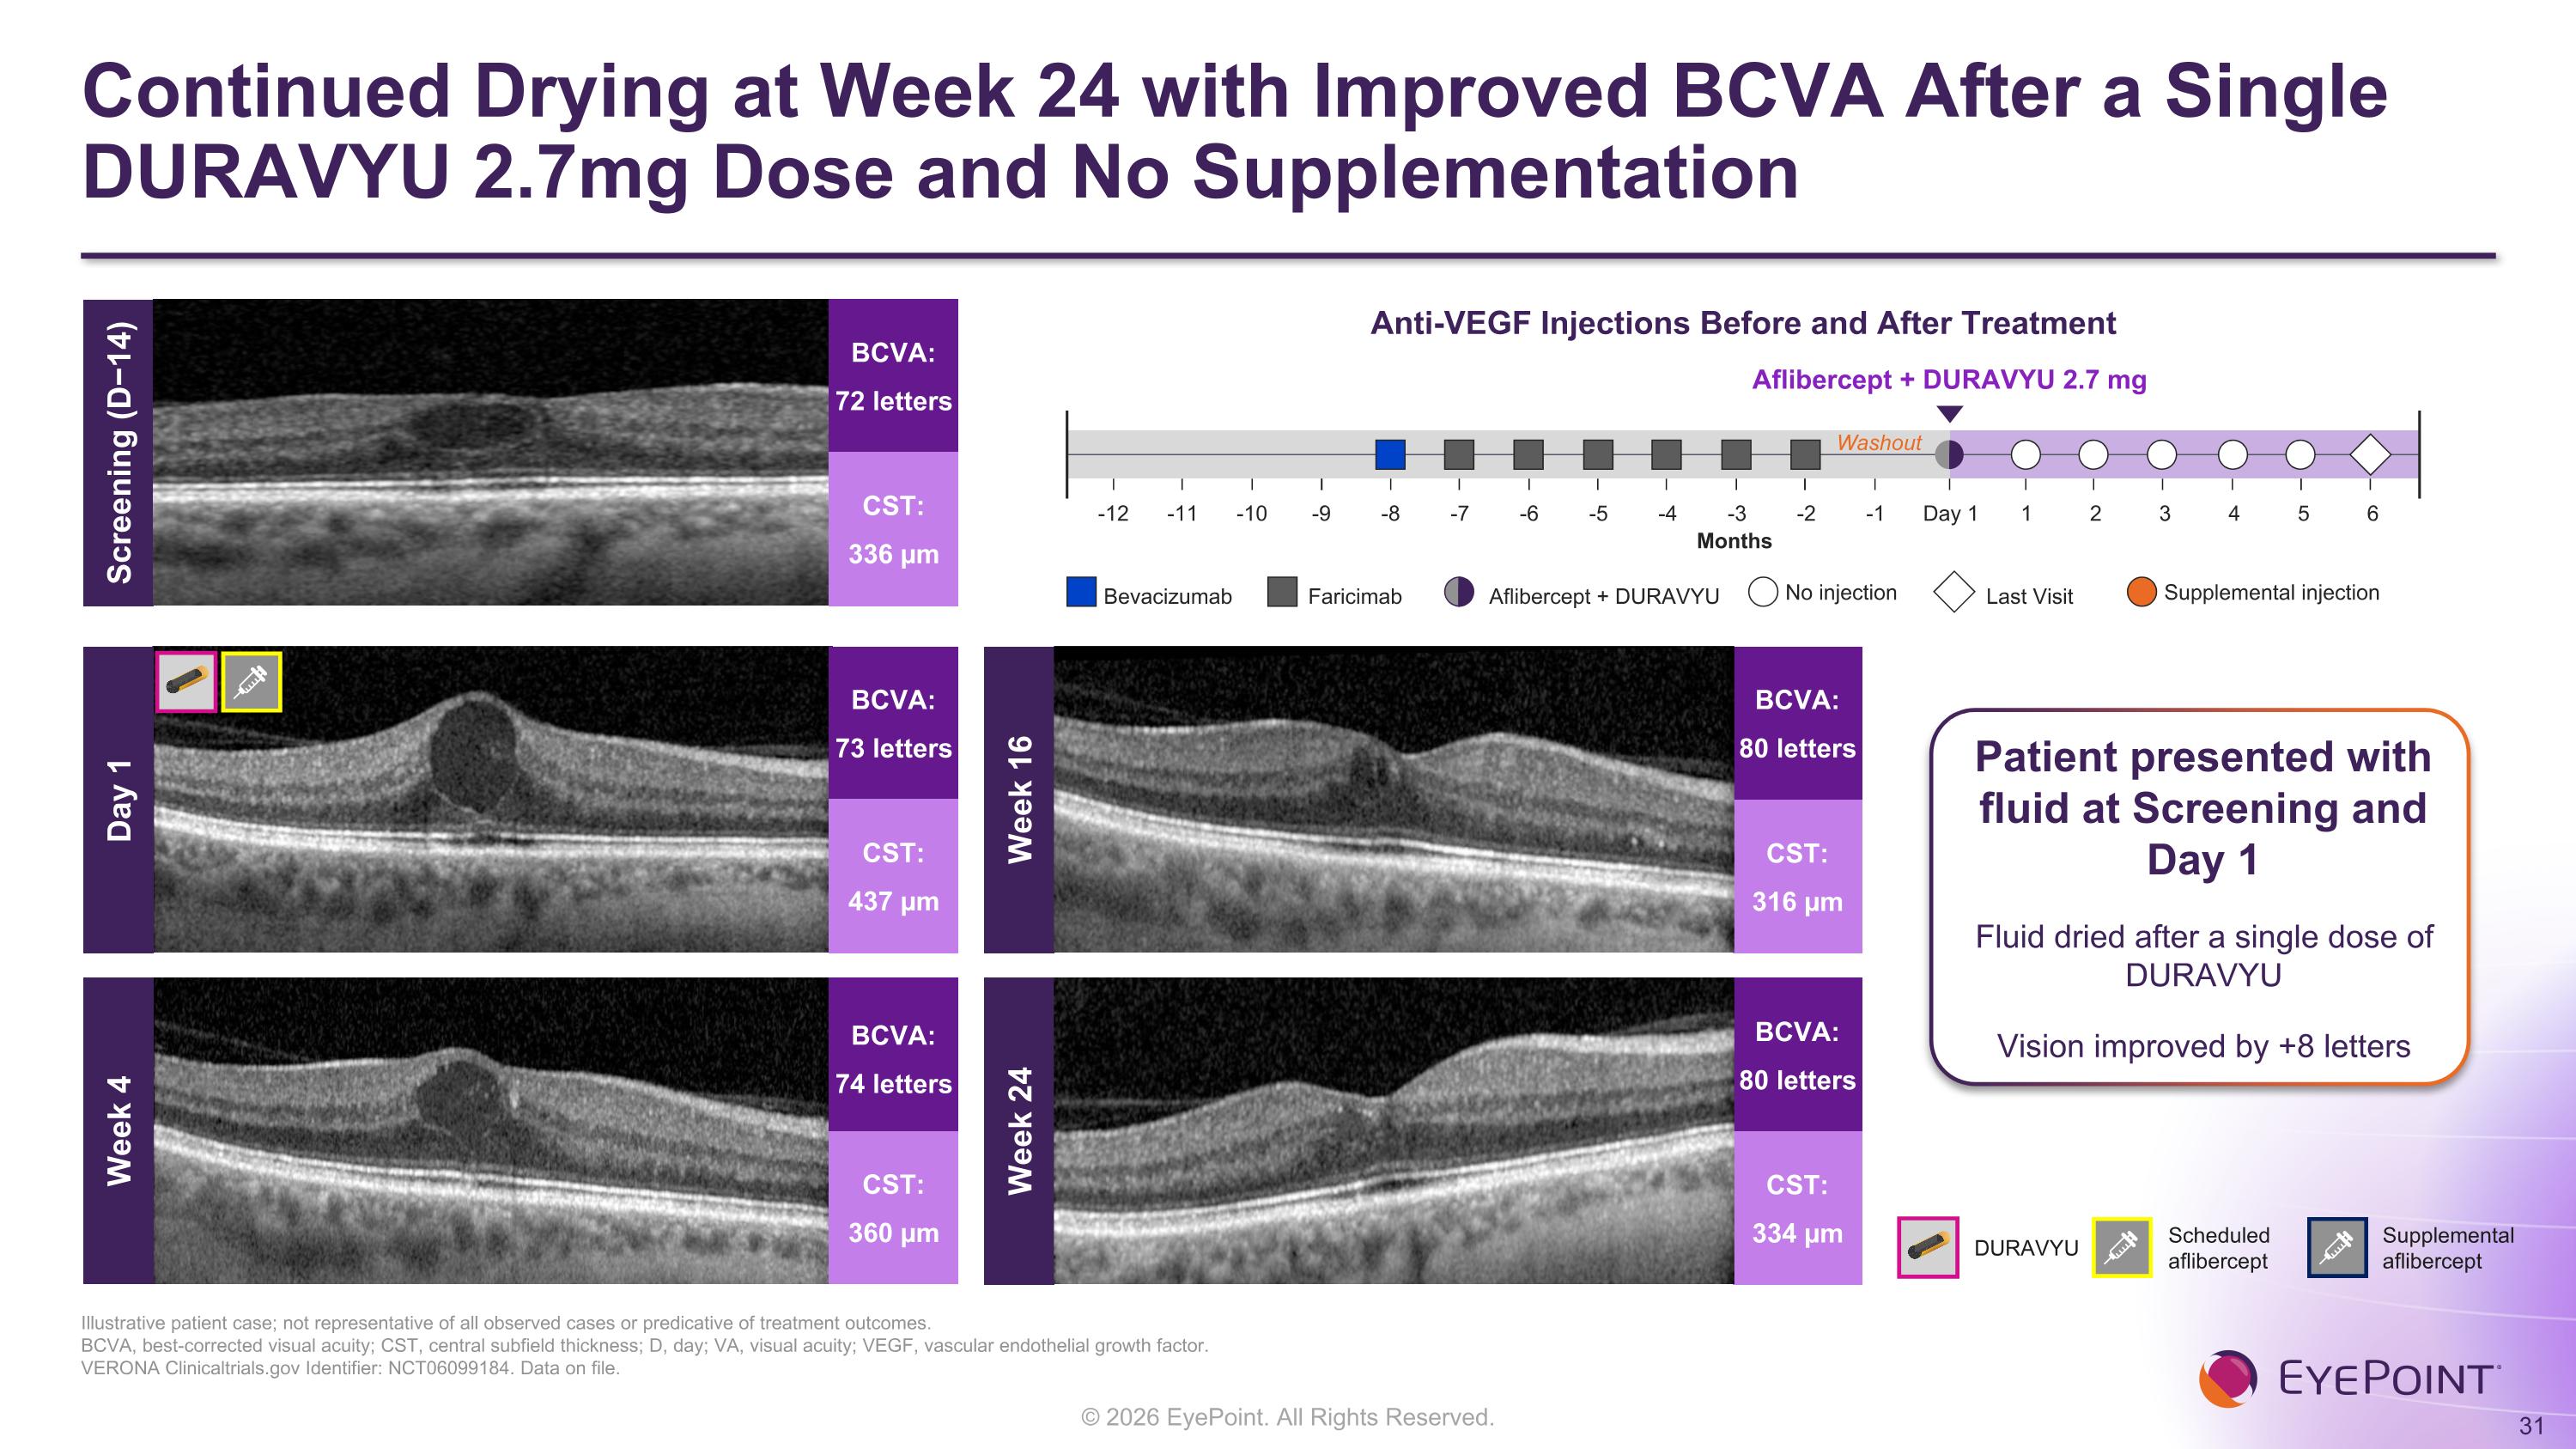
Continued Drying at Week 24 with Improved BCVA After a Single DURAVYU 2.7mg Dose and No Supplementation Illustrative patient case; not representative of all observed cases or predicative of treatment outcomes. BCVA, best-corrected visual acuity; CST, central subfield thickness; D, day; VA, visual acuity; VEGF, vascular endothelial growth factor. VERONA Clinicaltrials.gov Identifier: NCT06099184. Data on file. Week 4 BCVA: 74 letters CST: 360 µm Week 16 BCVA: 80 letters CST: 316 µm Week 24 BCVA: 80 letters CST: 334 µm Anti-VEGF Injections Before and After Treatment Aflibercept + DURAVYU 2.7 mg Months Washout Day 1 2 1 4 5 6 3 -1 -3 -2 -5 -4 -7 -6 -8 -10 -9 -12 -11 Bevacizumab No injection Supplemental injection Faricimab Last Visit Aflibercept + DURAVYU Patient presented with fluid at Screening and Day 1 Fluid dried after a single dose of DURAVYU Vision improved by +8 letters Screening (D−14) BCVA: 72 letters CST: 336 µm DURAVYU Scheduled aflibercept Supplemental aflibercept BCVA: 73 letters CST: 437 µm Day 1

Conclusions & Next Steps
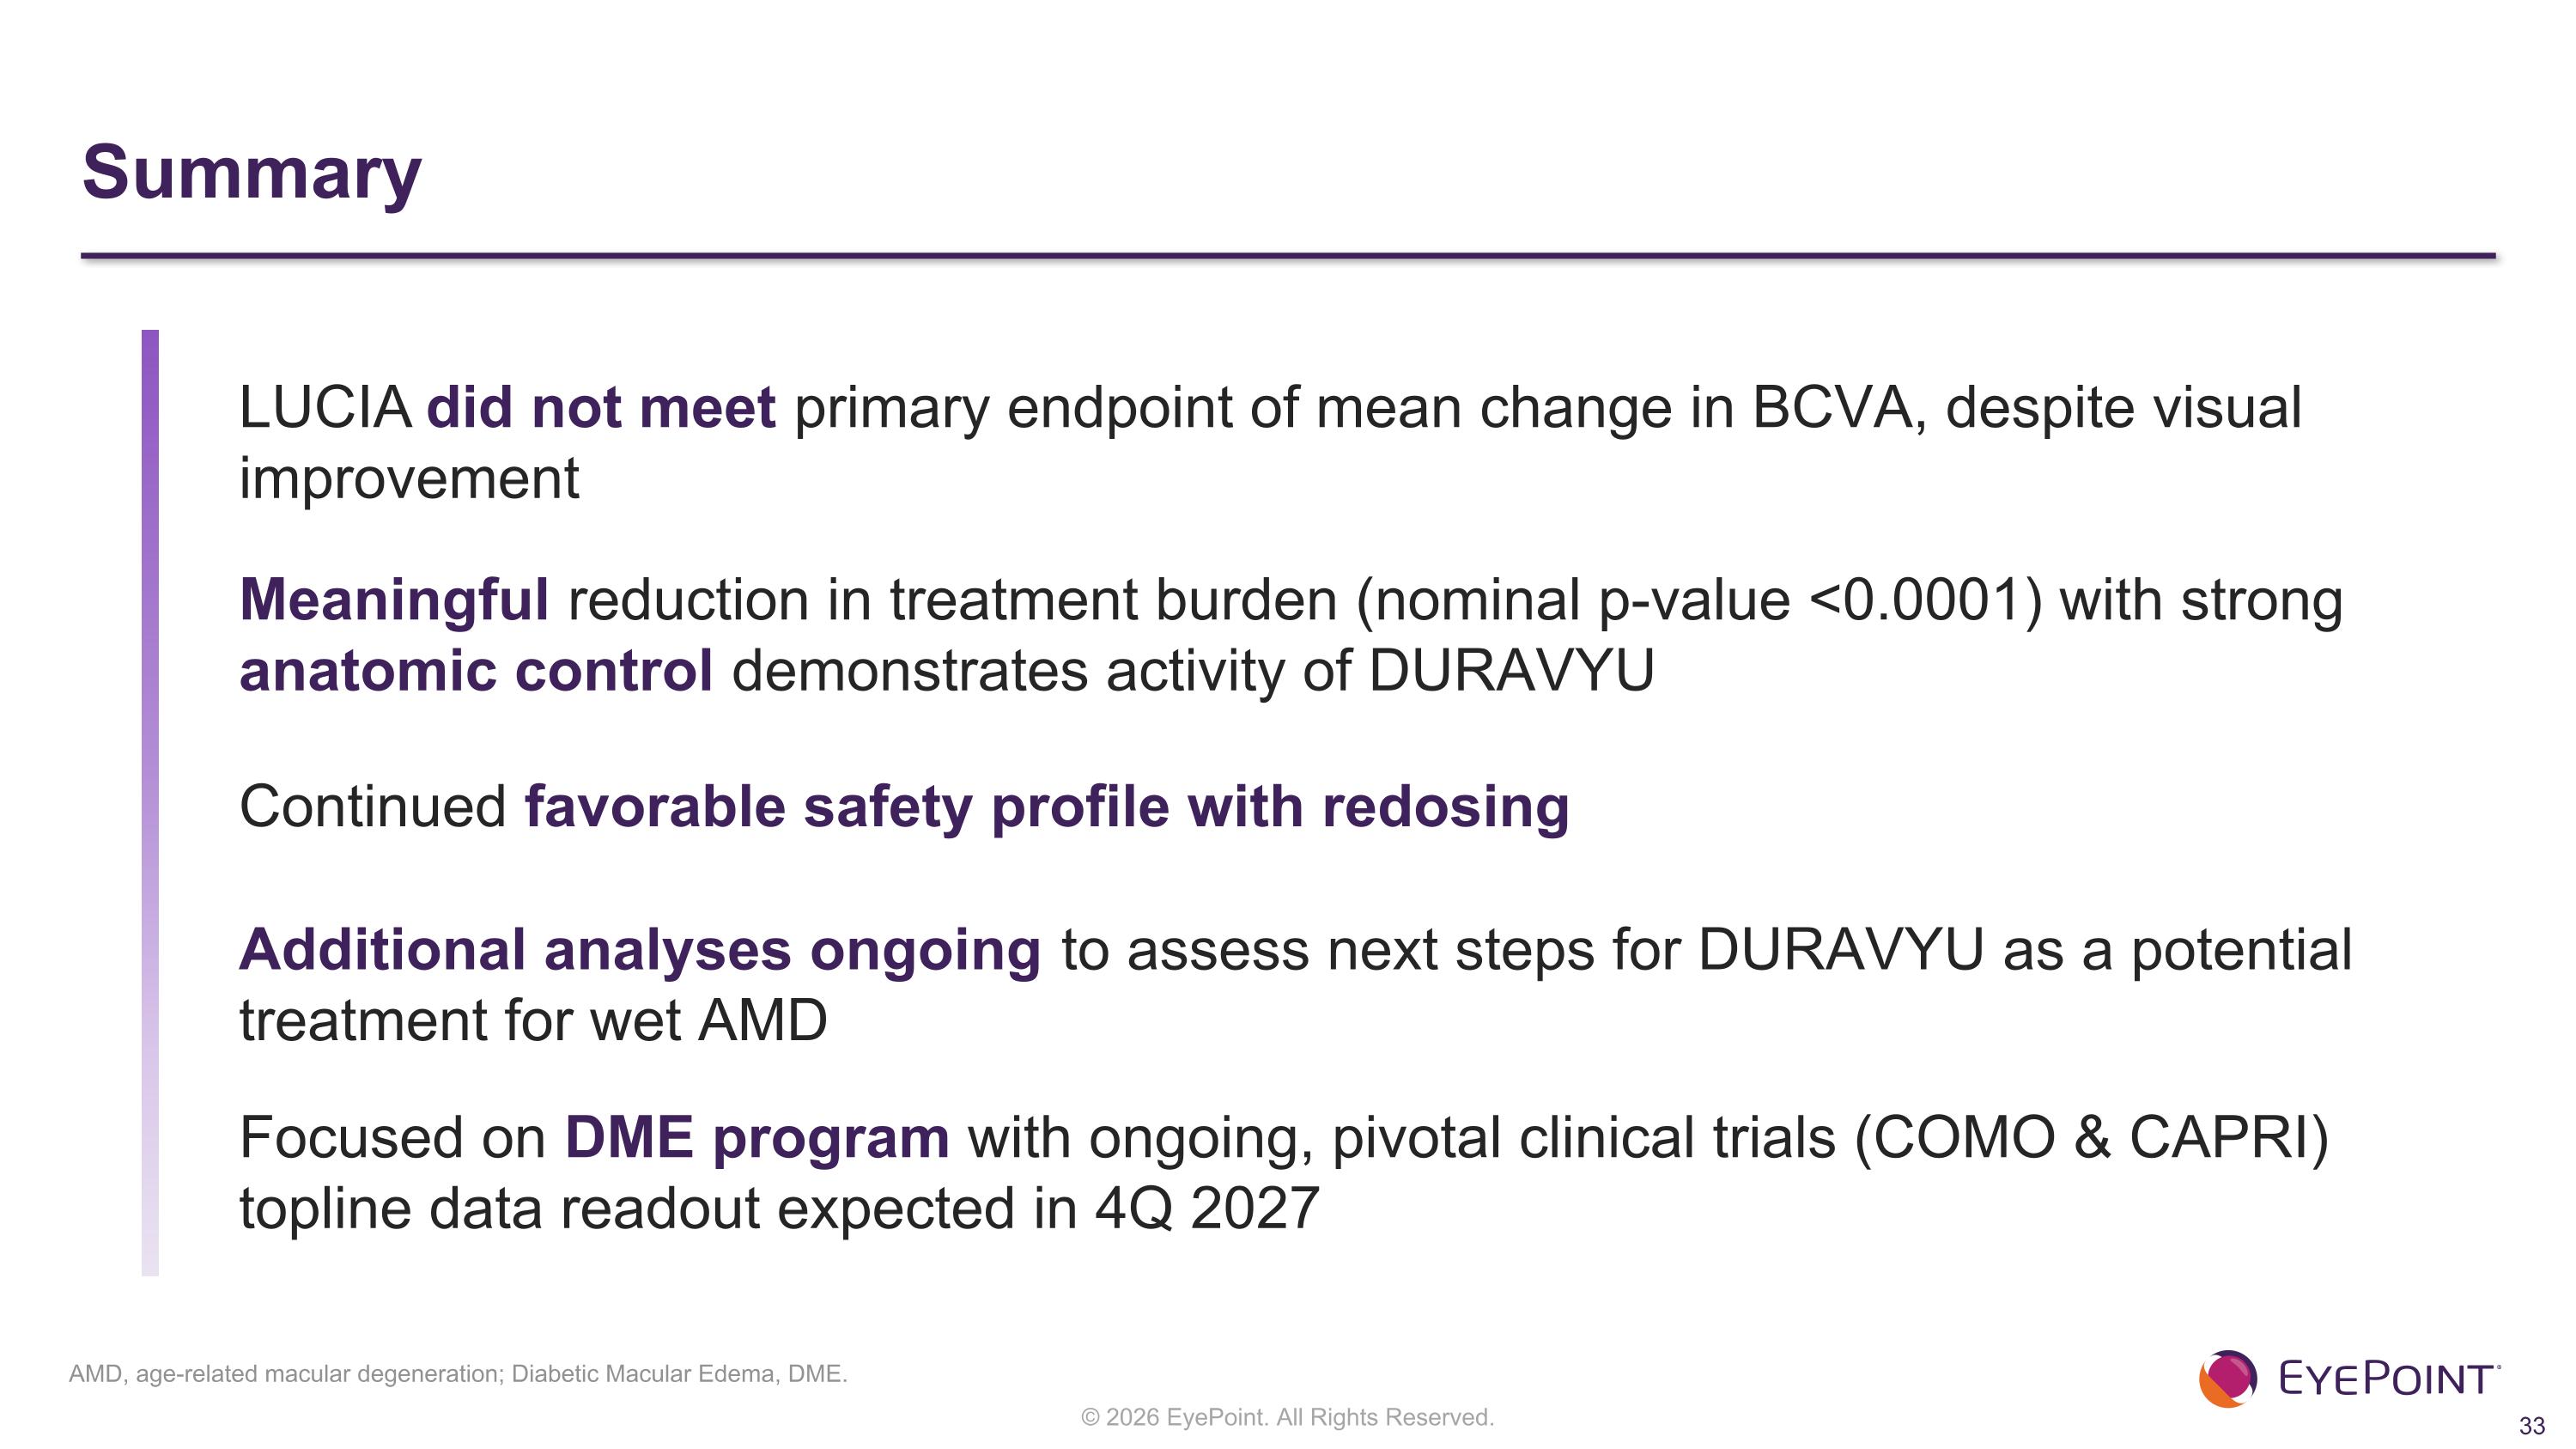
Summary LUCIA did not meet primary endpoint of mean change in BCVA, despite visual improvement Meaningful reduction in treatment burden (nominal p-value <0.0001) with strong anatomic control demonstrates activity of DURAVYU Continued favorable safety profile with redosing Additional analyses ongoing to assess next steps for DURAVYU as a potential treatment for wet AMD Focused on DME program with ongoing, pivotal clinical trials (COMO & CAPRI) topline data readout expected in 4Q 2027 AMD, age-related macular degeneration; Diabetic Macular Edema, DME.

LUCIA Phase 3 Clinical Trial DURAVYU in Wet AMD Topline Results | October 2026