
Exhibit 99.2
Company Overview SEPTEMBER 2026

2 Disclaimer This presentation (together with any information communicated orally in connection herewith, this "Presentation") is being pr ovi ded by North Immunology, Inc. ("North" or the "Company") on a confidential basis solely for informational purposes in connection with a proposed private placement of securities (the "Priv ate Placement") to be conducted concurrently with a proposed business combination between North and Aethlon Medical, Inc. (Nasdaq: AEMD) (“AEMD") pursuant to which a successor entity to Nor th would become a wholly owned subsidiary of AEMD (the "Transaction"). By accepting this Presentation, the recipient agrees to keep its contents confidential, not to reproduce or d ist ribute it in whole or in part, and to return or destroy it upon request. This Presentation does not purport to be all - inclusive or to contain all information a prospective investor may require and is q ualified in its entirety by the definitive transaction agreements and the disclosure documents referred to below No Offer or Solicitation This Presentation is not intended to and does not constitute an offer to sell or the solicitation of an offer to buy, subscri be for or purchase any securities, or the solicitation of any proxy, vote, consent or approval, nor shall there be any sale of securities, in any jurisdiction in which such offer, solicitation or sale wo uld be unlawful prior to registration or qualification under the securities laws of any such jurisdiction. The securities to be offered in the Private Placement have not been and will not be registered un der the Securities Act of 1933, as amended (the "Securities Act"), or any state securities laws, are being offered in a transaction not involving a public offering in reliance on the exemption fr om registration provided by Section 4(a)(2) of the Securities Act and Regulation D thereunder, and may not be offered or sold in the United States absent registration or an applicable exemption f rom the registration requirements. Any offer, if made, will be made solely to accredited investors by means of definitive subscription documents. No offer of securities shall be made except by mea ns of a prospectus meeting the requirements of Section 10 of the Securities Act. Additional Information and Where to Find It In connection with the Transaction, AEMD intends to file with the U.S. Securities and Exchange Commission (the "SEC") a regis tra tion statement on Form S - 4 (the "S - 4") that will contain a proxy statement of AEMD and a prospectus of AEMD (the "proxy statement/prospectus"). After the S - 4 is declared effective by the SEC, t he definitive proxy statement/prospectus will be mailed to AEMD’s stockholders. INVESTORS AND SECURITY HOLDERS OF AEMD AND NORTH ARE URGED TO READ THE S - 4, THE PROXY STATEMENT/PROSPECTUS AND ANY OTHER RELEVANT DOCUMENTS FILED OR TO BE FILED WITH THE SEC, AS WELL AS ANY AMENDMENTS OR SUPPLEMENTS THERETO, CAREFULLY AND IN THEIR ENTIRET Y W HEN THEY BECOME AVAILABLE, BECAUSE THEY WILL CONTAIN IMPORTANT INFORMATION ABOUT AEMD, NORTH, THE TRANSACTION AND RELATED MATTERS. Investors and securit y h olders will be able to obtain free copies of the S - 4 and the proxy statement/prospectus (when available), and other documents filed with the SEC by AEMD, through the SEC' s website at www.sec.gov and on the investors section of AEMD’s website. Participants in the Solicitation AEMD, North and their respective directors and executive officers may be deemed to be participants in the solicitation of pro xie s from AEMD’s stockholders in connection with the Transaction. Information about AEMD’s directors and executive officers, including a description of their interests in AEMD, is included in AE MD’s most recent definitive proxy statement, as filed with the SEC on September 1, 2026, and in AEMD’s Annual Report on Form 10 - K for the fiscal year ended March 31, 2026. To the extent that hold ings of AEMD’s securities by AEMD’s directors and executive officers have changed since the amounts set forth in AEMD’s most recent definitive proxy statement, such changes have been or wi ll be reflected on Statements of Change in Ownership on Forms 3, 4 or 5 filed with the SEC. Additional information regarding the persons who may, under the rules of the SEC, be deem ed participants in the solicitation of AEMD’s stockholders in connection with the Transaction, including a description of their direct or indirect interests, by security holdings or other wis e, will be included in the S - 4 and the proxy statement/prospectus and other relevant materials to be filed with the SEC when they become available. Disclaimer and Forward - looking Statements

3 Forward - Looking Statements This Presentation contains "forward - looking statements" within the meaning of the federal securities laws, including for purpose s of the safe harbor provisions under the Private Securities Litigation Reform Act of 1995. All statements other than statements of historical fact are forward - looking statements, including , without limitation, statements regarding the proposed Transaction and Private Placement and their expected timing and completion; the combined company's expected cash position and ca sh runway; NOR - 101's and North's other product candidates' target profiles, anticipated benefits, mechanism, dosing, and development plans; the timing and design of preclin ica l studies and clinical trials and the expected timing of data; market size and opportunity; and the combined company's strategy, prospects and future operations. Words such as "anticipate, " " believe," "expect," "intend," "may," "plan," "potential," "project," "target," "will" and similar expressions identify forward - looking statements. These statements are based on current e xpectations and assumptions and are subject to known and unknown risks and uncertainties (many beyond the parties' control) that could cause actual results to differ materially, incl udi ng, without limitation: the risk that the Transaction or the Private Placement may not be completed on the anticipated timeline or at all; the failure to satisfy closing conditions, including ob tai ning required stockholder approvals, the effectiveness of the S - 4, receipt of the minimum financing, and stock exchange listing approval; the outcome of preclinical studies and clinical trials ; r egulatory processes and the possibility that NOR - 101 target profiles are not achieved; the fact that NOR - 101 is investigational and cross - trial comparisons are not head - to - head; competition; relian ce on third parties; intellectual property risks; and the need for substantial additional funding. Additional risks will be described in the S - 4 and the proxy statement/prospectus and in AEMD’s f ilings with the SEC. Forward - looking statements speak only as of the date of this Presentation, and the parties undertake no obligation to update them except as required by law. You should n ot place undue reliance on forward - looking statements. Investigational Product Candidates NOR - 101 and North's other product candidates are investigational and have not been approved by the U.S. Food and Drug Administra tion or any other regulatory authority. Their safety and efficacy have not been established, and no representation is made as to their safety or effectiveness for the purposes for wh ich they are being investigated. Comparisons to approved products and to other investigational product candidates are based on separate studies with different designs, endpoints, timepoints a nd patient populations; no head - to - head studies have been conducted, and such comparisons are for illustrative purposes only. Industry and Market Data Certain information in this Presentation regarding the market and industry in which North operates, including market size, po sit ion and opportunity, is based on the Company's estimates and on third - party sources, internal analyses and assumptions that the Company believes to be reasonable but that have not been indepen dently verified. Such information is inherently uncertain and subject to change. Trademarks This Presentation contains trademarks, trade names and service marks of third parties (including Dupixent®, Ebglyss ®, Nemluvio ® and Rinvoq ®), which are the property of their respective owners. Solely for convenience, such marks are referred to without the ® and symbols, but such references are not intended to indicate any waiver of rights or that the owners will not assert their right s. Disclaimer and Forward - looking Statements
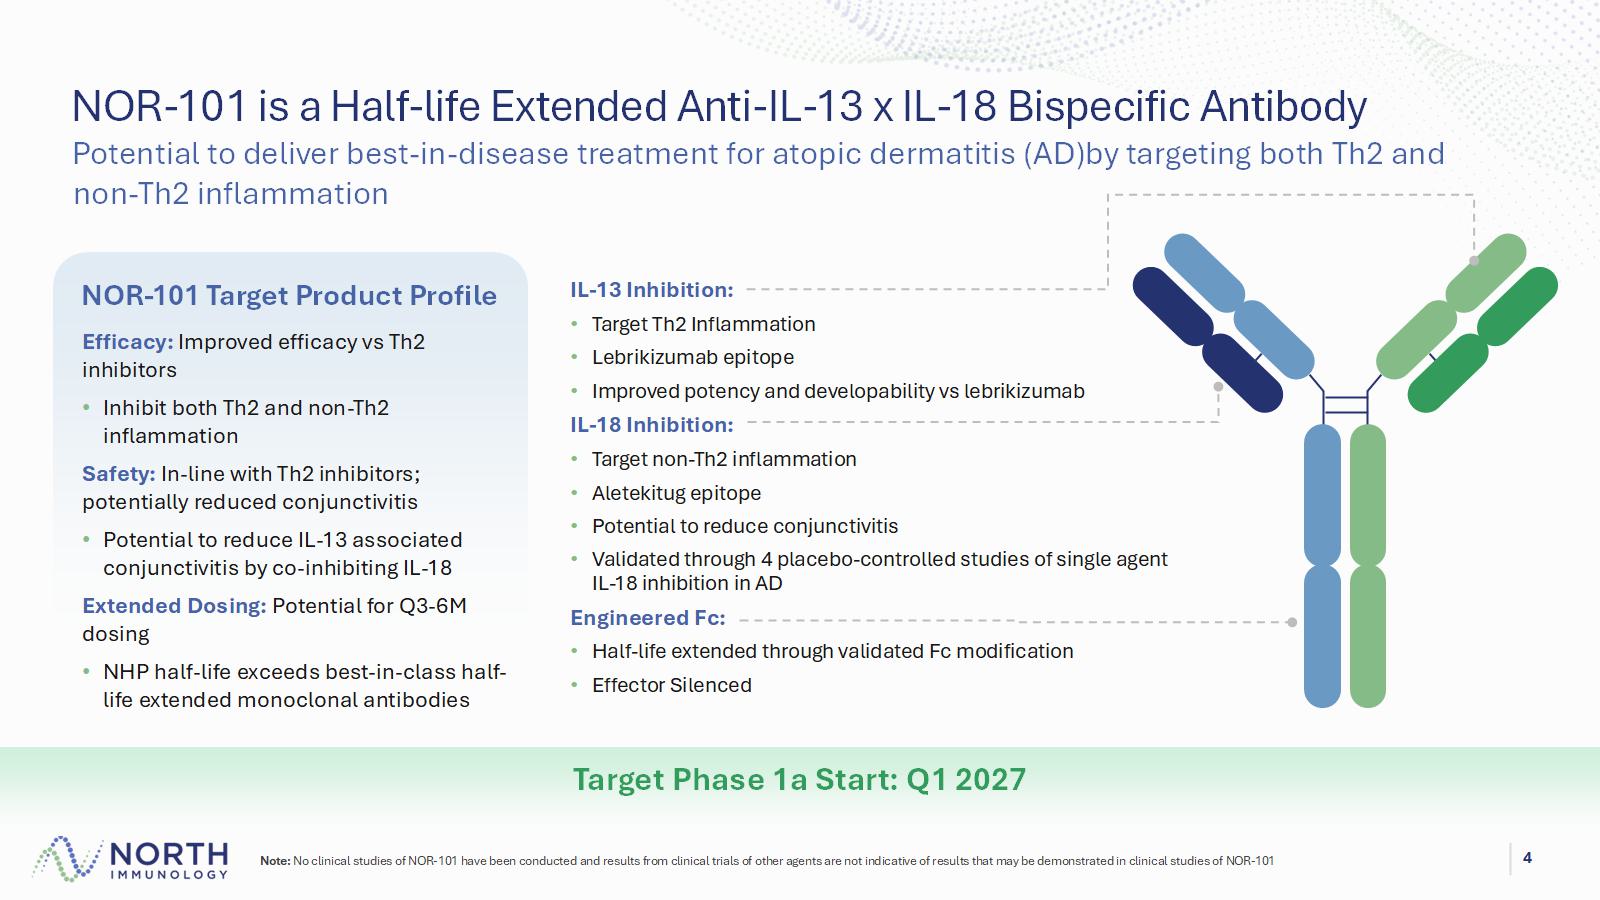
NOR - 101 Target Product Profile Note: No clinical studies of NOR - 101 have been conducted and results from clinical trials of other agents are not indicative of result s that may be demonstrated in clinical studies of NOR - 101 4 NOR - 101 is a Half - life Extended Anti - IL - 13 x IL - 18 Bispecific Antibody Potential to deliver best - in - disease treatment for atopic dermatitis (AD)by targeting both Th2 and non - Th2 inflammation Target Phase 1a Start: Q1 2027 Efficacy: Improved efficacy vs Th2 inhibitors • Inhibit both Th2 and non - Th2 inflammation Safety: In - line with Th2 inhibitors; potentially reduced conjunctivitis • Potential to reduce IL - 13 associated conjunctivitis by co - inhibiting IL - 18 Extended Dosing: Potential for Q3 - 6M dosing • NHP half - life exceeds best - in - class half - life extended monoclonal antibodies IL - 13 Inhibition: • Target Th2 Inflammation • Lebrikizumab epitope • Improved potency and developability vs lebrikizumab IL - 18 Inhibition: • Target non - Th2 inflammation • Aletekitug epitope • Potential to reduce conjunctivitis • Validated through 4 placebo - controlled studies of single agent IL - 18 inhibition in AD Engineered Fc: • Half - life extended through validated Fc modification • Effector Silenced
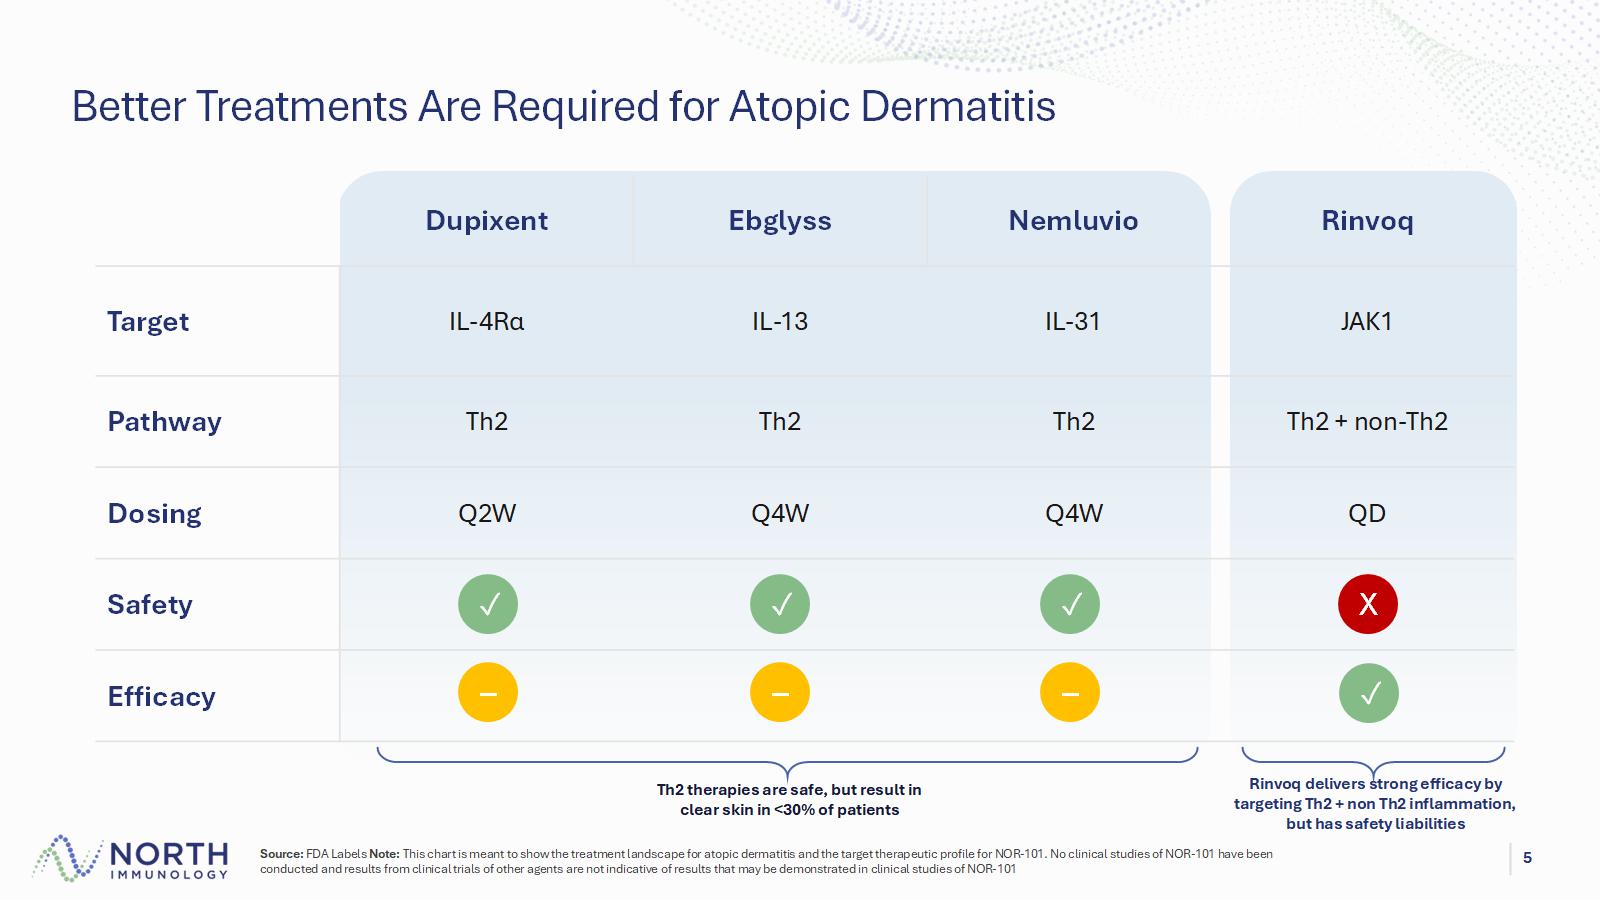
Source: FDA Labels Note: This chart is meant to show the treatment landscape for atopic dermatitis and the target therapeutic profile for NOR - 101. No cli nical studies of NOR - 101 have been conducted and results from clinical trials of other agents are not indicative of results that may be demonstrated in clinical st udies of NOR - 101 5 Better Treatments Are Required for Atopic Dermatitis Rinvoq Nemluvio Ebglyss Dupixent JAK1 IL - 31 IL - 13 IL - 4Rα Target Th2 + non - Th2 Th2 Th2 Th2 Pathway QD Q4W Q4W Q2W Dosing Safety Efficacy Rinvoq delivers strong efficacy by targeting Th2 + non Th2 inflammation, but has safety liabilities Th2 therapies are safe, but result in clear skin in <30% of patients ض – ض – ض – ض X
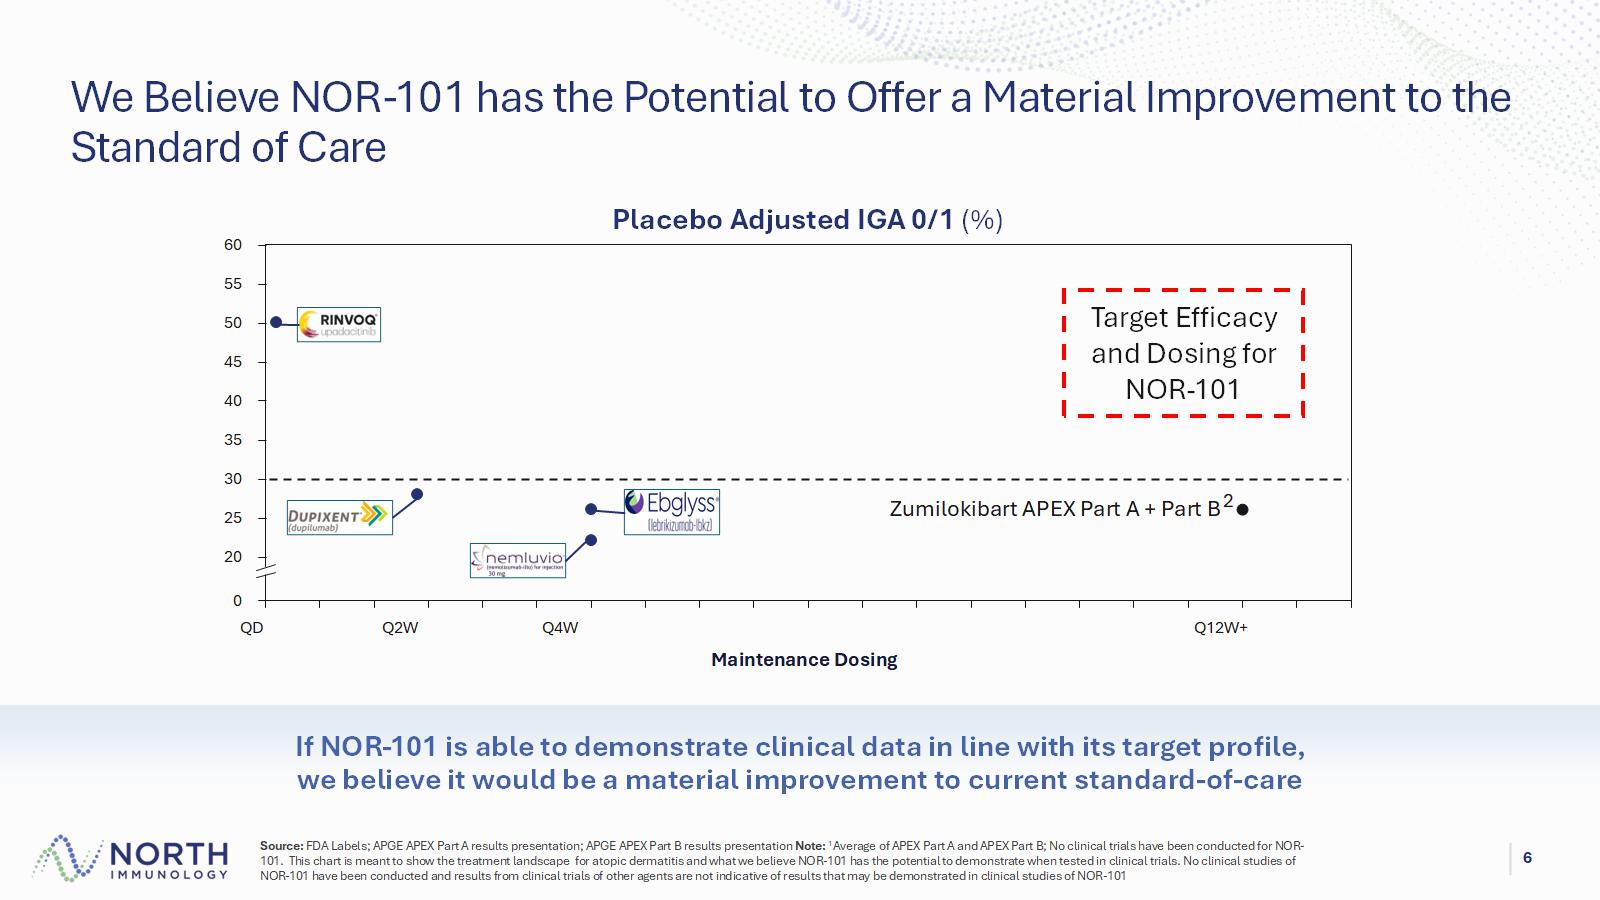
Source: FDA Labels; APGE APEX Part A results presentation; APGE APEX Part B results presentation Note: 1 Average of APEX Part A and APEX Part B; No clinical trials have been conducted for NOR - 101. This chart is meant to show the treatment landscape for atopic dermatitis and what we believe NOR - 101 has the potential t o demonstrate when tested in clinical trials. No clinical studies of NOR - 101 have been conducted and results from clinical trials of other agents are not indicative of results that may be demonstra ted in clinical studies of NOR - 101 6 We Believe NOR - 101 has the Potential to Offer a Material Improvement to the Standard of Care If NOR - 101 is able to demonstrate clinical data in line with its target profile, we believe it would be a material improvement to current standard - of - care Placebo Adjusted IGA 0/1 (%) 45 40 35 50 30 55 25 60 20 0 Zumilokibart APEX Part A + Part B Maintenance Dosing QD Q2W Q4W Q12W+ 2 Target Efficacy and Dosing for NOR - 101
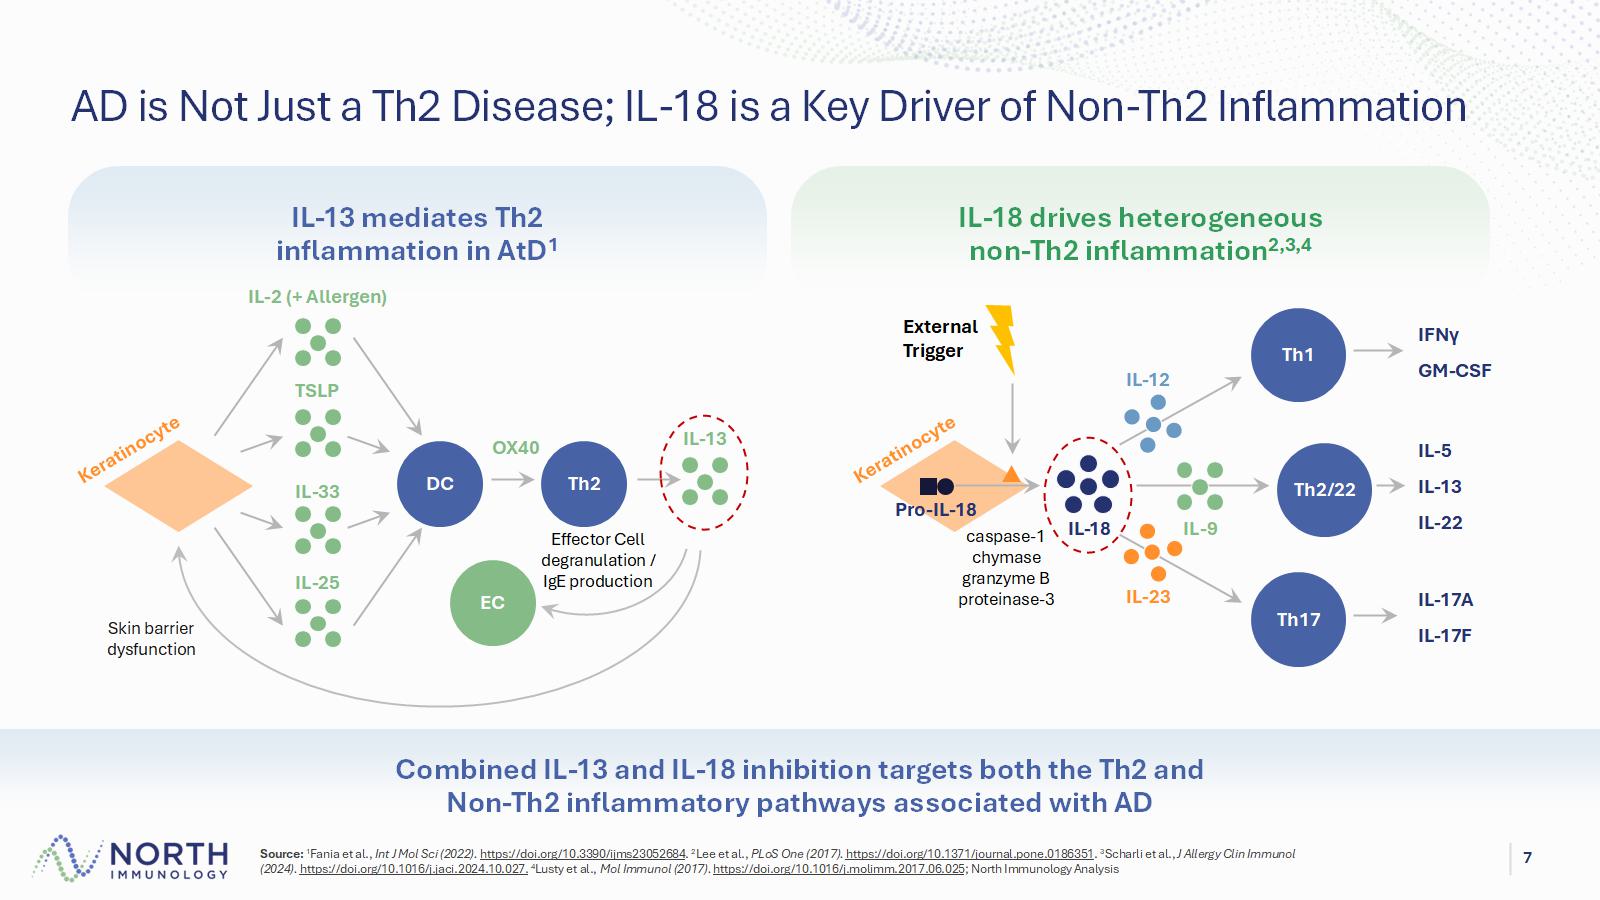
Source: 1 Fania et al., Int J Mol Sci (2022). https:// doi.org /10.3390/ijms23052684 . 2 Lee et al., PLoS One (2017). https:// doi.org /10.1371/journal.pone.0186351 . 3 Scharli et al., J Allergy Clin Immunol (2024). https:// doi.org /10.1016/j.jaci.2024.10.027. 4 Lusty et al., Mol Immunol (2017). https:// doi.org /10.1016/j.molimm.2017.06.025 ; North Immunology Analysis 7 AD is Not Just a Th2 Disease; IL - 18 is a Key Driver of Non - Th2 Inflammation IL - 18 drives heterogeneous non - Th2 inflammation 2,3,4 IL - 13 mediates Th2 inflammation in AtD 1 Combined IL - 13 and IL - 18 inhibition targets both the Th2 and Non - Th2 inflammatory pathways associated with AD Th2/22 IL - 18 IL - 9 IL - 5 IL - 13 IL - 22 Th1 IFN γ GM - CSF Th17 IL - 17A IL - 17F IL - 12 IL - 23 Pro - IL - 18 caspase - 1 chymase granzyme B proteinase - 3 External Trigger IL - 2 (+ Allergen) TSLP IL - 33 IL - 25 DC Th2 OX40 IL - 13 Effector Cell degranulation / IgE production EC Skin barrier dysfunction
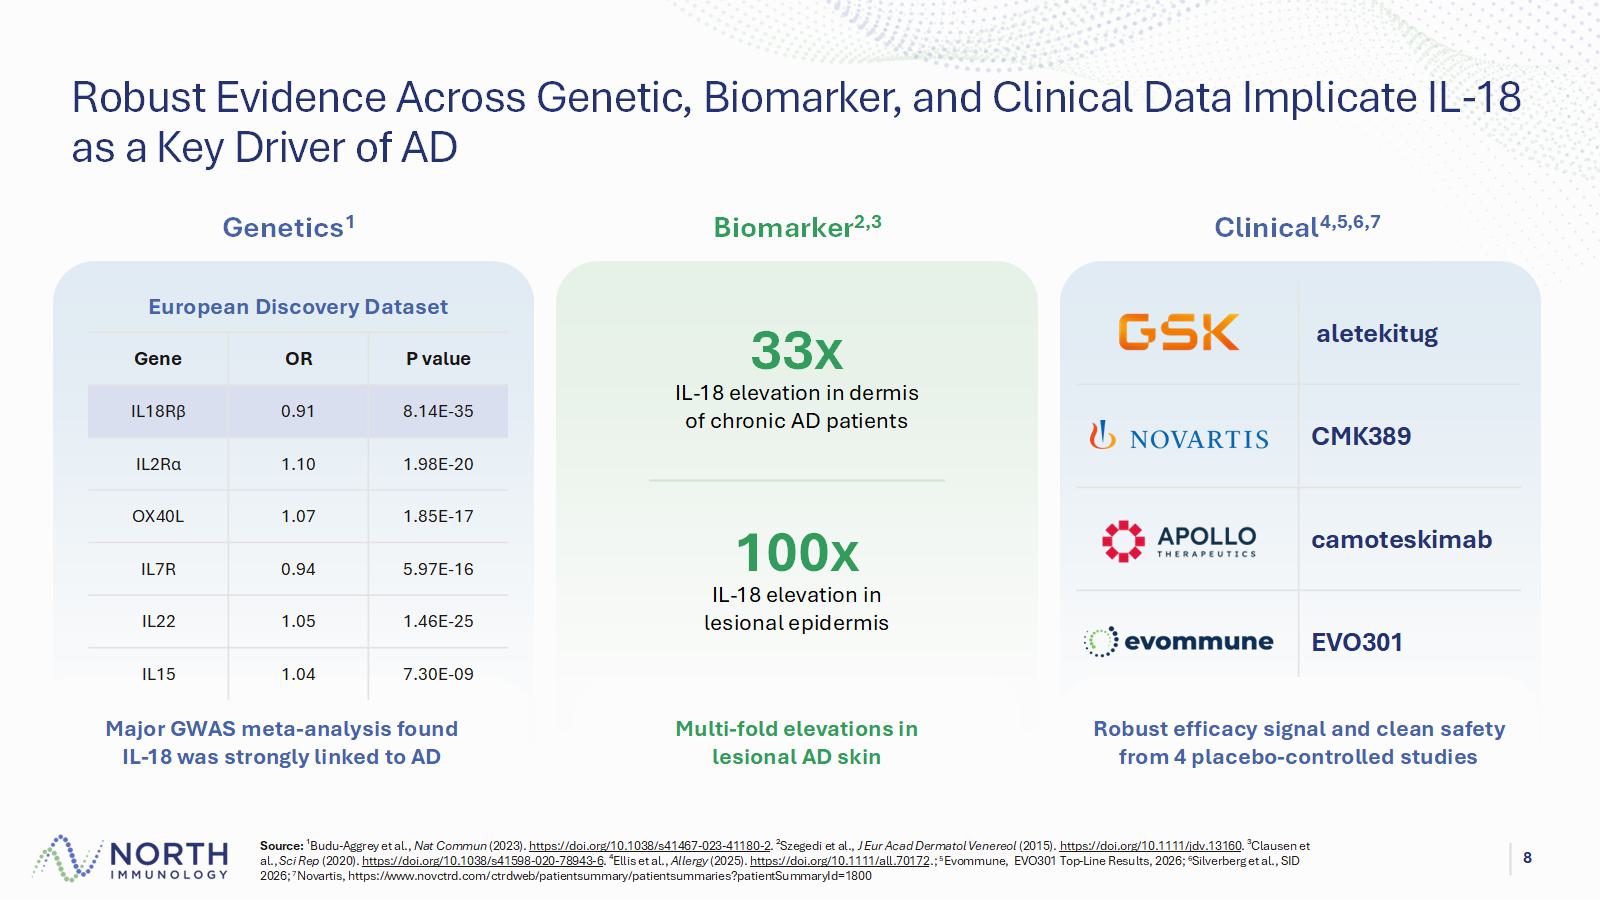
Clinical 4,5,6,7 aletekitug CMK389 camoteskimab EVO301 Source: ¹Budu - Aggrey et al., Nat Commun (2023). https://doi.org/10.1038/s41467 - 023 - 41180 - 2 . ²Szegedi et al., J Eur Acad Dermatol Venereol (2015). https://doi.org/10.1111/jdv.13160 . ³Clausen et al., Sci Rep (2020). https://doi.org/10.1038/s41598 - 020 - 78943 - 6 . ⁴Ellis et al., Allergy (2025). https://doi.org/10.1111/all.70172 .; 5 Evommune, EVO301 Top - Line Results, 2026; 6 Silverberg et al., SID 2026; 7 Novartis, https:// www.novctrd.com / ctrdweb / patientsummary / patientsummaries?patientSummaryId =1800 8 Robust Evidence Across Genetic, Biomarker, and Clinical Data Implicate IL - 18 as a Key Driver of AD Genetics 1 Biomarker 2,3 33x IL - 18 elevation in dermis of chronic AD patients 100x IL - 18 elevation in lesional epidermis Major GWAS meta - analysis found IL - 18 was strongly linked to AD Multi - fold elevations in lesional AD skin Robust efficacy signal and clean safety from 4 placebo - controlled studies European Discovery Dataset P value OR Gene 8.14E - 35 0.91 IL18Rβ 1.98E - 20 1.10 IL2Rα 1.85E - 17 1.07 OX40L 5.97E - 16 0.94 IL7R 1.46E - 25 1.05 IL22 7.30E - 09 1.04 IL15
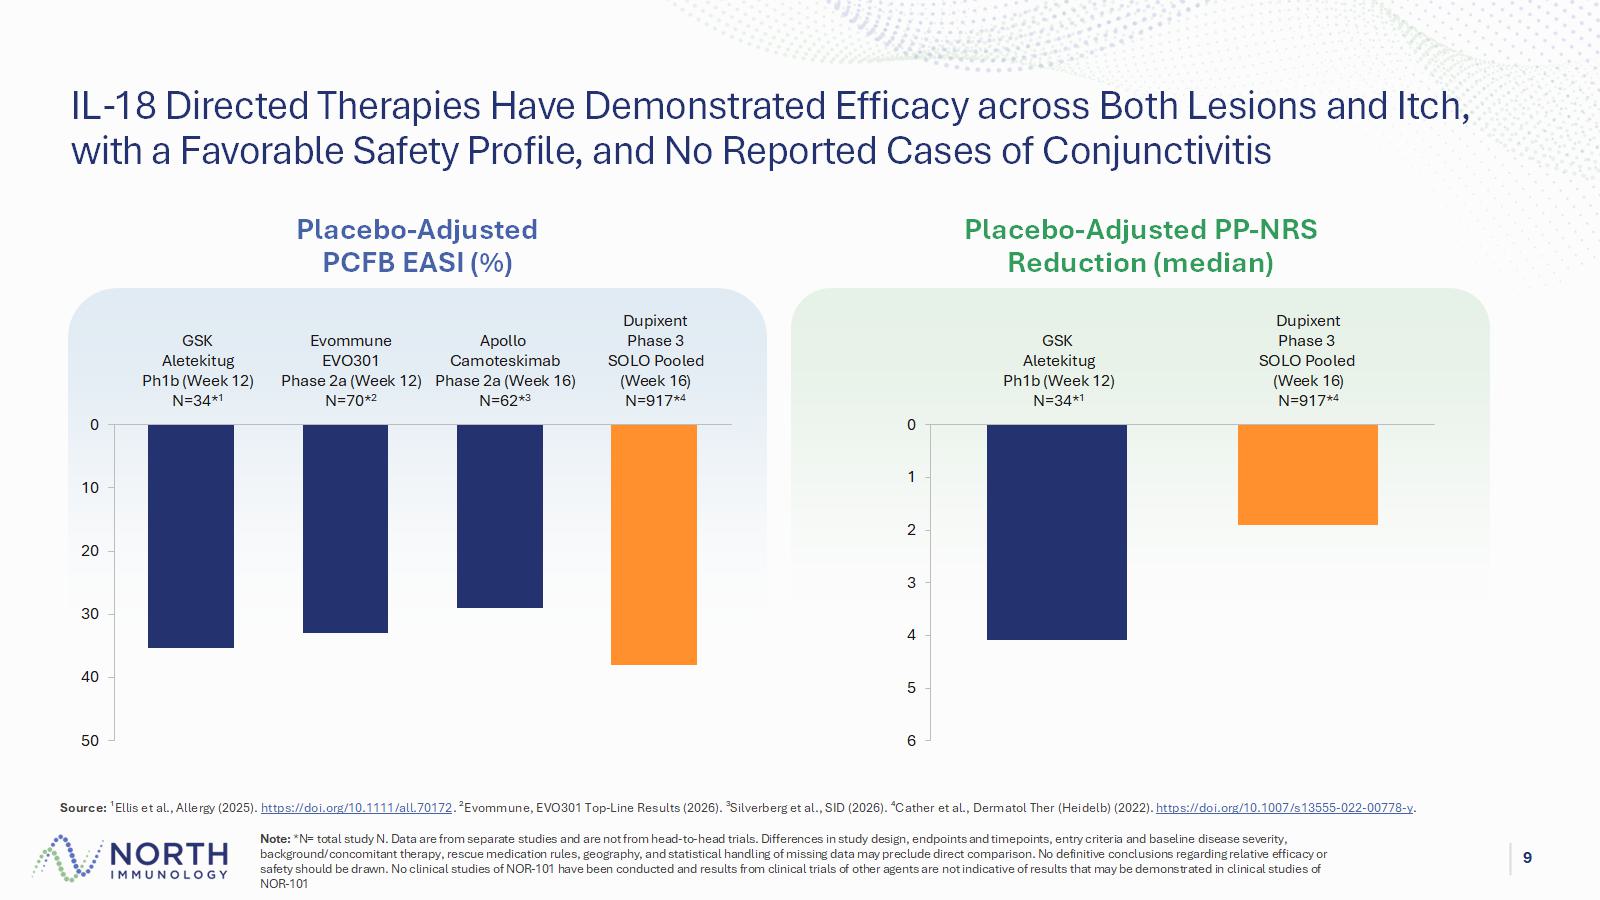
Note: *N= total study N. Data are from separate studies and are not from head - to - head trials. Differences in study design, endpoints a nd timepoints, entry criteria and baseline disease severity, background/concomitant therapy, rescue medication rules, geography, and statistical handling of missing data may preclude dir ect comparison. No definitive conclusions regarding relative efficacy or safety should be drawn. No clinical studies of NOR - 101 have been conducted and results from clinical trials of other agents are not indicative of results that may be demonstrated in clinical studies of NOR - 101 9 IL - 18 Directed Therapies Have Demonstrated Efficacy across Both Lesions and Itch, with a Favorable Safety Profile, and No Reported Cases of Conjunctivitis Source: ¹Ellis et al., Allergy (2025). https://doi.org/10.1111/all.70172 . ²Evommune, EVO301 Top - Line Results (2026). ³Silverberg et al., SID (2026). ⁴Cather et al., Dermatol Ther ( Heidelb ) (2022). https://doi.org/10.1007/s13555 - 022 - 00778 - y . Placebo - Adjusted PP - NRS Reduction (median) Placebo - Adjusted PCFB EASI (%) 0 10 20 30 40 50 GSK Aletekitug Ph1b (Week 12) N=34* 1 Apollo Camoteskimab Phase 2a (Week 16) N=62* 3 Dupixent Phase 3 SOLO Pooled (Week 16) N=917* 4 0 1 2 3 4 5 6 GSK Aletekitug Ph1b (Week 12) N=34* 1 Dupixent Phase 3 SOLO Pooled (Week 16) N=917* 4 Evommune EVO301 Phase 2a (Week 12) N=70* 2
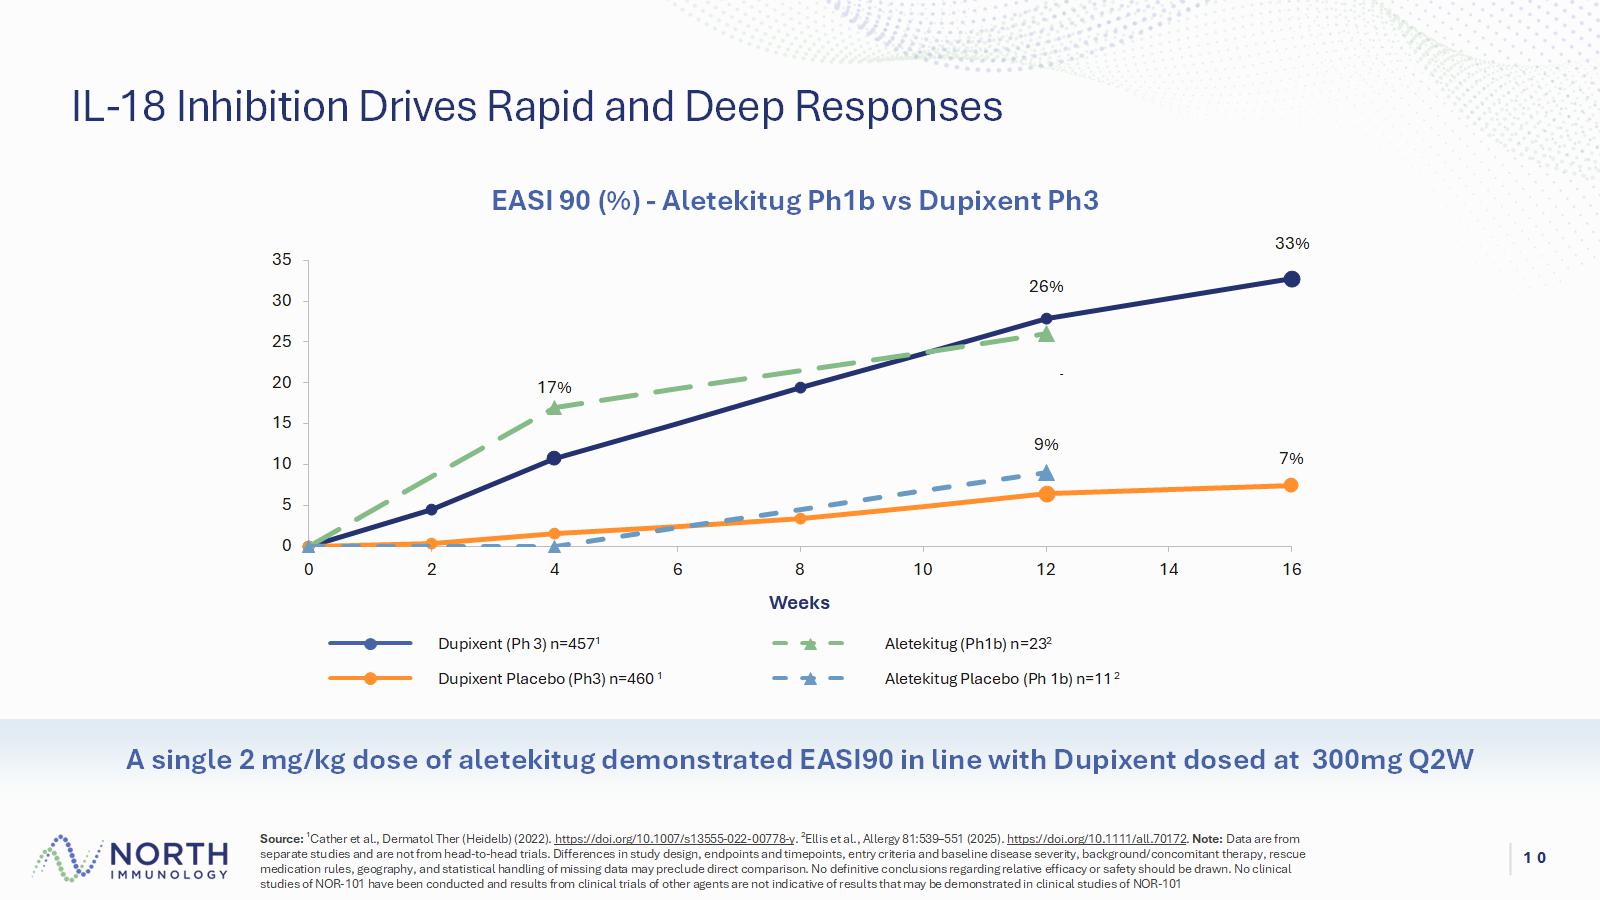
33% 7% 26% 9% 0 5 10 15 20 25 30 35 0 2 4 6 8 10 12 14 16 Source: ¹Cather et al., Dermatol Ther ( Heidelb ) (2022). https://doi.org/10.1007/s13555 - 022 - 00778 - y . ²Ellis et al., Allergy 81:539 – 551 (2025). https://doi.org/10.1111/all.70172 . Note: Data are from separate studies and are not from head - to - head trials. Differences in study design, endpoints and timepoints, entry criteria and baseline disease severity, background/concomitant therapy, rescue medication rules, geography, and statistical handling of missing data may preclude direct comparison. No definitive conclusio ns regarding relative efficacy or safety should be drawn. No clinical studies of NOR - 101 have been conducted and results from clinical trials of other agents are not indicative of results that may b e demonstrated in clinical studies of NOR - 101 10 IL - 18 Inhibition Drives Rapid and Deep Responses A single 2 mg/kg dose of aletekitug demonstrated EASI90 in line with Dupixent dosed at 300mg Q2W EASI 90 (%) - Aletekitug Ph1b vs Dupixent Ph3 17% Weeks Dupixent (Ph 3) n=457 1 Dupixent Placebo (Ph3) n=460 1 Aletekitug (Ph1b) n=23 2 Aletekitug Placebo (Ph 1b) n=11 2

11 IL - 18 mAbs Have Demonstrated a Clean Safety Profile and Human Genetic Evidence Suggests That Long - term IL - 18 Inhibition is not Deleterious • Clinical trials of IL - 18 inhibitors have not shown treatment related safety - signals to date • No cases of conjunctivitis reported across 4 different anti - IL - 18 programs 1 - 4 • Aletekitug studied in 3 Phase 2 studies up to 5mg/kg 5 - 7 in addition to phase 1b study in atopic dermatitis • Compassionate use case for IL - 18opathy associated IBD dosed up to 10mg/kg with no long term tolerability issues 8 Note: Data are from separate studies and are not from head - to - head trials. Differences in study design, endpoints and timepoints, entr y criteria and baseline disease severity, background/ concomitant therapy, rescue medication rules, geography, and statistical handling of missing data may preclude direct compari son . No definitive conclusions regarding relative efficacy or safety should be drawn. No clinical studies of NOR - 101 have been conducted and results from clinical trials of other agents are not indicative of results that may be demonstrated in clinical studies of NOR - 101 Source: ¹Ellis et al., Allergy (2025). https://doi.org/10.1111/all.70172 . ²Evommune, EVO301 Top - Line Results (2026). ³Silverberg et al., SID (2026). ⁴Novartis. https://www.novctrd.com/ctrdweb/patientsummary/patientsummaries?patientSummaryId=1800 . ⁵ ClinicalTrials.gov , NCT06447506. https://clinicaltrials.gov/study/NCT06447506 . ⁶McKie et al., PLoS One (2016). https://doi.org/10.1371/journal.pone.0150018 . ⁷Wlodek et al., PLoS One (2021). https://doi.org/10.1371/journal.pone.0247972 . ⁸Guha et al., J Clin Med (2024). https://doi.org/10.3390/jcm13206058 . ⁹Belkaya et al., J Exp Med (2019). https://doi.org/10.1084/jem.20190669 . ¹⁰Zhang et al., Proc Natl Acad Sci U S A (2021). https://doi.org/10.1073/pnas.2009217118 . ¹¹Dominy et al., J Allergy Clin Immunol (2026). https://doi.org/10.1016/j.jaci.2025.09.025 . Genetics Clinical Data • No known IL - 18 LoF phenotype • Loss of endogenous negative feedback via IL - 18BP or IL - 37 LoF associated with fulminant hepatitis 9 and colitis 10 respectively • Homozygous CASP1 LoF with undetectable IL - 18 levels and no change in life expectancy or increased risk of infection 11
Clinical Data: Strong responses to IL - 18 inhibition in Dupixent refractory patients Note: No clinical studies of NOR - 101 have been conducted and results from clinical trials of other agents are not indicative of result s that may be demonstrated in clinical studies of NOR - 101 12 Dual IL - 13 x IL - 18 Inhibition has the Potential to Drive Deeper and Broader Responses than IL - 13 Inhibitor Monotherapy 1 Biomarkers: Dupixent non - responders display a Th1 - skewed immune signature; Dupixent responders display a Th2 dominant signature 2 In Vitro: IL - 13 x IL - 18 inhibition demonstrated orthogonality and additivity 3 Clinical Observation: Th switching implicated in Dupixent loss of response 4
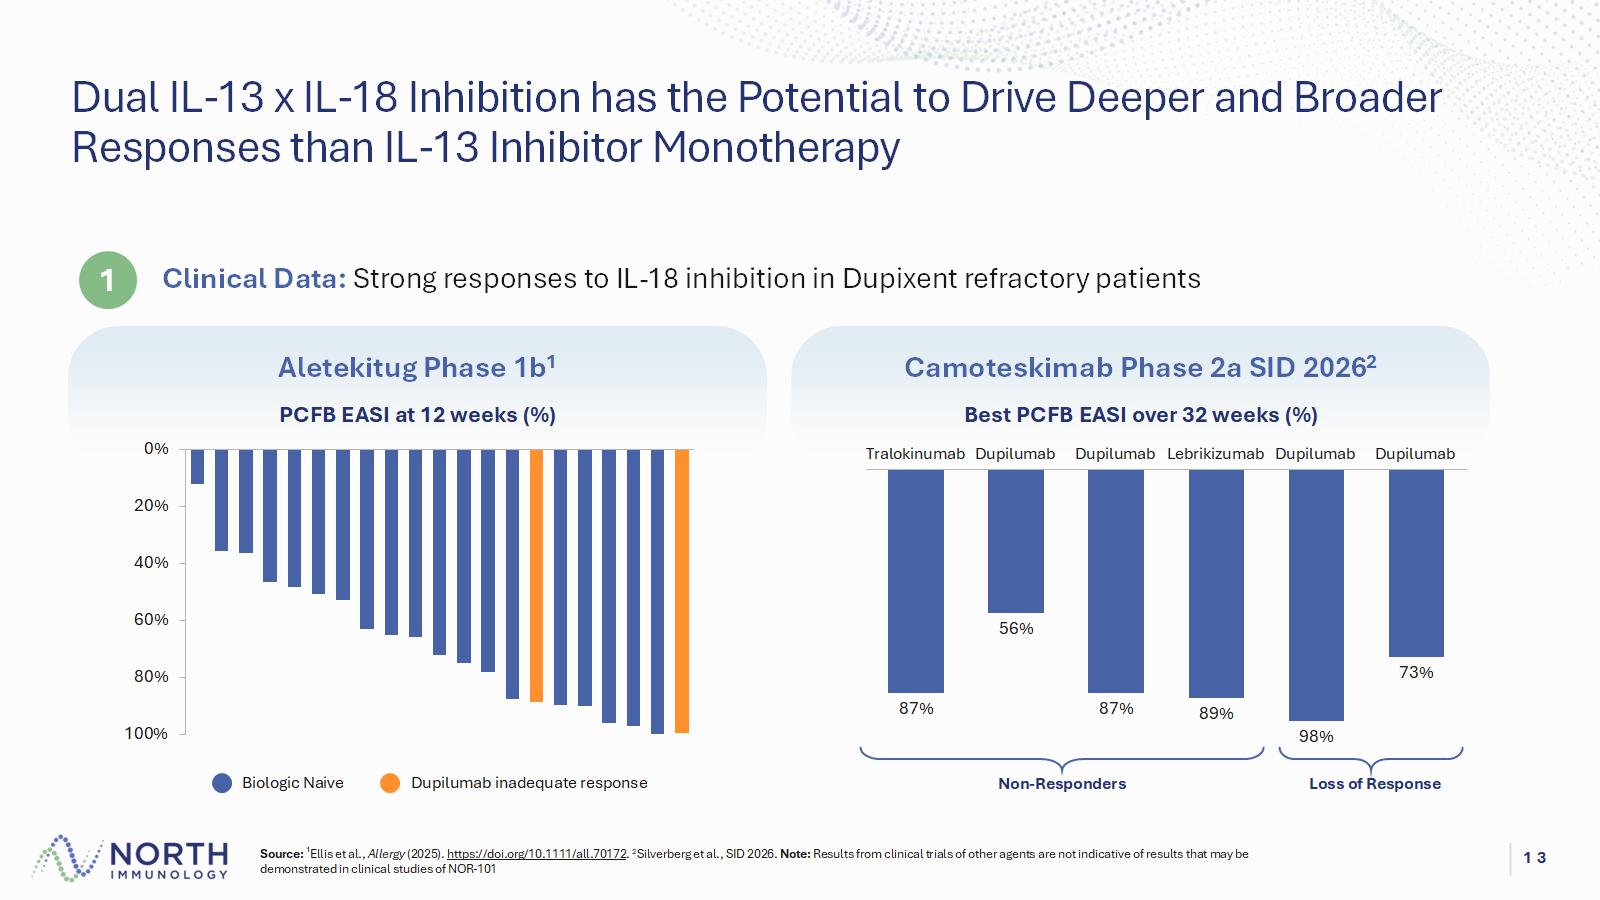
Source: ¹Ellis et al., Allergy (2025). https://doi.org/10.1111/all.70172 . 2 Silverberg et al., SID 2026. Note: Results from clinical trials of other agents are not indicative of results that may be demonstrated in clinical studies of NOR - 101 13 Dual IL - 13 x IL - 18 Inhibition has the Potential to Drive Deeper and Broader Responses than IL - 13 Inhibitor Monotherapy 1 Camoteskimab Phase 2a SID 2026 2 Clinical Data: Strong responses to IL - 18 inhibition in Dupixent refractory patients Aletekitug Phase 1b 1 87% 56% 87% 89% 98% 73% Tralokinumab Dupilumab Dupilumab Lebrikizumab Dupilumab Dupilumab Non - Responders Loss of Response Best PCFB EASI over 32 weeks (%) 0% 20% 40% 60% 80% 100% PCFB EASI at 12 weeks (%) Biologic Naive Dupilumab inadequate response
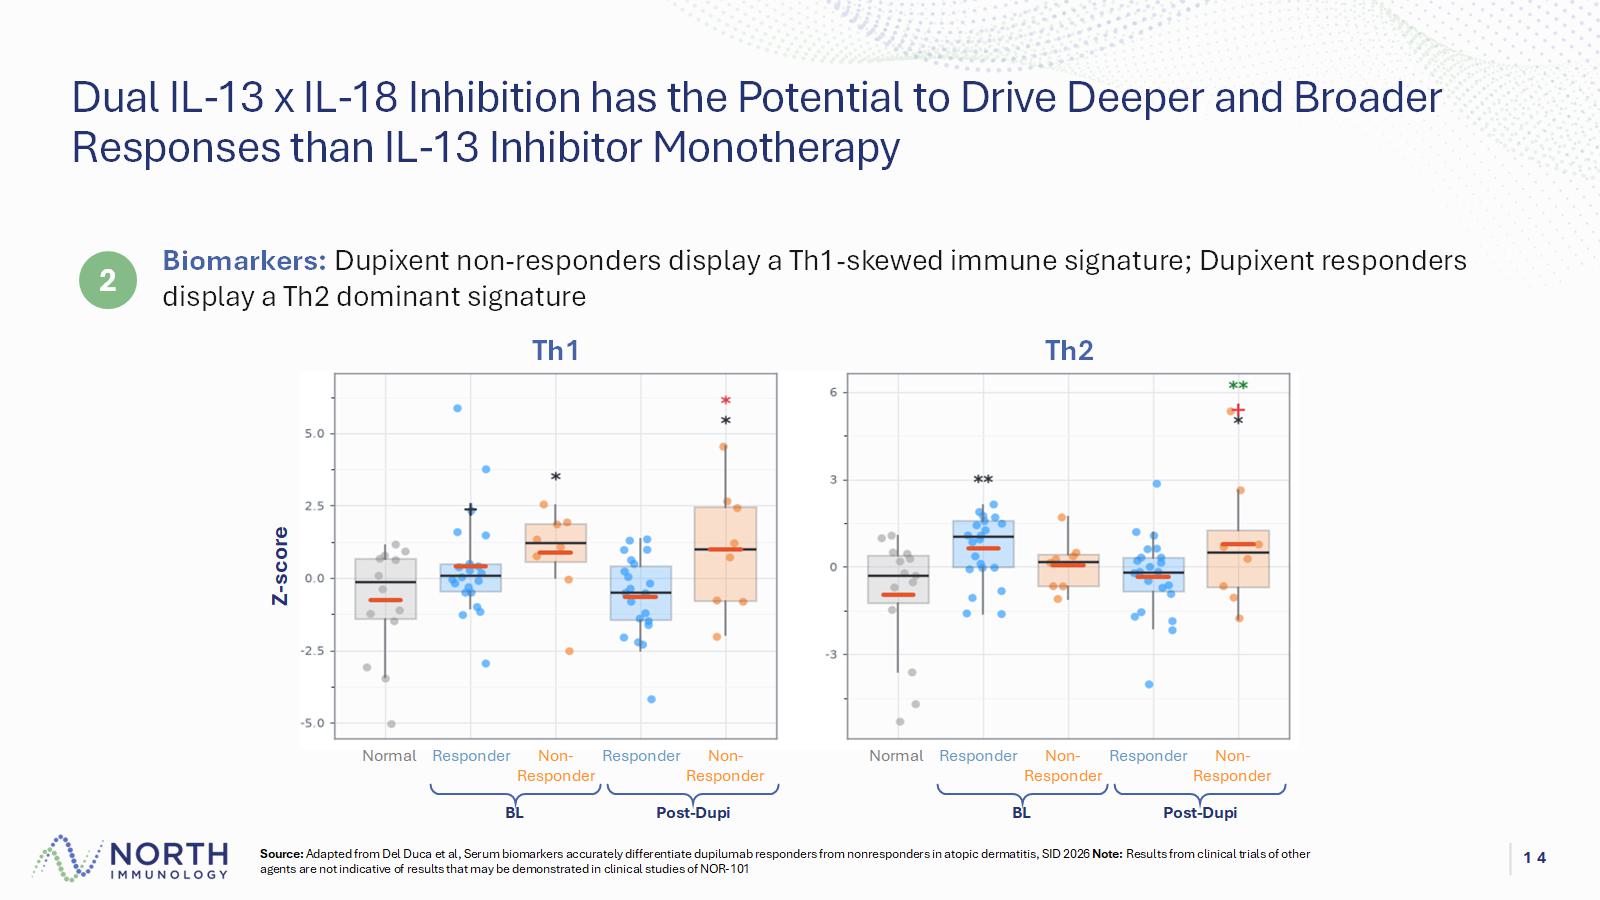
Source: Adapted from Del Duca et al, Serum biomarkers accurately differentiate dupilumab responders from nonresponders in atopic derm ati tis, SID 2026 Note: Results from clinical trials of other agents are not indicative of results that may be demonstrated in clinical studies of NOR - 101 14 Dual IL - 13 x IL - 18 Inhibition has the Potential to Drive Deeper and Broader Responses than IL - 13 Inhibitor Monotherapy 2 Biomarkers: Dupixent non - responders display a Th1 - skewed immune signature; Dupixent responders display a Th2 dominant signature Th1 Z - score Normal Responder Non - Responder Responder Non - Responder BL Post - Dupi Th2 Normal Responder Non - Responder Responder Non - Responder BL Post - Dupi
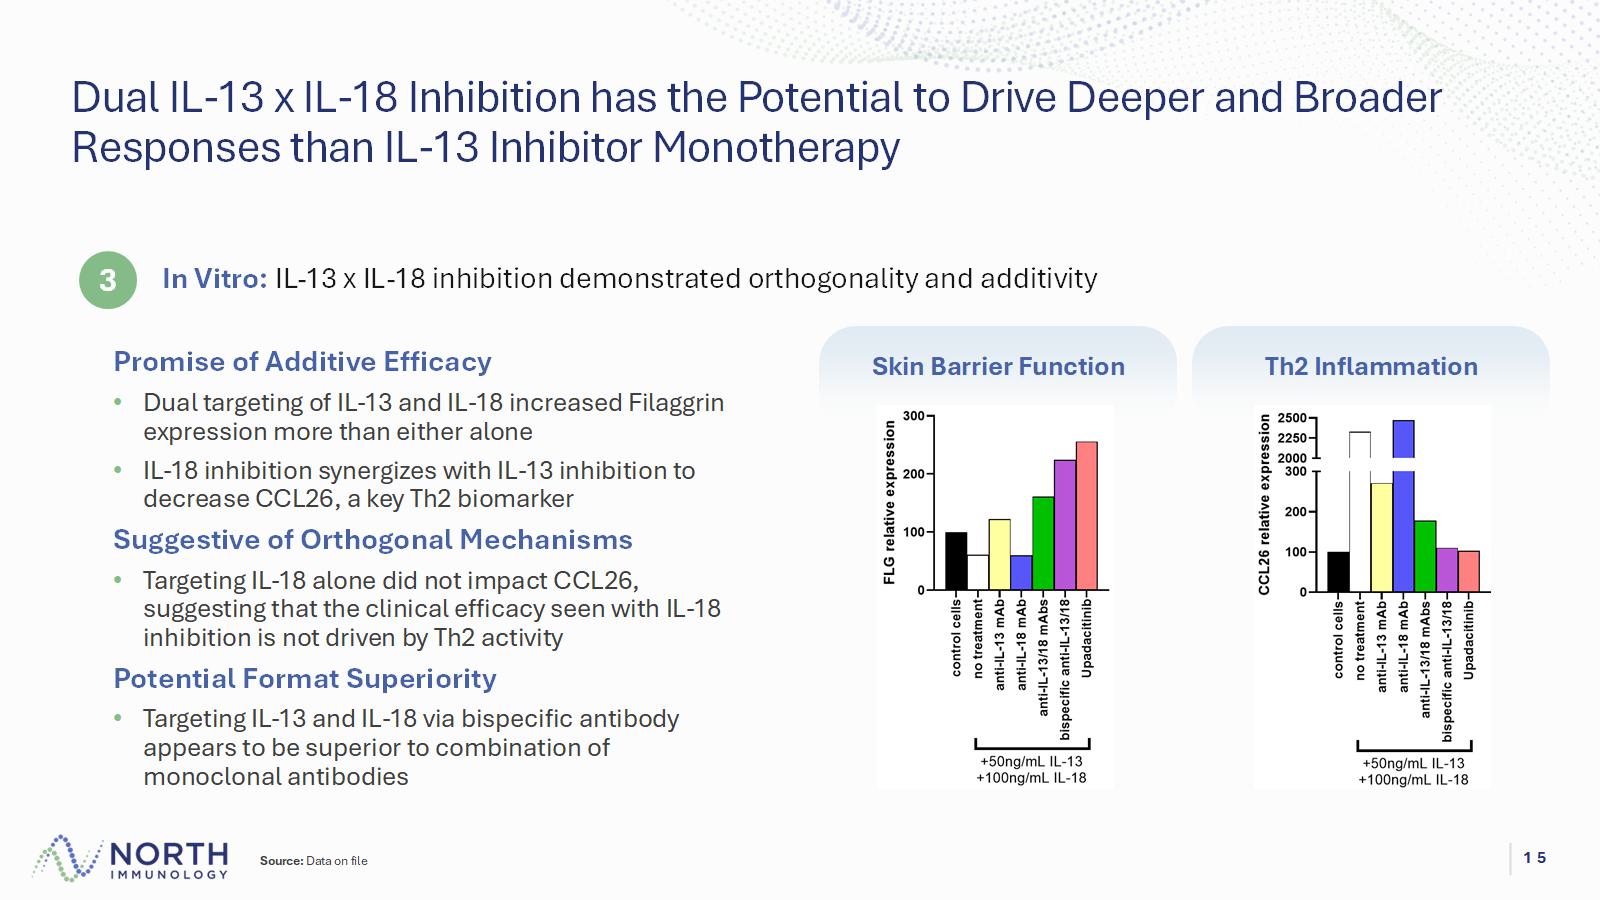
Source: Data on file 15 Dual IL - 13 x IL - 18 Inhibition has the Potential to Drive Deeper and Broader Responses than IL - 13 Inhibitor Monotherapy Promise of Additive Efficacy • Dual targeting of IL - 13 and IL - 18 increased Filaggrin expression more than either alone • IL - 18 inhibition synergizes with IL - 13 inhibition to decrease CCL26, a key Th2 biomarker Suggestive of Orthogonal Mechanisms • Targeting IL - 18 alone did not impact CCL26, suggesting that the clinical efficacy seen with IL - 18 inhibition is not driven by Th2 activity Potential Format Superiority • Targeting IL - 13 and IL - 18 via bispecific antibody appears to be superior to combination of monoclonal antibodies 3 In Vitro: IL - 13 x IL - 18 inhibition demonstrated orthogonality and additivity Skin Barrier Function Th2 Inflammation
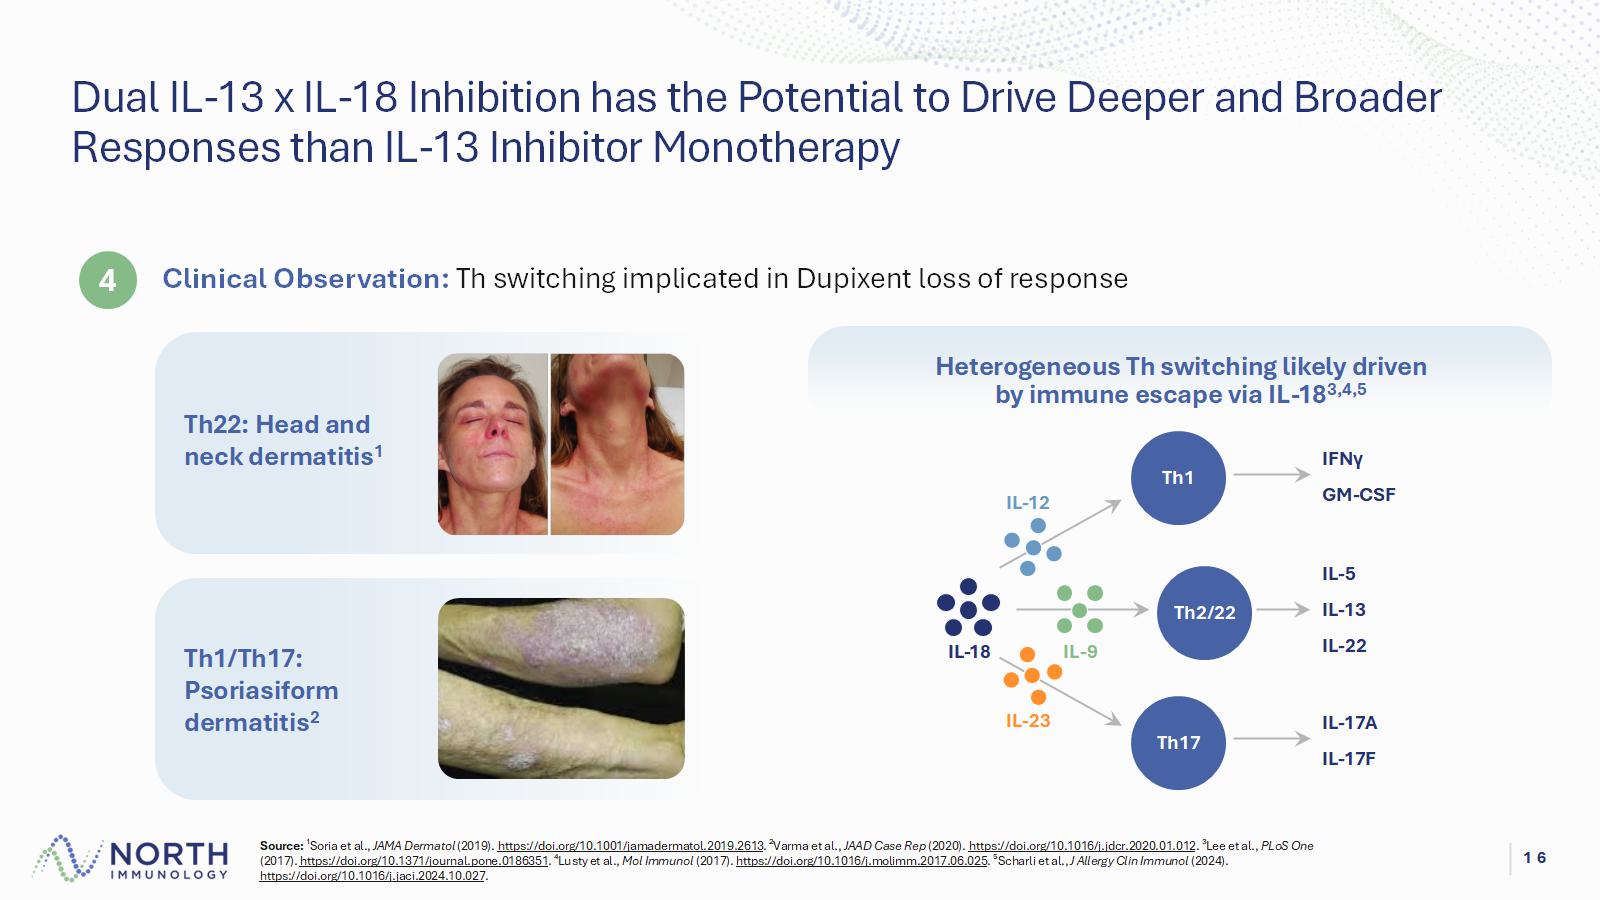
Source: ¹Soria et al., JAMA Dermatol (2019). https://doi.org/10.1001/jamadermatol.2019.2613 . ²Varma et al., JAAD Case Rep (2020). https://doi.org/10.1016/j.jdcr.2020.01.012 . ³Lee et al., PLoS One (2017). https://doi.org/10.1371/journal.pone.0186351 . ⁴Lusty et al., Mol Immunol (2017). https://doi.org/10.1016/j.molimm.2017.06.025 . ⁵ Scharli et al., J Allergy Clin Immunol (2024). https://doi.org/10.1016/j.jaci.2024.10.027 . 16 Dual IL - 13 x IL - 18 Inhibition has the Potential to Drive Deeper and Broader Responses than IL - 13 Inhibitor Monotherapy 4 Clinical Observation: Th switching implicated in Dupixent loss of response Heterogeneous Th switching likely driven by immune escape via IL - 18 3,4,5 Th22: Head and neck dermatitis 1 Th1/Th17: Psoriasiform dermatitis 2 Th2/22 IL - 18 IL - 9 IL - 5 IL - 13 IL - 22 Th1 IFN γ GM - CSF Th17 IL - 17A IL - 17F IL - 12 IL - 23
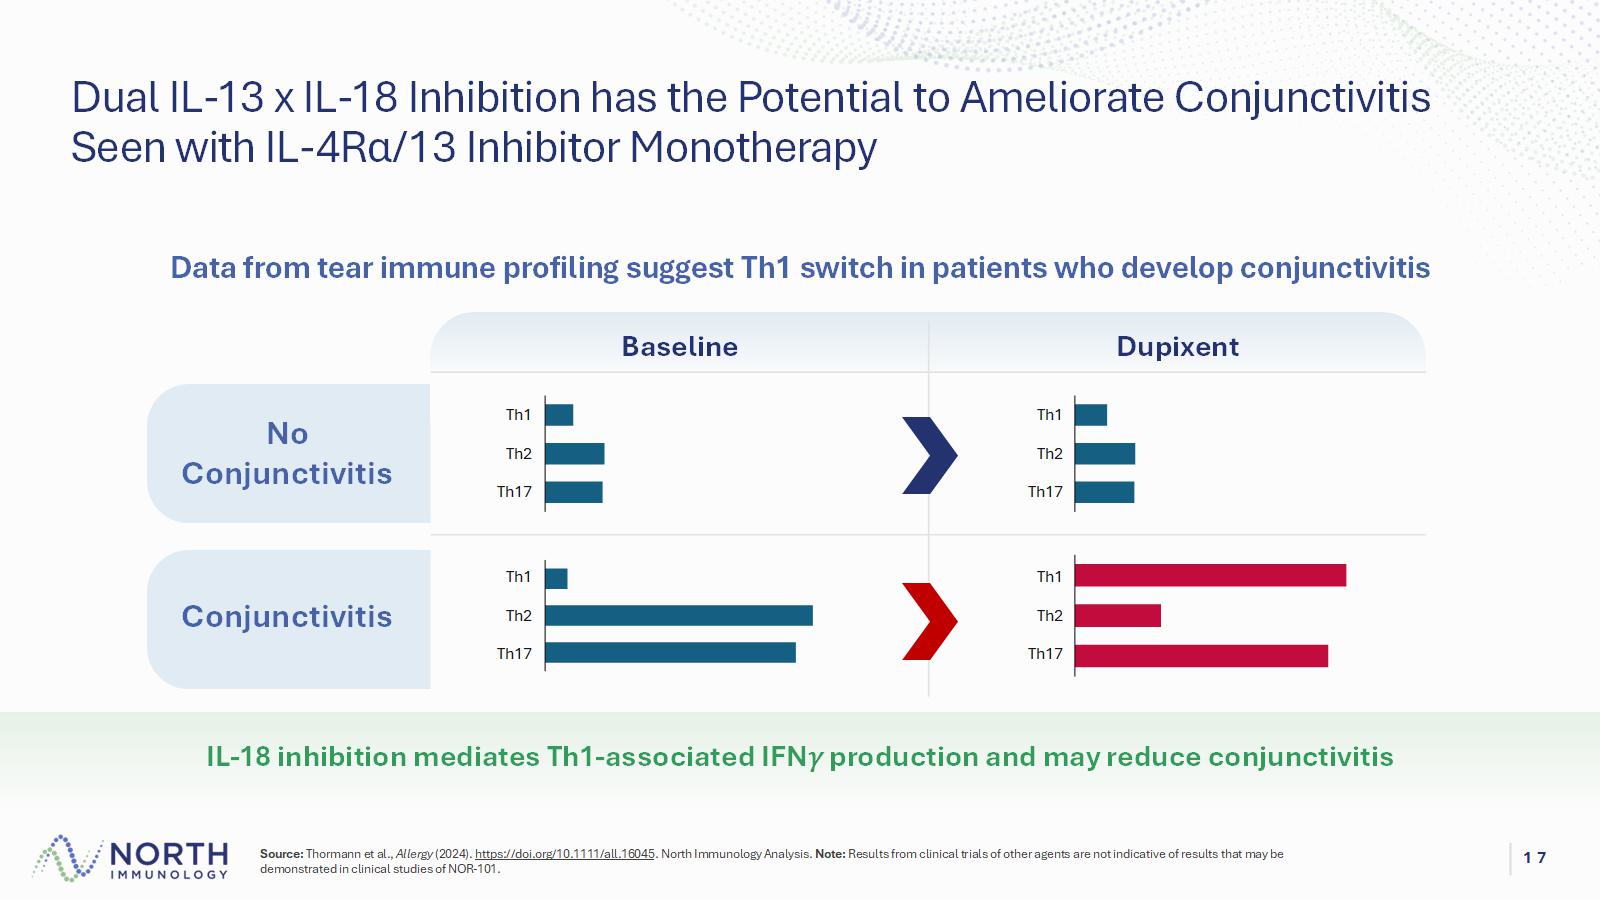
Source: Thormann et al., Allergy (2024). https://doi.org/10.1111/all.16045 . North Immunology Analysis. Note: Results from clinical trials of other agents are not indicative of results that may be demonstrated in clinical studies of NOR - 101. 17 Dual IL - 13 x IL - 18 Inhibition has the Potential to Ameliorate Conjunctivitis Seen with IL - 4R α/13 Inhibitor Monotherapy Data from tear immune profiling suggest Th1 switch in patients who develop conjunctivitis IL - 18 inhibition mediates Th1 - associated IFN ߛ production and may reduce conjunctivitis Dupixent Baseline No Conjunctivitis Conjunctivitis Th1 Th2 Th17 Th1 Th2 Th17 Th1 Th2 Th17 Th1 Th2 Th17
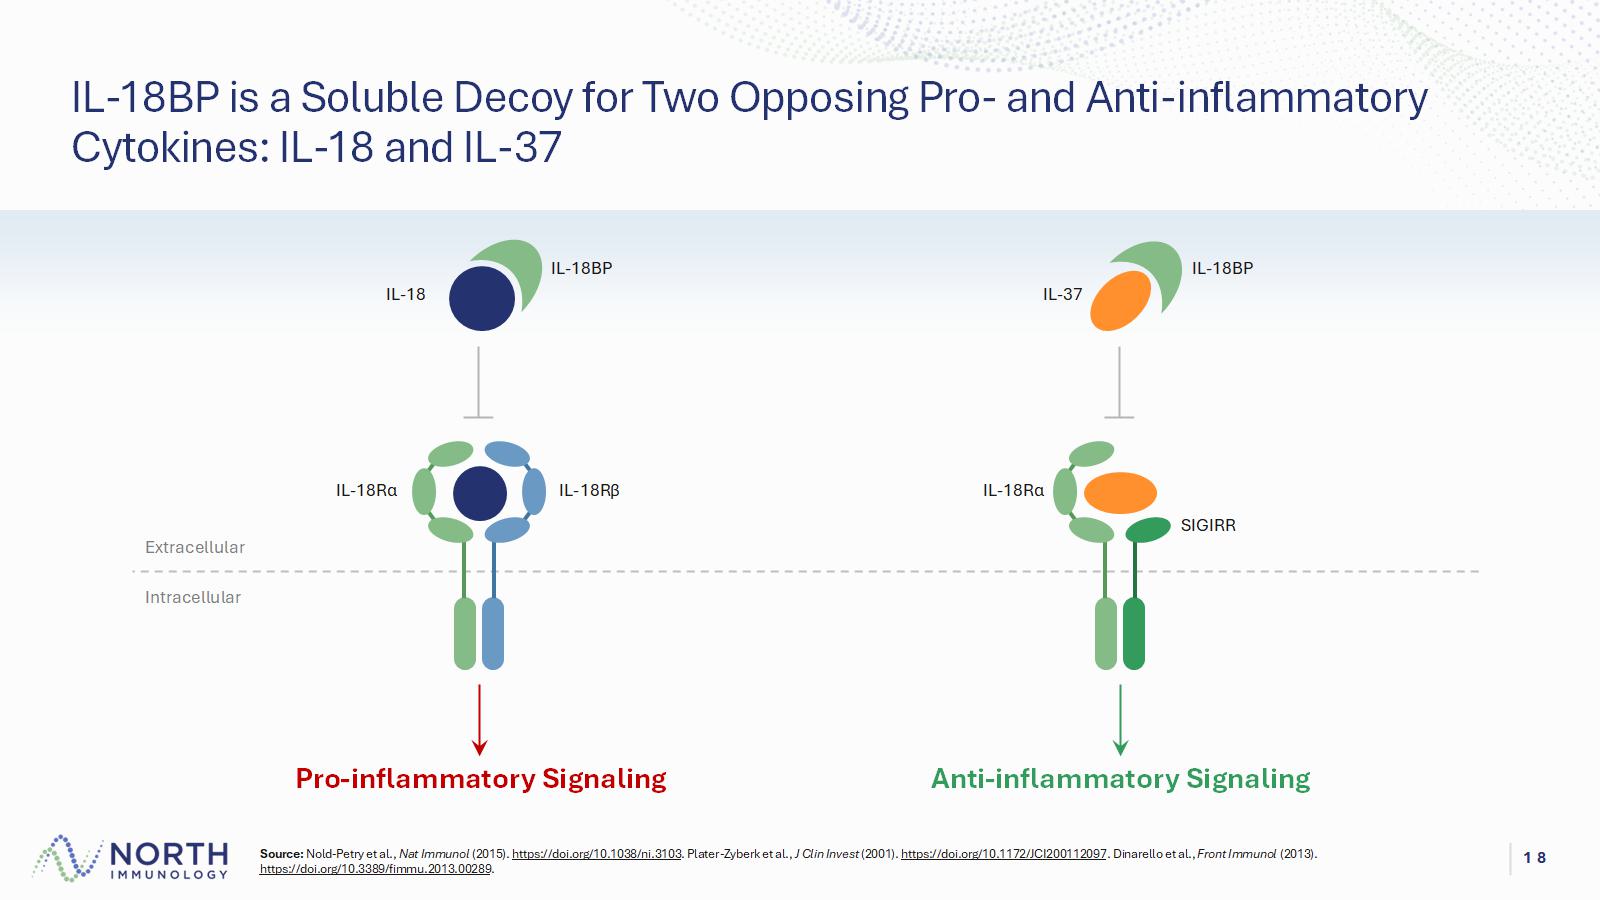
Source: Nold - Petry et al., Nat Immunol (2015). https://doi.org/10.1038/ni.3103 . Plater - Zyberk et al., J Clin Invest (2001). https://doi.org/10.1172/JCI200112097 . Dinarello et al., Front Immunol (2013). https://doi.org/10.3389/fimmu.2013.00289 . 18 IL - 18BP is a Soluble Decoy for Two Opposing Pro - and Anti - inflammatory Cytokines: IL - 18 and IL - 37 Pro - inflammatory Signaling Anti - inflammatory Signaling IL - 18BP IL - 18 IL - 18R α IL - 18R β Extracellular Intracellular IL - 18BP IL - 37 IL - 18R α SIGIRR
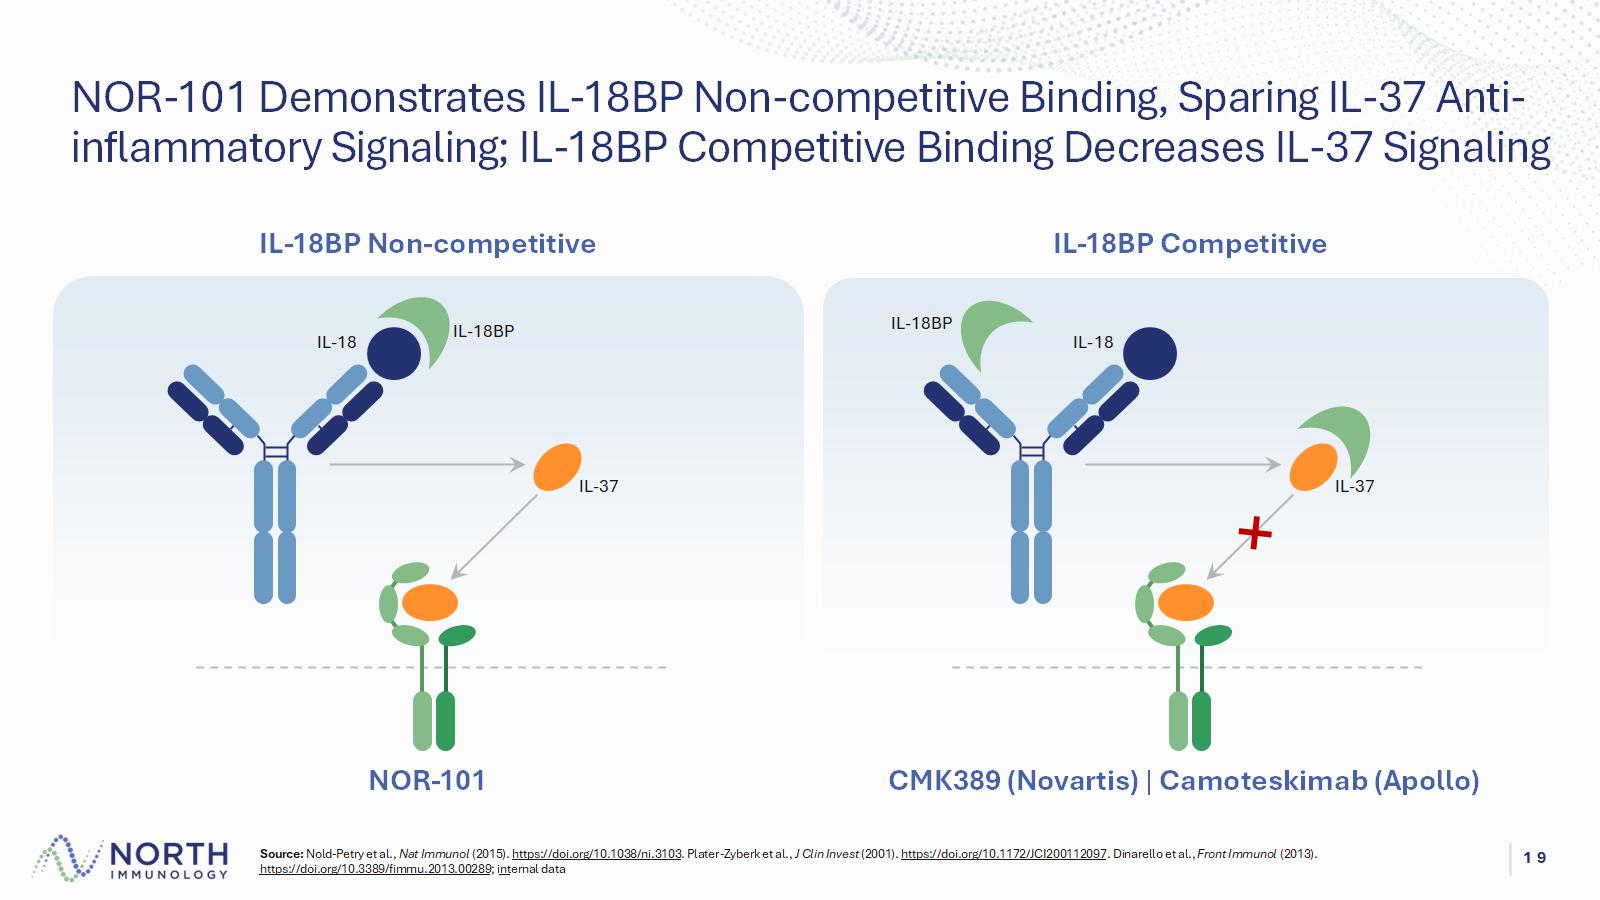
Source: Nold - Petry et al., Nat Immunol (2015). https://doi.org/10.1038/ni.3103 . Plater - Zyberk et al., J Clin Invest (2001). https://doi.org/10.1172/JCI200112097 . Dinarello et al., Front Immunol (2013). https://doi.org/10.3389/fimmu.2013.00289 ; i nt ernal data 19 NOR - 101 Demonstrates IL - 18BP Non - competitive Binding, Sparing IL - 37 Anti - inflammatory Signaling; IL - 18BP Competitive Binding Decreases IL - 37 Signaling IL - 18BP Non - competitive IL - 18BP Competitive IL - 18 IL - 18BP IL - 37 NOR - 101 IL - 18 IL - 18BP IL - 37 CMK389 (Novartis) | Camoteskimab (Apollo)
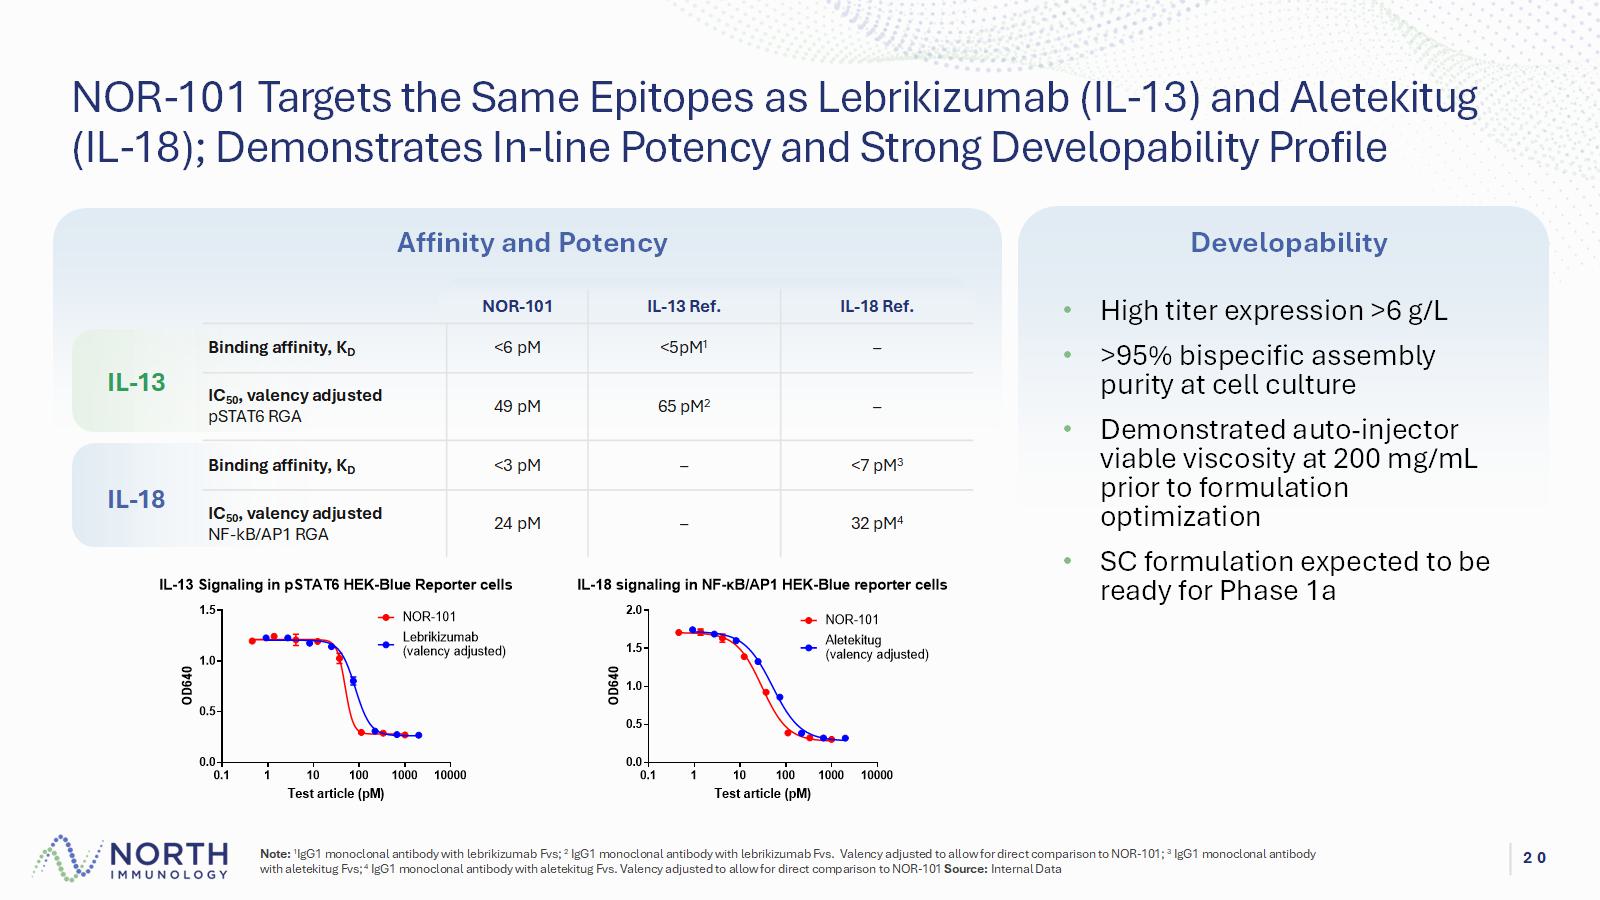
Note: 1 IgG1 monoclonal antibody with lebrikizumab Fvs ; 2 IgG1 monoclonal antibody with lebrikizumab Fvs . Valency adjusted to allow for direct comparison to NOR - 101; 3 IgG1 monoclonal antibody with aletekitug Fvs ; 4 IgG1 monoclonal antibody with aletekitug Fvs . Valency adjusted to allow for direct comparison to NOR - 101 Source: Internal Data 20 NOR - 101 Targets the Same Epitopes as Lebrikizumab (IL - 13) and Aletekitug (IL - 18); Demonstrates In - line Potency and Strong Developability Profile Affinity and Potency Developability • High titer expression >6 g/L • >95% bispecific assembly purity at cell culture • Demonstrated auto - injector viable viscosity at 200 mg/mL prior to formulation optimization • SC formulation expected to be ready for Phase 1a 0.1 1 10 100 1000 10000 0.0 0.5 1.0 1.5 IL-13 Signaling in pSTAT6 HEK-Blue Reporter cells Test article (pM) O D 6 4 0 Lebrikizumab (valency adjusted) NOR-101 0.1 1 10 100 1000 10000 0.0 0.5 1.0 1.5 2.0 IL-18 signaling in NF-κB/AP1 HEK-Blue reporter cells Test article (pM) O D 6 4 0 Aletekitug (valency adjusted) NOR-101 IL - 18 Ref. IL - 13 Ref. NOR - 101 – <5pM 1 <6 pM Binding affinity, K D IL - 13 – 65 pM 2 49 pM IC 50 , valency adjusted pSTAT6 RGA <7 pM 3 – <3 pM Binding affinity, K D IL - 18 32 pM 4 – 24 pM IC 50 , valency adjusted NF - kB/AP1 RGA
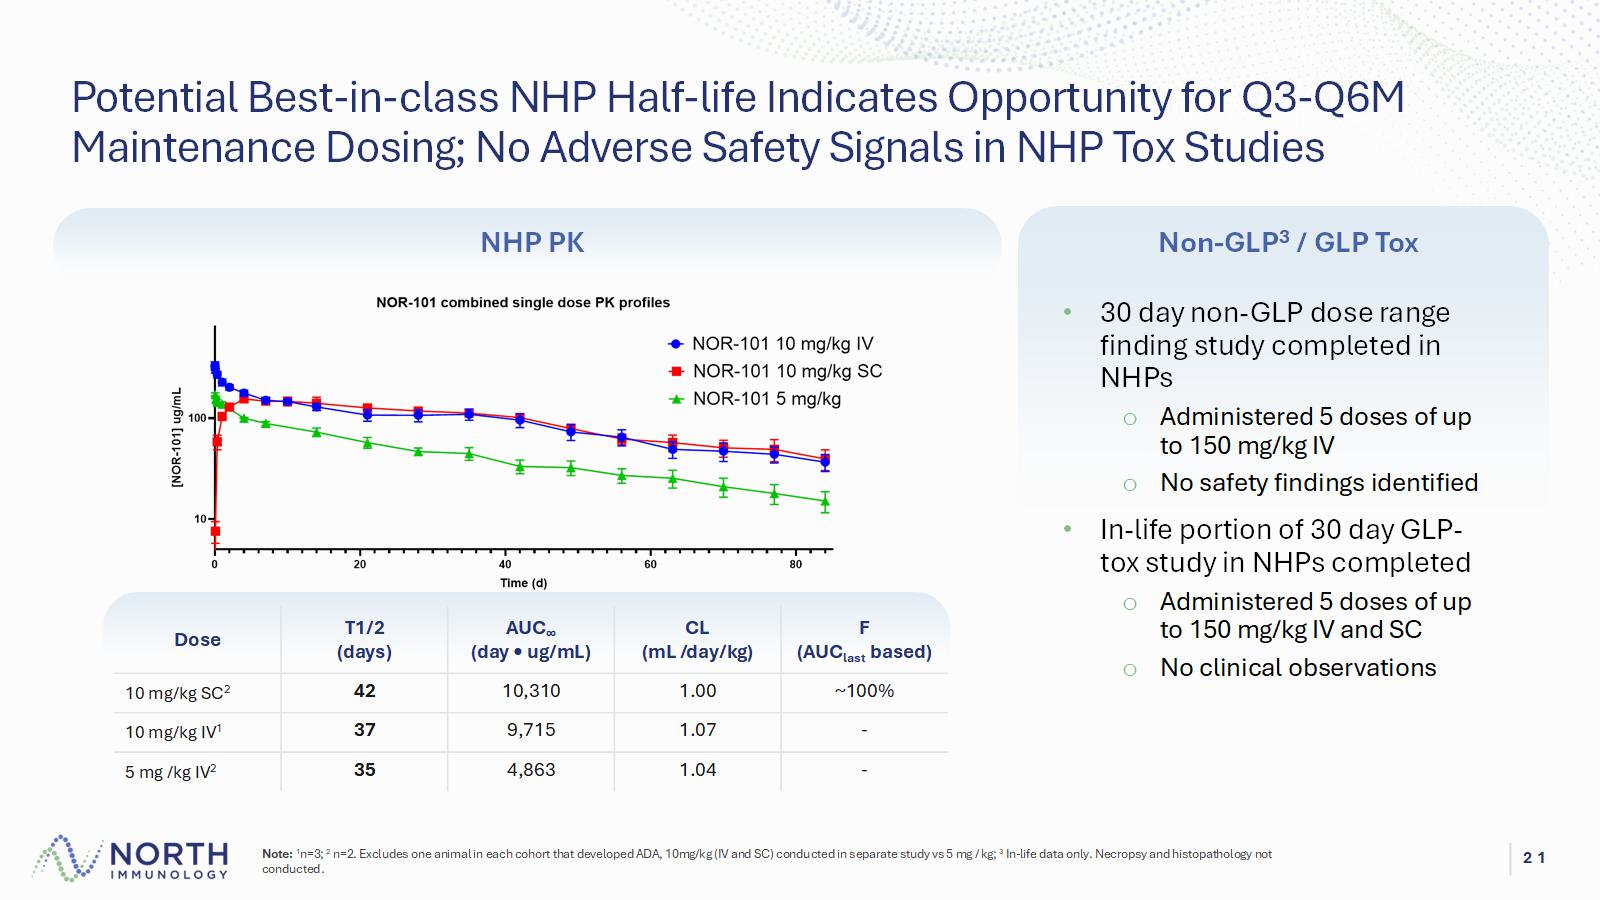
Note: 1 n=3; 2 n=2. Excludes one animal in each cohort that developed ADA, 10mg/kg (IV and SC) conducted in separate study vs 5 mg / kg; 3 In - life data only. Necropsy and histopathology not conducted. 21 Potential Best - in - class NHP Half - life Indicates Opportunity for Q3 - Q6M Maintenance Dosing; No Adverse Safety Signals in NHP Tox Studies NHP PK Non - GLP 3 / GLP Tox • 30 day non - GLP dose range finding study completed in NHPs o Administered 5 doses of up to 150 mg/kg IV o No safety findings identified • In - life portion of 30 day GLP - tox study in NHPs completed o Administered 5 doses of up to 150 mg/kg IV and SC o No clinical observations F ( AUC last based) CL (mL /day/kg) AUC ∞ (day • ug/mL) T1/2 (days) Dose ~100% 1.00 10,310 42 10 mg/kg SC 2 - 1.07 9,715 37 10 mg/kg IV 1 - 1.04 4,863 35 5 mg /kg IV 2
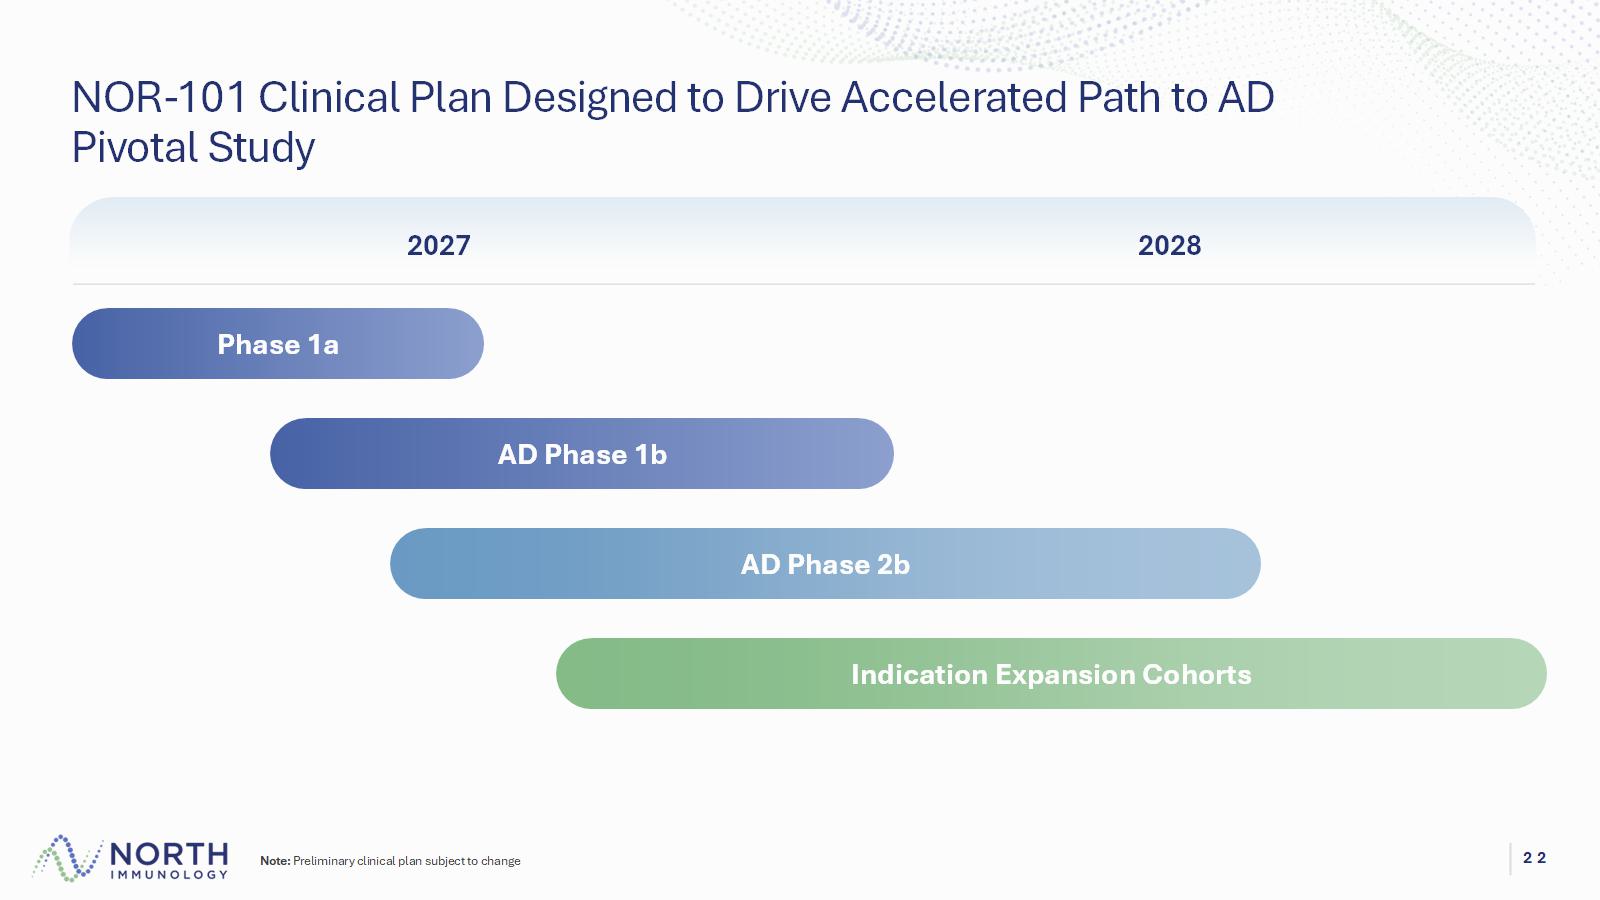
Note: Preliminary clinical plan subject to change 22 NOR - 101 Clinical Plan Designed to Drive Accelerated Path to AD Pivotal Study 2028 2027 Phase 1a AD Phase 1b AD Phase 2b Indication Expansion Cohorts
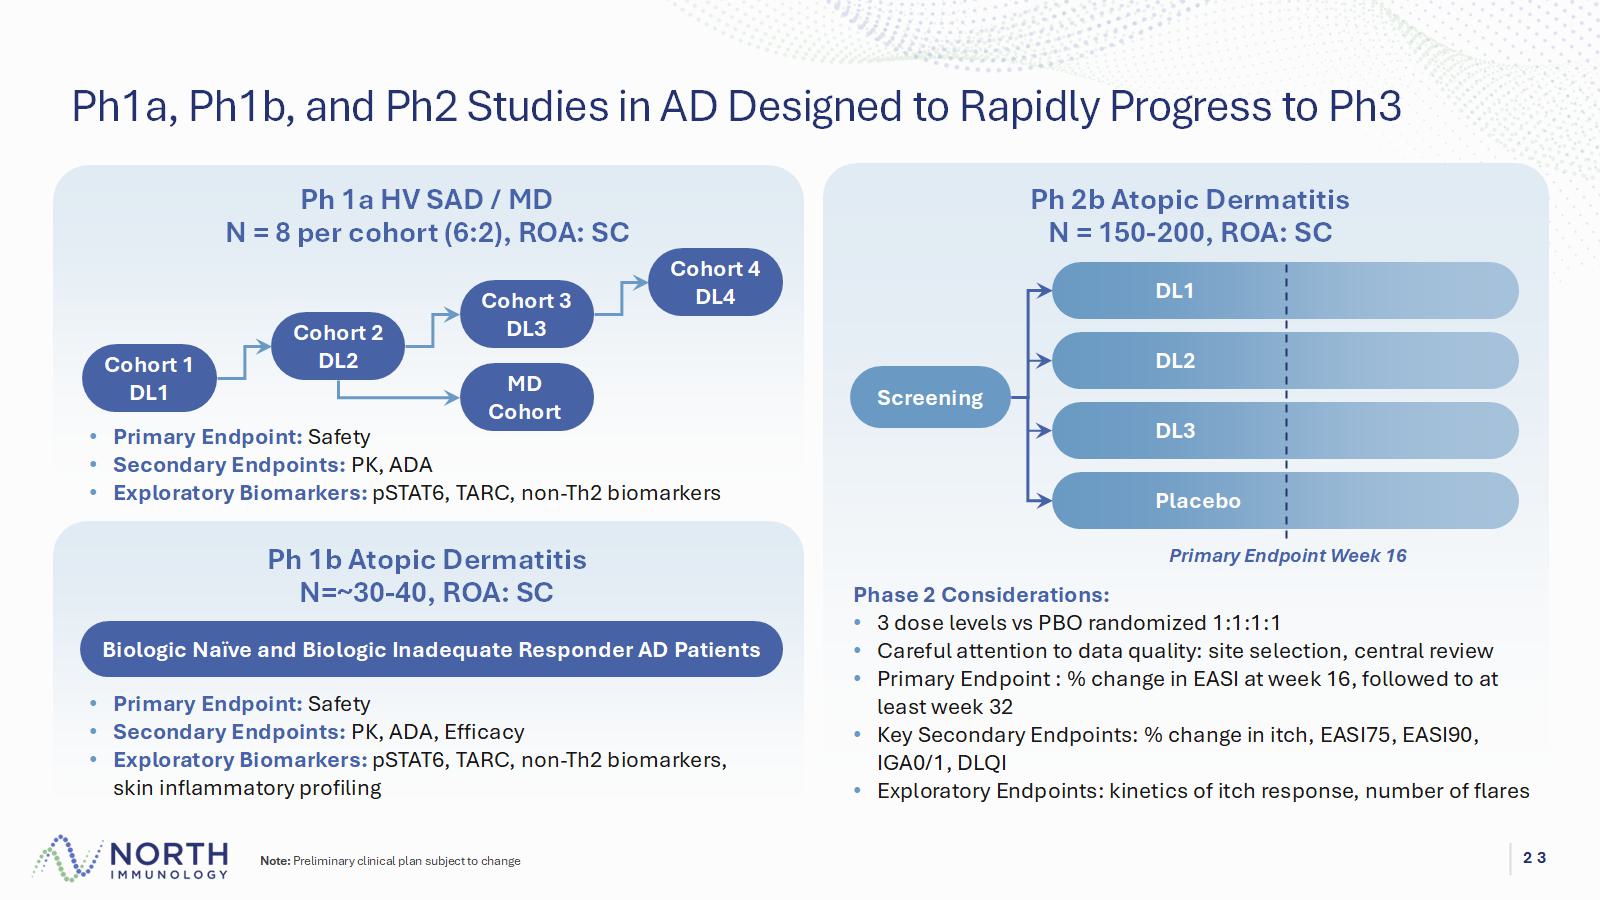
Note: Preliminary clinical plan subject to change 23 Ph1a, Ph1b, and Ph2 Studies in AD Designed to Rapidly Progress to Ph3 Ph 1a HV SAD / MD N = 8 per cohort (6:2), ROA: SC Ph 1b Atopic Dermatitis N=~30 - 40, ROA: SC Ph 2b Atopic Dermatitis N = 150 - 200, ROA: SC Biologic Naïve and Biologic Inadequate Responder AD Patients • Primary Endpoint: Safety • Secondary Endpoints: PK, ADA, Efficacy • Exploratory Biomarkers: pSTAT6, TARC, non - Th2 biomarkers, skin inflammatory profiling • Primary Endpoint: Safety • Secondary Endpoints: PK, ADA • Exploratory Biomarkers: pSTAT6, TARC, non - Th2 biomarkers Cohort 1 DL1 Cohort 2 DL2 Cohort 3 DL3 Cohort 4 DL4 Phase 2 Considerations: • 3 dose levels vs PBO randomized 1:1:1:1 • Careful attention to data quality: site selection, central review • Primary Endpoint : % change in EASI at week 16, followed to at least week 32 • Key Secondary Endpoints: % change in itch, EASI75, EASI90, IGA0/1, DLQI • Exploratory Endpoints: kinetics of itch response, number of flares Screening DL1 DL2 DL3 Placebo Primary Endpoint Week 16 MD Cohort
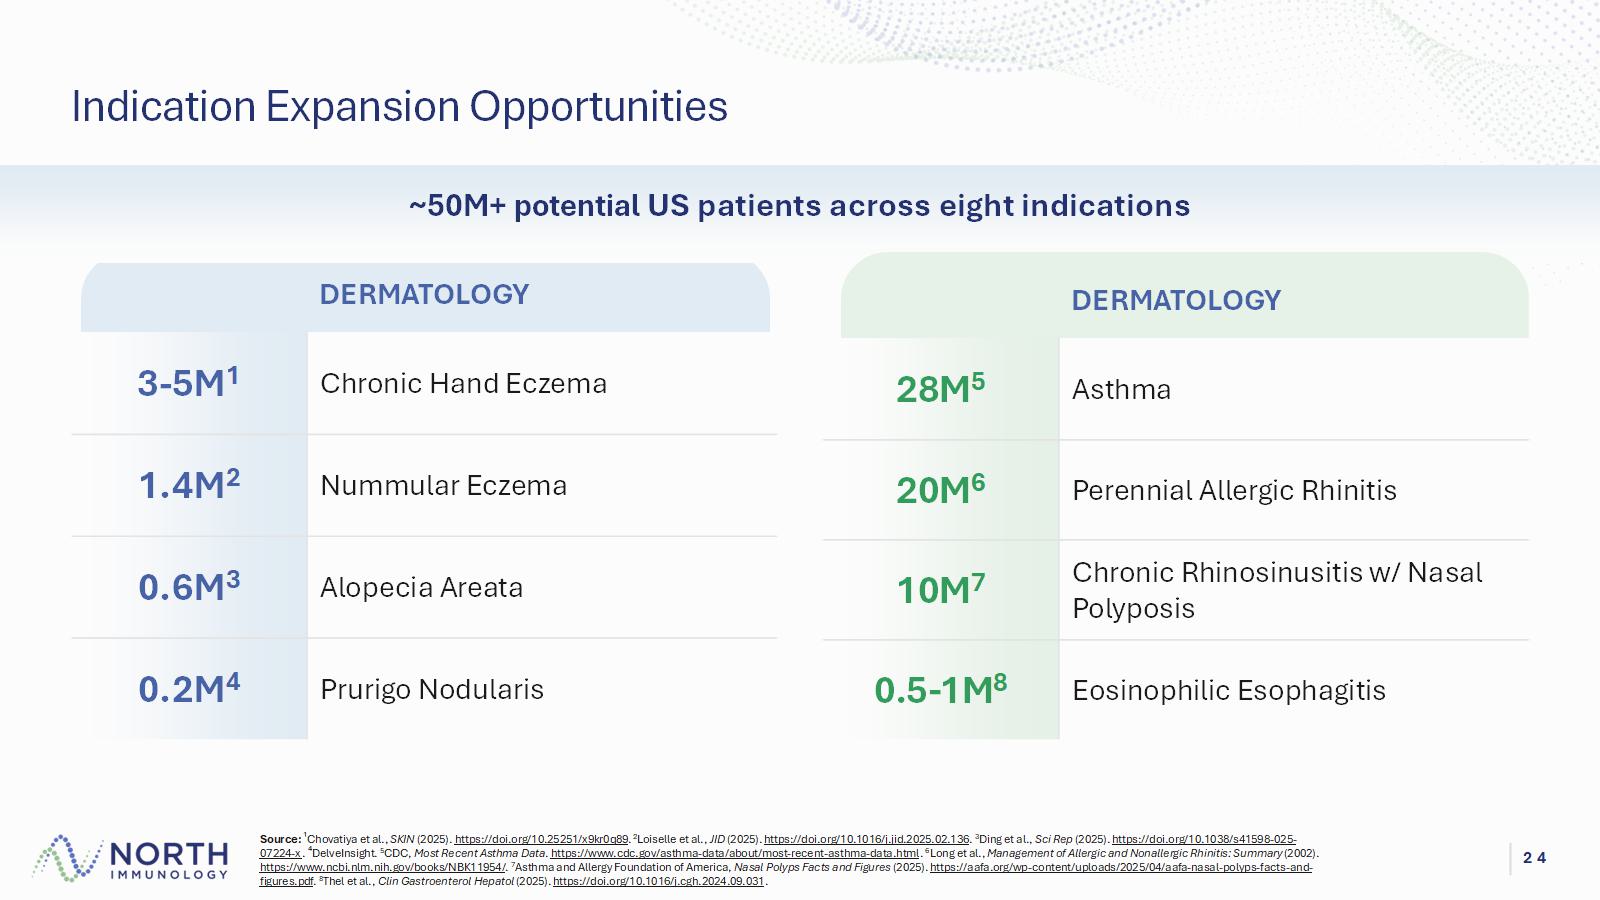
Source: ¹Chovatiya et al., SKIN (2025). https://doi.org/10.25251/x9kr0q89 . 2 Loiselle et al., JID (2025). https://doi.org/10.1016/j.jid.2025.02.136 . 3 Ding et al., Sci Rep (2025). https://doi.org/10.1038/s41598 - 025 - 07224 - x . ⁴ DelveInsight . 5 CDC, Most Recent Asthma Data . https://www.cdc.gov/asthma - data/about/most - recent - asthma - data.html . 6 Long et al., Management of Allergic and Nonallergic Rhinitis: Summary (2002). https://www.ncbi.nlm.nih.gov/books/NBK11954/ . 7 Asthma and Allergy Foundation of America, Nasal Polyps Facts and Figures (2025). https://aafa.org/wp - content/uploads/2025/04/aafa - nasal - polyps - facts - and - figures.pdf . 8 Thel et al., Clin Gastroenterol Hepatol (2025). https://doi.org/10.1016/j.cgh.2024.09.031 . 24 Indication Expansion Opportunities ~50M+ potential US patients across eight indications DERMATOLOGY Chronic Hand Eczema 3 - 5M 1 Nummular Eczema 1.4M 2 Alopecia Areata 0.6M 3 Prurigo Nodularis 0.2M 4 DERMATOLOGY Asthma 28M 5 Perennial Allergic Rhinitis 20M 6 Chronic Rhinosinusitis w/ Nasal Polyposis 10M 7 Eosinophilic Esophagitis 0.5 - 1M 8

25 2028 2027 2026 • Q1: Ph 1b Topline Data • 2028: Ph 2b Topline Data • Q1: Ph 1a Start • H1: Ph 1b Start • 2027: Ph 2b Start • Midyear: Ph 1a PK/ Safety Data • Q4: Australia HREC and CTN Submission NOR - 101 IL - 13xIL - 18 • Ph 1a Start • DC Nomination NOR - 201 Undisclosed Key Upcoming Milestones Anticipated $180M PIPE raise provides cash into 2H 2028

26 Agreement • IP to be owned by affiliate Central Therapeutics, LLC; NOR - 101 composition of matter exclusively licensed to North Immunology • North to control patent prosecution • License terms: o Option fee has been paid o Royalty: mid single digit o Milestones: Up to mid - single digit development and approval milestones IP / License Agreement IP Status • Initial IP filed with coverage through 2047+
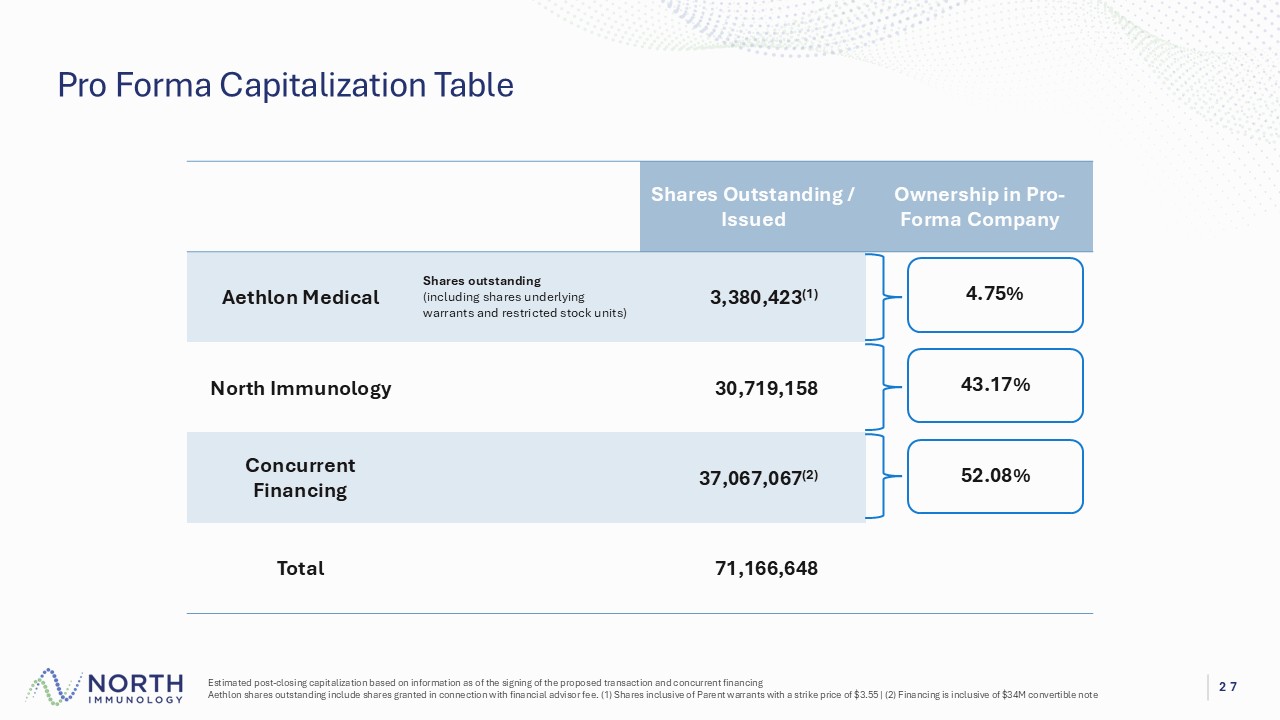
Estimated post - closing capitalization based on information as of the signing of the proposed transaction and concurrent financin g Aethlon shares outstanding include shares granted in connection with financial advisor fee. (1) Parent shares exclude 391,500 OT M warrants as of 09/13/26 | (2) Financing is inclusive of $34M convertible note 27 Pro Forma Capitalization Table Ownership in Pro - Forma Company Implied Valuation (in millions) Shares Outstanding / Issued $16.5 3,380,423 (1) Shares outstanding (including shares underlying warrants and restricted stock units) Aethlon Medical $150.0 30,719,158 North Immunology ~$180.0 37,067,067 (2) Concurrent Financing ~$346.5 71,166,648 Total 4.76% 43.29% 51.95%
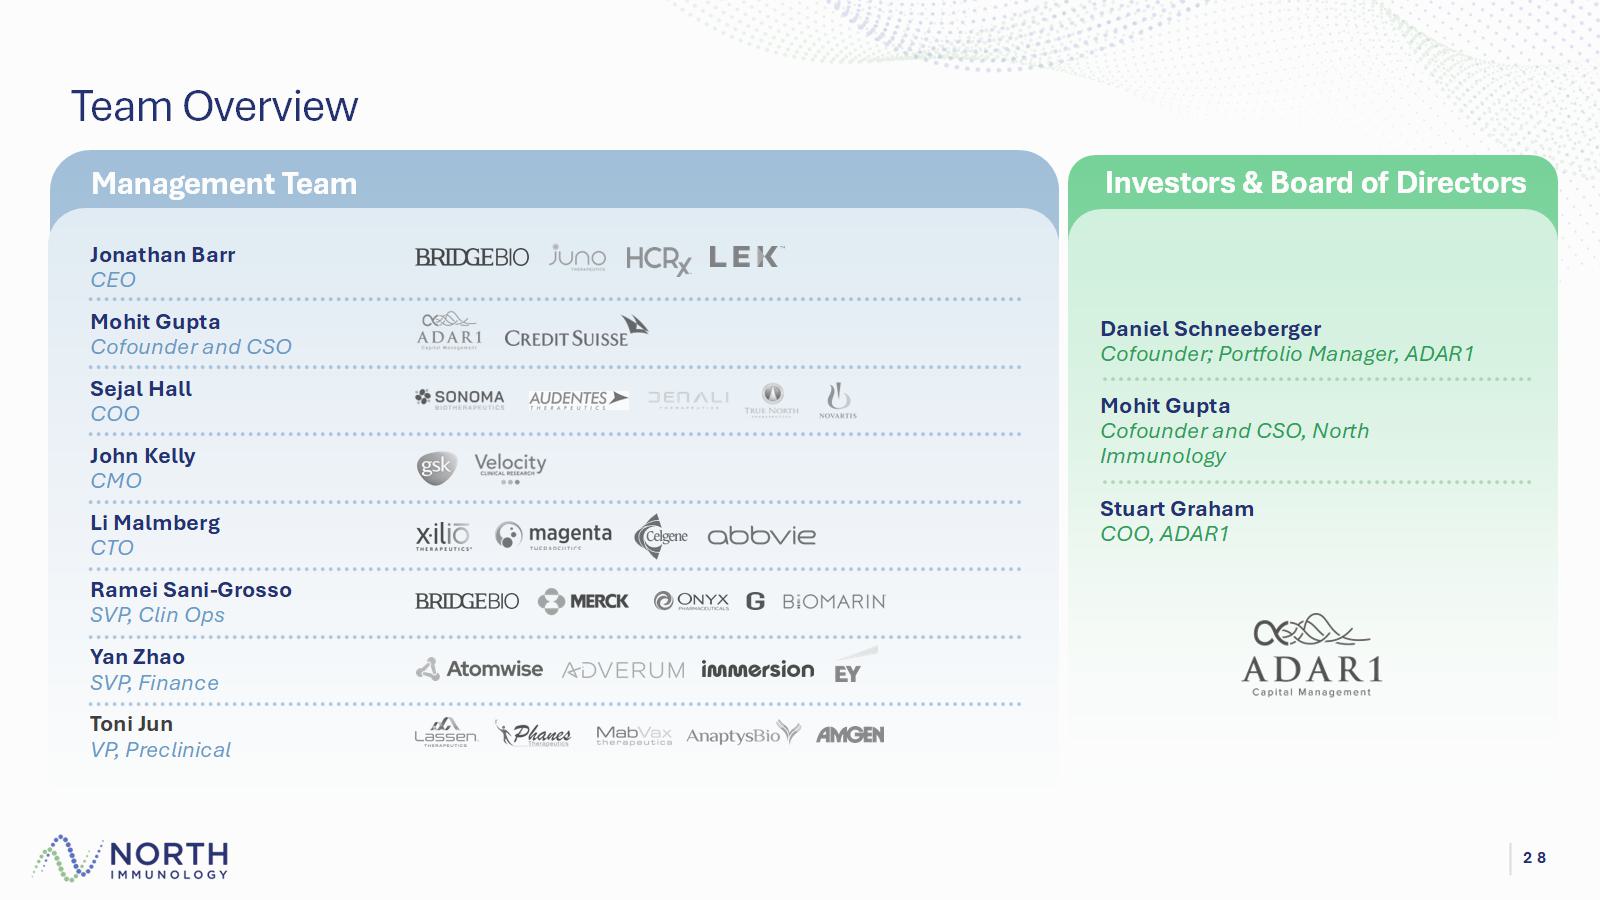
28 Jonathan Barr CEO Mohit Gupta Cofounder and CSO Sejal Hall COO John Kelly CMO Li Malmberg CTO Ramei Sani - Grosso SVP, Clin Ops Yan Zhao SVP, Finance Toni Jun VP, Preclinical Team Overview Management Team Investors & Board of Directors Daniel Schneeberger Cofounder; Portfolio Manager, ADAR1 Mohit Gupta Cofounder and CSO, North Immunology Stuart Graham COO, ADAR1

Thank You Company Overview SEPTEMBER 2026